





The mothers of newborns who are discharged from a neonatal intensive care unit (NICU) experience stress and anxiety due to the specialized care their child requires at home, affecting their perception of maternal self-efficacy.
ObjectiveTo evaluate the effect of the nursing intervention called Hospital Discharge Plan (HDP) on the promotion of self-efficacy in mothers of newborns discharged from the NICU.
MethodQuantitative study, quasi-experimental design with pre-test/post-test in a single group, using the Parental Evaluation Scale applied to a convenience sample of 72 mothers of high-risk newborns from a NICU located in the city of Villavicencio (Colombia). The first measurement was taken between days 3 and 4 before discharge and at 15 days’ post-discharge. Data processing was carried out using the statistical program SPSS, version 21. The intervention was based on the four concepts of self-efficacy by Barbara Resnick.
ResultsThe perception of maternal self-efficacy before the intervention showed a median of 8.9 points (RI 7.6–9.5); after the intervention it showed a median of 9.6 points (RI of 10–8.7); a statistically significant p-value < 0.001 was obtained before and after the intervention with the Wilcoxon rank test.
ConclusionsEducation and follow-up promoted the development of knowledge and skills in mothers for the care of high-risk newborns. This contributed to the experience of mastery and vicarious experience from the teaching-learning process and contact with the experience of other mothers, which contributes to the effective development of motherhood.
Las madres de los recién nacidos (RN) que egresan de una unidad de cuidado intensivo neonatal (UCIN) presentan estrés y ansiedad por el cuidado especializado que su hijo/a necesita en el hogar, afectando la percepción de la autoeficacia materna.
ObjetivoEvaluar el efecto de la intervención de enfermería Plan de Alta Hospitalaria (PAHO) sobre la promoción de la autoeficacia en madres de RN que egresan de la UCIN.
MétodoEstudio cuantitativo, diseño cuasiexperimental con preprueba/posprueba en un solo grupo, con la aplicación de la Escala de Evaluación Parental a una muestra por conveniencia de 72 madres de RN de alto riesgo, de una UCIN ubicada en la ciudad de Villavicencio (Colombia), la primera medición se realizó entre los días tres y cuatro antes del egreso y a los 15 días posteriores. El procesamiento de datos se llevó a cabo mediante el programa estadístico SPSS, versión 21.
ResultadosLa percepción de autoeficacia materna antes de la intervención presentó una mediana de 8,9 puntos (rango intercuartílico [IQR] 7,6–9,5); posterior a esta se observó una mediana de 9,6 puntos (IQR 10–8,7); de forma comparativa antes y después de la intervención con la prueba de rangos de Wilcoxon se obtuvo un valor p < de 0,001 estadísticamente significativo.
ConclusionesLa educación y seguimiento promovió en las mujeres el desarrollo de conocimientos y habilidades para el cuidado del RN de alto riesgo, aportó a la experiencia vicaria y de dominio a partir del proceso de enseñanza-aprendizaje y del contacto con la vivencia de otras madres, lo que contribuye al desarrollo efectivo de la maternidad.
The caregiving events that mothers with children being discharged from an intensive care unit undergo generate different levels of stress, fear and loss of confidence that confront them as caregivers.
What it contributesThe intervention created by Barbara Resnick’s work on the self-efficacy theory is intended to provide evidence on nursing practice and to promote parental self-efficacy.
Study implicationsVerbal reassurance and physiological feedback, which are significant in the judgement of parenting effectiveness, should be worked on throughout the hospitalisation process, since they underpin nursing care, based on theories of care.
IntroductionMothers of newborns (NBs) hospitalised in the neonatal intensive care unit (NICU) experience negative feelings such as fear, anguish and depression1 due to separation from their child. Also, the physical and technological environment of the unit, the procedures, the newborn’s health status and behaviour2 hinder maternal performance by limiting the satisfaction of basic needs, feeding, behavioural exchange3,4 and altering the perception of self-efficacy.5 Some of these feelings prevail after hospital discharge, especially if the newborn requires special care conditions at home. It has been reported, for example, that anxiety is present in 2 out of 5 parents up to the first month of life, especially in mothers,6 ranging from 18% to 78%,7,8 affecting maternal quality of life.9
As a consequence, the mother may establish an inappropriate judgement about her ability to learn and successfully perform maternal competence, the main modulator of the perception of maternal self-efficacy.10 This is understood as the ability that mothers develop in the personal, cognitive and contextual spheres to exercise their role.11
Given this premise, nursing becomes important in creating or reinforcing strategies so that the mother is confident in her abilities and is able to take on the challenges of caring for the newborn at home.12 This research accepts the concepts of the Barbara Resnick’s nursing theory of self-efficacy,5 based on the postulates of Bandura, which sets out four processes to promote the appropriate perception of self-efficacy:
- 1.
Mastery experience: is one of the positive sources of perceived self-efficacy. It encompasses the process of successfully executing a task in the face of a new challenge.5 In order for mothers to achieve this expertise, continuous contact between the two should be allowed from the time of hospitalisation, so that the mother recognises her child’s needs and establishes adequate communication that allows her to exercise her maternal role, trust in her role as caregiver and reduce stress. Nursing education for mothers consolidates knowledge and skills for the care of the child at home.13
- 2.
Vicarious experience: understood as the indirect experience gained from observing the successes and failures of others.5 Once hospital discharge is announced, the first source of vicarious experience for mothers is nursing, because through observation and enquiry, they acquire information for knowledge and caring skills.14
- 3.
Verbal persuasion: influence of verbal language on individuals, which elicits achievement or mastery of a task and contributes to a positive perception of self-efficacy.5 This task needs to be promoted by the nurse and the maternal support network, encouraging the fulfilment of the goal of care during the transition process to the home.15
- 4.
Physiological feedback or somatic and emotional state: refers to the influence of a person’s physical and emotional state, which is a predictor of success or failure in performing a task.5 Hospitalisation and home care generate feelings of fear, dread, guilt, stress and anxiety in the mother, which alters the mother’s physical state, maternal performance and perceived self-efficacy, especially if she is unaware of the child’s demands and is unable to meet his or her needs.16
Taking into account maternal problems and the postulates of Barbara Resnick, the following research question was established: What is the effect of the nursing intervention Hospital Discharge Plan (HDP) on the promotion of self-efficacy in mothers of newborns leaving the NICU?
The overall aim of the study was to evaluate the effect of the HDP nursing intervention on the perception of self-efficacy in mothers of NBs leaving the NICU.
The hypothesis stated that the HDP intervention aimed at mothers of newborns leaving the NICU would improve the perception of maternal self-efficacy.
MethodDesignQuantitative study with quasi-experimental design with pre-test/post-test in a single group.17
ScopeThe intervention was aimed at mothers of newborns hospitalised in the NICU between February and August 2021, in a tertiary level public institution of the city of Villavicencio (Colombia). Mothers were privileged in that, due to the COVID 19 health emergency the visiting hours were restricted to two hours in the morning and two in the afternoon, but the mothers were given priority of admission for breastfeeding.
SubjectsMothers of newborns in the process of hospital discharge (period comprising 3–4 days before discharge home, when the mothers received training) who met the inclusion criteria: over 18 years of age, first experience of hospitalisation of their child in the NICU, with a high risk newborn with a hospital stay of more than 3 days. The exclusion criteria were: mothers with children in the process of hospital discharge who presented with therapeutic effort limitations or congenital heart disease, and mothers with a diagnosis of cognitive impairment.
SampleBoth the probability of type I error (α) and type II error (β) was assigned at .05 and δ = .55σ was assumed as the choice of point on the power curve of the paired t-test for the determination of type II error size. The sample size calculation was fixed through the mathematical expression suggested by Desu and Raghavarao.18
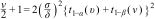
whose equality is obtained iteratively for ν, and constitutes the required size. In this expression, the upper percentiles t1−α y t1−β correspond to the t-distribution, σ is the value assumed as variability in the normal model and δ is the slack set for type II error specification purposes. Consequently, with the above preliminary sample size specifications, this study integrated a set of 72 mothers. Sampling was finally established by convenience based on the daily census of the unit.
VariablesIndependent variable: nursing intervention for the promotion of maternal self-efficacy; this included three moments based on the four concepts of Resnick’s self-efficacy theory: 1) a personalised meeting with the mother, to work on physiological feedback based on guiding questions and strategies for stress management 2) work with experiences of mastery, vicarious experiences and verbal persuasion, with an individualised educational process that empowered the mother in knowledge and care skills. An educational booklet, a neonatal simulator and actual newborn care practice were used, and 3) outpatient follow-up for 15 days via smartphone instant messaging or phone call (Fig. 1).

Dependent variable: perceived maternal self-efficacy as measured by the Parental Appraisal Scale. The instrument used was the Chamarrita Farkas-Klein Parental Evaluation Scale,19 which is a self-administered instrument that assesses satisfaction and feelings of self-efficacy about motherhood with children aged 0–2 years. It consists of 10 items, with a reliability of .85 for the total scale and a range between .66 and .81 for its items. The instrument’s references are the Parenting Sense of Competence (PSOC), by Johnston and Mash, 1989, and the Being a Parent scale, by Doyle and McCarthy, 2001 version 1.19 The scale has a total of 10 questions, each with a value of 10 points, for the assignment of the scores in each of the items. Items 2, 4 and 10 gave the direct score of the scales filled in by the mothers and for the results in numbers 1, 3, 5, 6, 7, 8 and 9 the evaluation was carried out inversely to the mother’s response as proposed by the instrument. For the final score of each instrument, the total number of items was added up and divided into 10, the result of 1–10 points being interpreted by stipulating that the higher the score, the better the perception of maternal self-efficacy.
Contextual variables: mother’s age, civil status, socio-economic level, educational level and number of children, gestational age, days of life and hospitalisation of the newborn.
Data collectionBased on the unit’s daily census, high-risk newborns who were in the process of being discharged from hospital were identified, their mothers were approached during visiting hours, where the HDP nursing intervention was explained individually. Those who agreed to participate signed the consent form and the socio-demographic data sheet and the Parental Evaluation Scale were applied, with the first measurement being taken 3–4 days prior to discharge. The first measurement was taken 3–4 days prior to discharge, and was taken two or three times a week until the sample was complete. A schedule was established with each mother for the application of Moments 1 and 2 which took place during hospitalisation. Moment 3 began after discharge and the second measurement was taken 15 days after discharge of the newborn.
Data analysisData processing was carried out with SPSS statistical software, version 21. For maternal and newborn contextual variables, frequencies and percentages were used. For the individual measurement of each instrument, before and after the intervention, median and inter-quartile ranges were used. The data obtained from the pre-test and post-test assessment were subjected to the Kolmogorov–Smirnov test to assess the fit of the data to the normal distribution. Thus, the test result showed an unsatisfactory fit to the Gaussian model. Based on these results, the non-parametric Wilcoxon rank test was used to validate the intervention.
Ethical considerationsThis research was governed by Colombian Resolution 8430 of 4 October 1993, which establishes the scientific, technical and administrative norms for health research, the Helsinki and Nuremberg codes. The research was rated as higher than minimal risk, taking into account that the newborn was involved in teaching mothers about home care. Participation was voluntary, with signature of informed consent. The project was approved by the Research and Ethics Committee of the Universidad de La Sabana, by means of Act 018 of 2020, and endorsed by the Teaching, Service and Research Coordination of the hospital where the study was conducted.
The principles of truthfulness were contemplated through the exercise of intellectual honesty and fidelity, preserving the confidentiality and safeguarding of information. The principle of autonomy of the participants was also ensured.
ResultsThe effect of the HDP nursing intervention on maternal self-efficacy was evaluated in 75 mothers with children hospitalised in a NICU. Of these, 3 were withdrawn from the sample: one because of a diagnosis of congenital heart disease in the newborn; one through misreporting of age (under 18 years) and one because the mother was not located after discharge. The socio-demographic characteristics of the mothers included in the study and of the newborns are shown in Table 1.
Description of the socio-demographic variables.
| Variable | Unit of measurement | |
|---|---|---|
| Age group of the mother, % (n) | Between 18–25 | 58.3% (n 42) |
| Between 25–30 | 25% (n18) | |
| Between 30–35 | 2.8% (n2) | |
| Over 35 | 13.9% (n10) | |
| Civil status, % (n) | Single | 16.7% (n12) |
| Married | 6.9% (n5) | |
| In a partnership | 72.2% (n52) | |
| Separated | 4.2% (n3) | |
| Socio-economic levela, % (n) | 1 | 51.4% (n37) |
| 2 | 26,4% (n19) | |
| 3 | 22,2% (n16) | |
| Level of education % (n) | Incomplete baccalaureate | 43.1% (n31) |
| Baccalaureate | 30.6% (n22) | |
| Technical or technological | 15.3% (n11) | |
| Professional | 11.1% (n8) | |
| Gestational age of newborn % (n) | Under 28 weeks | 4.2% (n3) |
| Between 29 and 32 weeks | 18.0% (n13) | |
| Between 33 and 37 weeks | 66.7% (n48) | |
| Over 37 weeks | 11.1% (n8) | |
| Average days of life | Moment 1 | 13.6 days |
| Moment 2 | 17.1 days | |
| Moment 3 | 28.6 days | |
Stratification in Colombia is determined to classify properties and assign subsidies to public services, under this premise people located in strata 1, 2 and 3 house the users with the lowest economic resources (DANÉS. DANE Information for All. DANE 2023. https://www.dane.gov.co/index.php/116-espanol/informacion-georreferenciada/2421-estratificacion-socioeconomica (Accessed 6 June 2023).
The results of maternal self-efficacy perception before the nursing intervention presented a median of 8.9 points (RI 7.6–9.5). After the HDP nursing intervention, mothers presented a median of 9.6 points (RI 10–8.7) (Fig. 2); a lower outlier was presented, with a self-efficacy score of 5.8 points, lower than the level before the intervention, related to the readmission of the NB due to complications inherent to prematurity. These data were subjected to the Wilcoxon signed-rank test which showed a p-value <.001 giving quantitative support to the HDP nursing intervention on the level of self-efficacy with a statistically significant relationship.
Discussion
The relationship analysis between the concepts and items in the measurement instrument concluded that items 2, 3, 4, 6 and 8 reflect caregiving skills and knowledge and thus provide a picture of mastery and vicarious experiences. Item 1 reflects on verbal persuasion and items 5, 7, 9 and 10 reflect the somatic state of the mother and contribute to physiological feedback.
A quasi-experimental study evaluated a neonatal discharge programme that measured parental efficacy and psychological distress, under the concepts of Bandura’s theory, in 42 parents with an intervention of face-to-face education, 1 h prior to hospital discharge for newborn care and telephone follow-up 2 weeks after discharge, finding significant relationships with maternal self-efficacy.20 These results are similar to those of the research, because after the implementation of the educational process with the mothers to empower them in skills and knowledge that support the experiences of mastery and verbal persuasion, an increase in the score of item 1 and relocation in the average score of the post-test of 1.3 points above the pre-test was reported. The activities mediated in these two theoretical concepts, led to a significant change in the values of self-efficacy.
Physiological feedback from mothers is an important factor for correct maternal self-efficacy and it is known that mothers of NBs leaving the NICU present with emotional distress during child care at home.12 In a prospective longitudinal study that measured self-efficacy in 67 mothers of high-risk children leaving the NICU, it was found that the psychological well-being of the mother was a predictive factor for better maternal self-efficacy.10 This aspect is similar to the results found in this research where it was evident that item 7 of the Parental Assessment Scale referring to the somatic state of the mother stood out with the lowest score in both pre-test and post-test, relating to high levels of maternal stress and/or distress. However, when comparing the pre-test with the post-test there was an increase of 1.79 points with the intervention.
The individualised nursing care of this intervention improved maternal self-efficacy perceptions of vicarious and mastery experiences, which allowed mothers to be more confident in their performance as caregivers of a child with special demands. This was evidenced by the increase in items 2 and 3 of the scale, which assess maternal judgement of the individual’s role as a mother with .9 additional points in the post-test. The result coincides with a convergent parallel mixed-method research that evaluated the effect of an intervention on parental confidence based on personalised care and focused on the recognition of the infant’s needs.21
Qualitative studies confirm that mothers present with fear and anguish related to the deficit of knowledge in several areas of care: hygiene, feeding, development, routine care and special care.22 This highlights the importance of offering the mother autonomy of care within the hospital setting, with a permanent and personalised accompaniment, as proposed in the different moments of this intervention, and emphasised with the use of the booklet as an educational aid.
The mothers in the research had positive results in the distribution of the Parental Assessment Scale measurement data after the intervention, where one of the strategies was mediated by information and communication technologies (ICT). The creation of an instant messaging application group for smartphones (WhatsApp) or phone calls facilitated follow-up at home. This is consistent with findings from a randomised clinical trial, which promoted learning basic newborn care to new mothers using ICTs, with statistically significant data comparing the experimental group with the control group in the first week after birth.23 The phone call also proved to be effective in promoting breastfeeding self-efficacy, with a 53% increase in the women involved.24
Regarding study limitations, we would mention that the COVID-19 health emergency made it difficult to obtain authorisation to enter health institutions to carry out the intervention, and this limited the inclusion of other possible participants in the research, such as the fathers.
ConclusionsThe level of maternal self-efficacy after the application of the HDP nursing intervention was maintained and improved to raise the medians to a higher level than that reflected before the intervention. The education and follow-up provided to the mothers developed knowledge and skills for the care of the high-risk newborn at home. This contributed specifically to the mastery and vicarious experiences involved in the effective development of motherhood.
It was found that items 5, 7 and 9 of the tool used, referring to feelings of expectation as a mother and the stress and anxiety generated by motherhood (Table 2) contributed to the reduction of the final score, thereby emphasising the importance of working on verbal persuasion and physiological feedback, as relevant points in the judgement on the effectiveness of the mother’s role. This should be worked on throughout the hospitalisation process by interdisciplinary means, because it has a high impact on the perception of maternal self-efficacy.
Average score for each item of the Parental Rating Scale before and after the intervention.
| Item | Statement | Average pre-test score | Average post-test score | Asymptotic p value |
|---|---|---|---|---|
| 1 | I feel constantly criticised or judged by others in my role as a mother. | 8.2 | 9.5 | .003 |
| 2 | I feel I am doing a good job as a mother. | 9.4 | 9.6 | .512 |
| 3 | My interests and talents lie in other areas of my life, not in maternity. | 9.0 | 9.7 | .005 |
| 4 | I believe that the decisions I make in raising my baby are the right ones. | 8.9 | 9.2 | .257 |
| 5 | Being a mother has not been as satisfying as I expected. | 8.2 | 8.5 | .553 |
| 6 | I find it really difficult to decide how to raise my baby. | 8.2 | 9.2 | .025 |
| 7 | The demands of motherhood make me feel tense and anxious. | 6.0 | 7.7 | Under .001 |
| 8 | I feel that in general the tasks of motherhood do not allow me to enjoy my baby. | 8.9 | 9.4 | .202 |
| 9 | I feel I have not managed to become the type of mother I would have wished to. | 7.5 | 9.3 | Under .001 |
| 10 | Being a mother makes me feel satisfied and happy. | 9.9 | 10 | .317 |
The authors have no conflict of interests to declare.
We would like to thank the Hospital Departamental de Villavicencio, Meta-Colombia, for their support in the development of this research.



