


This study aimed to assess serum Neuromedin U (NmU) levels in patients with Type 1 (T1DM) and Type 2 diabetes mellitus (T2DM) vs healthy controls and evaluate the correlation between NmU and body mass index (BMI).
Research design and methodsWe conducted a cross-sectional study with 134 participants: 45 with T1DM, 49 with T2DM, and 40 healthy controls. Serum NmU levels were measured using enzyme-linked immunosorbent assay (ELISA), and the correlation with BMI was assessed.
ResultsNmU levels were not significantly different between diabetic patients and healthy controls. No significant correlation was observed between NmU and BMI in T1DM or T2DM groups. However, the healthy control group found a significant inverse correlation between NmU and BMI (rho=−0.373, p<0.05).
ConclusionsNmU may not be a direct biomarker for diabetes, but its significant correlation with BMI in healthy individuals suggests a potential role in metabolic regulation. This is the first study ever conducted to compare NmU levels across diabetic subtypes, offering novel insights into the role of in metabolic homeostasis.
El objetivo de este estudio era evaluar los niveles séricos de neuromedinaU (NMU) en pacientes con diabetes mellitus (DM) tipo1 y tipo2 en comparación con controles sanos y evaluar la correlación entre la NMU y el índice de masa corporal (IMC).
Diseño y métodos de investigaciónSe realizó un estudio transversal con 134 participantes: 45 con DM tipo1, 49 con DM tipo2 y 40 controles sanos. Se midieron los niveles séricos de NMU mediante un ensayo inmunoenzimático (ELISA) y se evaluó la correlación con el IMC.
ResultadosLos niveles de NMU no fueron significativamente diferentes entre los pacientes diabéticos y los controles sanos. No se observó una correlación significativa entre NMU e IMC en los grupos de DM tipo1 o tipo2. Sin embargo, en el grupo de controles sanos se observó una correlación inversa significativa entre NMU e IMC (rho=−0,373, p<0,05).
ConclusionesEl NMU puede no ser un biomarcador directo de diabetes, pero su correlación significativa con el IMC en individuos sanos sugiere un papel potencial en la regulación metabólica. Este es el primer estudio en el que se comparan los niveles de NMU entre subtipos diabéticos, lo que ofrece nuevas perspectivas sobre el papel del NMU en la homeostasis metabólica.
Neuromedin U (NmU) is a neuropeptide that has gained attention due to its multifaceted roles in regulating physiological processes, including energy homeostasis, feeding behavior, and immune responses.1 It is expressed in various tissues, such as the central nervous system, the GI tract, and immune cells, and exerts its effects primarily through two G-protein-coupled receptors, NmUR1 and NmUR2. Recent studies have highlighted its involvement in glucose metabolism and insulin secretion, making it a potential player in diabetes pathophysiology.2–4
In diabetes research, NmU has been identified as a modulator of insulin secretion by acting on pancreatic β-cells.5 NmUR1, predominantly expressed in pancreatic cells, has been shown to suppress glucose-stimulated insulin release through inhibition by a G alpha protein signaling, thus leading to reduced insulin secretion and glucose intolerance.6 This suggests that NmU may contribute to the dysregulation of insulin homeostasis, a hallmark of diabetes mellitus. However, the literature on the role of NmU in diabetes is still emerging, and the exact mechanisms by which it influences glucose metabolism and insulin dynamics are not fully understood.
Despite the growing interest in NmU, the relationship between NmU levels and clinical parameters such as body mass index (BMI) in diabetic patients remains underexplored. As far as we know, no study has systematically compared NmU levels across diabetic subtypes (T1DM and T2DM) and healthy controls while evaluating potential correlations with key metabolic parameters such as the BMI.
The present study aims to fill this gap by investigating the serum levels of NmU in both Type 1 and Type 2 diabetic patients, alongside healthy controls, to determine whether NmU levels are impaired in the diabetic population and if they correlate with BMI. This is the first study of its kind exploring whether NmU could be a novel biomarker in the diabetic population, providing unique insights into its role in metabolic regulation and potential therapeutic applications. By understanding these relationships, this study aims to shed light on the clinical relevance of NmU in the management of diabetes and contribute to the growing body of research that positions NmU as a modulator of glucose metabolism and energy balance.6–8
MethodsStudy design and populationWe conducted this cross-sectional, observational study to investigate the relationship between serum NmU levels and clinical parameters in diabetic patients, including those with T1DM and T2DM and healthy controls. The study enrolled a total of 134 participants, stratified as follows:
- •
Type 1 diabetes group: 45 individuals diagnosed with T1DM.
- •
Type 2 diabetes group: 49 individuals diagnosed with T2DM.
- •
Control group: 40 healthy individuals with no past medical history of diabetes or significant metabolic disorders.
The study was conducted in full compliance with the Declaration of Helsinki, and approval was obtained from the Institutional Review Board prior to participant recruitment (protocol No.: 2011-KAEK-25 2019/07-10).
Participant recruitment and criteria- •
Inclusion criteria: Adults aged 18 years and older, diagnosed with T1DM or T2DM according to the American Diabetes Association clinical practice guidelines, or healthy individuals without a past medical history of metabolic or endocrine diseases.
- •
Exclusion criteria: Patients with comorbidities that could influence metabolic regulation, such as pregnancy, malignancies, chronic inflammatory conditions, or those on glucocorticoids, were excluded. Participants with renal failure, cardiovascular diseases, or other endocrine disorders were also excluded to minimize confounding variables.
For each participant, the following demographic and clinical data were collected:
- •
Demographic data: Age, gender, income, and number of children.
- •
Clinical data: Disease duration, insulin usage, systolic and diastolic blood pressure, pulse rate, weight, height, waist circumference, and hip circumference. The body mass index (BMI) was calculated as weight in kilograms divided by the square of height in meters. Insulin therapy type (basal, intensive, or none) and clinical control status (well-controlled vs poorly controlled) were documented for diabetic patients.
Venous blood samples were drawn from all participants after an overnight fast. The following parameters were measured:
- •
Hematological parameters: White blood cell (WBC) count, neutrophil count, lymphocyte count, hemoglobin (Hb), mean corpuscular volume (MCV), platelet count, and mean platelet volume (MPV).
- •
Glycemic parameters: Fasting blood glucose (FBG), post-prandial blood glucose (PPBG), C-peptide and HbA1c levels.
- •
Renal function: Blood urea nitrogen (BUN) and serum creatinine levels.
- •
Liver enzymes: Aspartate aminotransferase (AST), alanine aminotransferase (ALT), and gamma-glutamyl transferase (GGT).
- •
Lipid profile: Total cholesterol, high-density lipoprotein (HDL), low-density lipoprotein (LDL), and triglycerides.
- •
Urinary microalbumin in spot urination and albumin/creatinine ratio were measured to assess early kidney damage.
Serum NmU levels were determined using a high-sensitivity enzyme-linked immunosorbent assay (ELISA) specific to NmU. The ELISA kit was procured from a commercially available source and used based on the manufacturer's instructions for use. Measurements were assessed using an ELISA reader at a wavelength of 450±2nm. All samples were analyzed in duplicate to ensure reliability and reproducibility of results.
Statistical analysisData were analyzed using SPSS software (version 26.0). Continuous variables were tested for normality using the Shapiro–Wilk test. Normally distributed data were expressed as mean±standard deviation (SD), and non-normally distributed data as median and interquartile range (IQR). Categorical variables were expressed as frequencies and percentages.
- •
Inter-group comparisons: For normally distributed variables, independent samples t-tests and ANOVA were used. Non-normally distributed data were compared using the Mann–Whitney U test or Kruskal–Wallis test as appropriate.
- •
Correlation analyses: Spearman's rank correlation coefficient was calculated to evaluate the relationship between Neuromedin U levels and the BMI. A p-value of <0.05 was considered statistically significant for all analyses.
- •
Regression and outlier analysis: Additionally, we identified and examined influential values using Cook's distance and repeated the correlation analysis to assess their impact on the results. A p-value of <0.05 was considered statistically significant for all analyses.
A priori sample size calculation was conducted to determine the minimum number of participants required to detect a significant difference in NmU levels between diabetic patients and controls. Based on previous studies, a sample size of 40 participants per group was estimated to provide an 80% statistical power to detect a clinically significant difference in serum Neuromedin U levels with an alpha level of 0.05.
Ethical considerationsAll participants gave their prior written informed consent before being included in the study. The study protocol was approved by the Institutional Ethics Committee (protocol No.: 2011-KAEK-25 2019/07-10), and all procedures followed ethical standards in full compliance with the Declaration of Helsinki.
ResultsDemographic and clinical characteristicsA total of 134 participants were included: 45 with T1DM, 49 with T2DM, and 40 healthy controls. No significant differences were observed in age, gender distribution, or BMI between diabetic patients and controls. However, T2DM patients exhibited significantly higher systolic blood pressure (SBP), waist circumference (WC), and waist-to-hip ratio (WHR) vs T1DM and controls (Table 1).
The comparison of demographic and laboratory data between diabetic patients and healthy controls.
| Control group(n=40) | Diabetic patients with(n=94) | P | |||
|---|---|---|---|---|---|
| Mean±SD | Median (min–max) | Mean±SD | Median (min–max) | ||
| Age, years | 49±10.67 | 51.5 (21–73) | 44.18±14.43 | 45.5 (18–71) | 0.113 |
| Gender, female, n (%) | 21 (52.5) | 58 (61.7) | 0.322 | ||
| Number of children, n | 1.68±0.83 | 2 (0–3) | 2.06±1.94 | 2 (0–12) | 0.612 |
| Income, min. wage | 1.15±1.07 | 1.16 (0–5) | 1.07±0.96 | 1 (0–4) | 0.389 |
| Diabetes history | |||||
| T1DM, n (%) | N/A | 45 (47.9) | |||
| T2DM, n (%) | N/A | 49 (52.1) | |||
| Diabetes age, years | N/A | N/A | 10.3±7.55 | 11 (0.1–33) | <0.001 |
| No insulin, n (%) | N/A | 29 (30.9) | |||
| Basal insulin, n (%) | N/A | 11 (11.7) | |||
| Intensive insulin, n (%) | N/A | 54 (57.4) | |||
| Under good clinical control, n (%) | N/A | 49 (52.1) | |||
| Under bad clinical control, n (%) | N/A | 45 (47.9) | |||
| SBP, mmHg | 136.8±20.7 | 130 (100–182) | 145.63±27.78 | 144 (100–219) | 0.139 |
| DBP, mmHg | 85.35±14.93 | 82.5 (50–127) | 87.05±12.86 | 86 (60–124) | 0.505 |
| Pulse, beat/min | 75.95±6.99 | 74.5 (59–94) | 81.14±9.78 | 80 (61–105) | 0.003* |
| Weight, kg | 75.82±9.89 | 74.6 (57.4–98.9) | 74.37±14.83 | 72.85 (46.2–123.2) | 0.349* |
| Height, cm | 161.53±8.05 | 161 (148–179) | 161.52±9.68 | 160 (146–183) | 0.796 |
| BMI, kg/m2 | 29.13±3.9 | 29.2 (23.3–40.1) | 28.67±6.13 | 27.5 (18.9–50.6) | 0.304 |
| WC, cm | 96.65±9.47 | 98 (80–113) | 95.82±15.26 | 97.5 (66–137) | 0.75* |
| HC, cm | 107.28±6.71 | 106.5 (96–123) | 117.84±105.07 | 105.5 (88–1120) | 0.435 |
| Waist/hip ratio | 0.9±0.08 | 0.91 (0.75–1.07) | 0.89±0.1 | 0.89 (0.67–1.15) | 0.623* |
| NC, cm | 36.93±2.8 | 37 (32–44) | 37.54±3.33 | 38 (30–48) | 0.31* |
| WBC, cells/μL | 6640±1221.33 | 6540 (3360–9530) | 6899.61±2080.43 | 6910 (1026–11300) | 0.317 |
| Neutrophils, cells/μL | 3770±760.85 | 3815 (1740–5260) | 4267.98±1323.56 | 3990 (1690–7350) | 0.078 |
| Lymphocyte, cells/μL | 2243.75±670.05 | 2100 (1080–4130) | 2380.32±708 | 2285 (1150–4210) | 0.274 |
| Hemoglobin, g/dL | 13.97±1.4 | 14 (11.6–17.2) | 13.68±1.87 | 13.6 (8.1–18.1) | 0.386* |
| MCV, fL | 87.36±6.14 | 88 (61.5–96) | 84.77±6.94 | 87 (54–96) | 0.017 |
| Platelets, cells/μL | 252.8±57.14 | 240.5 (161–411) | 266.2±69 | 260.5 (136–449) | 0.238 |
| MPV, fL | 9.86±0.93 | 9.8 (8.3–12.5) | 10.19±1.11 | 10 (8.3–13.5) | 0.118 |
| FBG, mg/dL | 92.13±9.29 | 92 (72–113) | 177.18±91.21 | 145.5 (54–514) | <0.001 |
| PPBG, m/dL | 108.25±8.83 | 109 (89–125) | 249.61±132.27 | 203 (95–649) | <0.001 |
| HbA1c, % | 5.7±0.4 | 5.68 (4.96–6.43) | 8.83±2.68 | 7 (5.48–16.4) | <0.001 |
| BUN, mg/dL | 13.93±3.12 | 13.61 (8.55–20.05) | 12.03±3.5 | 11.73 (5.28–25) | 0.003 |
| Creatinine, mg/dL | 0.76±0.16 | 0.75 (0.52–1.16) | 0.72±0.16 | 0.7 (0.37–1.26) | 0.204 |
| AST, IU/L | 18.28±7.41 | 17 (8–54) | 17.09±10.44 | 15.5 (6–89) | 0.051 |
| ALT, IU/L | 21.23±14.43 | 17 (9–94) | 18.19±13.74 | 15 (3–106) | 0.056 |
| GGT, IU/L | 29.93±37.6 | 17.5 (8–171) | 27.52±44.51 | 16.5 (4–403) | 0.811 |
| Total cholesterol, mg/dL | 208.03±36.95 | 200.5 (132–288) | 188.6±38.25 | 190 (109–276) | 0.021 |
| HDL, mg/dL | 48.13±10.97 | 47 (33–77) | 49.02±13.63 | 49 (24–84) | 0.724 |
| LDL, mg/dL | 131.58±33.7 | 130 (48–221) | 108.56±32.51 | 103.5 (16–194) | <0.001* |
| Triglycerides, mg/dL | 138.8±73.29 | 125 (53–450) | 149.5±114.12 | 108 (29–672) | 0.493 |
| TSH, mIU/L | 2.55±1.39 | 2.19 (0.47–5.4) | 2.35±1.89 | 2.03 (0.02–11.4) | 0.192 |
| C-peptide, ng/mL | 1.73±0.61 | 1.66 (0.6–3.29) | 1.03±1.02 | 0.78 (0.05–4.77) | <0.001 |
| Urinary microalbumin, mg/L | 1.54±2.67 | 0.8 (0.2–13.1) | 4.91±11.78 | 1.6 (0.1–76.4) | <0.001 |
| Albumin/creatinine ratio | 12.99±15.28 | 7.18 (2.28–77.15) | 48.93±106.16 | 15.71 (1.18–623) | <0.001 |
| Neuromedin U, pg/mL | 7.06±10.6 | 4.84 (0–67.91) | 8.15±10.56 | 4.09 (0.82–60.26) | 0.732 |
DM: diabetes mellitus, SBP: systolic blood pressure, DBP: diastolic blood pressure, BMI: body mass index, WC: waist circumference, HC: hip circumference, NC: neck circumference, WBC: white blood cells, MCV: mean corpuscular volume, MPV: mean platelet volume, FBG: fasting blood glucose, PPBG: post-prandial blood glucose, BUN: blood urea nitrogen, AST: aspartate aminotransferase, ALT: alanine aminotransferase, HDL: high-density lipoprotein, LDL: low-density lipoprotein, TSH: thyroid stimulating hormone.
T2DM patients had significantly higher fasting blood glucose (FBG), post-prandial blood glucose (PPBG), and HbA1c levels vs T1DM and controls, reflecting poorer glycemic control. Lipid profiles showed significantly lower LDL cholesterol in diabetic groups than controls, while triglyceride levels were higher in T2DM. C-peptide levels were markedly lower in T1DM than T2DM, reflecting differences in endogenous insulin production. Mean corpuscular volume (MCV) was significantly lower in diabetic patients than controls (Table 2).
The comparison of demographic data among T1DM, T1DM and control groups.
| T1DM(n=45) | T2DM(n=49) | Control group(n=40) | P | P1 | P2 | P3 | ||||
|---|---|---|---|---|---|---|---|---|---|---|
| Mean±SD | Median (min–max) | Mean±SD | Median (min–max) | Mean±SD | Median (min–max) | |||||
| Age, years | 32.58±9.07 | 33 (18–54) | 54.84±9.27 | 56 (22–71) | 49±10.67 | 51.5 (21–73) | <0.001 | <0.001 | <0.001 | 0.003 |
| Gender, female, n (%) | 27 (60) | 31 (63.3) | 21 (52.5) | 0.581 | ||||||
| Number of children, n | 1.09±1.1 | 1 (0–4) | 2.96±2.12 | 2 (0–12) | 1.68±0.83 | 2 (0–3) | <0.001 | <0.001 | 0.005 | <0.001 |
| Income, min. wage | 1.09±1.2 | 1 (0–4) | 1.06±0.66 | 1 (0–3) | 1.15±1.07 | 1.16 (0–5) | 0.915 | 0.648 | 0.503 | 0.403 |
| Diabetes history | ||||||||||
| Diabetes age, years | 10.82±8.26 | 9 (0.3–33) | 9.82±6.89 | 11 (0.1–25) | 0±0 | 0 (0–0) | <0.001 | 0.644 | <0.001 | <0.001 |
| No insulin, n (%) | 0 (0) | 29 (59.29) | 40 (100) | |||||||
| Basal insulin, n (%) | 0 (0) | 6 (12.2) | 0 (0) | |||||||
| Intensive insulin, n (%) | 45 (100) | 14 (28.6) | 0 (0) | |||||||
| Under good clinical control, n (%) | 22 (48.9) | 27 (55.1) | N/A | |||||||
| Under bad clinical control, n (%) | 23 (51.1) | 22 (44.9) | N/A | |||||||
| SBP, mmHg | 132.47±18.05 | 127 (100–172) | 157.71±29.76 | 159 (100–219) | 136.8±20.7 | 130 (100–182) | <0.001 | <0.001 | 0.373 | 0.001 |
| DBP, mmHg | 81.38±8.9 | 80 (60–101) | 92.27±13.78 | 93 (60–124) | 85.35±14.93 | 82.5 (50–127) | <0.001 | <0.001* | 0.147* | 0.027* |
| Pulse, beat/min | 83.07±9.3 | 82 (64–103) | 79.37±9.96 | 78 (61–105) | 75.95±6.99 | 74.5 (59–94) | 0.002 | 0.066* | <0.001* | 0.061* |
| Weigh, kg | 66.47±11.13 | 66.2 (46.2–90.1) | 81.62±14.15 | 79.3 (56.4–123.2) | 75.82±9.89 | 74.6 (57.4–98.9) | <0.001 | <0.001 | <0.001 | 0.056 |
| Height, cm | 163.98±9.8 | 163 (148–183) | 159.27±9.09 | 158 (146–181) | 161.53±8.05 | 161 (148–179) | 0.045 | 0.022 | 0.284 | 0.150 |
| BMI, kg/m2 | 24.71±3.65 | 24.3 (18.9–36.8) | 32.3±5.68 | 31.1 (20–50.6) | 29.13±3.9 | 29.2 (23.3–40.1) | <0.001 | <0.001* | <0.001* | 0.003* |
| WC, cm | 84.58±10.69 | 84 (66–114) | 106.14±10.92 | 104 (82–137) | 96.65±9.47 | 98 (80–113) | <0.001 | <0.001* | <0.001* | <0.001* |
| HC, cm | 101.67±7.77 | 100 (88–125) | 132.69±144.44 | 110 (93–1120) | 107.28±6.71 | 106.5 (96–123) | 0.191 | <0.001 | <0.001 | <0.001 |
| Waist/hip ratio | 0.83±0.07 | 0.83 (0.67–0.92) | 0.95±0.08 | 0.94 (0.78–1.15) | 0.9±0.08 | 0.91 (0.75–1.07) | <0.001 | <0.001 | <0.001 | <0.001 |
| NC, cm | 35.7±2.8 | 35 (30–42) | 39.22±2.87 | 39 (33–48) | 36.93±2.8 | 37 (32–44) | <0.001 | <0.001* | <0.001* | <0.001* |
DM: diabetes mellitus, SBP: systolic blood pressure, DBP: diastolic blood pressure, BMI: body mass index, WC: waist circumference, HC: hip circumference, NC: neck circumference.
P: Probability among the groups.
P1: T1DM vs T2DM.
P2: T1DM vs control group.
P3: T2DM vs control group.
No significant differences in serum NmU levels were found between diabetic patients and healthy controls (p=0.732). However, T2DM patients had significantly higher NmU levels than T1DM (p=0.022), suggesting potential metabolic differences between the 2 subgroups. There were no notable differences between healthy controls and either diabetic subgroup (Table 3).
The comparison of laboratory data among T1DM, T1DM and control groups.
| T1DM(n=45) | T2DM(n=49) | Control group(n=40) | P | P1 | P2 | P3 | ||||
|---|---|---|---|---|---|---|---|---|---|---|
| Mean±SD | Median (min–max) | Mean±SD | Median (min–max) | Mean±SD | Median (min–max) | |||||
| WBC, cells/μL | 6598.44±1600.53 | 6300 (4050–9980) | 7176.18±2423.75 | 7500 (1026–11300) | 6640±1221.33 | 6540 (3360–9530) | 0.249 | 0.026 | 0.641 | 0.033 |
| Neutrophils, cells/μL | 3875.56±1279.53 | 3590 (1690–6630) | 4628.37±1271.38 | 4580 (2600–7350) | 3770±760.85 | 3815 (1740–5260) | 0.001 | 0.005* | 0.641* | <0.001* |
| Lymphocyte, cells/μL | 2154.67±616.32 | 2120 (1150–4210) | 2587.55±728.99 | 2630 (1320–4200) | 2243.75±670.05 | 2100 (1080–4130) | 0.006 | 0.003 | 0.57 | 0.017 |
| Hemoglobin, g/dL | 13.93±2.02 | 13.9 (9–18.1) | 13.45±1.7 | 13.5 (8.1–17.1) | 13.97±1.4 | 14 (11.6–17.2) | 0.287 | 0.331 | 0.965 | 0.28 |
| MCV, fL | 84.92±6.18 | 86 (64.7–94) | 84.64±7.63 | 87 (54–96) | 87.36±6.14 | 88 (61.5–96) | 0.128 | 0.88 | 0.031 | 0.043 |
| Platelets, cells/μL | 260.27±73.15 | 248 (136–449) | 271.65±65.24 | 270 (141–413) | 252.8±57.14 | 240.5 (161–411) | 0.396 | 0.256 | 0.673 | 0.109 |
| MPV, fL | 10.2±1.13 | 10.2 (8.3–12.6) | 10.17±1.1 | 9.9 (8.4–13.5) | 9.86±0.93 | 9.8 (8.3–12.5) | 0.267 | 0.817 | 0.144 | 0.199 |
| FBG, mg/dL | 173.02±77.88 | 163 (54–363) | 181±102.6 | 137 (77–514) | 92.13±9.29 | 92 (72–113) | <0.001 | 0.762 | <0.001 | <0.001 |
| PPBG, m/dL | 264.18±145.44 | 196 (103–540) | 236.22±118.84 | 210 (95–649) | 108.25±8.83 | 109 (89–125) | <0.001 | 0.37 | <0.001 | <0.001 |
| HbA1c, % | 8.9±2.58 | 8.15 (6.21–16.4) | 8.77±2.79 | 6.9 (5.48–13.76) | 5.7±0.4 | 5.68 (4.96–6.43) | <0.001 | 0.254 | <0.001 | <0.001 |
| BUN, mg/dL | 11.23±2.97 | 11.26 (5.28–18.69) | 12.77±3.81 | 12.8 (6.3–25) | 13.93±3.12 | 13.61 (8.55–20.05) | 0.001 | 0.03* | <0.001* | 0.118* |
| Creatinine, mg/dL | 0.71±0.15 | 0.69 (0.43–1.23) | 0.73±0.16 | 0.71 (0.37–1.26) | 0.76±0.16 | 0.75 (0.52–1.16) | 0.257 | 0.358* | 0.098* | 0.435* |
| AST, IU/L | 14.87±4.35 | 15 (7–26) | 19.12±13.6 | 16 (6–89) | 18.28±7.41 | 17 (8–54) | 0.081 | 0.205 | 0.018 | 0.273 |
| ALT, IU/L | 14.56±7.9 | 12 (3–35) | 21.53±16.87 | 16 (6–106) | 21.23±14.43 | 17 (9–94) | 0.026 | 0.005 | 0.002 | 0.726 |
| GGT, IU/L | 15.78±9.63 | 12 (4–61) | 38.31±59.2 | 23 (10–403) | 29.93±37.6 | 17.5 (8–171) | 0.034 | <0.001 | 0.011 | 0.049 |
| Total cholesterol, mg/dL | 178±38.17 | 181 (109–258) | 198.33±36.02 | 196 (127–276) | 208.03±36.95 | 200.5 (132–288) | 0.001 | 0.014 | 0.001 | 0.371 |
| HDL, mg/dL | 52.4±14.15 | 51 (27–84) | 45.92±12.49 | 45 (24–81) | 48.13±10.97 | 47 (33–77) | 0.046 | 0.014 | 0.107 | 0.362 |
| LDL, mg/dL | 100.79±31.04 | 97 (16–169) | 115.69±32.49 | 111 (46–194) | 131.58±33.7 | 130 (48–221) | <0.001 | 0.033 | <0.001 | 0.013 |
| Triglycerides, mg/dL | 109.78±98.82 | 85 (29–642) | 185.98±115.94 | 157 (56–672) | 138.8±73.29 | 125 (53–450) | 0.001 | <0.001 | 0.001 | 0.049 |
| TSH, mIU/L | 2.7±2.02 | 2.27 (0.02–10.11) | 2.03±1.72 | 1.82 (0.12–11.4) | 2.55±1.39 | 2.19 (0.47–5.4) | 0.151 | 0.064 | 0.947 | 0.031 |
| C-peptide, ng/mL | 0.22±0.24 | 0.05 (0.05–0.82) | 1.70±0.93 | 1.61 (0.35–4.77) | 1.73±0.61 | 1.66 (0.60–3.29) | <0.001 | <0.001 | <0.001 | 0.377 |
| Urinary microalbumin, mg/L | 2.24±4.37 | 1.4 (0.1–29.9) | 7.37±15.45 | 1.9 (0.3–76.4) | 1.54±2.67 | 0.8 (0.2–13.1) | 0.009 | 0.032 | 0.006 | <0.001 |
| Albumin/creatinine ratio | 20.33±28.82 | 12.14 (1.18–143) | 75.2±140.01 | 19.61 (4.21–623) | 12.99±15.28 | 7.18 (2.28–77.15) | 0.001 | 0.004 | 0.037 | <0.001 |
| Neuromedin U, pg/mL | 6.48±7.43 | 3.64 (0.82–30.8) | 9.67±12.68 | 5.19 (1.52–60.26) | 7.06±10.6 | 4.84 (0–67.91) | 0.296 | 0.022 | 0.267 | 0.647 |
WBC: white blood cells, MCV: mean corpuscular volume, MPV: mean platelet volume, FBG: fasting blood glucose, PPBG: post-prandial blood glucose, BUN: blood urea nitrogen, AST: aspartate aminotransferase, ALT: alanine aminotransferase, HDL: high-density lipoprotein, LDL: low-density lipoprotein, TSH: thyroid stimulating hormone.
P: Probability among the groups.
P1: T1DM vs T2DM.
P2: T1DM vs control group.
P3: T2DM vs control group.
In T2DM patients, Neuromedin U showed a weak, non-significant correlation with C-peptide (Spearman's rho=0.245; p=0.089; 95%CI, −0.047 to 0.499), indicating no clear association.
Correlation between Neuromedin U and anthropometric variablesNeuromedin U and BMI- •
In the control group, there was a significant inverse correlation between NmU and BMI (ρ=−0.341, p=0.0335), indicating a moderate negative relationship (Fig. 1a).
 Figure 1.
Scatter plots illustrating correlations between anthropometric measures and Neuromedin U levels in the control group. (a) Correlation between body mass index (BMI) and Neuromedin U levels; (b) correlation between waist circumference (WC) and Neuromedin U levels; (c) correlation between waist-to-hip ratio (WHR) and Neuromedin U levels. A dashed red line in each graph represents the regression trend, and red points denote influential observations identified by Cook's distance. Spearman's correlation coefficient (rho), p-value, and 95% confidence intervals are displayed for statistical interpretation.
- •
In T1DM, the correlation was weak and non-significant (ρ=−0.064, p=0.678) (Fig. 2a).
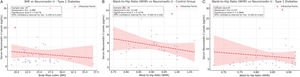 Figure 2.
Scatter plots depicting correlations between anthropometric parameters and Neuromedin U levels in T1DM patients. (a) Correlation between body mass index (BMI) and Neuromedin U levels; (b) correlation between waist circumference (WC) and Neuromedin U levels; (c) correlation between waist-to-hip ratio (WHR) and Neuromedin U levels. Each graph includes a dashed red regression trend line, with influential observations highlighted by red markers. Spearman's correlation coefficient (rho), p-value, and 95% confidence intervals are provided to aid statistical interpretation.
- •
In T2DM, the correlation was minimal (ρ=−0.025, p=0.867), suggesting a lack of association between NmU and BMI in diabetic patients (Fig. 3a).
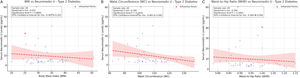 Figure 3.
Scatter plots illustrating correlations between anthropometric measures and Neuromedin U levels in T2DM patients. (a) Correlation between body mass index (BMI) and Neuromedin U levels; (b) correlation between waist circumference (WC) and Neuromedin U levels; (c) correlation between waist-to-hip ratio (WHR) and Neuromedin U levels. Each plot includes a dashed red regression trend line, with influential data points highlighted in red. Spearman's correlation coefficient (rho), p-value, and 95% confidence intervals are provided to evaluate the strength and significance of each correlation.
- •
Regression analysis confirmed a downward trend in all groups, though it was statistically significant only in healthy controls. Influential values were detected across groups.


- •
In the control group, a negative but non-significant correlation was observed (ρ=−0.240, p=0.141) (Fig. 1b).
- •
In T1DM, no meaningful correlation was detected (ρ=0.028, p=0.853) (Fig. 2b).
- •
In T2DM, a weak negative correlation was present but not significant (ρ=−0.185, p=0.202) (Fig. 3b).
- •
Regression analysis showed a non-significant decreasing trend across groups, with influential points identified.
- •
In the control group, the correlation was weakly negative but not statistically significant (ρ=−0.146, p=0.376) (Fig. 1c).
- •
In T1DM, a weak positive correlation was observed but was not significant (ρ=0.132, p=0.387) (Fig. 2c).
- •
In T2DM, the correlation remained weak and negative but did not reach significance (ρ=−0.184, p=0.206) (Fig. 3c).
- •
No significant correlations were found in any group, and regression analysis showed relatively flat regression lines.
Regression models were fitted for all groups of NmU vs BMI, WC, and WHR. Influential values, identified via Cook's distance, were present across all groups, indicating that a small number of individuals may strongly affect the observed correlation trends. After removing these influential values, the inverse relationship between NmU and BMI in healthy controls remained significant. However, in diabetic groups, excluding outliers did not alter the lack of correlation. These findings suggest that the metabolic role of NmU may be disrupted in diabetes, warranting further investigation into potential confounding factors.
DiscussionThis study aimed to evaluate serum NmU levels in patients with T1DM and T2DM vs healthy controls, and explore the relationship between NmU and BMI in these populations. Our findings indicate no significant differences in NmU levels between diabetic patients and healthy controls, suggesting that NmU is not a distinguishing biomarker between these groups. Furthermore, no significant correlations were observed between NmU levels and BMI in T1DM and T2DM patients, implying that the metabolic role of NmU may be altered or less pronounced in the context of diabetes. Interestingly, a significant inverse correlation between NmU levels and BMI was identified in the healthy control group, pointing toward a potential role for NmU in metabolic regulation in healthy individuals. These findings are novel as this is the first study to examine NmU levels across diabetes subtypes, highlighting its possible importance in metabolic processes in non-diabetic populations. Further investigation is warranted to determine whether NmU could serve as a therapeutic target for metabolic regulation, particularly in non-diabetic individuals.
The significantly higher NmU levels observed in T2DM vs T1DM (p=0.022) may be attributed to the distinct pathophysiological differences between these conditions. T2DM is characterized by insulin resistance and compensatory hyperinsulinemia, which could lead to an upregulation of NmU as a modulator of insulin secretion and metabolic regulation. Prior studies have demonstrated that NmU inhibits glucose-stimulated insulin secretion through G-protein-coupled pathways, potentially contributing to β-cell dysfunction and metabolic stress.9 This is consistent with our findings, where T2DM patients had higher fasting glucose, HbA1c, and C-peptide levels, reflecting preserved yet dysfunctional β-cell activity. In contrast, T1DM patients, characterized by autoimmune β-cell destruction, exhibited lower C-peptide and NmU levels. Additionally, systemic inflammation is more pronounced in T2DM, and inflammatory cytokines such as IL-6 and TNF-α have been involved in regulating the expression of NmU, which could further explain the observed elevation in this group.10 The lack of a significant correlation between NmU and BMI in the diabetic groups, despite a clear inverse association in healthy controls, suggests that the regulatory role of NmU in metabolic homeostasis may be disrupted in diabetes. Future studies should investigate whether NmU alterations in T2DM represent an adaptive response to metabolic dysregulation or a potential disease severity and progression biomarker.
The lack of significant differences in NmU levels between the diabetic groups and controls is striking given previous evidence suggesting the role of NmU in glucose and insulin regulation. NmU has been identified as a regulatory peptide that can influence insulin secretion via NMUR1, which predominantly uses Gαi signaling pathways to suppress insulin release by reducing intracellular calcium mobilization in pancreatic β-cells.6 This mechanism highlights the role of NmU in glucose homeostasis, making the absence of distinct differences in NmU levels across groups an intriguing finding. One possible explanation for this could be the complexity of the metabolic dysregulation seen in diabetes, where multiple pathways beyond NmU influence glucose and insulin dynamics.
Despite the emerging understanding of the role of NmU in energy homeostasis and feeding behavior, particularly in animal models, the direct role of NmU in human metabolic diseases, including diabetes, remains underexplored.11,12 Studies have shown that NmU can exert anorexigenic effects independent of leptin, suggesting a broader role in energy balance and body weight regulation.11 However, our study findings indicate that while NmU may contribute to metabolic regulation in healthy individuals, as evidenced by the inverse correlation with BMI in controls, this regulatory mechanism may be disrupted or diminished in the context of diabetes. The exact mechanisms by which diabetes affect NmU signaling and its relationship with BMI warrant further investigation.
Moreover, recent research has highlighted the multifactorial nature of diabetes, where genetic and environmental factors interact to influence metabolic outcomes. In a large-scale study of T2DM, multiple genetic loci were identified as contributors to β-cell dysfunction, demonstrating the complexity of the disease.13 The role of NmU in such a multifactorial disease environment may be influenced by these genetic factors, which could explain the lack of significant NmU changes in our diabetic groups. Additionally, it is possible that the chronic hyperglycemic state and insulin resistance in diabetes override the regulatory effects of NmU on energy balance and body weight, further complicating its role as a biomarker for diabetes.
Our study is the first to systematically evaluate NmU levels across diabetic subtypes and healthy controls, providing unique insights into its potential role in metabolic regulation. The significant inverse correlation between NmU and BMI in the healthy control group aligns with previous findings that suggest NmU may play a role in weight regulation in individuals without metabolic disorders,14–16 which could imply that the function of NmU is more pronounced in states of metabolic balance, where it acts to maintain energy homeostasis, but is disrupted in pathological conditions such as diabetes.
Additionally, while NmU has been shown to influence several physiological functions including circadian rhythms, immune responses, and stress regulation.17,18 Its specific role in metabolic regulation, particularly in humans, remains incompletely understood. The absence of significant changes in NmU levels in diabetic patients may point to the possibility that NmU is not directly involved in the pathogenesis of diabetes but may serve as a secondary regulator of metabolic homeostasis under normal conditions.
Our findings open several avenues for future research. Given the significant association between NmU and BMI in healthy individuals, future studies could explore whether NmU might serve as a therapeutic target in conditions such as obesity and metabolic syndrome, where energy imbalance plays a central role. Furthermore, studies investigating the molecular mechanisms by which NmU signaling is impaired in diabetes could provide deeper insights into its role in the disease. Longitudinal studies assessing NmU levels before and after the onset of diabetes could also help clarify whether changes in NmU signaling are a cause or consequence of metabolic dysfunction.
In conclusion, while NmU does not seem to serve as a direct biomarker for diabetes in this study, its significant correlation with BMI in healthy individuals suggests a role in metabolic regulation in non-diabetic populations. However, this regulatory mechanism appears to be disrupted in individuals with diabetes, potentially due to metabolic alterations, insulin resistance, or chronic hyperglycemia affecting NmU signaling. Future research should aim to further elucidate the role of NMU in metabolic disorders and explore its potential as a therapeutic target, particularly in non-diabetic individuals or in early-stage metabolic dysfunction.
Limitations of the studyThis study has several limitations that should be acknowledged. First, while we investigated the correlation between NmU and BMI, we did not adjust for potential confounding variables such as HbA1c levels in diabetic patients. Given the role of glycemic control in metabolic regulation, the relationship between NmU and BMI may be influenced by variations in long-term blood glucose levels. Second, the study cross-sectional design limits our ability to establish causality between NmU levels and metabolic parameters. Longitudinal studies are needed to determine whether changes in NmU are a consequence of diabetes progression or play a role in its pathophysiology. Additionally, while our study included a well-defined cohort, the sample size may not have been large enough to detect subtle but clinically relevant differences in NmU levels across subgroups. Future research should consider larger, multi-center studies with broader demographic representation to improve generalizability. Finally, we did not account for dietary intake, physical activity, or other lifestyle factors that could influence NmU levels and metabolic status. Controlling for these factors in future studies may help clarify the exact role of NmU in metabolic disorders.
Ethical approvalThe local ethics committee approval (2011-KAEK-25 2019/07-10) was obtained, and the study was conducted in full compliance with the declaration of Helsinki. The prior written informed consent form was obtained from all participants.
Conflicts of interestNone declared.


