





Alcohol consumption has been linked to increased aggressiveness and to different types of violence. It has been suggested that both the empathic disposition and the executive function (EF) are mediators and moderators of aggression in alcoholic patients and during alcohol intoxication. In this work, we analyze the cognitive-affective profile that mediates or modulates the relationship between alcohol consumption and violence in social drinkers.
MethodsAn intentional sample of adults (aged 21–65; n=393) was assessed through an online platform. Usual alcohol consumption patterns were assessed and the following standardized instruments were included: Alcohol Use Disorders Identification Test (AUDIT); Interpersonal Reactivity Index (IRI) and Reading the Mind in the Eyes Test (RME), to assess dimensions of empathy; Adult Executive Inventory (ADEXI) and Cognitive Flexibility Scale (CFS), to assess dimensions of EF. The cognitive-affective profile of the participants, classified according to their usual alcohol consumption patterns, was analyzed through ANOVA. Following that, several models of the relationship between alcohol consumption, the cognitive-affective variables and violence were tested through Structural Equation Modeling (SEM).
ResultsSignificant differences were found among alcohol abstainers, light drinkers, moderate drinkers and heavy drinkers in the variables working memory F(3.389)=3.32; p=.022, inhibition F(3.389)=8.89; p<.000 and perspective taking F(3.389)=6.62; p<.000. According to the post hoc testing, the differences in working memory, inhibition and perspective taking were significant among the group of heavy drinkers and the other drinkers groups, but not between abstainers, light and moderate drinkers. The SEM which showed better fit was the one in which inhibition mediates or modulates the relationship between alcohol consumption and violence (CMIN/DF=1.890; CFI=926; RMSEA=.048).
ConclusionsThe deficit in cognitive functions, particularly in the inhibitory response, constitutes a key factor in understanding the violence linked to alcohol consumption and, in a more general way, the social conflicts among people who drink alcohol.
El consumo de alcohol se ha relacionado con una mayor agresividad y con diferentes tipos de violencia. Se ha sugerido que tanto la disposición empática como la función ejecutiva (FE) son mediadores y moderadores de la agresión en pacientes alcohólicos y durante la intoxicación alcohólica. En este trabajo analizamos el perfil cognitivo-afectivo que media o modula la relación entre consumo de alcohol y violencia en bebedores sociales.
MétodoSe entrevistó a una muestra intencional de adultos (21 a 65 años; n=393) a través de una plataforma en línea. Se evaluaron los patrones habituales de consumo de alcohol y se incluyeron los siguientes instrumentos estandarizados: Alcohol Use Disorders Identification Test (AUDIT); Interpersonal Reactivity Index (IRI) y Reading the Mind in the Eyes Test (RME), para evaluar dimensiones de empatía; Adult Executive Inventory (ADEXI) y Cognitive Flexibility Scale (CFS), para evaluar dimensiones de las FE. El perfil cognitivo-afectivo de los participantes, clasificados según sus patrones habituales de consumo de alcohol, se analizó mediante la escala ANOVA. Posteriormente, se probaron varios modelos de la relación entre el consumo de alcohol, las variables cognitivo-afectivas y la violencia a través de Modelos de Ecuaciones Estructurales (SEM).
ResultadosSe encontraron diferencias significativas entre abstemios, bebedores leves, bebedores moderados y bebedores fuertes en las variables Memoria de Trabajo F (3.389)=3.32; p=0,022, Inhibición F (3.389)=8,89; p<0,000 y Toma de Perspectiva F (3.389)=6,62; p<0,000. De acuerdo con las pruebas post hoc, las diferencias en Memoria de Trabajo, Inhibición y Toma de Perspectiva fueron significativas entre el grupo de bebedores fuertes y los otros grupos de bebedores, pero no entre abstemios, bebedores leves y bebedores moderados. El SEM que mostró mejor ajuste fue aquel en el que la Inhibición modula la relación entre el consumo de alcohol y la violencia (CMIN/DF=1.890; CFI=926; RMSEA=0,048).
ConclusionesEl déficit en las funciones cognitivas, particularmente en la respuesta inhibitoria, constituye un factor clave para comprender la violencia ligada al consumo de alcohol y, de manera más general, los conflictos sociales entre las personas que beben alcohol.
Alcohol consumption has been linked to increased aggressiveness and to different types of violence.1 This poses a problem for the social environment of the drinkers and for the drinkers themselves. Interpersonal conflicts related to alcohol consumption have been linked to relapses in the treatments of Alcohol Use Disorders (AUD),2 which, in turn, exacerbate social problems over time, creating a vicious circle in which intra and interpersonal recovery and well-being become increasingly remote.
A number of studies have suggested that empathic disposition3,4 both constitutes a mediator and a moderator of aggression during alcohol intoxication. The ability to understand other people, to accurately interpret their emotional states, is fundamental for maintaining healthy social relationships. Problems with this ability could explain the relational and social conflicts that are frequently reported in people with alcohol consumption related disorders.5,6 Convergently, it has been suggested that empathy could play an important role in the reducing violent behavior and it has been linked to the sense of morality, altruism, pro-social behavior, and cooperation.7,8
Empathy is a lay concept, typically described as the ability to ‘put oneself in another's shoes’. It encompasses various processes, partially dissociated from a neurobiological perspective.9 These processes include the ability to recognize another person's mental states through emotional cues, the capacity to contextualize them based on information about that person to make more complex inferences regarding their mental states (thoughts, feelings, and perspectives), and the ability to respond affectively in a congruent manner to these mental states. From a multidimensional perspective, Blair proposed three partially dissociable neurocognitive systems, including a motor-empathy system, an emotional empathy system, and a cognitive or ‘Theory of Mind system’.10 These systems are interrelated. Representations of another person's internal mental state are assumed to serve as stimuli for the activation of an affective, empathic response.11 Furthermore, accurately discerning affective cues to identify mental states is necessary for contextualizing them and for developing more mature cognitive skills involved in adopting another person's perspective.12
Studies on empathy have usually centered their analyses alternatively on the relatively automatic and non-conscious processes of identifying emotions from affective-social cues (i.e., visual, auditory, multimodal), or on the inferential processes about others’ mental states, which are dependent on higher cognitive functions. These later processes are included in the term ‘cognitive empathy’ (CE) or referred to through concepts such as ‘perspective taking,’ ‘mentalizing,’ and ‘theory of mind.’ In the same way, studies on alcohol and empathy typically address a specific dimension of the construct at a time.
In the field of perception and recognition of emotional gestures, studies have found that alcoholic patients struggle with emotion identification through visual stimuli – facial expressions or bodily postures – and auditory stimuli – in the prosody of language–, as well as with multimodal processing – visual and auditory – of emotional stimuli.13–16 Some authors have also reported a tendency to misinterpret specific emotions, getting a few of them confused, for example, sadness with anger, and joy with a negative emotion;15,17,18 underestimating some, such as sadness and fear; and overestimating others, such as anger.14
Regarding the cognitive aspects of empathy, several studies have pointed that the performance of alcoholic patients in perspective taking, theory of mind and in mentalizing skills is worse than in healthy controls.19 These skills have been assessed in the understanding of funny stories19 and stories which include irony and sarcasm.20
Another construct that has been signaled as a possible mediator and modulator of the relationship between alcohol consumption and violence is the Executive Function (EF).4,21,22 The term EF refers to a set of cognitive processes which allow the regulation of our thoughts, our emotions and our behavior in order to orient them to the achievement of goals.23,24 An alternate way of referring to EF is as higher-order cognitive functions, or controlled processes, since they exert control over other cognitive processes and over conative processes.25 Through the regulation of cognitive, emotional and behavioral activity, the EF facilitates social adjustment and flexible adaptation to different personal–situational contexts. These process, by being involved in self-regulation, is very relevant when it comes to avoiding socially maladaptive behaviors.
Among the different perspectives on the study of the relationship between EF and alcohol consumption, studies analyzing the performance of EF during alcohol intoxication are the most prevalent ones. It has been consistently demonstrated that alcohol consumption has an acute effect on different dimensions of EF, including information updating, cognitive flexibility and inhibitory response.26 Results are more consistent regarding to some dimensions of the construct than regarding others. For instance, alcohol has an acute effect on the verbal and auditory working memory,27–29 but this effect is less evident on the visual-spatial working memory.30–32 Inhibitory response is the most studied dimension of EF regarding acute alcohol consumption,26 with evidence indicating the consistent detrimental effect alcohol intoxication has on inhibition.33–37 Research on the relationship between cognitive flexibility and acute alcohol intoxication is scarcer.38,39 Studies coming from this perspective also point that the effect alcohol intoxication has on the EF is dose-dependent, with a more severe outcome the higher the level of intoxication.40
Another significant part of the research regarding the relationship between EF and alcohol consumption has been conducted in clinical population. Alcohol Use Disorders (AUD), alcohol Abuse and Dependence have been related to long term deficits in EF, including processes such as fluency, working memory, inhibition, flexibility and decision making, with a reduction in the structure of the prefrontal cortex.41–45 AUD have also been associated with a dysfunction of the prefrontal cortex,46 which constitutes the neuroanatomical foundation of the EF.24
The relationship between AUD and EF has also been analyzed in the opposite direction.47,48 In fact, it has been established that the deficit in EF constitutes a risk factor for the development of AUD,26 increasing the likelihood of alcohol consumption related problems49 and limiting the benefits of the treatments.
Studies about the relationship between alcohol consumption and EF in social drinkers or in non-clinical population are scarcer and inconsistent. A meta-analysis of the relationship between EF and alcohol consumption in this population concluded that the EF is not affected in social drinkers.50 However, heavy drinkers have shown poorer performance than light drinkers in measures of flexibility and inhibitory control.50 In university students, binge-drinking (episodic consumption of large amounts of alcohol) has been related to poor EF performance.51 These inconsistencies could be related to the variety of EF assessment instruments and the variety of dimensions of the construct assessed in the different studies.26,50
Empathy and EF, both signaled as mediators and modulators of the relationship between alcohol consumption and violence are, besides, processes that have been linked with each other in different ways. Executive functioning has been related to social cognition and empathic ability, to the extent that some dimensions of EF, like cognitive flexibility, have been included as basic components in theoretical models of empathy.52 Studies conducted in patients with brain damage have reported a relationship between empathy and EF, particularly between cognitive empathy and flexibility,53–55 and also between working memory, inhibitory control and difficulties in the revision of inferences.56
Theory of Mind (TOM), as a concept overlapping empathy,57 has been related to executive functions in different ways, alternatively considering that: (1) the TOM is a prerequisite for executive control; (2) executive functions are fundamental for the development of the TOM, and; (3) the main tasks of the TOM involve executive components.58 In relation to the first of these hypotheses, Perner and collaborators postulated that the capacity underlying Theory of Mind (ToM) to understand representations as representations (i.e., metarepresentational capacity) is a prerequisite for the development of executive control.59,60 According to these authors, a child can successfully inhibit prepotent responses and perform well in tasks requiring inhibitory control only if they have developed a ToM. Regarding the reverse hypothesis, Russell61,62 proposed that an individual's ability to monitor actions and act voluntarily enables the development of a pre-theoretical self-awareness, which, in turn, is fundamental for the conceptual apprehension of the mind. In this line of thought, a crucial role has been attributed to inhibitory control in the emergence of attributing mental states,63 and a predictive value of Executive Functions (EF) in the development of ToM has been reported in longitudinal studies of preschool-age children.64,65 Finally, in support of the hypothesis that core ToM tasks include executive components, it has been found that responding adequately to tasks involving making inferences about the contents of another's mind requires the inhibitory component of the executive construct, allowing the suppression of incorrect responses.66,67
Regarding more “automatic” processes including in the concept of empathy, executive deficits has been associated with difficulties accurately interpreting facial affect or decoding emotional cues.68 This task could been affect by frontal functioning because subjects have to match the expression in a picture to expressions stored in memory and seen before in the context of a particular mental state.57 With regard to the emotional response linked to empathy, personal distress, as a subdimension of emotional empathy,69,70 is mediated by subcortical structures of the limbic system. However, moral decision-making and empathic concern for others, as another subdimension of emotional empathy that encompasses moral thinking, would be mediated by prefrontal structures.71
As we have mentioned before, the neuro-anatomical substrate of the EF is the Prefrontal Cortex (PFC), and EF deficits in alcoholic patients have been explained by the so-called “frontal lobe hypothesis”, which suggests a specific vulnerability of the PFC to the neurotoxic effects of alcohol. This hypothesis has been supported by research which analyze the changes produced in the brain due to alcoholism. They have provided evidence of a particular affectation of the frontal lobes,46 while the functional studies report reduced activity of the medial and superior frontal cortex, and of the cingulated cortex, in alcoholic patients.72 Considering, as described above, that empathy also depends, in part, on the processing taking place in the prefrontal cortex (PFC), deficits in the empathy of alcoholic patients could be explained by the same hypothesis: the specific vulnerability of the PFC to the neurotoxic effects of alcohol could affects structure that are clue to empathic processes, like ventromedial prefrontal cortex.73
In summary, while the relationship between alcohol consumption and various forms of violence has been widely studied and is of significant social relevance, the analysis of cognitive-affective deficits that may modulate this relationship is still under development4 and is particularly important for preventing and addressing this problem.
Research on alcohol and empathy is limited, particularly in terms of assessing different processes. Furthermore, the findings are somewhat contradictory. Some authors have reported deficits in various affective and cognitive processes related to empathy,19 while others have identified deficits only in the decoding of emotional expressions.74 Moreover, these studies have been conducted almost exclusively with chronic alcoholic patients and might not reflect the characteristics of these relationships in general population. Similarly, studies on alcohol and EF have predominantly focused on clinical population, or examined the acute effects of alcohol intoxication on cognitive functions. Research involving social drinkers or on non-clinical population is also sparse and has yielded conflicting results.26,50 Finally, there's a shortage of studies examining the potential mediating role of empathy or EF in the relationship between alcohol consumption and violence.3,4,21,22
In this general context, the aim of this work is to contribute to the study of the cognitive-affective profile that modulates the relationship between alcohol consumption and violence in general, non-clinical population with no history of alcoholism. To achieve this, the study describes cognitive-affective profiles of adults based on their usual alcohol consumption patterns. Additionally, it proposes explanatory models for the relationship between alcohol consumption and violence, analyzing the mediating role of executive functions and empathy.
MethodParticipantsAn intentional sample of 393 adults aged between 21 and 65 was interviewed (M=33.7; SD=12.3). The inclusion/exclusion criteria were: (1) being able to consent to the participation in the study, (2) not having a personal history of AUD; (3) not having other psychiatric, neurodevelopmental or learning disorder diagnoses that could influence the performance in the study tests.
This study was approved by the Ethics Committee of the Universidad Adventista del Plata. All participants provided their informed consent to participate. The informed consent included data about the study, its aim and institutional framework, as well as information regarding the handling of the data that would be generated from it – confidentiality and exclusively statistical treatment of the data.
Sixty-five percent were women. The educational level of the sample was high, considering that 43.1% were pursuing a university degree, 29.3% had completed university degrees, and 19.7% had finished post-graduate degrees.
Instruments- 1)
A questionnaire of clinical data, including personal and family AUD records, neurodevelopmental, psychiatric and learning disorders diagnoses, and sociodemographic data, developed ad-hoc.
- 2)
Amount/Frequency and Graduated Frequency Methods75 to assess alcohol consumption. The first method consists of asking interviewees how often they drink alcoholic beverages, with 9 response options, ranging from never to every day (1. Never; 2. 1–5 times a year; 3. 6–11 times a year; 4. About once a month; 5. 2–3 times a month; 6. 1–2 times a week; 7. 3–4 times a week; 8. Almost every day; 9. Every day). Then, interviewees are asked how many drinks (standard alcohol units, approximately 12g) they usually have when they consume (open response).
In the Graduated Frequency method, interviewees are asked how often they consume a specific amount of alcohol in order to assess episodic consumption of large amounts (binge-drinking). The consumption of 12 or more standard units and 6 or more standard units on the same occasion was assessed using the same 9 response options as in the usual alcohol consumption frequency question described above.
- 3)
Alcohol Use Disorders Identification Test (AUDIT),76 in its version adapted to local context.77 This is a screening test used to identify excessive alcohol consumption and disorders due to excessive consumption (risky consumption, harmful use, and possible dependency – ICD-10). It consists of 10 questions combining items about recent alcohol consumption, and items of symptoms of dependency and problems related to consumption. Previous evidence indicates that the test has a two-factor structure, with one factor grouping items related to consumption patterns and the other grouping items related to the behavioral and social symptoms of harmful use and dependence.78,79
- 4)
The version of the Adult Executive Functioning Inventory (ADEXI) adapted into Spanish.80,81 The ADEXI is a short EF inventory of only 14 items, suitable for assessing EF in adult population with non-clinical disorders, since it does not describe extreme or pathological behaviors. It assesses two specific EF dimensions: inhibition and working memory. The items of the dimension inhibition seek to explore the ability to inhibit thoughts, emotions and/or behaviors in order to solve a problem or reach a goal. The items of the dimension working memory focus on the ability to address attentional and mnesic resources in order to allow the manipulation and integration of relevant information in the conscience so as to complete a task or reach a goal.
- 5)
The version of the Cognitive Flexibility Scale (CFS) adapted into Spanish.82,83 This is a short scale of 12 items, used to assess Cognitive Flexibility, understood as the ability to recognize alternatives and options in any given situation, the desire to be flexible and to adapt to different contexts, and the feelings of self-efficacy regarding the ability to be flexible.
- 6)
The Interpersonal Reactivity Index (IRI).70 This is a measure of empathy that considers four dimensions, including emotional and cognitive aspects of the construct: fantasy and perspective taking (cognitive aspects), and Empathic Concern and Personal Distress (emotional aspects).
- 7)
The brief version of the Reading the mind in the eyes test (RME) adapted into Spanish.57,84 This is a test created to identify, through visual stimuli, slight deficits in the understanding of social cues. The test consists of attributing an emotional/mental state to a person (choosing between 4 options) through a minimal clue; a portion of a facial expression in a picture, correspondent to the area of a person's eyes. The short version, adapted into Spanish, consists of 18 stimuli.84
The test was conceived as a test of the ability to put oneself in the minds of others and ‘tune in’ with their mental states.57 It was described as an ‘advanced theory of mind test.’ Theory of mind is the ability to attribute mental states to oneself and others,85 and thereby make sense of or predict others’ behavior. This concept is also referred to as ‘mentalizing,’ and according to the authors of the test, it overlaps with the term ‘empathy’.57
Even though it is described as an advanced test of theory of mind, the RME actually only assesses the first stage of this ability, which is the attribution of the relevant mental state (e.g., compassion). It does not assess the second stage of theory of mind ability, which is the contextualization of that mental state in a particular person that allows one to truly understand him or her (e.g., compassion for his/her mother's loss).57 Attribution of the relevant type of mental state is, however, a basic part of theory of mind and empathy processes, necessary to make correct inferences about others’ mental states, engage in perspective taking, and experience empathic concern. Evaluation of this ability has proved to be useful in identifying people with mild deficits in social sensibility.57 An advantage of this test is that, unlike self-report tests, it is not susceptible to biases such as social desirability. Furthermore, as mentioned in the introduction, emotion identification through visual stimuli is a specific aspect of social cognition in which alcoholic patients tend to fail.13–16
- 8)
A version of the Aggression Scale (AS) adapted into Spanish.81,86 This is a measure of violent behavior that includes items to assess attitudinal, verbal and physical violence. People have to report how often each of the situations being described happened to them during the last month.
Participants were invited to be a part of the study through social media (Facebook, Instagram), messaging apps (Whatsapp) and institutional networks (internal networks of public and private universities, and institutes of scientific research). Interviews were conducted through an online platform. Before initiating the interview, participants had to provide their informed consent digitally, clicking on a button that indicated “I agree to participate”.
Data analysisFirstly, the alcohol consumption habits of the interviewees were described, using descriptive statistics.
Secondly, the performance of the interviewees regarding the cognitive-affective variables assessed, according to their usual alcohol consumption, was analyzed through ANOVA. In order to classify the participants based on their usual alcohol consumption, the Dietary Guidelines for Americans 2015–202087 and the Drinking levelsdefined88 were used, conforming the following 4 categories: Abstainers (no alcohol consumption during the last year), Light drinkers (consumption of less than 1.5 standard units of alcohol each time alcohol was consumed during the last year, and less than 7 standard units a week), Moderate drinkers (consumption between 1.5 and 3.4 standard units of alcohol each time alcohol was consumed during the last year, and less than 14 standard units a week), and Heavy drinkers (consumption of 3.5 or more standard units of alcohol each time alcohol was consumed during the last year, or more than 14 standard units a week).
Lastly, Pearson's correlations were conducted, including the following instruments and their dimensions: ADEXI, the CFS, the IRI, the RME, and the AUDIT, and after that, according to the background information and the correlations that were found, several explanatory models of the relationship between alcohol consumption and violence were tested, through Structural Equation Modeling (SEM).
For the management and analysis of the data, the programs used were SPSS vers. 17 and AMOS Graphics 7.0.
Results- 1.
Alcohol consumption habits
Among the interviewees, only 7.9% was lifelong abstainer, while 87% was current drinker (i.e. had consumed at least one standard unit of alcohol during the last year). Among the current drinkers, 90% had drunk during the last month, and 72.2% had drunk at least once during the week prior to the interview.
Most interviewees drank on a weekly basis (40.5%) or on a monthly basis (31.8%) (see Table 1). The average amount of regular alcohol consumption among current drinkers was 2.61 standard units (SD=2.2), with a minimum consumption of 1 standard unit each time alcohol was consumed, and a maximum of 20 standard units. The most frequently consumed drinks were beer (52.3%) and wine (23.1%).
- 2.
Cognitive-affective profiles based on usual alcohol consumption
Alcohol consumption patterns.
| Men | Women | No binary | Total | |||||
|---|---|---|---|---|---|---|---|---|
| Usual consumptionquantitya | ||||||||
| Average consumption | 3.15 | (SD=2.6) | 2.29 | (SD=1.8) | – | – | 2.6 | (SD=2.2) |
| Usual frequency of consumption | ||||||||
| n | % | n | % | n | % | N | % | |
| No current drinkersb | 9 | 2.3 | 41 | 10.4 | 1 | 0.3 | 51 | 13.0 |
| 1–5 times a year | 6 | 1.5 | 18 | 4.6 | 0 | 0.0 | 24 | 6.1 |
| 6–11 times a year | 3 | 0.8 | 15 | 3.8 | 0 | 0.0 | 18 | 4.6 |
| About once a month | 12 | 3.1 | 26 | 6.6 | 0 | 0.0 | 38 | 9.7 |
| 2 or 3 times a month | 27 | 6.9 | 60 | 15.3 | 0 | 0.0 | 87 | 22.1 |
| 1 or 2 times a week | 54 | 13.7 | 72 | 18.3 | 0 | 0.0 | 126 | 32.1 |
| 3 or 4 times a week | 19 | 4.8 | 14 | 3.6 | 0 | 0.0 | 33 | 8.4 |
| Almost every day | 3 | 0.8 | 10 | 2.5 | 0 | 0.0 | 13 | 3.3 |
| Every day | 2 | 0.5 | 1 | 0.3 | 0 | 0.0 | 3 | .8 |
| Total | 135 | 34.3 | 257 | 65.4 | 1 | 0.3 | 393 | 100.0 |
Significant differences were found among the groups (Abstainers, Light drinkers, Moderate drinkers, Heavy drinkers) in the variables working memory F(3.389)=3.32; p=.022, inhibition F(3.389)=8.89; p<.000, and perspective taking F(3.389)=6.62; p<.000. According to post hoc tests (Turkey), the difference in working memory was significant among the group of heavy drinkers and the groups of light drinkers (p=.006) and moderate drinkers (p=.020). The differences in inhibition were significant among the group of heavy drinkers and the other 3 groups: abstainers (p<0.000), light drinkers (p<0.000) and moderate drinkers (p<0.000). The differences in perspective taking were significant among the group of heavy drinkers and the other 3 groups: abstainers (p=0.005), light drinkers (p=0.001) and moderate drinkers (p<0.000). The descriptive statistics are presented in Table 2.
- 3.
Explanatory models of the relationship between alcohol consumption and violence.
Performance of each group of drinkers in Empathy and Executive functions.
| N | Mean | Standard deviation | |
|---|---|---|---|
| RME | |||
| Abstainers | 51 | 14.63 | 2.30 |
| Light drinkers | 76 | 14.67 | 2.89 |
| Moderate drinkers | 212 | 14.72 | 2.37 |
| Heavy drinkers | 54 | 14.19 | 2.48 |
| Total | 393 | 14.63 | 2.48 |
| Cognitive flexibilitya | |||
| Abstainers | 51 | 53.61 | 10.22 |
| Light drinkers | 76 | 54.97 | 9.50 |
| Moderate drinkers | 212 | 53.74 | 9.05 |
| Heavy drinkers | 54 | 51.06 | 9.35 |
| Total | 393 | 53.59 | 9.37 |
| Working memoryb | |||
| Abstainers | 51 | 37.67 | 6.45 |
| Light drinkers | 76 | 39.30 | 5.01 |
| Moderate drinkers | 212 | 38.48 | 5.56 |
| Heavy drinkers | 54 | 35.91 | 6.96 |
| Total | 393 | 38.18 | 5.86 |
| Inhibitionc | |||
| Abstainers | 51 | 20.31 | 3.92 |
| Light drinkers | 76 | 20.37 | 3.93 |
| Moderate drinkers | 212 | 19.68 | 3.69 |
| Heavy drinkers | 54 | 17.17 | 4.14 |
| Total | 393 | 19.55 | 3.94 |
| Perspective taking | |||
| Abstainers | 51 | 23.94 | 4.64 |
| Light drinkers | 76 | 23.99 | 3.97 |
| Moderate drinkers | 212 | 23.86 | 4.66 |
| Heavy drinkers | 54 | 21.00 | 4.26 |
| Total | 393 | 23.50 | 4.57 |
| Fantasy | |||
| Abstainers | 51 | 21.47 | 6.73 |
| Light drinkers | 76 | 20.53 | 5.12 |
| Moderate drinkers | 212 | 20.92 | 5.54 |
| Heavy drinkers | 54 | 21.02 | 5.44 |
| Total | 393 | 20.93 | 5.60 |
| Empathic concern | |||
| Abstainers | 51 | 26.80 | 4.98 |
| Light drinkers | 76 | 26.39 | 4.12 |
| Moderate drinkers | 212 | 26.95 | 4.16 |
| Heavy drinkers | 54 | 25.28 | 5.63 |
| Total | 393 | 26.60 | 4.51 |
| Personal distress | |||
| Abstainers | 51 | 17.57 | 5.54 |
| Light drinkers | 76 | 16.13 | 4.78 |
| Moderate drinkers | 212 | 16.24 | 5.10 |
| Heavy drinkers | 54 | 17.65 | 5.31 |
| Total | 393 | 16.58 | 5.15 |
The cognitive-affective variables that presented a significant relationship both with AUDIT's total scoring and with violence were: working memory (r=−.115 and −.288), inhibition (r=−.259 and −367), cognitive flexibility (r=−.124 and −.126) and perspective taking (r=−.173 and −.175). Among them, inhibition was the one that showed the strongest relationship with the AUDIT scoring and with the scoring in the violence scale. In turn, the EF dimension that showed a stronger relationship with perspective taking was Cognitive flexibility (r=.409). The complete correlations and their levels of significance are shown in Table 3.
Correlations.
| AUDIT | Aggression scale | Working memory | Inhibition | Cognitive flexibility | Perspective taking | Fantasy | Empathic concern | Personal distress | RME | |
|---|---|---|---|---|---|---|---|---|---|---|
| AUDITa | ||||||||||
| r | 1 | .118* | −.115* | −.259** | −.124* | −.173** | −.007 | −.151** | .038 | −.076 |
| p | .020 | .022 | .000 | .014 | .001 | .893 | .003 | .455 | .133 | |
| Aggression scale | ||||||||||
| r | 1 | −.288** | −.367** | −.126* | −.155** | .172** | −.087 | .140** | −.045 | |
| p | .000 | .000 | .012 | .002 | .001 | .085 | .005 | .371 | ||
| Working memoryb | ||||||||||
| r | 1 | .602** | .437** | .154** | −.181** | .071 | −.410** | .074 | ||
| p | .000 | .000 | .002 | .000 | .159 | .000 | .143 | |||
| Inhibitionb | ||||||||||
| r | 1 | .185** | .115* | −.163** | .131** | −.195** | .133** | |||
| p | .000 | .022 | .001 | .009 | .000 | .008 | ||||
| Cognitive flexibility | ||||||||||
| r | 1 | .409** | .001 | .239** | −.405** | .133** | ||||
| p | .000 | .985 | .000 | .000 | .008 | |||||
| Perspective taking | ||||||||||
| r | 1 | .255** | .462** | −.081 | .082 | |||||
| p | .000 | .000 | .107 | .106 | ||||||
| Fantasy | ||||||||||
| r | 1 | .353** | .321** | .071 | ||||||
| p | .000 | .000 | .161 | |||||||
| Empathic concern | ||||||||||
| r | 1 | .040 | .106* | |||||||
| p | .431 | .035 | ||||||||
| Personal distress | ||||||||||
| r | 1 | −.073 | ||||||||
| p | .151 | |||||||||
| RMEc | ||||||||||
| r | 1 | |||||||||
| p | ||||||||||
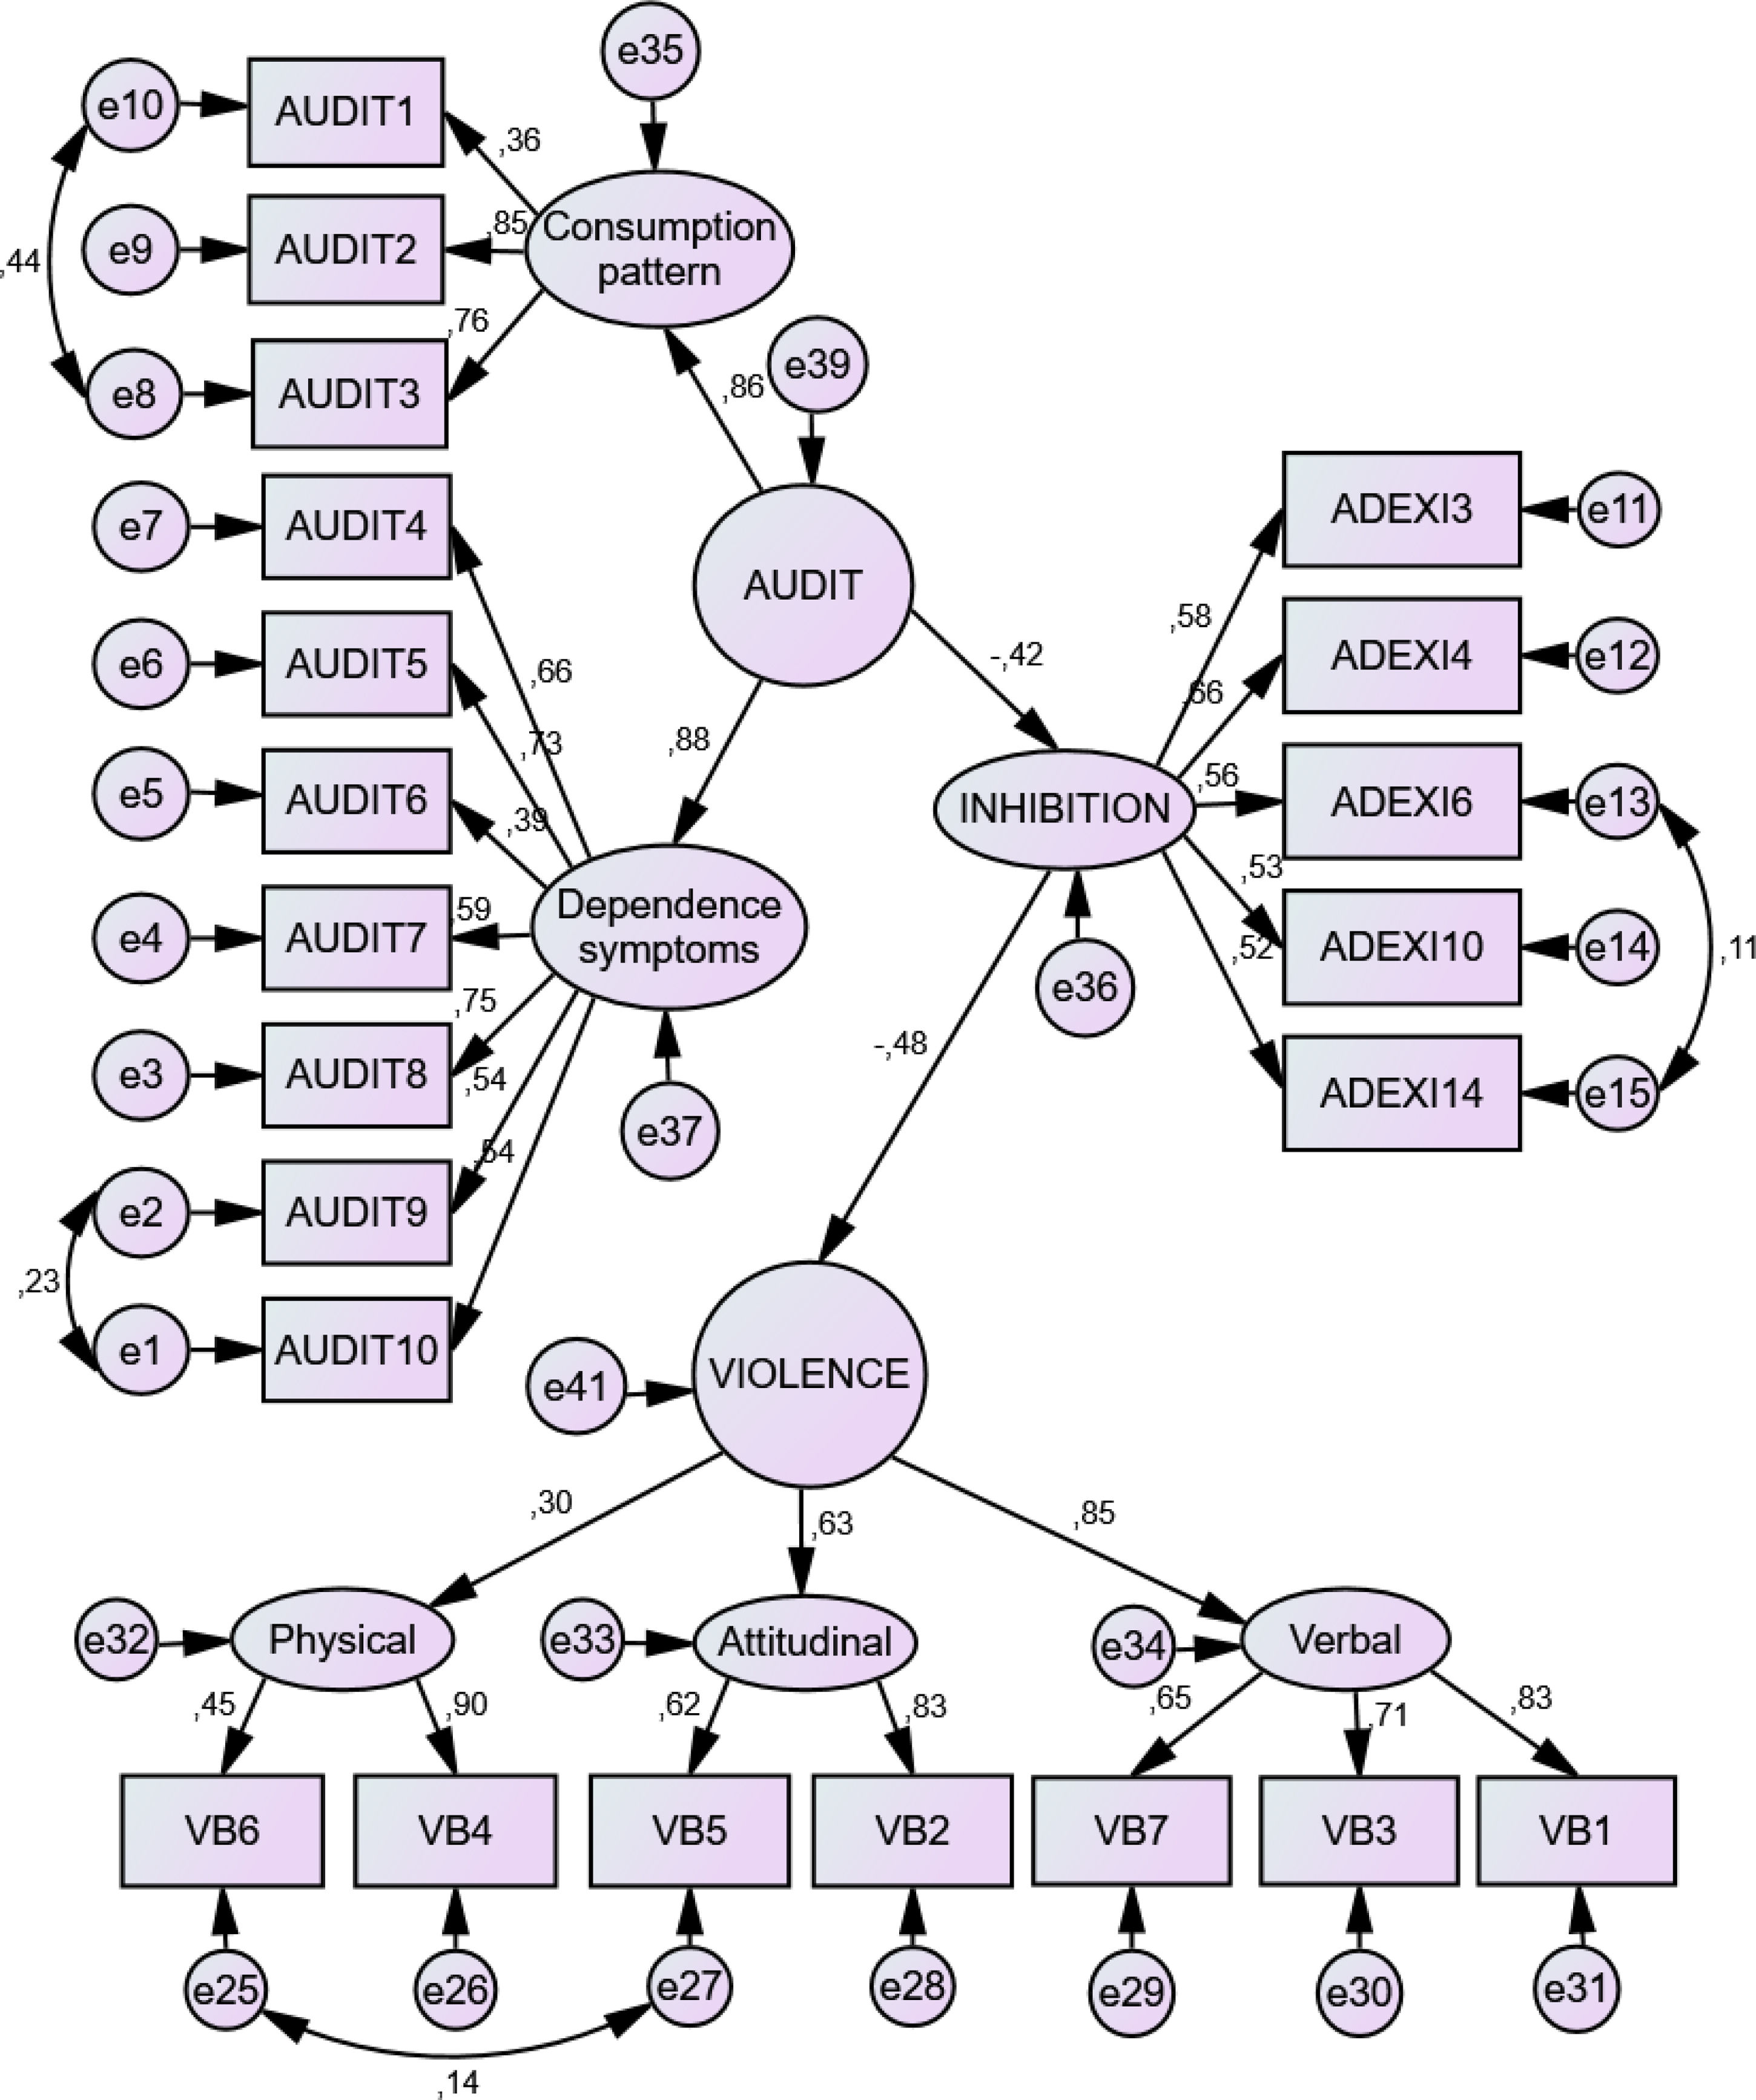
According to these correlations, 5 structural equation models were tested: (1) EF (working memory, inhibition and cognitive flexibility) mediates the relationship between alcohol consumption and violence; (2) perspective taking mediates the relationship between alcohol consumption and violence; (3) EFs and perspective taking mediate the relationship between alcohol consumption and violence; (4) cognitive flexibility and perspective taking mediate the relationship between alcohol consumption and violence; and (5) inhibition mediates the relationship between alcohol consumption and violence. Models 2 and 5 showed the best fit, but model 2 did not explain violence linked to consumption in a significant way. In model 2 the relationship between PT and violence was of −.12, while the relationship between INH and violence in Model 5 was of −.48 (see Fig. 1). The indexes of fit of all the studied models are shown in Table 4.

Model 5: alcohol consumption – inhibition – violence. References: Observable variables are items from the tests. The AUDIT test is presented in a two-factor model, in line with previous evidence regarding its factorial structure. The INHIBITION factor corresponds to that dimension of the ADEXI Inventory. The VIOLENCE factor corresponds to Aggression Scale scores, which are presented in a three-dimensional model, where items are grouped according to the type of violent behavior they involve (i.e., Physical, Attitudinal, and Verbal).
Comparison of explanatory models of the relationship between alcohol consumption and violence.
| Models | CMIN/DF | NFI | RFI | IFI | TLI | CFI | AIC | PCLOSE | RMSEA |
|---|---|---|---|---|---|---|---|---|---|
| 1 | 2.008 | .736 | .718 | .847 | .835 | .846 | 1984.867 | .364 | .051 |
| 2 | 1.850 | .844 | .822 | .922 | .910 | .921 | 611.587 | .796 | .047 |
| 3 | 2.014 | .693 | .676 | .818 | .805 | .816 | 2666.789 | .312 | .051 |
| 4 | 1.958 | .760 | .740 | .866 | .853 | .864 | 1379.804 | .579 | .049 |
| 5 | 1.890 | .856 | .832 | .927 | .913 | .926 | 528.168 | .693 | .048 |
The aim of this study was to contribute to the analysis of the cognitive-affective profiles that modulates the relationship between alcohol consumption and violence in a non-clinical population. To achieve this, cognitive-affective profiles of adults were described based on their typical alcohol consumption patterns, and explanatory models of the relationship between alcohol consumption and violence were explored. We identified significant differences in cognitive performance between the heavy drinkers and other drinker groups. In the explanatory models, inhibition played a fundamental role in modulating the relationship between alcohol consumption and violence.
The participants in this study reported high levels of alcohol consumption, particularly in terms of prevalence, but also regarding the frequency and the reported amount of usual consumption, in comparison to local, American, and European reports.89–94 As far as the cognitive-affective profiles of the participants according to their usual alcohol consumption are concerned, significant differences were found among the groups of drinkers regarding their performance in working memory (WM), inhibition (INH) and perspective taking (PT). In regards to this, it is important to highlight that the differences in these cognitive functions were not found among the groups of abstainers, light and moderate drinkers, but among these three groups and the group of heavy drinkers. In the mentioned functions, heavy drinkers showed an average cognitive performance that was significantly lower than that of the abstainers, light and moderate drinkers. These results suggest that alcohol consumption must be high in order for cognitive functions to be affected, and/or that deterioration in those functions is associated with heavy and problematic alcohol consumption, but not with light or moderate levels of consumption. In accordance with these results, previous studies have consistently signaled an impact on inhibition33–37 and on working memory, particularly verbal and auditory WM,27–29 during acute alcohol intoxication. Although previous studies on non-clinical population or on social drinkers are scarce, a study comparing the performance of heavy and light drinkers in EFs reported worse performance among heavy drinkers, particularly in measures of inhibitory control.50 Convergently, it has been established that the deficit in the EF, and particularly in inhibitory control, constitutes a risk factor for the development of alcohol use disorders (AUD).26
Regarding perspective taking, it is one of the cognitive dimensions of empathy. A number of studies have pointed out that the scores of alcoholic patients in cognitive aspects of empathy, such as the Theory of Mind and the mentalizing skills, are lower than in healthy controls.19 However, we did not find background information on the analysis of the relationship between the specific construct perspective taking and alcohol consumption.
In order to analyze this relationship, one should bear in mind that perspective taking is the dimension of empathy that has been more consistently linked to the EF, particularly to the dimension of cognitive flexibility,53,55 and that in this work both functions were found to be strongly related to each other (r=.409). Although cognitive flexibility has been less studied than other dimensions of the EF in relationship to alcohol consumption,26 some studies have pointed an affectation of said dimension during alcoholic intoxication38,39 and also in social drinkers with heavy consumption.50 In this study we did not find any significant relationships between cognitive flexibility and the patterns of alcohol consumption. This could be attributed, as has been previously suggested, to differences in the assessment measures of the construct.26,50 However, according to our results, the aspects of cognitive flexibility that are relevant to understand someone else's perspective could indeed be affected by heavy alcohol consumption.
When comprehensively judging the cognitive-affective profile linked to alcohol consumption patterns, it seems relevant that all the dimensions giving evidence of a relationship with consumption patterns are cognitive dimensions, controlled processes or processes dependent on higher-order cognitive functions; and not affective and/or automatic processes, such as emotional mirroring or the ability to recognize emotions in faces. Regarding empathy, this relationship being limited to one dimension of the construct does not seem surprising, taking into account that although the cognitive and affective components of empathy are complementary in normal functioning, evidence points out that they are dissociated processes from a functional55 and neurobiological point of view.10,95 On the other hand, although at first these results could seem contradictory when compared with those of previous studies, which have signaled difficulties in the recognition of emotional expressions and their intensity linked to alcohol consumption, it must be taken into consideration that all previously cited studies regarding this have been conducted in alcoholic patients.13,15–18 Taking these background information and the results of this study into account, the deficit in the recognition of emotions linked to alcohol consumption might not be a premorbid characteristic associated to the onset of AUD, but in a specific way, a consequence of the progressive neurological deterioration, due to strong and sustained consumption. In this line, studies have highlighted the unique vulnerability of the prefrontal cortex to the toxic effects of alcohol and the intervention of the orbitofrontal cortex in the processing of affective stimuli.16 Therefore, the results of some studies indicate an implication of the frontal and subcortical areas of both brain hemispheres at the base of the difficulties alcoholic patients present when identifying emotions.17
Lastly, regarding the mediating function of empathy, EF, and their dimensions in the relationship between alcohol consumption and violence, different explanatory models were tested, introducing as possible mediating variables those which showed a significant relationship both with violent behavior and with alcohol consumption and alcohol consumption problems: working memory, inhibition, cognitive flexibility, and perspective taking. Among the 5 studied models, those which showed better fit were: (a) perspective taking mediates the relationship between alcohol consumption and violence, and; (b) inhibition mediates the relationship between alcohol consumption and violence. Comparing those two models, perspective taking as mediating variable showed lower relationship with alcohol consumption and alcohol consumption problems, as well as lower ability to explain violent behavior linked to alcohol consumption, in comparison to inhibition.
From these analyses, and in line with the literature regarding both the relationship between inhibition, alcohol consumption and alcoholism,26,50 as well as between inhibition and violence,96 it could be concluded that inhibitory control is the variable that best explains the relationship between alcohol consumption and violent behavior. According to our results, this relationship is evident in a non-clinical population of social drinkers, indicating a link between the variables that goes beyond the moment of acute intoxication, and that has relative independence from the more severe neuro-cognitive deterioration produced as a result of the development of an AUD.
In conclusion, based on the analyses conducted in this study, it is evident that deficit in cognitive functions, particularly in the inhibitory response, constitutes a key factor in understanding alcohol consumption related violence and, more broadly, social problems among individuals who use alcohol. Given the strength of these relationships, the non-clinical nature of the population under study, and that the relationships have not been studied during acute alcohol intoxication, it could be hypothesized that the role of inhibition can be both as a mediator in the relationship between alcohol consumption and violence, as well as a modulator of violence linked to consumption.
As a premorbid condition, as suggested in previous studies, difficulties in EF could lead to an increase of alcohol consumption and to AUD.26 The hypothesis of the deficit arising as a consequence of consumption, on the other hand, is not necessarily an alternative to the former. The neurotoxic effect of alcohol may also contribute to the progressive deterioration of cognitive functions, deepening deficits in social skills and overall functioning, which could lead to even higher consumption as a means to compensate those deficits, and giving place to a vicious circle.74
Before concluding, we wish to point out a few particularities of the relationships among the variables under study. Within the range of violent behaviors that were assessed, both SEM (model 2 and 5) explained verbal and attitudinal violence to a greater extent than physical violence. This phenomenon could be attributed to the fact that, in general non-clinical population, this type of violence may be less prevalent. Notably, alcohol use disorders (i.e. AUDIT's items of dependency) exhibit the strongest relationship with physical violence. This suggests that deficit in higher-order cognitive functions and socio-emotional problems linked to AUD may play a crucial role in physical violence.
Another interesting aspect about the relationships that were found is the positive and significant, though weak, association between the Personal Distress dimension of empathy and violent behavior. It appears that experiencing distress when confronted with another person's distress, far from preventing violence, could actually contribute to it. This relationship may be explained considering that this type of emotional experience implies a certain level of cognitive deregulation, manifesting as a difficulty in establishing cognitive distance between oneself and others. This distance is crucial for recognizing one's own identity separate from others, even while understanding their pain or sadness. In line with this, an inverse and significant relationship between Personal Distress and all the dimensions of EF can be observed.
Finally, this study presents a number of limitations that could be addressed in future studies on the topic. As previously mentioned, the revisions and the meta-analyses of partial aspects of the relationships studied here, particularly those concerning the relationship between EF and alcohol consumption, have highlighted the difficulties linked to the variety of existing assessment instruments when comparing results and weighing the effects of variables. In this study, self-report instruments have been used to assess EF, empathy and violence. In this sense, it would be beneficial to replicate the study combining behavioral measures and/or objective indicators with self-report measures. In addition, it's important to note that the sampling method was intentional, which limits the generalizability of the results.
Despite the limitations mentioned, this study makes a relevant contribution to the study of alcohol-related violence, shedding light on a critical nexus between alcohol consumption and violent behavior among social drinkers. It emphasizes the pivotal role of cognitive and social cognition factors, including EF and perspective taking. The findings underscore that deficits in cognitive functions, particularly inhibitory responses, are fundamental drivers of alcohol-related violence and broader social conflicts in individuals who consume alcohol. Understanding these dynamics has significant implications for the development of targeted interventions and prevention strategies aimed at mitigating the social repercussions of alcohol use. By recognizing the profile that mediates or modulates the alcohol-violence relationship, we gain valuable insights into how cognitive and emotional factors contribute to and can potentially alleviate the consequences of alcohol-related aggression, ultimately promoting safer and more informed alcohol use in social drinkers. This knowledge could serve to the development of prevention strategies in non-clinical environments, such as educational institutions or community programs.
FundingThis research was funded by the Consejo Nacional de Investigaciones Científicas y Técnicas (CONICET) and the Universidad Adventista del Plata (UAP).
Conflict of interestThe authors have no conflicts of interest to declare.



