





Currently, in intensive care units (ICUs), the in-hospital transport (HIT) of patients is carried out without a unified criterion of personnel necessary for it.
ObjectiveTo evaluate the concordance of the Patient Assessment System for Transport-ICU (PAST-ICU) with the medical criteria (CM) to determine the Human Resources (HR) and identify Adverse Effects (AE).
MethodsDescriptive, cross-sectional and prospective study of the IHT of patients admitted to an area of adult medical-surgical critical patients. The PAST-ICU instrument was created to recommend the HR of HIT. Through the assessment of clinical parameters, the Past-ICU indicates whether the HIT should be performed with (1) a stretcher-bearer (2) Stretcher-bearer/nurse or (3) stretcher-bearer/nurse/doctor. AE were recorded during the hospital transfer. Prior to the IHT, the nurse performed the PAST-ICU and the result was contrasted with the Medical Criteria (MC) responsible for the patient, the latter prevailing.
Study periodPhase 1: pilot test 2013–2014. Phase 2: 2015–2021.
VariablesReason and duration HIT, PAST-ICU sheet, checklist, AE.
ResultsPhase 1: 458 IHT were analyzed. The concordance index between the PAST-ICU and the MC was 84,9% (389 IHT). The Cohen Kappa of 58,5% and p < 0,001. There were a total of 16 AE. Phase 2: 3423 IHT. The Concordance index of 87,2% (2984 TIH). The Cohen Kappa of 63%and the P < 0,001. Registered 49 AE.
ConclusionThe PAST-ICU could be a useful, safe and reliable tool to adapt the necessary HR. There was good concordance between the PAST-ICU vs the MC to determine the HR in the HIT. The percentage of AE was low.
Actualmente en las unidades de cuidados intensivos (UCI), el transporte intrahospitalario (TIH) de los pacientes, se realiza sin un criterio unificado de personal necesario para el mismo.
ObjetivoEvaluar la concordancia del Sistema de Valoración para el Transporte de UCI (SVPT-UCI) con el criterio médico (CM) para determinar el Recurso Humano (RH) en el traslado intrahospitalario. Identificar los Efectos Adversos (EA).
MétodoEstudio descriptivo, transversal y prospectivo de los TIH de los pacientes de un área de críticos médico-quirúrgica de adultos. Se creó el instrumento SVPT-UCI para recomendar el RH óptimo del TIH. Mediante valoración de parámetros clínicos el SVPT-UCI indica si el TIH debe efectuarse con: camillero o camillero/enfermera o camillero/enfermera/médico. Previamente al TIH la enfermera cumplimentó el SVPT-UCI contrastándose el resultado con el criterio médico (CM), prevaleciendo éste último.
Período de estudioFase 1: prueba piloto 2013-2014. Fase 2: 2015-2021.
VariablesMotivo y duración TIH, documento SVPT-UCI, listado de verificación, efectos adversos (EA).
ResultadosFase 1: 485 TIH incluidos. Índice de concordancia entre SVPT-UCI y CM del 84,9% (389 TIH). Se obtuvo una Kappa de Cohen del 58,5% y una p < 0,001. Registrados 16 EA. Fase2: 3423 TIH incluidos. Índice de concordancia de 87,2% (2984 TIH). Se obtuvo una Kappa de Cohen del 63% y una p < 0,001. Registrados 49 EA.
ConclusiónEl SVPT-UCI podría ser una herramienta útil, segura y fiable para adecuar el RH necesario. Hubo una buena concordancia entre el SVPT-UCI vs el CM para determinar el RH en el TIH. El porcentaje de EA fue bajo.
What is known?
Despite major technological advances leading to many complementary and/or diagnostic tests being performed within the ICU unit itself, the IHT of patients outside the unit is still necessary. Caring for patients in an IHT is a potentially risk-filled activity where the same safety measures as those in the ICU cubicle must be maintained throughout the transfer, avoiding AEs.
This study provides the use of a system for assessing patients admitted to the ICU to determine the optimum and necessary human resources in the IHT required to guarantee safety and quality of care.
Study implications
The use of an objective assessment system that safely and reliably determines the appropriate HR in the IHT will help optimise HR and reduce disparity in resource composition, leading to greater efficiency and effectiveness.
In recent years technological advances have led to high autonomy at work in intensive care units (UCI). However, several technologies with both diagnostic and therapeutic ends continue to exist which cannot be transferred to the patient’s bedside, thereby making intrahospital transport (IHT) of the patient essential.
The risk of complications, which may become adverse events (AE) are inherent in IHT, and on occasions may lead to severe consequences.1–5 Numerous publications provide recommendations aimed at reducing the AE during IH, referring to guidelines to safely carry out the transfer, including thorough preparation of the patient, review of the equipment, training of the personnel who must accompany the patient and standardised care systems.6–10
Focusing on the human resources (HR) which must accompany the patient we were unable to find in the literature consulted any specific and objective system to determine optimum HR. Studies contain variations, with no specificity being found in the composition of the personnel of the appropriate IHT team. Thus, we found that, in some hospitals in the United States, such as the one in Maryland, IHT is performed by specialised teams.9,11,12 Some authors mention the use of risk assessment scales for IHT of critically ill patients which establish a transport risk assessment, but they do not determine the HR who should accompany the patient during the transfer.13–15
Furthermore, protocols exist where the terms used for HR assignment are vague. They generically determine that the appropriate personnel and material are available based on the clinical situation of each patient for each transport, or even assigning the HR based on a series of items that do not always precisely correlate with the care the patient requires. There is even variability in the said studies regarding the said ítems.16–18
In the pre-hospital setting, more highly defined references on the specification of the transport team composition are available. In contrast, in the post-hospital setting, the composition of the transport teams is better specified. There are guidelines and protocols with recommendations for the provision of emergency health care with different territorial organisational models, together with documents defining the assignment of the necessary measures for applying medical emergency codes.19–23
Continuing with the prehospital setting, our study is based on the research by Moreno Millán.24–26 This in turn is based on the studies by Ehrenwerth et al.27 and Bion et al.14 who examined the risks involved in the transfer of patients in the interhospital setting and created a Patient Assessment System based on the need for support for Healthcare Transport. (PAST). After being validated by the author himself14,24 and then by Markakis et al.28 the system was applied in Europe and in some autonomous communities of Spain.29
Given the usefulness and validity of the PAST in interhospital transport,24,25 we consider it a safe tool to objectively determine the HR in the IHT of the patient admitted to an ICU as efficiently and effectively as the intensive care physicians could.
The main objective of the study was to evaluate the concordance of the Patient Assessment System for Intra-hospital Transport in the intensive care unit (PAST-ICU) with the standard model used called “medical criteria” (CM) to determine the HR in the IHT. The secondary objective was to determine the adverse events (AEs) related to this procedure.
MethodA descriptive, cross-sectional and prospective study conducted in a critically ill adult patient unit. The area had 16 ICU beds and 14 semi-critical beds. The nurse/patient ratio is 1:2 in the ICU and 1/5 in semi-critical patients.
The “medical criteria” (MC) was defined as the traditional model where the only criteria was that of the doctor, and the current model as the one in which the use of the PAST-ICU was added (implemented since 2015).
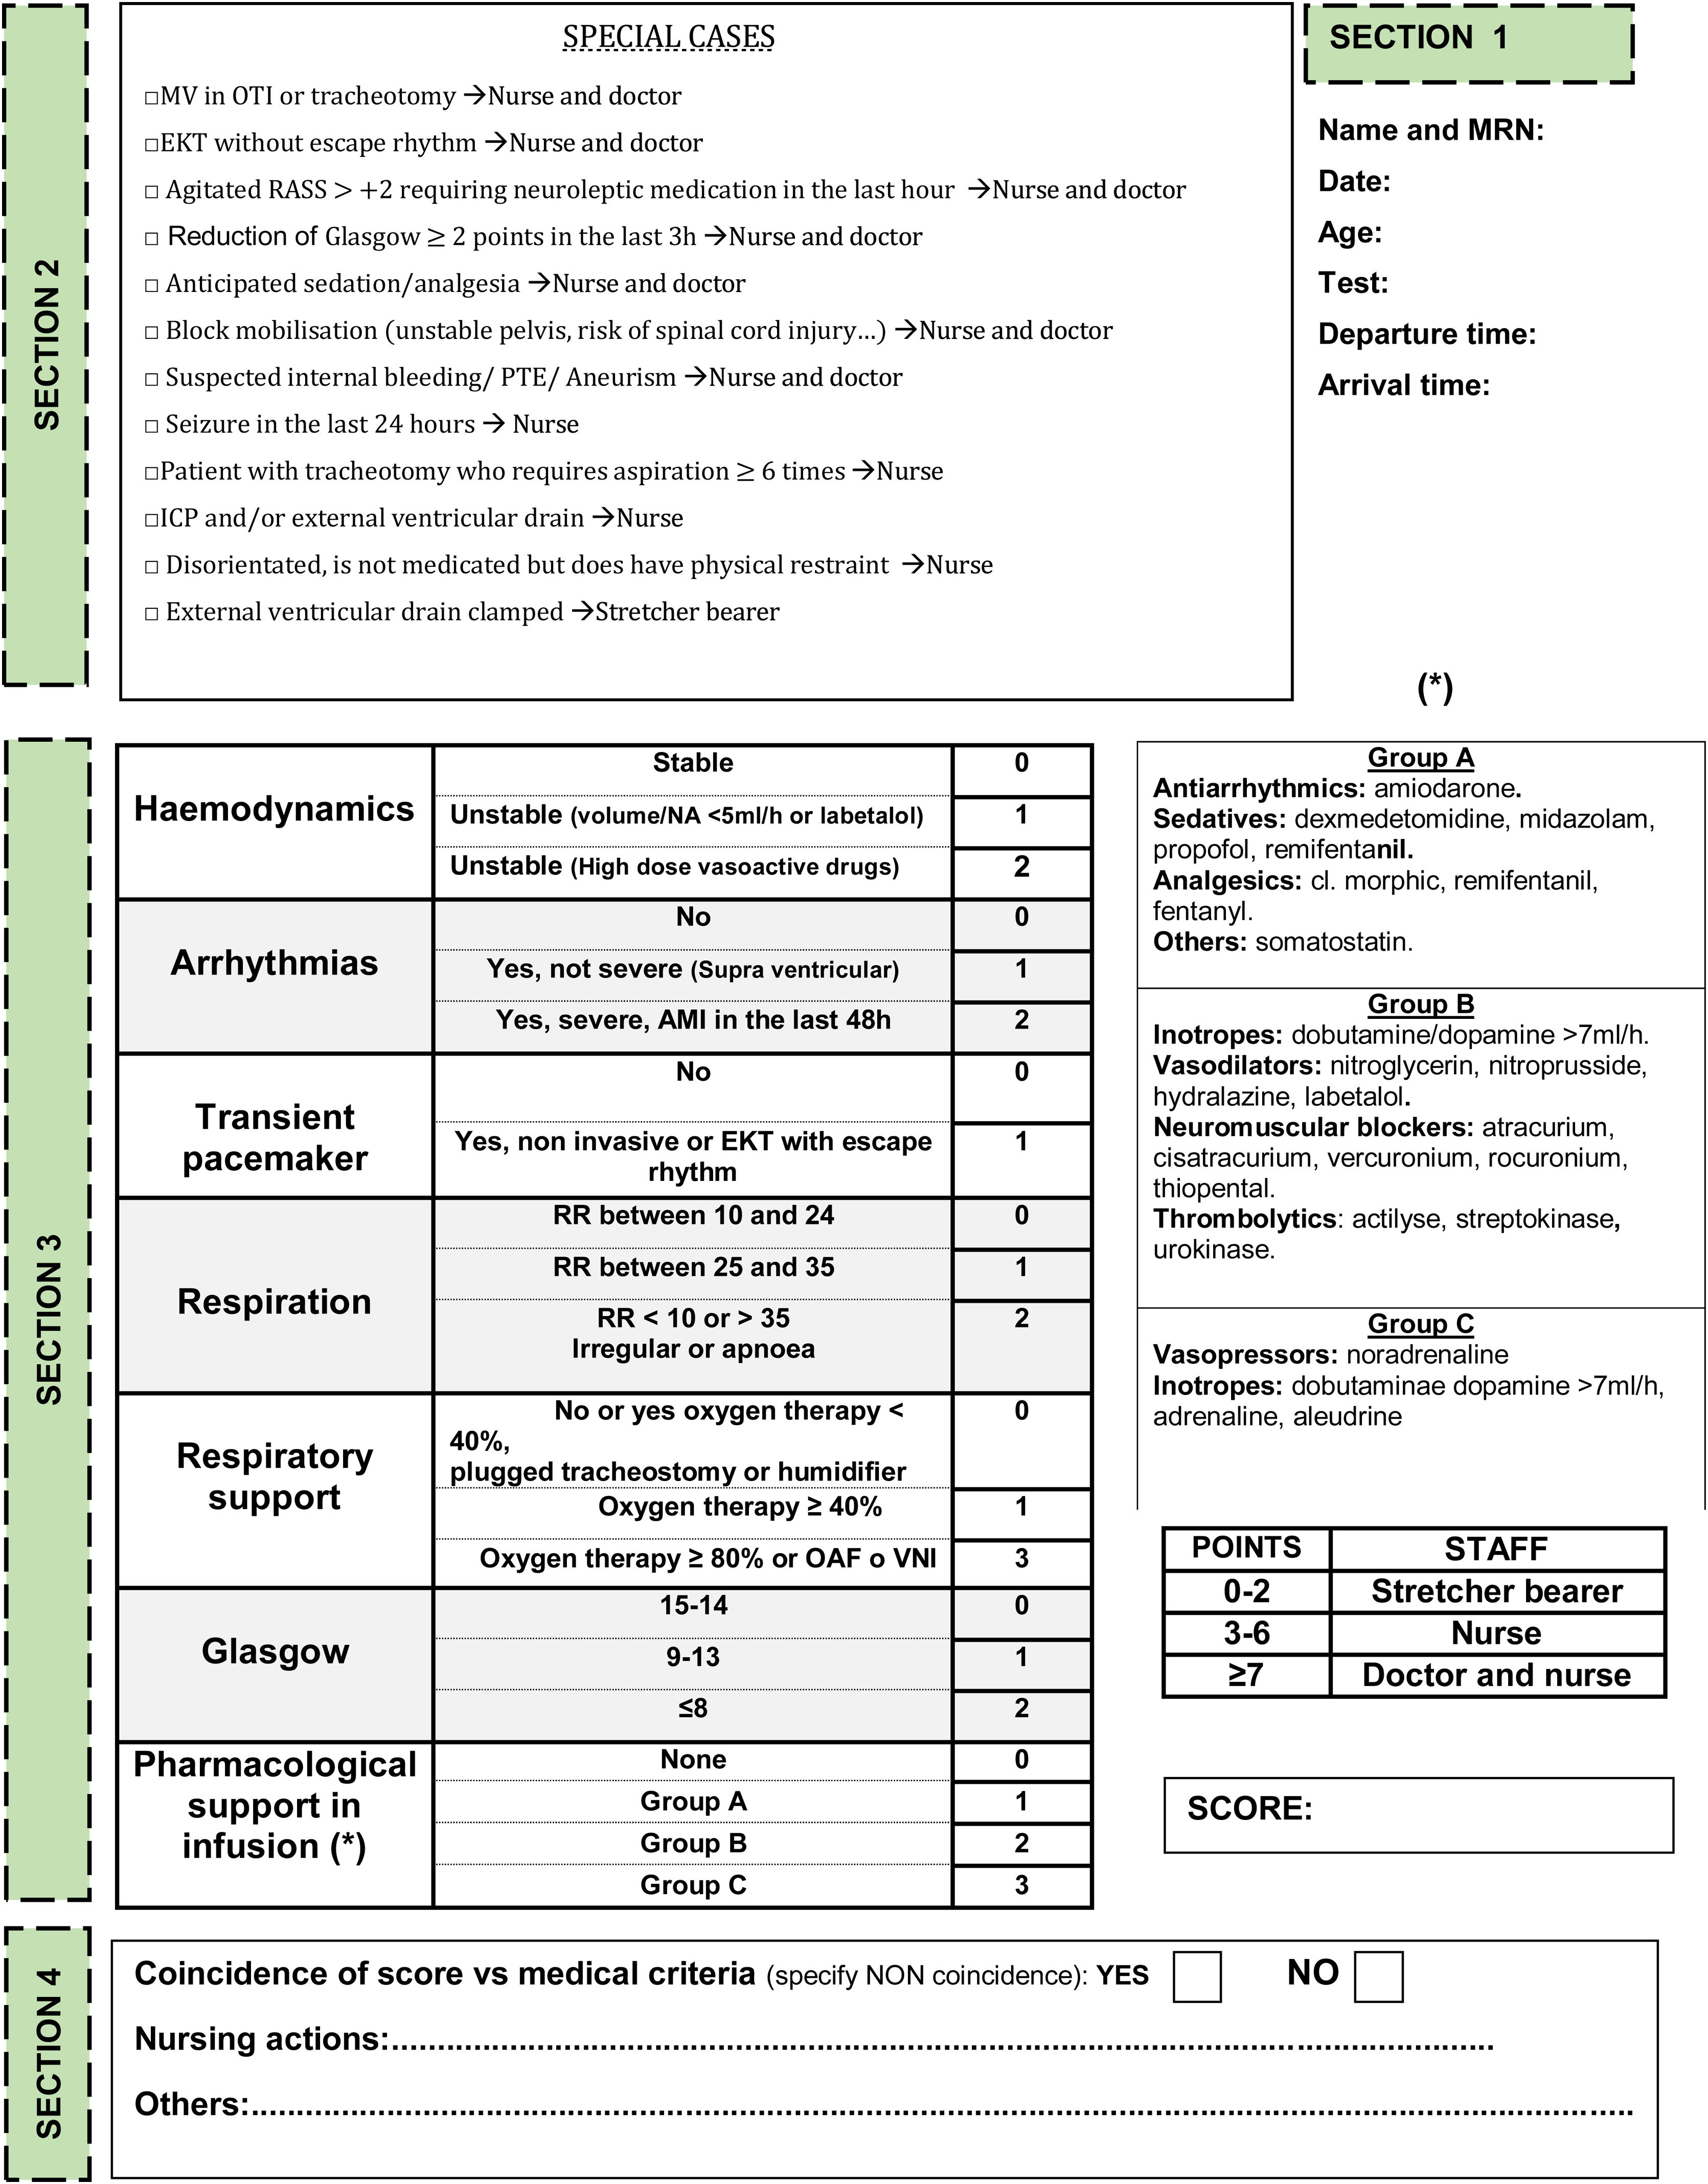
To assess the complexity of patients admitted to intensive care, and the risk attached to each IHT, the PAST-ICU was developed (Fig. 1). This PAST-ICU is based on the original PAST24 scale that was adapted with the inclusion of the clinical situations and specificities of our units (ICU and semi-critical patients).

The PAST-ICU consists of four sections:
Section 1: Contains general transfer data including the patient’s name and medical record number, the reason for transport, and the time of departure and arrival at the unit.
Section 2: Includes cases designated as special (SC) where the recommended HR is pre-established. This was defined and agreed upon with the multidisciplinary work group formed by the research nurses and an intensive care doctor.
Section 3: Is only completed if it is not a SC (section 2). It consists of 7 assessment items (haemodynamics, arrhythmias, temporary pacemaker, respiration, respiratory support, Glasgow and pharmacological support in infusion). In this case, the score obtained with the different items determines the HR necessary for that transfer: stretcher bearer (0–2 points), stretcher bearer and nurse (3–6 points), stretcher bearer, nurse, doctor (≥7 points).
Section 4: Is for the recording of actions carried out during the transport (aspiration of endotracheal secretions, administration of medication, etc.) and incidents not specified in the checklist. It also includes a section for recording the coincidence, or no-coincidence between the HR assigned by the PAST-ICU and the medical criteria.
On the back of the PAST-ICU document is the checklist, which details the actions to be carried out prior to the transport and the AEs that may occur during the procedure (Fig. 2).

Prior to PAST-ICU implementation, information sessions were held for the healthcare team involved. These sessions were taught by nurses from the research team and an intensive care physician.
The study was carried out in two phases:
Phase 1: Pilot study (2013–2014). Implementation of the PAST-ICU document.
To calculate the sample for this pilot study, a minimum of 322 transfers were included to estimate a concordance equal to or greater than 95% with a precision of 2% and a confidence level of 95%.
Phase 2: (2015–2021). PAST-ICU implementation, including the modifications assessed in phase-1. Initially, uncontemplated corrective factors were empirically introduced into the score (such as arrhythmias due to acute myocardial infarction in the last 48 hours, use of high-flow oxygenation, reduction of Glasgow by 2 points, etc.).
Inclusion criteriaAll IHT initiated and completed in the critical care unit (ICU/semi-critical patients).
Exclusion criteriaIHT called special cases (SC), and IHT with the PAST-ICU registration document incorrectly completed.
VariablesSociodemographic data of the patient, reason for IHT, time during which the patient was outside the unit, outcome obtained through the PAST-ICU, items from the IHT checklist, MC regarding the HR required for the transport and AEs that occurred during the procedure.
Data collectionThe nurse responsible for the patient prior to the transfer had to complete the PAST-ICU document and the IHT checklist. The result obtained (optimum HR) was contrasted with the MC, the latter being the one that prevailed.
Serious AEs were defined according to safety indicator number 98 published by the SEMICYUC30 (“Serious AE: including at least: death, recovered cardiac arrest, accidental extubation, accidental removal of catheters, lines, drains and tubes, interruption of oxygen supply, falls”) and situations that required intervention.
The research team was responsible for data collection and recording.
Data analysisFor qualitative variables, the frequencies and proportions of each category were determined, and are presented in tables and graphs for better data visualisation. The level of agreement between the PAST-ICU scores and the MC was evaluated with the concordance index and Cohen’s kappa.
Ethical considerationsThe researchers did not participate in any clinical decisions and data confidentiality and patient anonymity were guaranteed through pseudo-anonymity with the assignment of a code for each IHT. The study was approved by the Clinical Research Ethics Committee, with reference number 2013605. The management of medical records was carried out in accordance with Organic Law 7/2021 on personal data protection. The study was conducted in accordance with the Declaration of Helsinki.
ResultsA total of 7,421 IHTs were registered between both phases of the study (2013–2021). Three thousand five hundred and forty IHTs were rejected because they belonged to the group of special cases (3,180) or because registration of the PAST-ICU document was not complied with (360).
The reasons for IHT were: computed axial tomography (4417), magnetic resonance imaging (609), interventional radiology (1477), surgery (639), ultrasound (179) and others (150). The discrepancy between the number of tests (7471) and IHT (7421) is due to the fact that more than one test was carried out in the same IHT.
The average time per transport was 47.7 min (minimum time of 33.4 min and maximum time of 89.7 min).
Phase 1: (2013–2014). The total sample of the pilot test was 996 IHT, of which 458 met the inclusion criteria and 538 were excluded (499 for being SC and 39 for incomplete registration).
Of the 458 IHT included in the study, 334 were performed by the stretcher bearer (72.9%), 51 by the stretcher bearer and nurse (11.1%) and 73 by the entire team (stretcher bearer, nurse and doctor) (15.9%).
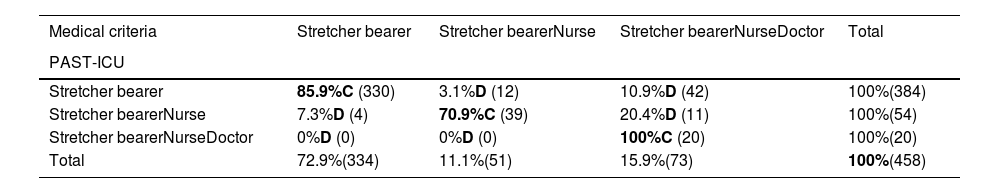
Table 1 shows the results regarding the coincidence/discrepancy in the HR assignment carried out using the PAST-ICU and the MC. A p < .001 was obtained, a concordance index between the two variables (MC and PAST-ICU) of 84.9% (389 IHT) and a Cohen’s kappa of 58.5%.
Coincidence/discrepancy in HR assignment by PAST-UCI and medical criteria [% (n)]. Pilot study (2013–2014).
| Medical criteria | Stretcher bearer | Stretcher bearerNurse | Stretcher bearerNurseDoctor | Total |
|---|---|---|---|---|
| PAST-ICU | ||||
| Stretcher bearer | 85.9%C (330) | 3.1%D (12) | 10.9%D (42) | 100%(384) |
| Stretcher bearerNurse | 7.3%D (4) | 70.9%C (39) | 20.4%D (11) | 100%(54) |
| Stretcher bearerNurseDoctor | 0%D (0) | 0%D (0) | 100%C (20) | 100%(20) |
| Total | 72.9%(334) | 11.1%(51) | 15.9%(73) | 100%(458) |
p < .001 TOTAL n: 458.
Concordance index (MC and PAST-ICU variables): 84,9% (389).
Cohen’s Kappa: 58,5%.
C: Coincidences; D: Divergence.
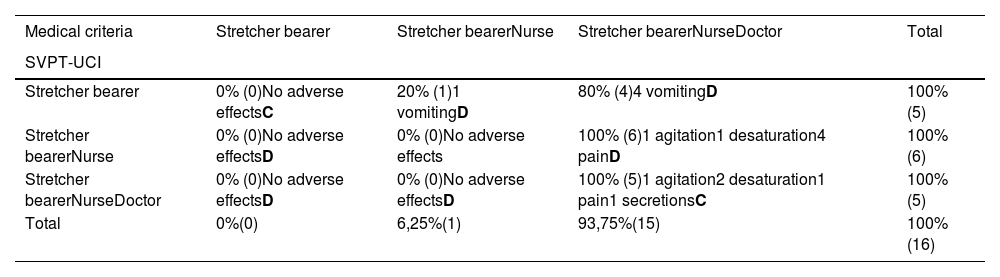
The AEs are described in Table 2, with no serious AEs recorded in the IHTs analysed.
Adverse effects recorded during the pilot study (2013–2014).
| Medical criteria | Stretcher bearer | Stretcher bearerNurse | Stretcher bearerNurseDoctor | Total |
|---|---|---|---|---|
| SVPT-UCI | ||||
| Stretcher bearer | 0% (0)No adverse effectsC | 20% (1)1 vomitingD | 80% (4)4 vomitingD | 100%(5) |
| Stretcher bearerNurse | 0% (0)No adverse effectsD | 0% (0)No adverse effects | 100% (6)1 agitation1 desaturation4 painD | 100%(6) |
| Stretcher bearerNurseDoctor | 0% (0)No adverse effectsD | 0% (0)No adverse effectsD | 100% (5)1 agitation2 desaturation1 pain1 secretionsC | 100%(5) |
| Total | 0%(0) | 6,25%(1) | 93,75%(15) | 100%(16) |
C: Coincidences; D: Divergencies.
Phase 2: (2015–2021) of a total of 6,425 IHT, 3,423 were included, with 3,002 being rejected (2,681 SC and 321 with incomplete registration).
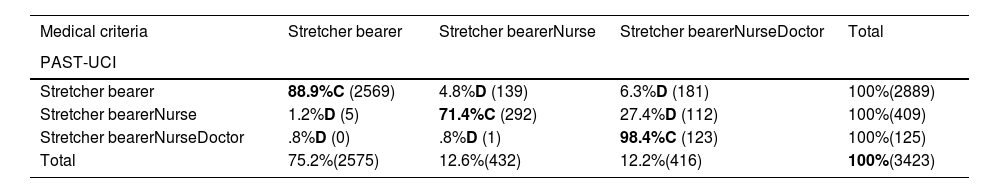
The comparison of coincidence/discrepancy in the assignment of HR between the PAST-ICU and MC is reflected in Table 3. A p < .001 was obtained, a concordance index between the two variables (MC and PAST-ICU) of 87, 2% (2984 IHT) and a Cohen’s kappa of 63%.
Coincidence/discrepancy in the assignment of HR by the PAST-UCI and the medical criteria [% (n)]. Study years 2015–2021.
| Medical criteria | Stretcher bearer | Stretcher bearerNurse | Stretcher bearerNurseDoctor | Total |
|---|---|---|---|---|
| PAST-UCI | ||||
| Stretcher bearer | 88.9%C (2569) | 4.8%D (139) | 6.3%D (181) | 100%(2889) |
| Stretcher bearerNurse | 1.2%D (5) | 71.4%C (292) | 27.4%D (112) | 100%(409) |
| Stretcher bearerNurseDoctor | .8%D (0) | .8%D (1) | 98.4%C (123) | 100%(125) |
| Total | 75.2%(2575) | 12.6%(432) | 12.2%(416) | 100%(3423) |
p < .001 TOTAL n: 3423.
Concordance index (MC and PAST-UCI variables): 87.2%.
Cohen’s Kappa: 63%.
C: Coincidences; D: Divergencies.
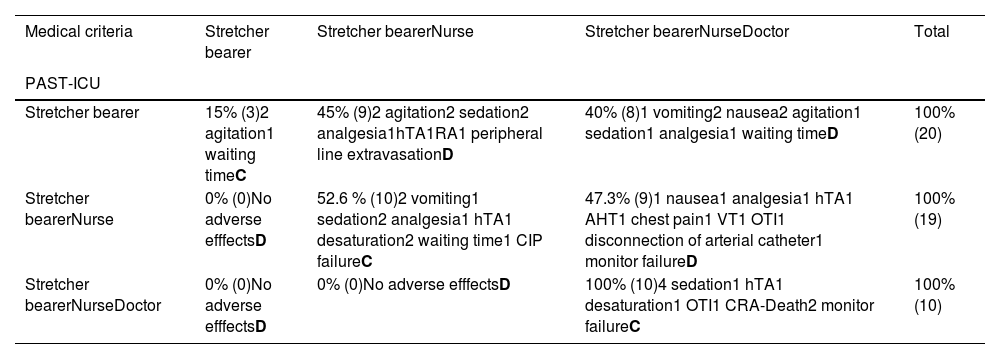
The 49 AEs recorded in this second phase are detailed in Table 4. Of the 439 IHTs (12.8%) where there was a discrepancy between the PAST-ICU and the MC, only 2 serious AEs were recorded, one respiratory arrest and one ventricular tachycardia.
Adverse effects recorded during the study years 2015–2021.
| Medical criteria | Stretcher bearer | Stretcher bearerNurse | Stretcher bearerNurseDoctor | Total |
|---|---|---|---|---|
| PAST-ICU | ||||
| Stretcher bearer | 15% (3)2 agitation1 waiting timeC | 45% (9)2 agitation2 sedation2 analgesia1hTA1RA1 peripheral line extravasationD | 40% (8)1 vomiting2 nausea2 agitation1 sedation1 analgesia1 waiting timeD | 100%(20) |
| Stretcher bearerNurse | 0% (0)No adverse efffectsD | 52.6 % (10)2 vomiting1 sedation2 analgesia1 hTA1 desaturation2 waiting time1 CIP failureC | 47.3% (9)1 nausea1 analgesia1 hTA1 AHT1 chest pain1 VT1 OTI1 disconnection of arterial catheter1 monitor failureD | 100%(19) |
| Stretcher bearerNurseDoctor | 0% (0)No adverse efffectsD | 0% (0)No adverse efffectsD | 100% (10)4 sedation1 hTA1 desaturation1 OTI1 CRA-Death2 monitor failureC | 100%(10) |
AHT: Arterialhypertension; CIP: Continuoue infusión pump; CRA: Cardio-Respiratory arrest; hTA: hypotension; OTI: Orotracheal intubation; RA: Respiratory arrest; VT: Ventricular tachycardia.
The main study finding was the good concordance obtained between the MC and the PAST-ICU to determine the HR necessary in IHT. This finding suggests that the PAST-ICU can stratify and identify patients who will require a higher or lower level of care during IHT and adjust the optimal HR based on this.
It is important to note that no other research has been found that specifically studies the allocation of HR in the intra-hospital setting through a patient assessment system, making it impossible to contrast the results in their entirety with analogous works. The study by Cardenete, C.29 addressed the optimisation of HR, taking into account the severity of the patient in the interhospital setting, and retrospectively applying Moreno Millán’s PAST.24 The results showed that 16.7% (66) of the transfers could have been carried out in a conventional ambulance with two medical transport technicians; 69.6% (275) in a conventional medically-equipped ambulance under the care of a nurse and 13.7% (54) in a mobile ICU under the supervision of a doctor and the care of a nurse, evidencing the allocation of more HR than necessary. We were able to establish a similarity or comparison in our study with the results of the study by Cardenete, C.29 Out of the total number of AEs in the cases in which there was a discrepancy between the MC and the PAST-ICU, the MC assigned a resource higher than that calculated by the PAST-ICU (14.1% and 11.4% in phase 1 and phase 2 respectively).
The randomised study conducted by Lieshout et al.31 compared nurse-led versus physician-led transfers in 298 patients, determining that AEs did not differ notably between the two groups (16.3% nurse-led group and 15.2% doctor-led group). However, the sample size was small to establish categorical inferiority.
Difference studies report a percentage of serious or clinically significant AEs of 1.7% to 16.8%4–5 which is higher than that obtained in our study, with a 3.5% of AEs recorded in the pilot study (phase 1) and 1.4% in the study period (phase 2). In the latter .02% of serious AEs (1 respiratory arrest and 1 cardio-respiratory arrest with death) were recorded. In the meta-analysis carried out by Murata et al.,32 we observed results closer to those of our study. Of the 12,313 IHT and 1,898 patients analysed in 24 studies, the incidence of life-threatening AEs was 0–1.5%, although the authors reported high diversity.
Veiga et al.33 reported 7.5% clinical events and 8.0% non-clinical events out of a total of 1559 IHTs with a mean transport time of 43 ± 34 min. In our study the average IHT time was 47.7 min. Although a longer duration of IHT is associated with an increase in the incidence of AEs,34 there are divergences on this point, since some authors did not find an association between AEs and transport time.35
In our study the registration of AEs was calculated on AEs freely declared by the professional responsible for the IHT, which may affect the number of AEs notified, due to omission or lack of registration.
An important aspect to also assess and that can support the implementation of a PAST-ICU is the clinical evolution of patients admitted to an ICU, which may change and which differs between patients. This means that throughout the care process, patients do not require the same type of support or the same intensity of care. This variability becomes evident when quantifying the severity of the patient's illness and the nursing workload. Thus, some authors report an average APACHE II score of 20 ± 7.3, with a minimum score of 4 and a maximum of 41.34 Regarding the estimation of the nurse’s workload, Fasoi et al.36 quantified the mean value of workload/patient, using the NAS (Nursing Activities Score) scale, with 54.8 points (±2.3) being the workload on the first day of admission to the ICU/patient of 65.1 (±13) with a minimum of 36.3 and a maximum of 89.8 points. These data are similar to those obtained by Valls et al.37 who reported a mean NAS score per patient of 62.5 (±16.8).
Likewise, there are patients in the ICU who cannot be discharged due to lack of beds on the ward, as stated in the study by Fernández38 which found that 4% of patients had a delayed discharge from the ICU due to lack of available beds on the ward.
Another factor to examine would be the impact the time spent in IHT has on nursing workload and the benefit of using PAST-ICU to reduce IHT time and workloads. According to Valls et al.,37 after the application of the NEMS workload assessment scales (Nine Equivalents of nursing Manpower use Score), NAS (Nursing Activities Score) and VACTE (Workload and Time Assessment Scale of Nursing), it became evident that there was a shortage of nurses in the ICUs. The Ministry of Health recommends one nurse for each patient in ICU level III care; 1:1.6 in ICU level II and 1:3 in ICU level I.39 In the majority of ICUs in our hospital setting the ratio is 1:2 and the nurse responsible for the patient to be transported is usually an integral member of the IHT care team. This entails leaving their other patient in the care of one of the remaining nurses on the unit, whose workload therefore increases.
Finally, if we compare interhospital transport with intrahospital transport, other relevant elements come into play when considering the possibility of establishing a PAST-ICU. This may be that it would be applied in a more controlled environment, the patient would be known and if necessary, medical help would be more quickly available.
LimitationsOne limitation of our study is that the level of experience of the doctor responsible for deciding the HR for the IHT (junior, senior intensive medicine specialist or internal resident doctor in training) as well as that of the nurse was not recorded. Given that decision-making in the context at hand was the responsibility of the doctor and the nurse, information could have been provided on the possible influence of professional experience in the ICU regarding the allocation of HR, with the consequent variability in the results.
Secondly, as this was a single-centre study, the results obtained can only be extrapolated to ICUs with similar characteristics and with the same nurse/patient ratio.
Also, possible errors/omissions when completing the PAST-ICU document may have led to under-registration of AEs.
Finally, the PAST-ICU has not been validated and the present study could be a starting point to carry out future research in providing solidity.
ConclusionOur results suggest that the PAST-ICU correctly determines the HR necessary for the IHT, which makes it a useful, safe and reliable tool to implement in critical areas with similar characteristics to the critical area studied, when implemented by trained professionals and serving a protocol that includes a checklist to prevent associated risks and possible AEs.
The incidence of AEs during IHT was low.
We believe that these data are important for future actions, in relation to the creation and implementation of IHT protocols that guarantee safe care for ICU patients with optimum technical and human resources.
Future multicentre studies are required for a broader assessment of PAST-ICU and in the different patient subgroups.
FundingThis study was funded in “14th Edition of the Taulí Grants for Research and Innovation of the Corporación de la Salud Parc TaulÍ”, Sabadell (Barcelona) (CIR: 2012/059).
The authors would like to thank Dr Jaume Mesquida Febrer, assistant physician of the intensive care area of Parc Taulí University Hospital for his help and collaboration in guiding different areas of this study. Our thanks to Óscar Hernández Vian, a nurse from the department of primary care methodologgy activity, quality and assessment for his contribution at the start of the study and to Esther Jové Ponseti, a nurse from the Parc Taulí Intensive Care Unit for her invaluable aid and unconditional support. Our thanks to Pedro Pidal Tonsaker for helping us with the translation. Also to Santi Fuster Foz for his help in text revision. Also to Joan Carles Oliva Morera from the Parc Taulí University Hospital department of statistics for his support with the statistical analysis.
The following are Supplementary data to this article:




