



Thanks to biochemical engineering, the glucagon-like peptide-1 (GLP-1) molecule has emerged as an essential element in the development of diverse agonists and multiagonists, based in the GLP-1 structure for obesity treatment. These new antiobesity medications can reach up to 24% weight loss, which makes possible an effective management of obesity and its complications. GLP-1 agonists affect diverse obesity etiopathogenic processes such as abnormal food intake regulation, adipocyte dysfunction, insulin resistance, adipokine production, inflammation, endothelial dysfunction, lipid metabolism, and oxidative stress. All these factors are significantly involved in the pathophysiology of multiple obesity-related complications, including diabetes mellitus, metabolic dysfunction-associated steatotic liver disease, heart failure, and atherosclerosis, among others. Potentiation and complementation of GLP-1 effects by co-stimulation of GIP (glucose-dependent insulinotropic peptide), glucagon, or amylin and other receptors contribute to additional benefits, opening new horizons in the therapeutic individualization for persons living with obesity.
La molécula del péptido análogo al glucagón tipo 1 (GLP-1) ha emergido, merced a la bioingeniería bioquímica, como un elemento esencial en el desarrollo de agonistas y multiagonistas basados en su estructura para el tratamiento de la obesidad. Estos nuevos fármacos llegan a alcanzar valores medios de pérdida de peso del 24%, lo que contribuye a su eficacia sobre las complicaciones de la obesidad. Sus efectos sobre las alteraciones en la regulación de la ingesta, disfunción adipocitaria, resistencia a la insulina, producción de adipoquinas, inflamación, disfunción endotelial, metabolismo lipídico y estrés oxidativo posibilitan el control de numerosas complicaciones como la diabetes, la enfermedad hepática metabólica, la insuficiencia cardiaca y la arteriosclerosis, entre otras. La potenciación y complementación de los efectos de GLP-1 que ofrece la coestimulación de receptores de GIP (polipéptido insulinotrópico dependiente de la glucosa), glucagón y amilina, promueven importantes beneficios adicionales, abriendo alentadores horizontes de individualización terapéutica para las personas que viven con obesidad.
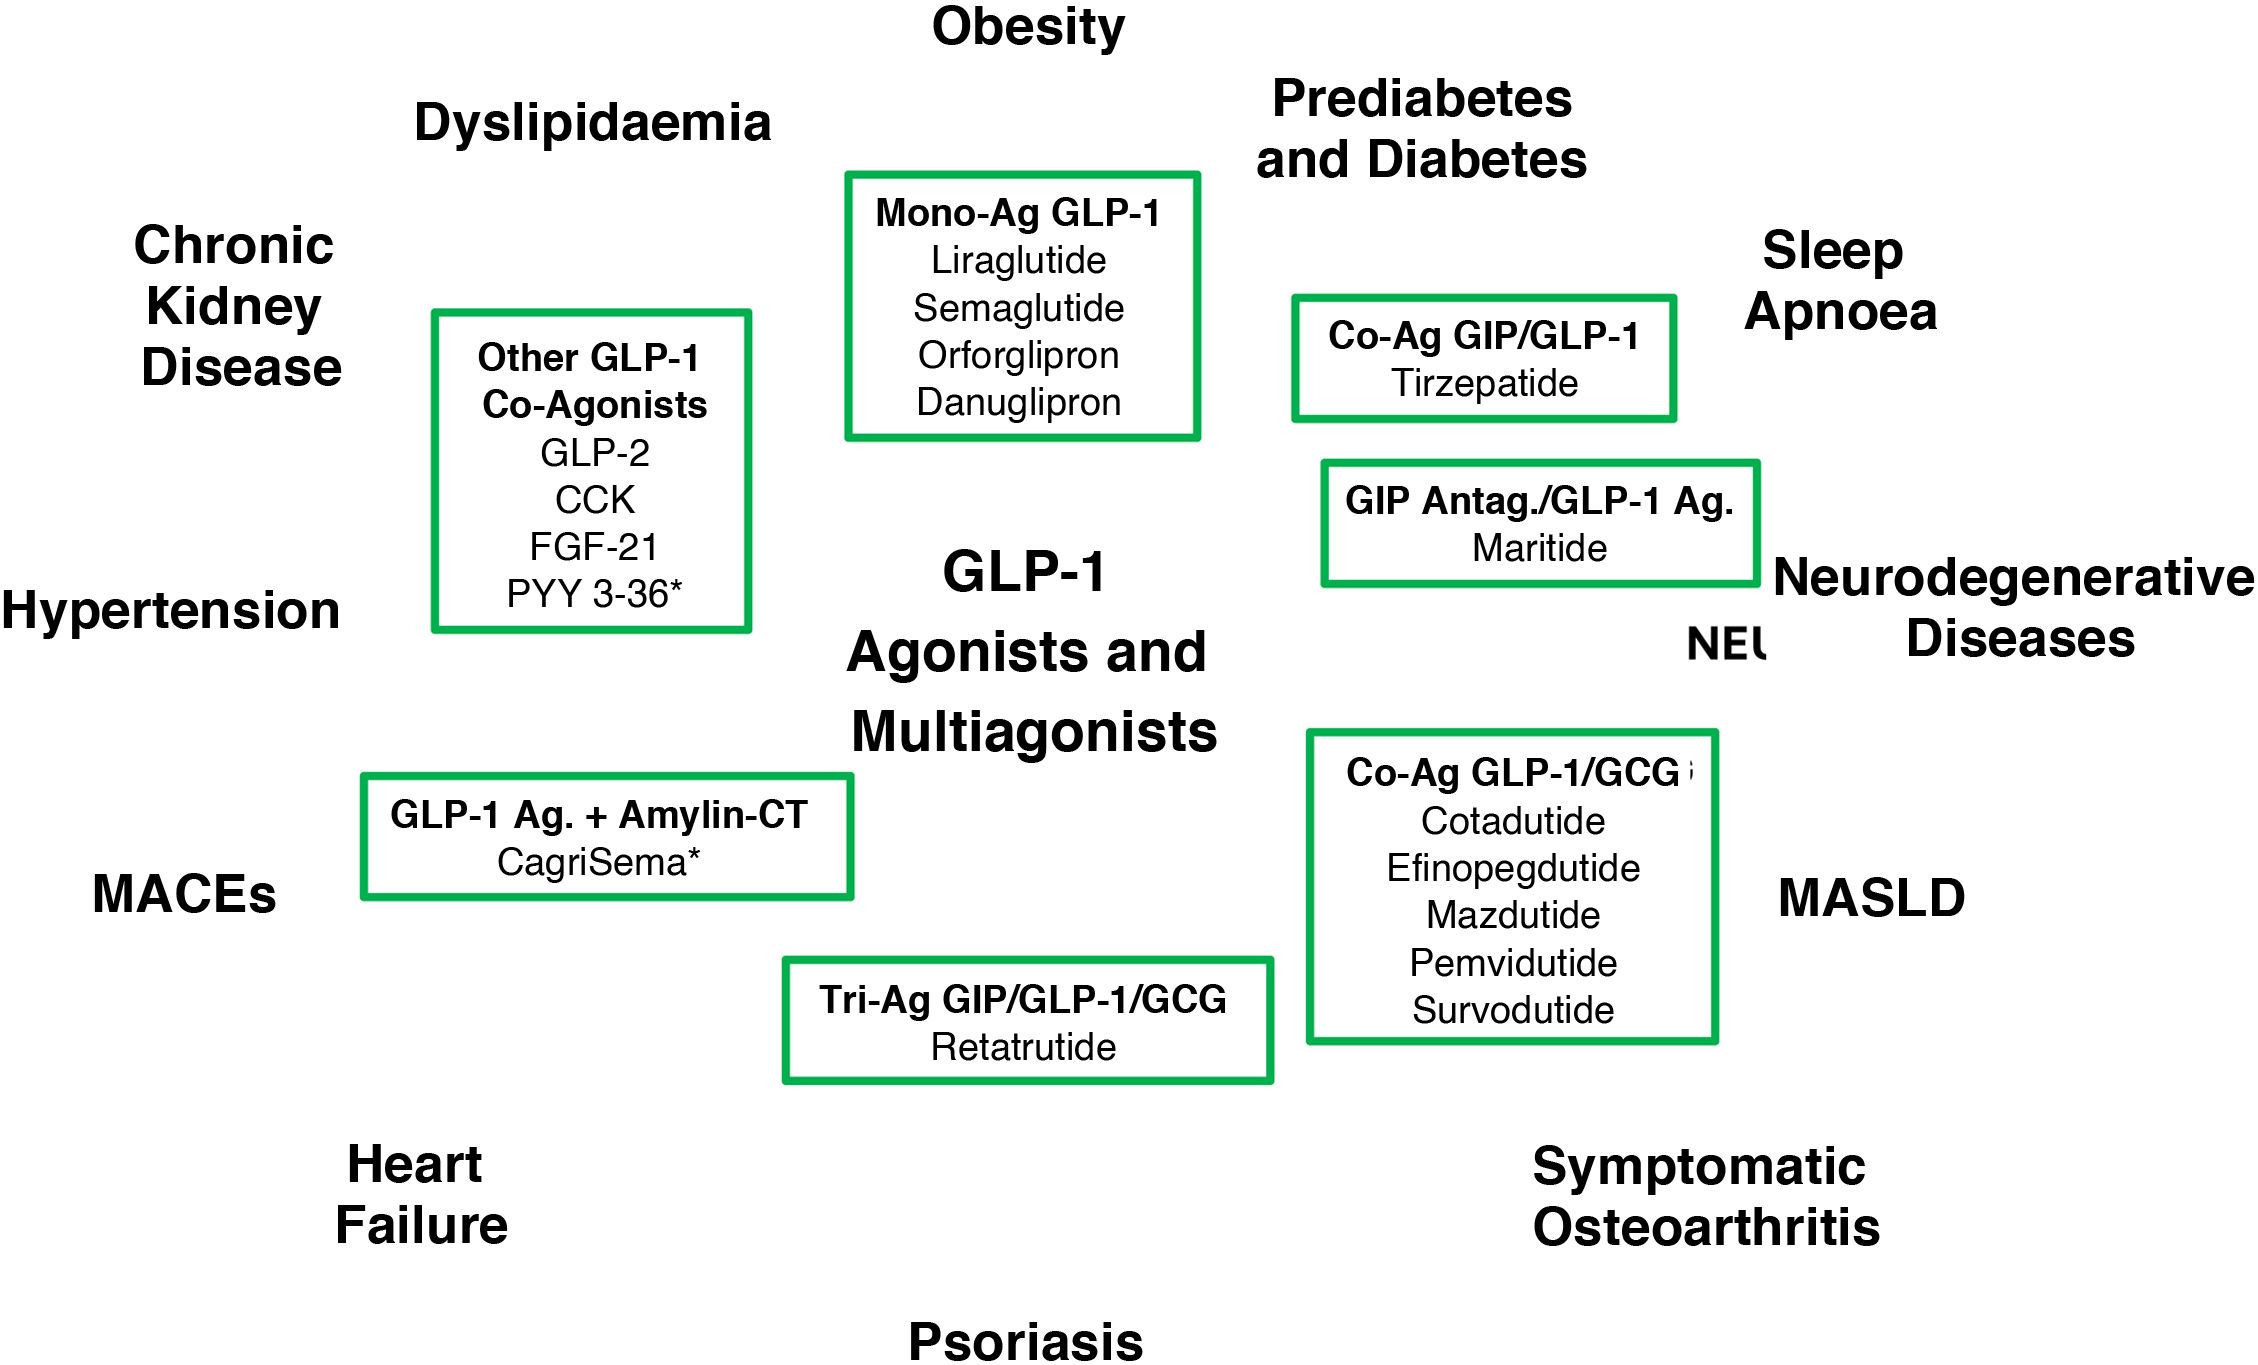
The accumulated evidence over recent decades regarding the efficacy of new pharmacological treatments for obesity has positioned the glucagon-like peptide-1 (GLP-1) analogue as a key component—whether as monoagonists, unimolecular multiagonists, or in combination therapies targeting multiple receptors.1 These drugs have made it possible to achieve previously unthinkable goals in terms of weight reduction and control of various obesity-related comorbidities (Fig. 1), placing them at the forefront of current and future advances in the treatment of obesity.

GLP-1 receptor agonists and multiagonists—either unimolecular or in combination—and the diseases in which they have shown efficacy in clinical or preclinical models.
CT: calcitonin; CCK: cholecystokinin; FGF-21: fibroblast growth factor-21; GLP-2: glucagon-like peptide-2 analogue; MACEs: major adverse cardiovascular events; MASLD: metabolic dysfunction-associated steatotic liver disease; PYY 3-36: peptide tyrosine-tyrosine 3-36.
*Combinations of agonists.
&GLP-1 receptor agonists have shown beneficial effects in preclinical models of neurodegenerative diseases, although the establishment of their clinical efficacy in prevention and treatment requires further studies.
GLP-1 7-36 is a 30 amino acid peptide derived from the proglucagon molecule that is synthesised in intestinal L cells, as well as in alpha cells of the pancreas and in neuronal clusters of the central nervous system (CNS).2 It is a peptide with a short half-life (2–3 min), due to rapid renal clearance and degradation by the enzyme dipeptidyl peptidase-4 (DPP-4), which converts GLP-1 into GLP-1 9-36, a form that does not interact with the GLP-1 receptor.1
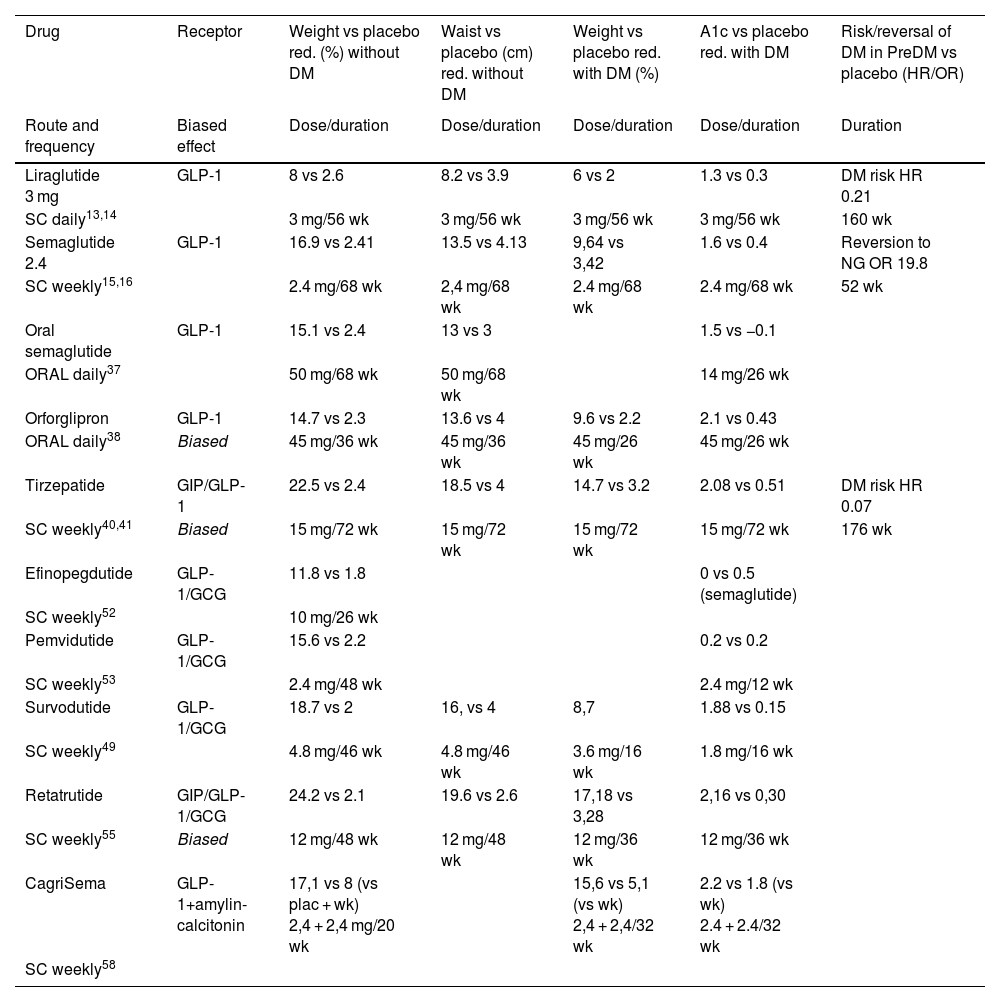
The GLP-1 receptor (GLP-1R) belongs to the class B G protein-coupled glucagon receptor family.2,3 Activation of the Gαs subunit leads to stimulation of adenylate cyclase, synthesis of cyclic AMP, mobilisation of intracellular calcium, and glucose-dependent insulin release by pancreatic beta cells.2,3 Intracellular signalling also involves various additional pathways, such as recruitment of beta-arrestin-1, which modulates receptor internalisation and desensitisation, as well as the effects of certain GLP-1R agonists.3,4 Depending on the structure of the ligand, intracellular signalling pathways are modulated towards cyclic AMP generation, activation of kinase cascades (ERK), and beta-arrestin-1 recruitment, all of which influence the biological effect and desensitisation of the GLP-1 receptor.4 Some GLP-1R agonists exhibit biased agonism, favouring intracellular activation of cyclic AMP with reduced beta-arrestin recruitment, which results in less GLP-1R desensitisation and a more prolonged biological action (Table 1).
Route of administration, periodicity, GLP-1 receptor bias and actions of GLP-1-based drugs on weight reduction, waist circumference, HbA1c and risk/reversal of diabetes.
| Drug | Receptor | Weight vs placebo red. (%) without DM | Waist vs placebo (cm) red. without DM | Weight vs placebo red. with DM (%) | A1c vs placebo red. with DM | Risk/reversal of DM in PreDM vs placebo (HR/OR) |
|---|---|---|---|---|---|---|
| Route and frequency | Biased effect | Dose/duration | Dose/duration | Dose/duration | Dose/duration | Duration |
| Liraglutide 3 mg | GLP-1 | 8 vs 2.6 | 8.2 vs 3.9 | 6 vs 2 | 1.3 vs 0.3 | DM risk HR 0.21 |
| SC daily13,14 | 3 mg/56 wk | 3 mg/56 wk | 3 mg/56 wk | 3 mg/56 wk | 160 wk | |
| Semaglutide 2.4 | GLP-1 | 16.9 vs 2.41 | 13.5 vs 4.13 | 9,64 vs 3,42 | 1.6 vs 0.4 | Reversion to NG OR 19.8 |
| SC weekly15,16 | 2.4 mg/68 wk | 2,4 mg/68 wk | 2.4 mg/68 wk | 2.4 mg/68 wk | 52 wk | |
| Oral semaglutide | GLP-1 | 15.1 vs 2.4 | 13 vs 3 | 1.5 vs −0.1 | ||
| ORAL daily37 | 50 mg/68 wk | 50 mg/68 wk | 14 mg/26 wk | |||
| Orforglipron | GLP-1 | 14.7 vs 2.3 | 13.6 vs 4 | 9.6 vs 2.2 | 2.1 vs 0.43 | |
| ORAL daily38 | Biased | 45 mg/36 wk | 45 mg/36 wk | 45 mg/26 wk | 45 mg/26 wk | |
| Tirzepatide | GIP/GLP-1 | 22.5 vs 2.4 | 18.5 vs 4 | 14.7 vs 3.2 | 2.08 vs 0.51 | DM risk HR 0.07 |
| SC weekly40,41 | Biased | 15 mg/72 wk | 15 mg/72 wk | 15 mg/72 wk | 15 mg/72 wk | 176 wk |
| Efinopegdutide | GLP-1/GCG | 11.8 vs 1.8 | 0 vs 0.5 (semaglutide) | |||
| SC weekly52 | 10 mg/26 wk | |||||
| Pemvidutide | GLP-1/GCG | 15.6 vs 2.2 | 0.2 vs 0.2 | |||
| SC weekly53 | 2.4 mg/48 wk | 2.4 mg/12 wk | ||||
| Survodutide | GLP-1/GCG | 18.7 vs 2 | 16, vs 4 | 8,7 | 1.88 vs 0.15 | |
| SC weekly49 | 4.8 mg/46 wk | 4.8 mg/46 wk | 3.6 mg/16 wk | 1.8 mg/16 wk | ||
| Retatrutide | GIP/GLP-1/GCG | 24.2 vs 2.1 | 19.6 vs 2.6 | 17,18 vs 3,28 | 2,16 vs 0,30 | |
| SC weekly55 | Biased | 12 mg/48 wk | 12 mg/48 wk | 12 mg/36 wk | 12 mg/36 wk | |
| CagriSema | GLP-1+amylin-calcitonin | 17,1 vs 8 (vs plac + wk) 2,4 + 2,4 mg/20 wk | 15,6 vs 5,1 (vs wk) 2,4 + 2,4/32 wk | 2.2 vs 1.8 (vs wk) 2.4 + 2.4/32 wk | ||
| SC weekly58 |
Biased: biased effect on GLP-1 receptor on intracellular signalling; DM: diabetes; HR: hazard ratio; OR: odds ratio; PreDM: prediabetes; Red: reduction. SC: subcutaneous; wk: weeks.
GLP-1Rs are expressed in the pancreas, intestinal intraepithelial lymphocytes, myocardium, adipose tissue, kidney, liver, blood vessels, lungs and in the CNS.2,3
Although GLP-1 is known for its incretin effect, which it shares with glucose-dependent insulinotropic peptide (GIP), the intake-regulating action, essential for its efficacy against obesity, occurs through its interaction with receptors located in the CNS.1,5 The GLP-1 peptide can reach the central nervous system (CNS) via peripheral vagal afferents, which transmit its action through the nodose ganglion to the nucleus tactus solitarius (NTS). In addition, circulating GLP-1 enters circumventricular areas of the CNS—such as the subfornical organ, the organum vasculosum of the lamina terminalis, the median eminence near the arcuate nucleus, and the area postrema—thanks to the partial permeability of the blood–brain barrier.2,3,6 In addition, NTS neurons, which receive peripheral afferent input, synthesise preproglucagon and serve as a source of GLP-1 within the CNS. This centrally produced GLP-1 reaches specific receptors located in key structures involved in appetite regulation, such as the paraventricular nucleus, the lateral septum, the nucleus accumbens and the lateral parabrachial nucleus.2,3,6 Furthermore, it promotes aversive responses, inhibits neuroinflammation and gastric emptying, and stimulates sympathetic tone and thermogenesis in experimental models.2,4,6 Activation of GLP-1R on neurons in the arcuate nucleus stimulates the production of pro-opiomelanocortin (POMC), which in turn inhibits neurons that produce neuropeptide Y (NPY), thereby generating an appetite-suppressing response.2 GLP-1 production has also been reported in the olfactory bulb, although its significance remains unclear.2,6
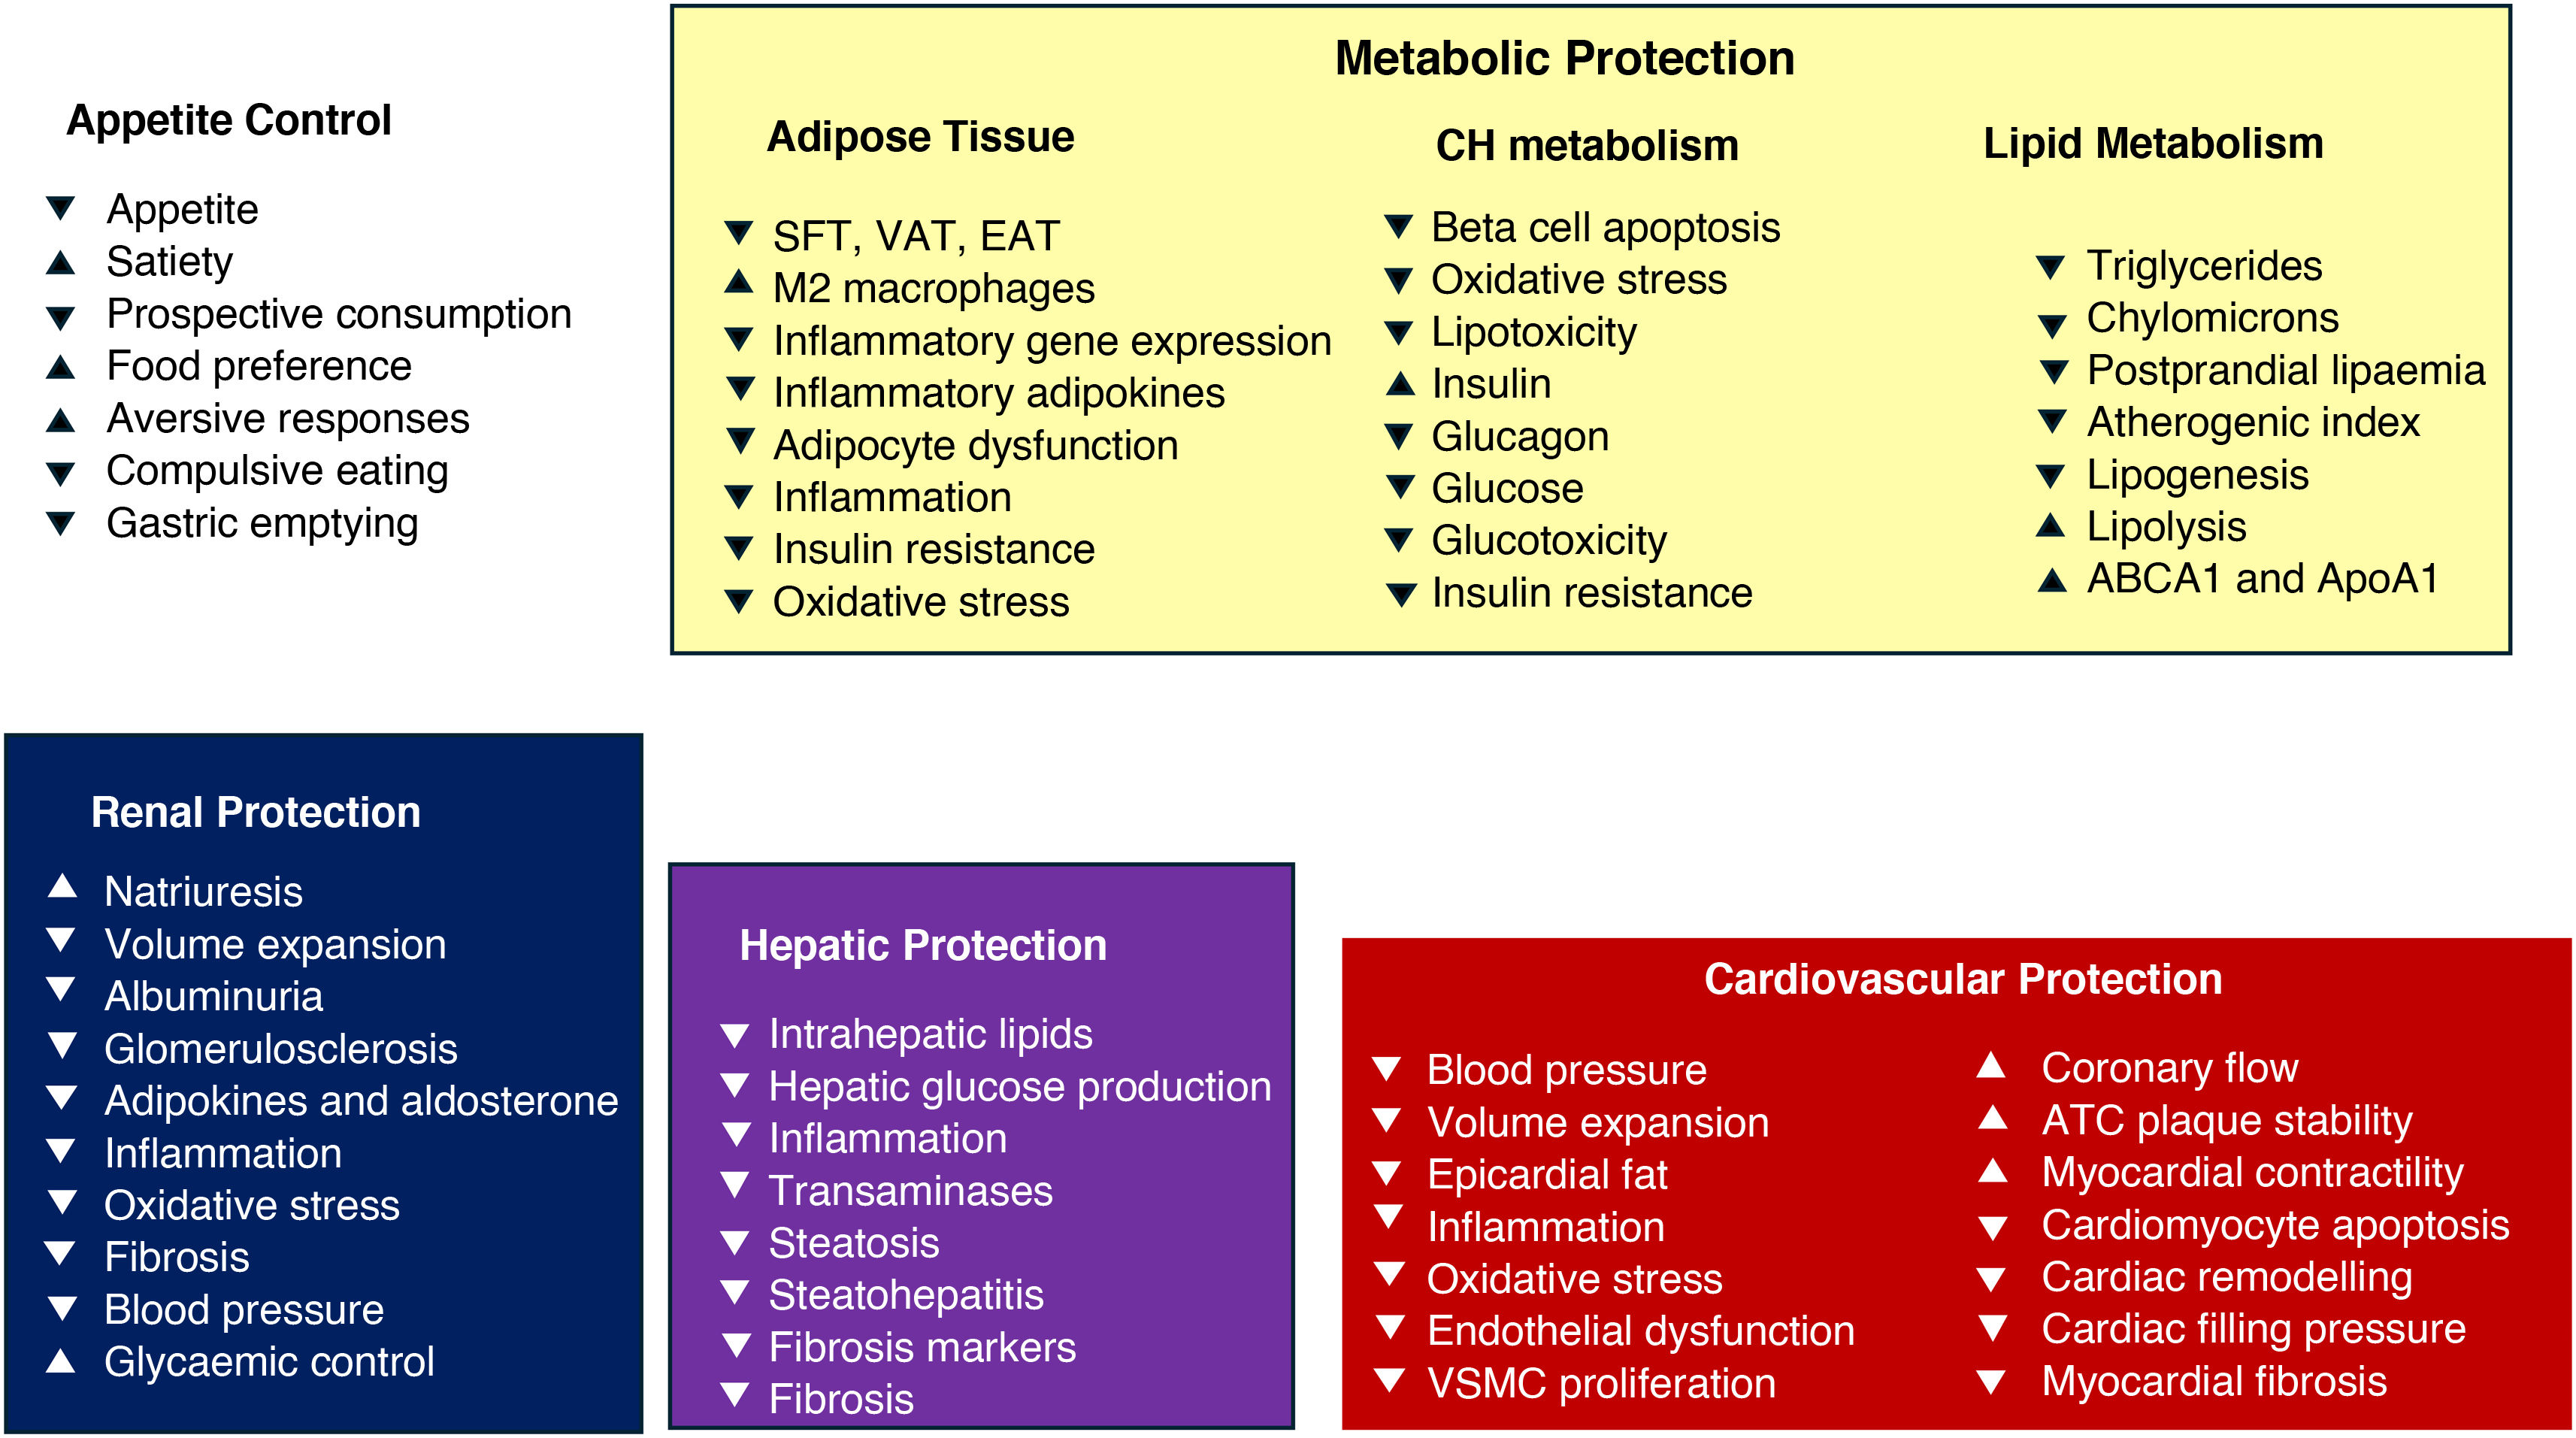
GLP-1R has been identified in the sinoatrial node, atrial and ventricular myocytes, and vascular endothelium. Activation of these receptors generates anti-inflammatory, oxidative stress-reducing and antiatherogenic effects, which support the cardioprotective and nephroprotective effects of GLP-1 agonists (Fig. 2).2,7,8 GLP-1 receptor expression in the liver is negligible,2 although a subset of γδ T cells in the endothelium and intrahepatic tissue express GLP-1R. Activation of these receptors has an anti-inflammatory effect.9 GLP-1R expression is known in subcutaneous, visceral and epicardial adipose tissue, although this is controversial at the adipocyte level.2,3

Mechanisms involved in the control of intake, metabolic protection, cardiovascular protection, hepatoprotection and nephroprotection of GLP-1 receptor agonists. Arrows indicate increased or decreased biological effect.
ABCA1: a protein involved in reverse cholesterol transport; ApoA1: apolipoprotein A1; ATC plaque: atherosclerotic plaque; EAT: epicardial adipose tissue; SFT: subcutaneous fatty tissue; VAT: visceral adipose tissue; VSMC prolif.: vascular smooth muscle cell proliferation.
The short half-life of native GLP-1 and advances in biochemical engineering led to the development of GLP-1 receptor agonists (GLP-1RAs). Modifications to the peptide chain to reduce degradation by DPP-4, combined with acylation to promote non-covalent binding to albumin, resulted in long-acting formulations, enabling their use in clinical practice.3,5 Initially, GLP-1 receptor monoagonists were marketed with the aim of treating type 2 diabetes, harnessing their incretin effect and glucose-dependent mechanism, along with their capacity to reduce body weight and their beneficial effects on associated comorbidities.1,3,5 Subsequently, research shifted its focus to obesity, employing higher doses than those used for diabetes.3,5 This was followed by the development of unimolecular structures with multi-receptor activity, such as GIP/GLP-1 and GLP-1/glucagon (GCG) coagonists, as well as GIP/GLP-1/GCG triagonists. Oral formulations were also developed.1,3,5
GLP-1 receptor monoagonists for the treatment of obesity: liraglutide and semaglutideThe first molecule to be marketed for the treatment of obesity was liraglutide (LIRA), administered via daily subcutaneous injection, which became available in 2014. Subsequently, semaglutide (SEMA), a once-weekly injectable GLP-1 receptor agonist, was launched in 2021.1,3
Structure and mechanism of actionBoth LIRA and SEMA are subcutaneously administered GLP-1 receptor agonists, sharing 97% and 94% homology, respectively, with the native GLP-1 molecule. Their half-lives are 13 hours (LIRA) and 7 days (SEMA), allowing for daily and weekly subcutaneous administration, respectively, thanks to the structural modifications introduced.5,10
Effects on obesity and glycaemic controlBoth LIRA 3 mg and SEMA 2.4 mg have demonstrated a strong appetite-suppressing and satiety-promoting effect, as well as a delaying effect on gastric emptying.11,12 The SCALE programme highlighted the efficacy of LIRA 3 mg in reducing body weight and waist circumference13 and confirmed a reduction in HbA1c levels in individuals with diabetes, along with a decreased progression from prediabetes to diabetes after three years of treatment14 (Table 1). The STEP programme showed a weight loss of up to 16.9% after one year of treatment with SEMA 2.4 mg, mainly at the expense of fat mass (difference versus placebo: fat mass −3.29%; lean mass +2.94%),15 with a clear superiority of SEMA 2.4 mg over LIRA 3 mg (15.8% vs 6.4%) as demonstrated in the STEP 8 study.16
The likelihood of reversal of diabetes by SEMA 2,4 mg was shown to be clearly superior to placebo in the STEP 10 study17 (Table 1).
The mechanisms underlying appetite suppression are closely linked to the neuronal pathways that regulate food intake within the central nervous system. Peripheral administration of LIRA leads to its localisation in circumventricular organs and the hypothalamic arcuate nucleus, where it promotes the activation of anorexigenic pathways and the inhibition of orexigenic ones. This is achieved through stimulation of pro-opiomelanocortin/cocaine- and amphetamine-regulated transcript (POMC/CART) neurons and the indirect inhibition of the orexigenic neuropeptide Y/agouti-related peptide (NPY/AgRP) axis via GABAergic mechanisms.18 The partial permeability of the blood–brain barrier in circumventricular structures and the arcuate nucleus, alongside potential GLP-1R-dependent involvement of tanycytes, facilitates the access of both LIRA and SEMA to brain regions that are essential in the regulation of food intake.
The distribution map of SEMA in the central nervous system shows a greater presence in the septal nuclei compared to LIRA.19 In addition to reducing food intake, SEMA has proven effective in modulating food preferences,12 likely through dopaminergic activation of the ventral tegmental area and a reduction in endocannabinoid tone.19 The subsequent activation of the parabrachial nucleus and other neural circuits involved in the hedonic regulation of food intake may be specific to SEMA, potentially helping to explain its differences from LIRA.19
The mechanisms involved in the improvement of glycaemic control by LIRA 3 mg and SEMA 2.4 mg are related to their incretin and glucagonostatic effects inherent to GLP-1 receptor agonism,3 as well as to those derived from weight loss, reduction in fat mass, and their associated consequences.20
Effects on other comorbiditiesThe SCALE programme shows that the apnoea-hypopnoea index reduces in cases of sleep apnoea syndrome when LIRA is used instead of a placebo (12.2 vs 6.1, p = 0.015).21 The contribution of weight loss to the effects of LIRA treatment in the SCALE programme varies. This ranges from approximately 100% for results relating to lipid fractions, blood pressure, and the apnoea–hypopnoea index to approximately 30% for effects relating to carbohydrate metabolism. This is probably related to the drug’s incretin effect.20
The demonstrated potential of SEMA to reduce adipose accumulation at the lingual level may represent an additional mechanism—beyond weight loss—for improving the control of sleep apnoea.22
The SCALE programme also demonstrated the ability of LIRA 3 mg to improve cardiovascular risk factors (CVRFs), including blood pressure, lipid profile and inflammation markers.13
The effects on glycaemic control and CVRFs associated with SEMA 2.4 mg in the STEP programme are qualitatively similar, but quantitatively superior to those observed with LIRA 3 mg, possibly related to the different weight loss.16
The SELECT study, conducted with SEMA 2.4 mg, consistently showed a reduction of major adverse cardiac events (MACE) of triple composite endpoint (non-fatal myocardial infarction, non-fatal stroke, cardiovascular mortality) of 20% relative to placebo in a population with established cardiovascular disease and BMI greater than 27 kg/m2 without diabetes after 39.8 months of follow-up.23
Although a direct role of SEMA cannot be ruled out, the influence of adipose reduction and the improvement of adipocyte dysfunction probably contribute to the evolving profile of cardiovascular risk factors.
However, the weight loss observed in the SELECT study (9.4%) was lower than that seen in previous STEP studies.23 The study design, which was not focused on obesity, may have influenced the lower-than-expected weight reduction, which did not parallel the trend in MACE reduction. The early divergence of the MACE occurrence curves between the SEMA and placebo groups23 suggests that SEMA may have been directly involved in the SELECT study results through its effects on angiogenesis, reduction of oxidative stress and inflammation, and anti-atherogenic actions derived from GLP-1R activation that promote endothelial function and cell survival7 (Fig. 2). Changes in HbA1c throughout the study were also not associated with reduced MACE.24
Additionally, the multiple pleiotropic effects of SEMA on metabolic, hepatic and renal function may indirectly contribute to cardiovascular protection.25
The HFpEF programme shows significant symptomatic improvement of heart failure symptoms with preserved ejection fraction (HFpEF) in obese patients treated with SEMA 2.4 mg26 (Fig. 3). In addition to significant weight loss, decreases in the inflammatory markers C-reactive protein and NT-proBNP26 were observed.

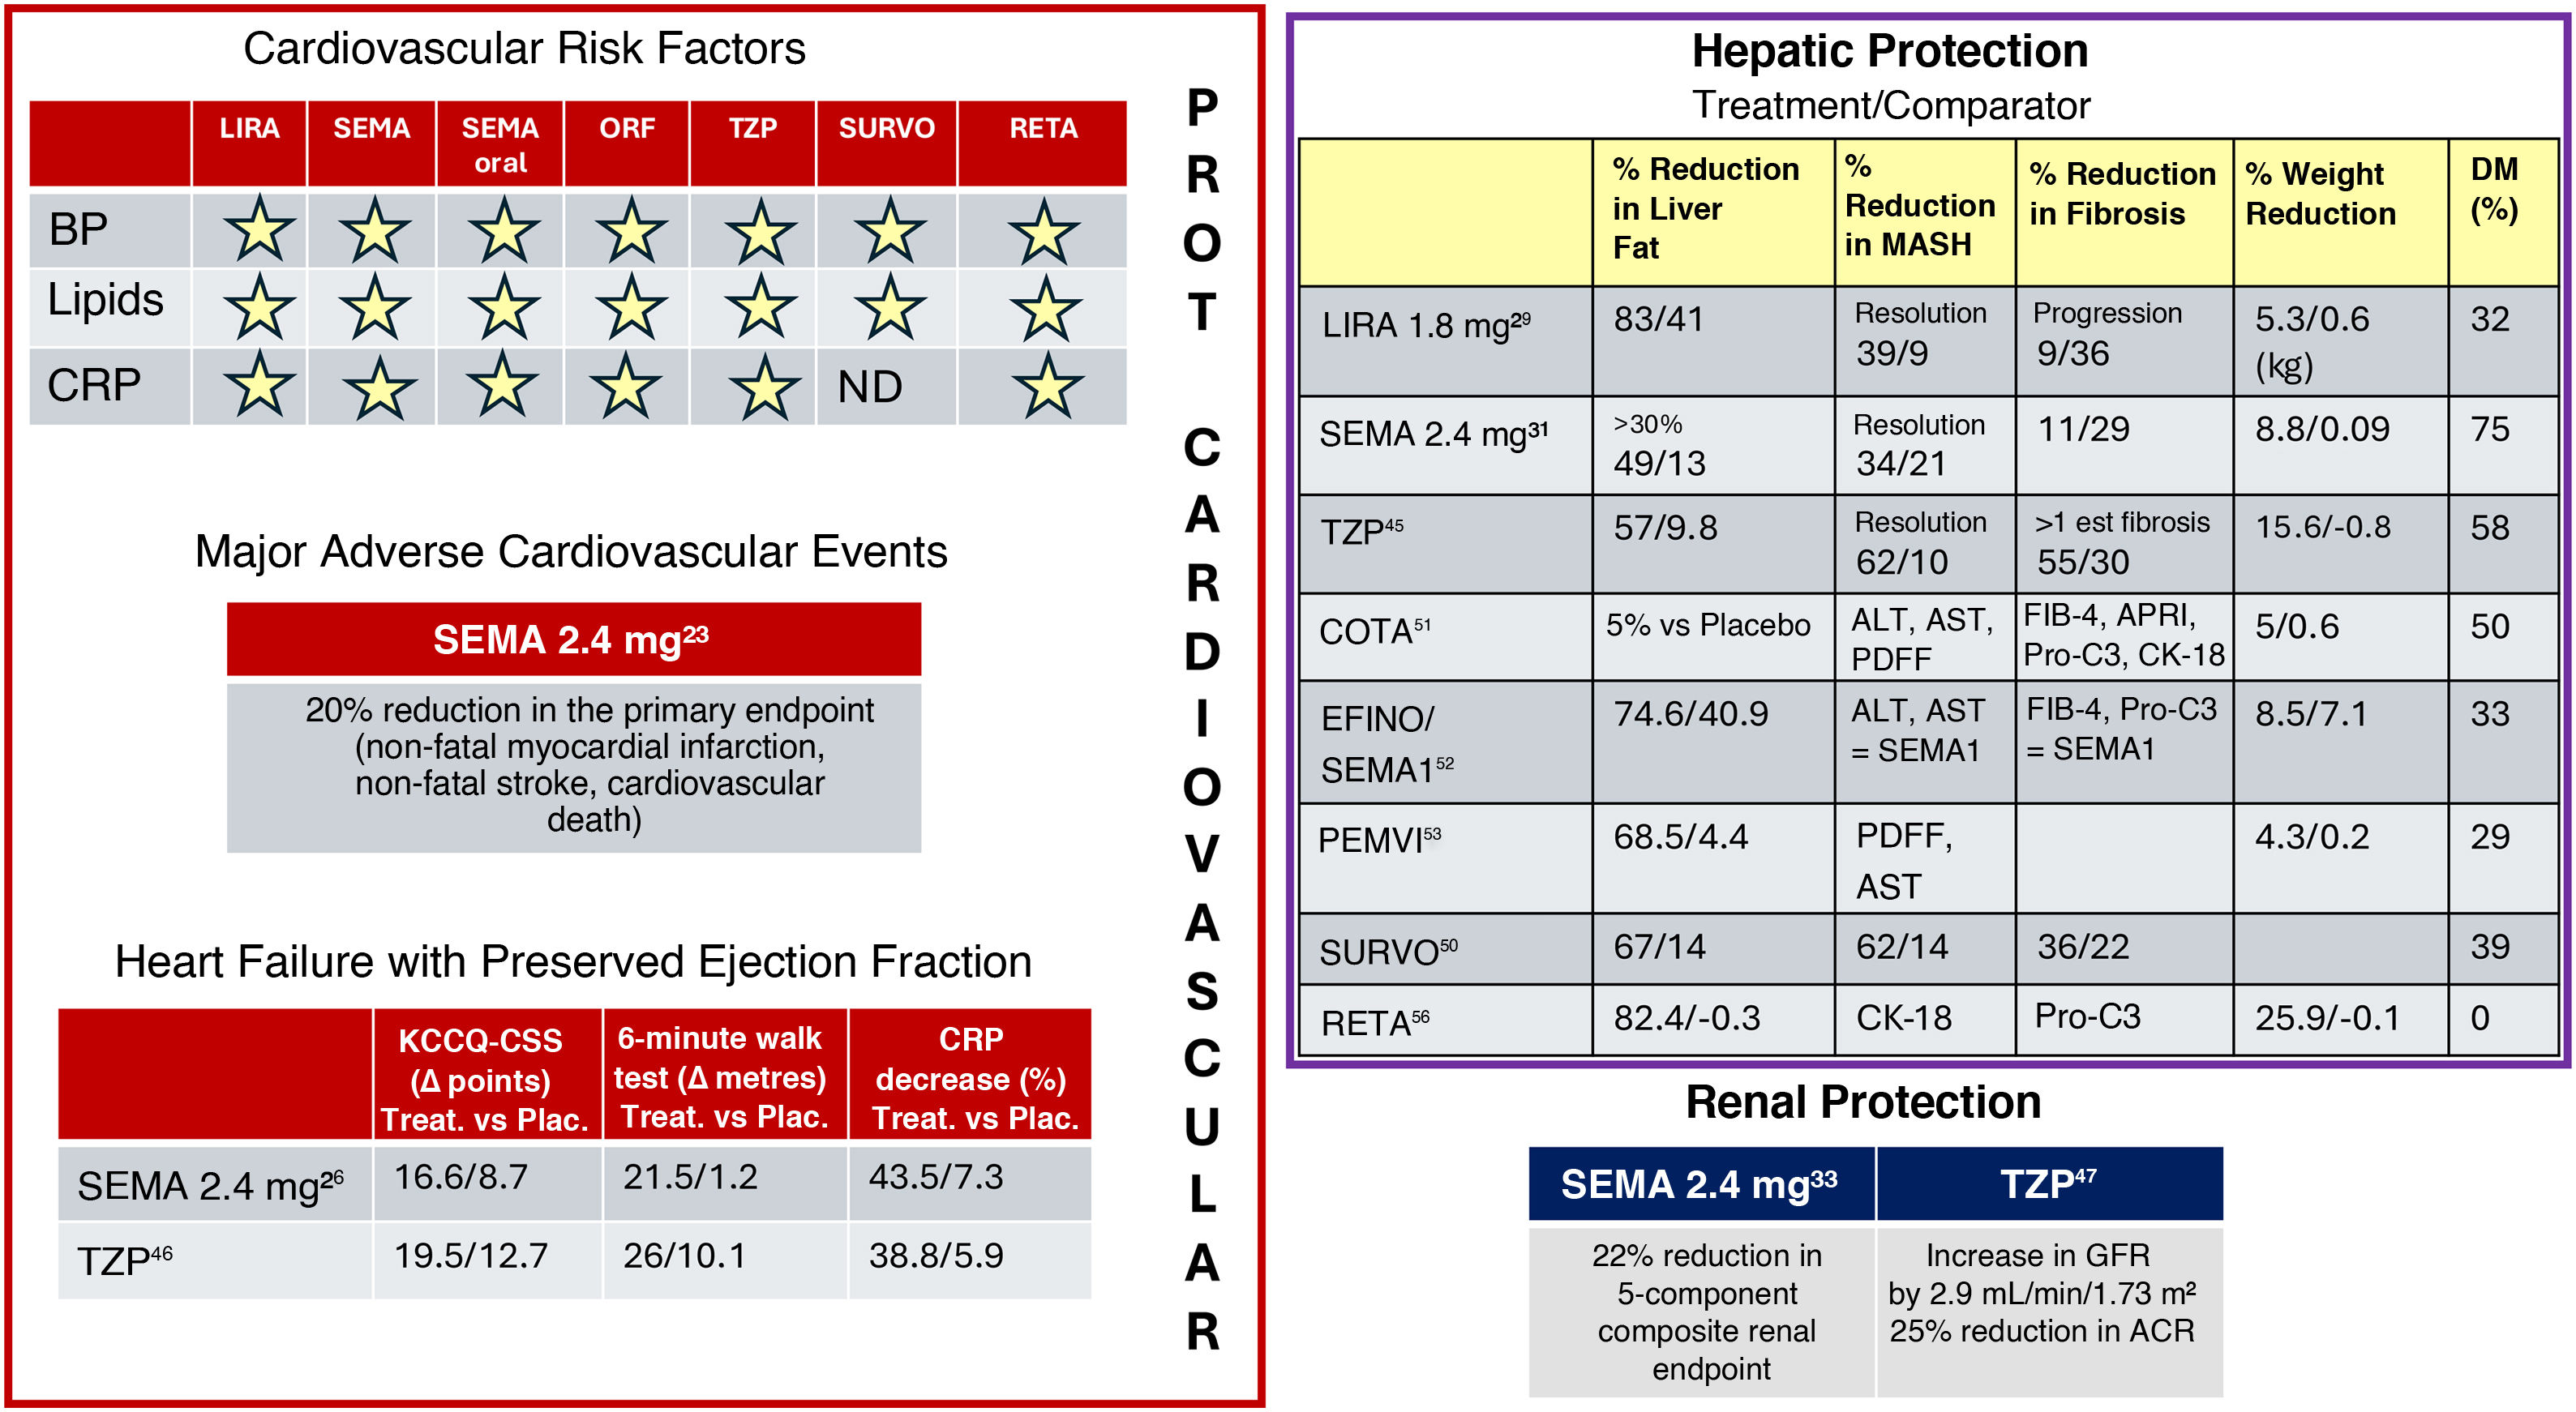
Clinical effects involved in the cardiovascular, hepatic, and renal protection of GLP-1 agonists, GIP/GLP-1 co-agonists, GLP-1/glucagon co-agonists, and GIP/GLP-1/glucagon tri-agonists. The star indicates a reduction in cardiovascular risk factors.
6-minute walk test: change in distance walked in 6 minutes; ACR: albumin-to-creatinine ratio; APRI: AST-to-platelet ratio index; CK-18: cytokeratin 18; BP: blood pressure; CRP: C-reactive protein; COTA: cotadutide; DM: diabetes mellitus; EFINO: efinopegdutide; EF: ejection fraction; FIB-4: fibrosis index; KCCQ-CSS: change in Kansas City Cardiomyopathy Questionnaire clinical summary score; LIRA: liraglutide; NA: not available; ORF: orforglipron; PDFF: fat fraction by proton density measured by MRI; PEMVI: pemvidutide; Pro-C3: collagen type III synthesis marker; RETA: retatrutide; SEMA: once-weekly subcutaneous semaglutide 2.4 mg; oral SEMA: daily oral semaglutide; SEMA 1: once-weekly semaglutide 1 mg; SURVO: survodutide; TZP: tirzepatide.
Among the operative mechanisms, protective effects of SEMA on cardiac remodelling with decreased hypertrophy and fibrosis with improved mitochondrial function, microvascular function and reduced apoptosis have been postulated in both experimental and clinical models,27,28 as well as other metabolic effects related to fat mass reduction (Fig. 2).
LIRA at a daily dose of 1.8 mg induces improvement in metabolic dysfunction-associated steatotic liver disease (MASLD), with resolution of steatohepatitis in 39% of cases, while fibrosis progressed in 9% of patients, compared to 36% in those treated with placebo29 (Fig. 3).
Studies of SEMA in metabolic liver disease have shown improvement in steatohepatitis with daily administration, but the results have been less satisfactory regarding the improvement of fibrosis at stages F2–F3 or F4,30 or with a weekly dose of 2.4 mg over 72 weeks.31 The results of the new phase III ESSENCE trial, evaluating SEMA 2.4 mg over 240 weeks, are highly anticipated.
The mechanisms involved in the beneficial actions of GLP-1 receptor agonists on MASLD are indirect, given the virtual absence of GLP-1R in hepatocytes, except for those in γδ T cells which are associated with anti-inflammatory effect.9 These include fat mass reduction, increased hepatic insulin sensitivity, reduced tissue lipotoxicity, anti-inflammatory effect and improved mitochondrial function32 (Fig. 2).
SEMA, as a treatment for obesity, has shown nephroprotective effects, with a 22% reduction in the composite renal endpoint in the SELECT33 trial in patients without diabetes, supporting the role of SEMA in the management of the cardio-renal-metabolic syndrome. Both LIRA and SEMA have demonstrated nephroprotective effects in individuals with diabetes, suggesting that systolic blood pressure and HbA1c levels—rather than weight—are the most influential mediators, although other factors also play a role (Fig. 2).
Some data suggest potential neuroprotective effects of LIRA and SEMA in neurodegenerative diseases,34 through various mechanisms possibly related to improved insulin sensitivity, anti-inflammatory actions, and inhibition of oxidative stress, mediated by GLP-1 receptors also present in astrocytes and microglia. These findings may support future applications in the treatment of dementia and other neurodegenerative disorders.
The effects of GLP-1ag on obesity, insulin resistance, inflammation, sleep apnoea and other CVRFs position this group of drugs favourably for the treatment of polycystic ovary syndrome and obesity-associated infertility.35
SEMA 2.4 mg has been shown to be effective in reducing symptoms of osteoarthritis of the knee in obese individuals after 68 weeks of treatment, probably related to the reduction in weight, adipocyte dysfunction and the anti-inflammatory effect of the molecule.36
Favourable effects of SEMA have also been reported in patients with hidradenitis suppurativa and psoriasis, probably related to its anti-inflammatory effect.
Oral GLP-1 receptor monoagonists: semaglutide, orforglipron and danuglipronOral semaglutide is formulated as a tablet with an absorption enhancer that facilitates its passage through the gastric mucosa. It is available for the treatment of type 2 diabetes. In individuals with obesity, at a daily dose of 50 mg, it achieved a 17.4% reduction in body weight over 68 weeks of treatment in the OASIS 1 trial37 (Table 1), attributed to its appetite-suppressing and satiety-enhancing effects. At the same time, it has proven effective in reducing cardiovascular risk factors and C-reactive protein (CRP), confirming the molecule’s anti-inflammatory effect.37
Orforglipron and danuglipron are orally administered, non-peptidic, small-molecule biased GLP-1 receptor agonists. They induce intracellular signalling that limits the recruitment of beta-arrestin-1, resulting in reduced GLP-1 receptor desensitisation and increased cyclic AMP production.4 Unlike oral SEMA, orforglipron does not require specific pre-administration conditions. Weight reduction is dose-dependent, reaching 15.4% at 36 weeks (Table 1), without evidence of a plateau, and is accompanied by a reduction in CVRFs38 (Fig. 3).
GIP/GLP-1 coagonists: tirzepatideStructure and mechanism of actionTirzepatide (TZP) is the only marketed drug of its kind. It is a unimolecular formulation based on the GIP structure, with structural modifications to the peptide chain that enable interaction with both GLP-1 and GIP receptors.39 Its biological action on the GIP receptor is five times greater than that on the GLP-1 receptor.39
Effects on weight loss, body composition and diabetes preventionThe SURMOUNT programme shows that TZP reduces weight in a dose-dependent manner, achieving a 22.5% weight reduction at the maximum weekly dose of 15 mg40 (Table 1). It is associated with a reduction in visceral adipose tissue and liver fat, along with a slight proportional increase in subcutaneous fatty tissue in patients with obesity and diabetes, suggesting a degree of compartmental selectivity. Additionally, it exerts a highly favourable effect on diabetes prevention in individuals with prediabetes (HR: 0.07 compared to placebo)41 (Table 1).
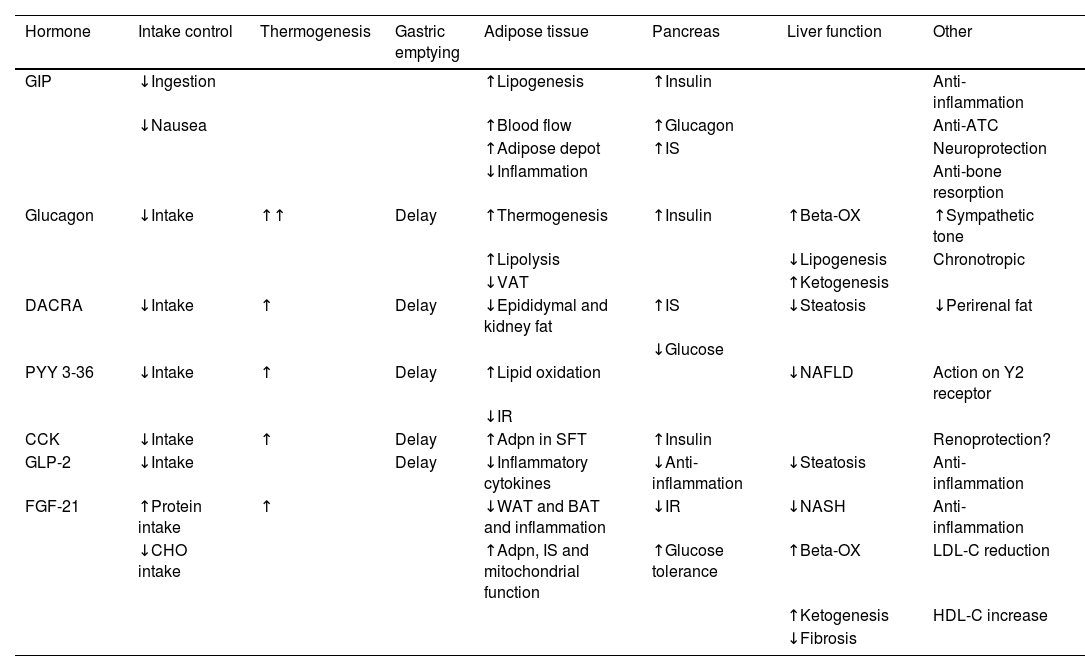
GIP agonism enhances the central incretin and anorectic effects of GLP-1, while reducing the incidence of nausea (Table 2).1,3,5 The effect on the GLP-1 receptor is biased due to the structure of TZP, which leads to reduced recruitment of beta-arrestin-1,42 thereby contributing to greater potency of the biological effect.
Effects of current and potential GLP-1-associated compounds in the context of multi-agonist drugs and combinations.
| Hormone | Intake control | Thermogenesis | Gastric emptying | Adipose tissue | Pancreas | Liver function | Other |
|---|---|---|---|---|---|---|---|
| GIP | ↓Ingestion | ↑Lipogenesis | ↑Insulin | Anti-inflammation | |||
| ↓Nausea | ↑Blood flow | ↑Glucagon | Anti-ATC | ||||
| ↑Adipose depot | ↑IS | Neuroprotection | |||||
| ↓Inflammation | Anti-bone resorption | ||||||
| Glucagon | ↓Intake | ↑↑ | Delay | ↑Thermogenesis | ↑Insulin | ↑Beta-OX | ↑Sympathetic tone |
| ↑Lipolysis | ↓Lipogenesis | Chronotropic | |||||
| ↓VAT | ↑Ketogenesis | ||||||
| DACRA | ↓Intake | ↑ | Delay | ↓Epididymal and kidney fat | ↑IS | ↓Steatosis | ↓Perirenal fat |
| ↓Glucose | |||||||
| PYY 3-36 | ↓Intake | ↑ | Delay | ↑Lipid oxidation | ↓NAFLD | Action on Y2 receptor | |
| ↓IR | |||||||
| CCK | ↓Intake | ↑ | Delay | ↑Adpn in SFT | ↑Insulin | Renoprotection? | |
| GLP-2 | ↓Intake | Delay | ↓Inflammatory cytokines | ↓Anti-inflammation | ↓Steatosis | Anti-inflammation | |
| FGF-21 | ↑Protein intake | ↑ | ↓WAT and BAT and inflammation | ↓IR | ↓NASH | Anti-inflammation | |
| ↓CHO intake | ↑Adpn, IS and mitochondrial function | ↑Glucose tolerance | ↑Beta-OX | LDL-C reduction | |||
| ↑Ketogenesis | HDL-C increase | ||||||
| ↓Fibrosis |
Adpn: adiponectin; BAT: brown adipose tissue; Beta OX: fatty acid beta-oxidation; CCK: cholecystokinin; DACRAs: dual amylin/calcitonin receptor agonists; FGF-21: fibroblast growth factor 21; GCG: glucagon; GIP: glucose-dependent insulinotropic polypeptide; GLP-2: glucagon-like peptide-2 analogue; IR: insulin resistance; IS: insulin sensitivity; NAFLD: non-alcoholic fatty liver disease; NASH: non-alcoholic steatohepatitis; PYY 3-36: peptide tyrosine-tyrosine; VAT: visceral adipose tissue; WAT: white adipose tissue.
Arrows indicate increase or decrease.
At the adipose tissue level, the combined GIP and GLP-1 agonism reduces M1 macrophage infiltration and pro-inflammatory cytokines such as leptin, increases adiponectin, and enhances insulin sensitivity, thereby improving adipocyte dysfunction.39 GIP additionally increases the storage capacity of adipose tissue, which lowers the likelihood of ectopic fat deposition and reduces the extent of visceral fat.1,5,39 Furthermore, it has demonstrated neuroprotective effects and promotes bone formation1 (Table 2).
Effects on other comorbiditiesTreatment with TZP is accompanied by a reduction in cardiovascular risk factors (Fig. 3) and an improvement in quality of life.40 Pending the results of cardiovascular safety studies in obesity (SURMOUNT MMO) and diabetes (SURPASS-CVOT), TZP has demonstrated in the SURMOUNT-1 trial a reduction in the predicted 10-year cardiovascular risk in patients with obesity and an initially moderate-to-high risk of cardiovascular disease.43
TZP treatment effectively reduces the apnoea–hypopnoea index by up to 23 events per hour, as well as blood pressure, C-reactive protein, and symptoms related to poor sleep quality (as assessed by PROMIS Sleep scales), likely due to weight loss and improvement in adipocyte dysfunction.44 Moreover, TZP induces remission of histologically confirmed metabolic dysfunction-associated steatohepatitis (MASH) in a dose-dependent manner (44–62% of cases, depending on the dose) and leads to improvement of at least one stage of liver fibrosis in 51–55% of cases—higher than that observed with placebo45 (Fig. 3). In addition to weight reduction, which may increase with longer treatment duration, GIP agonism appears to enhance insulin sensitivity, blood flow, and adipose tissue storage capacity32 (Table 2). The SUMMIT study shows that TZP treatment improves symptomatology and reduces the composite endpoint of cardiovascular mortality and worsening heart failure events in patients with HFpEF by 38%46 (Fig. 3). At 52 weeks, a reduction in circulating volume and blood pressure is observed, associated with decreased levels of adipokines and aldosterone, alongside reduced albuminuria and increased glomerular filtration rate compared with placebo, suggesting an additional renal benefit.47
GIP antagonist - GLP-1 agonist: MariTidaThis drug (Maridebart-cafraglutide or AMG 133), which is a conjugate of a monoclonal antibody to the GIP receptor and two GLP-1 receptor agonist molecules, is effective in reducing body weight in obese mice and cynomolgus monkeys. Results from the phase 1 human study show weight loss of 14% in 30 days with decreases in glucose, glucagon and C-reactive protein and an acceptable safety profile.48 It allows monthly subcutaneous administration. Although the mechanism of action is not fully understood, and GLP-1 and GIP receptor-related mechanisms may be involved, initial results show encouraging prospects in the treatment of obesity.
GLP-1/glucagon co-agonistsThe development of these unimolecular formulations targeting both GLP-1 and glucagon receptors enhances the anorectic effect of GLP-1, provides a lipolytic and lipogenesis-inhibiting effect (Table 2)—particularly at the hepatic level—and promotes thermogenic activity, thereby facilitating weight reduction and the treatment of MASLD.1,5,35
Survodutide generates dose-dependent weight reduction of up to 14.9% in 46 weeks.49 It is shown to be effective in reducing liver fat and improving MASH in up to 62% of participants treated with weekly injection of 4.8 mg. Improvement of at least one stage in liver fibrosis was evident in up to 36% of patients.50
Cotadutide is a balanced oxyntomodulin-derived GLP-1/GCG co-agonist administered daily that has demonstrated a moderate weight-reducing effect in patients with diabetes and obesity, with the ability to decrease the hepatic fat fraction assessed by MRI proton density, as well as markers of liver damage and fibrosis.51
Among other drugs are efinopegdutide—a peptide derived from oxyntomodulin conjugated with the Fc fragment of human IgG4 for monthly administration—pemvidutide, and mazdutide, all of which have demonstrated weight-reducing effects (Table 1) and reductions in liver fat (Fig. 3).52,53
GIP/GLP-1/glucagon triagonists: retatrutideRetatrutide is currently the most extensively studied GLP-1–GIP–GCG triagonist. It is derived from the GIP molecule, with peptide chain modifications that enable interaction with GIP, GLP-1, and glucagon receptors. It exhibits a biased effect on GLP-1 receptor interaction.54
Its mechanism of action and effects arise from the potentiation of the anorectic effects of all three components, while maintaining delayed gastric emptying. This is complemented by the incretin effect, insulin-sensitising properties, and promotion of subcutaneous fat accumulation mediated by GIP, as well as the thermogenic and lipolytic actions of GCG (Table 2).54 Its structure resists degradation by DPP-4 and enables binding to albumin, resulting in a half-life of six days, which allows for once-weekly subcutaneous administration. The interaction with the GIP receptor is more potent than that observed with the GLP-1 or GCG receptors.
It is currently the phase II drug associated with the greatest weight reduction, achieving a 24% decrease (28.5% in women) after 48 weeks with a weekly dose of 12 mg55 (Table 1), and providing significant benefits in the control of cardiovascular risk factors and the reduction of MASLD56 (Fig. 3). It is associated with an 82.4% reduction in liver fat and normalisation in 86% of cases with a weekly 12 mg dose over 24 weeks, in relation to visceral adipose tissue reduction, improved insulin sensitivity, decreased leptin levels, increased adiponectin, and favourable changes in lipid metabolism parameters and fibrosis markers such as Pro-C3.56
Amylin analogues in combination with GLP-1 receptor agonists: CagriSemaAmylin is a 37-amino-acid peptide that is co-secreted with insulin by pancreatic beta cells.57 It shares structural similarity with peptides of the calcitonin family. Its satiety effect is mediated by receptors expressed in the area postrema, which relay signals to other structures involved in appetite regulation, such as the nucleus of the solitary tract, the lateral parabrachial nucleus, the ventral tegmental area, and the arcuate nucleus in the hypothalamus.57 Some of amylin’s actions are mediated through interaction with calcitonin gene-related peptide (CGRP) receptors, which is why it is considered a dual amylin–calcitonin receptor agonist (DACRA).57
Cagrilintide is a long-acting DACRA that has been evaluated both as monotherapy and in combination with semaglutide (CagriSema) for body weight management in individuals with overweight or obesity, achieving a weight reduction of 17.1% over 20 weeks with the maximum weekly doses of both peptides (2.4 mg each).58 It has also proven effective in individuals with obesity and type 2 diabetes, although the weight reduction observed in this group was lower.
Amicretin is an oral unimolecular formulation in development that interacts with both amylin and GLP-1 receptors.
The combination of GLP-1, GIP and/or GCG agonist actions with amylin—through the incorporation of cagrisemaglutide or amicretin—opens the door to the development of new multiagonists as treatments for obesity, type 2 diabetes, and possibly other chronic diseases.
Other drugs in developmentOther multiagonists based on GLP-1 in combination with peptides such as GIP, GCG, PYY, secretin, and GLP-2—as well as new triagonists and tetraagonists incorporating DACRA agonism—are currently in the early stages of development1,59 (Table 2). These molecules enhance and complement the effects of GLP-1 and show promising prospects that will need to be confirmed throughout their development.
Future prospectsToday, the available pharmacological arsenal includes approaches to emerging conditions such as peripheral arterial disease and neurodegenerative disorders, further reinforcing the role of metabolic diseases in the pathophysiology of various conditions that have a profound impact on both quality of life and life expectancy in the population.60
Advances in knowledge and biochemical engineering are paving the way for intervention at multiple levels in the prevention and treatment of various complications, while also promoting therapeutic individualisation. These developments have the potential to change the natural history of many diseases as we know them and, supported by technology, represent a significant step forward towards a new era of precision medicine.
Ethical considerationsGiven its review nature and the absence of patient or procedural involvement, the need for informed consent does not apply.
FundingThis article did not receive any funding for its development or production.
Participation in teaching activities funded by Novo Nordisk Laboratories, Lilly Laboratories and Boehringer Ingelheim Laboratories, carried out as coordinator, speaker or moderator of scientific meetings.


