


Nodular Fasciitis in the breast is a rare pathology, categorized as a benign mesenchymal-origin breast tumor, with higher prevalence in middle-aged women. Its diagnosis is complex due to its low incidence and non-specific clinical presentation. However, although some authors suggest that microtrauma may be the origin, most patients do not report a history of trauma in the affected area. The pathology presents as a firm, painless, or slightly painful nodule that simulates breast cancer, typically located in the upper-outer quadrant (UOQ). The most common diagnostic tests are Mammography, which shows a dense and irregular nodule, and Ultrasound, which reveals a hypoechoic lesion with irregular margins. Excisional biopsy is the most commonly used procedure, with microscopic findings such as fibroblasts and frequent mitosis without atypia. A less invasive treatment is vacuum-assisted ultrasound-guided excision, although in some cases, a “wait and see” approach may be chosen due to the high rate of spontaneous resolution. Recurrences are exceptional, and the prognosis is generally favorable, although further studies are needed to draw definitive conclusions about its management and treatment. This article aims to summarize the currently available literature on this rare benign breast pathology, providing updated data—including immunohistochemical markers—to support clinicians in routine clinical practice.
Nodular fasciitis is a benign lesion considered a sarcoma mimic. It is characterized as a self-limited, reactive pseudosarcomatous process involving the proliferation of fibroblastic cells with rapid growth, often displaying high cellularity and mitotic activity. The lesions are usually small and solitary, most commonly appearing in the upper extremities of adults.
This entity was first described in 1955 by Konwaler [1] under the name pseudosarcomatous subcutaneous fibromatosis and was later designated as nodular fasciitis in 1966 by Mehregan.
Although rare, this process may develop within the breast, where it can clinically and radiologically mimic breast carcinoma. Therefore, establishing an accurate diagnostic and therapeutic approach is essential in order to properly manage these complex cases and avoid unnecessary treatments that could potentially cause further harm to patients.
Case reportWe present the case of a 41-year-old woman, a smoker, with a history of multiple surgical interventions for venous insufficiency of the right lower limb (CHIVA technique). She presented to the Breast Pathology Clinic with a left breast nodule of one month's duration, which she had detected during self-examination.
The patient reported a progressive increase in the size of the mass, without associated pain, erythema, or other significant symptoms. On physical examination, both breasts were well-shaped, with no deformity of the nipple–areola complex (NAC). At the junction of the upper quadrants (UQs) of the left breast, a firm, non-tender, irregularly bordered indurated area was palpated. No other abnormalities were found on bilateral breast, Spence's tail, or axillary examination.
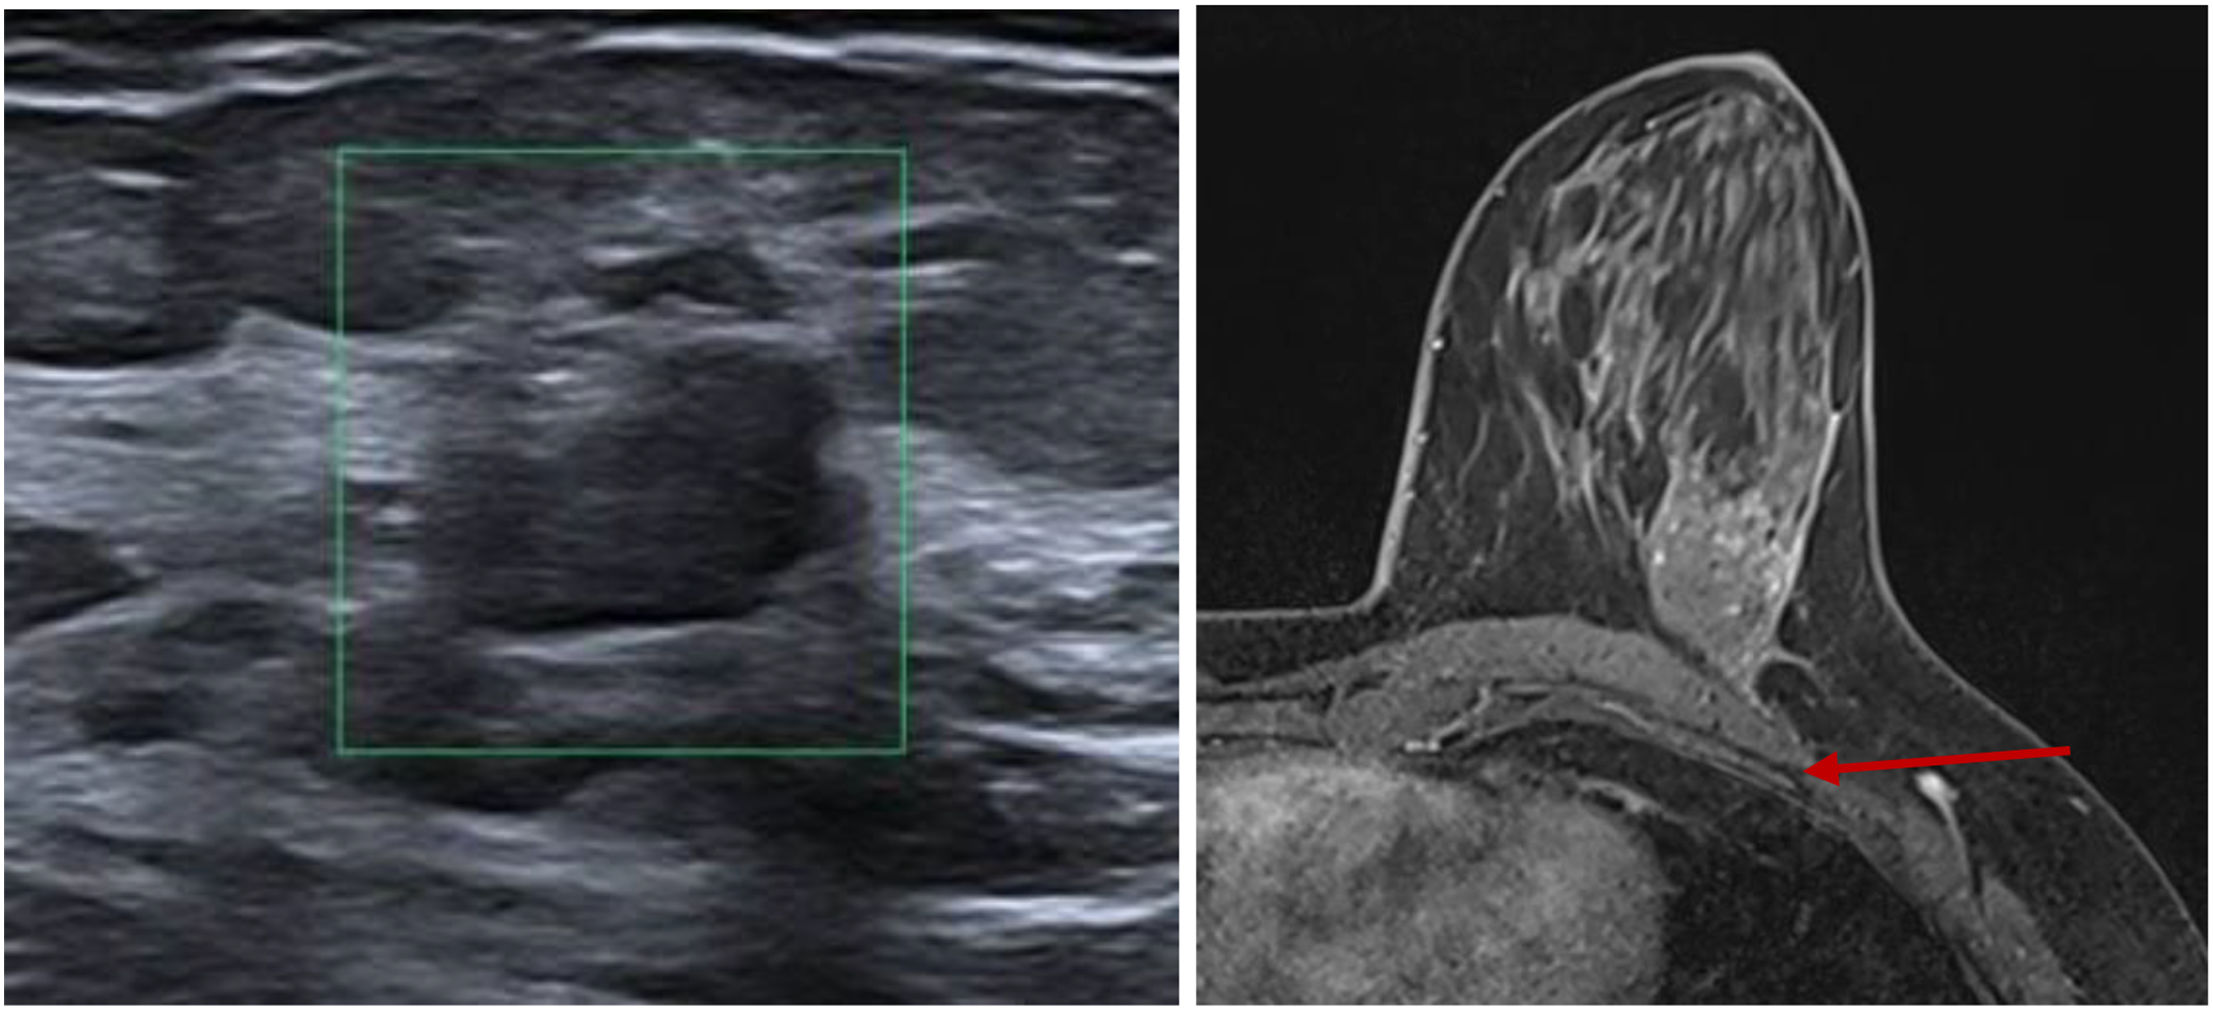
Bilateral mammography and breast ultrasound revealed a solid nodule measuring 11 mm (Fig. 1) in the aforementioned area. The lesion appeared hypoechoic, with lobulated contours, irregular margins, and adjacent tissue distortion with spiculation. No axillary lymphadenopathy was detected. The finding was classified as BIRADS 5.

The local assessment was complemented with contrast-enhanced breast magnetic resonance imaging (MRI), which demonstrated an early-enhancing, spiculated nodule located in the upper outer quadrant of the left breast, showing restricted diffusion and measuring 11 × 13 × 11 mm (Fig. 1.2). These findings were highly suggestive of malignancy (BIRADS 5). No suspicious axillary lymph nodes were identified in any of the three Berg levels.
Due to the suspicion of malignancy, an ultrasound-guided core needle biopsy (CNB) was performed. Histopathological examination revealed a spindle-cell proliferation, consistent with a diagnosis of nodular fasciitis.
The patient subsequently underwent surgical excision via a wire-guided lumpectomy of the lesion after providing informed consent.
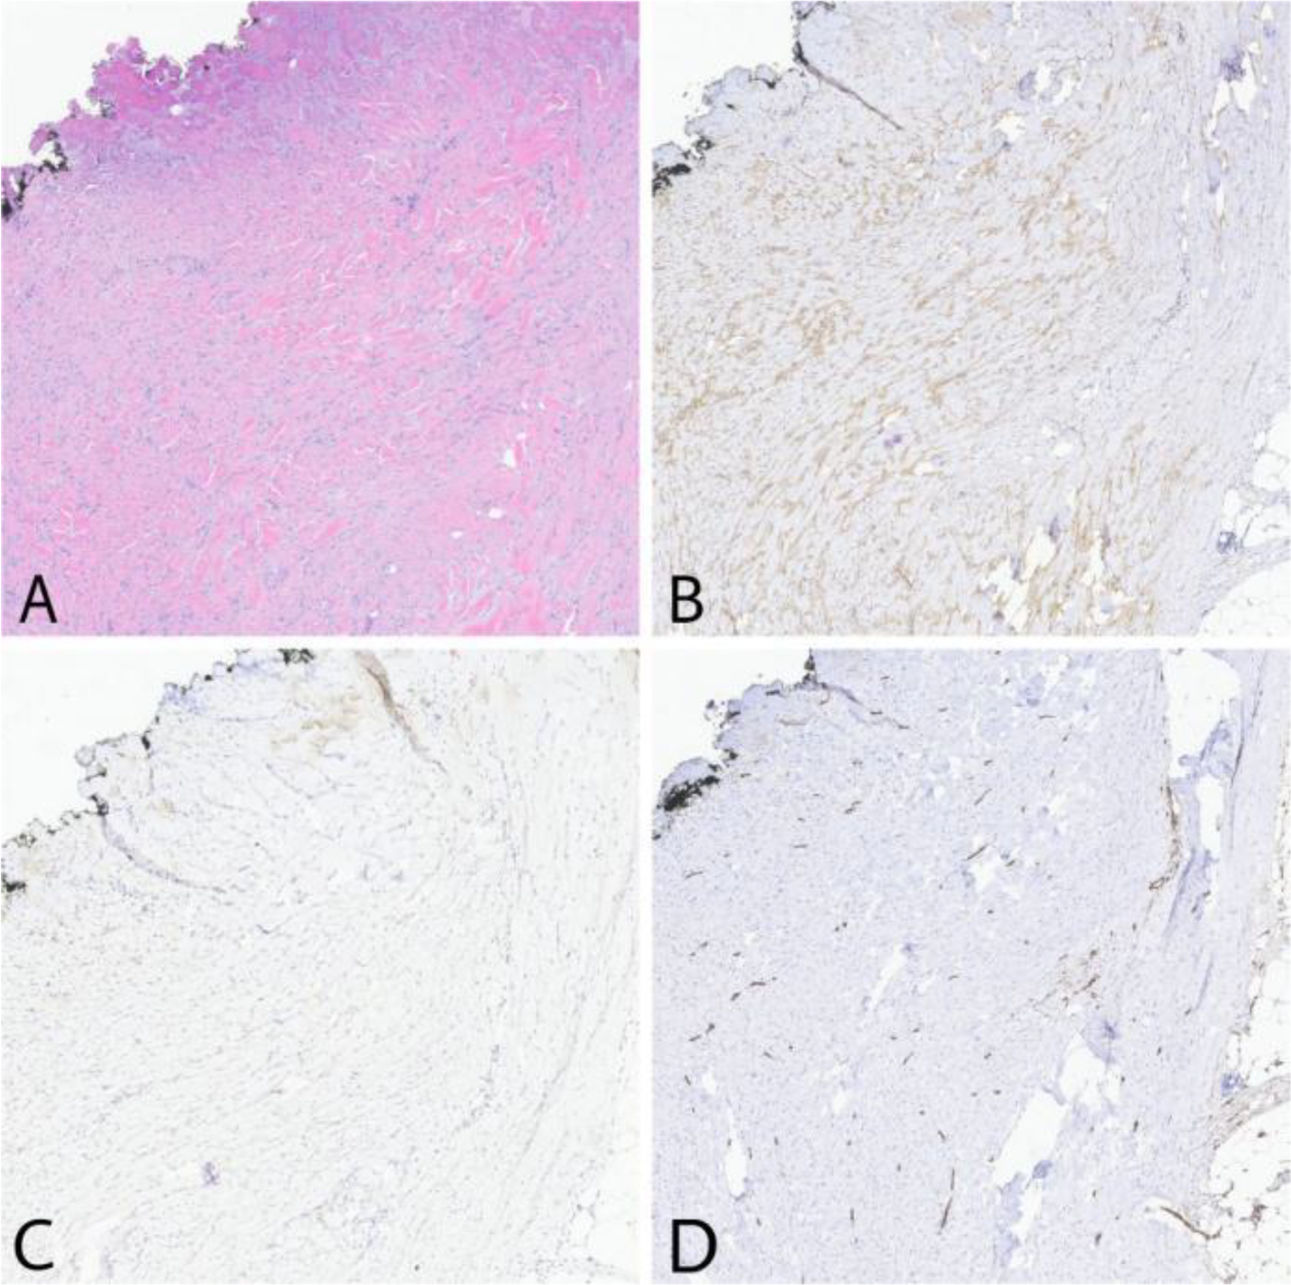
Final histopathological analysis confirmed a 13-mm nodular fasciitis, showing positive immunohistochemical staining for actin and desmin, and negative staining for β-catenin, cytokeratin AE1/AE3, p63, CD34, and S100 (Fig. 2).

Simple lumpectomy section of the breast. Nodular Fasciitis. A: Benign proliferation of spindle-shaped cells consistent with fibroblasts/myofibroblasts within a myxoid stroma with collagen disarray. B: Negative nuclear immunoexpression of beta-catenin. C: Negative immunoexpression for p63. D: Negative immunoexpression for CD34. (A: H&E; 6x); (B: β-catenin; 6x); (C: p63; 6x); (D: CD34; 6x).
Nodular fasciitis of the breast is an exceedingly rare condition, with very few cases reported in the medical literature. According to the World Health Organization (WHO), it is classified as a benign mesenchymal breast tumor and is more prevalent in women, typically of middle age [2]. In contrast, nodular fasciitis in other parts of the body tends to occur more frequently in men, with an incidence approaching 50%.
The diagnosis and, consequently, the management of nodular fasciitis are challenging due to its extreme rarity and its nonspecific clinical presentation and imaging findings. Therefore, a detailed study of this pathology is necessary to establish unified management guidelines and to avoid unnecessary interventions.
The pathogenesis of nodular fasciitis remains unknown. Many authors propose a relationship with microtrauma, although fewer than 10% of patients report a history of trauma in the affected area [2]. Likewise, a personal or family history of breast cancer does not appear to influence its development.
Clinically, nodular fasciitis of the breast typically presents as a sudden-onset, rapidly growing, small, firm, and painless nodule, although it may occasionally be tender, simulating the typical presentation of symptomatic breast carcinoma. The upper outer quadrant (UOQ) is the most commonly affected site, similar to other breast pathologies (e.g., carcinoma), likely due to the greater density of breast tissue in this quadrant [3].
Lesions are usually approximately 2 cm in size, although smaller or larger nodules have also been reported [4]. On palpation, the nodule is typically firm, well-defined, and mobile, although soft or adherent nodules have also been described.
Importantly, unlike malignant breast tumors, axillary lymph node involvement is absent [5]. This lesion is also characterized by rapid growth and evolution, features that can be considered pathognomonic.
The most commonly used diagnostic imaging modalities are mammography and ultrasonography. On mammography, nodular fasciitis appears as a dense, irregular, or spiculated mass with poorly defined margins, usually without calcifications. On ultrasound, it is typically hypoechoic with irregular margins and shows minimal or absent vascularity.
Excisional biopsy remains the most frequently used diagnostic-therapeutic procedure in routine clinical practice. Histologically, the lesion is characterized by bland-appearing stellate fibroblasts arranged in a loose fascicular to storiform pattern [6]. Cellularity is variable, and the extracellular matrix ranges from myxoid to collagenous. Extravasated red blood cells are often observed, and mitoses may be frequent but without atypical forms. Immunohistochemically, nodular fasciitis shows positivity for actin and negativity for cytokeratin (CK) and p63 [7]. A balanced translocation t(17;22)(p13;q13) resulting in MYH9-USP6 fusion has been identified in some cases [8].
A less invasive option is ultrasound-guided vacuum-assisted excision, as described by Rhee et al. In some cases, a “watch-and-wait” approach may be adopted due to the high rate of spontaneous lesion resolution.
Distinguishing pseudosarcomatous processes from true breast sarcomas is challenging due to overlapping clinical features. Pseudosarcomatous lesions usually have a more indolent course, while sarcomas grow rapidly and behave aggressively. Imaging may assist in evaluation, but no consistent vascularization pattern reliably differentiates the two. Histopathology remains essential, as reactive atypia characterizes pseudosarcomatous lesions versus true atypia and mitotic activity in sarcomas. Immunohistochemistry can provide additional support in select cases, yet its role is not standardized. These limitations underscore the need for integrated clinical, radiological, and pathological assessment.
However, establishing clear criteria to differentiate biopsy from conservative management is not always straightforward. Several studies recommend a non-surgical approach in typical cases, when clinical, radiological, and histopathological features are concordant [9]. If these criteria are not met, excisional biopsy (lumpectomy) or vacuum-assisted excision should be performed to establish a definitive diagnosis.
Regarding recurrence, nodular fasciitis appears to be exceptionally rare [10,11], although further studies are needed to draw more precise conclusions [2]. Overall, the prognosis of this lesion is excellent.
Ethical considerationsThe patient provided informed consent, and ethical principles and confidentiality were strictly observed.
FundingThis study received no external funding.
The authors declare no conflicts of interest.



