



Invasive fungal infections pose a clinical challenge due to their high morbidity and mortality. Since its introduction in 2016, isavuconazole has emerged as a new therapeutic option, highlighting the need to evaluate its use in real-world clinical practice.
AimsThe aim of this study was to evaluate the appropriateness of isavuconazole prescription in accordance with its drug label and the pharmacotherapeutic guidelines of Hospital Universitario de La Princesa, as well as to characterize the patient population receiving this treatment.
MethodsThis was a retrospective observational study of prescription–indication. All patients who received isavuconazole during hospitalization between January 2019 and June 2023 were included. Data were obtained by reviewing electronic medical records with 63.3% of these patients being male and a median age of 63.
ResultsA total of 129 patients were assessed, with 63.3% of these patients being male and a median age 63. Seventy seven percent suffered from malignant haematological diseases and 10.9% had been diagnosed with COVID-19 pneumonia with no other risk factor for invasive fungal infection. The percentage of inappropriate prescriptions was 22.5% (95% confidence interval: 15.2–29.8%). The main reasons for inappropriateness were prophylactic use (10.9%) and treatment of a non-indicated pathogen (4.7%). The frequency of prescription followed an upward trend, although goodness-of-fit to a linear regression model was low.
ConclusionsThe level of inappropriateness observed (15–30%) is relatively low compared to other studies on antifungal use, and the frequency of prescription does not exhibit a significant increase over the years. Although adherence to local and international prescribing guidelines remains suboptimal, these data demonstrate a relatively effective integration of isavuconazole into the hospital's therapeutic repertoire.
Las infecciones fúngicas invasivas representan un desafío clínico debido a su elevada morbimortalidad. Desde su introducción en 2016, el isavuconazol ha surgido como una nueva opción terapéutica, lo que hace necesario evaluar su utilización en la práctica clínica real.
ObjetivosEl propósito de este trabajo es evaluar el grado de adecuación de la prescripción de isavuconazol a las indicaciones de la ficha técnica y la guía farmacoterapéutica del Hospital Universitario de La Princesa y caracterizar a la población que recibe este fármaco.
MétodosSe realizó un estudio observacional retrospectivo de prescripción-indicación. Se incluyeron en el análisis a todos los pacientes que habían sido tratados con isavuconazol durante un ingreso hospitalario entre enero de 2019 y junio de 2023. Los datos se obtuvieron mediante la revisión de las historias clínicas digitales.
ResultadosCiento veintinueve pacientes fueron evaluados. Un 63.3% eran varones y la mediana de edad fue de 63 años. Un 77% presentaban una patología hematológica maligna de base y un 10.9% tenían una neumonía COVID-19 sin otro factor de riesgo de infección fúngica invasiva. El grado de inadecuación fue del 22.5% (intervalo de confianza del 95%: 15.2-29.8%). Los principales motivos de inadecuación en el uso del isavuconazol fueron el su uso profiláctico (10.9%) y el tratamiento de un microorganismo no indicado (4.7%). La frecuencia de la prescripción siguió una tendencia ascendente, aunque la bondad de ajuste al modelo de regresión lineal fue baja.
ConclusionesEl grado de inadecuación obtenido no es muy alto (15-30%) en comparación con otros trabajos sobre el uso de antifúngicos; la frecuencia de la prescripción no ha sufrido un incremento significativo con los años. Si bien la adherencia de la prescripción a las recomendaciones locales e internacionales todavía es subóptima, estos datos reflejan una incorporación relativamente efectiva del isavuconazol al arsenal terapéutico del hospital.
The incidence of invasive fungal infections (IFIs) has progressively increased in the past decades and remains associated with high morbidity and mortality rates. Immunosuppression is the primary risk factor for their development.17 The most common IFIs are caused by Candida species. Among IFIs primarily affecting the lungs, invasive aspergillosis is the most frequent, followed by mucormycoses.2,17 Systemic mycoses pose diagnostic and therapeutic challenges due to difficulties in early detection, narrow therapeutic windows of antifungal agents, and frequent adverse effects.18,20
Isavuconazole (Cresemba®) is a triazole antifungal agent authorized in Europe as an “orphan” drug in 2016 for hospital use. This designation implies that the drug is intended for use against a life-threatening or chronically debilitating disease, with low prevalence in general population and for which no satisfactory therapeutic alternatives exist or, if such alternatives are available, the medicinal product is expected to provide a significant clinical benefit.10 It is indicated for adults in two scenarios: (a) treatment of invasive aspergillosis, and (b) treatment of mucormycosis in patients for whom amphotericin B is not appropriate.1,2 The recommended dosage regimen consists of six loading doses of 200mg administered every 8h over a 48-h period, followed by a maintenance dose of 200mg once daily, starting 12–24h after the last loading dose. Treatment duration depends on clinical response, although courses exceeding six months require individualized risk–benefit assessment. No dose adjustment is required in elderly patients or in cases of renal impairment (including end stage renal disease) or mild-to-moderate hepatic impairment (Child–Pugh A and B).1,2
The efficacy of isavuconazole in invasive aspergillosis was demonstrated in the SECURE clinical trial,15 whereas data for mucormycosis are more limited and derived primarily from the VITAL study.16 However, the ACTIVE trial failed to demonstrate noninferiority of isavuconazol compared to caspofungin for primary treatment of candidemia and invasive candidiasis, supporting the greater intrinsic activity of echinocandins against Candida species, in line with previous reports.13 The drug is contraindicated in patients with short QT syndrome or those receiving ketoconazole, ritonavir, or strong CYP3A4/5 inducers.1 Isavuconazole is a moderate inhibitor of CYP3A4/5, therefore, therapeutic monitoring and dose adjustment of tacrolimus, sirolimus, or cyclosporine may be necessary. Additionally, it induces CYP2B6, requiring caution when co-administered with substrates of this enzyme.1 According to the clinical practice guideline of the Spanish Society of Infectious Diseases and Clinical Microbiology (SEIMC), updated in 2018, both voriconazole and isavuconazole are first-line agents for invasive aspergillosis in hematologic patients, although isavuconazole seems to be better tolerated.2,11,15 Regarding management of mucormycosis, in accordance with the “One World, One Guideline” initiative by the European Confederation of Medical Mycology (ECMM), high-dose liposomal amphotericin B is strongly recommended as first-line therapy, while posaconazole and isavuconazole are recommended as rescue treatments.8
On January 17th, 2019, the Pharmacy and Therapeutics Commission (CFyT) of the Hospital Universitario de La Princesa approved the inclusion of isavuconazole in the hospital's Pharmacotherapeutic Guide for the treatment of invasive aspergillosis in adults and for mucormycosis in patients for whom amphotericin B is not appropriate. Additional indications included cases where voriconazole is not suitable and isavuconazole is preferable due to baseline prolonged QTc or QTc prolongation with voriconazole; moderate to severe renal dysfunction (serum creatinine>2.5mg/dL) requiring intravenous therapy; hepatic enzyme elevations at baseline or during voriconazole treatment, or challenges in therapeutic drug monitoring of voriconazole.
The objective of this study is to characterize the population that has received treatment with isavuconazole during their admission to the hospital, from its inclusion in the hospital's Pharmacotherapeutic Guide (January 17th, 2019) until June 2023, and to assess the appropriateness of each prescription based on the clinical indication and the diagnoses documented in the medical records.
MethodsA retrospective observational prescription–indication study was conducted to evaluate prescription–indication appropriateness of isavuconazole. Data were extracted from electronic medical records in the Health Care Information System (HCIS) of Hospital Universitario de La Princesa.
The primary outcome is the proportion of patients with an inappropriate isavuconazole prescription compared to the total number of patients who received this drug, according to the hospital's pharmacotherapeutic guide and with the drug label. To assess inadequacy, the following were considered: indication, therapeutic or prophylactic use, treatment adjustment after microbiological isolation (in cases with isolation), presence of contraindications, and treatment regimen (dose and administration interval).
Inclusion criteria were: patients aged≥18 years of either gender admitted to the Hospital Universitario de La Princesa between January 2019 and June 2023 who received at least one dose of isavuconazole during hospitalization. For patients with multiple admissions involving isavuconazole, only the first episode was considered. Exclusion criteria included: unavailability of medical records in HCIS and isavuconazole initiation prior to January 2019.
All patients were followed from the start of isavuconazole therapy until December 2023. As a result, follow-up ranged from 6 months to 5 years, depending on the treatment start date. Thus, we ensured every patient had at least a 6-month follow-up period. Medical records were reviewed for route of administration, antifungal switching, treatment discontinuation dates, and adverse drug reactions (ADRs). Mortality was analyzed three and six months after initiation of isavuconazole. Overall mortality throughout the study period was also examined.
Invasive fungal infections were categorized as “possible”, “probable”, or “proven” according to the 2020 criteria established by the European Organization for Research and Treatment of Cancer/Mycoses Study Group Education and Research Consortium (EORTC/MSGERC).9 Specific definitions for Intensive Care Unit (ICU) patients were also applied.5 Study subjects were categorized considering predisposing factors, clinical findings (mainly imaging tests), and microbiological evidence (direct visualization, culture growth, or galactomannan positivity in plasma or bronchoalveolar lavage) during isavuconazole treatment (see Supplementary Table S1). The causal relationship between isavuconazole and suspected adverse drug reactions (ADRs) was assessed using the algorithm developed by the Spanish Pharmacovigilance System (SEFV).3
Statistical analysis was performed using SPSS version 29.0.2.0. The Kolmogorov–Smirnov test was applied to assess the normality of quantitative variables, which were then summarized using medians and interquartile ranges (IQR, 25–75th percentile) due to non-Normal distribution. Associations between categorical variables were assessed using the Chi-square test. Statistical significance was set for p-values<0.05.
To evaluate temporal trends in isavuconazole prescription, a time-series analysis was performed using the moving average method and a seasonal decomposition via multiplicative model. Linear regression was applied after adjusting for seasonal variation (see Supplementary Fig. S1).
This study was approved by the Research Ethics Committee for Medicines (CEIm) of Hospital Universitario de La Princesa, which also granted an exemption to the requirement for informed consent.
ResultsA total of 132 patients receiving isavuconazole during their hospitalization between January 2019 and June 2023 were identified. Of these, three patients were excluded from the study: one due to treatment initiation in 2018, and two who had been prescribed isavuconazole in outpatient settings for indications unrelated to posterior hospitalization.
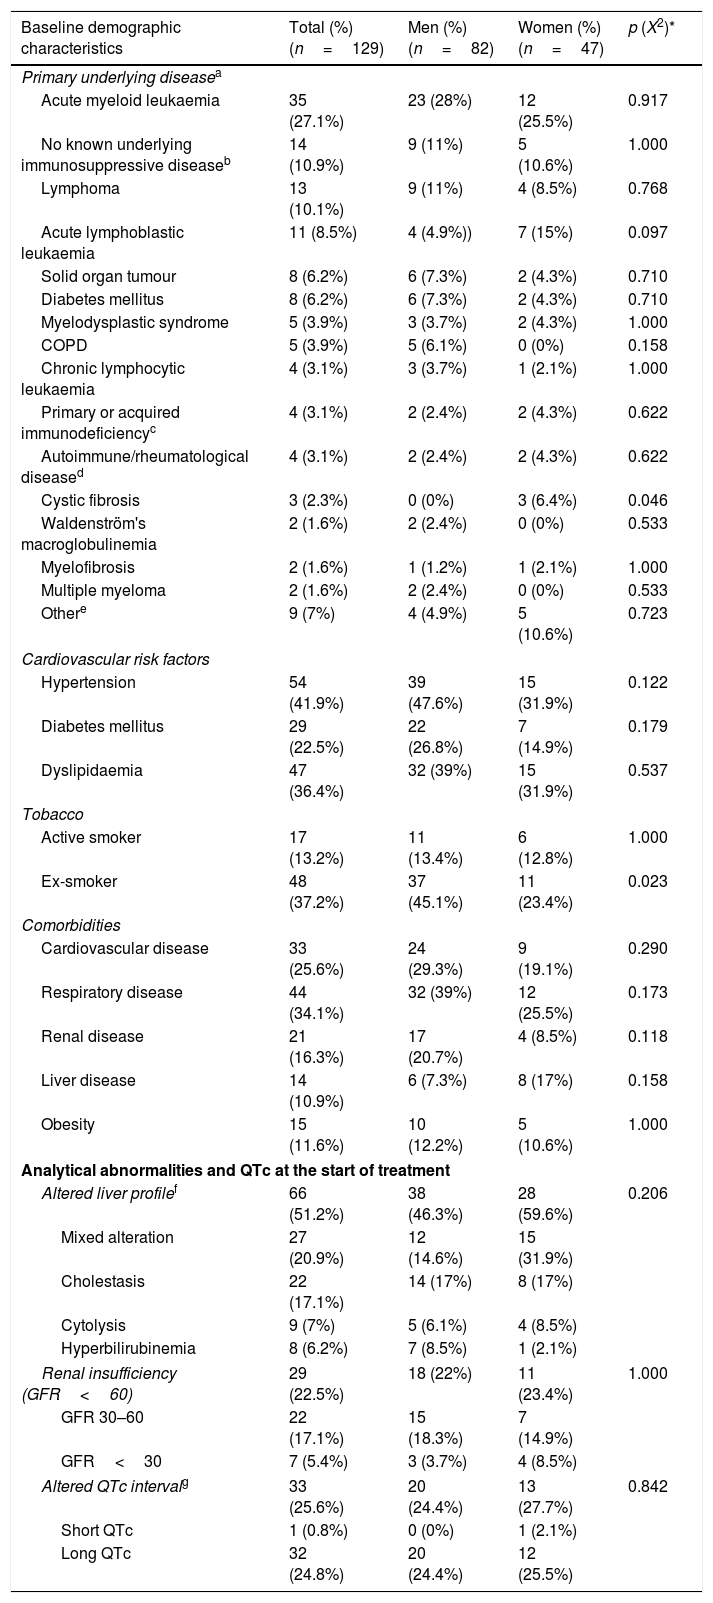
Of the 129 patients finally included in the analysis, 63.6% were male. The median age was 63 (IQR: 50–70), and the median weight was 70kg (IQR: 59–79). Other features of the study population are detailed in Table 1, with no relevant differences between women and men but more ex-smokers among men and more cystic fibrosis among women.
Baseline demographic and clinical data of patients treated with isavuconazole.
| Baseline demographic characteristics | Total (%) (n=129) | Men (%) (n=82) | Women (%) (n=47) | p (X2)* |
|---|---|---|---|---|
| Primary underlying diseasea | ||||
| Acute myeloid leukaemia | 35 (27.1%) | 23 (28%) | 12 (25.5%) | 0.917 |
| No known underlying immunosuppressive diseaseb | 14 (10.9%) | 9 (11%) | 5 (10.6%) | 1.000 |
| Lymphoma | 13 (10.1%) | 9 (11%) | 4 (8.5%) | 0.768 |
| Acute lymphoblastic leukaemia | 11 (8.5%) | 4 (4.9%)) | 7 (15%) | 0.097 |
| Solid organ tumour | 8 (6.2%) | 6 (7.3%) | 2 (4.3%) | 0.710 |
| Diabetes mellitus | 8 (6.2%) | 6 (7.3%) | 2 (4.3%) | 0.710 |
| Myelodysplastic syndrome | 5 (3.9%) | 3 (3.7%) | 2 (4.3%) | 1.000 |
| COPD | 5 (3.9%) | 5 (6.1%) | 0 (0%) | 0.158 |
| Chronic lymphocytic leukaemia | 4 (3.1%) | 3 (3.7%) | 1 (2.1%) | 1.000 |
| Primary or acquired immunodeficiencyc | 4 (3.1%) | 2 (2.4%) | 2 (4.3%) | 0.622 |
| Autoimmune/rheumatological diseased | 4 (3.1%) | 2 (2.4%) | 2 (4.3%) | 0.622 |
| Cystic fibrosis | 3 (2.3%) | 0 (0%) | 3 (6.4%) | 0.046 |
| Waldenström's macroglobulinemia | 2 (1.6%) | 2 (2.4%) | 0 (0%) | 0.533 |
| Myelofibrosis | 2 (1.6%) | 1 (1.2%) | 1 (2.1%) | 1.000 |
| Multiple myeloma | 2 (1.6%) | 2 (2.4%) | 0 (0%) | 0.533 |
| Othere | 9 (7%) | 4 (4.9%) | 5 (10.6%) | 0.723 |
| Cardiovascular risk factors | ||||
| Hypertension | 54 (41.9%) | 39 (47.6%) | 15 (31.9%) | 0.122 |
| Diabetes mellitus | 29 (22.5%) | 22 (26.8%) | 7 (14.9%) | 0.179 |
| Dyslipidaemia | 47 (36.4%) | 32 (39%) | 15 (31.9%) | 0.537 |
| Tobacco | ||||
| Active smoker | 17 (13.2%) | 11 (13.4%) | 6 (12.8%) | 1.000 |
| Ex-smoker | 48 (37.2%) | 37 (45.1%) | 11 (23.4%) | 0.023 |
| Comorbidities | ||||
| Cardiovascular disease | 33 (25.6%) | 24 (29.3%) | 9 (19.1%) | 0.290 |
| Respiratory disease | 44 (34.1%) | 32 (39%) | 12 (25.5%) | 0.173 |
| Renal disease | 21 (16.3%) | 17 (20.7%) | 4 (8.5%) | 0.118 |
| Liver disease | 14 (10.9%) | 6 (7.3%) | 8 (17%) | 0.158 |
| Obesity | 15 (11.6%) | 10 (12.2%) | 5 (10.6%) | 1.000 |
| Analytical abnormalities and QTc at the start of treatment | ||||
| Altered liver profilef | 66 (51.2%) | 38 (46.3%) | 28 (59.6%) | 0.206 |
| Mixed alteration | 27 (20.9%) | 12 (14.6%) | 15 (31.9%) | |
| Cholestasis | 22 (17.1%) | 14 (17%) | 8 (17%) | |
| Cytolysis | 9 (7%) | 5 (6.1%) | 4 (8.5%) | |
| Hyperbilirubinemia | 8 (6.2%) | 7 (8.5%) | 1 (2.1%) | |
| Renal insufficiency (GFR<60) | 29 (22.5%) | 18 (22%) | 11 (23.4%) | 1.000 |
| GFR 30–60 | 22 (17.1%) | 15 (18.3%) | 7 (14.9%) | |
| GFR<30 | 7 (5.4%) | 3 (3.7%) | 4 (8.5%) | |
| Altered QTc intervalg | 33 (25.6%) | 20 (24.4%) | 13 (27.7%) | 0.842 |
| Short QTc | 1 (0.8%) | 0 (0%) | 1 (2.1%) | |
| Long QTc | 32 (24.8%) | 20 (24.4%) | 12 (25.5%) | |
COPD, chronic obstructive pulmonary disease; GFR, glomerular filtration rate; QTc, QT interval corrected using the Bazett formula.
Includes 14 patients with Covid-19 pneumonia but without an immunosuppressive disease that could act as a risk factor for invasive fungal infection.
Patients with rheumatoid arthritis, scleroderma, overlap syndrome of myopathy/scleroderma, thyroiditis, and atrophic gastritis.
Other: 9 patients with one of the following: chronic pulmonary aspergillosis, asthma and recurrent bronchitis, POEMS syndrome, acute leukaemia with mixed phenotype, tuberous sclerosis, recurrent acute cholangitis, T prolymphocytic leukaemia, erythroleukemia, and polytrauma.
Cholestasis: elevation of gamma-glutamyl transferase (GGT) and alkaline phosphatase (ALP)+/- bilirubin above the upper limit of normal (ULN). Cytolysis: elevation of liver transaminases above the ULN. Hyperbilirubinemia: elevation of bilirubin (total, direct, or indirect) above the ULN. Mixed alteration: combination of any of the previous analytical alterations.
The most frequent underlying conditions were malignant haematological diseases (77%). Respiratory comorbidities were present in 44 patients (34.1%) and 33 patients (25.6%) suffered from cardiovascular disease. Liver enzyme abnormalities were observed in 51.2% of patients at baseline, while renal impairment was present in 22.5% (Table 1). Fifty-seven patients (44.2%) required admission to the intensive care unit (ICU). Notably, COVID-19 pneumonia was diagnosed in 10.9% of patients without any classical immunosuppressive condition. Overall, 38.8% of patients were diagnosed with SARS-CoV-2 respiratory infection during hospitalization.
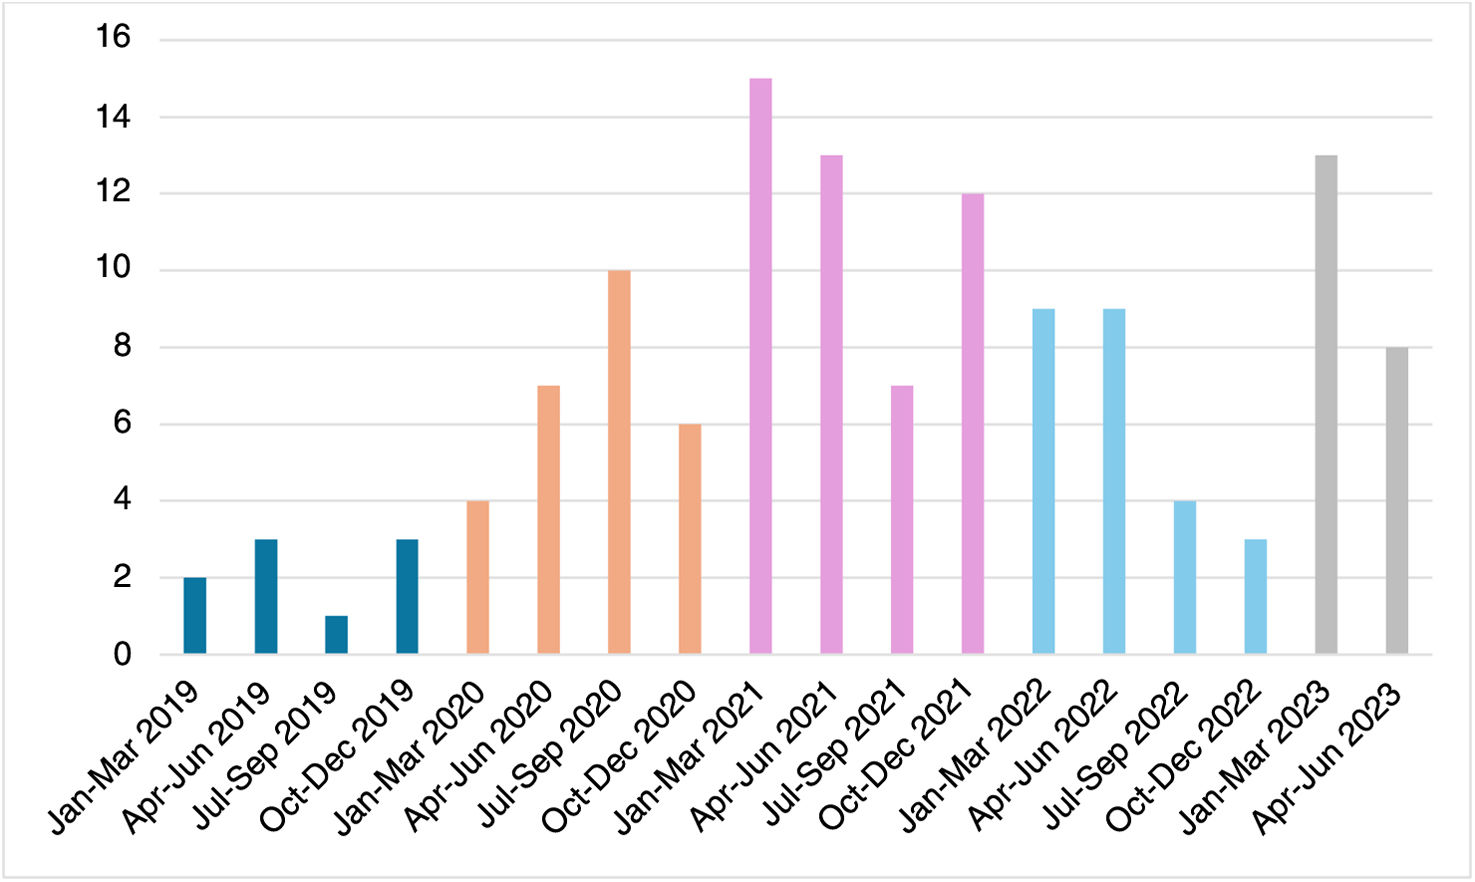
Temporal evolution of isavuconazole prescriptions is detailed in Fig. 1 and Supplementary material Fig. S1A. Although there were certain temporal fluctuations, a slight upward trend in isavuconazole prescriptions was observed following its inclusion in the hospital's Pharmacotherapeutic Guide. This trend fitted a linear regression model (p=0.042), although the goodness of fit was very low (R2=0.08).

The median duration of hospitalization was 35 days (IQR: 20–62). The most common reason for admission was SARS-CoV-2 respiratory infection (25.6%). A total of 17.8% of admissions were scheduled for chemotherapy administration, hematopoietic stem cell transplantation, or surgery (see Supplementary Table S2).
The characteristics of fungal infections that emerged during hospitalization are detailed in Supplementary Table S3; six patients had proven IFI, 19 had probable IFI, and 33 had possible IFI, according to the 2020 EORTC/MSGERC criteria (12) (Supplementary Table S1). Among patients who did not fulfil EORTC/MSGERC IFI criteria, 14 received isavuconazole as antifungal prophylaxis, and two as empirical treatment for suspected meningitis. The remaining 55 patients did not meet the predefined IFI definitions, but were given empirical isavuconazole therapy due to persistent fever or pneumonia lasting more than 4 days despite appropriate antibiotic coverage, combined with risk factors for IFI. Of these, 28 (50.9%) had SARS-CoV-2 pneumonia, predominantly during 2020 and 2021. The lower respiratory tract was the most common site of suspected or confirmed IFI (76%). Cultures were performed on samples obtained from 105 patients. Microbiological isolates were recovered in 40 patients. The most frequently isolated pathogen was Aspergillus fumigatus, identified in 20 patients (see Supplementary Table S3).
The median duration of isavuconazole therapy was 14 days (IQR: 5–36), and seven patients (5.4%) exceeded the maximum recommended treatment duration of 6 months as stated in the drug label. In 56 cases (43.4%), treatment was discontinued due to low suspicion of fungal infection or favourable clinical progression. Death or limitation of therapeutic effort was the second most common reason for treatment discontinuation (36 patients, 27.9%) (see Supplementary Table S4). In 30 patients (23.3%) isavuconazole was switched to another antifungal. The most common reason for switching was the need to initiate antifungal prophylaxis after ruling out active fungal infection or after liver function improvement (10 patients), for which posaconazole was primarily used (9 out of 10 patients). Anidulafungin was selected in all six cases of hepatic or renal toxicity during isavuconazole treatment. Voriconazole was the drug of choice in cases of intravenous isavuconazole shortages with difficulty in using the oral route (five patients, four of whom switched to voriconazole) (see Supplementary Table S5).
Regarding the dosing regimen, six patients did not receive a loading dose, and other two patients received a lower-than-recommended loading dose. Seventeen patients (13.2%) were treated exclusively with the loading dose for 48h with treatment discontinued shortly thereafter due to death or limited therapeutic effort (n=6), or low clinical suspicion of IFI (n=4) (see Supplementary Table S6). In three cases, maintenance dosing deviated from label recommendations. The intravenous route was the most common method of initial administration (69%). Additionally, 30 patients (23.3%) underwent a switch in the route of administration during hospitalization. After discharge, 36 patients (27.9%) continued treatment with oral isavuconazole.
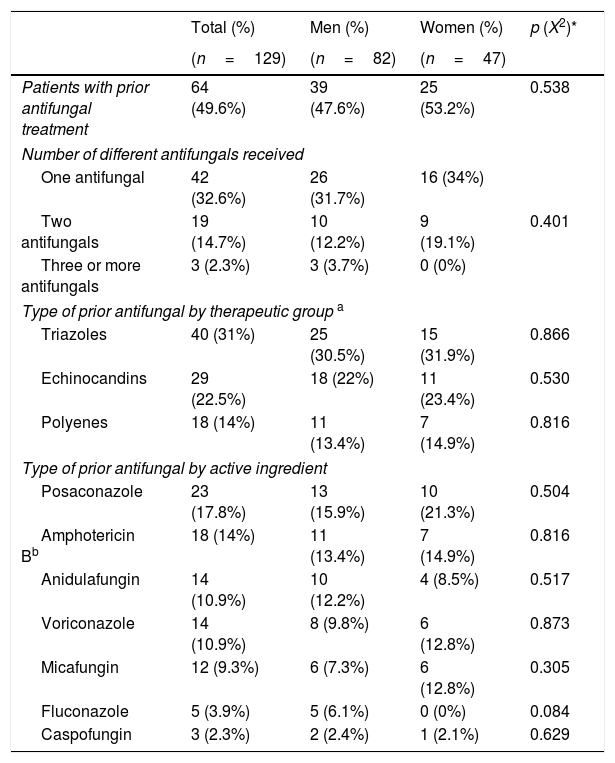
Nearly 50% of the patients (64 patients) had received at least one antifungal in the previous month, and 17.1% (22 patients) had been exposed to more than one antifungal. The most frequently administered antifungal was posaconazole (17.8%), followed by amphotericin B (14%) (Table 2). The main reasons for previous treatment discontinuation are exposed in Supplementary Table S7.
Prescription of antifungals in the month prior to treatment with isavuconazole.
| Total (%) | Men (%) | Women (%) | p (X2)* | |
|---|---|---|---|---|
| (n=129) | (n=82) | (n=47) | ||
| Patients with prior antifungal treatment | 64 (49.6%) | 39 (47.6%) | 25 (53.2%) | 0.538 |
| Number of different antifungals received | ||||
| One antifungal | 42 (32.6%) | 26 (31.7%) | 16 (34%) | |
| Two antifungals | 19 (14.7%) | 10 (12.2%) | 9 (19.1%) | 0.401 |
| Three or more antifungals | 3 (2.3%) | 3 (3.7%) | 0 (0%) | |
| Type of prior antifungal by therapeutic group a | ||||
| Triazoles | 40 (31%) | 25 (30.5%) | 15 (31.9%) | 0.866 |
| Echinocandins | 29 (22.5%) | 18 (22%) | 11 (23.4%) | 0.530 |
| Polyenes | 18 (14%) | 11 (13.4%) | 7 (14.9%) | 0.816 |
| Type of prior antifungal by active ingredient | ||||
| Posaconazole | 23 (17.8%) | 13 (15.9%) | 10 (21.3%) | 0.504 |
| Amphotericin Bb | 18 (14%) | 11 (13.4%) | 7 (14.9%) | 0.816 |
| Anidulafungin | 14 (10.9%) | 10 (12.2%) | 4 (8.5%) | 0.517 |
| Voriconazole | 14 (10.9%) | 8 (9.8%) | 6 (12.8%) | 0.873 |
| Micafungin | 12 (9.3%) | 6 (7.3%) | 6 (12.8%) | 0.305 |
| Fluconazole | 5 (3.9%) | 5 (6.1%) | 0 (0%) | 0.084 |
| Caspofungin | 3 (2.3%) | 2 (2.4%) | 1 (2.1%) | 0.629 |
Number of patients who received at least one antifungal within each therapeutic group. Patients in the same group who received two or more antifungals (e.g., posaconazole and voriconazole) are counted as a single entry in that group.
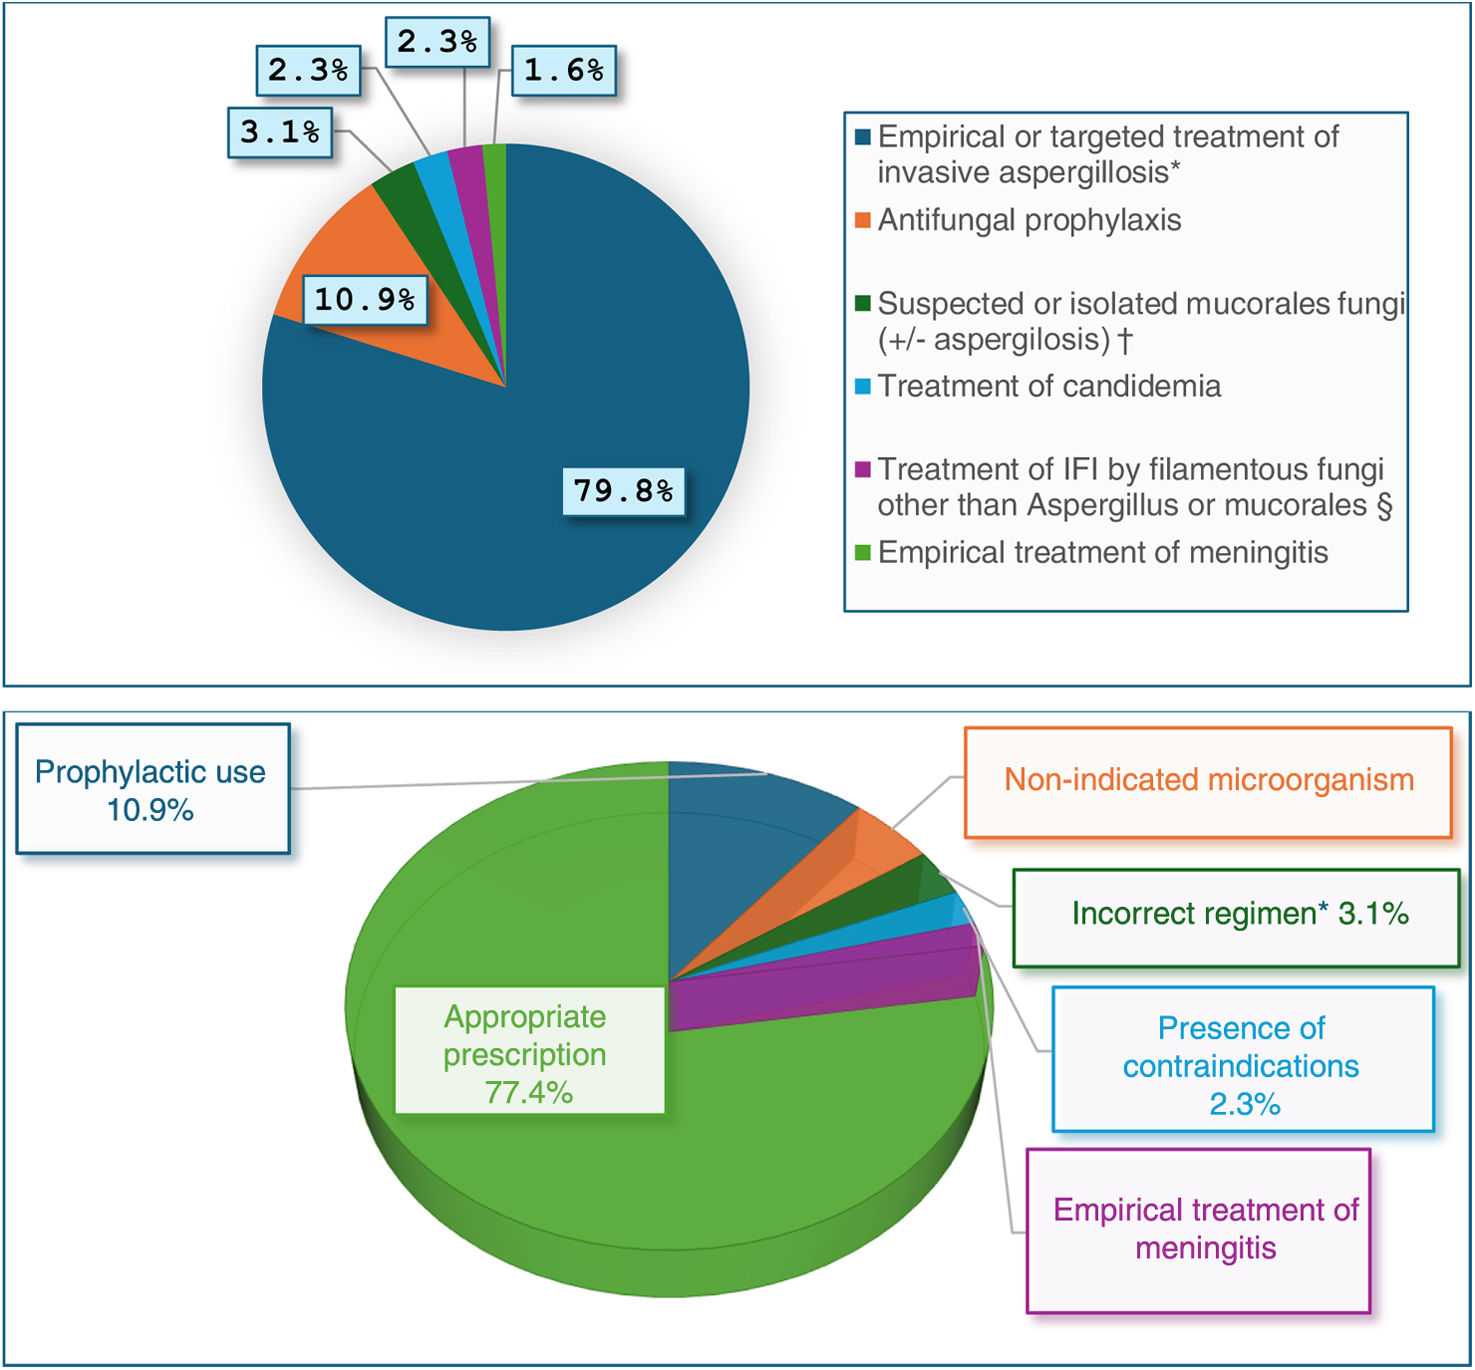
The reasons for isavuconazole prescription are detailed in Fig. 2A. Of the 129 patients included, 115 (89.1%) received isavuconazole as empirical or targeted treatment for suspected or confirmed fungal infections, while 14 patients (10.9%) received it as prophylaxis. Of these patients, seven were admitted to hospital to initiate chemotherapy and one to undergo a programmed surgery. Among the other six patients, three were diagnosed with graft-versus-host disease (GVHD), one had fever of unknown origin, another patient suffered Sweet syndrome, and the last one was admitted for the study of new onset aphasia.

(A) Reasons for prescribing isavuconazole. Reasons for prescribing isavuconazole during hospitalization. *Includes cases of “proven”, “probable”, and “possible” aspergillosis, as well as those that did not meet EORTC/MSGERC 2020 criteria but presented fever or pneumonia for more than 4 days without response to antibiotic treatment and had risk factors for developing an invasive fungal infection (IFI). † One patient with a mucorales isolate, one patient with both mucorales and Aspergillus isolates, two patients with suspected mucormycosis or aspergillosis, but with no fungal isolations. § Exophiala dermatitidis, Scedosporium apiospermum, Sarocladium strictum. (B) Reasons considered inappropriate for prescribing isavuconazole. *Incorrect regimen: includes patients with an appropriate indication for isavuconazole who did not follow the treatment regimen recommended in the drug label. One patient had two reasons for inadequate use: prophylactic use and incorrect regimen; this patient was classified under the “prophylactic use” group.
The percentage of inappropriate prescriptions was 22.5% (29 patients) (95% CI: 15.2–29.8%). Fig. 2B illustrates the underlying factors contributing to prescription inadequacy. Regarding temporal evolution of prescription inadequacy, fluctuations were observed over the study period without a clear trend (p=0.991 in the linear regression model) (Fig. 3 and Supplementary Fig. S1).
In fifty-seven patients (44.2%) the use of isavuconazole instead of voriconazole for invasive aspergillosis treatment was justified due to baseline prolonged QTc or QTc prolongation with voriconazole (27 patients), elevated transaminases at treatment initiation (25 patients), history of voriconazole toxicity (13 patients), and moderate-to-severe renal impairment requiring intravenous therapy (9 patients). (Note: 16 patients met more than one criterion). Among the remaining 50 patients, 46 received isavuconazole as an alternative to voriconazole without a clear justification, and in four patients it was used due to suspected mucormycosis. These cases were also considered appropriate based on clinical context.
A total of 18 suspected ADRs related to isavuconazole were identified. Applying the SEFV algorithm, five cases were classified as “probable”, eight as “possible”, two as “conditional or unlikely”, and three as “unrelated”. Based on this classification, 13 patients (10.1%) experienced ADRs potencially related to isavuconazole: abnormal liver biochemical tests (eight patients, 6.2%), skin rash (two patients, 1.6%), dyspepsia, visual hallucinations, and acute kidney injury (one patient each, 0.8%). In total, seven ADR cases led to treatment discontinuation: four due to abnormal liver biochemical tests and three due to skin rash, dyspepsia, or renal toxicity (one each). Potential pharmacological interactions involving isavuconazole were identified (see Supplementary Table S8). No interactions had clinical consequences except for one case of pneumonitis attributed to ibrutinib.
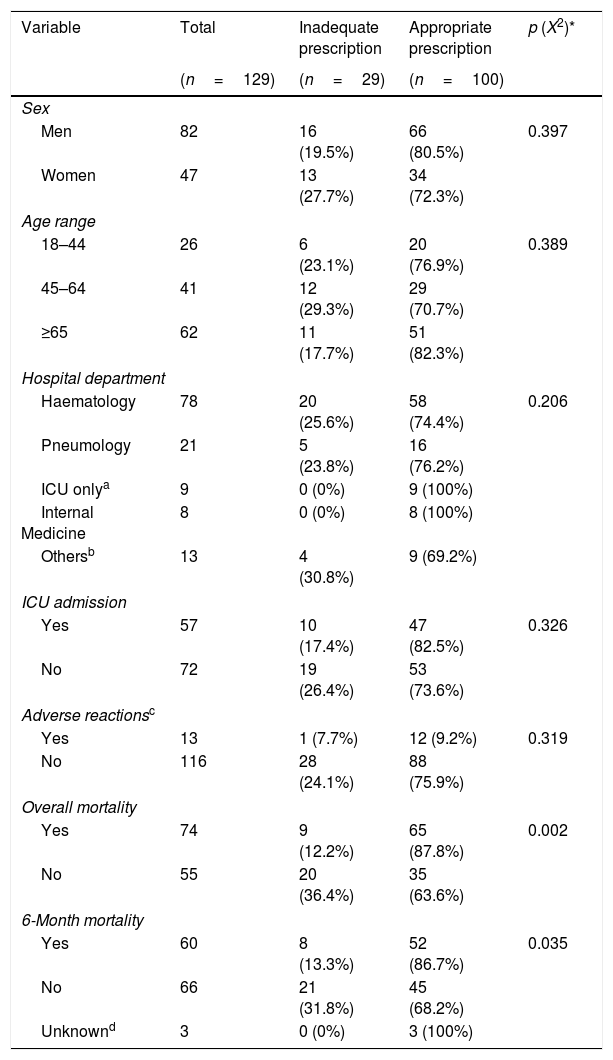
Mortality and prescription inadequacyOverall mortality among the study population was 57.4% (74 patients). A total of 42 patients (32.6%) died during hospitalization, while the remaining 87 were discharged home or transferred to another facility. The highest number of deaths (23 patients) occurred in 2021. Hematologic malignancies (and complications related to their treatment) were the primary cause of death in more than half of the deceased patients (59.5%). Additionally, the most common immediate cause of death was COVID-19 pneumonia, primarily in 2021 (24.3% of total deaths, 56.5% of deaths in 2021) (see Supplementary Table S9). The three-month mortality rate following the initiation of isavuconazole was 38% (49 patients), and the six-month mortality was 46.5% (60 patients). Temporal trends in mortality are shown in Fig. 3. No statistically significant associations were found between prescription inappropriateness and sex, age group, or hospital department of admission. Similarly, the occurrence of adverse drug reactions did not differ significantly between appropriate and inappropriate prescription groups. Nevertheless, in patients with an inappropriate prescription for isavuconazole, both the six-month mortality rate and the overall mortality rate were found to decrease (Table 3).
Analysis of prescription inadequacy.
| Variable | Total | Inadequate prescription | Appropriate prescription | p (X2)* |
|---|---|---|---|---|
| (n=129) | (n=29) | (n=100) | ||
| Sex | ||||
| Men | 82 | 16 (19.5%) | 66 (80.5%) | 0.397 |
| Women | 47 | 13 (27.7%) | 34 (72.3%) | |
| Age range | ||||
| 18–44 | 26 | 6 (23.1%) | 20 (76.9%) | 0.389 |
| 45–64 | 41 | 12 (29.3%) | 29 (70.7%) | |
| ≥65 | 62 | 11 (17.7%) | 51 (82.3%) | |
| Hospital department | ||||
| Haematology | 78 | 20 (25.6%) | 58 (74.4%) | 0.206 |
| Pneumology | 21 | 5 (23.8%) | 16 (76.2%) | |
| ICU onlya | 9 | 0 (0%) | 9 (100%) | |
| Internal Medicine | 8 | 0 (0%) | 8 (100%) | |
| Othersb | 13 | 4 (30.8%) | 9 (69.2%) | |
| ICU admission | ||||
| Yes | 57 | 10 (17.4%) | 47 (82.5%) | 0.326 |
| No | 72 | 19 (26.4%) | 53 (73.6%) | |
| Adverse reactionsc | ||||
| Yes | 13 | 1 (7.7%) | 12 (9.2%) | 0.319 |
| No | 116 | 28 (24.1%) | 88 (75.9%) | |
| Overall mortality | ||||
| Yes | 74 | 9 (12.2%) | 65 (87.8%) | 0.002 |
| No | 55 | 20 (36.4%) | 35 (63.6%) | |
| 6-Month mortality | ||||
| Yes | 60 | 8 (13.3%) | 52 (86.7%) | 0.035 |
| No | 66 | 21 (31.8%) | 45 (68.2%) | |
| Unknownd | 3 | 0 (0%) | 3 (100%) | |
ICU, intensive care unit.
To compare prescription inadequacy by hospital admission department, only patients who were admitted exclusively to the ICU and not to other departments are considered. Differences in prescriptions are analyzed separately between patients who required ICU admission at any point during this episode (regardless of whether they were also admitted to other departments) and patients who did not require ICU admission.
Others: Medical Oncology (4 patients), Neurology (3 patients), Recovery (2 patients), Thoracic Surgery (1 patient), Radiation Oncology (1 patient), Rheumatology (1 patient), Traumatology (1 patient).
Adverse reactions related to isavuconazole according to the algorithm of the Spanish Pharmacovigilance System.
In this study, the rate of inappropriate isavuconazole prescription was relatively low (22.5%; 95% CI: 15–30%). These results differ considerably from the systematic review by Reslan et al.,19 where the proportion of inappropriate antifungal prescriptions in hospitalized patients exceeded 50% in all articles, except for one by Berking et al.,6 which reported a 25% inappropriateness rate. It is noteworthy that this latter study, like ours, focused on a single antifungal agent (posaconazole) and used institutional guidelines rather than the international ones for evaluation. Furthermore, in our analysis, moderate or severe potential drug interactions are not considered an inappropriateness criterion due to ongoing debate about their clinical significance and the lack of standardized thresholds for defining inappropriateness in this context.19 By contrast, Reslan et al.19 did include potential drug interactions, which accounted for 2–38% of inappropriately prescribed antifungals in their review. This methodological difference may explain part of the discrepancy in reported rates.
The highest number of prescriptions occurred in 2021, which coincided with the peak incidence of COVID-19. Additionally, 14 patients (10.9%) who received isavuconazole had severe COVID-19 pneumonia without any other classic risk factor (causing immunosuppression) for developing an IFI, a finding consistent with recent literature, as most cases of COVID-19-associated pulmonary aspergillosis (CAPA) have been described in immunocompetent individuals.12 In recognition of this, severe SARS-CoV-2 infection was included in the 2020 “EORTC-MSGERC Intensive Care Working Group” definitions as a new predisposing factor in ICU patients for developing invasive aspergillosis.5 However, the presence of CAPA is difficult to assess since it often presents with nonspecific clinical and radiological findings, complicating the selection of patients for antifungal therapy.12
The 3-month mortality rate in our cohort (38%) exceeded that observed in the SECURE trial (28.3% at day 84).15 Several factors may explain this discrepancy: a) clinical trial inclusion criteria are stricter, so patients with liver dysfunction or moderate-to-severe renal disease were excluded, as well as those who did not meet the EORTC/MSGERC IFI definitions (in this study, only 45% of patients who received isavuconazole met the IFI criteria); b) SARS-CoV-2 pneumonia, which was absent during the SECURE trial period, was a major contributor to morbidity and mortality in our population. Interestingly, lower mortality was observed among patients whose isavuconazole prescriptions were deemed inappropriate. This seemingly paradoxical result is likely due to the fact that the most frequent reason for inappropriateness was prophylactic use. These patients were probably less severely ill at baseline, which may explain their better outcomes. Besides, most patients who received isavuconazol as treatment were hospitalized with severe acute infections such as pneumonia or sepsis, which were not present in the prophylaxis group at the time of isavuconazol administration.
Isavuconazole possesses several pharmacological advantages over other azoles contributing to its growing appeal in both prophylactic and therapeutic settings. Unlike most triazoles, it does not prolong the QTc interval and may even shorten it. Additionally, isavuconazole exhibits superior tolerability compared to voriconazole, with fewer clinically significant drug-drug interactions, as well as a linear, more predictable pharmacokinetics. Indeed, therapeutic drug monitoring is generally not recommended, although further pharmacokinetic studies are warranted in specific populations, such as patients receiving renal replacement therapy, extracorporeal circulation, or those who are obese or paediatric.14
Resistance to triazole antifungals is a well-recognized concern. In Aspergillus spp., alterations in the Cyp51A gene represent the most frequently reported mechanism and may confer cross-resistance to other azoles.21 It is important to note that susceptibility to isavuconazole varies among Mucorales species; therefore, it is advisable to perform species identification and antifungal susceptibility testing.7 Additionally, prolonged antifungal exposure in hospitalized patients may promote resistance, representing a significant challenge given the limited therapeutic options and the immunocompromised status of many affected patients.
Cost-effectiveness analyses have also been conducted, as the acquisition cost of isavuconazole in Spain (€12,000–13,000 per patient) is higher than that of voriconazole (€7000–8000), the main alternative for aspergillosis.4 However, an economic evaluation by Azanza et al.4 reported a cost-utility ratio of €11,734.79 per QALY, below the commonly accepted willingness-to-pay threshold of €25,000. Similar results have been observed in other countries, supporting the use of isavuconazole instead of voriconazole in patients with suspected invasive aspergillosis prior to pathogen identification.4 Although isavuconazole has demonstrated in vitro activity against most Candida species, it failed to meet non-inferiority criteria compared to caspofungin in the ACTIVE trial for candidemia and invasive candidiasis.13 Consequently, its use for these infections is not currently approved as first-line therapy.1,2 Despite this, 2.3% of patients in our cohort received isavuconazole for the treatment of candidiasis.
As limitations we should mention that this study may be subject to information bias due to its retrospective observational design. Second, it is a single-centre study, reflecting clinical practice in a very specific setting, which may limit its external validity. Additionally, follow-up duration varied across patients, although all were monitored for at least 6 months. Finally, comparison with voriconazole is biased, as only patients in whom voriconazole was discontinued were included, rather than all patients receiving voriconazole.
ConclusionsThe degree of inappropriate prescription of isavuconazole found in this study is relatively low (15–30%) compared to previously reported antifungal stewardship studies. Additionally, the frequency of prescription has not increased significantly over the years, although the trend is slightly upward. While adherence to both local and international prescription guidelines remains suboptimal, our findings reflect a reasonable integration of isavuconazole into the hospital's therapeutic repertoire.
On the other hand, the observed rate of inappropriateness – predominantly linked to prophylactic use – highlights the need for continued stewardship efforts and clearer guidance regarding antifungal use in emerging clinical contexts, such as COVID-19-associated pulmonary aspergillosis.
Contribution to scientific literatureIn this study we assess patterns of isavuconazole use in real clinical practice. We found uncertainty among physicians concerning the indications of this drug. Covid-19 pneumonia acted both as a risk and a confounding factor for aspergillosis.
The followings are the supplementary data to this article:




