



The posterolateral (PL) column is often the most difficult one to access and manage in tibial plateau fractures. Although multiple approaches have been described, many provide limited flexibility to address diverse fracture patterns. The Versatile Extended Anterolateral (EAL) Approach with four progressive windows has been previously introduced within the Main Deformity Direction (MDD) framework. In this cadaveric study, we provide a detailed anatomical and technical description of this modified approach, characterized by an optimized skin incision and four stepwise deep windows for PL column management. The primary aim was to assess the technical feasibility of this approach. Potential reduction and fixation options associated with each window were also explored descriptively.
Materials and methodsFour fresh-frozen cadaveric specimens were used to evaluate surgical exposure and relationships with relevant anatomical structures. Based on the anatomical exposure achieved with each window, potential reduction and fixation strategies were explored descriptively. Representative clinical cases were included to illustrate fixation techniques.
ResultsThe skin incision allowed access to all windows, achieving safe progressive PL column exposure. The four windows (pre-fibular, supra-fibular, retro-fibular, trans-fibular) expanded reduction and fixation possibilities stepwise. The trans-fibular window enabled complete articular and metaphyseal exposure. The anterior tibial artery crossing, located at a mean of 3.5cm from the tip of the fibular head, represented the distal anatomical limit of posterior exposure.
ConclusionThe versatile EAL Approach is a feasible option for managing lateral and PL columns in tibial plateau fractures. Its progressive four-window strategy may allow tailored exposure and fixation according to fracture-specific requirements.
La columna posterolateral (PL) es con frecuencia la más difícil de abordar y manejar en las fracturas de meseta tibial. Aunque se han descrito múltiples abordajes, muchos ofrecen una flexibilidad limitada para adaptarse a distintos patrones de fractura. El abordaje Anterolateral Extendido Versátil (EAL) con cuatro ventanas progresivas ha sido previamente introducido dentro del marco conceptual del Main Deformity Direction (MDD). En este estudio cadavérico presentamos una descripción anatómica y técnica detallada de este abordaje modificado, caracterizado por una incisión cutánea optimizada y cuatro ventanas profundas progresivas para el manejo de la columna PL. El objetivo principal fue evaluar la viabilidad técnica del abordaje. Además, se exploraron de forma descriptiva las posibles opciones de reducción y fijación asociadas a cada ventana.
Material y métodosSe utilizaron cuatro especímenes cadavéricos frescos congelados para evaluar la exposición quirúrgica y las relaciones con las estructuras anatómicas relevantes. En función de la exposición anatómica obtenida con cada ventana, se exploraron de forma descriptiva las posibles estrategias de reducción y fijación. Se incluyeron casos clínicos representativos para ilustrar las técnicas de fijación.
ResultadosLa incisión cutánea permitió el acceso a todas las ventanas, logrando una exposición progresiva y segura de la columna PL. Las cuatro ventanas (pre-fibular, supra-fibular, retro-fibular y trans-fibular) ampliaron de forma escalonada las posibilidades de reducción y fijación. La ventana trans-fibular permitió una exposición articular y metafisaria completa. El cruce de la arteria tibial anterior, situado a una distancia media de 3,5cm desde la punta de la cabeza del peroné, representó el límite anatómico distal de la exposición posterior.
ConclusiónEl abordaje EAL Versátil es una opción factible para el manejo de las columnas lateral y PL en fracturas de meseta tibial. Su estrategia progresiva de cuatro ventanas puede permitir adaptar la exposición y la fijación a las características específicas de la fractura.
The posterolateral (PL) column is often one of the most difficult areas to access and manage in tibial plateau fractures.1–5 Anatomical structures, especially the fibular head, lateral collateral ligament, common peroneal nerve, lateral sural cutaneous nerve, and the anterior tibial artery, may significantly limit surgical exposure and pose a potential risk of iatrogenic injury during surgery.3–6 On the other hand, the biomechanical and structural importance of the PL column makes an appropriate surgical approach and strategy necessary to achieve anatomical reduction and stable fixation of this column.1,2,4,5,7–9
Multiple approaches and options have been described for managing this complex PL column.2–4 These strategies include extended anterolateral approaches with lateral plates in the most posterior aspect of the lateral tibia,10–12 intra-articular osteotomy of the lateral column,12–14 supra-fibular rim plating,15,16 direct posterolateral approaches,17,18 posterolateral windows through lateral approaches,19,20 fibular osteotomy (neck21–24 or partial head25,26), lateral femoral epicondyle osteotomy,27–31 deep posteromedial interval approaches,32,33 and posterior approaches between gastrocnemius.34–37
However, PL column fractures may present heterogeneous requirements, making the choice of surgical strategy challenging. There is no single optimal technique for all cases, and the precise indications remain controversial.2,4,5,8,33,38,39 In this regard, many current approaches offer limited flexibility to accommodate different technical options for managing the PL column.4 Consequently, adopting a flexible approach that allows deep exposure according to the specific requirements of each fracture may offer significant advantages.2 Within a previously proposed fracture-specific strategy based on the Main Deformity Direction (MDD) concept, a Versatile Extended Anterolateral (EAL) Approach with progressive windows was introduced to address both the lateral and PL columns.2
In the present study, we provide a detailed cadaveric anatomical and technical description of this modified approach, defining an optimized single skin incision and considering four deep progressive windows (pre-fibular, supra-fibular, retro-fibular, and trans-fibular) for managing the PL column according to fracture-specific requirements.2 The primary aim of the study was to assess the technical feasibility of this approach. Potential reduction and fixation options associated with each progressive window were also explored descriptively.
Material and methodsCadaveric studyFour fresh-frozen cadaveric specimens (entire leg from groin to foot) were selected for detailed anatomical and technical study. All specimens were adult; three were female and one was male, with two left legs and two right legs. The average age at death was 86 (range 83–92) years. Exclusion criteria were previous knee surgeries or documented injuries, poor preservation conditions and skin abnormalities. Cadaveric dissections and observations were performed by two orthopaedic surgeons with experience in anatomic dissections. For this anatomical study, all specimens were positioned in the prone semi-lateral position because it represents the preferred fixed position in complex multi-columnar PL-MDD fractures.2 Relevant anatomical structures at each step were evaluated and photographed. The skin incision was assessed with respect to any limitation in performing the four deep windows or recognizing key anatomical structures. Relationships with cutaneous, deep neurovascular and other relevant structures were evaluated. The distance from the tip of the fibular head to the anterior tibial artery (ATA) crossing was measured. The potential options for managing the PL column using the different windows of this approach were explored descriptively based on the anatomical exposure achieved with each window or combined windows. Representative clinical case examples were included to illustrate the proposed PL column fixation techniques in clinical practice. Images from a cadaveric specimen (left leg) are provided to illustrate the stepwise procedure of the EAL approach, highlight the relevant anatomic and technical details, and the exposure achieved through each progressive window.
Surgical technique and anatomic details- •
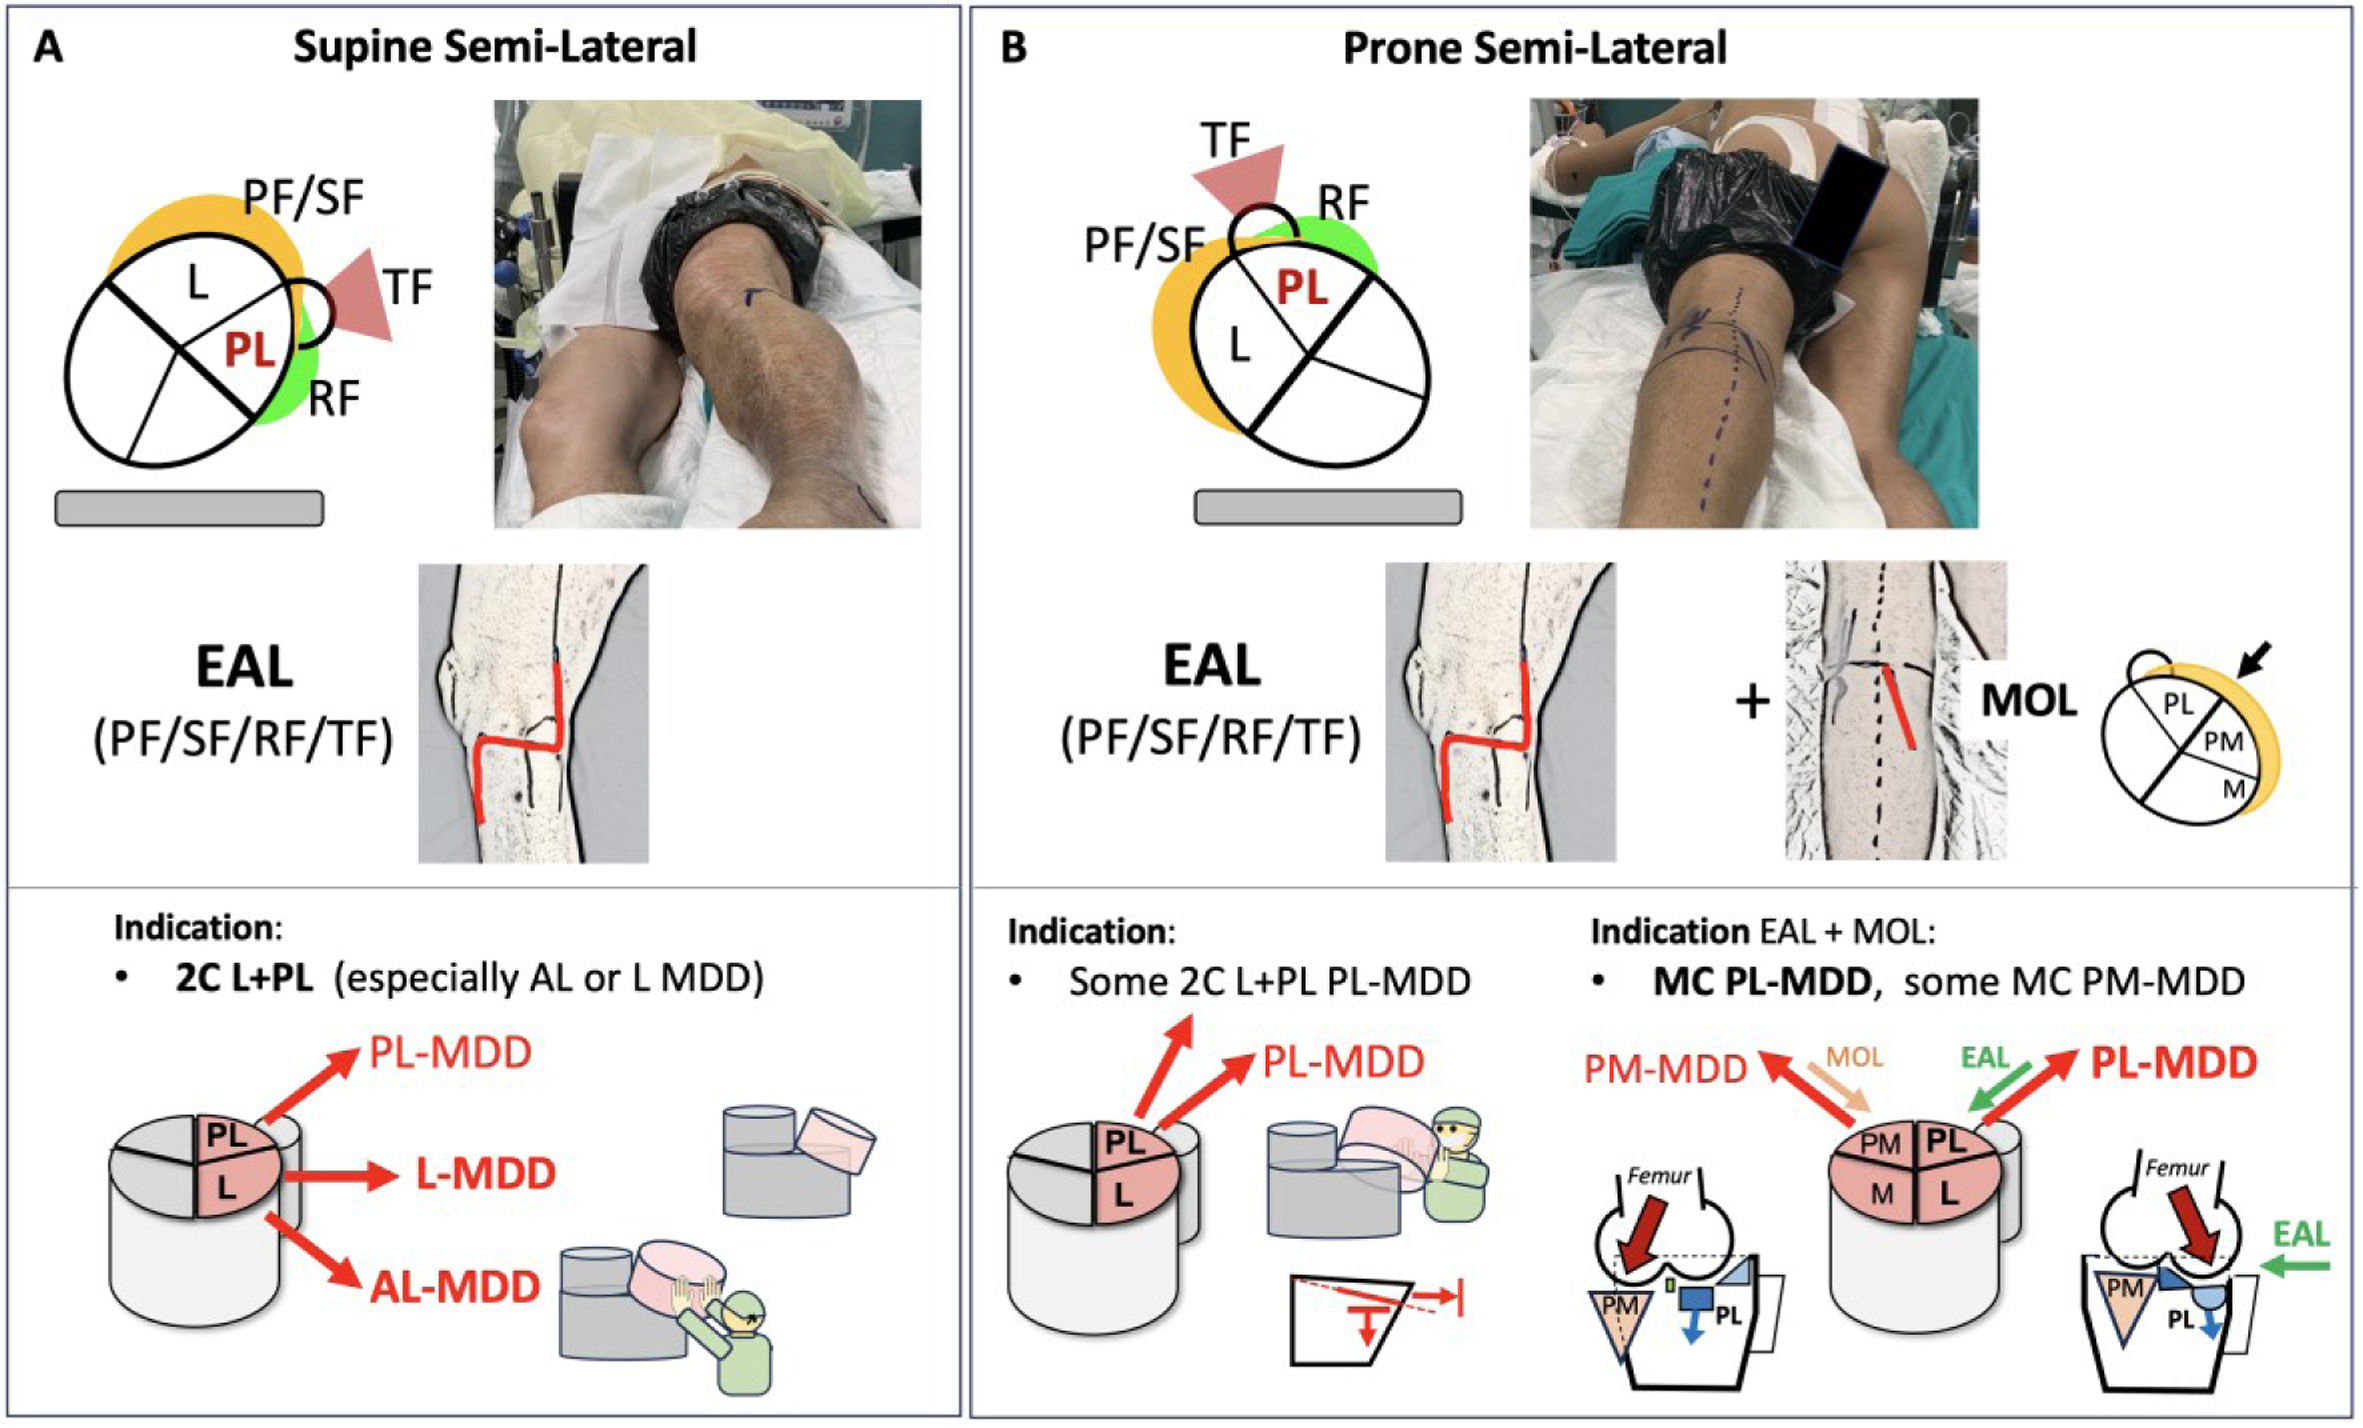
Position: This approach can be performed in two main fixed positions without changing the surgical procedure (Fig. 1). The choice between supine semi-lateral and prone semi-lateral depends on the associated columns and the Main Deformity Direction (MDD), understood as a theoretical vector of global displacement or deformity of the columns in a specific direction2:
- ∘
Supine semi-lateral position2 (Fig. 1A). This position is mainly used in two-column lateral+posterolateral fractures (2C L+PL), especially when the MDD is anterolateral or lateral.
- ∘
Prone semi-lateral position2,33 (Fig. 1B). This position can be useful in some 2C L+PL fractures with PL-MDD (e.g. posterior displacement or angulation) to facilitate reduction of the posterior deformity. The main indication for this fixed position is in multi-columnar fractures (L+PL+PM+/−M) with PL-MDD or PM-MDD,2,40 allowing MDD control and simultaneous global fracture management by combining the EAL Approach with the Modified Oblique Lobenhoffer (MOL) approach.33
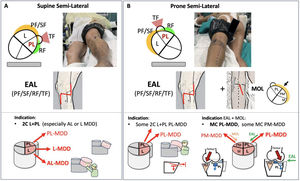 Fig. 1.
Patient fixed positioning for the Versatile Extended Anterolateral (EAL) Approach and main indications for each position (A. Supine semi-lateral. B. Prone semi-lateral). Schematic representations of a left tibial plateau in these positions and the access through each window (PF: pre-fibular; SF: supra-fibular; RF: retro-fibular; TF: trans-fibular) to the lateral (L) and posterolateral (PL) columns. In prone semi-lateral position, the EAL Approach can be combined simultaneously with the Modified Oblique Lobenhoffer (MOL) approach. Diagrams illustrate the relationship between the Main Deformity Direction (MDD), associated PL column deformities and the preferred fixed position to counteract the deformity vector. In complex multicolumnar (MC) PL-MDD fractures, the EAL Approach in prone semi-lateral position may facilitate control of the posterolateral deformity (green arrow). The EAL and MOL approaches can also be complementary for simultaneous management of the PL column in selected multicolumnar fractures.
- ∘
- •
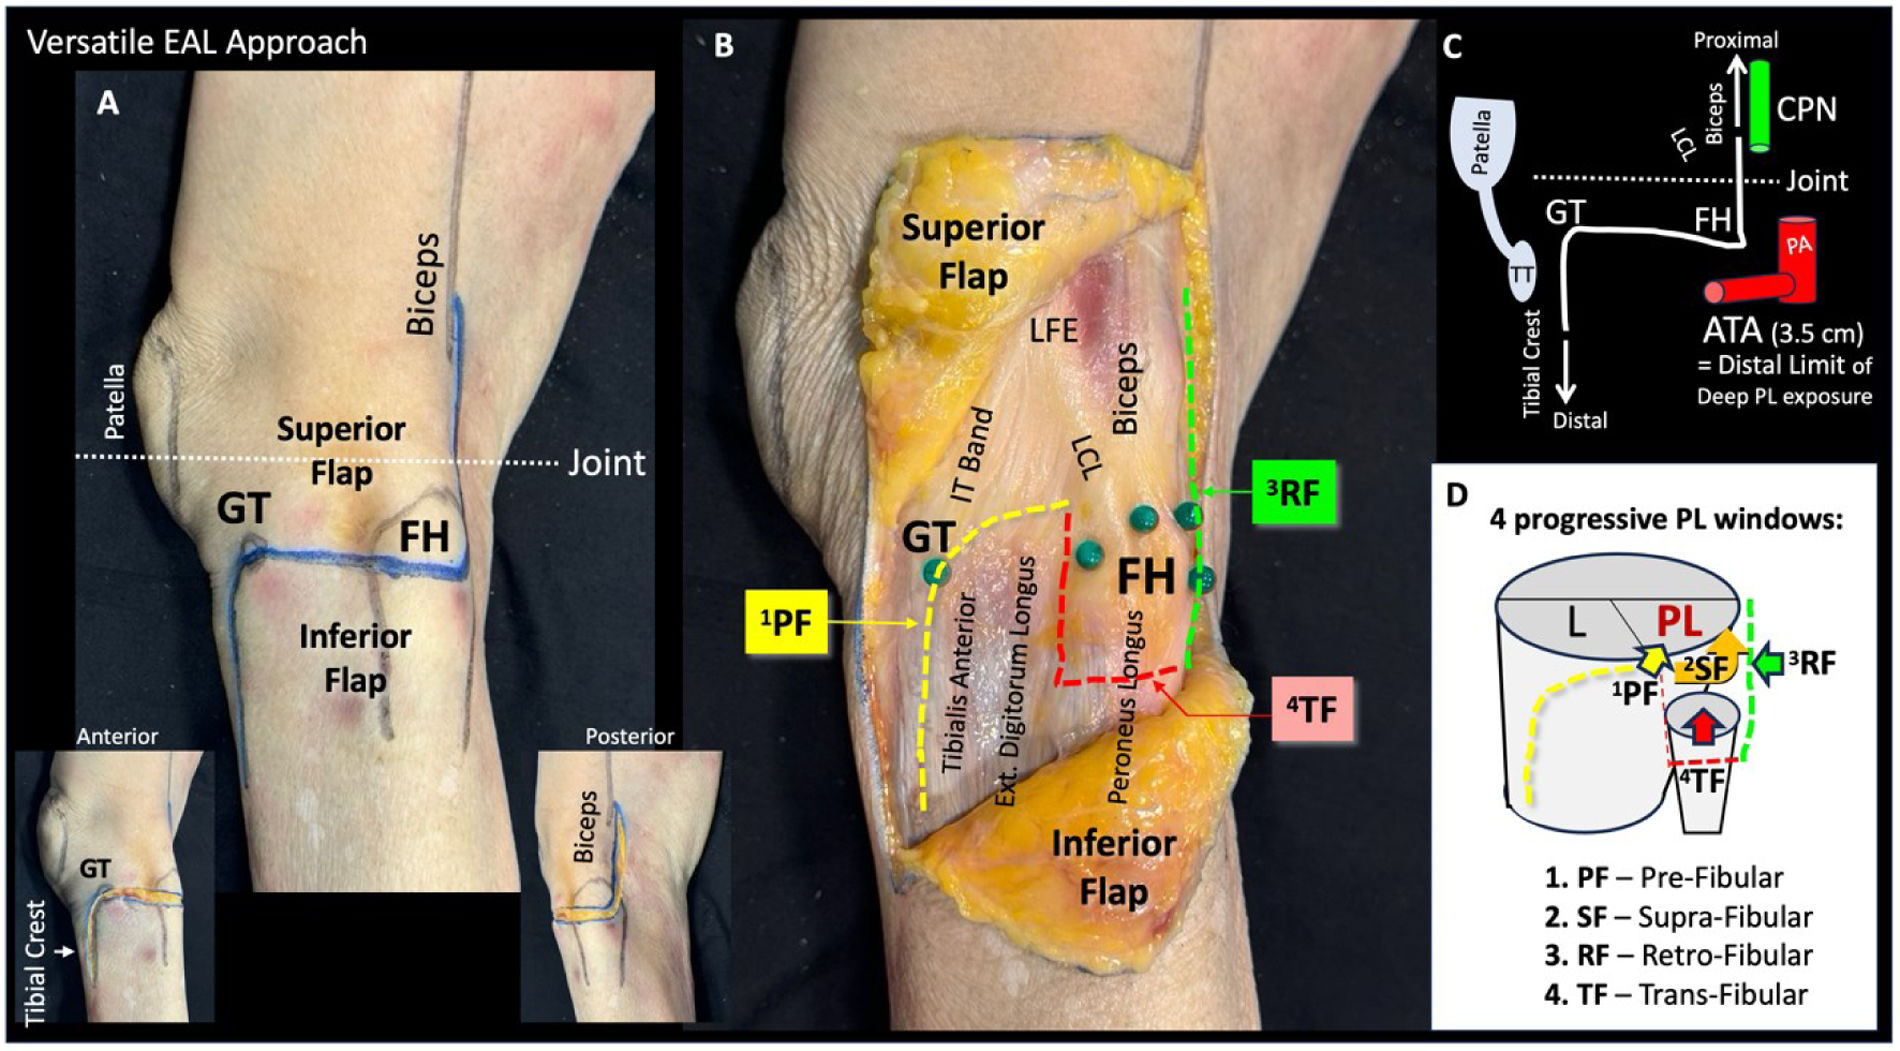
Landmarks and skin incision (modified S-shaped) (Fig. 2): The skin incision starts 1cm lateral to the tibial crest. Longitudinal incision is extended proximally to Gerdy's tubercle, where it curves posteriorly in a transverse direction towards the fibular head, to a point approximately 2cm inferior to its tip. At the posterior aspect of the fibular head the incision curves and runs proximally to the posterior border of the biceps femoris (Fig. 2A). The length of the posterior proximal extension of the incision, proximal to the joint line, depends on the need for exposure of the common peroneal nerve (CPN), required to perform the third and fourth windows (Fig. 2C). The length of the anterior distal extension should be determined by the reduction needs of the lateral column.
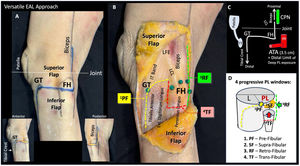 Fig. 2.
Versatile EAL Approach. (A) Landmarks and skin incision (blue line). GT: Gerdy's tubercle. FH: Fibular head. Additional anterior and posterior views highlight the relationship of the incision with the tibial crest and the posterior curve around the fibular head. Note that the transverse part of the skin incision is below the joint line. (B) Full-thickness skin flaps. Fascia incision for each progressive window: 1 pre-fibular (PF) (yellow line), 3 retro-fibular (RF) (green line), 4 trans-fibular – fibular neck osteotomy (TF) (red line). IT band: iliotibial band; LCL: lateral collateral ligament; LFE: lateral femoral epicondyle. Green pushpins mark the palpable osseous landmarks. (C) Rationale for the “skin incision design” related to the deep exposure. The proximal extension just behind the biceps allows localization of the common peroneal nerve (CPN) when RF or TF windows are needed. The distal level of the posterior incision at the fibular head allows optimal exposure of the RF and TF windows and avoids unnecessary posterior distal skin incision according to deep anatomical limits. The anterior tibial artery (ATA) crossing represents the deep posterolateral distal limit, and it is usually located at 3.5cm from the tip of the fibular head. The popliteal artery (PA) represents the posterior (or medial) limit of the deep approach. Anterior distal incision parallel to the tibial crest is expandable distally to control the apex of the lateral column fracture. Anterior exposure of the anterior tibial tuberosity (TT) or the most anterior cortex under the patellar tendon are also accessible. (D) Schematic representation of the four deep progressive posterolateral windows.
- •
Skin flaps (Fig. 2B): Full-thickness cutaneous flaps are developed to expose the fascia and identify the underlying anatomy. The superior flap provides exposure of the joint (from lateral and from posterior), and the proximal anatomical structures above the fibular head, including the lateral collateral ligament (LCL) and biceps. Proximal extension of the incision (through posterior) allows the exposure of the CPN and the lateral femoral epicondyle. The inferior flap provides exposure of the fibular neck (CPN crossing) and the crossing of the anterior tibial artery (ATA) at the posterior aspect of the approach (Fig. 2C). In clinical practice, the authors recommend careful handling of skin flaps, avoiding unnecessary skin extensions, and performing percutaneous distal fixation of the lateral plate.
- •
Fascial incision and windows: Four progressive windows can be developed to manage the PL column: (1) pre-fibular, (2) supra-fibular, (3) retro-fibular and (4) trans-fibular (fibular neck osteotomy) (Fig. 2D). The fascial incisions are connected in the complete approach when the last window is used (Fig. 2B).
- •
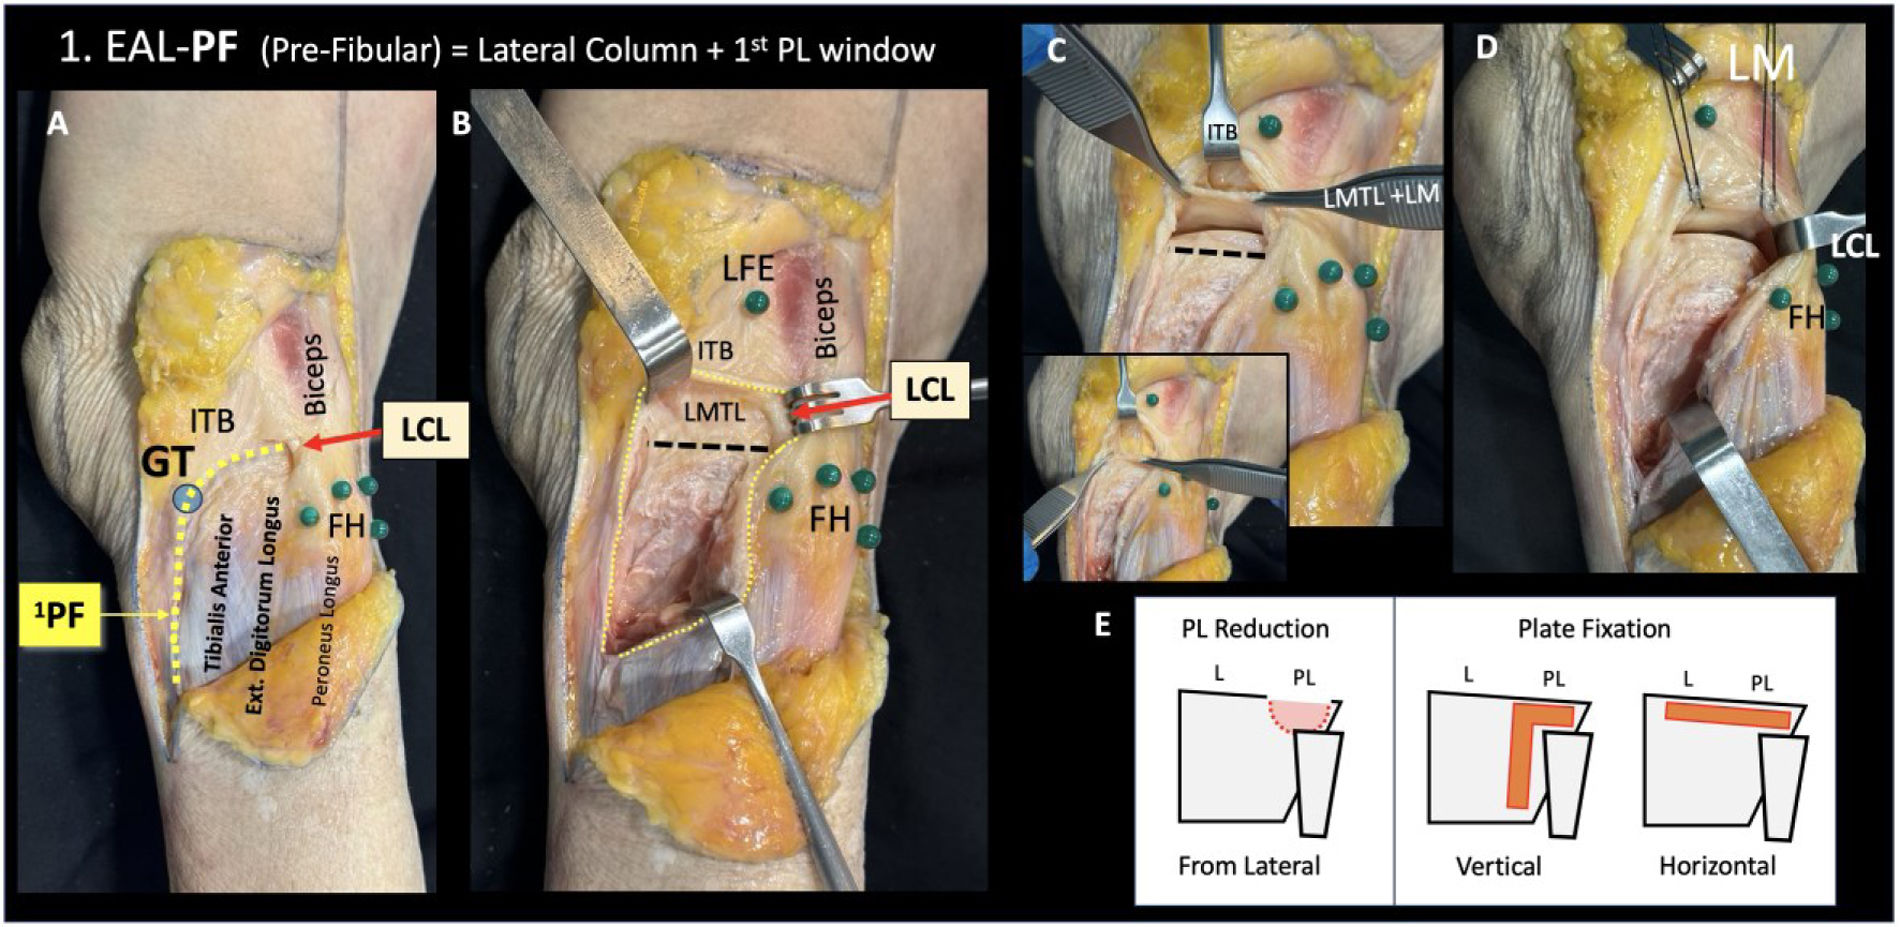
First window – pre-fibular (EAL-PF) (Fig. 3): The fascial incision starts 1cm lateral to the tibial crest, seeking proximally the center of Gerdy's tubercle. At this point, the fascial incision curves posteriorly incising the posterior surface of the iliotibial band. The lateral collateral ligament (LCL), located between the lateral femoral epicondyle and the anterosuperior aspect of the fibular head,41 represents the posterior limit of the fascial incision (Fig. 3A). Identification of the LCL under the fascia is essential to prevent iatrogenic injury. Subperiosteal release of the iliotibial band from Gerdy's tubercle, and the origin of the extensor muscles (tibialis anterior and extensor digitorum longus) is performed. At the joint level, meticulous dissection is necessary to properly develop the interval between the iliotibial band and the joint capsule, including the lateral meniscotibial ligament.42 This step is essential to allow tension-free closure of the iliotibial band (Fig. 3B). A submeniscal arthrotomy43 is then performed by initiating the transverse incision on bone, approximately 5mm below the joint line, rather than at the joint level, in order to facilitate reinsertion of the lateral meniscotibial ligament and the lateral meniscus (Fig. 3B and C). After protecting and retracting the LCL posteriorly, the arthrotomy can be extended posteriorly to increase exposure of the PL column on the lateral aspect. The use of anterior and posterior traction sutures to facilitate manipulation of the lateral meniscus is recommended (Fig. 3D).
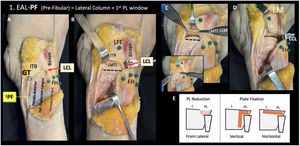 Fig. 3.
First window: pre-fibular (PF). (A) Fascial incision (yellow line). Note the posterior curve from Gerdy's tubercle (GT), performing a transverse-oblique incision of the iliotibial band (ITB) cranial to the origin of the extensor muscles. The lateral collateral ligament (LCL), located from the lateral femoral epicondyle (LFE) to the anterosuperior part of the fibular head (FH), represents the posterior limit of the fascial incision. Careful fascial dissection is essential to identify the LCL and avoid iatrogenic injury. (B) Release of the extensor muscles origin and careful development of the interval between the ITB and the lateral meniscotibial ligament (LMTL). Black dotted line represents the recommended level for submeniscal arthrotomy, located 5mm below the joint line, to facilitate LMTL and meniscus reinsertion at the end of the procedure. (C) Submeniscal arthrotomy elevating the LMTL and lateral meniscus (LM). The inset image highlights how the distal level of the arthrotomy facilitates reinsertion during closure. (D) Posterolateral exposure retracting LCL posteriorly and increasing capsulotomy posteriorly. (E) Schematic diagrams of PL column reduction and fixation options from the PF window. Selected depression PL column fractures with intact posterior cortex can be managed through this first window.
- •
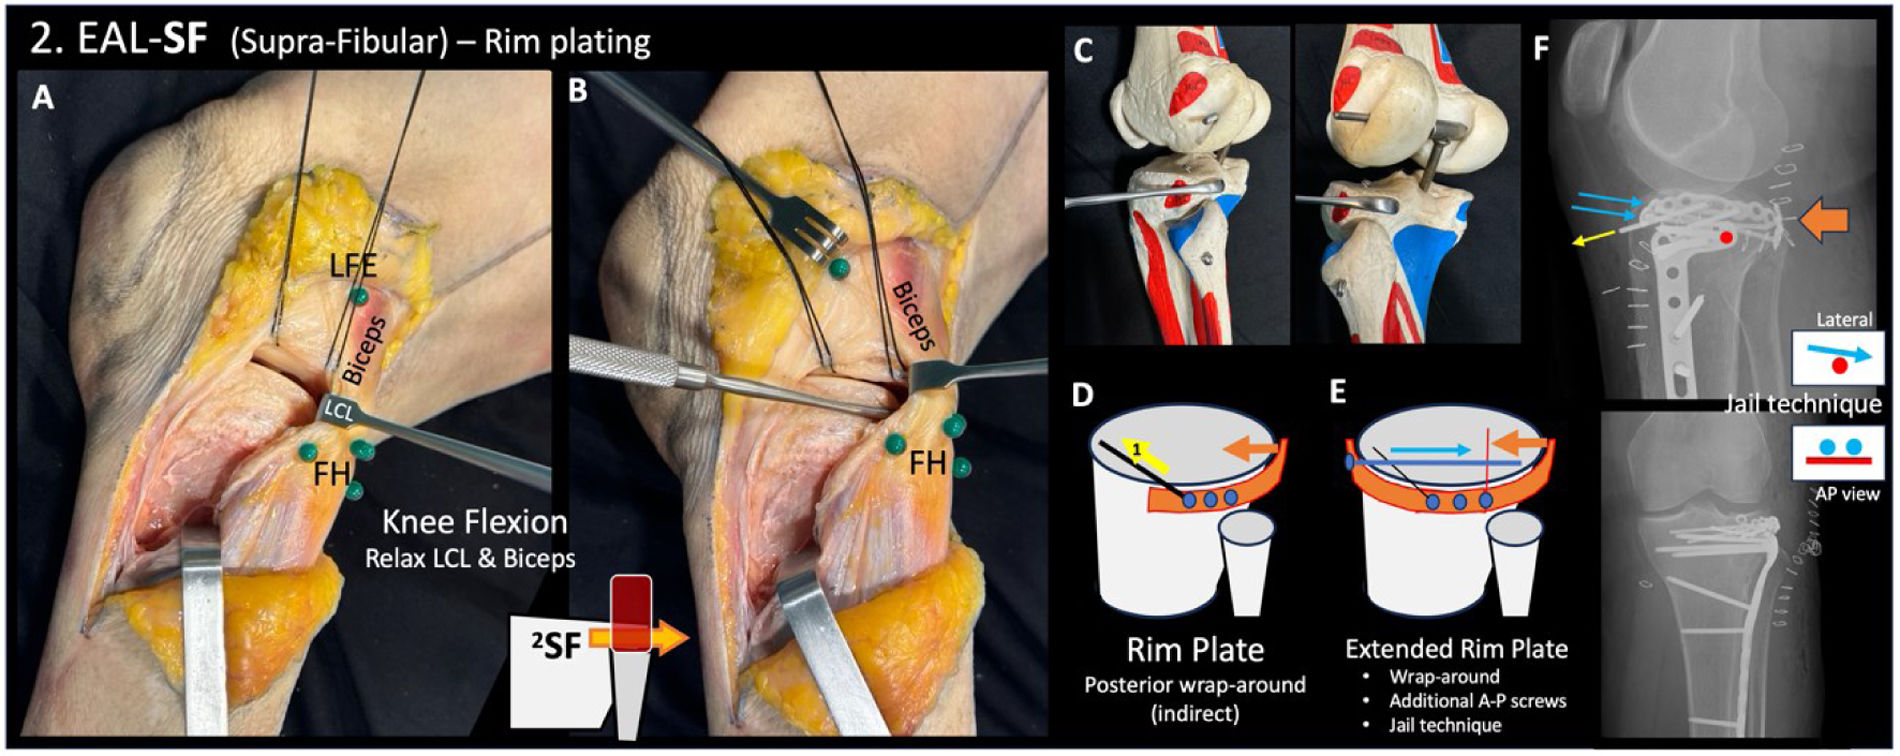
Second window – supra-fibular (EAL-SF) (Fig. 4): Without additional superficial fascia incision, the exposure of the PL column can be increased through the space above the fibular head, between the lateral tibial plateau and the LCL and biceps (supra-fibular corridor). Knee flexion relaxes the LCL and biceps (Fig. 4A). After retracting these fibular structures posteriorly, lateral and posterior (PL corner) subperiosteal release through the supra-fibular space is performed (Fig. 4B and C). Expanding the capsulotomy posteriorly allows the visualization of the posterior articular corner from lateral (Fig. 4A and B). The SF window aims to create the necessary supra-fibular corridor for horizontal “rim plating”16 using a curved plate to indirectly wrap-around the posterior cortex (without direct postero-anterior screws) (Fig. 4D). Combining the exposure of the PF and SF windows may provide sufficient workspace for additional antero-posterior screws through the anterior part of the pre-fibular window. This configuration may allow application of concepts related to the “jail technique”44 using an “extended rim plate” (from posterior to anterior) (Fig. 4E and F).
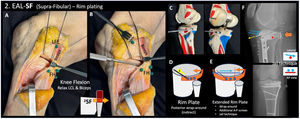 Fig. 4.
Second window: supra-fibular (SF) for rim plating. (A) Exposure of the posterior articular corner. Knee flexion to relax the lateral collateral ligament (LCL) and biceps. (B) Subperiosteal dissection under the LCL and biceps (supra-fibular space) towards the posterior aspect of the tibial plateau. (C) Direction of the periosteal elevator in an anatomical model. (D) Diagram representing the horizontal supra-fibular “rim plate” concept. Indirect posterior wrap-around effect of the PL cortex (orange arrow) without direct postero-anterior screws. Starting with an anteriorly directed screw (yellow arrow) may facilitate the plate's pulling effect. (E) Diagram representing the “extended rim plate” from posterior to anterior, combining the “rim plate” concept (orange arrow) with additional antero-posterior (A-P) screws through the plate (blue arrow) and concepts related to the “jail technique” using a lateral locking screw (red line) below the A-P screw through the horizontal plate. (F) Clinical case example of a horizontal “extended rim plate” (2.7mm) illustrating concepts related to the jail technique. Orange arrow: posterior wrap-around effect of the rim plate. Yellow arrow: anteriorly directed screw (pulling effect). Blue arrows (lateral view)/blue points (AP view): two locking screws through the rim plate from anterior to posterior, located just above the screws from the lateral vertical plate (red circle in lateral view/red line in AP view). Diagram represents the jail technique concept in lateral and AP views.
- •
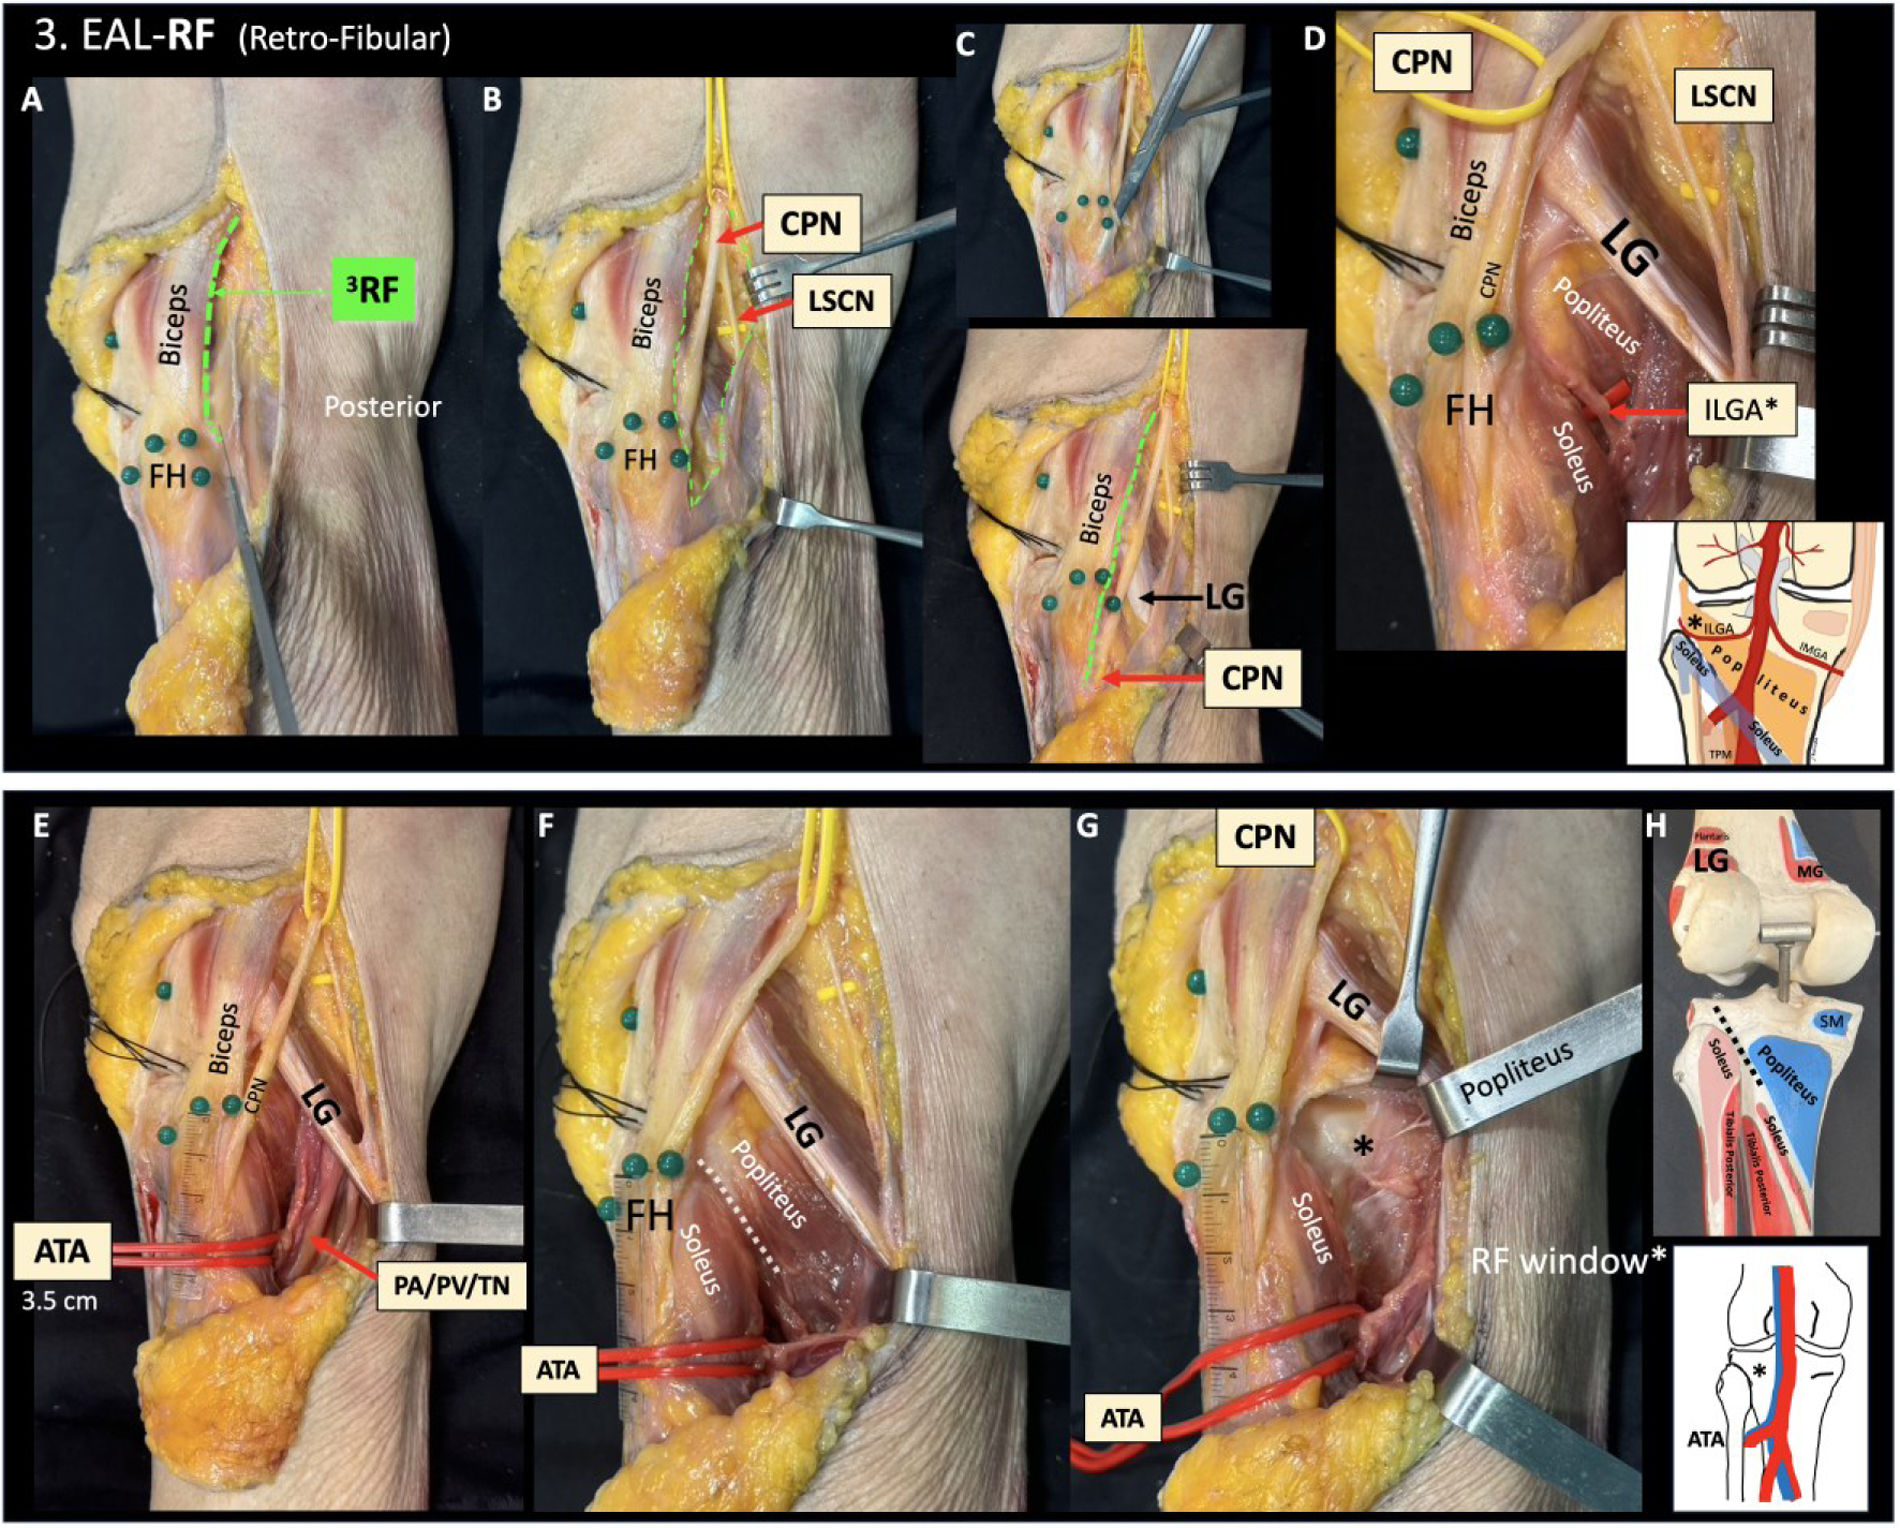
Third window – retro-fibular (EAL-RF) (Fig. 5A–H): The surgeon repositions to the opposite side of the operating table to address this window from posterior, without altering the patient's position. The fascial incision starts proximal to the joint level and just posterior to the biceps femoris (Fig. 5A). Careful dissection is performed to identify the common peroneal nerve (CPN) located under this fascia and just posterior to the biceps. The lateral sural cutaneous nerve (LSCN) can be found on the posterior part of the surgical field, as a posterior branch of the CPN,45,46 and it must be protected (Fig. 5B). Anatomical variants or small branches of the LSCN may be present and should be recognized and protected. However, in certain cases, sacrificing small anterior ascending branches must be considered.45,46 From proximal to distal, the CPN is dissected to safely open the distal fascia, behind the fibular head and over the fibular neck, protecting the nerve (Fig. 5C). Lateral gastrocnemius can be identified under the CPN and addressed through the interval between the CPN and LSCN18 (Fig. 5C). The lateral gastrocnemius is retracted medially to identify the fibular origin of the soleus muscle (posterior aspect of the fibular head) and the popliteus muscle (posterior aspect of the tibia). At this point, the inferior lateral genicular artery, located between the lateral gastrocnemius and popliteus muscle, may be present in the surgical field over the popliteus (or proximal, closer to the joint).47–49 In these cases, this small artery must be ligated4,18–20 (Fig. 5D).
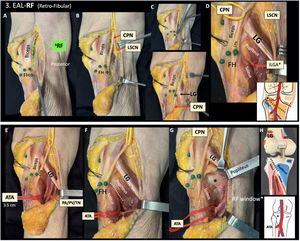 Fig. 5.
Third window: Retro-fibular (RF). A) Fascial incision just posterior to the biceps (green line). B) Identification of the Common Peroneal Nerve (CPN) and the Lateral Sural Cutaneous Nerve (LSCN) under the fascia. C) Distal progression of the fascial incision following the pathway of the CPN over the fibular neck. Identification of the lateral gastrocnemius (LG) under the CPN. D) Medial / posterior retraction of the LG and identification of the soleus (fibular origin) and the popliteus. At this point, the inferior lateral genicular artery (ILGA) can be present over the popliteus and ligated. Asterisk in the diagram: ILGA. Note that the workspace is between the CPN and LSCN. E) Anatomical detail of the popliteal neurovascular bundle location in the interval between the lateral gastrocnemius (LG) and the popliteus (not necessary for the surgical approach). The red vessel loop identifies the anterior tibial artery (ATA), located at 3.5 cm from the tip of the fibular head in this cadaveric specimen. PA: popliteal artery. PV: popliteal vein. TN: tibial nerve. CPN: common peroneal nerve. F) Interval between the popliteus (tibia) and soleus (fibula) (white dotted line). G) Exposure of the retro-fibular window (asterisk) retracting the popliteus superiorly. The ATA represents the distal limit for exposure through this window. Note that the skin incision is designed to facilitate maximal exposure of this window. H) Reference of the deep retro-fibular interval (dotted line) in an anatomic model, and diagram of the RF window (asterisk) limited distally by the ATA.
Before continuing the dissection, anatomical knowledge of the popliteal neurovascular bundle and the ATA location, as well as awareness of anatomical variants, is essential6,33,50; however, specific dissection or direct identification of these structures is not necessary for the surgical approach (Fig. 5E). The popliteal neurovascular bundle is protected with retraction of the lateral gastrocnemius. The crossing of the ATA represents the distal limit of the RF window and should be recognized (even without specific dissection) to prevent injury (Fig. 5F, G, and H).
The exposure of the PL column is obtained through the interval between the soleus and popliteus muscles.18,19 Superomedial elevation and retraction of the popliteus (and lateral gastrocnemius) are performed to expose the RF window (Fig. 5F, G, and H). The soleus muscle can be detached from the posterior surface of the fibular head and retracted distally,19 but only if required to increase the exposure or to proceed with the fourth window (fibular osteotomy). Posterior capsulotomy can be performed continuing the previous anterolateral transverse incision on bone (Fig. 3) while preserving the popliteal tendon and the popliteofibular ligament.42,51 In exceptional cases, release of an inferoposterior band of the popliteofibular ligament may be required to achieve adequate exposure in anatomical variants (Olewnik type III, 7.3%51). Popliteal tenotomy may also be considered only when visualization remains insufficient,4 but requiring subsequent repair. When progression to the trans-fibular window is anticipated, release of the popliteofibular ligament or popliteal tenotomy is generally unnecessary, as these structures are mobilized cranially with the fibular neck osteotomy.
The limited working space of the RF window for short plate fixation18,19 (Fig. 5G and H) can be extended through three complementary technical strategies that may expand the posterior fixation options available through the third window:
- (1)
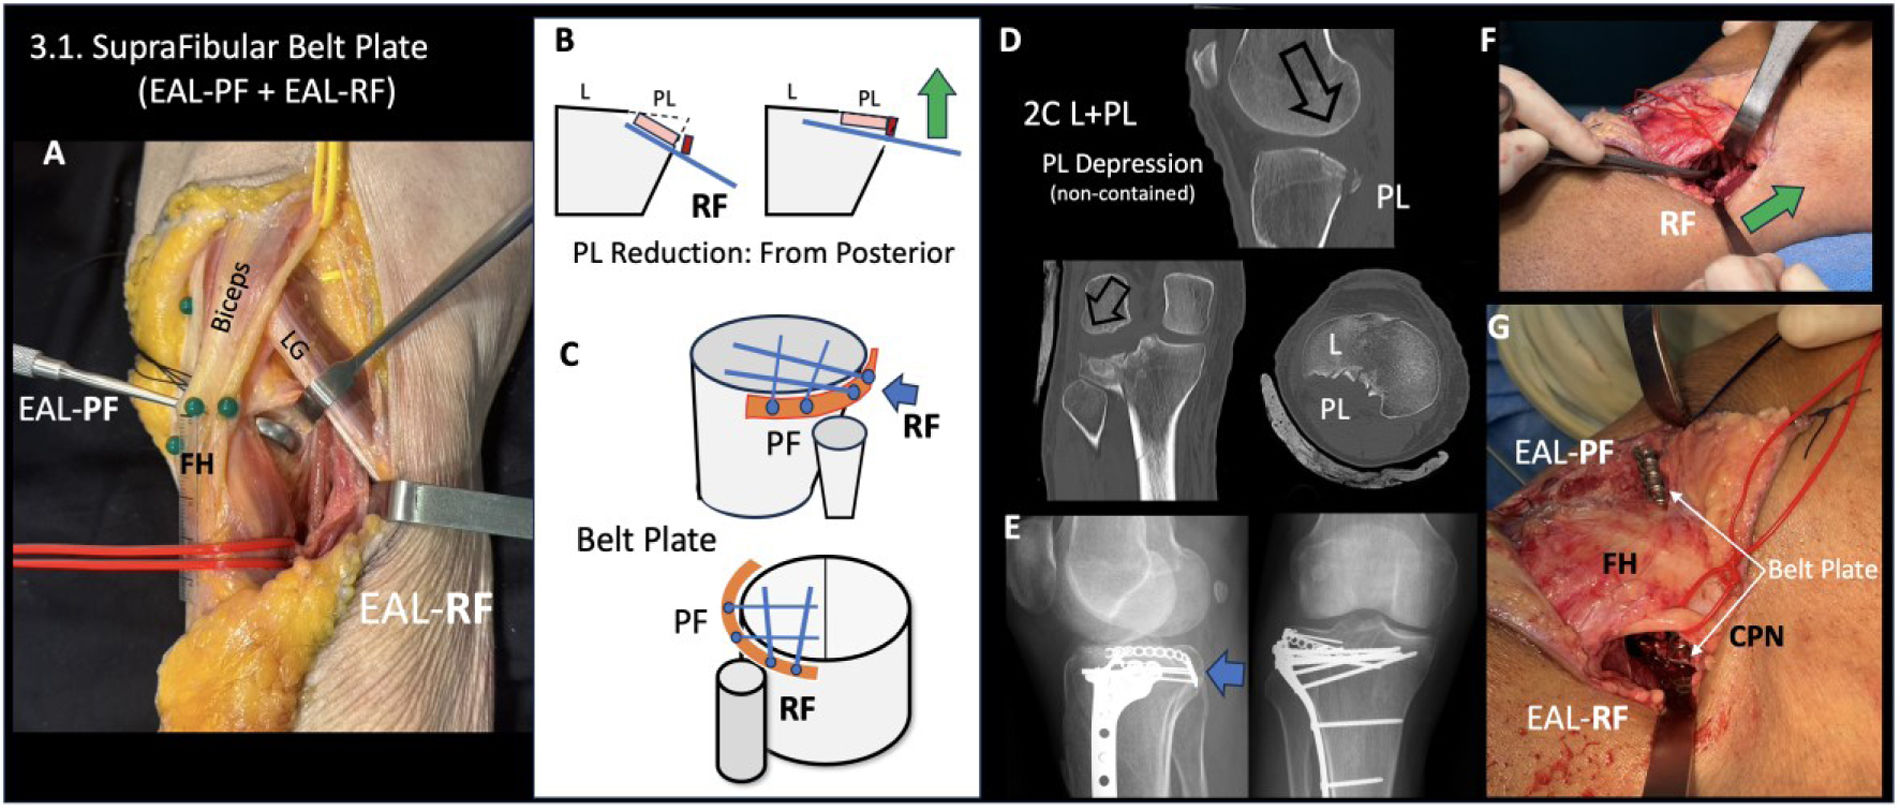
Application of a “horizontal belt plate”,52 combining the first three windows through the supra-fibular corridor, allowing posterior-to-anterior screws from the RF window and lateral-to-medial screws from the PF window (Fig. 6).
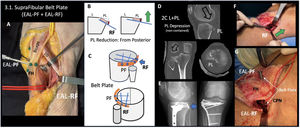 Fig. 6.
Technique concept: supra-fibular horizontal belt plate combining the pre-fibular (PF) and retro-fibular (RF) windows. (A) Periosteal elevator through the supra-fibular corridor from PF to RF windows (cadaveric specimen). (B) Diagram representing PL reduction in a non-contained PL depression combined with PL column angular deformity through posterior. From the RF window a chisel or a k-wire (blue line) can be used to correct the angulation from posterior, elevating the fragment (green arrow). (C) Diagrams representing the supra-fibular belt plate with direct fixation from posterior (blue arrow) through the RF window. Note the difference compared with the “rim plating” (in Fig. 4) without posterior screws. (D) Clinical case example of a two-column (2C) lateral (L)+posterolateral (PL) fracture. PL column depression fracture with angular sagittal deformity towards posterior and the posterior cortex affected (non-contained depression). Black arrows represent the MDD. (E) Horizontal belt plate with screws from posterior (blue arrow). (F) Clinical image performing the PL column reduction from posterior through the RF window in supine semi-lateral position. Green arrow represents the elevation of the fragment. Reduction check can be done through RF and PF windows. (G) Clinical image of the belt plate through PF and SF windows. FH: fibular head; CPN: common peroneal nerve.
- (2)
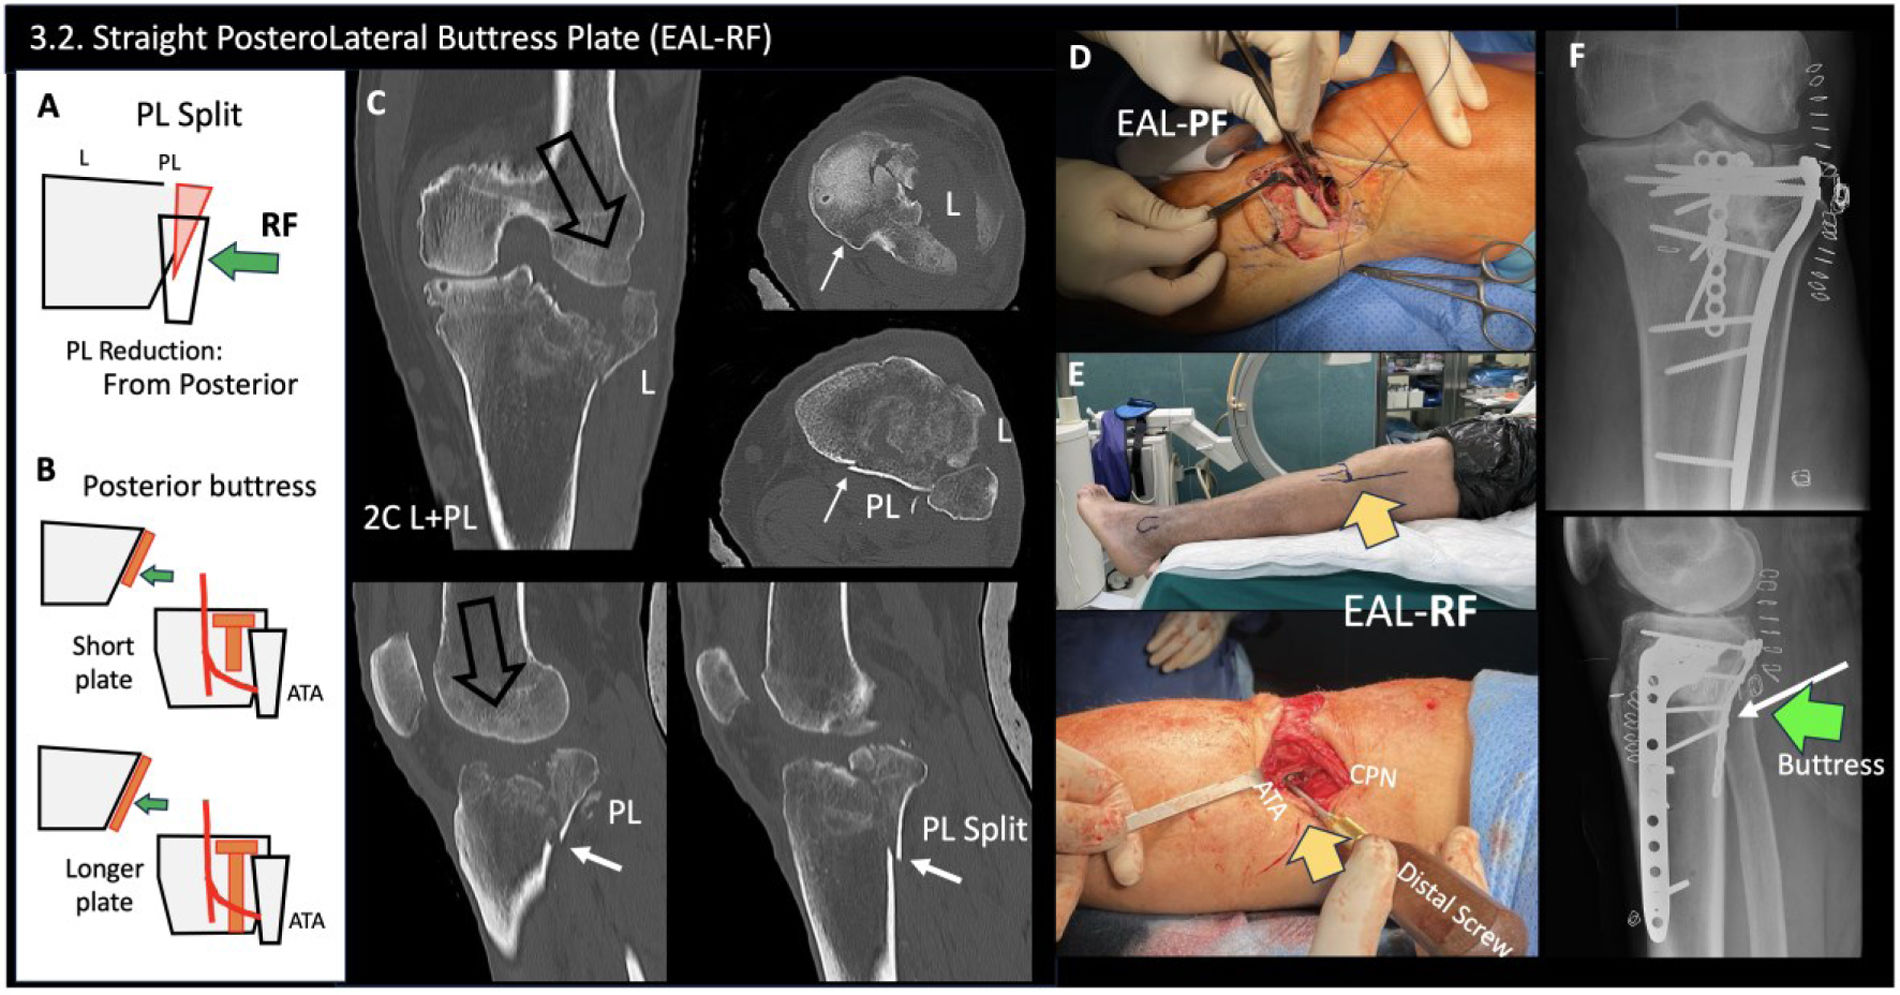
Placement of a longer longitudinal straight posterior buttress plate, carefully inserted subperiosteally beneath the ATA, avoiding screws distal to the arterial crossing (Fig. 7).
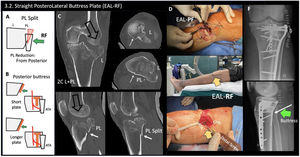 Fig. 7.
Technique concept: straight posterolateral buttress plate through the retro-fibular (RF) window. (A) Diagram representing PL reduction in PL column split fracture with the apex located distally to the level of the fibular head. From the RF window distal reduction of the apex may be feasible. (B) Diagram represents the relation between the posterior buttress plates and the anterior tibial artery (ATA) in AP view, and the buttress effect in lateral view (green arrows), using a short plate or a longer plate beneath the ATA. (C) Clinical case example of a two-column (2C) lateral (L)+posterolateral (PL) fracture. PL column split fracture with the apex located distal to the fibular head level, where posterior buttress plate fixation was considered preferable. Note that in this case a horizontal supra-fibular (rim or belt) plate could displace the PL apex distally, not being appropriate for biomechanical control of the split PL fracture. (D) Clinical image of the pre-fibular (PF) window. Through the PF window: reduction and fixation of the lateral column (split-depression fracture), and reduction of the articular part of the PL column (split fracture). (E) Clinical image of the supine semi-lateral fixed position and the retro-fibular (RF) window (yellow arrow). Through the RF window: reduction of the distal apex of the PL split fracture using a posterior buttress plate. Screwdriver is marking the direction of the distal screw. The ATA was present just distally. (F) Postoperative radiology. Note that the screw fixation of the posterior plate is limited distally by the ATA, however it is possible to use a longer plate, to increase the buttress effect (green arrow), carefully sliding subperiosteally the plate beneath the ATA like in this case example. White arrow: inferior obliquity direction of the most distal screw, cranial to the ATA location.
- (3)
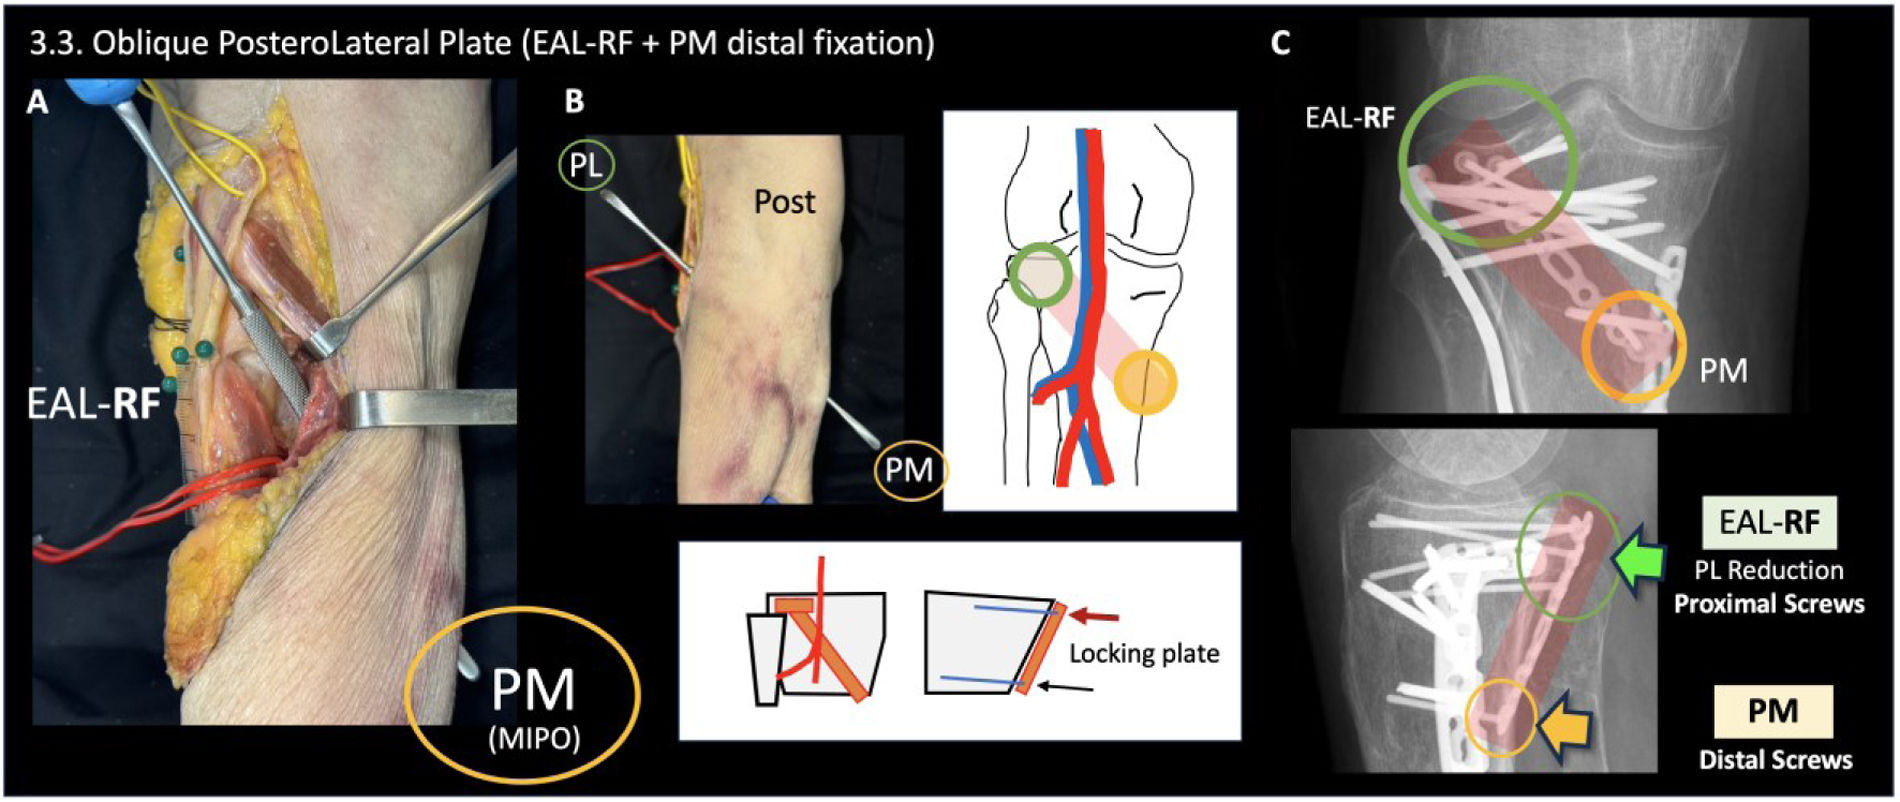
Combination of the RF window with a distal percutaneous (or open) posteromedial approach, enabling oblique posterolateral plating beneath the vessels with posteromedial distal fixation of the plate (Fig. 8).
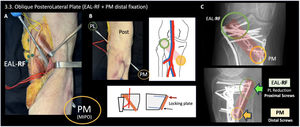 Fig. 8.
Technique concept: oblique posterolateral plate combining the retro-fibular (RF) window with posteromedial (PM) distal fixation. Technique for longer posterolateral plate beneath the vessels. (A) Periosteal elevator from RF window to PM (cadaveric specimen). Minimally invasive PM approach can be used for distal fixation of the plate (MIPO). (B) Posterior view. Diagrams representing the oblique posterior plate beneath the vessels. Green circle: RF window. Yellow circle: PM window. Note that this technique may allow fixing PL column fragments with a posterior locking plate when distal plate fixation is not feasible through the RF window (e.g. fracture extension distal to ATA). (C) Clinical case example using this technique. Only one screw in healthy distal PL bone was feasible through the RF window. PL column reduction and proximal locking screws was performed through EAL-RF (green circle/arrow) with additional distal fixation through PM (yellow circle/arrow).
- (1)
- •
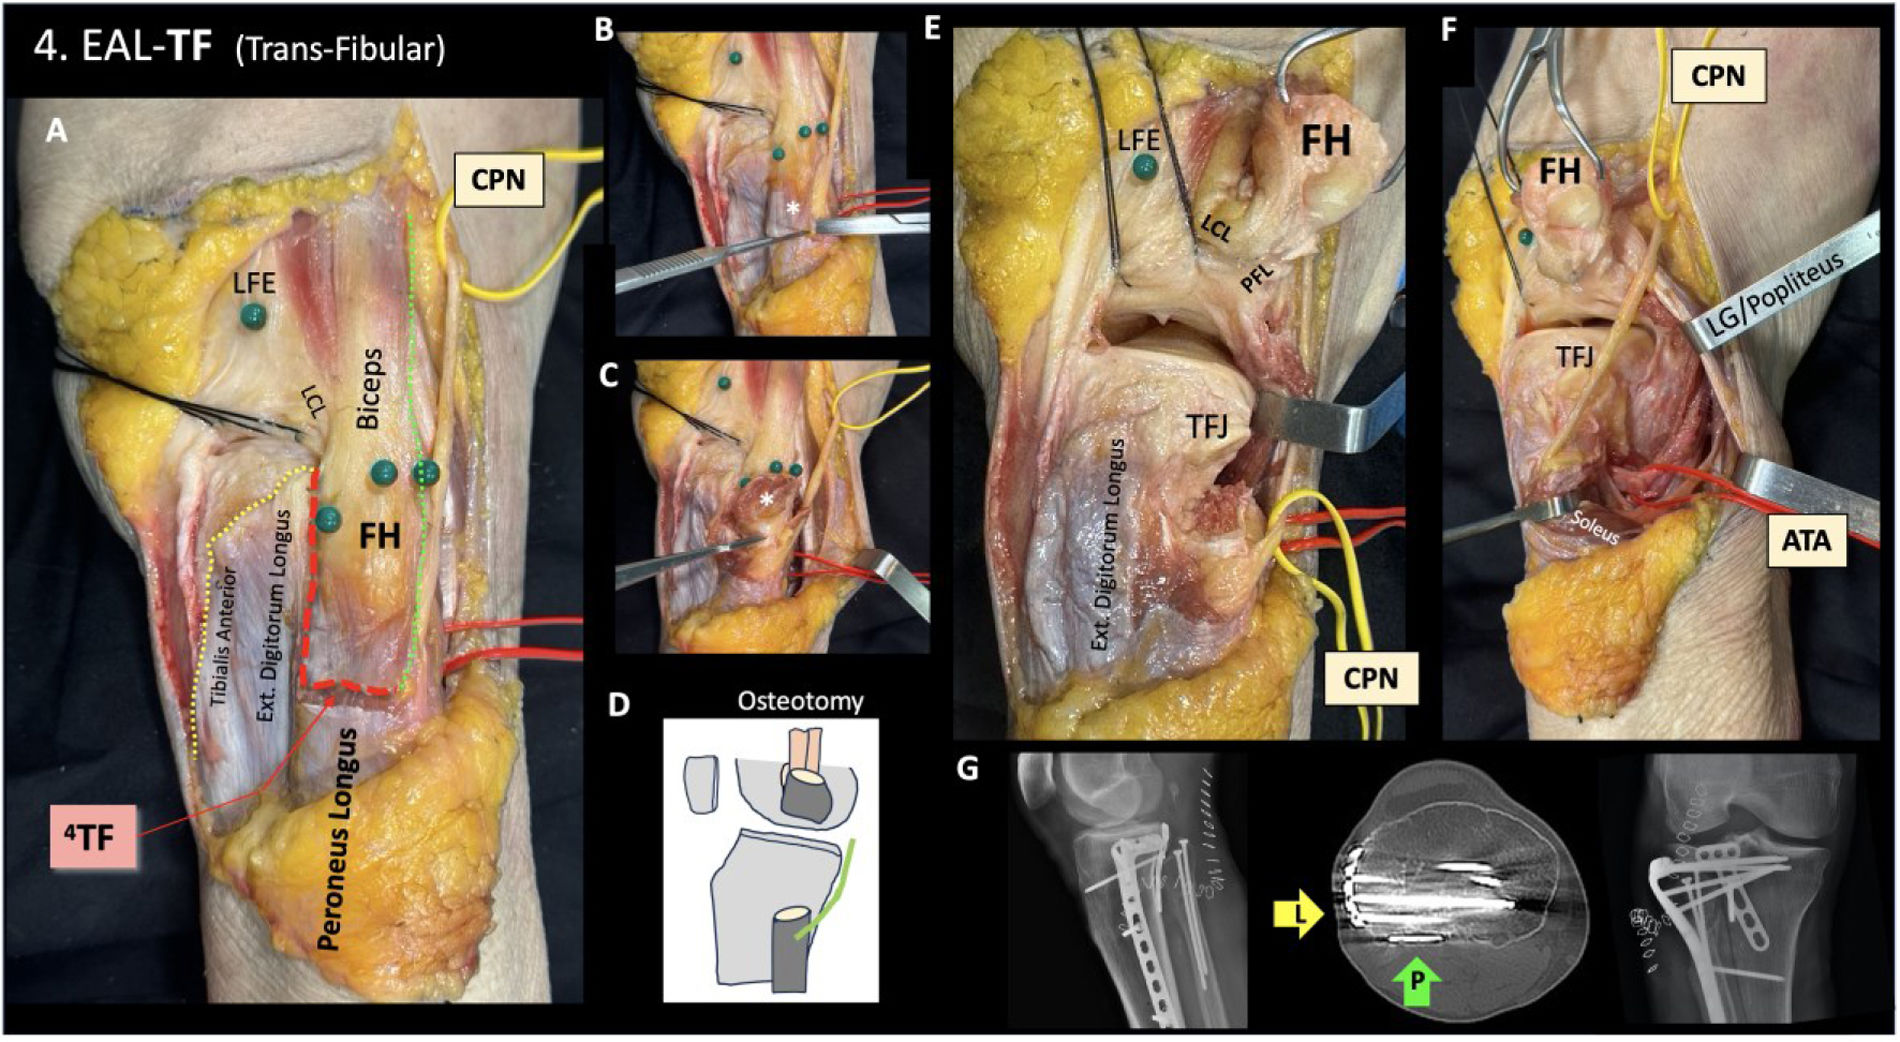
Fourth window – trans-fibular (EAL-TF) (Figs. 9 and 10): The fascial incision is completed connecting the previous PF and RF fascial incisions. From the previous PF fascial incision (at the level of the LCL), a longitudinal incision between the posterior border of the extensor digitorum longus and the anterior border of the fibular head and peroneus longus is performed. A transverse incision of the peroneus longus fascia, just cranial to the CPN crossing previously identified, connects with the previous RF fascial incision (Fig. 9A). Protecting the CPN, a transverse incision of the peroneus longus muscle is carefully performed. The peroneus longus muscle is subperiosteally reflected cranially to expose the fibular neck (Fig. 9B and C). The fibular osteotomy is performed with a chisel a few millimeters above the CPN crossing (Fig. 9C and D). Elevation of the fibular head is completed with the incision of the tibiofibular capsule.53 The LCL, popliteofibular ligament and biceps, inserted on the fibular head,41,51 are elevated cranially with the osteotomy allowing varus maneuver to further increase the articular visualization (Fig. 9E). After mobilizing the CPN posteriorly or anteriorly, articular and metaphyseal exposure of the lateral and posterior aspects of the PL column, including the tibiofibular joint area, can be achieved (Fig. 9E and F). The posterior exposure is limited distally by the ATA (Fig. 9F) and medially by the popliteal neurovascular bundle.
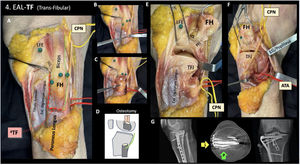 Fig. 9.
Fourth window: trans-fibular (TF). Fibular neck osteotomy. (A) Trans-fibular fascial incision (red dotted line). Longitudinal fascial incision between the posterior border of the extensor digitorum longus and the anterior aspect of the fibular head and peroneus longus. Transverse fascial incision of the peroneus longus just cranial to the common peroneal nerve (CPN) crossing. Note that the TF fascial incision connects the previous fascial incisions (PF: yellow dotted line. RF: green dotted line). (B) Careful incision of the peroneus longus muscle (asterisk) protecting the CPN. (C) Cranial retraction of the peroneus longus muscle (asterisk) exposing the fibula. Osteotome at the level of fibular osteotomy (cranial to the CPN location). (D) Diagram representing the fibular neck osteotomy. (E) Exposure of the TF window: lateral view retracting the CPN posteriorly. Tibiofibular joint (TFJ) is visible allowing control of fractures in this area. Fibular head (FH) cranially elevated with the lateral collateral ligament (LCL) and popliteofibular ligament (PFL). Varus maneuver, not limited by the LCL and biceps, may further increase the articular visualization. (F) Exposure of the TF window: posterior view retracting the CPN anteriorly, and the lateral gastrocnemius (LG) and popliteus posteriorly. The anterior tibial artery (ATA) represents the posterior distal limit. Note the extensive exposure of the lateral and posterolateral columns, including both the articular surface and the metaphysis. (G) Clinical case example illustrating fixation possibilities through the EAL-TF window. Lateral plate (L) located in the most posterior part of the lateral aspect of the tibia. Posterior buttress plate (P). Fibular osteotomy was fixed with two long 3.5mm screws from the pelvis set.
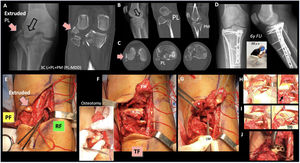 Fig. 10.
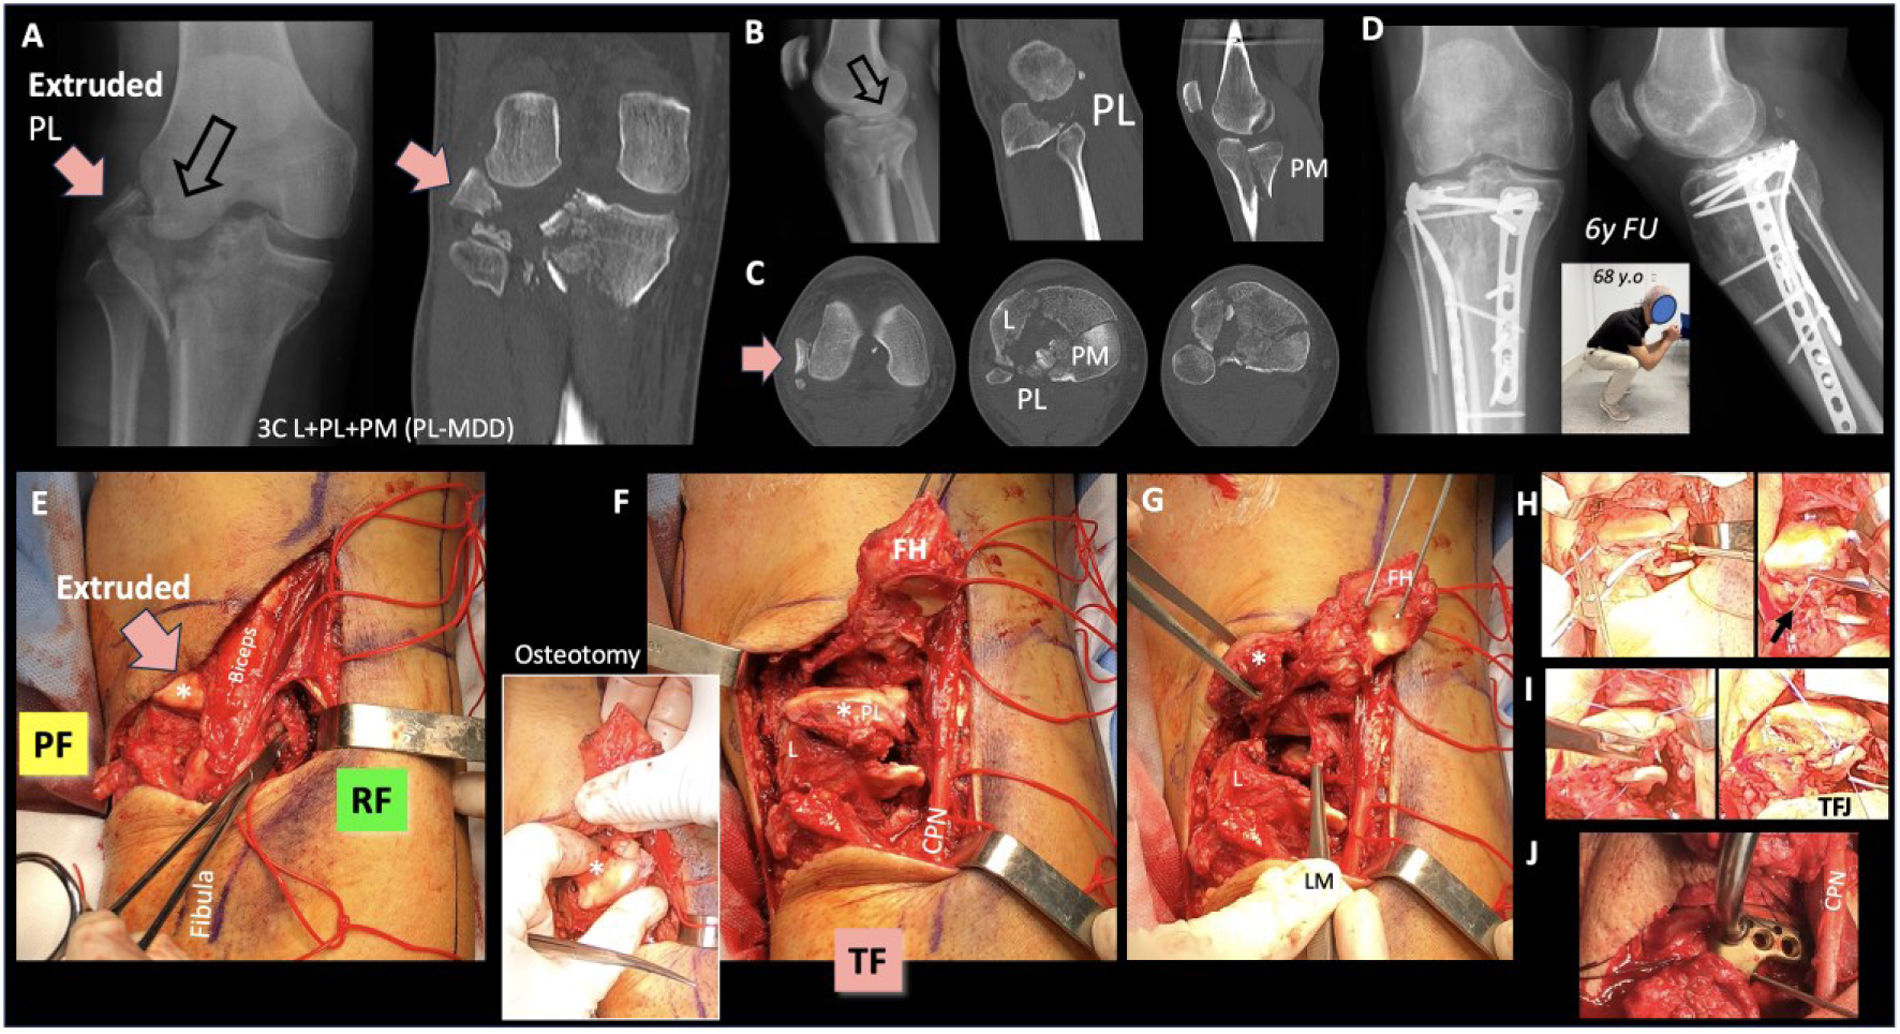
Clinical case example of a multicolumnar PL-MDD fracture managed using the trans-fibular window (EAL-TF). (A) AP/coronal view. Extruded posterolateral fragment (red arrow) embedded between the fibular head and the lateral femoral condyle. PL-MDD: posterolateral Main Deformity Direction (black arrows). (B) Lateral/sagittal view. Defect on the posterolateral (PL) column corresponding to the extruded fragment. (C) Axial CT. Extruded fragment (red arrow) and PL defect. (D) Follow-up radiographs and clinical image at 6 years postoperatively. (E) EAL approach in prone semi-lateral position. The embedded fragment (asterisk) could not be mobilized through the pre-fibular (PF) and retro-fibular (RF) windows. (F) Fibular neck osteotomy allowing mobilization of the trapped extruded fragment (asterisk) through the trans-fibular (TF) window. Expanded exposure of the lateral (L) and posterolateral (PL) columns. CPN: common peroneal nerve. Note the involvement of the tibiofibular joint in the fracture pattern. (G) Fracture exposure after mobilization of the extruded fragment (asterisk). Lateral meniscus (LM) identified within the fracture gap. (H) Reduction and fixation maneuvers. Clamp reduction and interfragmentary screw from posterior (PL column) to anterior (lateral column). Clamp reduction and interfragmentary K-wire fixation of the PL fragments (wire cut). (I) Tibiofibular joint (TFJ) reconstruction with trans-osseous sutures. (J) Lateral plate positioned in the posterior aspect of the lateral tibia. The lateral meniscus was reattached before fixation of the fibular osteotomy with a 3.5mm intramedullary screw.
- •
Closure: The lateral meniscus is reattached before fixing the osteotomy (Figs. 3C and 10J). The fibular osteotomy can be fixed with one or two long intramedullary 3.5mm screws, usually 80mm in length (Figs. 9G and 10D).23 Other complementary options for fibular fixation may include sutures, cerclage, miniplates or even tibiofibular screws or arthrodesis.24,53 The fascia is sutured in the anterior part of the approach restoring the anatomy of the iliotibial band and extensor muscles, including the closure of the posterior longitudinal incision between the extensor digitorum longus and the fibular head/peroneus longus. The transverse peroneus longus fascia, and the longitudinal retro-fibular and retro-biceps fascia incisions, are left open to prevent compression or scarring over the CPN. The subcutaneous tissue and skin are sutured starting by the two apices of the skin flaps.


The cadaveric study showed safe and adequate progressive PL column exposure in all specimens, while maintaining a complete lateral column exposure. The skin incision design was considered optimal for addressing all deep windows and identifying key anatomical structures without limitations or requiring further skin extensions. The posterosuperior longitudinal skin incision allowed CPN and LSCN exposure (Fig. 5B). The posteroinferior corner of the skin incision at the posterior part of the fibular head (combined with the inferior flap) allowed the optimal exposure of the ATA crossing, the CPN crossing at the fibular neck, and the RF and TF windows (Figs. 5G and 9F). The transverse skin incision (below the joint line), combined with the superior skin flap, allowed identification of the lateral femoral epicondyle and the LCL, while maintaining a complete exposure of the lateral column, through the PF window (Fig. 3B). The anterior part of the lateral column and the patellar tendon were also accessible.
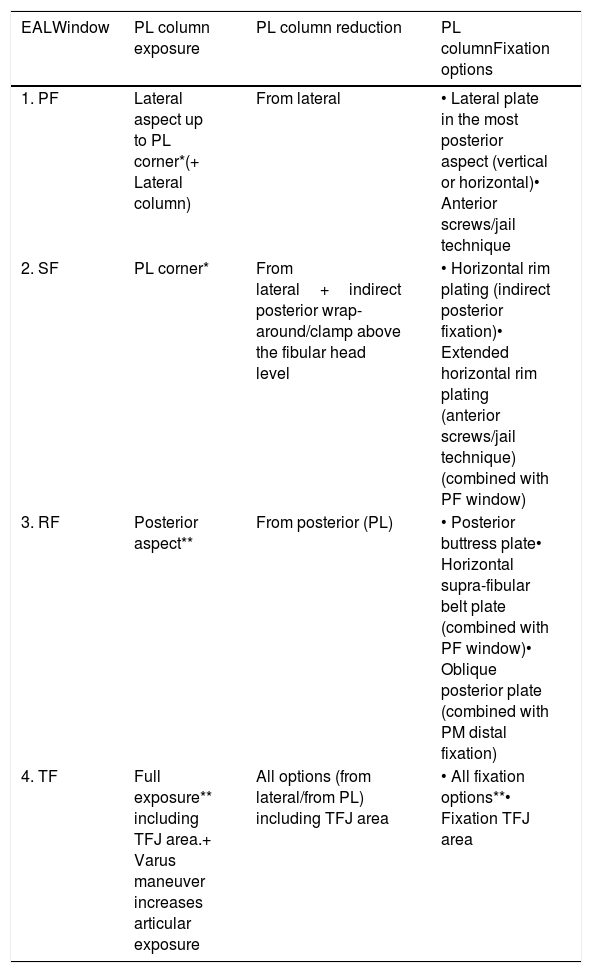
The results of the evaluation of the exposure and the theoretical possibilities for reduction and fixation using each progressive window are summarized in Table 1. Diagrams and clinical case examples explaining the possible PL fixation techniques with each window are presented in Figs. 3E, 4, 6, 7, 8, 9 and 10.
Versatile EAL approach: potential PL column management options.
| EALWindow | PL column exposure | PL column reduction | PL columnFixation options |
|---|---|---|---|
| 1. PF | Lateral aspect up to PL corner*(+ Lateral column) | From lateral | • Lateral plate in the most posterior aspect (vertical or horizontal)• Anterior screws/jail technique |
| 2. SF | PL corner* | From lateral+indirect posterior wrap-around/clamp above the fibular head level | • Horizontal rim plating (indirect posterior fixation)• Extended horizontal rim plating (anterior screws/jail technique) (combined with PF window) |
| 3. RF | Posterior aspect** | From posterior (PL) | • Posterior buttress plate• Horizontal supra-fibular belt plate (combined with PF window)• Oblique posterior plate (combined with PM distal fixation) |
| 4. TF | Full exposure** including TFJ area.+ Varus maneuver increases articular exposure | All options (from lateral/from PL) including TFJ area | • All fixation options**• Fixation TFJ area |
PF: pre-fibular; SF: supra-fibular; RF: retro-fibular; TF: trans-fibular; TFJ: tibiofibular joint.
The first window (PF) allowed complete exposure of the lateral column. The key limiting anatomical structure of this window for PL column exposure was the LCL.41 Retracting posteriorly the LCL and biceps, the exposure of the PL column up to the PL articular corner was obtained in all specimens. Techniques for reduction of the lateral and PL columns from lateral were considered feasible, but without any control of the posterior cortex if it were disrupted. Complete lateral exposure from the anterior aspect to the PL corner facilitates the use of horizontal lateral plates or vertical L-type plates above the fibular head.
The second window (SF), expanding the release posteriorly from lateral, allowed indirect traction of the posterior cortex in the upper part of the tibia (proximal to the fibular head). Theoretical indirect reduction of the upper posterior cortex of the PL column may be achieved. Sufficient space was available in all specimens to accommodate horizontal rim plating (indirect posterior wrap-around fixation). The exposure of the PL corner was not considered sufficient to properly position screws from the posterior cortex.
The third window (RF) required the dissection of the CPN. LSCN was found diverging from the CPN at the posterior aspect, and proximal to the knee joint, in all specimens. The distal limitation of the exposure of this window was the crossing of the ATA, located at a mean of 3.5cm (3.0–4.0cm) from the tip of the fibular head. Subperiosteal elevation beneath the ATA was possible in all specimens without damaging the artery. This allowed a periosteal elevator (or a potential plate) to be passed beneath the ATA inferiorly, or beneath the popliteal neurovascular bundle towards inferomedial (exiting through a posteromedial stab incision). Theoretical reduction of the PL column from posterior and fixation with posterior buttress plating was anatomically feasible in all specimens. Subperiosteal communication beneath the vessels between the RF window and a stab percutaneous posteromedial incision allowed potential posteromedial distal fixation of a longer oblique PL plate (Fig. 8). Additionally, a simulated horizontal supra-fibular belt plate could be applied by combining both PF and RF windows (Fig. 6).
The fourth window (TF) required additional dissection of the CPN crossing over the fibular neck. The fibular neck osteotomy was performed conditioned by the level of the CPN crossing, but no limitations for adequate osteotomy level were found. The exposure on the posterior metaphyseal aspect remained limited by the ATA crossing distally and by the popliteal neurovascular bundle medially, without changes compared to the RF window. However, proximal PL articular exposure from lateral and from posterior was increased due to the possibility of varus maneuver. Full exposure of the proximal metaphyseal aspect covered by the fibula, including the tibiofibular joint area, was obtained without evident theoretical limitation to deal with split fractures located at this level or PL column depressions under the level of the fibular head. The range of theoretical fixation options from lateral or from posterior was further enhanced by the possibility of access to the tibiofibular joint area.
DiscussionMultiple individual options for PL column management in tibial plateau fractures have been described10–37 and the decision-making for choosing the best individual option remains controversial.2,3,5,8,33,39,54–57 Recently, Hoskins and Kfuri,4 in a comprehensive review of the current approaches to address the PL column, stated that “one surgical approach does not fit all fracture morphologies of the PL quadrant”, presenting each approach their strengths, weaknesses and relative indications.4 In our strategy, rather than selecting an individual or limited option, the main advantage of the versatile EAL approach lies in integrating most of the previously described concepts for managing the PL column from lateral or posterolateral,10–24 while employing a single skin incision and a progressive, versatile deep approach.2 The four windows (PF, SF, RF and TF) represent progressive and complementary options for exposure, reduction, and fixation of the PL column from lateral or posterolateral.
According to the 4-column and MDD classification,2,40 the choice of the versatile EAL approach can be especially indicated for addressing the PL column (and the lateral column) in two-column L+PL and multi-columnar PL-MDD fractures.2 The deformities of the PL column in PL-MDD fractures, such as greater depression of the posterolateral lateral segment compared with the posterolateral central segment, or fracture angulation or displacement towards PL direction, may be best addressed from the EAL approach to counteract these deformities2 (Fig. 1B). In one-column PL fractures, this approach may also be considered, especially when PF or SF windows are planned (with potential extension to RF or TF windows).2 However, in simple low-energy fractures requiring posterior buttress plating, the direct PL approach described by Yu et al.,18 can be an alternative, as a limited approach equivalent to an isolated RF window with direct PL skin incision.2 On the other hand, several authors include posteromedial approaches in their algorithms for certain PL column fractures,2,8,16,33,39,55 but limitations of the PL column exposure should be considered depending on the type of posteromedial approach selected.8,33,56,57 In this sense, we consider the MOL approach as a feasible option to address the whole PL column from posteromedial.33 The MOL approach can be especially indicated for addressing the PL column in two-column PM+PL and multicolumnar PM-MDD fractures.2,33 The versatile EAL and MOL approaches can also be complementary for managing the PL column in complex cases, allowing the fixed prone semi-lateral position to be performed both approaches simultaneously2,33,40 (Fig. 1B).
Regarding previously described approaches to address simultaneously the lateral and PL column, several skin incision types have been designed.10,15,16,19–25,27–31 Extended anterolateral approaches centered on Gerdy's tubercle can be excellent for lateral column exposure and PF or SF windows,5,10,16 but are limited for further posterior exposure, especially for retro-fibular access.5,16 Straight lateral approaches centered on the fibular head can provide better posterior exposure, including retro-fibular access,5,19,58 but are sometimes limited or require extensive longitudinal incisions to achieve simultaneous adequate anterior and posterior exposure.5,20 Additionally, the location of the ATA crossing, 35.7±9.0mm distal to the fibular head,6 can be considered the inferior limit for posterior deep exposure in the RF or TF windows.6,18,19 Therefore, we believe that extending a straight vertical skin incision distally in the lateral or posterolateral area beyond the ATA crossing may be unnecessary (Fig. 2C). In this context, S-shaped skin incisions may better optimize the relationship between the skin and the deep exposure required for managing both lateral and PL columns.2,20 In addition, cutaneous perfusion of the knee is characterized by a highly interconnected genicular vascular network with significant collateral circulation, which may support the tolerance of reasonable variations in surgical incision design.47,48,59 The rationale for the skin incision design in the versatile EAL approach was to center the incision on both key structures, Gerdy's tubercle and the posterior aspect of the fibular head, to optimize access to the four deep PL windows while maintaining excellent lateral column exposure. The level of the posterior apex of the skin incision was adjusted to obtain an appropriate RF window exposure according to the deep limits (ATA crossing distally and popliteal neurovascular bundle medially) (Figs. 2C, 5E, 5G). The longitudinal (expandable) incisions were designed to expose key areas: proximally posterior (CPN dissection or even ligament reconstruction) and distally anterior (reduction of the apex of the lateral column and plating).
Preoperative planning is essential to anticipate the fracture requirements and the appropriate surgical approach.2,4,5,39 When using the versatile EAL approach, the appropriate window should also be planned in advance, although intraoperative progression to subsequent windows remains possible depending on the actual fracture behavior. Furthermore, the four windows can be considered complementary. The first window (PF) allows the exposure of the whole lateral column and the lateral part of the PL column. Reduction and fixation of the PL column can be performed from lateral, using lateral plates in the most posterior aspect, as several authors described in their extended anterolateral approaches.10–12 This option can be especially indicated when the posterior cortex is intact, and the depression of the PL column can be properly reduced from lateral.5 Another possible indication can be some split fractures with a large PL column fragment where at least two screws through the lateral plate maintain this fragment.60 In this sense, according to the MDD concept,2 in AL-MDD or lateral-MDD fractures with the PL column presenting anterior or lateral deformities (e.g. anterior angulation, depression or displacement), this PF window could be especially beneficial to counteract these deformities from lateral.
The second window (SF) increases the posterior exposure from lateral, allowing control of the PL corner for reduction clamps or the use of the horizontal supra-fibular rim plating concept (without screws from posterior) described by Cho et al.15,16 Horizontal plating is especially useful in non-contained peripheral rim-type fractures.39 Combined screws from anterior to posterior, especially with the “jail technique concept”,44 can increase fracture stability60 or prevent screw cut-out.39 In our practice, we consider an additional feasible option, placing these anterior screws through an “extended horizontal rim plate” (Fig. 4). We believe that the SF window, and related techniques, should be indicated only when horizontal plates can provide indirect wrap-around support of the PL cortex and adequately contain the fracture without requiring direct posterior access. Depression or short split-depression fractures affecting the PL column above the level of the fibular head, without a clear posterior-MDD (e.g. posterior angulation), could benefit from these supra-fibular techniques with indirect posterior reduction and fixation. Conversely, the SF window can also be combined with the MOL approach to allow direct posterior reduction from posteromedial of selected PL column depression patterns in multicolumnar PM-MDD fractures and placement of a long horizontal supra-fibular belt plate extending from posteromedial to lateral.33
The PF and SF windows represent the options for PL column management from lateral. However, within the EAL approach, for the management from posterior and the application of direct posterior plates or screws, the RF window is required.4,19 This third window corresponds to the deep PL interval described by Carlson in 1998,17 and subsequently used in the approaches described by Yu et al.18 (straight direct PL skin incision), and Frosch et al.19 (straight lateral skin incision). Several authors reported no complications and better clinical results using approaches based on this RF window compared to anterolateral approaches particularly when the posterior cortex is disrupted.5,20,58 However, more complex anatomical dissection is required.4 This window is developed through the interval between the CPN and LSCN,45,46 and is limited by the ATA distally,6 and by the popliteal neurovascular bundle medially.50 Short posterior buttress plating can be used in this limited working space,4,18,19 being this option especially indicated in split or shear-type fractures39 with posterior deformity.2,40 In our practice, two additional options can be considered to increase the usefulness of this window. Firstly, to be able to use longer posterior vertical plates, the RF window can be combined with posteromedial approaches, even percutaneous, for distal fixation of an oblique PL plate (Fig. 8). In this respect, for large PL column fractures extending below the level of the ATA, requiring direct reduction of distal cortex fragments and long PL plates, the MOL approach (from posteromedial) may be suitable to overcome the ATA limitation.33 The second option is the use of horizontal belt plates (with screws from posterior) combining the RF and PF windows (Fig. 6), being this option especially considered in PL column depression or non-contained peripheral rim-type fractures39,52 with posterior deformity.2,40 Regarding the MDD concept,2 in PL-MDD or posterior-MDD fractures, with the PL column presenting posterior deformities (e.g. posterior angulation, depression or displacement), the RF window may allow to reduce and counteract these deformities from posterior (Figs. 6B and 7A).
In some cases, the three previously described windows, or equivalent surgical approaches, may be insufficient to achieve an adequate outcome, thereby requiring an additional step to improve exposure and expand surgical options.2,4,9,39 Although the skin incision of the versatile EAL approach would readily allow a lateral femoral epicondyle (LFE) osteotomy (as an alternative fourth window), we prefer to consider the fibular neck osteotomy as the fourth window for several reasons. The fibular osteotomy provides greater articular visualization in comparative studies with the LFE osteotomy.29 Additionally, direct articular and metaphyseal control in fractures involving the tibiofibular joint area can be one of the indications for the trans-fibular window (Fig. 10),2,23,24 whereas the LFE osteotomy does not allow equivalent exposure and control of the posterior metaphyseal region concealed by the fibula.4 Moreover, sometimes the fibular head has a blocking effect for reducing the PL column, requiring the elevation of the fibular head, particularly when the split divides two large fragments in the tibiofibular area,24 or in cases with trapped extruded fragments (Fig. 10). Shen et al.24 also included articular surface collapse >12mm, hidden by the fibula and requiring clear articular exposure, among their indications for fibular osteotomy. Regarding other aspects, some authors justify the use of LFE osteotomy by highlighting its potential to reduce the risk of neurovascular injury compared with fibular osteotomy.29 Nevertheless, in addition to previous comparative considerations, the LFE osteotomy without an additional posterior window (or RF window) does not allow posterior buttress plate fixation.3,4,27,30 In this respect, the posterior window carries a similar risk of neurovascular injury, whether or not a fibular osteotomy is performed.3,6 In conclusion, the versatile EAL approach, through the combination of the RF and TF windows, provides complete lateral and PL column exposure (articular and metaphyseal), and allows maximum PL column fixation options (from lateral, from posterior and even through the tibiofibular joint area), with only limited additional CPN dissection beyond that required for the RF window.2 In several series using fibular osteotomies, no neurovascular injuries, osteotomy nonunion, or knee instability were reported.2,21–24 From a practical standpoint, our main indication for using the TF window is when the previous three windows are insufficient to deal with the complexity of the fracture. In our experience, particularly PL-MDD fractures with the MDD located just at the tibiofibular area2,40 and presenting severe PL column deformities (large depression or split-depression under the level of the fibular head, angulation towards this area, irreducible split in this area) or blocked extrusions, may require progressing to the TF window.
This study has some potential limitations. The anatomical study was based on only four cadaveric specimens. However, our anatomical findings were consistent with those reported in the literature. The reduction and fixation techniques proposed for each window were derived from cadaveric exposure. Although these techniques appeared technically feasible based on the anatomical exposure obtained, reduction maneuvers or plate application were not formally evaluated in this study using non-fractured cadaveric specimens. Nevertheless, their feasibility is illustrated by representative clinical case examples outlined in the figures of this paper. The suggested indications for each window are based on theoretical assumptions and our clinical experience and should therefore be considered a preliminary framework until validated by dedicated clinical studies. Although no relevant skin complications related to the incision design have been observed in our practice, wound outcomes could not be formally assessed in this cadaveric study. Further clinical studies are required to confirm the safety and effectiveness of this approach.
The strength of this study is that it presents a detailed description of this approach and the surrounding complex anatomy, making it reproducible for surgeons dealing with complex tibial plateau fractures. The anatomical and clinical rationale for this modified approach is described in detail and reinforced by clinical case examples. Furthermore, we propose additional technical options and integrate, within a single approach, most of the previous techniques described for the management of PL column fractures from lateral or posterolateral. The inclusion in this paper of potential indications based on the MDD concept and related deformities of the PL column may contribute to a better understanding of these fractures8 and may assist in anticipating the optimal surgical window. The versatility of the approach may also offer clinical benefits by enabling stepwise intraoperative progression to the appropriate window according to intraoperative fracture requirements. In this sense, the four windows can also be considered complementary, allowing the use of some techniques through combinations of different windows. Within a fracture-specific surgical strategy based on the MDD concept,2,40 the progressive four-window configuration of the versatile EAL approach, in combination with the MOL approach,33 may represent a comprehensive surgical tool set for managing complex PL column fractures. Deep knowledge of the anatomy and careful surgical dissection are essential to manage these complex injuries.
ConclusionsOn the basis of the present cadaveric study, the versatile EAL approach is a feasible option to access lateral and PL columns in tibial plateau fractures. The skin incision design optimizes the relationship between anatomical limits and the requirements for deep exposure. The four progressive windows (PF, SF, RF, TF) may provide versatility by gradually increasing PL column exposure and expanding the available reduction and fixation options to accommodate the specific features or requirements of the fracture. Complete articular and metaphyseal exposure of the PL and lateral columns can be achieved through progression to the final window with fibular osteotomy.
Level of evidenceLevel of evidence: IV.
Author's contributionsJBM developed the idea and designed the approach. JBM designed the study. BOL, PFC, AMH, EMM, JLPB and MHP made some contribution to the study design. JBM and PFC performed the cadaveric dissections and the anatomical study. JBM and BOL performed the surgeries presented in the figures. JBM and BOL drafted the manuscript. JBM made the anatomical drawings and diagrams. JBM performed the figures. All authors made some contribution in the evaluation and recommendations for the final manuscript. All authors read and approved the final manuscript.
Ethics approval and consent to participateThe clinical cases included in this study were reviewed and approved by the Clinical Research Ethics Committee of Complejo Hospitalario Universitario de Canarias (CEIm CHUC. Code: CHUC_2022_110), in accordance with applicable regulations. Informed consent for the use of clinical data and images was obtained from all patients.
The anatomical cadaveric study was conducted using specimens obtained through the Body Donation Program of the Universitat de Lleida, in accordance with Spanish legislation and institutional regulations governing the use of human bodies for teaching and research purposes. According to national regulations, ethical committee approval and informed consent from next of kin are not required for anatomical studies performed exclusively on donated cadaveric material.
All procedures were conducted in compliance with the principles of the Declaration of Helsinki and ensured respectful handling and anonymity of human remains.
Consent for publicationNot applicable.
FundingNot applicable.
Declaration of competing interestsThe authors declare that they have no competing interests.
The authors thank the Department of Anatomy, Faculty of Medicine, Universitat de Lleida, for the support and collaboration in this study.


