



Insertional Achilles tendinopathy (IAT) significantly impairs function and quality of life, particularly in young athletes. When conservative treatment fails, surgical options include Zadek osteotomy and calcaneoplasty with tendon reinsertion. Although certain preoperative radiological parameters, such as calcaneal inclination and tuberosity length, may influence functional outcomes, comprehensive studies analyzing their impact on calcaneoplasty results remain limited.
ObjectivesTo evaluate the mid- and long-term effectiveness of calcaneoplasty with Achilles tendon reinsertion in patients with refractory IAT and to assess the relationship between preoperative radiological parameters (calcaneal inclination) and postoperative functional outcomes.
MethodsA retrospective analysis was conducted on 38 patients who underwent calcaneoplasty with reinsertion between 2011 and 2024. Mean follow-up was 22 months (IQR: 71) with a median age of 55 years (IQR: 10). Preoperative radiological parameters (Ruch, Fowler-Phillips, CLA, BRINK angles, among others) and functional scales (VAS, AOFAS, EFAS, VISA-A, Tegner) were assessed before and after surgery.
ResultsSignificant postoperative improvement was observed across all functional scales (p<.001, Wilcoxon signed-rank test). Mean VAS pain scores decreased from 8.75±1.27 to 1.71±2.02, while AOFAS scores increased from 38.36±14.55 to 88.82±11.95. EFAS and VISA-A scores improved by 16.46 and 45.59 points, respectively. Tegner scores showed an increase of 50.48 points in athletic capacity. Two complications (5.26%) were reported: one suture granuloma and one case of lateral plantar nerve neuralgia, both successfully managed conservatively. No significant correlation was found between calcaneal inclination or tuberosity length and postoperative functional outcomes. Strengths of the study include a comprehensive functional assessment and consistent follow-up, while limitations include the retrospective design and use of two reinsertion techniques (single- and double-row), with no significant differences in outcomes.
ConclusionCalcaneoplasty with Achilles tendon reinsertion is effective for refractory insertional Achilles tendinopathy, providing sustained mid- and long-term benefits. Preoperative radiological parameters were not significantly associated with postoperative functional outcomes.
La tendinopatía insercional del tendón de Aquiles (TIA) afecta significativamente a la funcionalidad y la calidad de vida, especialmente en deportistas jóvenes. Cuando el tratamiento conservador fracasa, las opciones quirúrgicas incluyen la osteotomía tipo Zadek y la calcaneoplastia con reinserción. Aunque ciertos parámetros radiológicos preoperatorios, como la inclinación calcánea y la longitud de la tuberosidad, pueden influir en los resultados funcionales, los estudios exhaustivos que analizan su impacto en los resultados de la calcaneoplastia son limitados.
ObjetivosEvaluar la eficacia a medio y a largo plazo de la calcaneoplastia con reinserción en pacientes con TIA refractaria al tratamiento conservador y analizar la relación entre los parámetros radiológicos preoperatorios (inclinación calcánea) y los resultados funcionales postoperatorios.
MétodosSe realizó un análisis retrospectivo de 38 pacientes que se sometieron a calcaneoplastia con reinserción entre 2011 y 2024. El seguimiento promedio fue de 22meses (IQR: 71) con una mediana de edad de 55años (IQR: 10). Se analizaron los parámetros radiológicos preoperatorios (ángulos de Ruch, Fowler-Phillips, CLA, BRINK, entre otros) y las escalas funcionales (EVA, AOFAS, EFAS, VISA-A, Tegner) antes y después de la cirugía.
ResultadosSe observó una mejoría significativa en todas las escalas funcionales postoperatorias (p<0,001, prueba de rangos con signo de Wilcoxon). La EVA mostró una reducción media del dolor de 8,75±1,27 a 1,71±2,02 y se objetivó un aumento de la puntuación de AOFAS de 38,36±14,55 a 88,82±11,95. Las escalas EFAS y VISA-A mostraron mejoras de 16,46 y 45,59 puntos, respectivamente. El Tegner mostró un aumento de 50,48 puntos en la capacidad atlética. Se reportaron dos complicaciones (5,26%): un granuloma por sutura y un caso de neuralgia del nervio plantar lateral, tratados ambos con éxito de forma conservadora. Sin embargo, no se encontró una correlación significativa entre la inclinación calcánea o la longitud de la tuberosidad y los resultados funcionales postoperatorios. Entre las fortalezas del estudio destaca un análisis funcional exhaustivo y un seguimiento uniforme; las limitaciones incluyen el diseño retrospectivo y el uso de dos técnicas de reinserción (hilera simple y doble), sin diferencias significativas en los resultados.
ConclusiónLa calcaneoplastia con reinserción es eficaz para la tendinopatía insercional refractaria al tratamiento conservador, con beneficios a mediano y a largo plazo. Los parámetros radiológicos preoperatorios no se asociaron significativamente con los resultados funcionales postoperatorios.
Insertional Achilles tendinopathy (IAT) is a common cause of hindfoot pain, particularly in middle-aged and active adults. This complex condition has a multifactorial aetiology, including mechanical factors, structural abnormalities of the calcaneus, and degenerative changes in the enthesis.1,2 Clinically, patients report localised pain at the Achilles tendon insertion, morning stiffness, and progressive limitation of walking or athletic activity. Diagnosis is based on medical history, physical examination, and imaging studies, especially lateral ankle radiographs and magnetic resonance imaging (MRI), which allow for the evaluation of both bone deformities and the degree of tendon degeneration.3
Initial treatment is conservative, including relative rest, physical therapy, orthotics, and shockwave therapy.4 However, approximately 20–30% of cases do not respond adequately to these measures and require surgical treatment.4 The two main surgical alternatives described are dorsal calcaneal osteotomy (Zadek osteotomy) and calcaneoplasty with Achilles tendon reinsertion.
Zadek osteotomy is primarily indicated in patients without significant tendon degeneration. It works by modifying the tendon's traction vector through a dorsal subtraction wedge osteotomy of the posterior calcaneal tuberosity.5 By subtracting the wedge, the posterior calcaneal tuberosity is reoriented, elevating the tendon's insertion point and reducing impingement, thus mitigating the impingement without the need for tendon debridement.5 In contrast, reinsertion calcaneoplasty is indicated in cases with objective findings of tendon degeneration and prominent bone deformities. This technique allows for the resection of the posterosuperior border of the calcaneus, the removal of degenerated tendon tissue, and the reinsertion of the Achilles tendon using bone anchors.6
Several studies have attempted to correlate morphological radiological parameters with clinical outcomes in the surgical treatment of TIA. In this regard, studies on the Zadek osteotomy have demonstrated that certain radiographic parameters, such as the Fowler-Phillips angle and calcaneal tilt, are significantly associated with clinical results.7,8 However, most of these studies focus on the choice between osteotomy and bone resection techniques, without specifically analysing the prognostic value of these parameters on functional outcomes after calcaneoplasty with reinsertion.
Furthermore, it is important to emphasize that IAT should not be understood solely as a biomechanical problem. The enthesis is the insertion point of a tendon into a bone, and the concept of the “enthesis organ,” whose prototype is the Achilles–calcaneal insertion, describes a functional complex designed to dissipate tensile and compressive forces and ensure a solid anchor to the bone.9 This complex consists of a gradual transition of tissues, from the tendon (with tenocytes and collagen fibres) to non-mineralised fibrocartilage, then to mineralised fibrocartilage, and finally to the bone.9 It also includes adjacent structures such as a bursa and a fat pad that act as shock absorbers to mitigate mechanical stress.9 This histopathological approach reinforces the need to evaluate each case individually, considering not only the morphological parameters of the hindfoot but also the degree of structural involvement of the tendon.9
The aim of this study is to analyse the clinical and functional outcomes obtained after calcaneoplasty with Achilles tendon reinsertion and to explore possible associations between certain preoperative radiological parameters and postoperative evolution. This seeks to provide additional evidence that contributes to better patient selection and optimised surgical planning for this pathology.
Materials and methodsStudy designThis is a retrospective, descriptive, non-experimental study that includes all consecutive calcaneoplasty procedures with Achilles tendon reinsertion performed between January 2011 and December 2024. All cases were operated on by members of the Centre's Foot and Ankle Unit. The study was reviewed and approved as a research project by the centre's Clinical Research Ethics Committee, meeting all necessary requirements.
The inclusion criteria included all patients diagnosed with IAT who underwent open calcaneoplasty with Achilles tendon reattachment and who had received at least 6 months of conservative treatment prior to surgery, with magnetic resonance imaging (MRI) showing more than 40% involvement of the entheseal organ. Patients with less than 6 months of follow-up, those without preoperative radiographs, and those who did not complete pre- or postoperative functional assessments were excluded. No sample size calculation was performed. A retrospective case series of patients meeting the inclusion criteria was selected. The total number of patients selected was 38.
Study variablesDemographic data of the included patients, such as age, sex, laterality, and body mass index (BMI), were recorded. Complications secondary to surgery were also recorded
Radiographic analysisPreoperative weight-bearing lateral radiographs of the ankle and foot were taken to determine the following radiological parameters:
- -
X/Y ratio. Total calcaneal length divided by the length of the calcaneal tuberosity, with a normal value of 2.5.
- -
Ruch pitch angle. Angle between the horizontal and a line tangent to the inferior border of the calcaneus passing through the point of support, with a normal value between 20° and 30°.
- -
Fowler-Phillips angle. Angle formed by the tangent to the posterior border of the calcaneal tuberosity and the line passing through the lowest point of support on the posteromedial tuberosity to the end of the calcaneocuboid joint line, with a normal value greater than 75°.
- -
Calcaneal pitch angle. Angle between the tangent line to the inferior calcaneal border passing through the support point and the plantar line, with normal values between 20° and 30°.
- -
Chauveaux-Liet angle (CLA). Angular difference between the Ruch inclination angle and the angle formed by a line perpendicular to the ground passing through the posterior calcaneal border and the tangent to the posterior tuberosity passing through the same point, with a normal value of 12°.
- -
Botchu-Reilly-Iyengar-Nischal-Kakarala angle (BRINK). Angle between the tangent line to the plantar surface of the calcaneus and the line connecting the highest point of the calcaneal tuberosity and the anterosuperior extremity of the calcaneus, with normal values greater than 20°–25°.
To evaluate the functional outcomes achieved with surgery, data were obtained from the Visual Analogue Scale (VAS), AOFAS, EFAS, VISA-A, and the Lysholm-Tegner scales. Preoperative and final follow-up values were recorded.
Statistical analysisCategorical variables were represented as frequencies and percentages. Continuous variables were reported as means and standard deviations (SD). The chi-square (@χ2) test or Fisher's exact test was used to evaluate qualitative variables, while the Student's t-test was used for quantitative variables. The normality of the sample was assessed using the Shapiro–Wilk test (p=.02), which rejected the hypothesis of normality; therefore, the Wilcoxon signed-rank test was used to compare the pre- and postoperative functional scales. The relationship between preoperative calcaneal tilt and postoperative functional outcomes was studied using Spearman's rank correlation coefficient. For all statistical tests, a p-value <.05 was considered statistically significant. The analysis was performed using SPSS version 26.0 software (IBM Corp., Armonk, NY, USA).
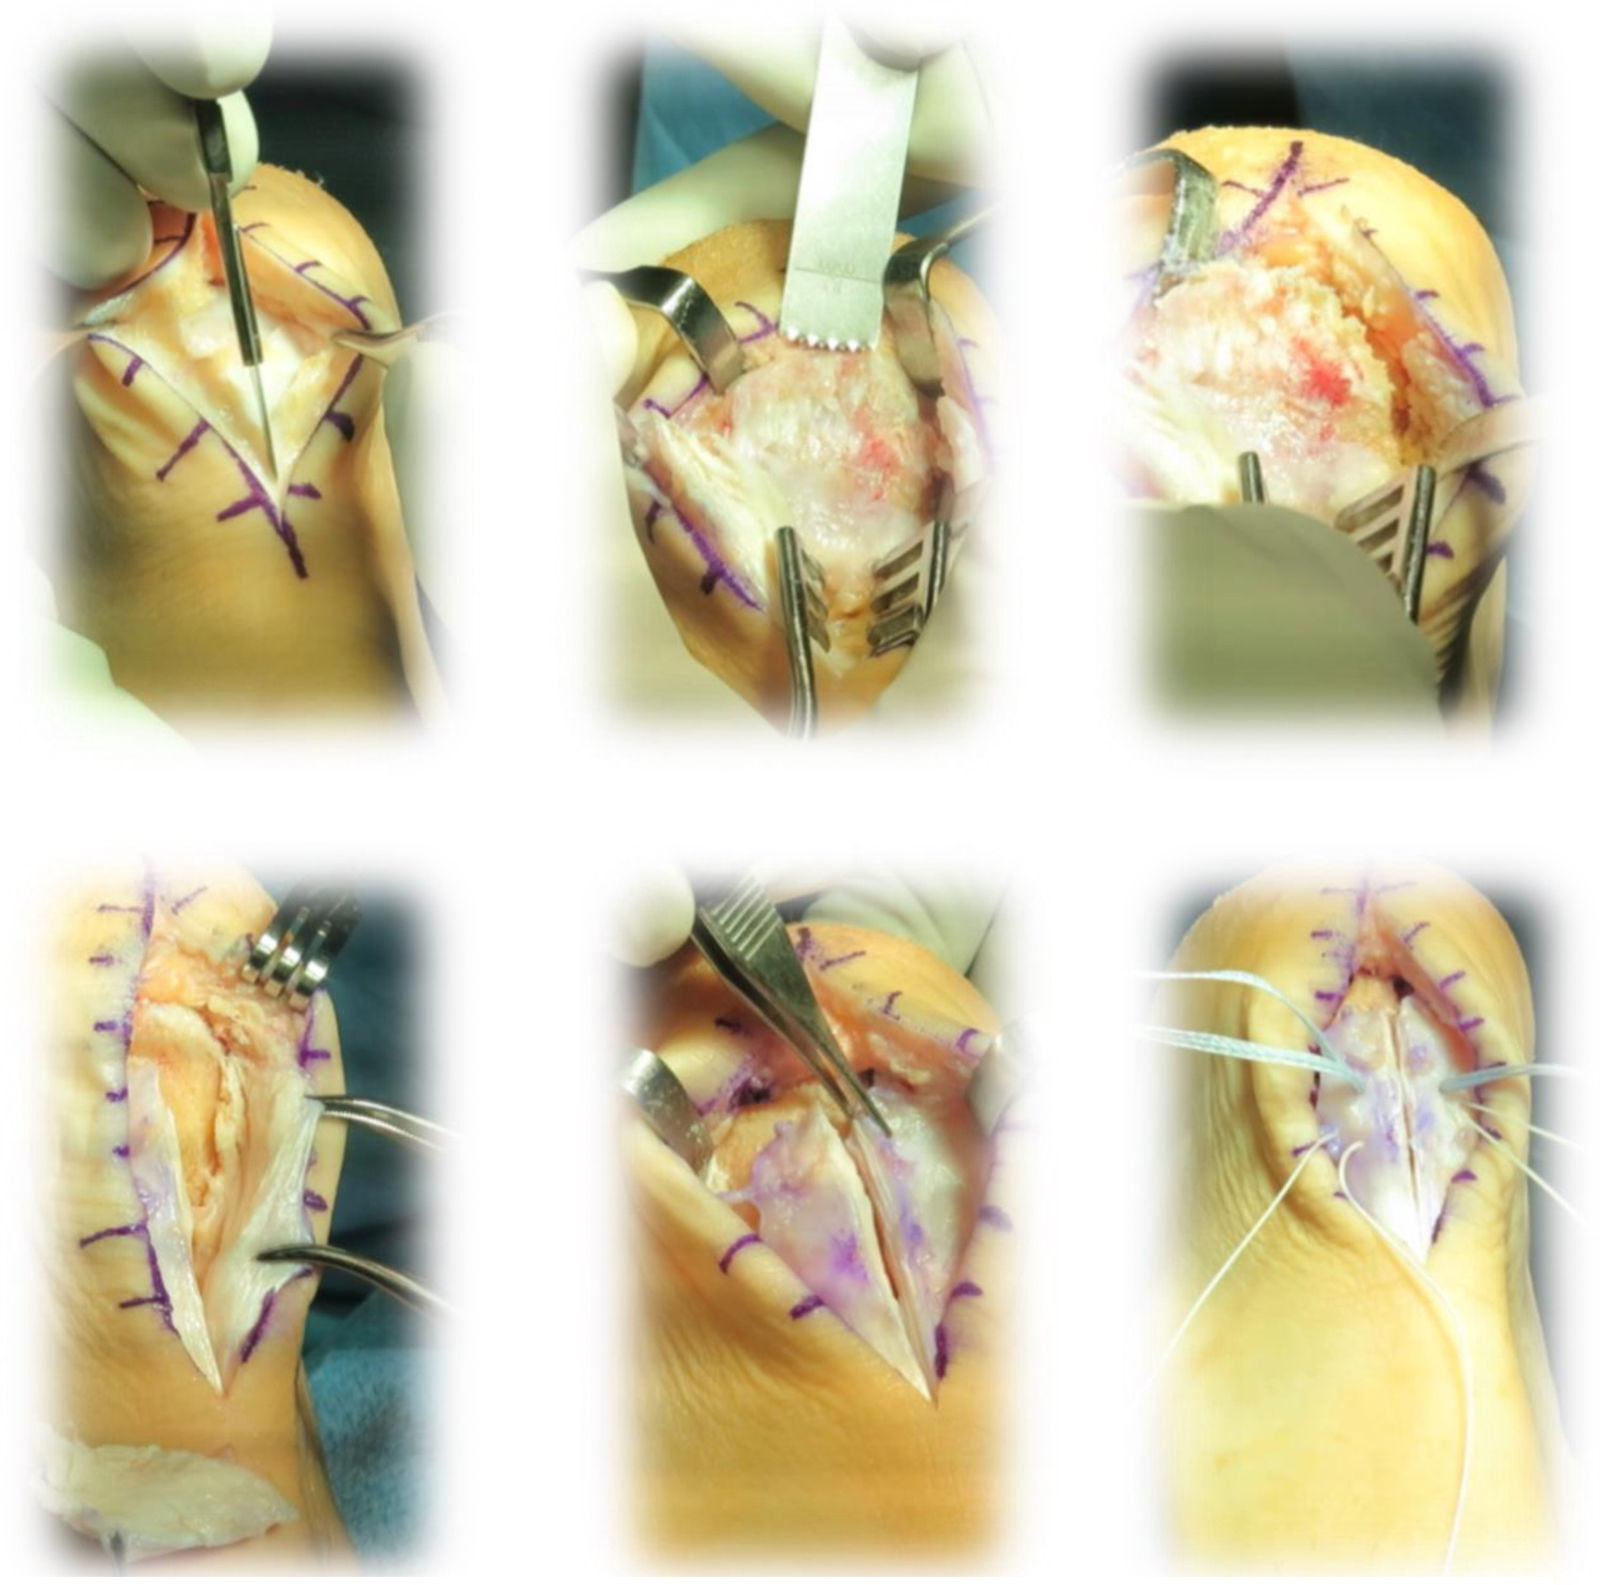
Surgical technique (Fig. 1)Patients were placed in the prone position with a tourniquet applied to the thigh. A straight midline incision was made over the Achilles tendon, exposing the tendon and its insertion on the calcaneus, while avoiding excessive detachment. Subsequently, a longitudinal incision was made over the tendon, detaching all midline fibres, but attempting to preserve the more lateral and medial fibres. Degenerated tissue was identified and removed, preserving healthy tissue. Calcaneoplasty was then performed, initiated with an oscillating saw and completed with a periosteal elevator. Finally, tendon reinsertion was performed using either a double-row or single-row system, advancing the tendon insertion after the calcaneoplasty. The double-row system began to be used in 2017 with the arrival at the hospital and department of the new Achilles SpeedBridge System implantable anchors (Arthrex, Naples, FL, USA). Finally, the paratenon was closed, and the wound was definitively closed.
Results
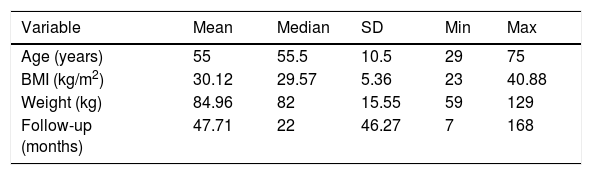
The total number of patients selected was 38 (21 women [55.26%] and 17 men [44.73%]). Twenty-one left ankles (55.26%) and 17 right ankles (44.73%) were operated on. The mean age was 55±10.5 years. The mean BMI was 30.12±5.36. The double-row suture system was used in 21 patients, and the single-row suture system in 17 patients. Additional demographic variables are shown in Table 1.
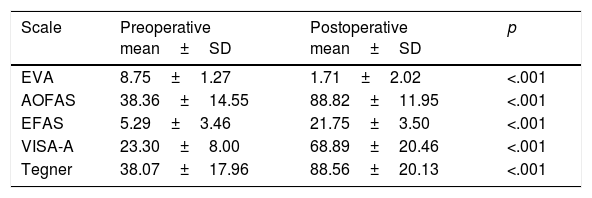
A significant and sustained improvement was observed in all functional scales after surgical intervention with calcaneoplasty and Achilles tendon reinsertion. On the VAS scale, used to assess pain intensity, patients experienced a mean reduction from 8.75±1.27 before surgery to 1.71±2.02 afterward (p<.001). The AOFAS scale showed a significant improvement from a mean preoperative score of 38.36±14.55 to 88.82±11.95 postoperatively (p<.001). The EFAS scale demonstrated an improvement from 5.29±3.46 to 21.75±3.50 (p<.001). The VISA-A scale showed an increase from 23.30±8.00 to 68.89±20.46 points (p<.001), indicating a substantial improvement in terms of pain and physical activity. Finally, the Tegner scale demonstrated an improvement from a mean of 38.07±17.96 to 88.56±20.13 points (p<.001). These results are shown in Table 2.
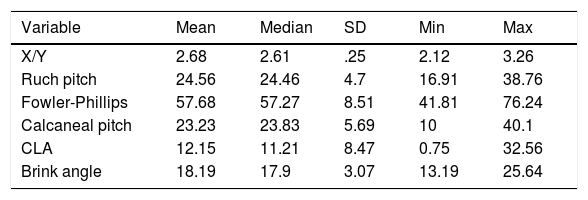
Regarding the preoperative radiological parameters (Table 3), the following values were obtained: the X/Y parameter had a mean of 2.68±.25; The Ruch inclination angle showed a mean of 24.56°±4.70°; the Fowler-Phillips angle had a mean of 57.68°±8.51°; the calcaneal inclination had a mean of 23.23°±5.69°; the CLA angle had a mean of 12.15°±8.47°; and finally, the Brink angle had a mean of 18.19°±3.07°.
Radiological preoperative parameters.
| Variable | Mean | Median | SD | Min | Max |
|---|---|---|---|---|---|
| X/Y | 2.68 | 2.61 | .25 | 2.12 | 3.26 |
| Ruch pitch | 24.56 | 24.46 | 4.7 | 16.91 | 38.76 |
| Fowler-Phillips | 57.68 | 57.27 | 8.51 | 41.81 | 76.24 |
| Calcaneal pitch | 23.23 | 23.83 | 5.69 | 10 | 40.1 |
| CLA | 12.15 | 11.21 | 8.47 | 0.75 | 32.56 |
| Brink angle | 18.19 | 17.9 | 3.07 | 13.19 | 25.64 |
When correlating the different scales with the preoperative measurement of calcaneal tilt, no statistically significant differences were found (p=.467 with the AOFAS results; p=.297 with the EFAS results; p=.285 with the VISA-A results; and p=.136 with the Tegner scale results).
Regarding complications, two patients (5.26%) experienced them. One case presented with a suture-related granuloma, and the other developed lateral plantar neuralgia. Both were managed conservatively without the need for re-surgical intervention and with satisfactory resolution.
DiscussionInsertional Achilles tendinopathy (IAT) is a progressive and degenerative condition associated with repetitive microtrauma, chronic inflammation, and structural changes at the tendon insertion, resulting in significant pain and dysfunction.1,3 The lack of response to conservative treatment in a high percentage of patients has led to the development of multiple surgical options, including calcaneoplasty with tendon reinsertion. In the present study, this technique has proven to be highly effective, with significant functional improvement on all evaluated scales and a substantial reduction in pain, supporting the surgical approach in refractory cases and reinforcing the role of tendon reinsertion in restoring the functionality of the Achilles–calcaneal–plantar complex. Furthermore, the low complication rate observed confirms the safety of this procedure and its viability as a standard treatment option in patients with severe IAT.
The results obtained are similar to those reported in the most recent literature, both in terms of pain management (VAS) and functional outcomes.10–15 Abarquero-Diezhandino et al. present a series of 13 patients in which they obtained an improvement in the VAS scale from 8.8 to 1.3 points and from 34.8 to 90.9 points in the AOFAS scale (increase of 56.1 points [95% CI: 48.1–64.1; p<0.01]).10 In the series of 42 patients presented by Greiner et al., the VAS scale improved from 8.91 to 1.47 and AOFAS evolved from 51.0±12.5 preoperatively to 91.3±14.3 postoperatively; they also used the Foot Function Index (FFI) and Foot and Ankle Outcome Score (FAOS) scales, in which they obtained statistically significant improvements postoperatively.11 Cuesta-Saiz et al. also achieved statistically significant improvement at 3, 6, and 12 months after surgery, going from an AOFAS scale score of 52 points preoperatively to 79 points at 3 months and exceeding 90 points at 6 and 12 months.12 The superiority of double-row calcaneoplasty over allograft was demonstrated in the study by Yan et al., with AOFAS scores increasing from 47.2 to 86.3 in the calcaneoplasty group and from 49.4 to 81.9 in the allograft group.13 In larger series, with up to 50 patients, the results remain similar and comparable to those of our series, with the group of Lewis et al. Improvements were observed in the Manchester-Oxford Foot Questionnaire (MOXFQ) score from 48.5 to 12.4 points (p<.01); in the EuroQol EQ-5D-5L quality of life questionnaire, the score improved from 2.7±.46 to 1.2±.37 (p<.01).14
Regarding the number of complications following surgery, the results of this study are similar to those obtained in the most recent case series, with no major complications and only two minor ones: discomfort from a suture that required removal and the development of lateral plantar neuralgia. Lewis et al. reported four minor complications (two superficial infections and two transient neuralgias).14 In the review of 42 patients by Greiner et al., one patient experienced irritation and discomfort due to a suture, which required removal, and two patients developed a superficial infection, for which no further surgery was required.11
Another relevant aspect of our publication is the correlation investigated between preoperative radiological parameters and the clinical-functional outcomes obtained after the surgical procedure. While previous research has analysed the outcomes of this surgical technique, few studies have considered the impact of radiological factors on postoperative recovery. In particular, we studied the influence of the calcaneal pitch, given that a high value has been theoretically associated with a more vertical hindfoot and greater tension on the Achilles tendon insertion, which could compromise functional outcomes. However, our findings did not show a significant correlation between a higher calcaneal pitch and worse clinical outcomes.
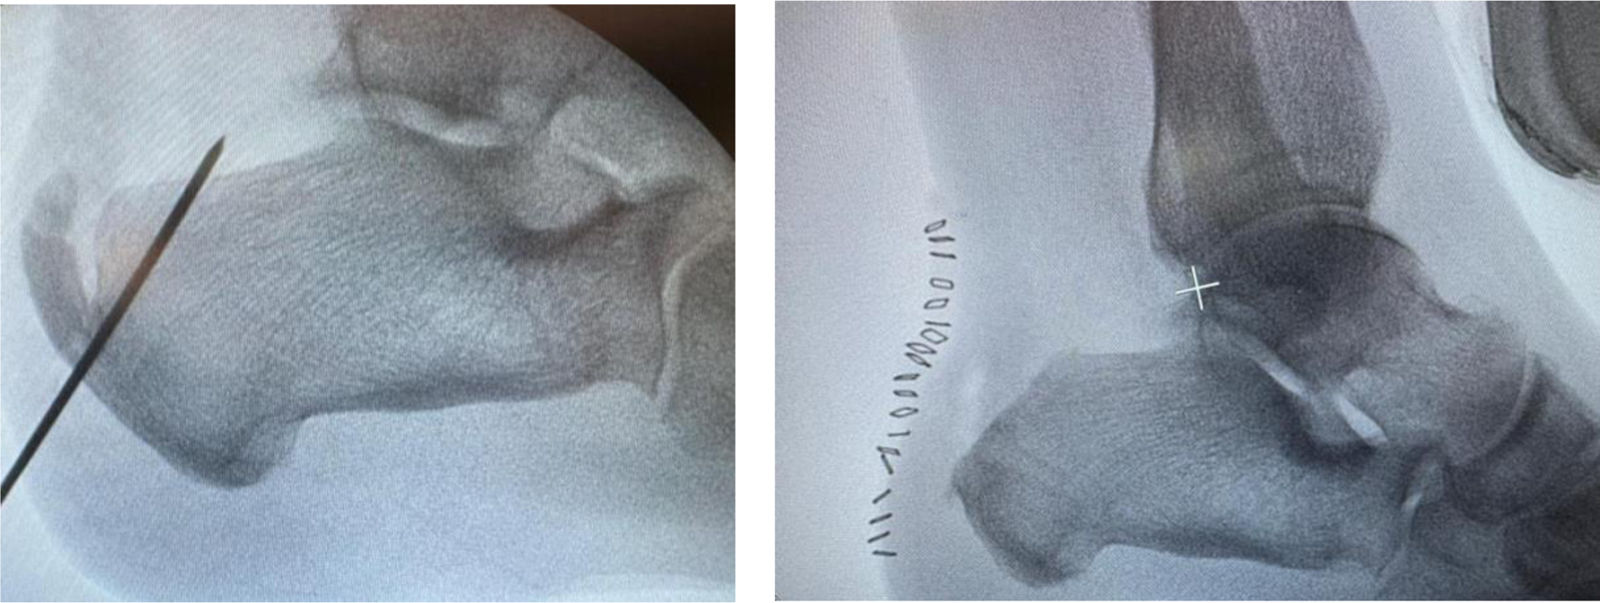
Our study's finding that there is no significant correlation between preoperative radiological parameters and postoperative functional outcomes of calcaneoplasty is consistent with the philosophy of this surgery. Calcaneoplasty focuses on the resection of local pathology, such as degeneration and calcifications, and its success depends directly on the quality of debridement and reinsertion.4,5,9 The overall morphology of the calcaneus, reflected in the radiological angles, is secondary to the severity of the local disease, which is more accurately assessed with MRI, which can identify intratendinous degeneration, extensive calcifications, and retrocalcaneal bursitis.9,15–17 Therefore, the success of calcaneoplasty lies not in correcting an angle, but in eliminating the cause of the pain and restoring tendon function. However, during the course of this research, we have observed intraoperatively and under fluoroscopy that calcaneoplasty allows for the advancement of the new tendon insertion, thus increasing the X/Y angle, as can be seen in Fig. 2, where the X/Y ratio changed from 2.42 before the calcaneoplasty to 2.65 after the procedure and the advancement of the new tendon insertion. In fact, when comparing the mean X/Y ratio preoperatively (2.68±.25), an increase was observed postoperatively (3.04±.2), although this difference was not statistically significant (p=.67). This has not yet been studied in the literature, to the researchers’ knowledge, and could be the starting point for new research hypotheses on whether reinsertional calcaneoplasty allows for modification of the X/Y parameter.

In contrast, studies such as those by Tourne et al. suggest that certain parameters, such as the Fowler-Phillips angle and the X/Y ratio, may be more useful for selecting patients who are candidates for a Zadek-type osteotomy.7 The Zadek osteotomy is a technique explicitly designed to correct pathological biomechanics, making bone angles and proportions the primary selection criteria.8 This technique aims to reduce the length of the calcaneus and elevate the Achilles tendon insertion point, thereby decreasing stress at its insertion.7,18 Studies on the Zadek osteotomy have shown that this technique significantly modifies parameters such as the X/Y ratio, a parameter that measures the total length of the calcaneus relative to the length of the tuberosity.7 Unlike the Zadek osteotomy, calcaneoplasty does not modify the calcaneal inclination. However, resection of the posterosuperior prominence in calcaneoplasty can influence the X/Y ratio, as discussed above.
A rational approach to the surgical treatment of IAT should be based on a structured decision algorithm that integrates clinical assessment, imaging findings, and the intrinsic characteristics of available surgical techniques. In our practice, we advocate for calcaneoplasty and reinsertion for patients with a symptomatic tendon degenerated by more than 40%, provided the calcaneal tilt angle does not exceed 30°. If the tendon degeneration is less than 40% and the calcaneal tilt is greater than 30°, Zadek osteotomy may be a better option.
Both techniques have demonstrated excellent functional outcomes in the literature, with comparable improvements in pain and function scores. The main distinction between the two techniques lies in their complication profile and recovery.19 Calcaneoplasty with reinsertion, which often requires an open approach for thorough tendon debridement and fixation with anchors, can be associated with wound complications such as infection or healing problems.7 In contrast, the Zadek osteotomy, especially when performed percutaneously, has a significantly lower complication rate, particularly regarding wound problems.7,19 Recovery from percutaneous osteotomy is also associated with an earlier return to full activity compared to open tendon debridement.19 This is a critical factor in clinical practice that must be weighed in decision-making.
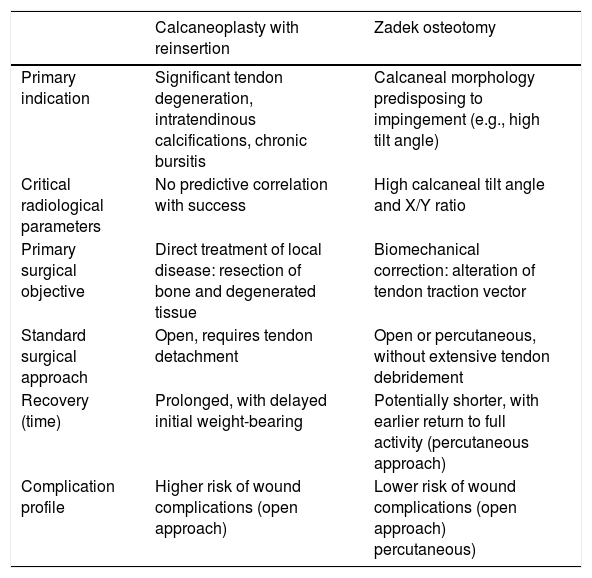
Based on the above, Table 4 summarises the comparison between the two techniques.
Comparative: calcaneoplasty vs. Zadek osteotomy.
| Calcaneoplasty with reinsertion | Zadek osteotomy | |
|---|---|---|
| Primary indication | Significant tendon degeneration, intratendinous calcifications, chronic bursitis | Calcaneal morphology predisposing to impingement (e.g., high tilt angle) |
| Critical radiological parameters | No predictive correlation with success | High calcaneal tilt angle and X/Y ratio |
| Primary surgical objective | Direct treatment of local disease: resection of bone and degenerated tissue | Biomechanical correction: alteration of tendon traction vector |
| Standard surgical approach | Open, requires tendon detachment | Open or percutaneous, without extensive tendon debridement |
| Recovery (time) | Prolonged, with delayed initial weight-bearing | Potentially shorter, with earlier return to full activity (percutaneous approach) |
| Complication profile | Higher risk of wound complications (open approach) | Lower risk of wound complications (open approach) percutaneous) |
However, our study has certain limitations that should be considered. First, the sample size is small. Second, it is a retrospective study, which implies a potential bias in data collection. Furthermore, there was no complete uniformity in the surgical technique employed, as some patients underwent single-row fixation while others used double-row fixation, which could have influenced the clinical outcomes.
ConclusionThis study robustly demonstrates that calcaneoplasty with reinsertion is an effective and safe treatment for refractory insertional Achilles tendon tendinopathy when tendon involvement exceeds 40%. Its success is based on the direct treatment of the degenerative component of the pathology. Although preoperative radiological parameters were not predictive of success for calcaneoplasty in this study, they are fundamental factors for the indication of a Zadek osteotomy.
In short, the choice of surgical technique for Achilles tendonitis is not arbitrary, but rather should be personalised and based on a comprehensive algorithm that includes both calcaneal morphology (radiology) and the histopathological status of the tendon (MRI). This approach elevates the decision-making process, ensuring that each patient receives the surgical intervention best suited to their specific pathological profile, thereby optimising clinical outcomes and patient satisfaction.
Level of evidenceLevel of evidence III.
Ethical considerationsIn all cases, informed consent was obtained from patients for the retrospective collection of their demographic and subjective satisfaction data. This project strictly adheres to national and regional regulations regarding patient privacy and data protection.
FundingThis research did not receive specific funding from public or commercial sector agencies.
Conflict of interestsThe authors have no conflict of interests to declare.


