




The prediction of outcomes in Legg-Calvé-Perthes disease (LCPD) has traditionally relied on femoral head sphericity and hip joint congruence as determinants of the risk of osteoarthritis in adulthood. However, other less explored radiographic parameters may enhance the ability to anticipate functional prognosis. The aim of this study was to analyze the relationship between novel radiographic parameters of LCPD and patient-reported outcome measures (PROMs) in adulthood, including hip function, sports activity level, and quality of life.
Material and methodsA retrospective observational study was conducted in patients over 18 years of age with a history of LCPD in childhood. The latest available hip radiograph was assessed for sphericity and congruence (Stulberg classification), degree of osteoarthritis (Tönnis), femoral neck height (FNH), articulo-trochanteric distance (ATD), epiphyseal extrusion index (EEI), Sharp angle (SA), and neck-shaft angle (NSA). Patients completed the Hip Disability and Osteoarthritis Outcome Score (HOOS), Oxford Hip Score (OHS), modified Harris Hip Score (mHHS), UCLA Activity Level, and the 12-Item Short Form Survey (SF-12).
ResultsA total of 141 adults (154 hips) were included, with a mean age of 31.6 years (19–71) and a mean follow-up of 22.1 years (10–68). The distribution according to Stulberg classification was: class I (12%), II (18%), III (32.5%), IV (28%), and V (10.5%). Sixty percent of patients showed radiographic signs of osteoarthritis, with 34% being Tönnis grade 1. Multiple regression analysis identified femoral neck shortening (FNH), trochanteric overgrowth (reduced ATD), and femoral head extrusion (increased EEI) as predictors of poorer PROMs (p<.05). Regression equations were developed to estimate PROMs in adulthood based on these three parameters.
ConclusionIn addition to femoral head sphericity, joint congruence, and the degree of osteoarthritis, measurement of FNH, ATD, and EEI provides predictive value regarding functional outcomes, sports activity level, and quality of life in adults with a history of childhood LCPD.
La predicción del resultado de la enfermedad de Legg-Calvé-Perthes (ELCP) se ha basado tradicionalmente en la esfericidad y la congruencia articular de la cadera como determinantes del riesgo de coxartrosis en la edad adulta. No obstante, otros parámetros radiológicos poco explorados podrían mejorar la capacidad de anticipar la evolución a nivel funcional. El objetivo de este estudio fue analizar la relación entre nuevos parámetros radiológicos de la ELCP y los resultados percibidos por los pacientes (PROMs) en la edad adulta en términos de función articular, nivel de actividad deportiva y calidad de vida.
Material y métodosEstudio observacional y retrospectivo en pacientes mayores de 18 años con antecedente de ELCP en la infancia. En la última radiografía de cadera disponible se evaluaron la esfericidad y la congruencia (clasificación de Stulberg), el grado de coxartrosis (Tönnis), la altura del cuello femoral (ACF), la distancia artículo-trocantérea (DAT), el índice de extrusión epifisaria (IEE), el ángulo de Sharp (AS) y el ángulo cervicodiafisario (ACD). Los pacientes completaron los cuestionarios Hip Disability and Osteoarthritis Outcome Score (HOOS), Oxford Hip Score (OHS), Harris Hip Score modificado (mHHS), UCLA Activity Level y 12-Item Short Form Survey (SF-12).
ResultadosSe incluyeron 141 adultos (154 caderas), con una edad media de 31,6 años (19-71) y un seguimiento medio de 22,1 años (10-68). La distribución de Stulberg fue: clase I (12%), II (18%), III (32,5%), IV (28%) y V (10,5%). El 60% de los pacientes presentó signos de coxartrosis, siendo el 34% grado 1 de Tönnis. El análisis de regresión múltiple identificó como predictores de peor resultado en PROMs el acortamiento del cuello femoral (ACF), el hipercrecimiento trocantéreo (DAT reducida) y la extrusión femoral (IEE elevado) (p<0,05). Se obtuvieron ecuaciones de regresión que permiten estimar los PROMs en función de estos 3 parámetros.
ConclusiónAdemás de la esfericidad, de la congruencia articular y del grado de coxartrosis, la medición de la ACF, la DAT y el IEE aporta valor predictivo sobre los resultados funcionales, el nivel deportivo y la calidad de vida en la edad adulta de los pacientes que sufrieron ELCP en la infancia.
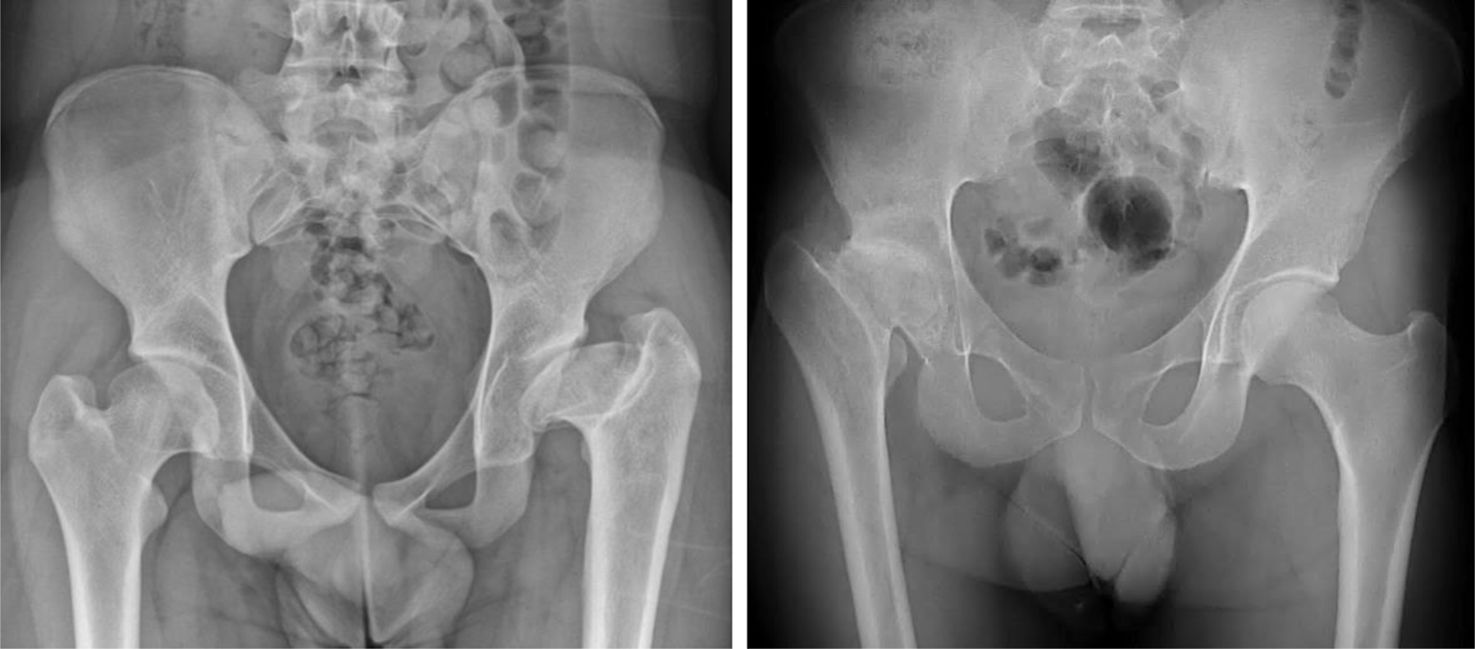
Legg-Calvé-Perthes disease (LCPD) is ischaemic necrosis of the femoral head that occurs in childhood. It causes pain and lameness and affects the shape and function of the hip.1 Although it is self-limiting, it can leave sequelae after skeletal maturity and into adulthood, including functional impairment, lower limb length discrepancy, and early hip osteoarthritis (Fig. 1).2–5

Sequelae of LCPD upon reaching skeletal maturity. The X-ray on the left shows the hips of an 18-year-old male who suffered bilateral LCPD in childhood: the right hip has adequate sphericity and congruency (Stulberg class II), while the left hip has a deformity with severe ovalisation and joint incongruence (Stulberg class V), but without degenerative changes. The X-ray on the right shows the hips of a 40-year-old male who suffered from LCPD in the right hip during childhood, currently presenting a Stulberg class IV deformity (flattening of the head and short neck) and greater trochanteric overgrowth, in addition to grade 3 Tönnis hip osteoarthritis.
The prognosis of LCPD has traditionally been assessed using the Stulberg classification (1981), which determines the risk of developing early hip osteoarthritis based on femoral head sphericity and joint congruency.2 However, this approach does not take into account other components of residual deformity. In recent decades, additional radiological parameters have been described, such as femoral neck shortening, greater trochanteric overgrowth, epiphyseal extrusion, and acetabular dysplasia.6–9
At the same time, the development of new surgical techniques – facilitated by the safe hip dislocation approach proposed by Ganz et al.10 – has enabled the treatment of sequelae through procedures such as osteochondroplasty and relative femoral neck lengthening,11,12 and femoral head reduction osteotomy.13,14
Furthermore, there is growing interest in patient-reported outcome measures (PROMs), which offer a complementary view by assessing function, activity level, and quality of life from the patient's perspective.15 This is particularly relevant given that the presence of hip osteoarthritis does not always correlate with poorer functional perception.
This study aims to analyse radiological parameters of LCPD that have not been described before, and to determine their association with PROMs in adulthood. This will help us to identify which parameters may affect patients’ joint function, sporting ability, and quality of life.
Materials and methodsWe conducted an observational, retrospective study of patients who suffered from LCPD in childhood and were over 18 years of age at the time of evaluation. Cases treated at our institution were included, as well as others diagnosed in different hospitals in Spain, recruited through the Asociación de Familias con Perthes (ASFAPE). Patients with concomitant hip involvement, those who did not authorise the use of clinical data, those who did not have an available recent X-ray (≤12 months) or who did not complete the questionnaires were excluded.
A total of 141 patients (154 hips) were included, 13 (9.2%) of whom had bilateral involvement. A total hip replacement (THR) had been performed in 28 hips (18.2%), although in these cases, the last preoperative X-ray was analysed and the functional situation immediately prior to surgery was recorded.
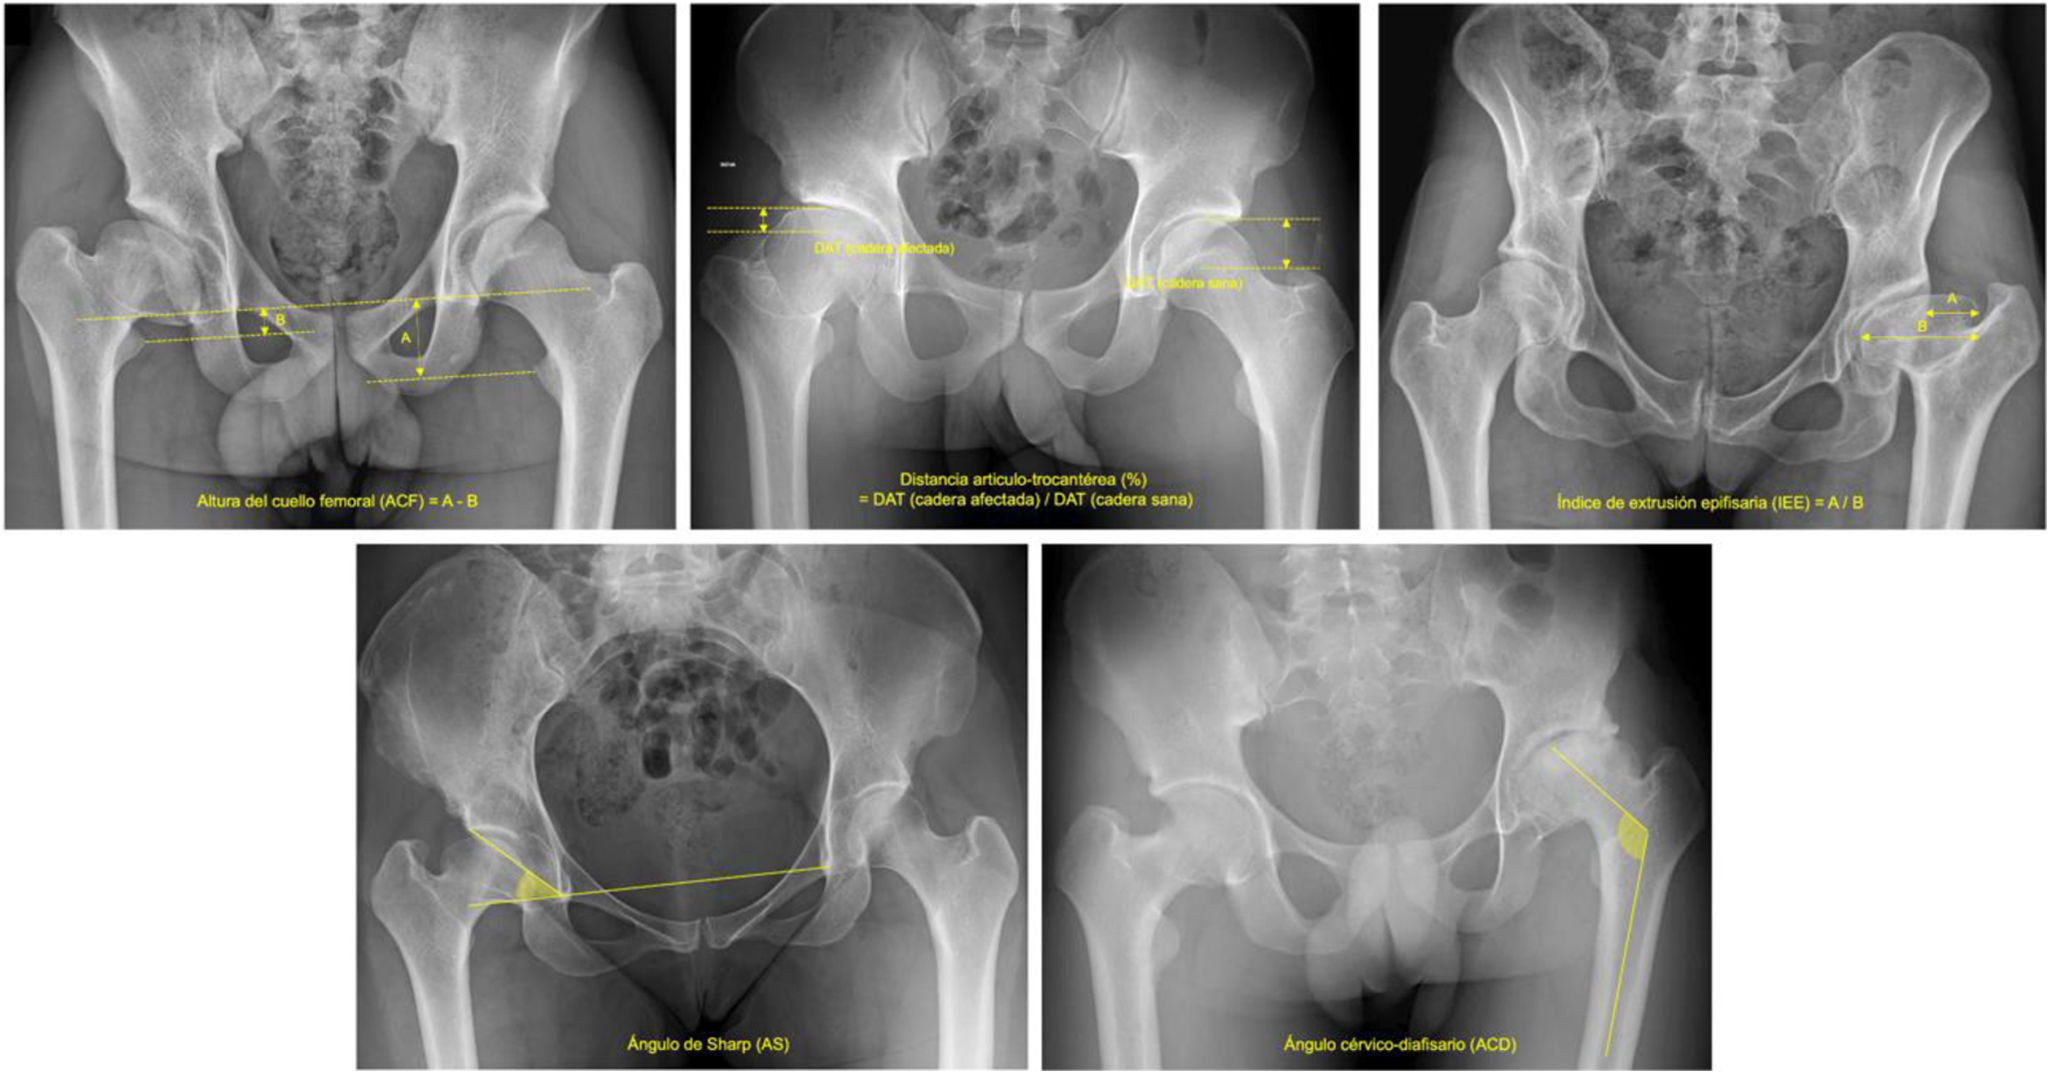
Medical records were reviewed to collect demographic data and information on the treatments received during the active phase of the disease. The most recent hip X-ray was used to evaluate residual deformity according to the Stulberg classification,2 the degree of hip osteoarthritis using the Tönnis classification,20 femoral neck height (FNH) using the Woolson et al. method, comparing the distance between the acetabular teardrop and both lesser trochanters in both hips,16 and trochanteric overgrowth using the articulo-trochanteric distance (ATD)17 expressed as a percentage relative to the contralateral hip (in patients with bilateral involvement, the ATD was defined as the ratio between the most affected hip and the least affected hip, as there are no publications reporting reference values in the healthy population), femoral head extrusion using the epiphyseal extrusion index (EEI),6 acetabular development using the Sharp angle (SA),18 and residual coxa vara using the NSA (neck-shaft angle)19 (Fig. 2).

Radiological parameters analysed in the last available X-ray. The femoral neck height (FNH) was measured as the difference between the distance from the acetabular teardrop to the lesser trochanter in both hips; the articulo-trochanteric distance (ATD) was calculated as the distance between the upper surface of the femoral head and the tip of the greater trochanter, expressed as a percentage relative to the healthy hip; the epiphyseal extrusion index (EEI) was measured as the percentage of acetabular uncovering relative to the horizontal; the Sharp angle (SA) corresponds to the acetabular inclination relative to the horizontal; and the neck shaft angle (NSA) measured the degree of residual coxa vara of the proximal femur.
All patients completed the following questionnaires online: the Hip Dysfunction and Osteoarthritis Outcome Score (HOOS),21 the Oxford Hip Score (OHS),22 the modified Harris Hip Score (mHHS),23 the UCLA Activity Level,24 and the 12-Item Short Form Survey (SF-12).25
The study was approved by our institution's Ethics Committee (code PI-5348), and all participants signed an informed consent form for the anonymised processing of their clinical data.
Statistical analysis was performed using SPSS® Statistics 26 (IBM, Chicago, USA) and R Statistical Software v4.1.2 (R Core Team, 2021). The normality of the continuous variables was verified using the Kolmogorov–Smirnov test (p>.05). The association between the questionnaire results and the Stulberg and Tönnis classifications was evaluated using the Kruskal–Wallis test. For quantitative radiological parameters, a multiple linear regression model was applied, after verifying the normality of the errors (Kolmogorov–Smirnov, p>.05), homoscedasticity, independence of the residuals, and absence of multicollinearity. A statistical significance level of 95% (alpha=.05) was set.
ResultsBaseline characteristicsThe mean age at diagnosis of LCPD was 6.7±2.6 years (range: 3.1–11), while the mean age at the time of the study was 31.6±11.4 years (18.8–70.9). The mean follow-up was 22.1±10.6 years (9.8–68). Eighty-seven patients (61.7%) were male, and the right hip was slightly more affected (85 cases, 55.2%). The mean weight was 73.6±17.9kg (43–140), the mean height was 168.1±8.4cm (150–186), and the body mass index (BMI) was 25.9±5.96kg/m2 (17.4–57.5). Most patients (81.8%) had received some type of treatment during childhood: 55 (36%) used a Petrie cast or abduction orthosis, and 71 (46%) underwent surgery in the active phase (epiphyseal containment) or in the sequelae phase.
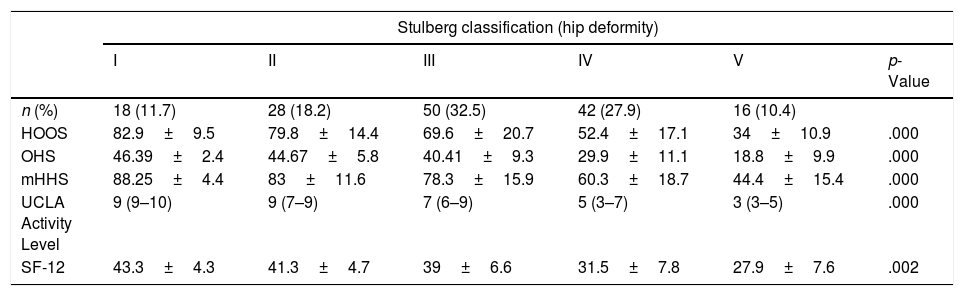
Radiological aspects of the hip (Table 1)The distribution according to the Stulberg classification was class I in 18 hips (11.7%), class II in 28 (18.2%), class III in 50 (32.5%), class IV in 42 (27.9%), and class V in 16 (10.4%). Sixty-point-one percent of the hips (92 cases) showed some degree of joint space narrowing; 64 (41.6%) had osteophytes; 51 (38.3%) had subchondral cysts; and 81 (52.6%) had sclerosis. Overall, 94 hips (61%) showed radiological signs of hip osteoarthritis, with Tönnis grade I predominating (33.8%).
Association between Stulberg classification of hip deformity and Tönnis grade of hip osteoarthritis with patient-reported outcomes (PROMs) (n=154 hips).
| Stulberg classification (hip deformity) | ||||||
|---|---|---|---|---|---|---|
| I | II | III | IV | V | p-Value | |
| n (%) | 18 (11.7) | 28 (18.2) | 50 (32.5) | 42 (27.9) | 16 (10.4) | |
| HOOS | 82.9±9.5 | 79.8±14.4 | 69.6±20.7 | 52.4±17.1 | 34±10.9 | .000 |
| OHS | 46.39±2.4 | 44.67±5.8 | 40.41±9.3 | 29.9±11.1 | 18.8±9.9 | .000 |
| mHHS | 88.25±4.4 | 83±11.6 | 78.3±15.9 | 60.3±18.7 | 44.4±15.4 | .000 |
| UCLA Activity Level | 9 (9–10) | 9 (7–9) | 7 (6–9) | 5 (3–7) | 3 (3–5) | .000 |
| SF-12 | 43.3±4.3 | 41.3±4.7 | 39±6.6 | 31.5±7.8 | 27.9±7.6 | .002 |
| Tönnis classification (hip osteoarthritis) | |||||
|---|---|---|---|---|---|
| 0 | 1 | 2 | 3 | p-Value | |
| n (%) | 60 (39) | 52 (33.8) | 26 (16.9) | 16 (10.4) | |
| HOOS | 80.8±14.1 | 66±17.6 | 45.6±17.6 | 32.9±10.1 | .000 |
| OHS | 44.9±4.7 | 38.6±9.3 | 24±11.5 | 18.4±8.6 | .000 |
| mHHS | 85±9.3 | 75.2±14.6 | 50.9±17.2 | 42.1±15.2 | .000 |
| UCLA Activity Level | 9 (7–10) | 7 (6–9) | 3 (3–5) | 3 (3–4) | .030 |
| SF-12 | 42.1±4.1 | 37.2±6.9 | 29.2±7.3 | 26.7±7.3 | .044 |
HOOS: Hip Disability and Osteoarthritis Outcome Score; mHHS: modified Harris Hip Score; OHS: Oxford Hip Score; SF-12: Short Form Survey.
The Kruskal–Wallis’ test was used to calculate the p-value.
Regarding the new radiological parameters, the mean FNH was .94±.63cm difference from the healthy hip (range: 0–4); the mean ATD was .27±.39, i.e., 27% compared to the healthy hip (−.83–.9); the mean EEI was .25±.01, i.e., 25% lateral extrusion of the affected hip (.04–.5); the mean SA was 41.5±4.9° (25–65); and the mean NSA was 130.3±7 (112–154).
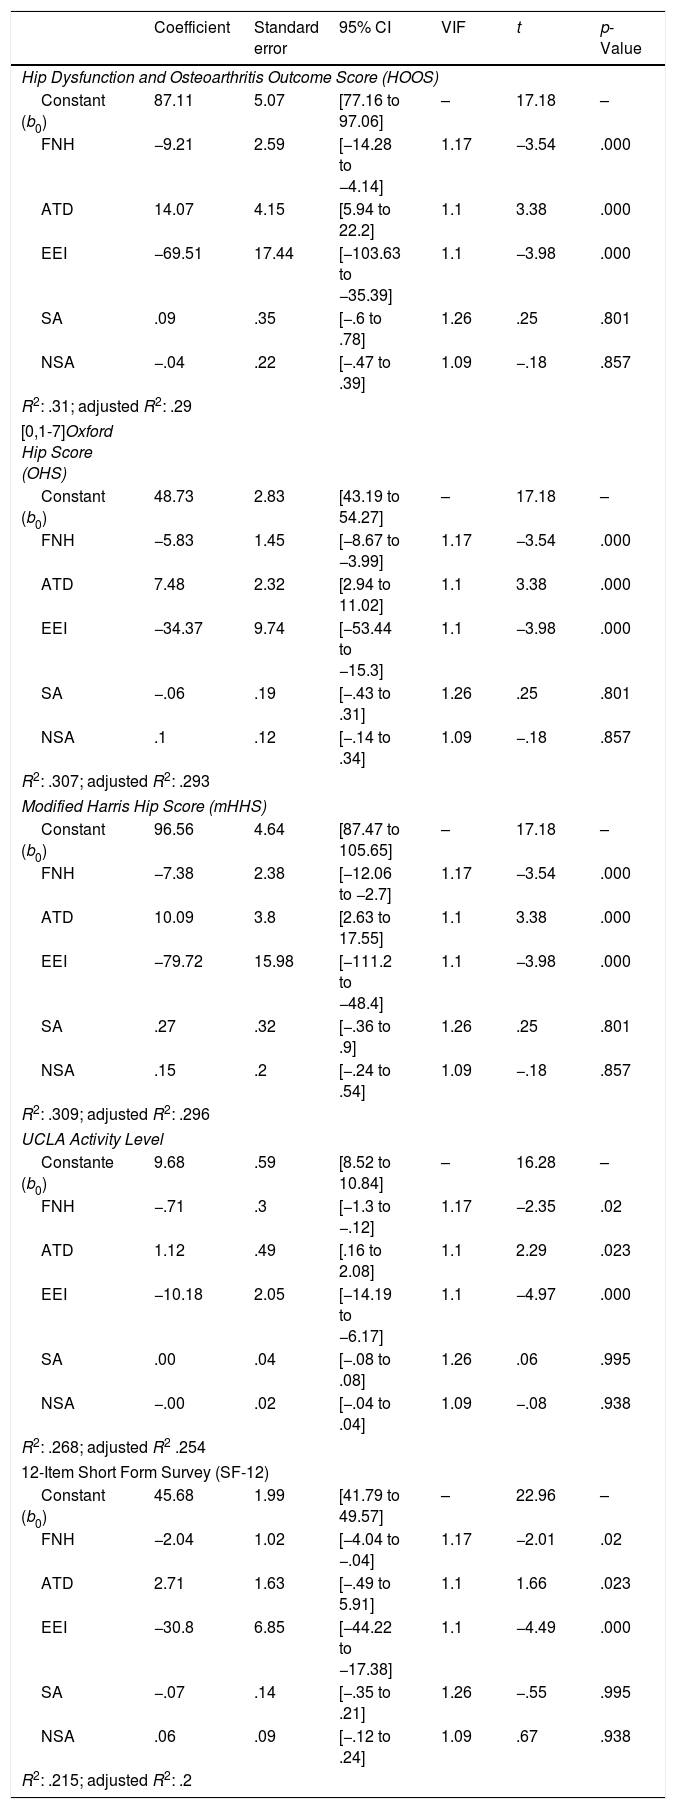
Association of PROMs with radiological aspects of the hip (Tables 1 and 2)The mean HOOS score was 64.6±22.4 (18.7–100), being lower with higher Stulberg classes and higher Tönnis grades (p<.05). The multiple regression model identified FNH, ATD, and EEI as significant predictors (p<.05), explaining 29.7% of the variability (adjusted R2=.297).
The mean OHS score was 36.5±12.5 (6–48). Worse scores were observed with higher Stulberg class, Tönnis grade, and lower FNH, lower ATD, and higher EEI (p<.05). These three parameters explained 29.3% of the variability (adjusted R2=.293).
The mean mHHS score was 71.3±20.4 (20–91). A higher Stulberg and Tönnis grade were associated with worse outcomes (p<.05). Multiple regression showed a significant association with FNH, ATD, and EEI (p<.05), explaining 29.6% of the variability (adjusted R2=.296).
The median UCLA Activity Level score was 7 (2–10), with the most frequent option being ‘regular participation in active events such as cycling’. Patients with higher Stulberg class and Tönnis grade scores showed a lower level (p<.05). Multiple regression confirmed the influence of FNH, ATD, and EEI on activity level (p<.05), explaining 25.4% of the variability (adjusted R2=.254).
Finally, the mean SF-12 score was 36.68±8.25 (17–47), being lower in higher Stulberg classes and Tönnis grades (p<.05). Multiple regression showed that lower FNH, lower ATD, and higher EEI were associated with worse outcomes, explaining 20% of the variability (adjusted R2=.20).
After adjusting for age (younger or older than 35 years) and treatment received in childhood (conservative or surgical), the associations between radiological parameters (FNH, ATD, and EEI) and PROMs remained significant (p<.05).
Prediction of PROMs and regression equationsBased on the regression coefficients (b0) of each independent variable (FNH, ATD, and EEI) (Table 2), predictive equations for PROMs (HOOS, OHS, mHHS, UCLA, and SF-12) were generated. For example, in the HOOS model: for each centimetre increase in the FNH difference, the score decreases by 9.21 points; for each unit (100%) increase in ATD, the score increases by 14.07 points; and for each unit (100%) increase in EEI, the score decreases by 69.51 points, with the other variables remaining constant. The results are shown in detail in Table 3.
Multiple regression study.
| Coefficient | Standard error | 95% CI | VIF | t | p-Value | |
|---|---|---|---|---|---|---|
| Hip Dysfunction and Osteoarthritis Outcome Score (HOOS) | ||||||
| Constant (b0) | 87.11 | 5.07 | [77.16 to 97.06] | – | 17.18 | – |
| FNH | −9.21 | 2.59 | [−14.28 to −4.14] | 1.17 | −3.54 | .000 |
| ATD | 14.07 | 4.15 | [5.94 to 22.2] | 1.1 | 3.38 | .000 |
| EEI | −69.51 | 17.44 | [−103.63 to −35.39] | 1.1 | −3.98 | .000 |
| SA | .09 | .35 | [−.6 to .78] | 1.26 | .25 | .801 |
| NSA | −.04 | .22 | [−.47 to .39] | 1.09 | −.18 | .857 |
| R2: .31; adjusted R2: .29 | ||||||
| [0,1-7]Oxford Hip Score (OHS) | ||||||
| Constant (b0) | 48.73 | 2.83 | [43.19 to 54.27] | – | 17.18 | – |
| FNH | −5.83 | 1.45 | [−8.67 to −3.99] | 1.17 | −3.54 | .000 |
| ATD | 7.48 | 2.32 | [2.94 to 11.02] | 1.1 | 3.38 | .000 |
| EEI | −34.37 | 9.74 | [−53.44 to −15.3] | 1.1 | −3.98 | .000 |
| SA | −.06 | .19 | [−.43 to .31] | 1.26 | .25 | .801 |
| NSA | .1 | .12 | [−.14 to .34] | 1.09 | −.18 | .857 |
| R2: .307; adjusted R2: .293 | ||||||
| Modified Harris Hip Score (mHHS) | ||||||
| Constant (b0) | 96.56 | 4.64 | [87.47 to 105.65] | – | 17.18 | – |
| FNH | −7.38 | 2.38 | [−12.06 to −2.7] | 1.17 | −3.54 | .000 |
| ATD | 10.09 | 3.8 | [2.63 to 17.55] | 1.1 | 3.38 | .000 |
| EEI | −79.72 | 15.98 | [−111.2 to −48.4] | 1.1 | −3.98 | .000 |
| SA | .27 | .32 | [−.36 to .9] | 1.26 | .25 | .801 |
| NSA | .15 | .2 | [−.24 to .54] | 1.09 | −.18 | .857 |
| R2: .309; adjusted R2: .296 | ||||||
| UCLA Activity Level | ||||||
| Constante (b0) | 9.68 | .59 | [8.52 to 10.84] | – | 16.28 | – |
| FNH | −.71 | .3 | [−1.3 to −.12] | 1.17 | −2.35 | .02 |
| ATD | 1.12 | .49 | [.16 to 2.08] | 1.1 | 2.29 | .023 |
| EEI | −10.18 | 2.05 | [−14.19 to −6.17] | 1.1 | −4.97 | .000 |
| SA | .00 | .04 | [−.08 to .08] | 1.26 | .06 | .995 |
| NSA | −.00 | .02 | [−.04 to .04] | 1.09 | −.08 | .938 |
| R2: .268; adjusted R2 .254 | ||||||
| 12-Item Short Form Survey (SF-12) | ||||||
| Constant (b0) | 45.68 | 1.99 | [41.79 to 49.57] | – | 22.96 | – |
| FNH | −2.04 | 1.02 | [−4.04 to −.04] | 1.17 | −2.01 | .02 |
| ATD | 2.71 | 1.63 | [−.49 to 5.91] | 1.1 | 1.66 | .023 |
| EEI | −30.8 | 6.85 | [−44.22 to −17.38] | 1.1 | −4.49 | .000 |
| SA | −.07 | .14 | [−.35 to .21] | 1.26 | −.55 | .995 |
| NSA | .06 | .09 | [−.12 to .24] | 1.09 | .67 | .938 |
| R2: .215; adjusted R2: .2 | ||||||
The independent relationship between the new radiological parameters and the questionnaire scores (PROMs) (n=154 hips).
ATD: articulotrochanteric distance; 95% CI: 95% confidence interval for a population (calculated as the sample mean±(1.96*standard error); FNH: femoral neck height; NSA: neck-shaft angle; SA: Sharp angle; VIF: variance inflation factor.
Equations derived from the multiple linear regression study.
| HOOS=87.11−9.21*FNH+14.07*ATD−69.51*EEIOHS=48.73−5.83*FNH+7.48*ATD−34.37*EEImHHS=96.56−7.38*FNH+10.09*ATD−79.72*EEIUCLA Activity Level=9.68−.71*FNH+1.12*ATD−10.18*EEISF-12=45.68−2.04*FNH+2.71*ATD−30.8*EEI |
ATD: articulotrochanteric distance; EEI: epiphyseal extrusion index; FNH: femoral neck height; HOOS: Hip Disability and Osteoarthritis Outcome Score; mHHS: modified Harris Hip Score; OHS: Oxford Hip Score; SF-12: Short Form Survey.
As there were no previous publications on which to base an a priori sample calculation, a post hoc power analysis was performed using an F-test for multiple regression. With n=141 patients, 3 predictors (FNH, ATD, EEI), α=.05, and a desired power of .80, the study was found to have sufficient power to detect a minimum effect size f2=.06 (partial R2=.057).
DiscussionThe epidemiological profile of our sample is similar to that reported in large series published, with a mean age at diagnosis of 6.7 years (consistent with values reported in the literature between 6 and 7.5 years2,26,27), and a higher prevalence in males, although without a clear predominance, possibly due to the lack of standardised patient selection in most LCPD studies.17,18
In our series, one-third of the hips were classified as Stulberg III, which is a higher percentage than that described by Stulberg in his original series (17%),2 but similar to that reported by Larson et al.5 (32%) and slightly lower than the 40% published by Huhnstock et al.28 This reveals the heterogeneity of the populations included in the main long-term studies. Nevertheless, there is consistent evidence that loss of femoral head sphericity and joint congruency is associated with an increased risk of hip osteoarthritis (Table 1). Notably, the proportion of hips with degenerative changes in our study (61%) clearly exceeds that of other series,4,5,28,29 a difference that does not seem attributable to the mean age or follow-up, which are similar to those in the literature. Rather, it is probably due to methodological factors related to sample selection.
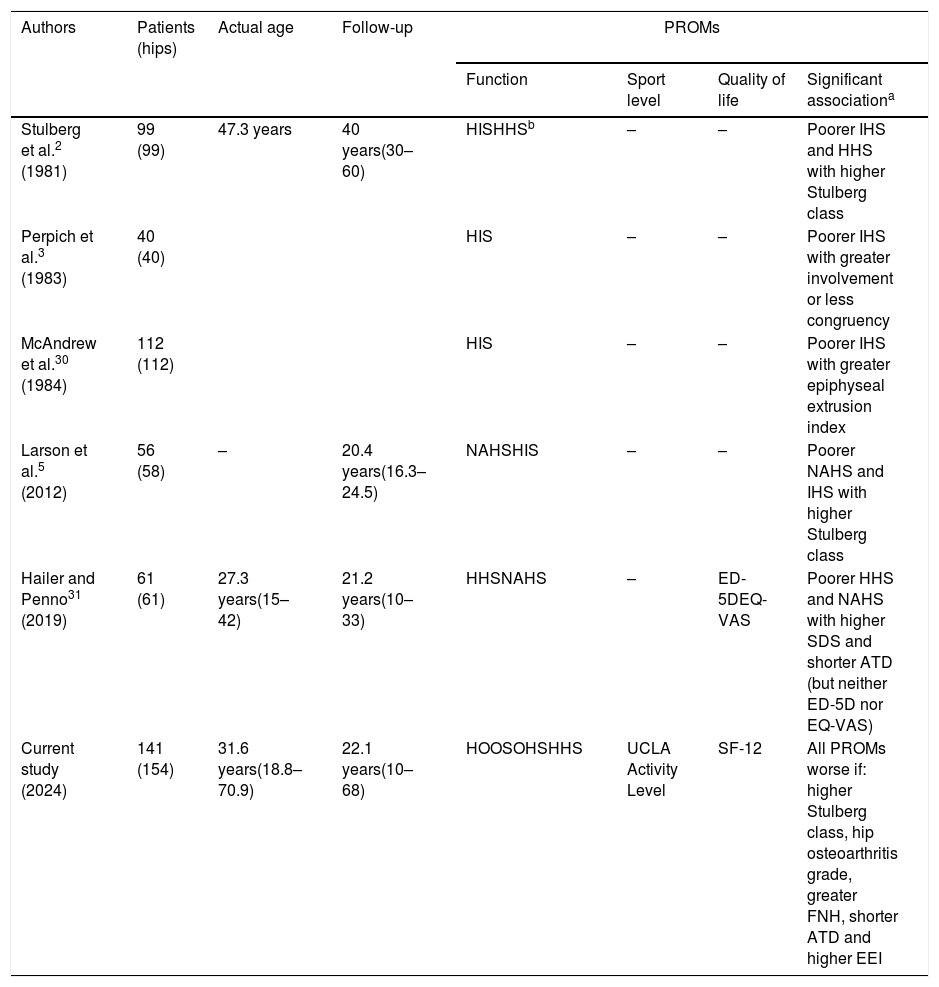
There are few publications relating radiographic parameters to PROMs in LCPD. Generally, a correlation has been described between higher Stulberg classes and poorer patient-perceived outcomes,2,3,5,28,30 which is consistent with our findings and is detailed in Table 4.
Major long-term studies that include PROMs as a measure of outcomes.
| Authors | Patients (hips) | Actual age | Follow-up | PROMs | |||
|---|---|---|---|---|---|---|---|
| Function | Sport level | Quality of life | Significant associationa | ||||
| Stulberg et al.2 (1981) | 99 (99) | 47.3 years | 40 years(30–60) | HISHHSb | – | – | Poorer IHS and HHS with higher Stulberg class |
| Perpich et al.3 (1983) | 40 (40) | HIS | – | – | Poorer IHS with greater involvement or less congruency | ||
| McAndrew et al.30 (1984) | 112 (112) | HIS | – | – | Poorer IHS with greater epiphyseal extrusion index | ||
| Larson et al.5 (2012) | 56 (58) | – | 20.4 years(16.3–24.5) | NAHSHIS | – | – | Poorer NAHS and IHS with higher Stulberg class |
| Hailer and Penno31 (2019) | 61 (61) | 27.3 years(15–42) | 21.2 years(10–33) | HHSNAHS | – | ED-5DEQ-VAS | Poorer HHS and NAHS with higher SDS and shorter ATD (but neither ED-5D nor EQ-VAS) |
| Current study (2024) | 141 (154) | 31.6 years(18.8–70.9) | 22.1 years(10–68) | HOOSOHSHHS | UCLA Activity Level | SF-12 | All PROMs worse if: higher Stulberg class, hip osteoarthritis grade, greater FNH, shorter ATD and higher EEI |
ATD: articulotrochanteric distance; ED-5D and EQ-VAS: quality-of-life questionnaires; EEI: epiphyseal extrusion index; FNH: femoral neck height; HHS: Harris Hip Score; IHS: Iowa Hip Score; NAHS: Nonarthritic Hip Score; OHS: Oxford Hip Score.
However, only the study by Hailer et al. (2019) analysed specific parameters of hip deformity in LCPD and compared them with quality-of-life scales (EQ-5D and EQ-VAS), without finding significant associations.31 In contrast to that study, we observed a reduction in both physical (SF-12 PH) and mental (SF-12 MH) quality of life in our cohort, which was associated with greater deformity (Stulberg) and a higher degree of hip osteoarthritis. Another novel aspect of this study is the analysis of sporting activity levels in adulthood, assessed using the UCLA Activity Level. Our results demonstrate a linear and statistically significant relationship between this index and three specific radiological parameters of LCPD (FNH, ATD, and EEI), a relationship that had not been described to date.
Although no a priori sample size calculation was performed, the post hoc power analysis showed that the sample size (n=154 hips) provides ≥80% power to detect small to moderate joint effects (f2≈.06) in the multiple regression models used. This confirms that the available sample is adequate for the study objectives and that the observed effects (adjusted R2 .20–.30) are above the minimum detectable threshold.
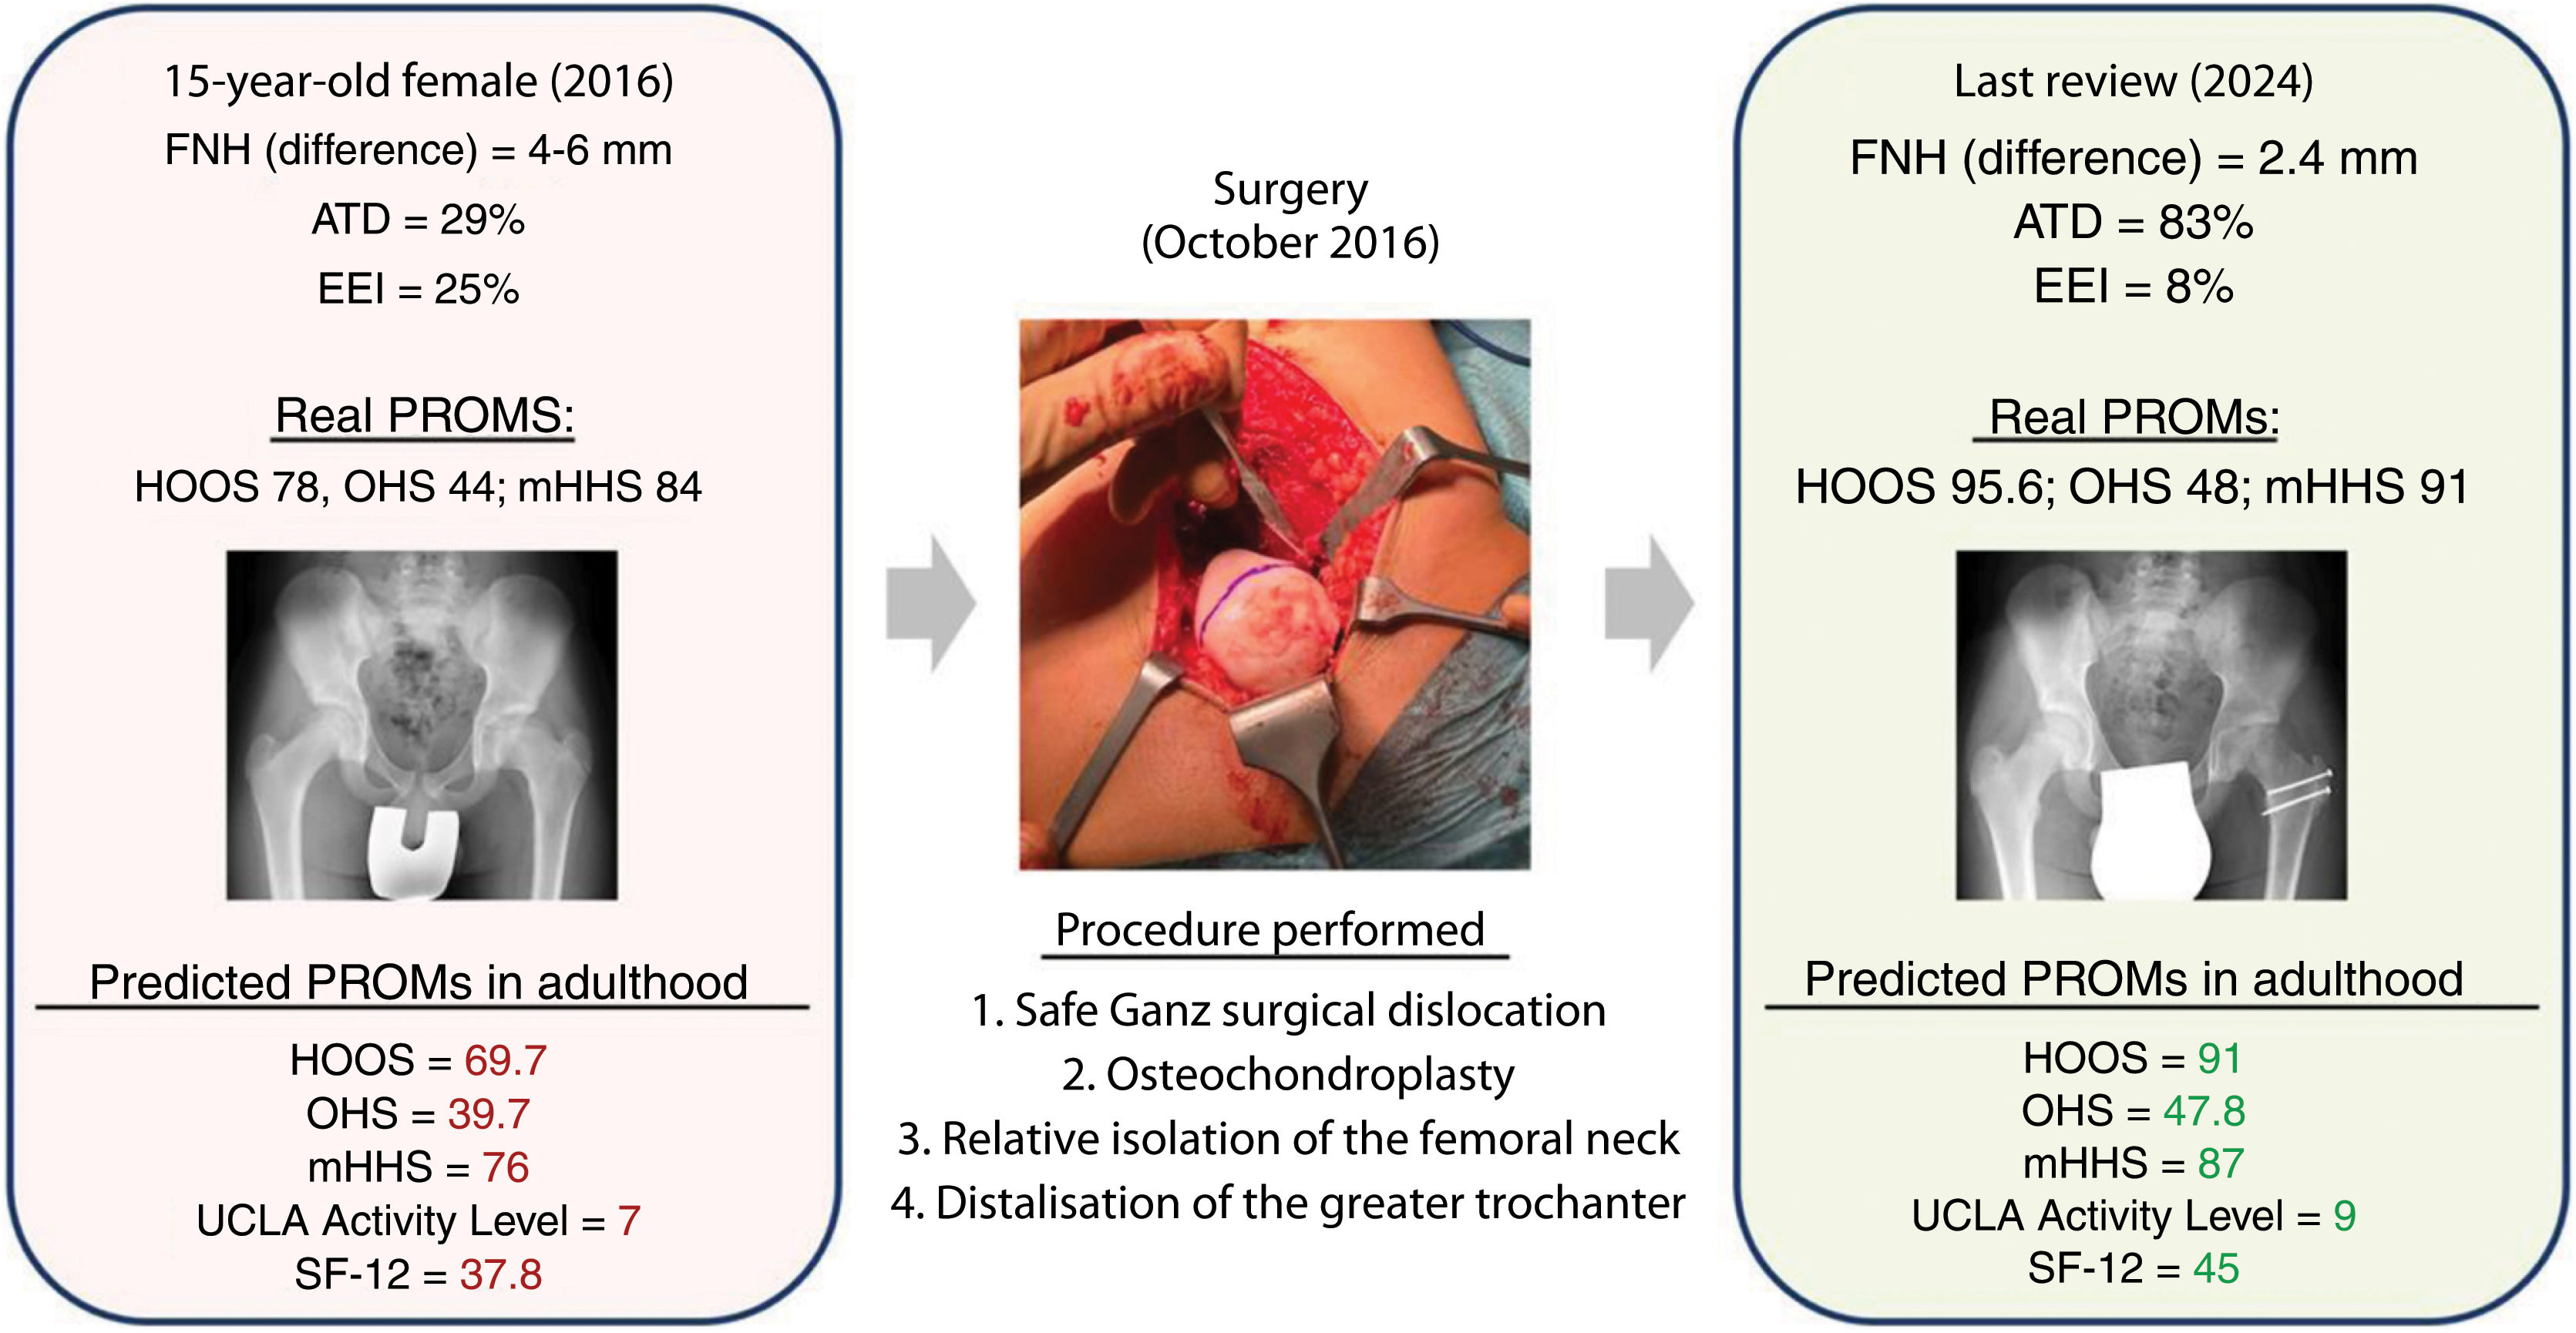
In light of these findings, we believe that the prognosis of LCPD in adulthood should not be limited to the presence of coxarthrosis or the need for THR, as has traditionally been the case. Instead, it should also incorporate the patient's perspective through PROMs. The multiple linear regression model we have developed allows us to predict hip function, athletic level, and quality of life based on FNH, ATD, and EEI, three parameters that are easily measured on plain radiographs. Fig. 3 presents an illustrative example of a PROMs prediction in adulthood. Following hip remodelling surgery, which included osteochondroplasty of the femoral head and relative lengthening of the femoral neck, the PROMs obtained at the last review exceeded both the pre-surgery values and those estimated in the prediction based on the last X-ray.

Example of PROMs prediction in adulthood. 15-Year-old female with sequelae of LCPD in the right hip operated on at our centre (2016) for osteochondroplasty of the femoral head, relative lengthening of the femoral neck, and distalisation of the greater trochanter. After 8 years of follow-up (2024), not only has the preoperative situation improved (actual scores), but so has the predicted outcome in adulthood (after applying our prediction model).
Additionally, our prediction model can be useful in the opposite sense: to guide surgeons regarding the degree of correction necessary to achieve certain functional outcomes, enabling individualisation of the degree of femoral neck remodelling (increasing FNH), distalisation of the greater trochanter (increasing ATD), and resection of the extruded epiphyseal hump (decreasing EEI). Future research should confirm whether surgically modifying these parameters actually translates into objective improvement in function, sports activity, and quality of life in adulthood. Ideally this would be achieved through prospective studies with a larger number of patients and prolonged follow-up.
ConclusionsIn addition to the sphericity of the femoral head and joint congruency, femoral neck shortening (FNS), greater trochanteric overgrowth (ATD), and femoral head extrusion (EEI) are associated with poorer outcomes (hip function, sports level, and quality of life) in adults who suffered from LCPD in childhood. Using these three radiological parameters in the sequelae phase, it is possible to predict PROMs so that patients and their families know what to expect in adulthood and, based on this, decide whether to change the shape of their hip.
LimitationsThe study has several limitations.
Firstly, the retrospective design may be subject to memory bias, especially in patients who underwent THR, as the questionnaires were completed with reference to their functional status prior to surgery.
Secondly, the absence of previous studies linking the radiological parameters evaluated with PROMs prevented the calculation of an adequate sample size, which limits the statistical power and makes this an exploratory and hypothesis-generating study. However, the post hoc power analysis showed that the sample has sufficient power (≥80%), so the probability of type II error is low, supporting the adequacy of the sample for the study objectives.
Selection bias must also be considered, as participation through the ASFAPE association may have attracted more severe cases or those with greater personal involvement in the disease.
Fourthly, we recognise that inter-individual heterogeneity (given by the variability in BMI, the fact of having undergone surgery in childhood, and the wide age range) may partially influence the PROMs, particularly in older patients with incipient hip osteoarthritis or different functional demands. Therefore, future studies should perform subgroup analyses.
Similarly, the radiographic analysis was based solely on X-rays and did not use three-dimensional techniques (CT) or techniques that analyse soft tissues (MRI).
Finally, reference values for the PROMs used are lacking in the general population, with the exception of the SF-12. This prevents the establishment of cut-off points that define ‘good’ or ‘excellent’ results, limiting their direct application to the planning of follow-up surgeries.
Level of evidenceLevel of evidence IV.
Informed consentAll patients gave their informed consent to access their medical records.
Ethical considerationsThis study was approved by the Drug Research Ethics Committee of Hospital Universitario La Paz (internal code: PI-5348).
FundingThis study is a recipient of a grant for “Proyectos de Iniciación a la Investigación en Cirugía Ortopédica y Traumatología” (Introductory Projects in Orthopaedic Surgery and Traumatology Research) awarded by the SECOT Foundation in 2023 (Sociedad Española de Cirugía Ortopédica y Traumatología).
Conflict of interestsThe authors have no conflict of interests to declare.


