




Cardiovascular polypills, that combine aspirin, antihypertensive and statin, are controversial with respect to cardiovascular risk factors (CVRFs) and cardiovascular events (CVE). We conducted a meta-analysis to examine their effects.
MethodologyA systematic review was conducted, searching clinical studies, both randomised and observational, that compared polypills versus administering the individual drugs separately. Four bibliographic databases (PubMed, Cochrane Library, Science Direct, and Google Scholar) were searched till December 2024. Risk of bias was assessed using the Newcastle-Ottawa Scale, the Cochrane bias risk assessment tool and the Egger's test. We developed separate analyses for the CNIC-polypill (ramipril, aspirin and atorvastatin), which is recommended by the WHO, and other polypills with different compositions. Outcomes CVRF (systolic and diastolic blood pressure or SBP and DBP, and LDL cholesterol), CVE, and adherence were meta-analysed, estimating mean differences (MD) and relative risks (RR) with 95% confidence intervals (CIs).
ResultsThere were 15 studies (n=24,364) included. Randomised trials (n=13) and observational studies (n=2) both showed low risk of bias. The CNIC-polypill decreased SBP (MD=−1.43mmHg [95% CI: −2.86; −0.00], p=0.05), DBP (MD=−2.62mmHg [95% CI: −5.41; 0.18], p=0.07), LDL cholesterol (MD=−5.52mg/dL [95% CI: −8.66; −2.38], p=0.0006), and CVE (RR=0.82 [95% CI: 0.73–0.92], p=0.0007), in clinical trials and observational studies combined. The other polypills also decreases SBP (MD=−2.93mmHg [95% CI: −3.96; −1.91], p<0.000001), DBP (MD=−1.52mmHg [95% CI: −2.00; −1.05], p<0.00001), LDL (MD=−10.48mg/dL [95% CI: −16.89; −4.07], p=0.001), and CVE (RR=0.77 [95% CI: 0.68–0.87], p<0.0001). There was higher therapeutic adherence both with the CNIC-polypill (RR=1.16 [95% CI: 1.12–1.21], p<0.00001) as well as with other polypills (RR=1.26 [95% CI: 1.04–1.52], p=0.02).
ConclusionsPolypills were effective in reducing CVRF and CVE, and improved adherence compared to taking the constituent individual drugs separately.
Las polipíldoras cardiovasculares, que combinan aspirina, antihipertensivos y estatinas, son controvertidas con respecto a los factores de riesgo cardiovascular (FRCV) y los eventos cardiovasculares (ECV). Realizamos un metaanálisis para examinar sus efectos.
MetodologíaSe realizó una revisión sistemática, buscando estudios clínicos, tanto aleatorizados como observacionales, que compararan las polipíldoras con la administración de los medicamentos individuales por separado. Se buscaron 4 bases de datos bibliográficas (PubMed®, Cochrane Library, Science Direct® y Google Scholar®) hasta diciembre de 2024. Se evaluó el riesgo de sesgo mediante la escala de Newcastle-Ottawa, la herramienta de evaluación del riesgo de sesgo de Cochrane y la prueba de Egger. Desarrollamos análisis separados para la polipíldora CNIC (ramipril, aspirina y atorvastatina), que está recomendada por la OMS, y otras polipíldoras con diferentes composiciones. Los resultados de los FRCV (presión arterial sistólica y diastólica o PAS y PAD, y colesterol LDL), ECV y adherencia fueron sometidos a un metaanálisis, estimando diferencias medias (DM) y riesgos relativos (RR) con intervalos de confianza (IC) del 95%.
ResultadosSe incluyeron 15 estudios (n=24.364). Los ensayos aleatorizados (n=13) y los estudios observacionales (n=2) mostraron ambos un bajo riesgo de sesgo. La polipíldora CNIC disminuyó la PAS (MD=−1,43mmHg [IC 95%: −2,86; −0,00]; p=0,05), la PAD (MD=−2,62mmHg [IC 95%: −5,41; 0,18]; p=0,07), el colesterol LDL (MD=−5,52mg/dl [IC 95%: −8,66; −2,38]; p=0,0006) y los ECV (RR=0,82 [IC 95%: 0,73-0,92]; p=0,0007), en ensayos clínicos y estudios observacionales combinados. Las otras polipíldoras también disminuyen la PAS (MD=−2,93mmHg [IC 95%: −3,96; −1,91]; p<0,000001), la PAD (MD=−1,52mmHg [IC 95%: −2,00; −1,05]; p<0,00001), el LDL (MD=−10,48mg/dl [IC 95%: −16,89; −4,07]; p=0,001) y los ECV (RR=0,77 [IC 95%: 0,68-0,87]; p<0,0001). Hubo una mayor adherencia terapéutica tanto con la polipíldora CNIC (RR=1,16 [IC 95%: 1,12-1,21]; p<0,00001) como con otras polipíldoras (RR=1,26 [IC 95%: 1,04-1,52]; p=0,02).
ConclusionesLas polipíldoras fueron efectivas en la reducción de los FRCV y los ECV, y mejoraron la adherencia en comparación con la toma de los medicamentos individuales por separado.
Cardiovascular disease (CVD), the combination of ischemic diseases of the heart, brain, and peripheral circulatory system, is characterised by atherosclerosis as the common pathophysiological basis. It is a leading cause of death,1 and its prevention is a priority in primary care. The control of cardiovascular risk factors (CVRFs) along with antiplatelet therapy with acetylsalicylic acid (ASA) is the main treatment strategy following a cardiovascular event (CVE).2
The concept of the polypill emerged in the early 2000s, when the simultaneous administration of several drugs in a single pill was proposed for targeting different CVRF.3 Originally, to support this idea theoretically, the evidence on the effectiveness of each drug individually was combined. Subsequently, an empirical study evaluated a polypill in a clinical trial testing Polycap (hydrochlorothiazide, atenolol, ramipril, and ASA), demonstrating an effect compared to monocomponents.4,5 Another clinical trial comparing the effects of CNIC-polypill (Centro Nacional de Investigación Cardiovascular, Spain) that included ramipril, atorvastatin and aspirin, compared with the same components separately, demonstrated a decrease in blood pressure and LDL cholesterol6 and, more recently, its efficacy in the prevention of CVE was also confirmed.7
The CNIC-polypill could offer an additional benefit. A clinical trial analysed the individual effect of each molecule on lowering blood pressure (ramipril) and LDL levels (atorvastatin) compared to the polypill, with a greater decrease in both CVRFs in the latter. The authors concluded that there could be a synergistic effect between aspirin and ramipril for the control of CVRFs when used in combination.8 We can distinguish two types of polypills, the CNIC polypill, which is the only one included in the WHO (World Health Organization) Model List of Essential Medicines,9 and other polypills with different combinations of drugs, however, all of them contain at least aspirin, antihypertensive and statin.
In general, the polypills may have a role via the promotion of adherence to treatment in a chronic disease. It has been estimated that, after 6 months of a CVE, more than 50% of patients no longer fully comply with the prescribed pharmacological treatment or lifestyle habits.10 This lack of adherence is associated with an increase in hospitalization and mortality rates, with the consequent healthcare cost.11 Therefore, theoretically, it seems reasonable that any treatment that can combine drugs into a single pill could improve adherence by simplifying the patient's therapeutic regimen.
Despite the numerous studies demonstrating the benefits of polypills in reducing CVRF, and CVE, the treatment remains controversial, and the published meta-analyses do not provide consistent results.12,13 Given the above background, a systematic review of clinical studies, including randomized and observational, comparing the polypills versus treatment using the component drugs individually, was undertaken to analyse whether it offers superior control of CVRF (such as blood pressure and LDL cholesterol), and in cardiovascular prevention. As a secondary aim, we reviewed the levels of adherence.
MethodsThe systematic review reporting followed PRISMA.16
Literature searchIn December 2024, a comprehensive literature search was conducted in the following databases: PubMed, Cochrane Library, Science Direct, and Google Scholar. The time period covered between January 2009 and December 2024. The search was conducted using the following terms as keywords, which were combined with MeSH terms and the boolean operators AND, OR, and NOT: “polypill”, “polypills”, “combined modality therapy”, “fixed-dose combination”, “fixed-dose”, “drug combination”, “drugs combination”, “FDC”, “secondary prevention”, “primary prevention”, “heart outcomes prevention”, “cardiovascular disease”, “cholesterol”, “blood pressure”, “adherence”, “MACE”. The types of studies included were observational cohort studies or randomized clinical trials, selected by two independent researchers. Reviews, duplicates, and book chapters were excluded. Additional manual searches were conducted using the “related articles” function on PubMed. Finally, all the references of the included articles were reviewed for any articles that might have been missed in the original literature search.15
Inclusion and exclusion criteria for the studiesThe studies that met the following inclusion criteria were included: (i) study conducted between January 2009 and December 2024; (ii) study design: randomized clinical trials or cohort studies, which could be prospective, retrospective, or ambispective; (iii) the comparison must be between a polypill (which will include ACE inhibitors or ARBs, statin, and antiplatelet) and the same molecules in monotherapy; (iv) the studies must evaluate as a goal any of the following parameters: changes in systolic blood pressure (SBP), diastolic blood pressure (DBP), LDL cholesterol, or incidence of cardiovascular events; (v) the studies must follow the publication guidelines; and (vi) article in English, Spanish, and/or translation into English and/or Spanish available. In studies with overlapping patient populations, we only included the study with the largest number of patients.
Studies that met any of the following criteria were excluded: (i) study design different from those described above: conference proceedings, clinical guidelines, reviews, commentaries, book chapters, or clinical cases; (ii) duplicate study. The studies that included several published articles with the same objective were analysed based on the work with the largest number of patients; (iii) absence of relevance in the bibliography; (iv) low level of quality defined by any of the following scales, according to the study design: Newcastle-Ottawa Scale evaluation criteria for cohort study with a score lower than 5 points or Cochrane bias risk assessment tool for RCTs with a score below 4 points; (v) absence of evaluation of any of the established objectives, (vi) absence of informed consent in the study and (vii) retracted articles.16
Data extraction and quality assessmentTwo independent researchers reviewed the selected articles, recording for each study the type of study, year of publication, sample size, included population, follow-up time, presence or absence of previous CVD, components of the polypill, objectives, outcomes, and adverse effects. The mean variations in systolic blood pressure (SBP) and diastolic blood pressure (DBP), and LDL cholesterol were used as outcome variables to address the main objective of the meta-analysis. The relative risks or odds ratio for CVE, and for digestive haemorrhagic events, were other outcomes. The degree of treatment adherence was also extracted. Additionally, both researchers evaluated the quality of the studies using the Newcastle-Ottawa Scale17 evaluation criteria for observational cohort studies and the Cochrane bias risk assessment tool18 for randomized clinical trials.19 The risk of publication and related biases was assessed using the Egger's test.
Statistical synthesisThe studies finally included in the analysis were classified into two analysis groups: the CNIC-polypill (ramipril, acetylsalicylic acid, and atorvastatin) and other types of polypill combinations. The analyses were developed comparing the CNIC-polypill and other polypills, independently, against the same components separately. Heterogeneity was assessed using the I2 parameter, considering heterogeneity values above 50% as high. Effects were meta-analysed using mean difference (MD) for the CVRF and relative risk (RR) for CVE and adherence, employing a fixed-effects model in cases of low heterogeneity and a random-effects model if heterogeneity was high.20 Measures such as RAR and NNT have not been included due to the methodology followed by the studies included in the analysis. The results were presented with 95% confidence intervals (CIs). The software Review Manager 5.4.1 was used.
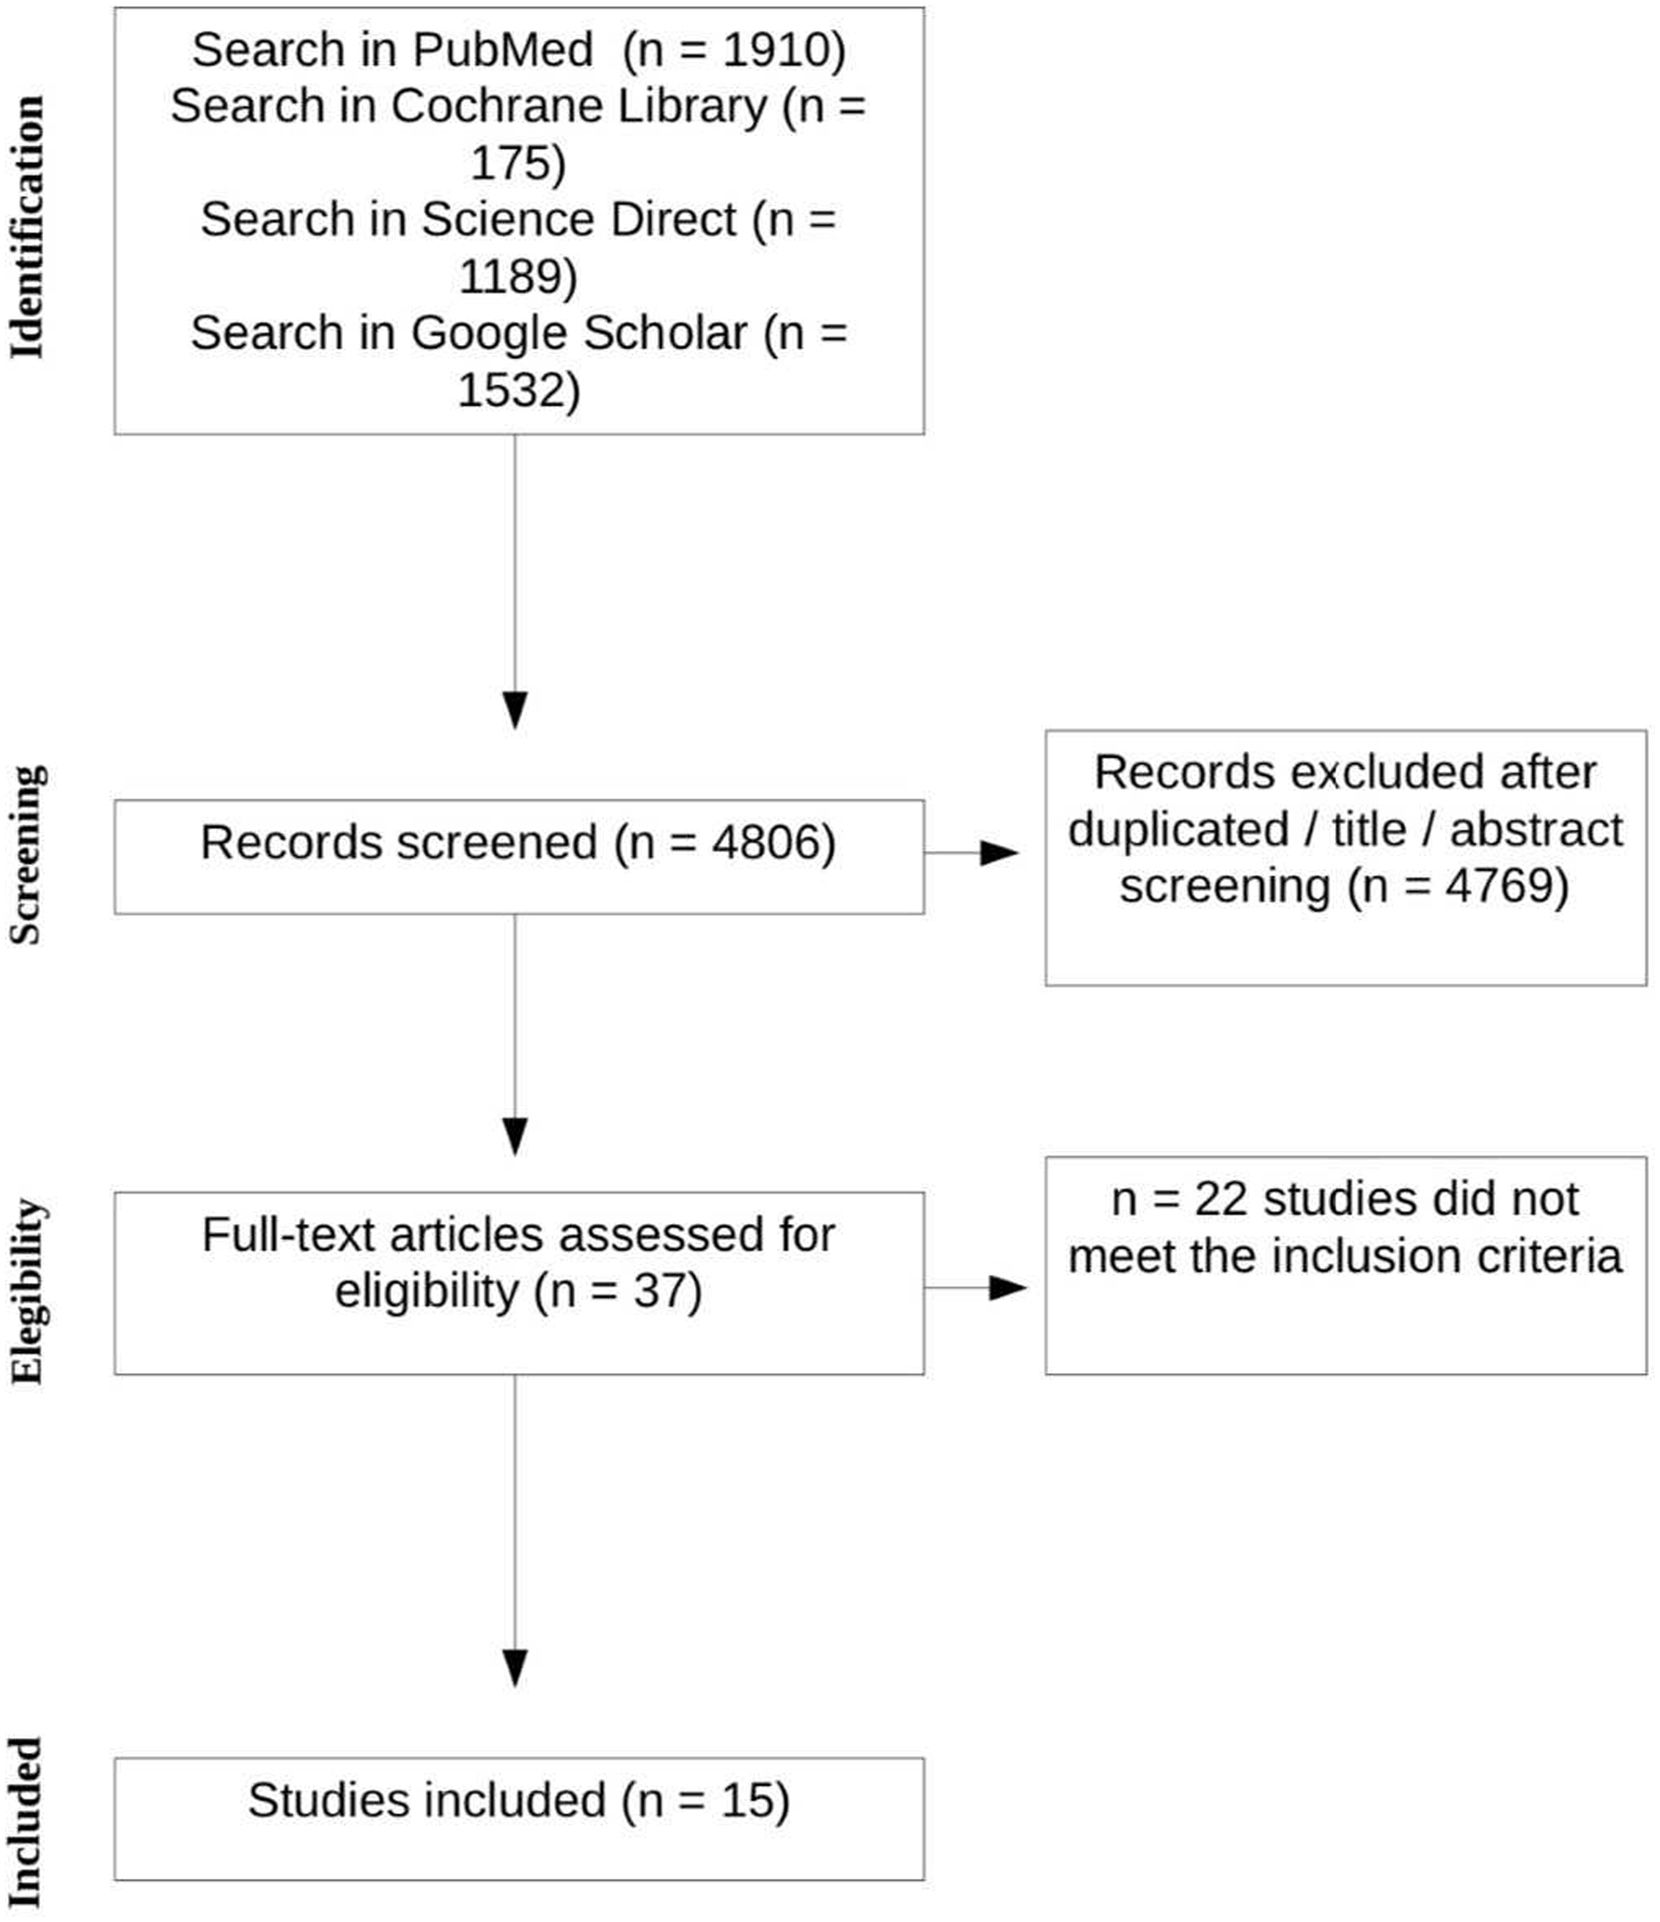
ResultsIncluded studies and characteristicsA total of 15 studies were included (Fig. 1), 13 of which are randomized clinical trials and 2 were observational studies, with a total of 24,364 patients. Out of the total, 5 studies tested the CNIC-polypill (n=6405), and the rest tested other polypills (n=17,959) (Tables S1 and S2). The follow-up time provided by the studies ranged from 3 to 60 months, with a mean of 17.6 months and a median of 12 months. A total of 8 studies provided results on blood pressure and LDL cholesterol or total cholesterol CVE, and adherence level.
Quality of the studies and publication bias
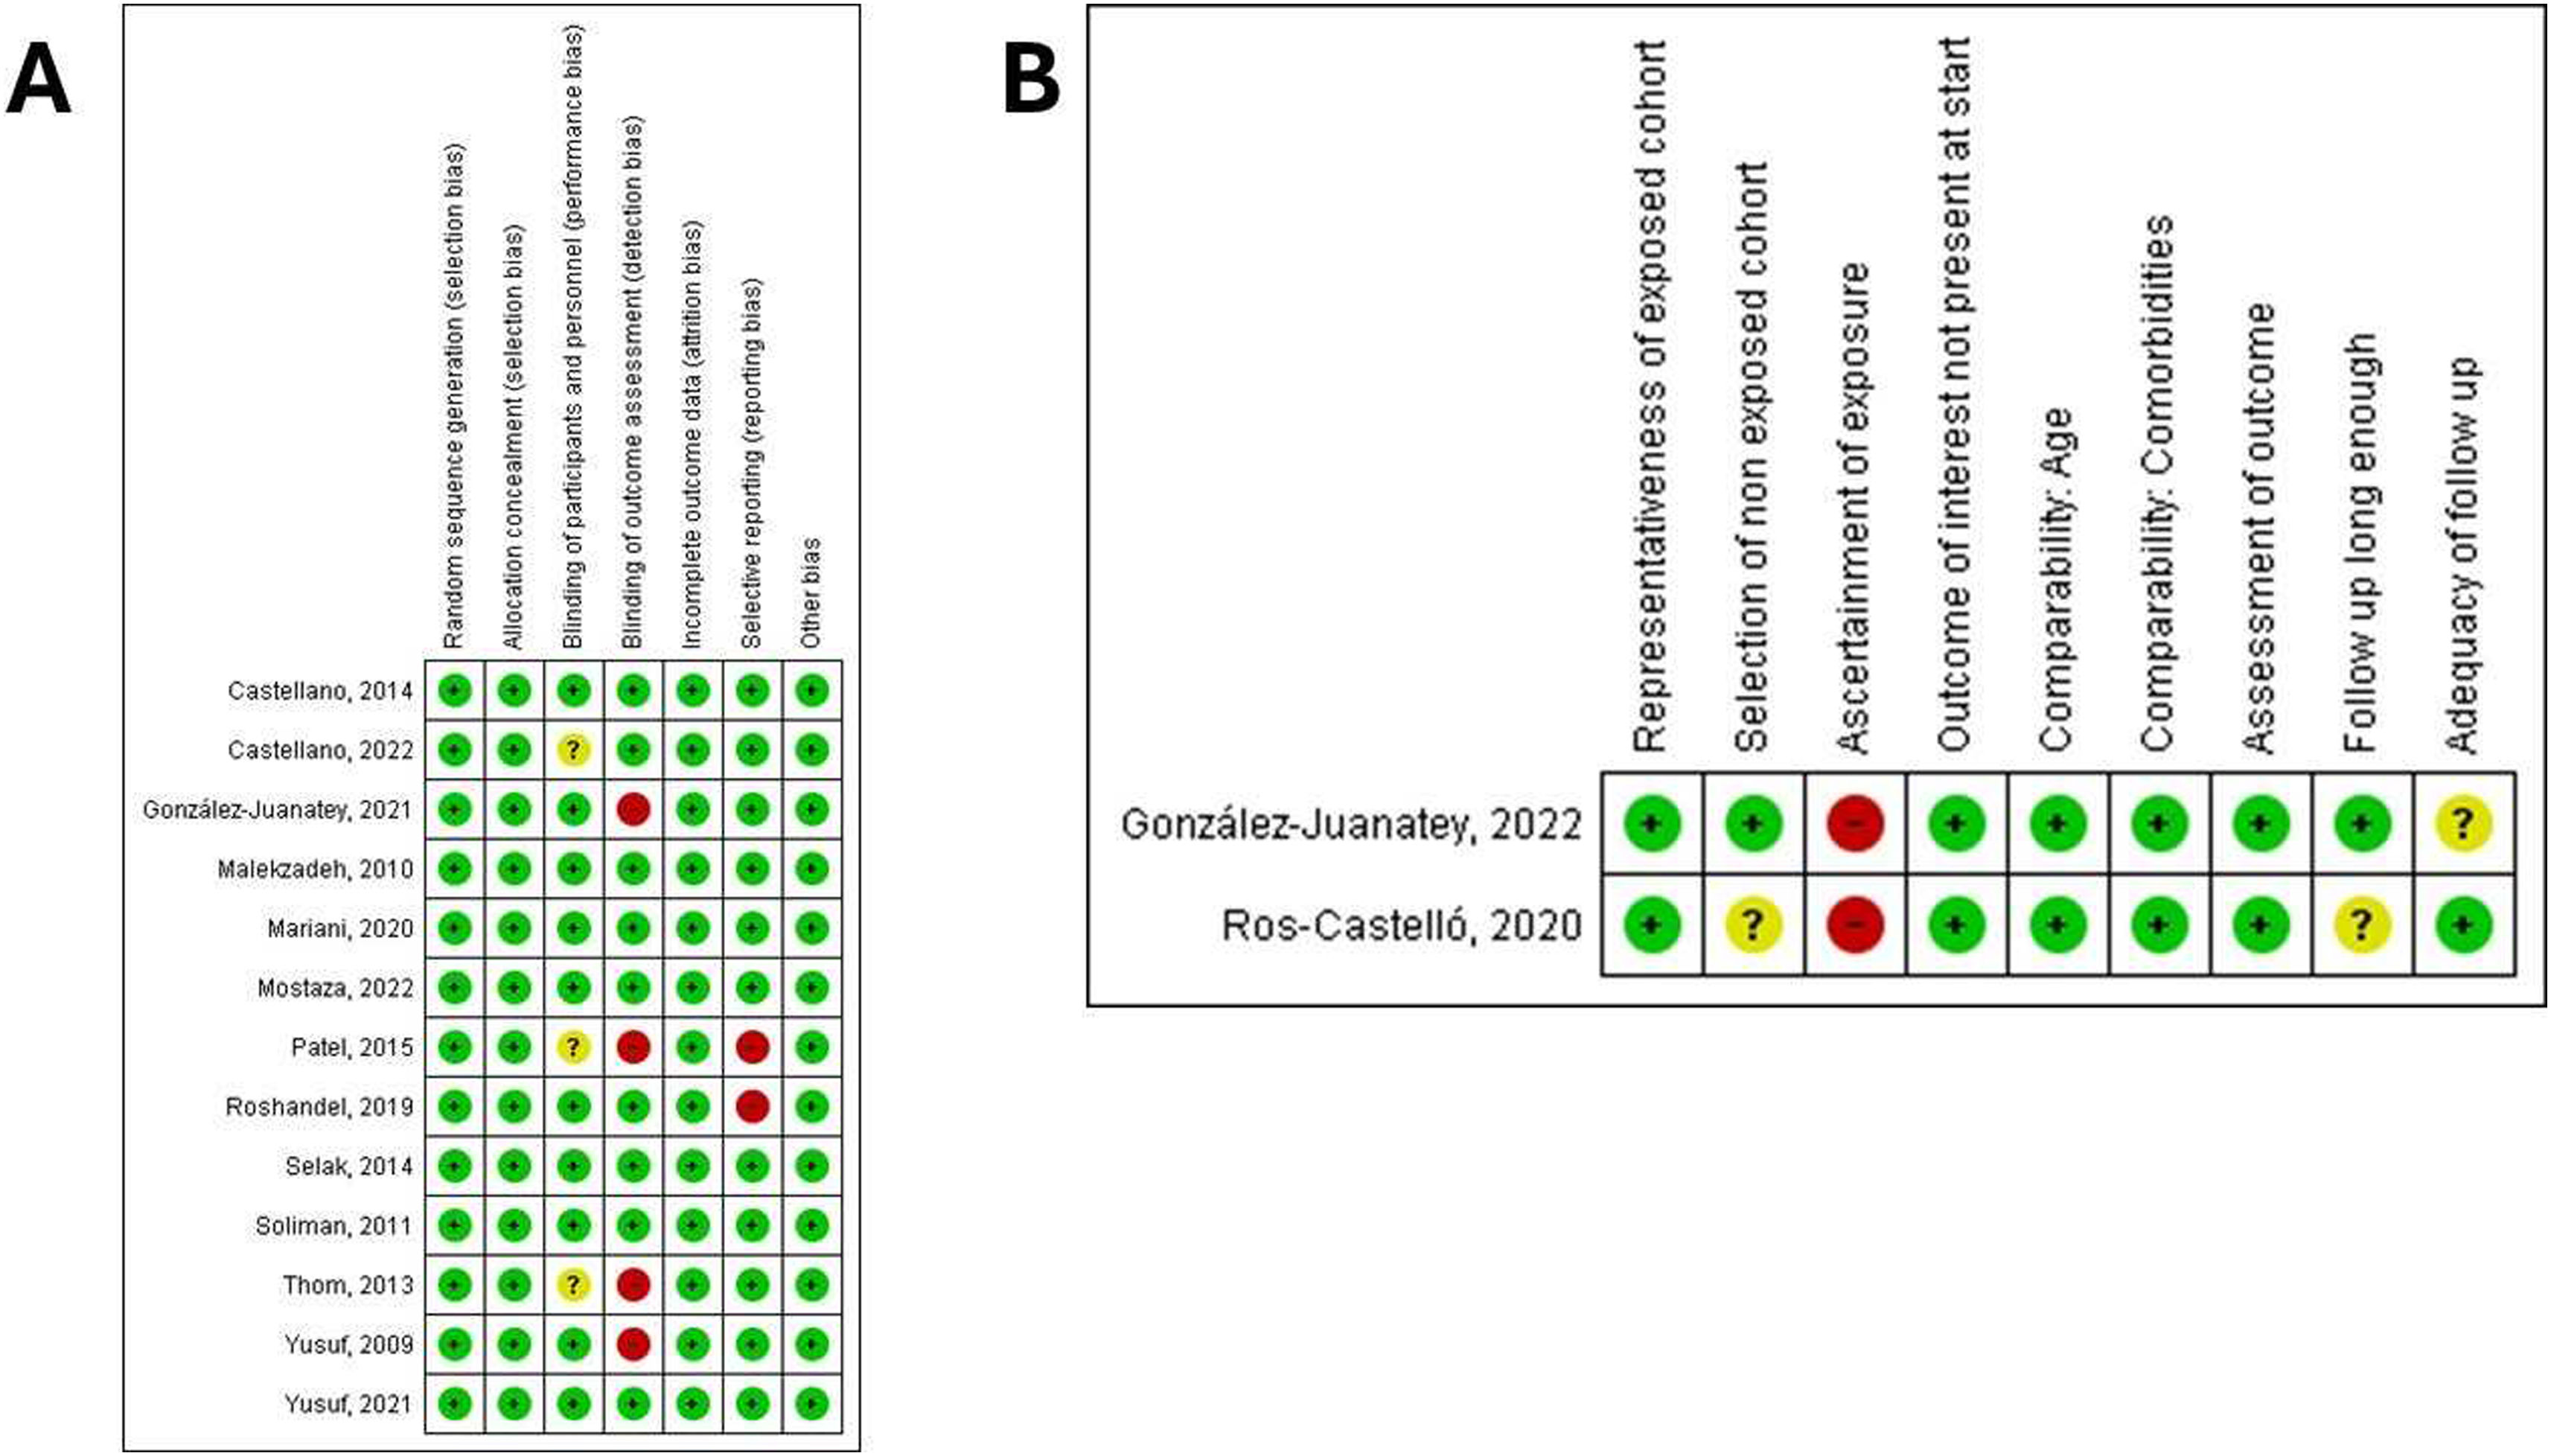
In clinical trials (n=13), the quality was medium (Fig. 2A), with the low possibility of reporting, procedure, and detection bias (Fig. S1). The observational studies (n=2) showed high methodological quality (Fig. 2B and supplementary material Figs. S1 and S2).

The publication bias analysis showed a low probability of there being funnel asymmetry (supplementary material Figs. S3–S8). The publication bias analysis for CVE showed no risk in the CNIC-polypill studies nor in the studies of the other polypills, Fig. S9 (Egger's test combined for all studies, p=0.689).
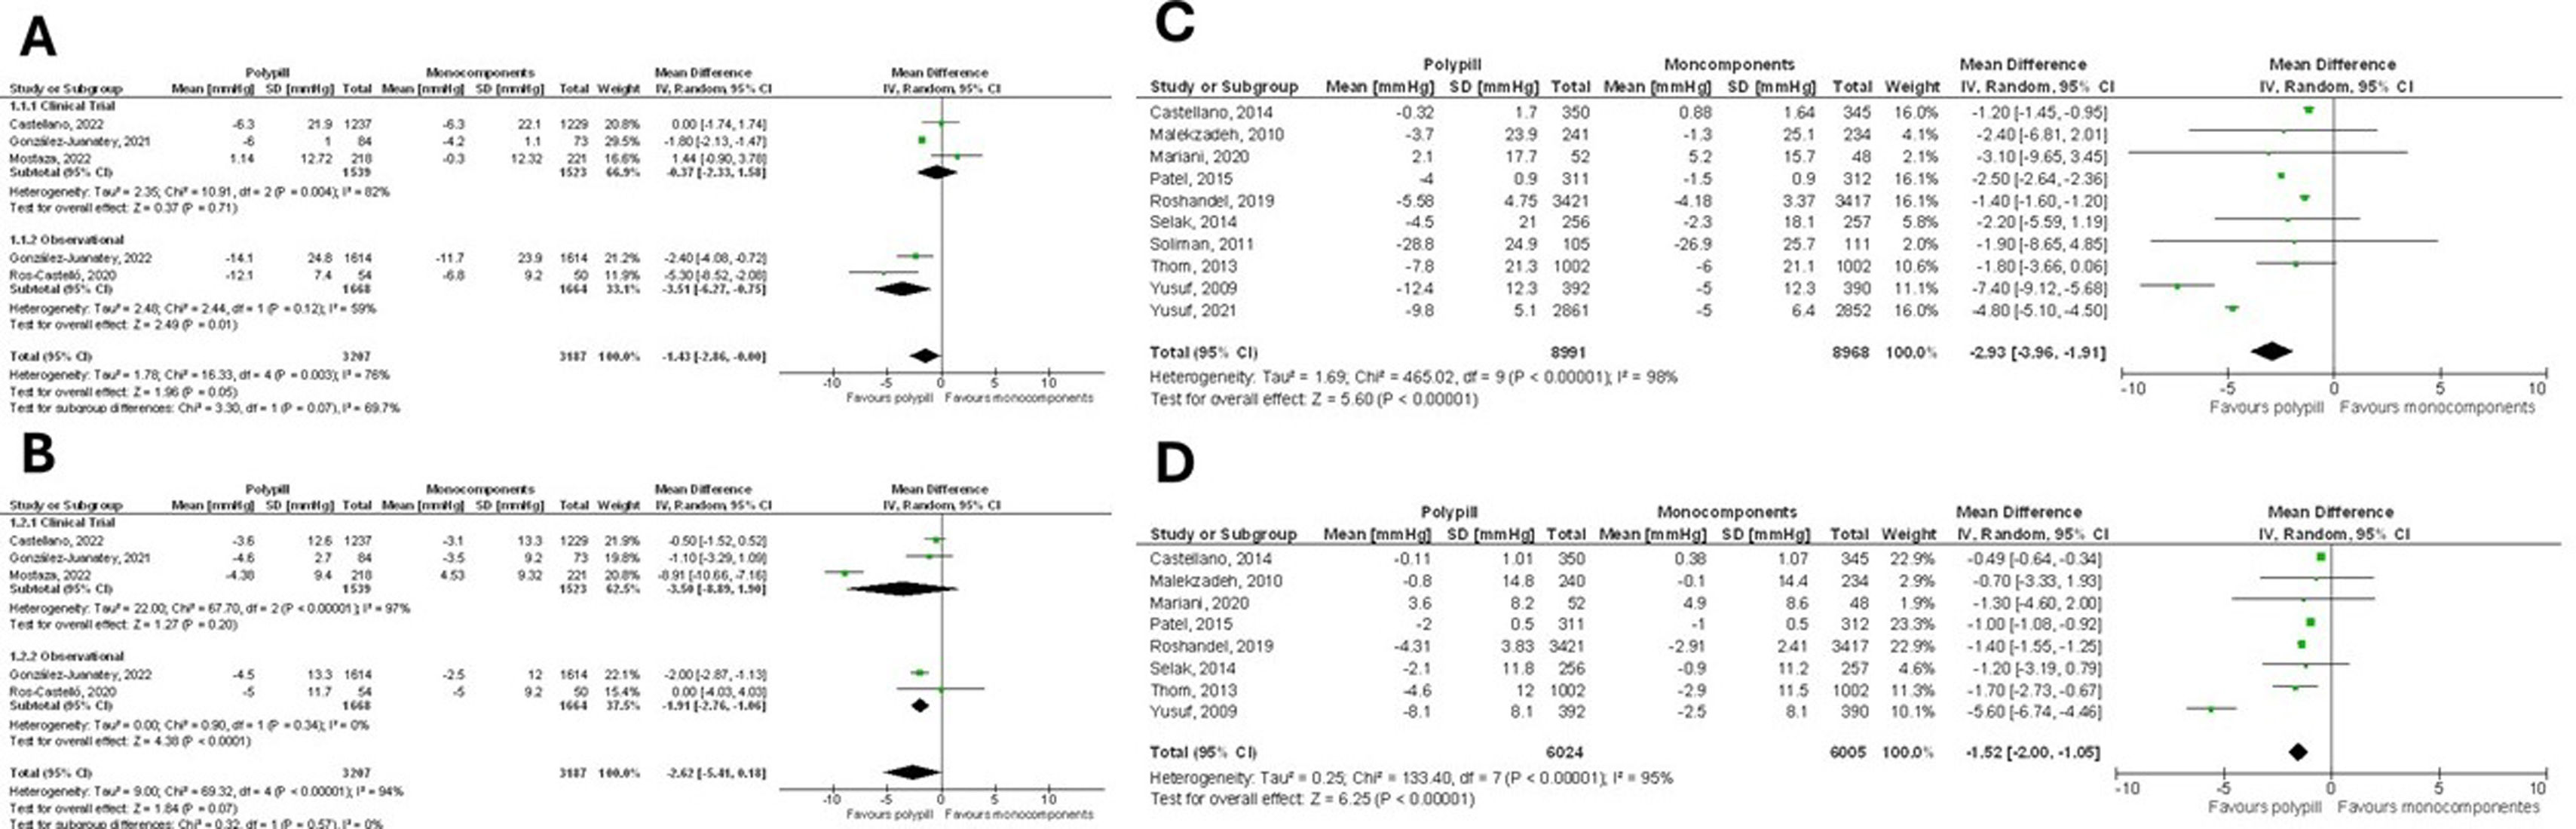
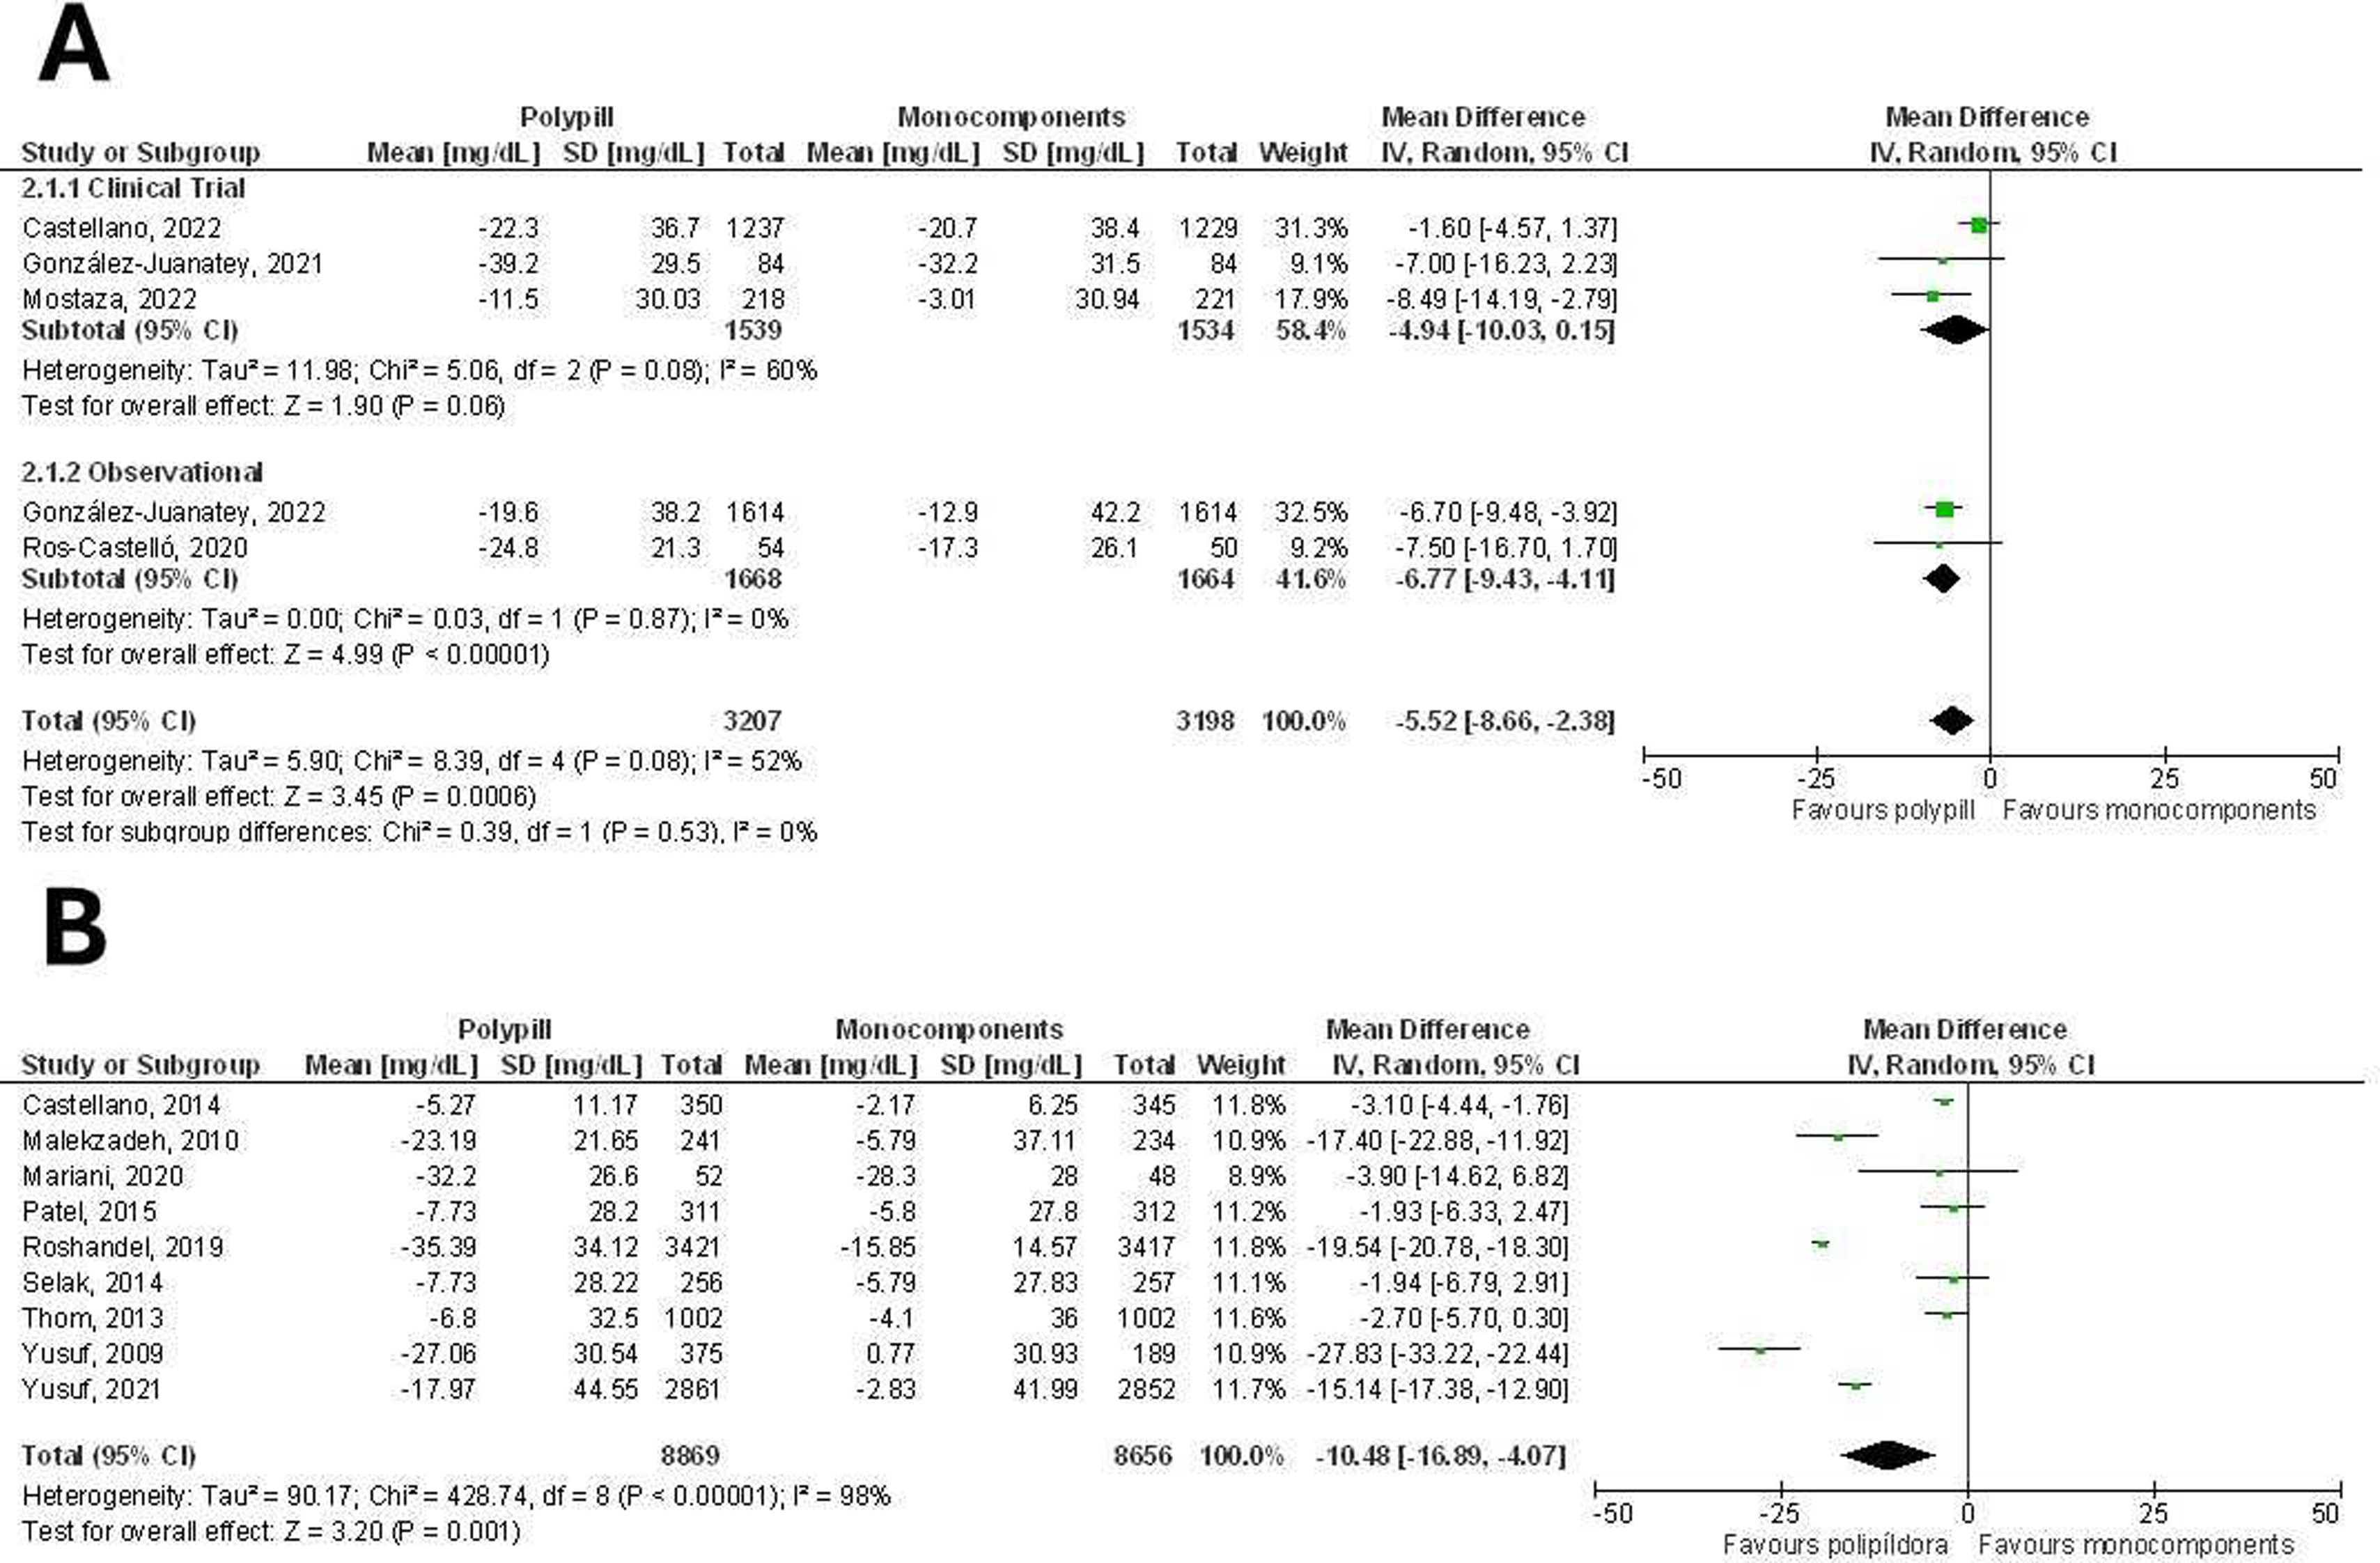
EffectivenessA total of 5 studies (3 clinical trials and 2 observational studies) provided results regarding the variation of SBP, DBP, and LDL cholesterol for the CNIC-polypill (n=6394). The CNIC-polypill showed a decrease in SBP (MD=−1.43mmHg [95% CI: −2.86; −0.00], p=0.05, I2=76%) (Fig. 3A), a decrease observed in both observational studies and one of the clinical trials. The DBP showed a decrease that did not reach statistical significance (MD=−2.62mmHg [95% CI: −5.41; 0.18], p=0.07, I2=94%) (Fig. 3B), a result shown by one of the clinical trials and one of the observational studies. In the case of the other polypills, a decrease in SBP was observed (MD=−2.93mmHg [95% CI: −3.96; −1.91], p<0.000001, I2=98%) (Fig. 3C), described in 5 out of the 10 studies, and in DBP (MD=−1.52mmHg [95% CI: −2.00; −1.05], p<0.00001, I2=95%) (Fig. 3D), described in 5 out of the 8 studies. The CNIC-polypill showed a reduction in LDL cholesterol in one clinical trial and another observational study, which contributed to a favourable overall decrease for the combination (MD=−5.52mg/dL [95% CI: −8.66; −2.38], p=0.0006, I2=52%) (Fig. 4A). For the rest of the polypills, 5 out of 9 clinical trials showed a decrease in this parameter, with an overall reduction (MD=−10.48mg/dL [95% CI: −16.89; −4.07], p=0.001, I2=98%) (Fig. 4B).


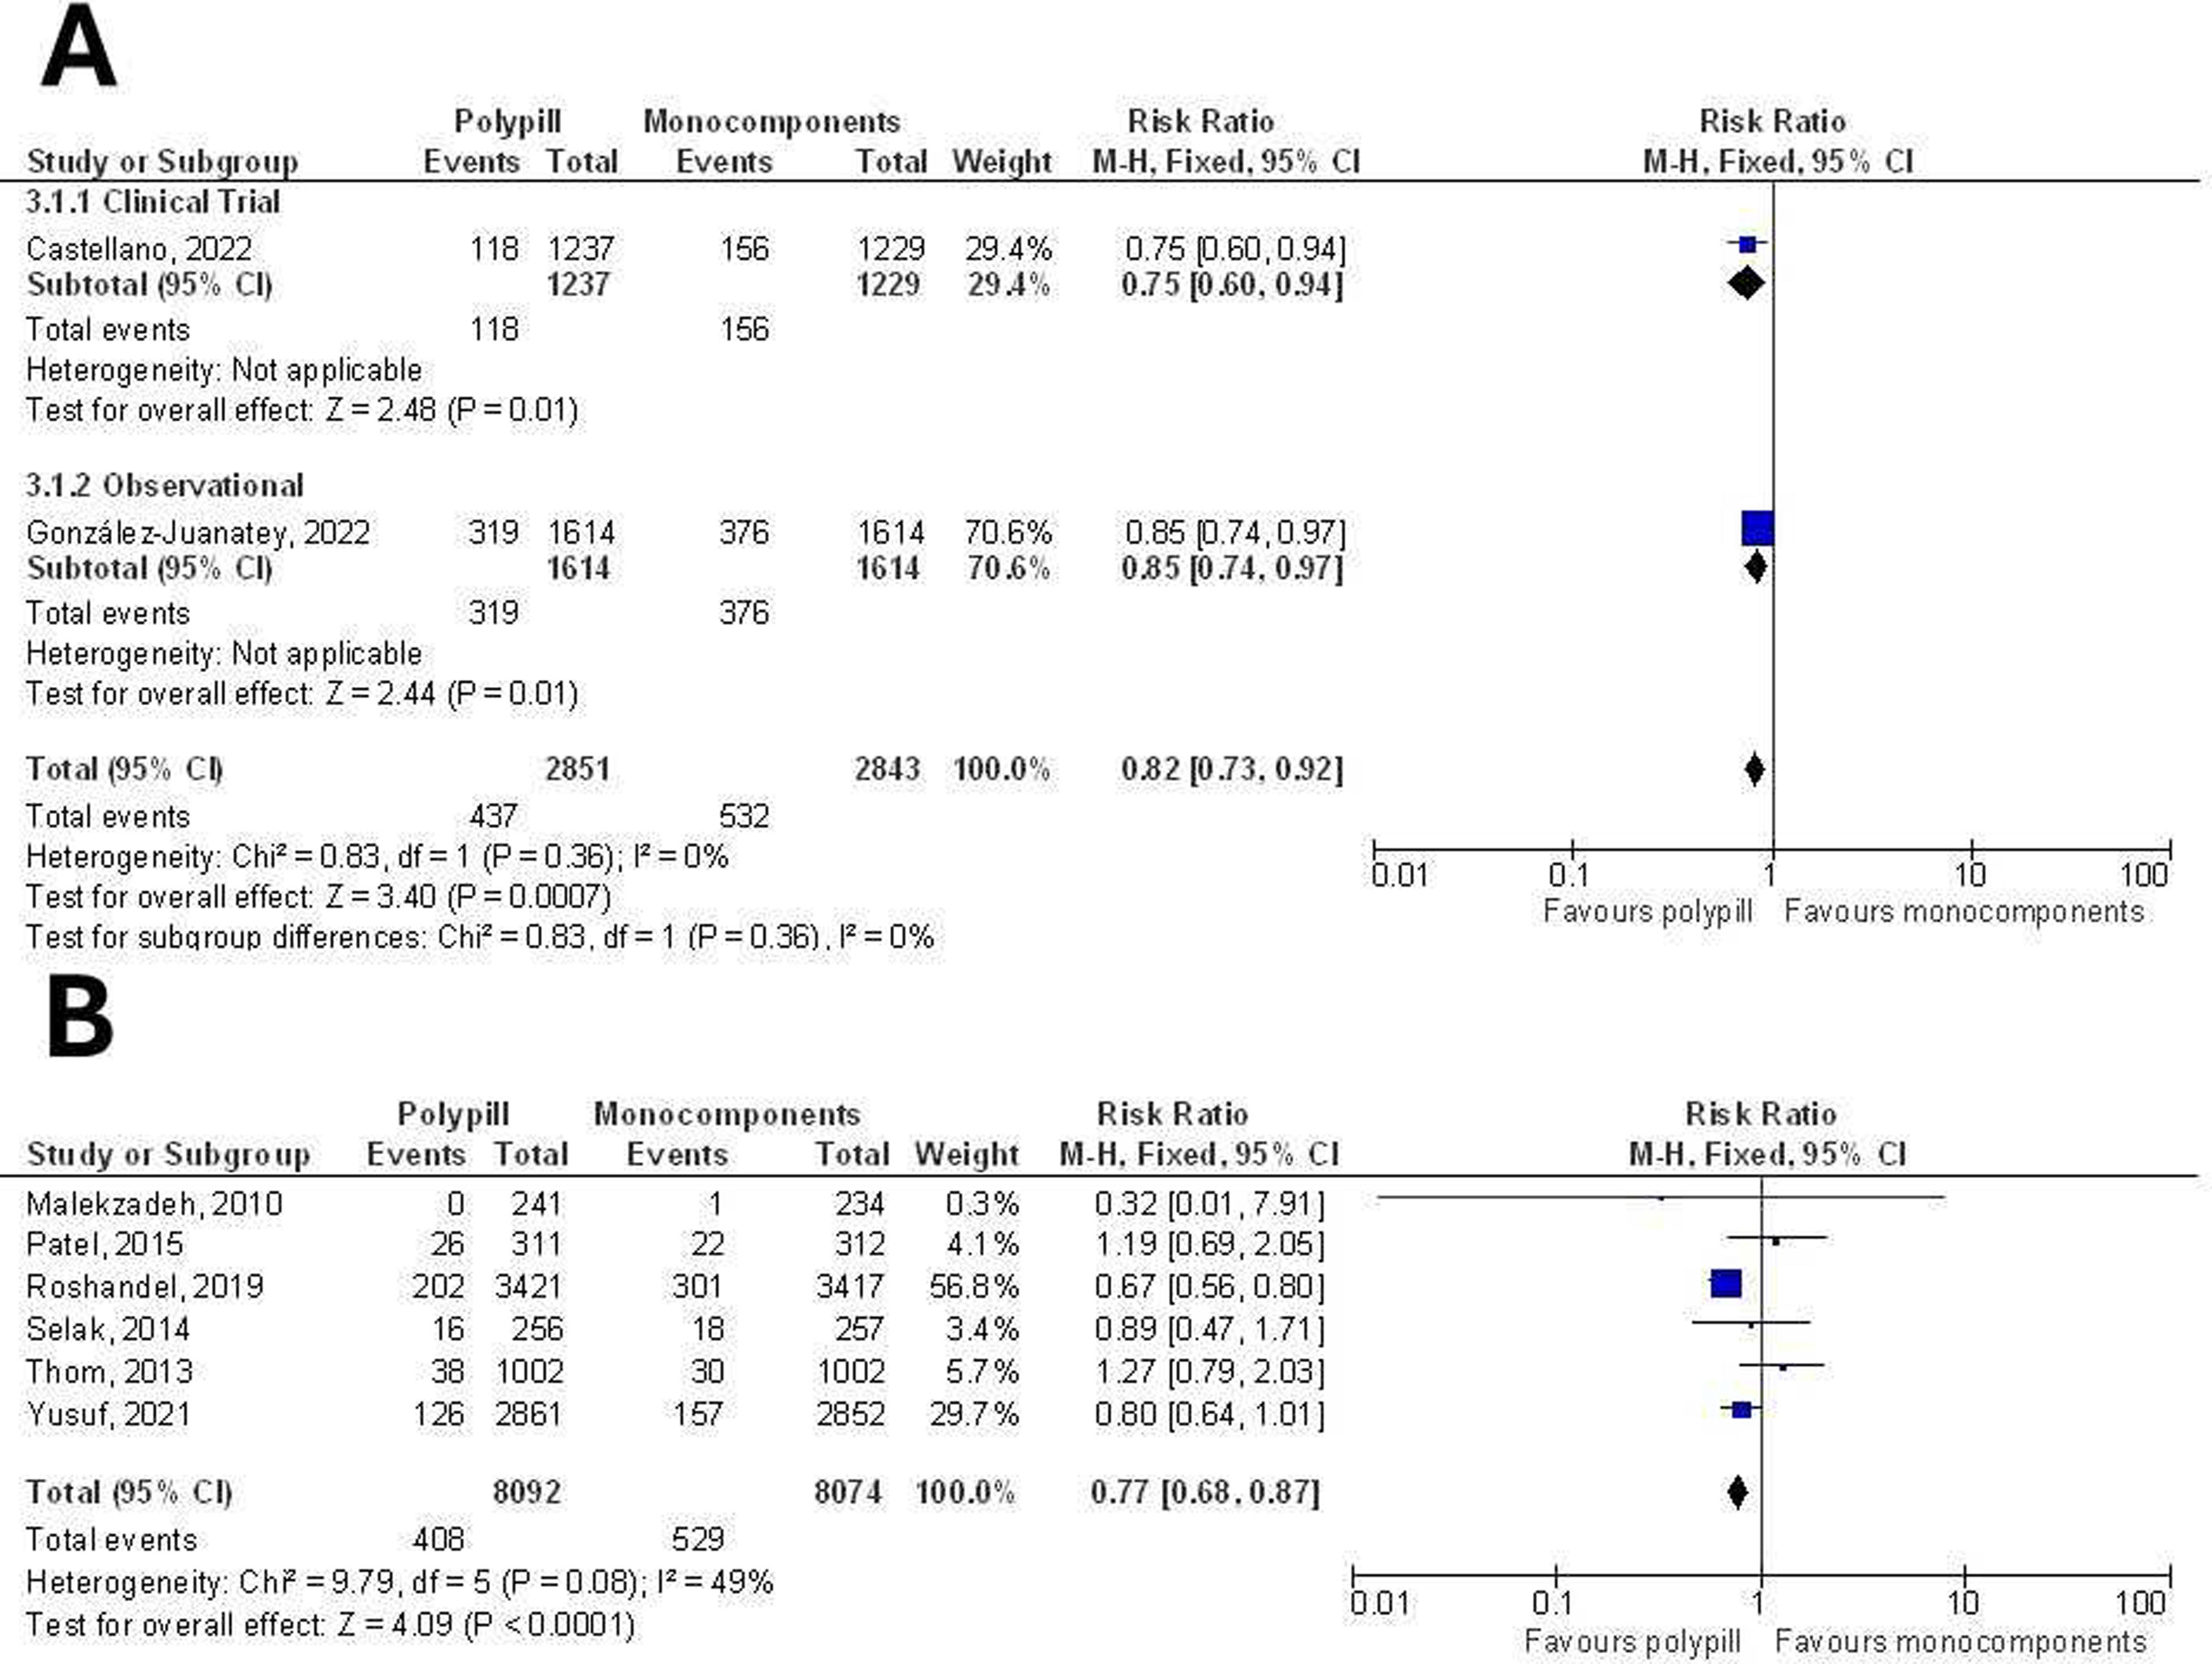
The cardiovascular prevention of the CNIC-polypill was analysed in 5694 patients from the SECURE7 and NEPTUNO21 studies. A risk reduction of 18% was observed (RR=0.82 [95% CI: 0.73–0.92], p=0.0007, I2=0%) (Fig. 5A). The rest of the polypills had results on CVE in 6 studies, showing an overall benefit (RR=0.77 [95% CI: 0.68–0.87], p<0.0001, I2=49%), which was mainly contributed by one of the studies, the one with the largest sample size (Fig. 5B).
Level of adherence to polypills
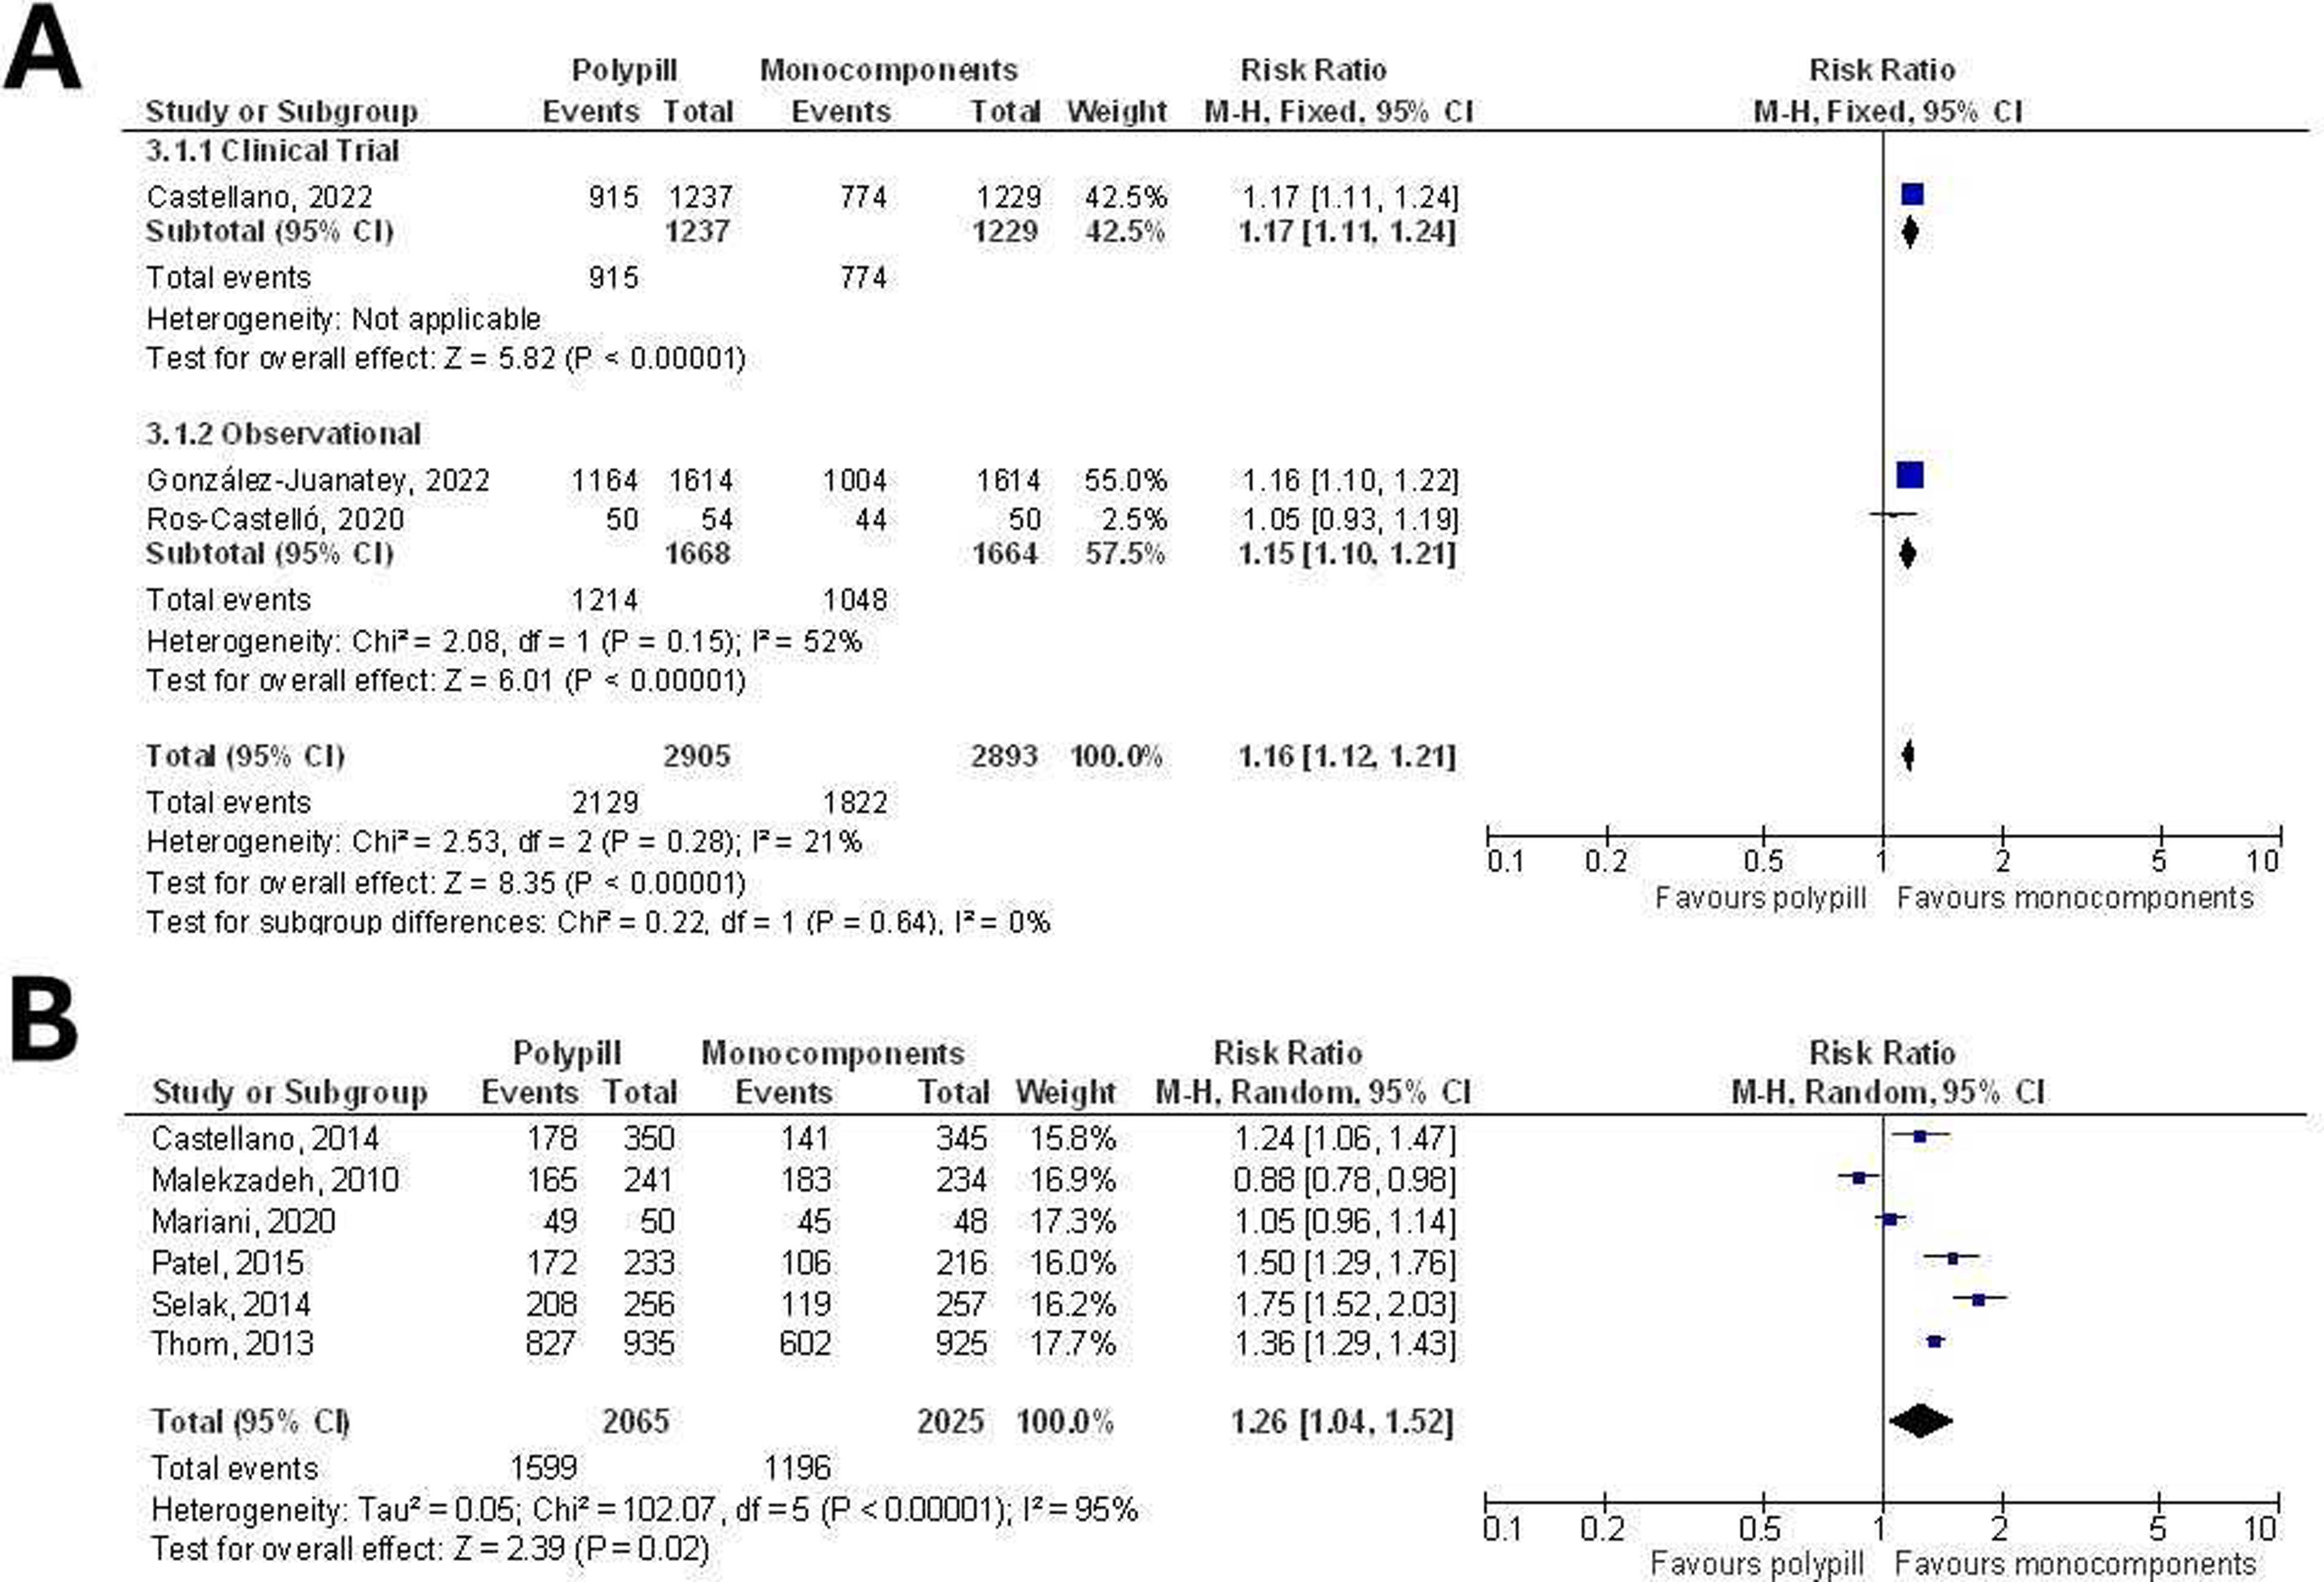
The outcome of therapeutic adherence was measured by either patient self report in questionnaires such as the Morisky-Green test or direct pill count. Only 3 out of the 5 studies with the CNIC-polypill published adherence results, which were superior to monotherapy in 2 of them.7,21 Patients randomized to the CNIC-polypill had increased therapeutic adherence overall compared with those randomized to monocomponents (RR=1.16 [95% CI: 1.12–1.21], p<0.0001, I2=21%) (Fig. 6A), as well as those in 6 studies of other polypills (RR=1.26 [95% CI: 1.04–1.52], p=0.02, I2=95%) (Fig. 6B).22–27
Safety
Adverse reactions were reported in all studies, most of them mild, with low incidence, and they did not cause treatment discontinuation with polypill. The reporting of them was measured using different methodologies in the studies, making comparison more difficult. The CNIC-polypill studies described dyspepsia and epigastralgia, cough, headache, dizziness, hypotension, or myalgia as the most frequent; the other polypills also reported mild effects such as dizziness, hypotension, myalgia, and cough, with bradycardia added due to the presence of a beta-blocker in some polypills. The incidence of bleeding was not described in all studies, despite the use of acetylsalicylic acid. In the case of the CNIC-polypill, it was described in 3 studies. The Hospital Cohort Study published the higher incidence of epistaxis in the polypill (1.9%) and upper gastrointestinal bleeding in the monocomponent branch (2%).28 The VULCANO study described a higher incidence in patients with the CNIC-polypill of ecchymosis (4.8%) and melena (4.8%) not described in the monocomponent branch.29 The SECURE study globally analysed all haemorrhages with a slightly higher incidence in patients with the CNIC-polypill (4.6% vs 4.0%).7 With the rest of the polypills, only 2 out of the 10 studies reported bleeding data. The IMPACT study reported a 1.56% incidence of bleeding in patients with the polypill.26 The PolyIran study reported 0.3% of intracranial haemorrhages in both branches, and gastrointestinal haemorrhages were slightly higher in patients with the polypill (0.4% vs 0.3%).30
DiscussionMain findingsIn this meta-analysis designed to separately evaluate the CNIC-polypill and other polypills in reducing CVRF and CVE, we have described a reduction in CVE, as well as a decrease in LDL cholesterol and, to a lesser extent, in blood pressure, with an incidence of side effects similar to monotherapy treatments. There was increased adherence to polypills. Both CNIC-polypill and the rest of the polypills demonstrate a decrease in CVRF and CVE. Additionally, clinical trials and observational studies have been included in our analysis, consistently demonstrating the preventive capacity of polypills.
Many meta-analyses13,31,32 have been published on the effect of polypills both in the control of CVRF and in the prevention of fatal and non-fatal CVE. However, both the selection of medications, which usually combine different molecules, and the selection of studies, including clinical trials, very varied among them. Their objectives sometimes focus on the reduction of CVRF and other times on CVE, and the results are inconsistent. The majority of meta-analyses published included only a few studies of CNIC-polypill. In Abushouk et al.31 none of the studies included CNIC-polypill and Hennawi et al.13 had only one study. More recently, Virk et al., did include CNIC-polypill studies but only clinical trials without observational studies. Three of them showed a decrease in all CVRF and a reduction in CVE.32 Our work offers segregated analyses for the CNIC-polypill and the other combinations of polypills. It allows us to put forward the evidence to underpin the recommendation to use polypills as an option in the treatment of patients with various CVRF after a CVE for the prevention of subsequent events.
Strengths and limitationsOur evidence synthesis addressed a focused question, taking the public health perspective where the comparator to the polypill is the use of the component drugs individually. This approach is more pragmatic and different to the regulatory perspective, where a placebo is the comparator commonly. This allows us to generate evidence for informing practice guidelines, going one step further than regulatory approval.33 Our search was exhaustive. However, compared with other meta-analyses, e.g. Virk et al.32 or Mohamed et al.12 each with more than 20 studies, our work included a low number of studies. This was because the other meta-analyses did not restrict to the combination of the three drugs we did, for example they included some trials that did not contain aspirin. Despite this, our work allowed us to confirm the effect of the polypills on cardiovascular protection, improved adherence, and patient safety with precision, i.e., the 95% CIs around overall effects were narrow.
This is the first time in the literature that segregated analyses of the different combinations of polypills have been conducted, including studies with different designs. Design combinations in meta-analyses are frowned upon. The latter adds greater heterogeneity, but it also provides greater external validity to the results. To avoid concern about design combinations, we presented the design-based subgroups along with the overall meta-analytic summary. This approach permits readers to draw their own conclusions. It is important to note that the design-based subgroup interactions were not statistically significant, a feature relevant to the interpretation of the findings. We did not have consumer engagement in the review. This approach requires further development.34 The lack of public pre-registration of a meta-analysis is a weakness of the project.14 This was so because the review was developed in the context of a doctoral thesis. However, as doctoral work has supervisors’ prior approval and continuous oversight, this provides protection against risks inherent in unregistered projects. The ideal, for transparency, would have been prospective registrations. This way, we could have been more confident in the recommendation for the use of polypills in CV prevention.
Polypills in clinical practiceThe combined role of various CVRFs in the development of CVE, especially hypertension and LDL cholesterol, has been known, and this is a very common in clinical scenario in primary care.35 Having a treatment that allows the control of both CVRF in a single pill may be of interest in the clinical practice of family doctors and other specialists who care for these patients. The hypothesis concerning a synergistic effect of some of the molecules contained in the CNIC-polypills, as suggested by Gonzalez-Juanatey et al., would need confirmation in future research.8 Polypills include an antiplatelet agent, which contribute in the prevention of CVE. The SECURE study confirmed the prevention of CVE with the CNIC-polypill but without decreasing CVRF, so the authors suggested that better adherence to the polypill would explain the reduction in events through the role of the antiplatelet agent.7 Yusuf et al., in their clinical trial comparing the polypill without the antiplatelet agent, showed that the presence of the latter prevented more CVE.5
Polypills offer an advantage in clinical practice, as they usually include generic drugs, at a lower cost, that address the control of various CVRF commonly present in patients with CVD, along with acetylsalicylic acid as an antiplatelet. Moreover, various cost analyses both in our country36,37 and abroad38 have demonstrated that it is an efficient treatment.39 All studies and our results confirm that the use of polypills is associated with better treatment adherence as it simplifies the regimen, and the rate of adverse effects is no different to that associated with the same treatments in monotherapy.40 Therefore, they should be considered as an option for patients after CVE for prevention and improving prognosis. Primary care is the most appropriate level of care to implement this prevention. The polypill would help simplify the therapeutic regimen for patients.
ConclusionsFrom our meta-analysis, we conclude that polypills are effective in reducing CVRF, as well as in preventing CVE. We also observed higher adherence to polypills than taking the drugs separately. The adverse effects were mostly mild, and their rate was similar to that of monotherapies. These results make polypills, compared to taking the component drugs individually, a competitive option in clinical practice to allow for improved control of CVRF and to safely reduce CVE.
CRediT authorship contribution statementThree authors participated in the same degree of study design, investigation, data collection, data analysis, review of analyzed data and results, manuscript writing and review.
Ethical considerationsThis meta-analysis did not require formal ethical approval as it consists solely of analysis of published literature.
FundingThe Semergen Foundation has supported the development of the work by offering methodological support.
Conflict of interestThe authors declare no conflicts of interest in relation to this article.
Vicente Martin Sanchez as the driving force behind the original project and motivator in the development of the meta-analysis.
The following are the supplementary data to this article:



