





To estimate the association between psychoactive substance use and suicidal thoughts among Colombians who consumed at least one psychoactive substance in the last twelve months of 2019.
MethodsAnalytical cross-sectional study. This report corresponds to a subsample of the National Survey on Psychoactive Substance Use (2019), which analyzed 27,252 individuals, habitual residents of Colombia, aged between 12 and 65 years, who reported having used at least one psychoactive substance in the past 12 months. Sociodemographic characteristics (age, sex, ethnicity, marital status), the frequency of suicidal thoughts in the previous 12 months, and the use of 14 psychoactive substances during the same period (including alcohol, cigarettes, among others) were examined. For each of the 14 included substances, an independent question was asked to determine whether the respondent had used that substance in the past 12 months. Generalized linear models (family: binomial; link: log) were used to estimate the association between suicidal thoughts and the use of different psychoactive substances.
ResultsAll the substances analyzed showed relationships with STs, except for alcohol and ecstasy. Notably, those who consumed coca paste (PR: 16.16, 95% CI: 10.97–23.70) and cocaine (PR: 8.72, 95% CI: 6.52–11.68) evidenced the highest associations. Finally, a directly proportional relationship was found between the number of drugs used and the likelihood of having had suicidal thoughts.
ConclusionsThere is a strong association between the consumption of psychoactive substances and suicidal ideation in the Colombian population during 2019.
Estimar la asociación entre el consumo de sustancias psicoactivas y las ideas suicidas en la población colombiana, que reportó haber consumido al menos una sustancia psicoactiva en los últimos 12 meses del año 2019.
MétodosEstudio transversal analítico. Este reporte corresponde a una submuestra del Estudio Nacional de Consumo de Sustancias Psicoactivas del año 2019, donde se analizaron 27.252 personas, residentes habituales de Colombia, con edades comprendidas entre 12 y 65 años, y que acusaron haber consumido al menos una sustancia psicoactiva en los últimos 12 meses. Se examinaron las características sociodemográficas (edad, sexo, etnia y estado civil), la frecuencia de pensamientos suicidas (PS) en los 12 meses previos, y el consumo de 14 sustancias psicoactivas en el mismo periodo (se incluyeron alcohol y cigarrillo, entre otras). Para cada una de las 14 sustancias incluidas, se formuló una pregunta independiente para determinar si el encuestado había consumido esa sustancia durante los últimos 12 meses. Se utilizaron modelos lineales generalizados (familia: binomial; enlace: log) para estimar la asociación entre los PS y el consumo de diferentes sustancias psicoactivas.
ResultadosTodas las sustancias analizadas mostraron relaciones con los PS, excepto el alcohol y el éxtasis. Notablemente, quienes consumieron bazuco (RP: 16,16; IC 95%: 10,97-23,70) y cocaína (RP: 8,72; IC 95%: 6,52-11,68) evidenciaron las asociaciones más altas. Finalmente, se encontró una relación directamente proporcional entre la cantidad de drogas consumidas y la probabilidad de haber tenido PS.
ConclusionesExiste una fuerte asociación entre el consumo de sustancias psicoactivas y la ideación suicida en la población colombiana durante el año 2019.
Suicidal thoughts (STs) are crucial indicators of serious mental health problems.1,2 Whether expressed verbally or kept silent by those experiencing them, suicidal thoughts carry significant risk for suicide attempts in the near future.3 STs can vary in intensity and frequency, and their occurrence may be a sign of elevated risk for suicidal behavior in the future.4 People experiencing such thoughts often feel trapped in a state of hopelessness. Thus, they are led to consider death as a possible way out of their distress.5
Many people resort to using different psychoactive substances (PAS) in an attempt to relieve emotional pain, anxiety or stress.6 However, substance use can have the opposite effect by exacerbating symptoms of mental health disorders such as depression and anxiety.7 In addition, it increases the likelihood of STs.8 This phenomenon is not only limited to a linear effect. It is crucial to consider reverse causality in this association, as not only can substance use lead to STs.8 In addition, those people already facing such challenges may seek refuge in hallucinogenic drugs or other substances in an attempt to control their internal distress.6
Consuming substances such as alcohol and opioids has been associated with an increased risk of STs,9 particularly those acting as central nervous system depressants. It can aggravate hopelessness and sadness, and lead to increased vulnerability to self-harm and suicidal ideation. According to records, PAS consumers present modifications in their state of consciousness, like confusion and instability, as well as in their mood, self-concept, behavior and thought processes.10
Analyses on school adolescents in Colombia show several PAS associated to STs episodes.9 This interaction was one of the findings of interest, as PAS polydrug users showed a greater association.9 In addition, longitudinal studies have reported that cannabis use is associated with elevated suicidal ideation risk.11 Likewise, the more frequency, intensity, time of use and coexistence with other mental disorders increase, the more probability of violent behavior towards themselves.12
However, so far research has been mostly conducted on adolescents. There is little information on suicidal ideation in older people. This age group evidences more suicide cases since these individuals use lethal methods and show fewer warning signs. Therefore, they are more difficult to detect.13 Consequently, STs occurrence in adults is more likely to end in completed suicide. They evidence suicidal ideation causes such as chronic diseases, functional loss and disability.14
As it has been stated, this report aims to estimate the association between psychoactive substance use and suicidal thoughts among Colombians who consumed at least one psychoactive substance in the last twelve months of 2019.
Materials and methodsType of studyAnalytical cross-sectional study. It is a secondary analysis of the information obtained in the national survey on the consumption of psychoactive substances (ENCSPA-2019). It was conducted by the Colombian Drug Observatory (ODC), the Ministry of Justice and Law, the Ministry of National Education, and the Ministry of Health and Social Protection. It was supported by the Inter-American Drug Abuse Control Commission (CICAD), of the Organization of American States (OAS).15
Population and sampleThe universe was composed of Colombian inhabitants aged between 12 and 65 years.15 It consisted of a non-institutional civilian population, usual households’ residents from the national territory. The 2005 Population and Housing Census conducted by the National Administrative Department of Statistics16 – DANE – was used as a sampling frame. The sample design used in the ENCSPA-2019 was probabilistic, clustered, stratified and multistage. The questions related to STs were applied only to individuals who reported having consumed at least one psychoactive substance in the previous 12 months. Finally, the sample consisted of 27,252 subjects. Thus, abstainers of any substance are not included in this analysis.
ProceduresData collection was structured in several stages, including clearly defined roles to ensure quality and efficiency. The collection staff conducted direct interviews in the assigned households and ensured information completeness. Critical and typing supervision organized and controlled the data review and digitization phases. Additionally, typing teams verified, rectified, and transcribed the forms into the system.
Suicidal thoughtsThe question asked for PAS assessment, was: “During the last 12 months, how often have you seriously thought about committing suicide?”. The options were (1) Never; (2) Once; (3) Twice; (4) Three times or more.
Sociodemographic variablesThe sociodemographic variables considered were, as follows: (1) sex (male and female); (2) ethnicity (indigenous, gypsy, Afro-descendant and none: “they are those who do not self-identify as belonging to an ethnic minority”); (3) marital status (married/free union, widowed/separated, single); (4) educational level (none, up to high school, technological, university/postgraduate); (5) children (no children, with children).
Substance useSince suicidal ideation and self-injury were assessed in a time window of the previous twelve (12) months, it was decided that substance use would be considered in the same time window. Therefore, participants were considered users if reporting substance use at least once in the previous twelve (12) months. The following substances were taken for analysis: (1) cigarette/tobacco; (2) alcohol; (3) tranquilizers; (4) stimulants; (5) inhalants; (6) methylene chloride (dick, ladyes or fragancia in Spanish); (7) popper; (8) marijuana; (9) coca paste; (10) ecstasy; (11) opioids; (12) LSD; (13) mushrooms, yagé or ayahuasca, Angel's Trumpet; and (14) cocaine. For each of the 14 substances included in the present analysis, an independent question was asked to determine whether the respondent had consumed the substance during the last twelve months. The question was phrased as follows: “During the last twelve months, have you consumed the (name of each of the fourteen substances)?”
Statistical analysisFirstly, there was an exploratory analysis. STs frequency was described by using sociodemographic variables and consumption of psychoactive substances involved. The description was carried out by using absolute frequencies and percentage frequencies. Generalized linear models (family: binomial; link: log) were used for estimating the association between the variables of interest and STs. Initially, an ordinal regression model was attempted based on the dependent variable nature. However, assumptions were not met when assessing them. For this reason, the dependent variable was dichotomized into yes (those who reported having had at least one STs episode), and no (those who reported not having had STs episodes). Prevalence ratios (PR) were estimated with bivariate and multivariate binomial regressions. Statistical analyses were performed with Stata software, version 17.
Bias statementSelectionThe selected individuals’ weight was not considered because ST's was evaluated only in individuals who had declared having consumed at least one of the fourteen substances evaluated. It may generate an underestimation of the magnitudes of association.
ClassificationThere is a possible classification bias in the STs variables, since it was done by author report and with a single question.
Ethical considerationsThe study was developed according to the regulation established in Resolution # 8430 of 1993, issued by the Colombian Ministry of Health. The primary study had an ethics committee. It approved all data collection procedures. The present secondary analysis adhered to the GATHER declaration.
ResultsThe sample consisted of 27,252 subjects between 12 and 65 years, with an average age of 35.6 (13.5). A total of 50.3% were male. Afro-descendants accounted for 11.6% of the sample, while 6.8% were Indigenous. A total of 41.0% lived with a partner, and 15.0% reported being widowed or divorced. Additionally, 63.4% stated they had at least one child. The prevalence of STs in the previous twelve months was 2.0%. Table 1 shows ST's distribution in the previous twelve months according to sociodemographic variables and substance use.
Distribution of suicidal thoughts, sociodemographic variables and substance use.
| Three times or more | Twice | Once | Never | |
|---|---|---|---|---|
| Age (years), mean [SD] | 31.7 [13.7] | 32.3 [13.5] | 33.5 [13.8] | 36.6 [13.5] |
| Sex, n (%) | ||||
| Male | 61 (0.4%) | 39 (0.3%) | 119 (0.9%) | 13752 (98.4%) |
| Female | 93 (0.7%) | 58 (0.4%) | 180 (1.3%) | 13500 (97.6%) |
| Ethnicity, n (%) | ||||
| Indigenous | 12 (0.7%) | 7 (0.4%) | 17 (1.0%) | 1686 (97.9%) |
| Gypsy | 1 (4.0%) | 0 (0.0%) | 1 (4.0%) | 23 (92.0%) |
| VAfro-descendant | 18 (0.6%) | 11 (0.3%) | 24 (0.7%) | 3166 (98.4%) |
| None | 123 (0.5%) | 79 (0.3%) | 257 (1.1%) | 22377 (98.0%) |
| Marital status, n (%) | ||||
| Married/free union | 37 (0.3%) | 24 (0.2%) | 81 (0.7%) | 11248 (98.8%) |
| Widowed/separated | 33 (0.8%) | 18 (0.4%) | 51 (1.2%) | 4065 (97.6%) |
| Single | 84 (0.7%) | 55 (0.4%) | 167 (1.4%) | 11939 (97.5%) |
| Educational level, n (%) | ||||
| None | 4 (1.7%) | 0 (0.0%) | 1 (0.4%) | 235 (97.9%) |
| Up to high school | 102 (0.7%) | 58 (0.4%) | 185 (1.2%) | 14754 (97.7%) |
| Technological level | 23 (0.4%) | 16 (0.3%) | 52 (1.0%) | 5309 (98.3%) |
| University/postgraduate | 25 (0.4%) | 23 (0.3%) | 61 (0.9%) | 6954 (98.5%) |
| Children, n (%) | ||||
| No children | 75 (0.7%) | 41 (0.4%) | 131 (1.3%) | 9931 (97.6%) |
| With children | 79 (0.4%) | 56 (0.3%) | 168 (1.0%) | 17321 (98.3%) |
| Cigarette/tobacco, n (%) | ||||
| Yes | 66 (1.1%) | 34 (0.6%) | 102 (1.7%) | 5701 (96.6%) |
| No | 88 (0.4%) | 63 (0.3%) | 197 (0.9%) | 21551 (98.4%) |
| Alcohol, n (%) | ||||
| Yes | 140 (0.5%) | 88 (0.3%) | 286 (1.1%) | 25849 (98.1%) |
| No | 14 (1.0%) | 9 (0.6%) | 13 (0.9%) | 1403 (97.5%) |
| Tranquilizers, n (%) | ||||
| Yes | 14 (4.8%) | 10 (3.4%) | 17 (5.8%) | 252 (86.0%) |
| No | 140 (0.5%) | 87 (0.3%) | 282 (1.0%) | 27000 (98.1%) |
| Stimulants, n (%) | ||||
| Yes | 0 (0.0%) | 2 (11.8%) | 0 (0.0%) | 15 (88.2%) |
| No | 154 (0.6%) | 95 (0.3%) | 299 (1.1%) | 27237 (98.0%) |
| Inhalants, n (%) | ||||
| Yes | 5 (16.7%) | 0 (0.0%) | 0 (0.0%) | 25 (83.3%) |
| No | 149 (0.5%) | 97 (0.3%) | 299 (1.1%) | 27227 (98.0%) |
| Methylene chloride (dick, ladyes or fragancia in Spanish), n (%) | ||||
| Yes | 0 (0.0%) | 1 (7.1%) | 1 (7.1%) | 12 (85.7%) |
| No | 154 (0.6%) | 96 (0.3%) | 298 (1.1%) | 27240 (98.0%) |
| Popper, n (%) | ||||
| Yes | 12 (6.6%) | 7 (3.9%) | 8 (4.4%) | 154 (85.1%) |
| No | 142 (0.5%) | 90 (0.3%) | 291 (1.1%) | 27098 (98.1%) |
| Marijuana, n (%) | ||||
| Yes | 33 (2.7%) | 24 (2.0%) | 42 (3.4%) | 1124 (91.9%) |
| No | 121 (0.5%) | 73 (0.3%) | 257 (1.0%) | 26128 (98.3%) |
| Coca paste, n (%) | ||||
| Yes | 8 (14.0%) | 3 (5.3%) | 6 (10.5%) | 40 (70.2%) |
| No | 146 (0.5%) | 94 (0.3%) | 293 (1.1%) | 27212 (98.1%) |
| Extasis, n (%) | ||||
| Yes | 0 (0.0%) | 0 (0.0%) | 2 (3.1%) | 63 (96.9%) |
| No | 154 (0.6%) | 97 (0.3%) | 297 (1.1%) | 27189 (98.0%) |
| Opioids, n (%) | ||||
| Yes | 6 (4.2%) | 1 (0.7%) | 6 (4.2%) | 129 (90.8%) |
| No | 148 (0.5%) | 96 (0.3%) | 293 (1.1%) | 27123 (98.1%) |
| LSD, n (%) | ||||
| Yes | 2 (2.5%) | 2 (2.5%) | 3 (3.8%) | 73 (91.3%) |
| No | 152 (0.5%) | 95 (0.3%) | 296 (1.1%) | 27179 (98.0%) |
| mushrooms, yagé or ayahuasca, Angel's Trumpet, n (%) | ||||
| Yes | 4 (3.1%) | 3 (2.3%) | 3 (2.3%) | 120 (92.3%) |
| No | 150 (0.5%) | 94 (0.3%) | 296 (1.1%) | 27132 (98.0%) |
| Cocaine, n (%) | ||||
| Yes | 17 (6.9%) | 12 (4.8%) | 13 (5.2%) | 206 (83.1%) |
| No | 137 (0.5%) | 85 (0.3%) | 286 (1.0%) | 27046 (98.2%) |
n: absolute frequency; %: percentage frequency; SD: standard deviation.
Binomial regression models showed that all substances, except alcohol and ecstasy, were associated with STs. Notably, those who consumed coca paste (PR: 16.16, 95% CI: 10.97–23.70) and cocaine (PR: 8.72, 95% CI: 6.52–11.68) evidenced the highest associations. Table 2 shows the association between STs in the previous twelve months, and sociodemographic variables, and substance use.
Association between suicidal thoughts, sociodemographic and substance use.
| Bivariate modelPR (95% CI) | Multivariate modelPR (95% CI) | |
|---|---|---|
| Age (years) | 0.98 (0.97–0.98) | 0.98 (0.97–0.98) |
| Sex | ||
| Male | Reference | Reference |
| Female | 1.53 (1.29–1.81) | 1.52 (1.28–1.80) |
| Ethnicity | ||
| Indigenous | 1.27 (0.83–1.93) | 1.30 (0.85–1.97) |
| Gypsy | 4.86 (1.25–18.85) | 5.24 (1.36–20.13) |
| Afro-descendant | Reference | Reference |
| None | 1.22 (0.92–1.62) | 1.22 (0.92–1.62) |
| Marital status | ||
| Married/free union | Reference | Reference |
| Widowed/separated | 1.96 (1.53–2.53) | 2.07 (1.60–2.66) |
| Single | 2.00 (1.65–2.44) | 1.67 (1.32–2.12) |
| Educational level | ||
| None | 1.35 (0.56–3.28) | 1.85 (0.76–4.51) |
| Up to high school | 1.48 (1.20–1.83) | 1.59 (1.28–1.97) |
| Technological level | 1.09 (0.83–1.44) | 1.09 (0.83–1.44) |
| University/postgraduate | Reference | Reference |
| Children | ||
| No children | 1.41 (1.20–1.67) | 1.55 (1.28–1.97) |
| With children | Reference | Reference |
| Cigarette/tobacco | ||
| Yes | 2.15 (1.81–2.55) | 2.42 (2.04–2.89) |
| No | Reference | Reference |
| Alcohol | ||
| Yes | 0.78 (0.56–1.09) | 0.68 (0.48–0.95) |
| No | Reference | Reference |
| Tranquilizers | ||
| Yes | 7.56 (5.62–10.17) | 6.80 (5.06–9.12) |
| No | Reference | Reference |
| Stimulants | ||
| Yes | 5.97 (1.62–21.99) | 5.05 (1.38–18.42) |
| No | Reference | Reference |
| Inhalants | ||
| Yes | 8.49 (3.80–18.99) | 7.08 (3.20–15.70) |
| No | Reference | Reference |
| Methylene chloride (dick, ladyes or fragancia in Spanish) | ||
| Yes | 7.24 (2.00–26.20) | 5.16 (1.43–18.61) |
| No | Reference | Reference |
| Popper | ||
| Yes | 7.88 (5.51–11.27) | 6.38 (4.43–9.19) |
| No | Reference | Reference |
| Marijuana | ||
| Yes | 4.77 (3.87–5.88) | 4.62 (3.71–5.77) |
| No | Reference | Reference |
| Coca paste | ||
| Yes | 15.52 (10.33–23.32) | 16.16 (10.97–23.79) |
| No | Reference | Reference |
| Ecstasy | ||
| Yes | 1.56 (0.40–6.11) | 1.31 (0.33–5.15) |
| No | Reference | Reference |
| Opioids | ||
| Yes | 4.72 (2.79–7.97) | 4.44 (2.64–7.48) |
| No | Reference | Reference |
| LSD | ||
| Yes | 4.47 (2.19–9.11) | 3.69 (1.80–7.52) |
| No | Reference | Reference |
| Mushrooms, yagé or ayahuasca, Angel's Trumpet | ||
| Yes | 3.94 (2.16–7.19) | 3.72 (2.05–6.75) |
| No | Reference | Reference |
| Cocaine | ||
| Yes | 9.19 (6.88–12.26) | 8.72 (6.52–11.68) |
| No | Reference | Reference |
PR: prevalence ratio; 95% CI: 95% confidence interval; model adjusted for: sex, age, marital status, children.
Significant values are shown in bold.
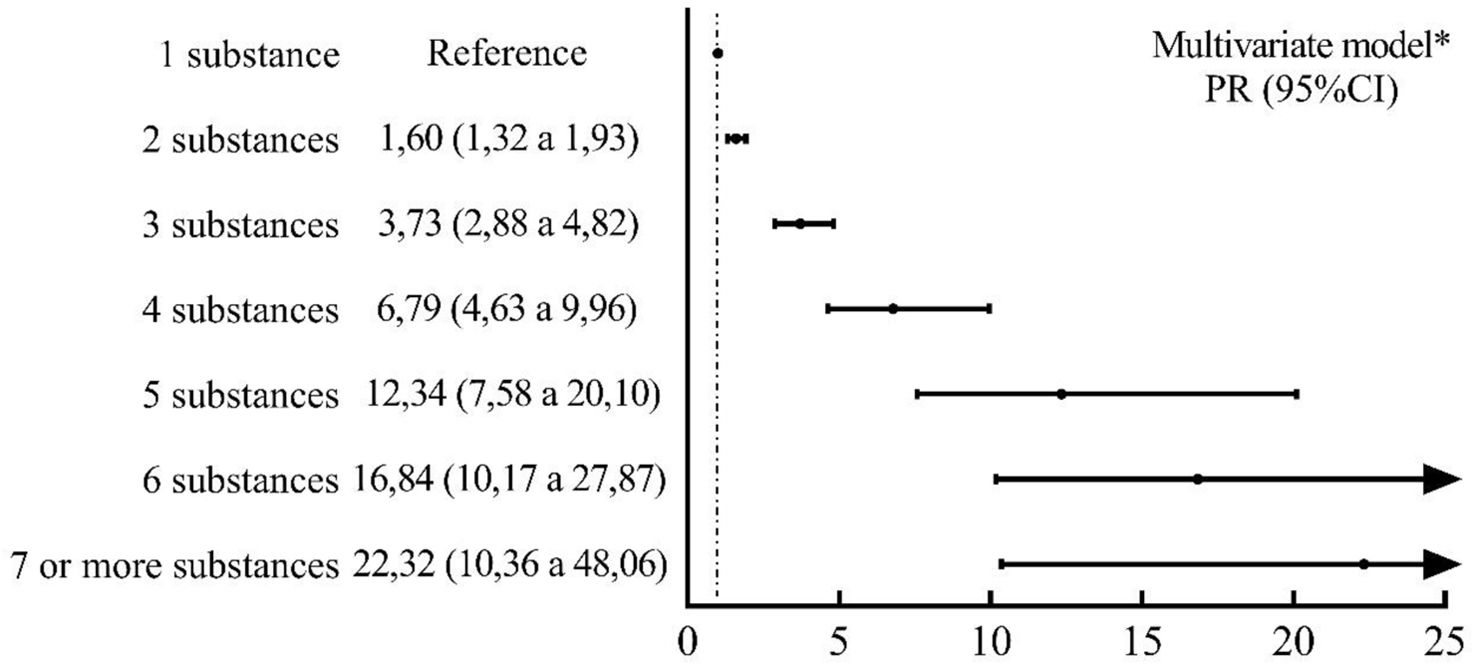
Fig. 1 shows that as the number of substances consumed increases, the magnitude of the association with STs does too. It indicates a dose–response relationship between different substances and STs.
Discussion
The most important finding was that, as in Colombian adolescents,9 almost all the substances analyzed showed a relation with STs, except for alcohol and ecstasy. Regarding sociodemographic variables, being female, having no permanent partner, and having no children were associated with a higher STs risk. Although these results are of interest, the present study will not discuss them in depth. The focus is on exploring the relationship between consuming different psychoactive substances and STs.
Alcohol and ecstasy were the only two substances that showed no association with STs. In the case of alcohol, this result may be explained by the fact that approximately 55% of the Colombian population over 12 years old report having consumed alcohol at least once in the past 12 months.15 This suggests that alcohol is a popular substance, and it has only been linked to STs when its use is problematic.17,18 According to recent meta-analyses, it has significantly increased the risk of suicidal ideation (OR: 1.86), attempted suicide (OR: 3.13) and completed suicide (OR: 2.59).17 Additionally, a linear relationship has been reported between AUDIT scores and the frequency of suicidal ideation.18 Likewise, interventions to reduce alcohol consumption decrease PAS frequency.19 Regarding this study, there is little evidence of association between sporadic alcohol consumption and PAS.
The second substance showing no association with STs was ecstasy. When we compared with a study developed in U.S. adults, its use was associated with a lower probability of suicidal thoughts in them,20 results that have also been found in American adolescents.21 Although few studies have examined the relationship between sporadic ecstasy use and STs, ecstasy has been reported as one of the most frequently detected substances in individuals who have died by suicide.22
Cigarette smoking showed a direct association with STs (PR 2.15; 95% CI 1.81–2.55). Similar results have been reported in young adults in the USA,23 and in adolescents in Colombia.9 In general, cigarette smoking has been considered a risk factor for suicidal ideation. Recently, a meta-analysis including more than two million people reported that current smokers had 84% and 35% higher risk of suffering STs, compared to nonsmokers and sporadic smokers.24 In general, studies show a directly proportional dose–response relation between number of cigarettes smoked and suicide risk.25
Marijuana use was associated with STs (PR 4.77; 95% CI 3.87–5.88). This result is almost twice higher than that reported in Colombian adolescents.9 It is consistent with results reported by a meta-analysis evaluating data from 34,859 young adults. According to its findings, marijuana use increases the risk of suicidal ideation, suicide attempts, and suicide planning.26 Such results are consistent with a twin study results where the marijuana-dependent individual was 2.5–2.9 times more likely to have STs compared to the non-dependent twin.27 Likewise, it has been reported that the more subjects reported frequent marijuana use, the more risk of STs they had.28
Regarding tranquilizers use, it increases STs probability (PR 7.56; 95% CI 5.62–10.17). Although this substance had been reported as the most associated with STs in Colombian adolescents,9 it is in fourth position in the case of adults. It should be noted that young women with suicidal ideation are more likely to use substance use, including sedatives or hypnotics.29 Nevertheless, no studies evaluating tranquilizer use and STs were found.
Firstly, the present study found that subjects who reported consuming stimulants without a physician's order evidenced an association with STs (PR=5.97; 95% CI 1.62–21.99). This result is similar to that reported in Colombian adolescents.9 However, such results cannot demonize the use of these drugs, since their use without a physician's order is high in Colombia.30 In the clinical intervention framework, studies found a significant reduction in suicidal behaviors31 when evaluating the effect of stimulants treatment.
Secondly, a statistically significant prevalence ratio was found between the use of poppers and STs (PR=7.88; 95% CI 5.51–11.27). A study in a cohort of young men who have sex with men found that nitrite inhalants use (poppers) was associated with an increased risk of suicidal ideation.32
Thirdly, there was a direct association between cocaine (PR=9.19; 95% CI 6.88–12.26) and coca paste use (PR=15.52; 95% CI 10.33–23.32) and STs. These two substances showed a greater relationship with STs, which is a similar result to that found in patients attending psychiatric emergency services. There, 43.7% of patients having only cocaine use disorders expressed suicidal ideation. That is a higher rate than that in those showing substance use disorders.33 Additionally, it has been shown that individuals displaying depression and cocaine use evidenced an association with increased prevalence of suicidal behavior and suicidal ideatio.34
Finally, when studying poly consumption, there was a proportional relation between the number of substances consumed and a greater possibility of having STs. This result had been previously reported in Colombian adolescents by different studies.35 For example, United States young adults who consume three or more types of substances (such as cigarettes, alcohol, marijuana and prescription opioids) are three to five times more likely to experience suicidal ideation, make a suicide plan or attempt suicide, compared to non-users.35
Strengths and limitationsThe principal strengths of this work include: (1) It is the first report that estimates the association between consumption of psychoactive substances and ST in a representative sample of Colombian adults; (2) The sample size is sufficiently robust to estimation these associations. Nonetheless, the research is subject to several limitations, stemming from its cross-sectional design, which precludes the examination of any causal mechanisms; although in this investigation the dependent variable was ST, it is imperative to underscore that the directionality provided is solely for the purpose of statistical analysis, and the causal relationship may indeed be bidirectional, or these two phenomena may arise from other underlying factors, such as additional mental health disorders. Another limitation pertains to the timeframe utilized for the assessment of consumption of various psychoactive substances, which was restricted to the preceding 12 months; it is pertinent to emphasize that the most robust indicator of consumption pertains to the prior month. Furthermore, no potentially confounding variables were incorporated into the analysis, including nutritional classification, levels of physical activity, religious beliefs, socioeconomic status, personal or familial history of ST, and history of depression, anxiety, or other mental health disorders.
ConclusionsThe results, herein, corroborate that use of psychoactive substances is associated with suffering from ST, similar to that described in Colombian adolescents.9 Poly-consumption of substances revealed a gradient, given that as the number of psychoactive substances increases, there is a greater chance of having suicidal thoughts; similar to that reported with other mental health problems. Emphasis must be placed on these three substances because these are the substances most-often used by adolescents. Further studies are suggested to evaluate those associations in the Colombian population.
FundingThe ENCSPA-2019 was funded by the Colombian government. Additionally, the authors have been supported by University of Pamplona and the University of Los Llanos.
Conflicts of interestWe declare no conflicts of interest.
We acknowledge the authorship and responsibility for this work. The original funding and contributions for its development are the responsibility of the authors and their affiliated institutions.


