




Dietary habits are closely related to symptom modulation in irritable bowel syndrome (IBS), yet their characterization remains limited. Understanding habitual food intake in IBS patients may contribute to diagnosis and support personalized management.
ObjectivesTo identify dietary patterns associated with IBS and to develop a diet-based score to aid in clinical stratification and nutritional guidance.
MethodsA case–control study was conducted including 109 participants (53 IBS patients and 56 healthy controls). Dietary intake was assessed using a validated short food frequency questionnaire. Multivariate logistic regression identified food items that best distinguished IBS patients from controls, which were then used to construct a composite dietary score.
ResultsIBS patients exhibited distinct dietary patterns, characterized by higher intake of carbohydrates and lower consumption of dairy products, while fruit and vegetable intake were similar between groups. A score based on the intake of rice, bread, yoghurt, minced meat, and distilled beverages showed good discriminatory capacity (sensitivity: 85.7%, specificity: 81.1%).
ConclusionsIBS patients present characteristic dietary profiles that may have diagnostic and therapeutic implications. The proposed dietary score could serve as a complementary tool to support clinical decision-making and guide personalized nutritional counseling. Further research is warranted to validate its applicability in routine clinical practice.
Los hábitos alimenticios están estrechamente relacionados con la modulación de los síntomas en el síndrome del intestino irritable (SII), pero su caracterización sigue siendo limitada. Comprender la ingesta habitual de alimentos en los pacientes con SII puede contribuir al diagnóstico y facilitar el tratamiento personalizado.
ObjetivosIdentificar los patrones alimenticios asociados al SII y desarrollar una puntuación basada en la dieta que ayude a la estratificación clínica y a la orientación nutricional.
MétodosSe realizó un estudio de casos y controles en el que participaron 109 personas (53 pacientes con SII y 56 controles sanos). La ingesta alimentaria se evaluó mediante un cuestionario breve y validado sobre la frecuencia de consumo de alimentos. Mediante una regresión logística multivariante se identificaron los alimentos que mejor distinguían a los pacientes con SII de los controles, que luego se utilizaron para construir una puntuación alimentaria compuesta.
ResultadosLos pacientes con SII mostraron patrones alimentarios distintos, caracterizados por una mayor ingesta de carbohidratos y un menor consumo de productos lácteos, mientras que la ingesta de frutas y verduras fue similar entre los grupos. Una puntuación basada en la ingesta de arroz, pan, yogur, carne picada y bebidas destiladas mostró una buena capacidad discriminatoria (sensibilidad: 85,7%, especificidad: 81,1%).
ConclusionesLos pacientes con SII presentan perfiles dietéticos característicos que pueden tener implicaciones diagnósticas y terapéuticas. La puntuación dietética propuesta podría servir como herramienta complementaria para respaldar la toma de decisiones clínicas y orientar el asesoramiento nutricional personalizado. Se necesitan más investigaciones para validar su aplicabilidad en la práctica clínica habitual.
Irritable bowel syndrome (IBS) is nowadays the most prevalent gastrointestinal disorder in the world, and it is progressively growing, especially in occidental countries. There are variations in the prevalence of this disease between different continents, from 7% in the Middle East and Southeast Asian; 11.8–14% in North America, North Europe, and Australia, to 15–21% in South Europe, Africa, and South America.1 Developing countries are finding an increase in IBS prevalence due to the progressive adoption of a western diet and lifestyle, which is one of the risk factors of developing this pathology.1
IBS is a functional gastrointestinal disorder whose main symptoms are abdominal pain, and changes in stool frequency and consistency.2 IBS diagnosis is based on the clinical parameters of Rome IV criteria3; however, the process can be complex and time-consuming. This underscores the need for simpler, practical scoring tools to facilitate early and accurate detection.
Despite its high prevalence, the etiology and pathophysiology of IBS remains unclear. Some hypotheses report that IBS is a multifactorial pathology, considering microbiota dysbiosis, psychosocial disorders and diet as predisposing factors.4 The role of diet has been widely studied as etiology and possible treatment of IBS. Actually, sensitivity to certain food is one of the hypotheses for the development of IBS,5 and approximately 50% of patients have the perception of having a food intolerance. Moreover, a higher incidence of IBS has been demonstrated among patients diagnosed with food intolerances.6 However, results from daily practice show no correlation between food intolerances or allergies and IBS.7 Nevertheless, there are investigations that show a higher number of positive skin allergy tests in IBS patients.8 Additionally, diet has been investigated as a possible prebiotic factor that enhances some intestinal microbiota changes. It also stimulates gut bacteria fermentation, leading into the production of bacterial metabolites, which can influence gut health.9
Diet can also be part of the treatment for IBS patients. The first line of dietary changes is free-FODMAP diet (a diet free from Fermentable Oligosaccharides, Disaccharides, Monosaccharides, and Polyols), which has shown improvements in IBS symptomatology, superior to any other dietary change.10 Other possible dietary interventions are avoiding gas-producing foods or introducing 20–30g of fiber per day in the diet. As a second line dietary intervention, gluten-free and lactose-free diet are recommended if excluding gas-producing food does not improve symptomatology.11 However, these two dietary restrictions are not agreed by all the investigations as there is not enough evidence yet.12 Diet is an important factor for IBS in two ways, on the one hand it can be a predisposal factor to develop or worsen IBS symptomatology. On the other hand, it can be used as a treatment for IBS patients, showing improvement of symptomatology. However, the implication of dietary habits as predictor factors of IBS remains unexplored. We hypothesized that individuals with IBS exhibit distinct dietary patterns that can influence the disease. To test this hypothesis, we conducted a case-control study comparing dietary habits between IBS patients and healthy controls, and used multivariate logistic regression to develop a composite score. This work is expected to advance the field by providing a novel, dietary-based complementary tool to guide personalized nutritional counseling and support clinical decision-making.
Materials and methods109 participants have been included from three different medical specialties consultations: primary care consultations of Univérsitas health center (Zaragoza, Spain), hospital emergencies and gastroenterology consultations of Hospital Clínico Lozano Blesa (Zaragoza, Spain). This study has been approved by the Ethical Committee of the Autonomic Community of Aragón (CEICA) with the favorable report number PI19/184, and inform consent has been obtained for all the participants. Although the present study is a preliminary effort to develop a dietary score associated with IBS diagnosis, we have reviewed the STARD and TRIPOD guidelines and implemented the recommendations relevant to this initial phase. Where applicable, specific items from these guidelines have been addressed within the manuscript, and a Supplementary table has been provided detailing the corresponding sections and justifications for items not applicable to this type of study.
ParticipantsThe minimum required sample size was calculated using the GRANMO online calculator. Due to the lack of previous studies reporting expected effect sizes for dietary interventions in patients with IBS, sample size estimation was based on differences between two proportions for a related clinical outcome. Specifically, expected proportions were derived from the reported prevalence of anxiety/depression, conditions known to be strongly associated with IBS.13 Accepting an alpha risk of 0.05 and a beta risk of 0.2 in a one-sided test, 50 subjects per group were required to detect differences between two proportions (expected proportions: 0.05 in the reference group and 0.20 in the exposed group), based on previously published prevalence data.14 The result of this calculation was that sample size should be formed by minimum 50 cases and 50 controls to obtain statistic results. After meeting the inclusion criteria, 109 persons were randomly selected to participate in this investigation. The inclusion criteria were for both cases and controls giving consent to participate in this study and were aged between 18 and 75 years old. For cases inclusion criteria were being diagnosed of IBS by meeting Rome IV criteria. For both cases and controls the exclusion criteria were being under or above the age range or suffering from another digestive illness. The study sample was made of 53 patients diagnosed of IBS and 56 healthy controls. We made personal interviews with each participant and reviewed their clinical history. Participants were asked for demographical information, clinical information as clinical history, pharmacotherapy, and dietary habits.
QuestionnairesShort, validated food frequency questionnaire was used to analyze the dietary habits. The questionary measures the weekly consumption frequency of 45 groups of foods (including fruits, vegetables, meat, fish, or bread) and alcoholic and non-alcoholic drinks. This method obtains information about the long-term habitual food consumption pattern in large populations. Its reproducibility has a correlation of 60% with respect to other questionnaires, especially if the aim of the study are groups of foods, macronutrients or energy.15
Statistical analysesThe statistical analysis was made using the program IBM-SPSS 22.0. With the data obtained, we made a descriptive statistical analysis and afterwards a comparative one, analyzing the distribution of the variables between cases and controls. Finally, a multivariate binary logistic regression analysis was carried out to develop a composite score. The selection of variables for this score was performed with the program UAB AllSetsReg – Linear & Logistic.
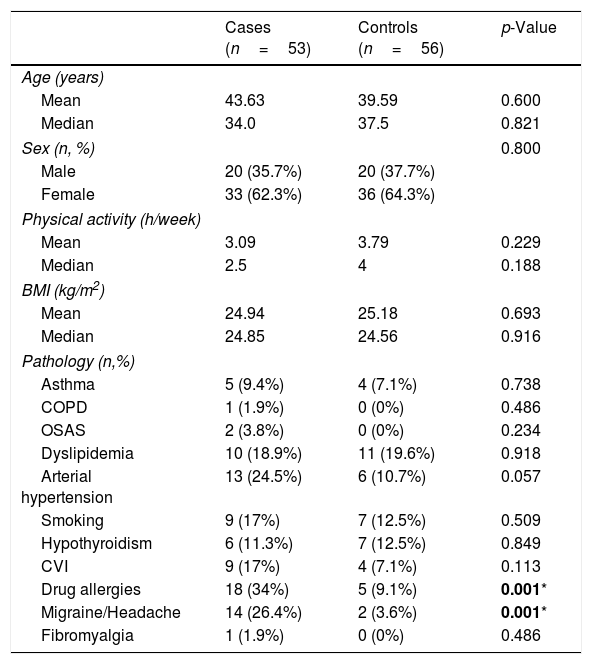
ResultsParticipant characteristicsIn total, 109 persons were included in this study, being 53 IBS patients and 56 healthy controls (Table 1). As the diagnosis of IBS is prevalently female, there were more women in both groups, accounting 36 women and 20 men in the control group and 33 women and 20 men in case group. In total, 63.3% of the sample was female and 36.7% male. The average age of the study sample was 42.09±2.01 years, and the median age was 36 years. In the case group, the average age was 43.63±19.36 and in the controls one, 39.59±13.09 years old (Table 1). Body Mass Index (BMI) was also calculated for both cases and controls, finding an average of BMI of 25.18±1.29 in the control group and 24.94±1.62 in the cases (p=0.693). Similarly, there were not differences in their medians (p=0.916), finding a median of 24.85 in controls and 24.56 in cases. Regarding physical activity, the case and control groups practiced sports an average of 3.08h and 3.79h per week, respectively (Table 1).
Demographic variables and clinical history of the participants: cases: IBS patients and healthy controls.
| Cases (n=53) | Controls (n=56) | p-Value | |
|---|---|---|---|
| Age (years) | |||
| Mean | 43.63 | 39.59 | 0.600 |
| Median | 34.0 | 37.5 | 0.821 |
| Sex (n, %) | 0.800 | ||
| Male | 20 (35.7%) | 20 (37.7%) | |
| Female | 33 (62.3%) | 36 (64.3%) | |
| Physical activity (h/week) | |||
| Mean | 3.09 | 3.79 | 0.229 |
| Median | 2.5 | 4 | 0.188 |
| BMI (kg/m2) | |||
| Mean | 24.94 | 25.18 | 0.693 |
| Median | 24.85 | 24.56 | 0.916 |
| Pathology (n,%) | |||
| Asthma | 5 (9.4%) | 4 (7.1%) | 0.738 |
| COPD | 1 (1.9%) | 0 (0%) | 0.486 |
| OSAS | 2 (3.8%) | 0 (0%) | 0.234 |
| Dyslipidemia | 10 (18.9%) | 11 (19.6%) | 0.918 |
| Arterial hypertension | 13 (24.5%) | 6 (10.7%) | 0.057 |
| Smoking | 9 (17%) | 7 (12.5%) | 0.509 |
| Hypothyroidism | 6 (11.3%) | 7 (12.5%) | 0.849 |
| CVI | 9 (17%) | 4 (7.1%) | 0.113 |
| Drug allergies | 18 (34%) | 5 (9.1%) | 0.001* |
| Migraine/Headache | 14 (26.4%) | 2 (3.6%) | 0.001* |
| Fibromyalgia | 1 (1.9%) | 0 (0%) | 0.486 |
BMI, body mass index.
Data are presented as means and medians for demographic characteristic. Student's t-test was used to compare means, and the Mann–Whitney U test was applied for non-parametric comparison of medians. Data from medical history illnesses were collected, including respiratory illnesses (asthma, Chronic Obstructive Pulmonary Disease-COPD, Obstructive Sleep Apnea Syndrome-OSAS), cardiovascular risks (dyslipidemia, arterial hypertension, smoking, Chronic venous insufficiency-CVI), pain disorders (migraine or headache, fibromyalgia) and other illnesses (hypothyroidism, chronic venous insufficiency, drug allergies). Data are presented as frequencies and percentages, n (%). The chi-square test was used to assess differences between groups; Fisher's exact test was applied when expected cell counts were below 5.
In the personal interviews, and afterwards revising medical histories from the participants of this study, the previous illnesses were analyzed and compared between both groups (Table 1). Respiratory diseases as asthma, chronic obstructive pulmonary disease or obstructive sleep apnea syndrome, show no differences between both groups. Regarding cardiovascular risk factors, dyslipidemia, smoking, and arterial hypertension were assessed; 6 controls and 13 cases were diagnosed with arterial hypertension (p=0.057). Drug allergies show statistical differences, but no disparities were found in general allergies (rhinitis, conjunctivitis). Marked differences were found in migraine or headache, counting 2 controls and 14 cases suffering from this condition. Regarding fibromyalgia, another condition that courses with pain, no differences were discovered, finding only one case and no controls diagnosed of fibromyalgia (p=0.486).
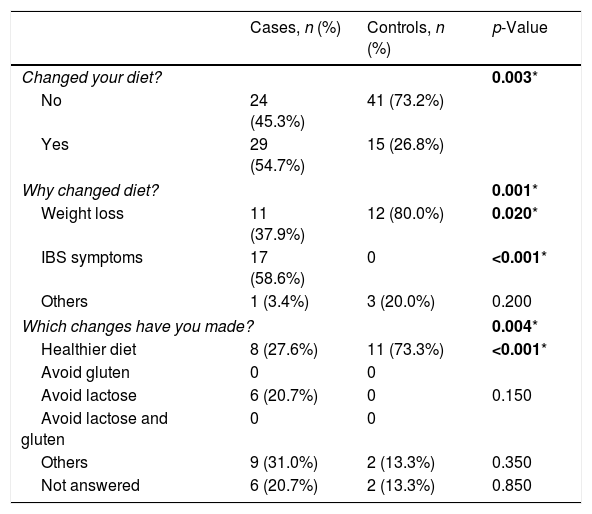
Dietary differences between IBS cases and healthy controlsParticipants were asked whether they had recently made changes into their diets. 54.7% of cases reported dietary changes compared to controls (26.8%). Among cases, the primary reason for altering their diet was IBS-related symptoms (58.6%), whereas in controls, the main reason was weight loss (80%) (Table 2). Participants who had modified their diets were then asked about the specific changes they made, categorized into five groups: adopting a healthier diet (reducing fatty and sugary foods), avoiding gluten, avoiding lactose, avoiding both gluten and lactose, or making other changes. Eleven controls (73.33%) and eight cases (27.6%) shifted to a healthier diet. No controls but six cases (20.7%) avoided lactose-containing foods, while two controls (13.33%) and nine cases (31%) made other dietary modifications.
Diet changes in cases (IBS patients) and healthy controls.
| Cases, n (%) | Controls, n (%) | p-Value | |
|---|---|---|---|
| Changed your diet? | 0.003* | ||
| No | 24 (45.3%) | 41 (73.2%) | |
| Yes | 29 (54.7%) | 15 (26.8%) | |
| Why changed diet? | 0.001* | ||
| Weight loss | 11 (37.9%) | 12 (80.0%) | 0.020* |
| IBS symptoms | 17 (58.6%) | 0 | <0.001* |
| Others | 1 (3.4%) | 3 (20.0%) | 0.200 |
| Which changes have you made? | 0.004* | ||
| Healthier diet | 8 (27.6%) | 11 (73.3%) | <0.001* |
| Avoid gluten | 0 | 0 | |
| Avoid lactose | 6 (20.7%) | 0 | 0.150 |
| Avoid lactose and gluten | 0 | 0 | |
| Others | 9 (31.0%) | 2 (13.3%) | 0.350 |
| Not answered | 6 (20.7%) | 2 (13.3%) | 0.850 |
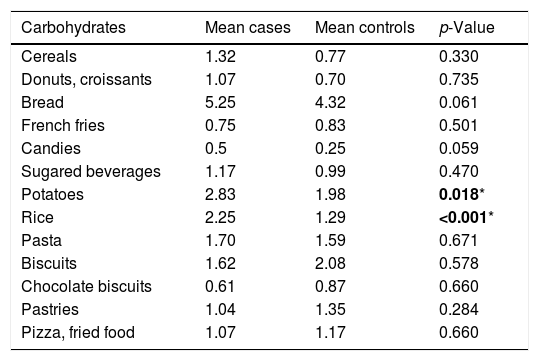
The weekly consumption of several food groups was assessed using a short, validated Food Frequency Questionnaire. Potato and rice intake were considerably higher in the case group than in the control group, with cases consuming 43% more potatoes and 75% more rice. Conversely, controls documented a higher intake of yoghurt, minced meat, ice cream, wine, beer, and distilled beverages. Additionally, cases showed a trend toward consuming fewer cakes, seafood, and milk, and more bread. All completed data are shown in Supplementary data 1.
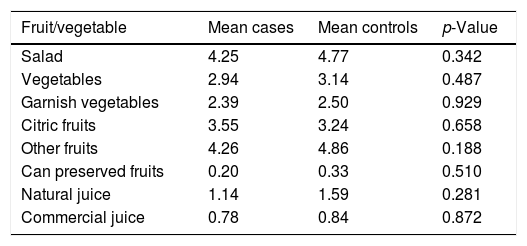
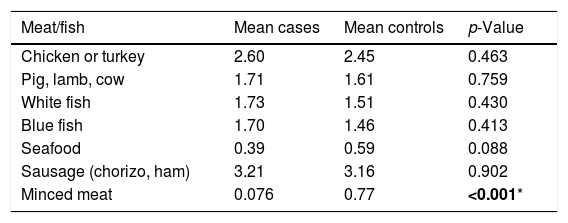
Our results show that individuals with IBS consume carbohydrates more frequently than healthy controls. The overall weekly intake of carbohydrates is higher in IBS cases compared to controls (21.18 versus 18.19 times per week), as presented in Table 3. Some carbohydrate sources, such as potatoes and rice, show higher consumption in IBS cases than in controls. Interestingly, the consumption of cookies, chocolate cookies, pastries, pizza, and fried foods is greater in the control group than in IBS cases. Regarding the consumption of fruits and vegetables, and animal protein, Tables 4 and 5 summarize the weekly intake data. No differences were found in the consumption of various fruit and vegetable groups. However, in terms of meat consumption, our study identified that IBS cases consumed minced meat significantly less frequently than controls (p < 0.001). Additionally, seafood consumption is less consumed in IBS cases compared to controls (p=0.088).
Weekly consumption (times per week) of carbohydrates; cases: IBS patients and healthy controls.
| Carbohydrates | Mean cases | Mean controls | p-Value |
|---|---|---|---|
| Cereals | 1.32 | 0.77 | 0.330 |
| Donuts, croissants | 1.07 | 0.70 | 0.735 |
| Bread | 5.25 | 4.32 | 0.061 |
| French fries | 0.75 | 0.83 | 0.501 |
| Candies | 0.5 | 0.25 | 0.059 |
| Sugared beverages | 1.17 | 0.99 | 0.470 |
| Potatoes | 2.83 | 1.98 | 0.018* |
| Rice | 2.25 | 1.29 | <0.001* |
| Pasta | 1.70 | 1.59 | 0.671 |
| Biscuits | 1.62 | 2.08 | 0.578 |
| Chocolate biscuits | 0.61 | 0.87 | 0.660 |
| Pastries | 1.04 | 1.35 | 0.284 |
| Pizza, fried food | 1.07 | 1.17 | 0.660 |
Weekly consumption (times per week) of fruits and vegetables; cases: IBS patients and healthy controls.
| Fruit/vegetable | Mean cases | Mean controls | p-Value |
|---|---|---|---|
| Salad | 4.25 | 4.77 | 0.342 |
| Vegetables | 2.94 | 3.14 | 0.487 |
| Garnish vegetables | 2.39 | 2.50 | 0.929 |
| Citric fruits | 3.55 | 3.24 | 0.658 |
| Other fruits | 4.26 | 4.86 | 0.188 |
| Can preserved fruits | 0.20 | 0.33 | 0.510 |
| Natural juice | 1.14 | 1.59 | 0.281 |
| Commercial juice | 0.78 | 0.84 | 0.872 |
Data are expressed as the mean weekly consumption (times per week). Student's t-test was used to compare means.
Weekly consumption (times per week) of meat and fish; cases: IBS patients and healthy controls.
| Meat/fish | Mean cases | Mean controls | p-Value |
|---|---|---|---|
| Chicken or turkey | 2.60 | 2.45 | 0.463 |
| Pig, lamb, cow | 1.71 | 1.61 | 0.759 |
| White fish | 1.73 | 1.51 | 0.430 |
| Blue fish | 1.70 | 1.46 | 0.413 |
| Seafood | 0.39 | 0.59 | 0.088 |
| Sausage (chorizo, ham) | 3.21 | 3.16 | 0.902 |
| Minced meat | 0.076 | 0.77 | <0.001* |
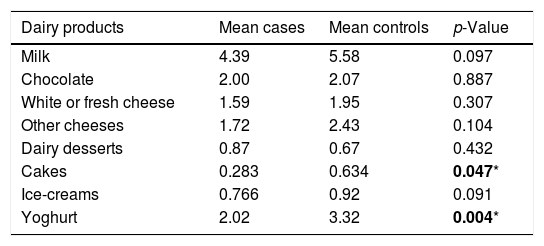
Contrary to the trend observed with carbohydrates, the overall consumption of dairy products was lower in IBS cases than in controls (13.64 versus 17.57 times per week) as displayed in Table 6. With the exception of dairy desserts, all dairy product groups were consumed less frequently by IBS cases, especially cakes, which weekly consume was 0.28 (0–0.588) in cases and 0.63 (0.207–0.889) in controls (p=0.047) and yoghurt, which consume was 2.02 yoghurts per week in cases and 3.32 in controls (p=0.004). Although the mean consume of ice cream between cases and controls was similar 0.92 (0.571–1.256) in controls and 0.766 (0.124–0.454) in cases (p=0.091), the comparison of medians showed differences (p=0.024) (Supplementary data 1).
Weekly consumption (times per week) of dairy products; cases: IBS patients and healthy controls.
A univariate analysis was performed, including all study variables with a p-value less than 0.20. Afterwards, the existence of interactions between variables was evaluated, dismissing it, as these interactions were not statistically different. Later, a logistic regression was done by the program “UAB AllSetsReg – Linear & Logistic”, considering finally as variables for the equation: rice, bread, yoghurt, minced meat and distilled beverages. As these variables are quantitative, Exp (B) indicates the change of proportion of individuals with IBS for each unit of increase or decrease of weekly consume of each food. To facilitate the interpretation, we decided to dichotomize these variables by stablishing the cut-off points that differentiated the medians of one group and the other, ending up in the following way: bread consume >5 vs ≤5/week; Rice consume >1 vs ≤1/week; distilled beverages consume=0 vs >0/week; minced meat consume=0 vs >0/week; yoghurt consume >1 vs ≤1/week.
We verified the existence of differences in both groups doing a comparison of proportions with the Chi-squared test for each food. We analyzed it with different cut-off points for each food, choosing the point that resulted more discriminative between both groups. Being these variables dichotomized, Exp (B) can be interpreted as the relative risk. Results from the logistic regression analysis are shown in Supplementary data 3. Although the p-value for distilled beverages was <0.05 in the univariate analysis and 0.056 in the multivariate one, this variable was included in the logistic regression model because its weigh in the final model was high and statistically significant (Supplementary data 5).
Having these data into account, the logistic regression equation obtained was:
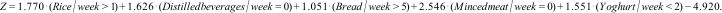
In order to simplify the score calculation, we rounded the coefficients of this equation obtaining the following score:
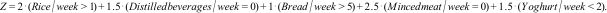
The application of this score gives us the probability of an individual belonging to the IBS-group (Supplementary data 2). To use the score, we have to multiply by one each coefficient of those food intake that our patient does. As an example, when we suspect that a patient can be suffering from IBS, and we know that this patient eats rice more often than once a week, drinks distilled beverages twice a week, eats bread 6 times/week, and yoghurt 3 times/week, and does no consume minced meat, the score will result this way: Z=2·1+1.5·0+1·1+2.5·1+1.5·0=5.5.
Once we obtain the punctuation of the score, we check the probability of belonging to the IBS-group in Supplementary data 2. Obtaining a Score punctuation of 4.5 or above, makes IBS probability higher than 50%. Supplementary data 4 shows the classification power of the score as a diagnostic test. Our score presents 85.7% of sensitivity and 81.1% of specificity.
DiscussionOur study found that IBS patients exhibited distinctive dietary patterns, including higher consumption of rice and potatoes and lower intake of minced meat. While fruit and vegetable intake were comparable between groups, individuals with IBS reported reduced consumption of cakes and yoghurt. Based on these findings, a composite score was developed using the intake of rice, bread, yoghurt, minced meat, and distilled beverages. This score showed high diagnostic accuracy, with a sensitivity of 85.7% and specificity of 81.1%. These results suggest that habitual dietary patterns may serve as a valuable tool in supporting the IBS management through a novel, food-based scoring approach. However, as the sample was not obtained through a random selection process, the statistical measures reported (including confidence intervals) should be viewed as approximate. Accordingly, the true uncertainty may be somewhat greater than the amount quantified.
Diet may be a predisposing factor to develop IBS. It is conjectured that some food could work as prebiotics for intestinal microbiota, favoring the growth of certain fermentable bacteria strains, which would contribute to symptoms as bloating, gases, or abdominal pain.9 Moreover, products from bacterial fermentation could derive in cellular changes in the intestinal mucosa which induce dysmotility and an abnormal intestinal secretion.16 Short-chain fatty acids (SCFAs), propionate, acetate, and butyrate, are also produced by intestinal microbiota, which can modulate the serotoninergic system and intestinal homeostasis, potentially leading to the development of intestinal or neuropsychiatric pathologies. Moreover, SCFAs production have been related with an improvement in IBS symptoms and lower inflammatory colonic response.17 On this matter, other studies have found a higher abundance of Faecalibacterium prausnitzii, associated to a higher intake of dietary fiber and iron in IBS patients.18 In this work, we have found higher intake of rice, potatoes, bread, cereals, and pasta in cases than controls, which are foods rich in fiber. However, the consumption of vegetables, legumes, nuts, and fruits, which are also fiber-rich foods, showed no difference between both groups. Some studies have described the diet as a part of IBS pathophysiology, as there are changes in IBS incidence between different parts of the world. Asian countries, where people consume a diet rich in unrefined carbohydrates (such as whole grains), vegetables, legumes, and low-calorie beverages like tea, and low in red meat and saturated fat,19 have a lower incidence of IBS compared to Western countries, whose diet is predominantly high in fat, sugar, and processed foods.16 Moreover, the Western diet, which is high in sugar and fat, has been described as a risk factor for IBS development and also, the consumption of processed food has demonstrated an association with IBS development.20
IBS patients frequently associate their symptomatology to the intake of certain foods as wheat-derived products, lactose, onion, spicy spices, alcohol, coffee, or fried food. Seeking a symptomatology improvement, patients eliminate certain foods from their diet.21 In agreement, our results show marked dietary changes between cases and controls; the main reason being gastrointestinal symptomatology. Our IBS cases reduce lactose and alcohol consume, as it has been evidenced by Nybacka et al. who prove that IBS patients avoid gluten, lactose, and alcohol more often than healthy individuals and these latter changes are due to abdominal pain.22 However, some studies revealed that a lactose-free diet should not be routinely recommended for IBS patients.23 On the other hand, the experience of medical dietary changes in IBS patients has been studied, highlighting on the feeling of being supported by clinicians, but also the difficulty to maintain these changes long term.24
Our study showed different dietary patterns of IBS cases and controls. Cases eat rice and potatoes more often than healthy controls. Additionally, they eat more bread and carbohydrates than controls. Contrarily, Zhang et al. expose that there is no correlation between the proportion of carbohydrates in the diet and IBS.25 However, among the diets analyzed as a possible treatment for IBS, the Very Low Carbohydrate Diet (VLCD) has demonstrated improvement of IBS symptomatology. This diet consists in the intake of 20g of carbohydrates per day and it could be correlated to our findings, as IBS patients show several digestive symptoms which could be caused by a higher intake of carbohydrates. In the same way, some IBS patients that carry a genetic variation in the enzyme hCAZyme may be beneficiary of diets with lower quantities of carbohydrates, showing more improvement of their symptomatology.26
Another possible reason for the higher consume of rice and potatoes is the astringent nature of both foods, which can relieve diarrhea in some patients. Furthermore, a diet rich in rice has shown ulterior changes in microbiota composition, such as an increase of Clostridium senso stricto 1, Eubacterium nodatum, Ruminococcus gauvreauii, Eubacterium coprostanoligenes and Ruminococcus 1, which can influence in gut motility.27
Conversely, the general consumption of dairy products was lower in IBS cases than in controls. Cases have a lower consume of yoghurt, ice-creams, and cakes than controls, which could be related to the withdrawal of lactose from diet, although there are no notable differences in the consume of milk. Since IBS patients complain about symptomatology worsening with FODMAPs intake, and lactose is a fermentable disaccharide, this could be a reason why these groups of foods are less consumed in cases than controls. Although the proinflammatory effect of milk and dairy products has been studied, showing there is no inflammatory effect on the consume of these products.28 Interestingly, a study with symbiotic yoghurt demonstrated improvements in symptomatology and microbiota composition in IBS patients.29 In the same way, there is a lower use of alcohol in cases than controls, which is in accordance with the withdrawal of the food groups described above. Some studies have described an inversely proportional relation between alcohol drink and IBS prevalence, supporting these results.30
The intake of minced-meat is remarkable, as it is a very strong variable in the multivariant analysis, resulting that people who do not consume minced-meat have 12.8 times more probability of belonging to the IBS-group than those individuals consuming minced-meat. It is difficult to conclude with this result that general population should eat minced meat, but we can suggest the implementation of a balanced diet, including all kind of foods, without excesses or defects of any specific kind. It has been studied that women avoid certain self-perceived unhealthy foods more often than men; these foods include red meat and food additives among others. This could be a reason why IBS patients (who are predominantly women) could avoid eating minced meat. Considering FODMAP free diet, meat is not a high FODMAP food, but as minced meat can be mixed with more ingredients, those are probably high in FODMAP. That could be another reason of the withdrawal of minced meat of cases. On the other hand, minced meat is easier digested than meat steaks, turning into possible changes in the microbiota composition, and thus into possible digestive symptoms.31
The data obtained from the multivariate analysis are very interesting for the development of a consensual diet to treat IBS patients and as a complementary tool to guide personalized nutritional counseling and support clinical decision-making. Dietary habits have also been studied as a possible underlaying factor for the development of other digestive illnesses, concluding that some diets are a risk factor for the contract of pancreatitis or that the western pattern diet predisposes patients to have ulcerative colitis.32
Our results allow for the development of a composite score based on dietary patterns that may facilitate the IBS management. This approach could also improve patients’ quality of life by guiding them toward a personalized, effective diet that helps reduce the intensity of their symptoms. Nevertheless, this score must be validated in the future by applying it to more IBS patients and examining its consistency and changes over time.
Author contributionsM. Gros: Investigation, Data curation, Formal analysis, Writing – Original Draft.
B. Gros-Bañeres: Investigation, Formal analysis, Methodology.
J.E. Mesonero: Conceptualization, Funding acquisition, Supervision, Writing – Review & Editing.
E. Latorre: Conceptualization, Supervision, Writing – Original Draft, Writing – Review & Editing.
Ethical considerationsThe study was conducted in accordance with the ethical principles outlined in the Declaration of Helsinki and complied with the Uniform Requirements for Manuscripts Submitted to Biomedical Journals. Informed consent was obtained from all participants prior to their inclusion in the study. The study was approved by the corresponding Research Ethics Committee (CEICA), and participants’ privacy and confidentiality were rigorously protected throughout the research.
FundingThis work was funded by grants from the Foundation for the Study of Inflammatory Bowel Diseases in Aragón (ARAINF 2012/0567) and from European Social Found (ESF) and the Aragón Regional Government (A20_23R).
Conflict of interestsThe authors declare no competing interests.
The authors have no acknowledgments to declare.
The followings are the supplementary data to this article:






