




Anabolic androgenic steroids (AAS), used at supraphysiological doses, are an underrecognized cause of primary hepatocellular tumors, particularly hepatocellular adenoma (HCA) and carcinoma (HCC), typically arising in young, non-cirrhotic patients outside the usual demographic for liver cancer. This review summarizes the clinical presentation, imaging features, and molecular basis of androgen-associated hepatocellular neoplasia and provides a practical framework for recognition and management. Androgen receptor (AR) signaling drives hepatocarcinogenesis through the cell cycle-related kinase/β-catenin pathway and mTOR complex 1-mediated AR stabilization; the β-catenin-activated HCA subtype, over-represented in this setting, carries the highest risk of malignant transformation. Because serum alpha-fetoprotein is often normal and cirrhosis is typically absent, diagnosis requires a high index of clinical suspicion and a structured exposure history. We outline an approach to imaging work-up, AAS cessation, and follow-up, and discuss when referral for biopsy, resection, or specialist hepatology review is warranted.
Los esteroides androgénicos anabolizantes (EAA), utilizados a dosis suprafisiológicas, constituyen una causa infrarreconocida de tumores hepatocelulares primarios, en particular el adenoma hepatocelular (AHC) y el carcinoma hepatocelular (CHC), que suelen aparecer en pacientes jóvenes, no cirróticos, fuera del perfil demográfico habitual del cáncer de hígado. Esta revisión resume la presentación clínica, las características de imagen y las bases moleculares de la neoplasia hepatocelular asociada a andrógenos, y ofrece un marco práctico para su reconocimiento y manejo. La señalización del receptor androgénico (RA) impulsa la hepatocarcinogénesis a través de la vía de la cinasa relacionada con el ciclo celular/β-catenina y de la estabilización del RA mediada por el complejo mTOR 1; el subtipo de AHC activado por β-catenina, sobrerrepresentado en este contexto, conlleva el mayor riesgo de transformación maligna. Dado que la alfafetoproteína sérica suele ser normal y la cirrosis está habitualmente ausente, el diagnóstico requiere un alto índice de sospecha clínica y una anamnesis estructurada sobre la exposición. Se describe un enfoque para el estudio por imagen, el cese del consumo de EAA y el seguimiento, y se analiza cuándo está indicada la derivación para biopsia, resección o valoración especializada en hepatología.
Anabolic androgenic steroids are synthetic compounds structurally related to testosterone that exert both anabolic effects (promotion of muscle growth and nitrogen retention) and androgenic effects (virilization). In current clinical practice, AAS retain a limited number of legitimate indications, including selected forms of hypogonadism and certain hematologic disorders, whereas their much broader use is non-medical and performance- or appearance-oriented.1–4 Contemporary patterns of misuse involve supraphysiological doses, stacking of multiple agents, prolonged cycles, and concomitant use of other performance-enhancing drugs, all of which substantially increase the risk of systemic toxicity.1–3
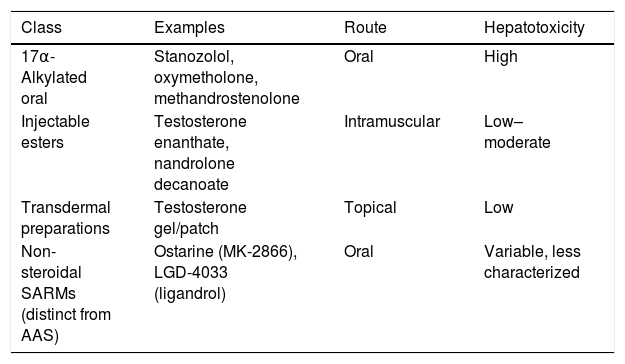
Hepatic injury is one of the most consistently recognized non-endocrine complications of AAS exposure. Reported manifestations range from mild and transient aminotransferase elevation to prolonged cholestatic injury, peliosis hepatis, vascular abnormalities, and focal liver lesions including both benign and malignant tumors.5–7 Oral 17α-alkylated derivatives appear particularly hepatotoxic, a characteristic attributed to impaired hepatic first-pass metabolism, although clinically significant injury can also occur with other formulations1,5 (Table 1).
Classification of anabolic androgenic steroids and their relative hepatotoxicity.
| Class | Examples | Route | Hepatotoxicity |
|---|---|---|---|
| 17α-Alkylated oral | Stanozolol, oxymetholone, methandrostenolone | Oral | High |
| Injectable esters | Testosterone enanthate, nandrolone decanoate | Intramuscular | Low–moderate |
| Transdermal preparations | Testosterone gel/patch | Topical | Low |
| Non-steroidal SARMs (distinct from AAS) | Ostarine (MK-2866), LGD-4033 (ligandrol) | Oral | Variable, less characterized |
AAS: anabolic androgenic steroids; SARM: selective androgen receptor modulator. SARMs are non-steroidal synthetic androgen receptor ligands and are pharmacologically distinct from AAS; they are included here for context given frequent co-use but are not classified as steroids. Among true AAS, hepatotoxic potential is determined primarily by chemical structure—particularly 17α-alkylation, which confers resistance to hepatic first-pass metabolism—rather than by route of administration alone. Hepatotoxicity ratings are based on published clinical and mechanistic data.1,4,5
The oncologic relevance of this topic is underscored by the fact that hepatocellular carcinoma remains among the leading causes of cancer-related mortality worldwide, with approximately 906,000 new cases and 830,000 deaths estimated in 2020 alone.8 Most clinicians traditionally associate HCC with cirrhosis, chronic viral hepatitis, or metabolic dysfunction-associated steatotic liver disease.8–10 In contrast, AAS-associated hepatic tumors may arise in younger individuals without the typical background of advanced chronic liver disease, creating a clinical scenario in which diagnosis may be substantially delayed unless a history of androgen exposure is actively sought.6,11
MethodologyA literature review was performed using PubMed/MEDLINE and Scopus as primary databases. Search terms included combinations of “anabolic androgenic steroids,” “hepatocellular adenoma,” “hepatocellular carcinoma,” “androgen receptor,” “β-catenin,” “mTOR,” “liver tumor,” “hepatotoxicity,” and “peliosis hepatis.” Articles published up to January 2026 were screened. Original experimental and immunohistochemical studies, molecular classification studies, narrative and systematic reviews, and histopathologically informative case reports were considered when relevant to the morphological and molecular characterization of androgen-associated hepatocellular tumors. Non-English-language articles, duplicate records, and reports without clear relevance to liver injury or liver tumorigenesis were excluded. Reference lists of retrieved articles were additionally screened to identify further relevant sources.
ReviewClinical context and patterns of AAS exposureThe prevalence of non-medical AAS use has increased substantially over the past three decades, expanding well beyond competitive athletes to include recreational bodybuilders, strength athletes, and a broad population of men and women motivated by body image concerns.1–3 Contemporary users frequently obtain compounds through informal online markets, combine injectable and oral preparations (“stacking”), and use doses that far exceed therapeutic replacement regimens, sometimes by factors of 10–100.1,2 This pattern is important because the risk of hepatotoxicity depends not only on the specific compound but also on the route of administration, cumulative duration of exposure, and coexisting use of alcohol, dietary supplements, or other hepatotoxic substances.1,5
The demographic shift in AAS misuse, now extending to amateur athletes and fitness-oriented individuals of both sexes, implies that exposure may be encountered in patients who do not fit the stereotypical profile of a competitive bodybuilder.3 Clinicians should therefore maintain a broad index of suspicion when evaluating hepatic abnormalities in young or middle-aged patients with a history of intensive physical training or interest in physique enhancement.1,2,4
Spectrum of AAS-associated hepatic pathologyAAS-related hepatic injury represents a morphological and clinical continuum rather than a single, uniform phenotype. At the milder end, biochemical abnormalities may be transient and detected incidentally on laboratory testing. At the more severe end, patients may develop prolonged cholestasis, peliosis hepatis—a condition characterized by blood-filled sinusoidal spaces within the hepatic parenchyma—spontaneous hemorrhage from hepatic adenomas, or frank malignant transformation.5–7 The 17α-alkylated oral steroids are consistently associated with the highest hepatotoxic potential, partly through inhibition of bile acid transport proteins and alteration of hepatocellular tight junctions, leading to intrahepatic cholestasis.5
A practical diagnostic challenge arises because intense resistance training itself may increase serum aminotransferase concentrations through skeletal muscle injury, potentially obscuring the hepatic signal. Isolated laboratory abnormalities in AAS users should therefore be interpreted alongside markers less affected by muscular exertion, such as gamma-glutamyltransferase or conjugated bilirubin, and in the broader context of exposure history and clinical presentation.5,6
Molecular basis of androgen-driven hepatocarcinogenesisThe biological activity of androgens is mediated by the androgen receptor (AR), a ligand-activated nuclear transcription factor that, upon binding testosterone or synthetic AAS, translocates to the nucleus and regulates transcription of target genes.12 AR signaling in hepatocellular carcinoma may also occur through constitutively active, ligand-independent states, providing a plausible mechanism for sustained oncogenic signaling even after AAS cessation.13
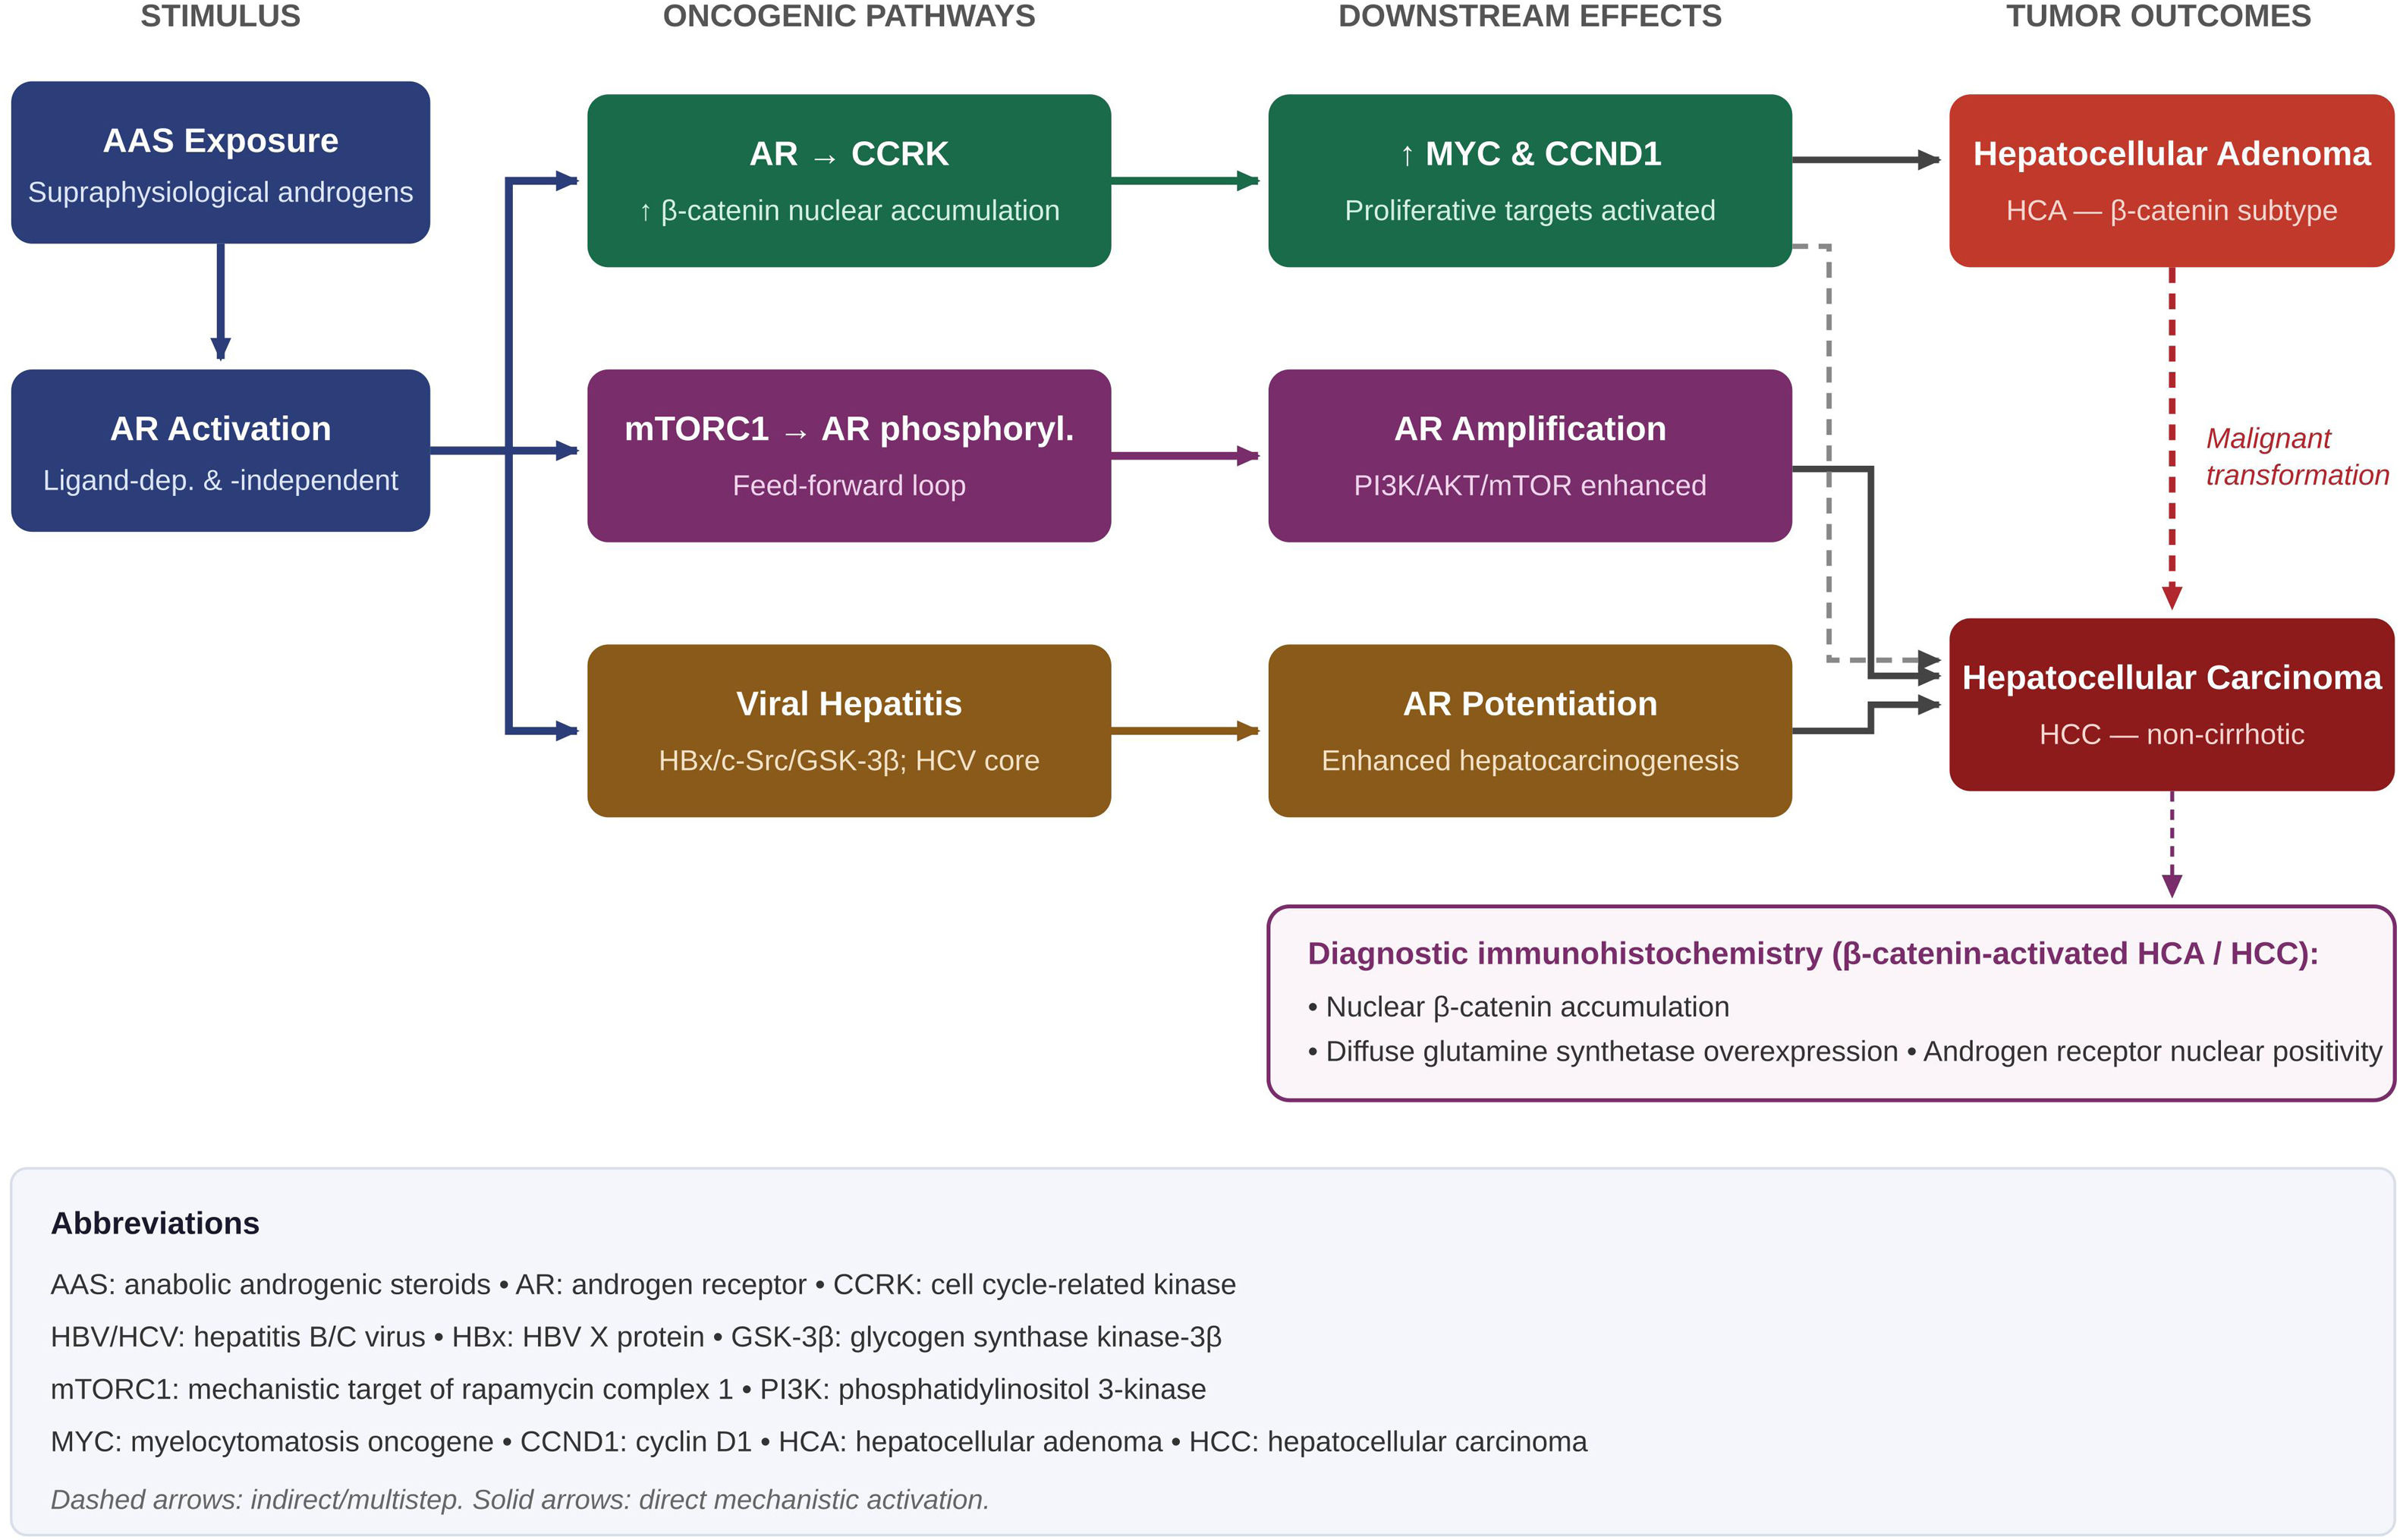
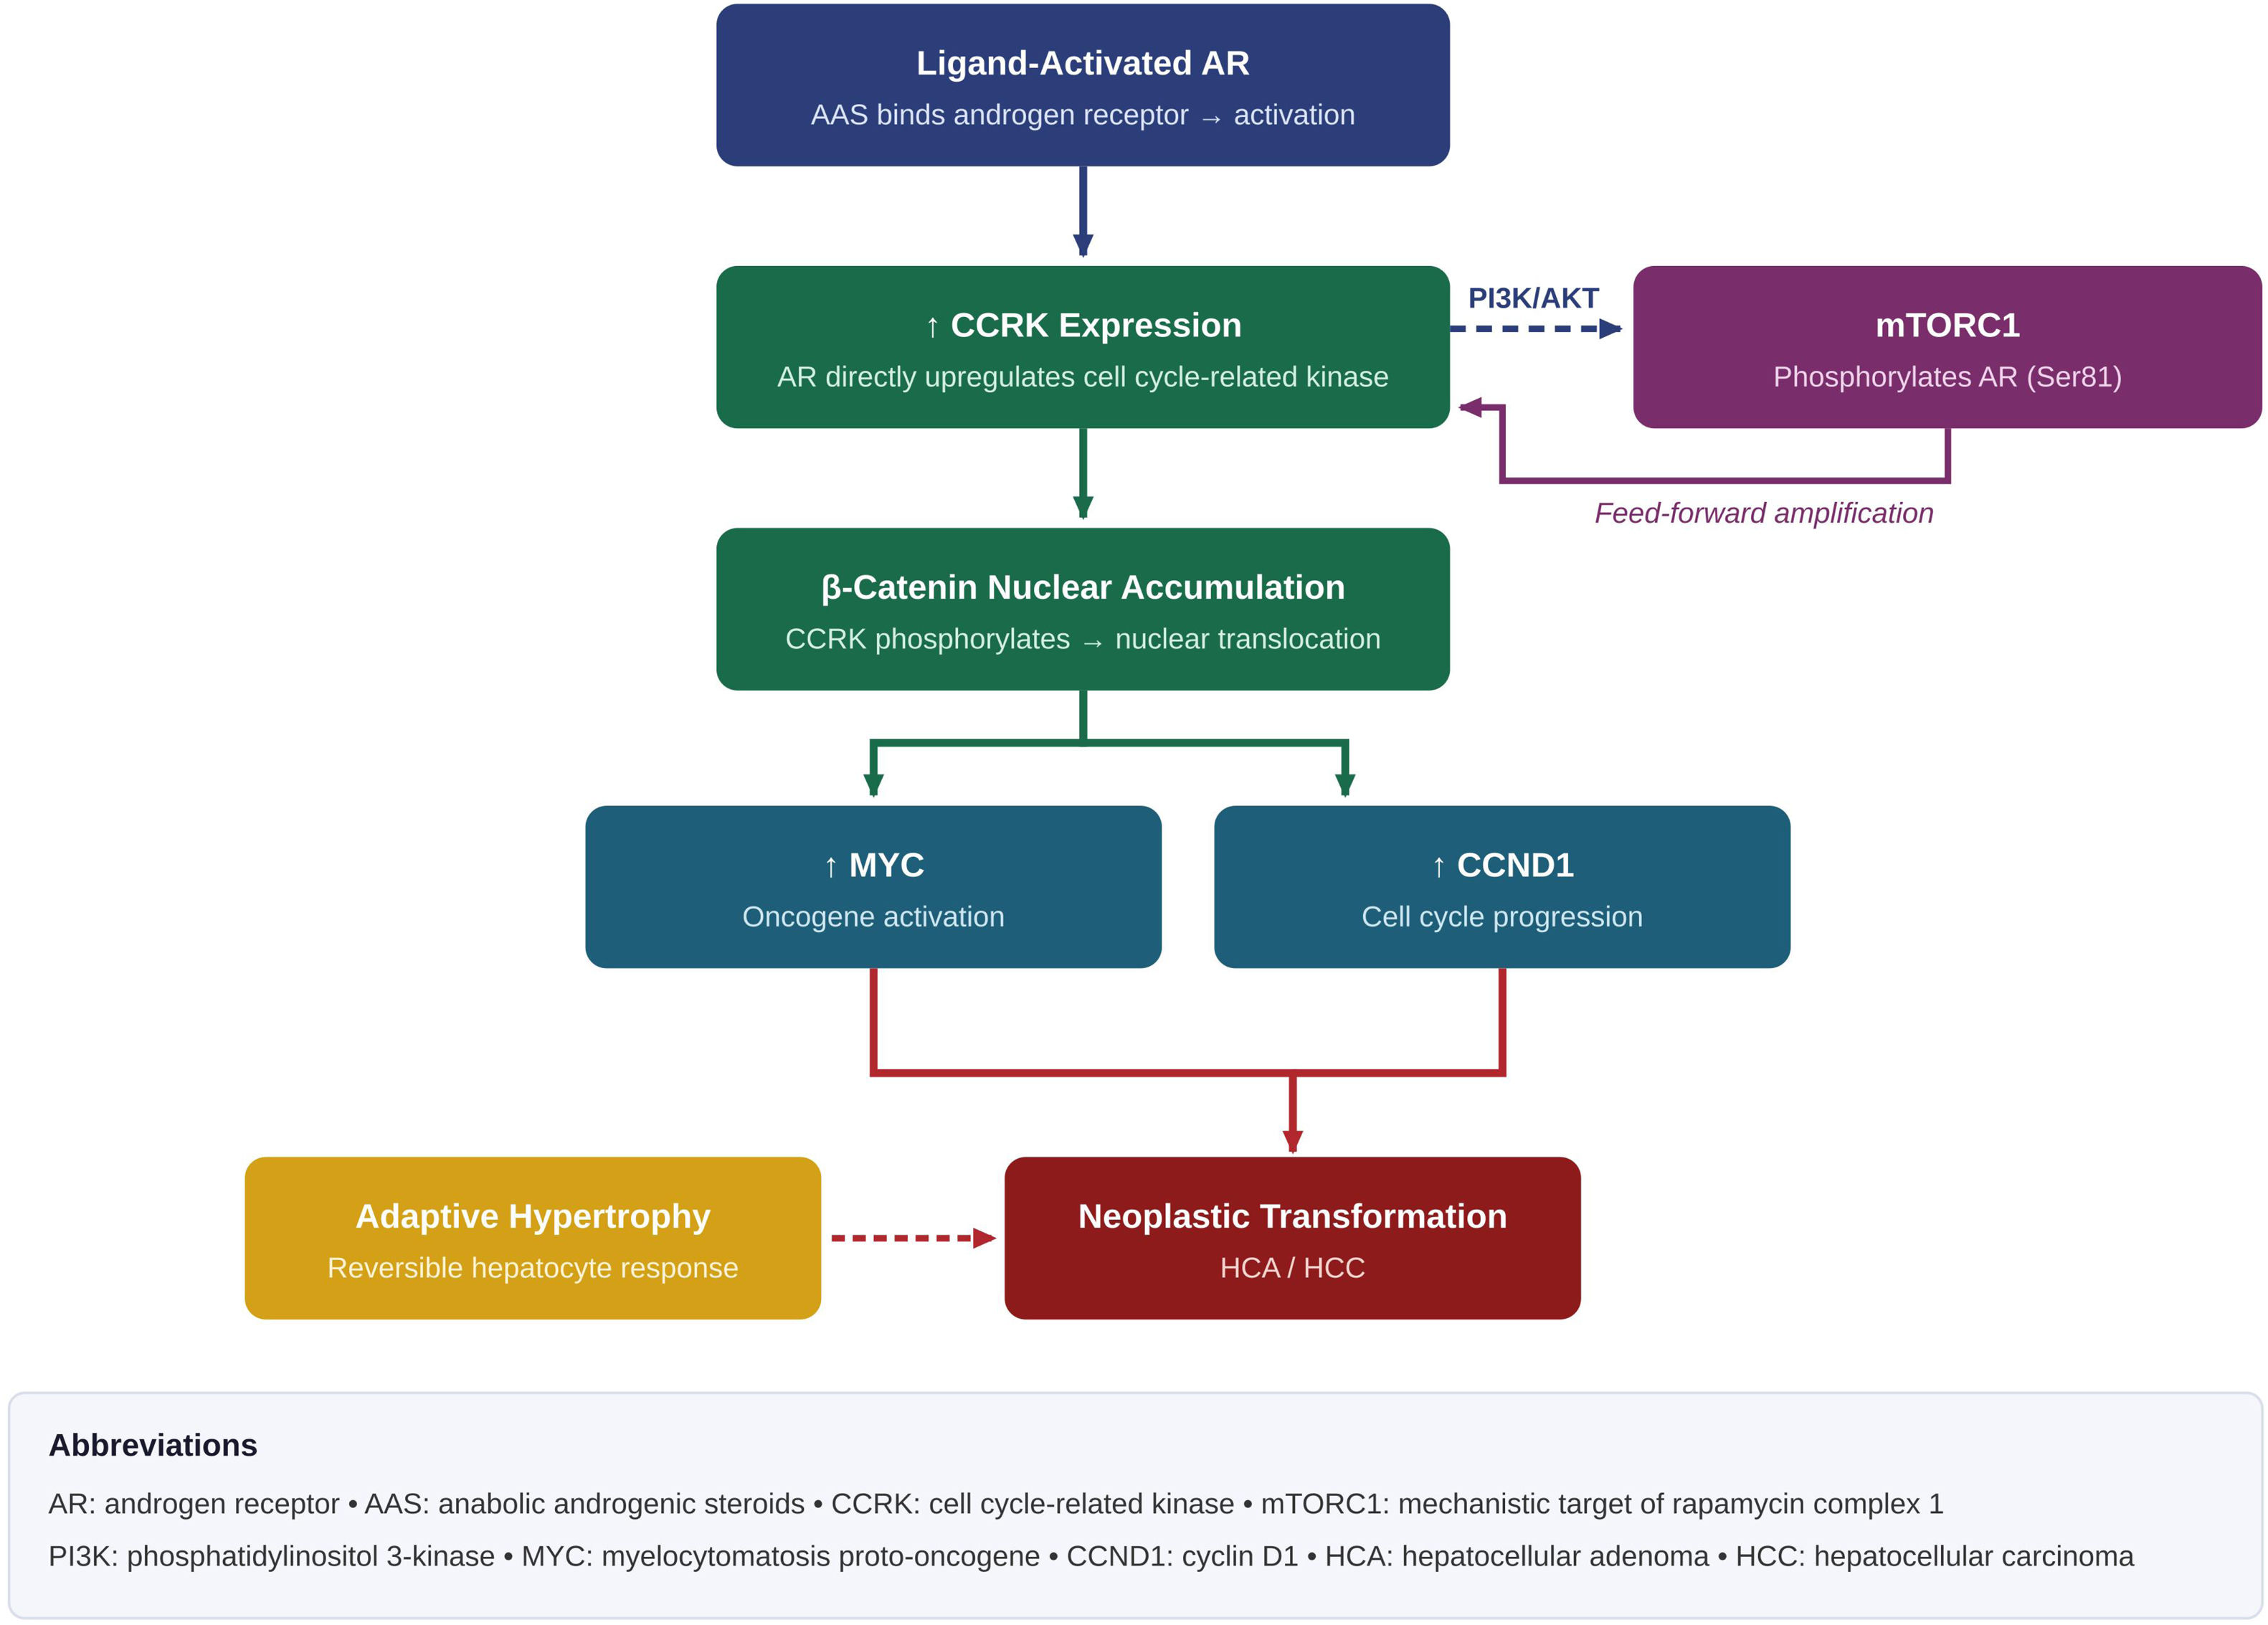
Two AR-driven pathways are of particular relevance for clinicians managing these patients. First, AR activation transcriptionally upregulates cell cycle-related kinase (CCRK), which promotes nuclear accumulation of β-catenin and activation of downstream proliferative targets including MYC and cyclin D1.14 Second, mTOR complex 1 (mTORC1)-mediated phosphorylation of AR stabilizes the receptor and enhances its transcriptional activity, creating a feed-forward loop that amplifies hepatocyte proliferation15,16; this interaction also represents a potential therapeutic target, as mTOR inhibitors have shown efficacy in experimental models.15,16 Viral hepatitis further modulates this process: the HBV X protein and HCV core protein both potentiate AR transcriptional activity through distinct mechanisms, offering a biologically coherent explanation for part of the male predominance observed in HCC epidemiology.9,17,18 These pathways are summarized in Figs. 1 and 2.

Schematic representation of molecular pathways linking anabolic androgenic steroid (AAS) exposure to liver tumorigenesis. Following androgen receptor (AR) activation, the AR-CCRK-β-catenin axis, the PI3K/AKT/mTORC1 pathway, and viral hepatitis-driven AR potentiation (HBx protein of HBV; core protein of HCV) collectively promote hepatocyte proliferation, genomic instability, and progression from hepatocellular adenoma (HCA) to hepatocellular carcinoma (HCC). AR: androgen receptor; AAS: anabolic androgenic steroids; CCRK: cell cycle-related kinase; HBV: hepatitis B virus; HCV: hepatitis C virus; mTORC1: mechanistic target of rapamycin complex 1; PI3K: phosphatidylinositol 3-kinase.

Schematic summary of the androgen receptor (AR)-driven proliferative signaling cascade in AAS-exposed hepatocytes. Ligand-activated AR upregulates CCRK expression, driving nuclear β-catenin accumulation and transcriptional activation of MYC and CCND1. Concurrently, mTORC1-mediated phosphorylation of AR creates a feed-forward amplification loop. These converging signals progressively shift the hepatocyte from adaptive hypertrophy toward neoplastic transformation. AR: androgen receptor; CCRK: cell cycle-related kinase; mTORC1: mechanistic target of rapamycin complex 1.
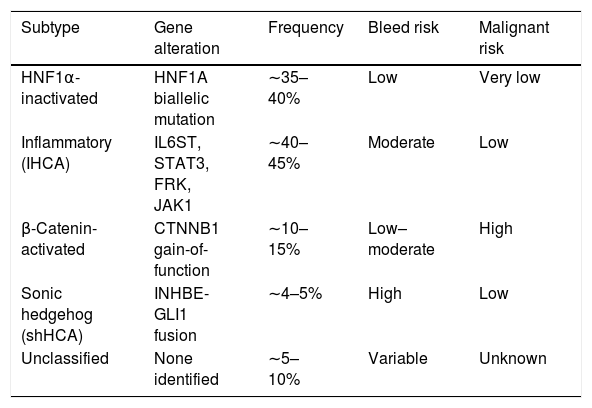
Hepatocellular adenoma is a rare benign liver tumor with a well-established hormonal component, classically associated with oral contraceptive use in women and, less commonly, with androgen exposure in men.19,20 Contemporary molecular classification distinguishes four principal subtypes—HNF1α-inactivated, inflammatory, β-catenin-activated, and sonic hedgehog adenomas—each with a distinct bleeding risk and potential for malignant transformation (Table 2).19,20 Of these, the β-catenin-activated subtype predominates in the androgen-exposed setting and carries the highest risk of malignant transformation.19,20
Molecular subtypes of hepatocellular adenoma (HCA) and their main clinicopathologic features.
| Subtype | Gene alteration | Frequency | Bleed risk | Malignant risk |
|---|---|---|---|---|
| HNF1α-inactivated | HNF1A biallelic mutation | ∼35–40% | Low | Very low |
| Inflammatory (IHCA) | IL6ST, STAT3, FRK, JAK1 | ∼40–45% | Moderate | Low |
| β-Catenin-activated | CTNNB1 gain-of-function | ∼10–15% | Low–moderate | High |
| Sonic hedgehog (shHCA) | INHBE-GLI1 fusion | ∼4–5% | High | Low |
| Unclassified | None identified | ∼5–10% | Variable | Unknown |
For the clinician, contrast-enhanced magnetic resonance imaging (MRI) with hepatobiliary contrast agents is the preferred non-invasive modality for subtype characterization, since signal intensity, enhancement pattern, and hepatobiliary phase retention correlate with the underlying molecular subtype and can often avoid the need for biopsy.21,22 Biopsy is not required in most cases when imaging findings are typical, given the bleeding risk inherent to sampling a hypervascular lesion; it should be reserved for atypical imaging features, diagnostic uncertainty between HCA and HCC, or situations in which subtype classification would directly change management.19,21,22 Contrast-enhanced ultrasound (CEUS) is a valuable alternative when MRI is not readily available: its real-time assessment of arterial-phase enhancement and portal/late-phase washout can help distinguish HCA from focal nodular hyperplasia and from HCC and avoids ionizing radiation, although its accuracy for HCA subtyping remains inferior to hepatobiliary MRI.21,22 Multiphase contrast-enhanced computed tomography (CT) is a reasonable alternative when neither MRI nor CEUS is available or feasible, providing adequate lesion detection and vascular characterization, albeit with less soft-tissue contrast and subtype discrimination than MRI21,22; in centers without access to hepatobiliary MRI, this stepwise reliance on ultrasound, CEUS, and CT should not delay referral to a center capable of definitive characterization whenever malignancy cannot be confidently excluded. Current EASL and AISF guidelines recommend individualized management based on lesion size, imaging subtype, patient sex, hormonal exposure history, and bleeding risk.23,24
Androgen-associated HCA warrants particular clinical attention because it may be multifocal (hepatocellular adenomatosis), may develop after prolonged or cumulative androgen exposure, and may coexist with other AAS-related hepatic findings such as peliosis hepatis.6,7,11 Importantly, discontinuation of AAS has been reported to lead to regression of hepatic adenomas, which is a key argument for exposure-focused counseling rather than surgery as first-line management in most cases.5,6
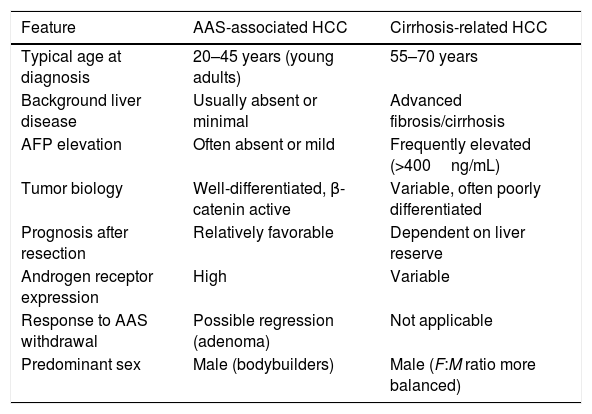
Hepatocellular carcinoma and malignant transformation: recognition in non-cirrhotic liverCurrent evidence primarily supports an association between long-term AAS exposure and HCC rather than a definitively established causal relationship, a distinction that is particularly relevant in patients with underlying hematologic disorders, in whom the disease itself or its treatment may independently contribute to hepatic carcinogenesis. With this caveat, the literature contains well-characterized cases in both patients receiving long-term therapeutic androgens for hematologic conditions (such as aplastic anemia and Fanconi anemia) and in bodybuilders using supraphysiological regimens.6,11 A defining clinical feature is that steroid-associated HCC frequently develops in non-cirrhotic livers, contrasting with the usual epidemiologic and pathophysiologic context of HCC, in which advanced chronic liver disease, cirrhosis, and portal hypertension are the dominant risk factors8–10 (Table 3). This is not, however, a feature unique to AAS exposure: HCC arising in non-cirrhotic liver is also well recognized in metabolic dysfunction-associated steatotic liver disease, fibrolamellar carcinoma, and, less commonly, chronic viral hepatitis without advanced fibrosis, and these entities should be kept in mind as part of the differential diagnosis.9
Comparative clinicopathologic features of AAS-associated versus cirrhosis-related hepatocellular carcinoma.
| Feature | AAS-associated HCC | Cirrhosis-related HCC |
|---|---|---|
| Typical age at diagnosis | 20–45 years (young adults) | 55–70 years |
| Background liver disease | Usually absent or minimal | Advanced fibrosis/cirrhosis |
| AFP elevation | Often absent or mild | Frequently elevated (>400ng/mL) |
| Tumor biology | Well-differentiated, β-catenin active | Variable, often poorly differentiated |
| Prognosis after resection | Relatively favorable | Dependent on liver reserve |
| Androgen receptor expression | High | Variable |
| Response to AAS withdrawal | Possible regression (adenoma) | Not applicable |
| Predominant sex | Male (bodybuilders) | Male (F:M ratio more balanced) |
AFP: alpha-fetoprotein; AAS: anabolic androgenic steroids; HCC: hepatocellular carcinoma. Features are based on published case series and review data.6,8,9,11,16 It should be noted that a substantial proportion of patients with HCC overall (up to approximately 30%) have normal AFP levels at diagnosis regardless of etiology, reinforcing that a normal AFP should not be used to exclude malignancy.9
The biological rationale for malignant transformation in the AAS context rests on persistent AR-β-catenin-mTOR proliferative signaling rather than on the classical fibrosis-driven carcinogenesis model.6,14,15 A clinically important pitfall is that serum alpha-fetoprotein (AFP) is not reliably elevated in steroid-associated HCC, so a normal value cannot be used to exclude malignant disease when imaging is suspicious or atypical.6
Malignant transformation within an androgen-associated adenoma can be subtle even on histological review, since β-catenin (CTNNB1) mutation is an early event in the adenoma-carcinoma sequence and additional alterations accompany the final transition to carcinoma.14,19,20 In practice, this means that any new or growing nodule within a known β-catenin-activated adenoma, particularly if imaging features are atypical, warrants prompt hepatology and multidisciplinary evaluation rather than reassurance based on the original benign diagnosis.13,14,19,20 Because established HCC surveillance protocols are designed for and targeted at patients with cirrhosis, a focal hepatic lesion in a young, non-cirrhotic AAS user should not be dismissed as benign purely on the basis of age or a normal AFP value.6,9 The AR-driven proliferative cascade in AAS-exposed hepatocytes is schematically represented in Fig. 2.
Differential diagnosis of suspected AAS-related liver injuryAs with any suspected drug-induced liver injury, a diagnosis of AAS-related hepatic pathology should not be reached by exclusion alone but should prompt systematic consideration of alternative or concomitant causes of liver disease. Viral hepatitis B and C, alcohol-related liver disease, metabolic dysfunction-associated steatotic liver disease, and other forms of drug- or supplement-induced liver injury (including concomitant use of stimulants, non-steroidal anti-inflammatory drugs, or other hepatotoxic supplements common among AAS users) should be actively screened for, since these conditions may coexist with androgen exposure and independently influence both the hepatic phenotype and its natural history.1,5,9 In patients with a known hematologic disorder receiving therapeutic androgens, the underlying disease process itself, prior chemotherapy, or transfusion-related iron overload should also be considered as potential contributors to liver injury or tumorigenesis, rather than attributing the entire clinical picture to AAS exposure by default.6,11
Clinical management, surveillance, and follow-upFor clinicians evaluating a patient with a suspected AAS-associated hepatic lesion, a structured approach is more useful than reliance on any single test (Table 4). A detailed and non-judgmental exposure history—covering AAS, prohormones, and supplements—is essential, since use is frequently underreported.1,2 This inquiry should be incorporated as a routine component of the standard evaluation of any patient with unexplained liver injury or a focal hepatic lesion, rather than reserved for cases in which AAS use is already suspected on clinical grounds. Liver biochemistry should be interpreted as a complete panel—including aminotransferases, bilirubin, alkaline phosphatase, and gamma-glutamyltransferase—alongside markers less influenced by resistance training, to avoid misattributing an abnormality to muscular exertion.5 Contrast-enhanced MRI remains the preferred imaging modality for lesion characterization and for distinguishing HCA subtypes from focal nodular hyperplasia and from HCC.21,22,25
Proposed stepwise diagnostic and clinical management algorithm for AAS-associated hepatic lesions.
| Step | Action | Rationale/Key points |
|---|---|---|
| 1 | Detailed exposure history | Systematically ask about AAS, prohormones, and supplement use as part of a thorough clinical history, since use is frequently underreported unless directly and specifically elicited1,2 |
| 2 | Liver biochemistry | Interpret the complete liver biochemical profile (aminotransferases, bilirubin, alkaline phosphatase, GGT) alongside skeletal muscle markers (CK, LDH) to distinguish hepatic from muscular origin and characterize the pattern of injury5 |
| 3 | Abdominal ultrasound | First-line imaging for detection of focal lesions; limited for subtype characterization |
| 4 | Contrast-enhanced MRI | Preferred modality for HCA subtype identification and differentiation from FNH; essential when lesion>2cm21,22,25 |
| 5 | AFP and liver panel | Recognize that normal AFP does not exclude malignancy in the AAS context6 |
| 6 | Multidisciplinary review | Involve hepatology, radiology, hepatobiliary surgery, and oncology for lesions>5cm, multiple adenomas, or suspicious features23,24 |
| 7 | AAS discontinuation | Strongly advise cessation of AAS use; this recommendation applies primarily to non-medical use, whereas therapeutic AAS should be reassessed by the prescribing specialist rather than discontinued unilaterally5,6 |
| 8 | Surveillance/biopsy | Individualize based on lesion size, imaging characteristics, and persistence after AAS withdrawal23–25 |
AAS: anabolic androgenic steroids; AFP: alpha-fetoprotein; CK: creatine kinase; FNH: focal nodular hyperplasia; HCA: hepatocellular adenoma; LDH: lactate dehydrogenase; MRI: magnetic resonance imaging.
HCA: hepatocellular adenoma; HCC: hepatocellular carcinoma; AR: androgen receptor; ACG: American College of Gastroenterology; EASL: European Association for the Study of the Liver.
AAS discontinuation should be strongly and explicitly recommended at diagnosis, both because it removes the driving proliferative stimulus and because it may lead to regression of hepatic adenomas.5,6 Follow-up imaging is reasonable to confirm regression or stability after cessation; persistence, growth, or the development of atypical features on interval imaging should prompt multidisciplinary discussion involving hepatology, radiology, and, where relevant, hepatobiliary surgery.23,24 Biopsy or resection should be considered for lesions with imaging features indeterminate between HCA and HCC, for lesions exceeding 5cm, for the β-catenin-activated subtype specifically given its malignant potential, or for any lesion that grows despite AAS cessation.16,23–25 Because this is a relatively rare and likely underrecognized entity, maintaining a low threshold to consider it in a young patient with a focal liver lesion—regardless of how atypical the exposure history may initially seem—is itself a clinically actionable message of this review.
ConclusionsAnabolic androgenic steroids should be regarded as a clinically relevant, if underrecognized, cause of primary liver tumors, particularly in young male patients who lack the conventional risk factors for hepatocellular disease. The mechanistic literature supports a model in which AR activation, β-catenin signaling, mTOR-mediated feedback, and, in some patients, viral hepatitis converge to drive hepatocyte proliferation and, in susceptible individuals, neoplastic transformation. The β-catenin-activated HCA subtype is of particular clinical importance given its heightened malignant potential and its association with androgen exposure.
For gastroenterologists, hepatologists, and internists, the practical message is straightforward: evaluation should begin with a comprehensive clinical history, within which a specific, structured, and non-judgmental inquiry about androgen and performance-enhancing drug use should be routinely incorporated when clinically appropriate, rather than reserved for cases in which such exposure is already suspected. This is particularly relevant for a focal liver lesion in a young, non-cirrhotic patient—especially one engaged in intensive resistance training—since this history is easily missed and a normal AFP does not exclude malignancy. Management should center on AAS cessation, appropriate imaging follow-up, and a low threshold for multidisciplinary referral when lesions are large, atypical, or growing. Greater clinical awareness of this entity may shorten the time to diagnosis and help avoid both under- and over-treatment in a patient population that is often otherwise healthy.
CRediT authorship statementEnrico Fulco: Conceptualization, Investigation, Methodology, Writing – original draft, Writing – review & editing, Visualization. Alessia Stingo: Writing – original draft. Giancarlo Orlando: Writing – original draft. All authors read and approved the final manuscript.
Ethical considerationsNot applicable. This manuscript is a narrative review of previously published literature and did not involve human participants, animal subjects, identifiable patient data, or original clinical images. Consequently, no ethics committee approval or informed consent for participation was required or obtained.
FundingThis research received no specific grant from any funding agency in the public, commercial, or not-for-profit sectors.
Conflict of interestsThe authors declare no competing interests.
Data availability statementNo data was used for the research described in this article.




