


Measles, a highly contagious airborne disease, has seen a resurgence in Spain despite the successful implementation of vaccination programs. This study examines two cases of vaccine-associated measles in children attending the same nursery school, both of whom received the measles–mumps–rubella vaccine.
MethodsRetrospective descriptive study of two children with vaccine-associated measles in May 2025 on the island of Gran Canaria (Spain).
ResultsThe first case involved a 12-month-old girl who developed symptoms six days post-vaccination, while the second case, a 13-month-old boy, exhibited symptoms eight days after receiving the vaccine. Both cases were confirmed as genotype A, indicating the vaccine strain. The investigation included extensive contact tracing, identifying 107 close contacts, with vaccinations administered to susceptible individuals. Laboratory tests confirmed measles through polymerase chain reaction (PCR) analysis. The findings highlight the rarity of clinically significant vaccine-associated disease and the absence of evidence for human-to-human transmission of the vaccine strain.
ConclusionThis study underscores the importance of genotyping in distinguishing between vaccine-associated rash illness and wild-type measles, as well as the need for continued vigilance in monitoring vaccine efficacy and outbreak responses. Ultimately, while the possibility of transmission cannot be entirely dismissed, the evidence suggests that these cases are more likely coincidental rather than a result of transmission.
El sarampión, una enfermedad altamente contagiosa transmitida por vía aérea, ha resurgido en España a pesar del éxito de los programas de vacunación. Este estudio examina dos casos de sarampión vacunal en niños de la misma guardería vacunados con triple vírica (sarampión, rubeola, parotiditis).
MétodosEstudio descriptivo retrospectivo de dos niños con sarampión vacunal en mayo de 2025 en Gran Canaria (España).
ResultadosEl primer caso fue una niña de 12 meses que presentó síntomas seis días después de la vacunación, mientras que el segundo caso, un niño de 13 meses, presentó síntomas ocho días después de la vacuna. Se confirmó el genotipo A, cepa vacunal, en ambos. Se identificaron 107 contactos cercanos y se administró la vacuna a las personas susceptibles. Se confirmó el sarampión mediante reacción en cadena de la polimerasa (PCR). Los hallazgos destacan la rareza de la enfermedad clínicamente significativa asociada a la vacuna y la falta de evidencia de transmisión de persona a persona de la cepa vacunal.
ConclusiónEste estudio subraya la importancia de la genotipificación para distinguir entre el sarampión vacunal y de tipo salvaje, así como la necesidad de una vigilancia continua para monitorizar la eficacia de la vacuna y la respuesta a los brotes. Si bien no se puede descartar por completo la posibilidad de transmisión, la evidencia sugiere que es más probable que estos casos sean casuales que una transmisión entre ellos.
Measles is a highly contagious airborne disease that can lead to severe complications, including pneumonia, acute encephalitis, and even death. However, the implementation of vaccination programs has resulted in a significant decrease in both incidence and mortality rates.1 Against measles, one dose of MMR is 93% effective and two doses are 97% effective.2 In Spain, the measles vaccine was incorporated into the national vaccination schedule in 1977. Following a series of modifications over the years, the current schedule was established in 2012, with the first dose of measles–mumps–rubella (MMR) administered at 12 months of age and the second dose given between 3 and 4 years of age.3
As a result, the World Health Organization (WHO) declared Spain free of endemic measles transmission in 2017. However, cases and outbreaks have been reported in Spain since 2023, increasing throughout 2024 and 2025.4 In the Canary Islands, no cases were identified between 2020 and 2023. One outbreak and three isolated imported cases were reported in 2024,5 and two more isolated cases in 2025.
Clinically significant vaccine-associated disease is rare and, when it occurs, is indistinguishable from wild measles.6 In contrast with the wild form of the disease, there is no evidence of vaccine-associated human-to-human transmission of measles.7
In this study, we present two cases of measles in two children who attended the same nursery school and received the measles vaccine.
MethodsRetrospective descriptive study of two children with vaccine-associated measles in May 2025 on the island of Gran Canaria (Spain). The definition of the national surveillance protocol was used to identify measles cases8: person with fever (body temperature above 38°C) and maculopapular rash with at least one of these three symptoms: cough; rhinitis/runny nose; conjunctivitis; or person with a history of having received two doses of measles vaccine who presents fever and rash, but does not present cough, rhinitis/runny nose, or conjunctivitis.
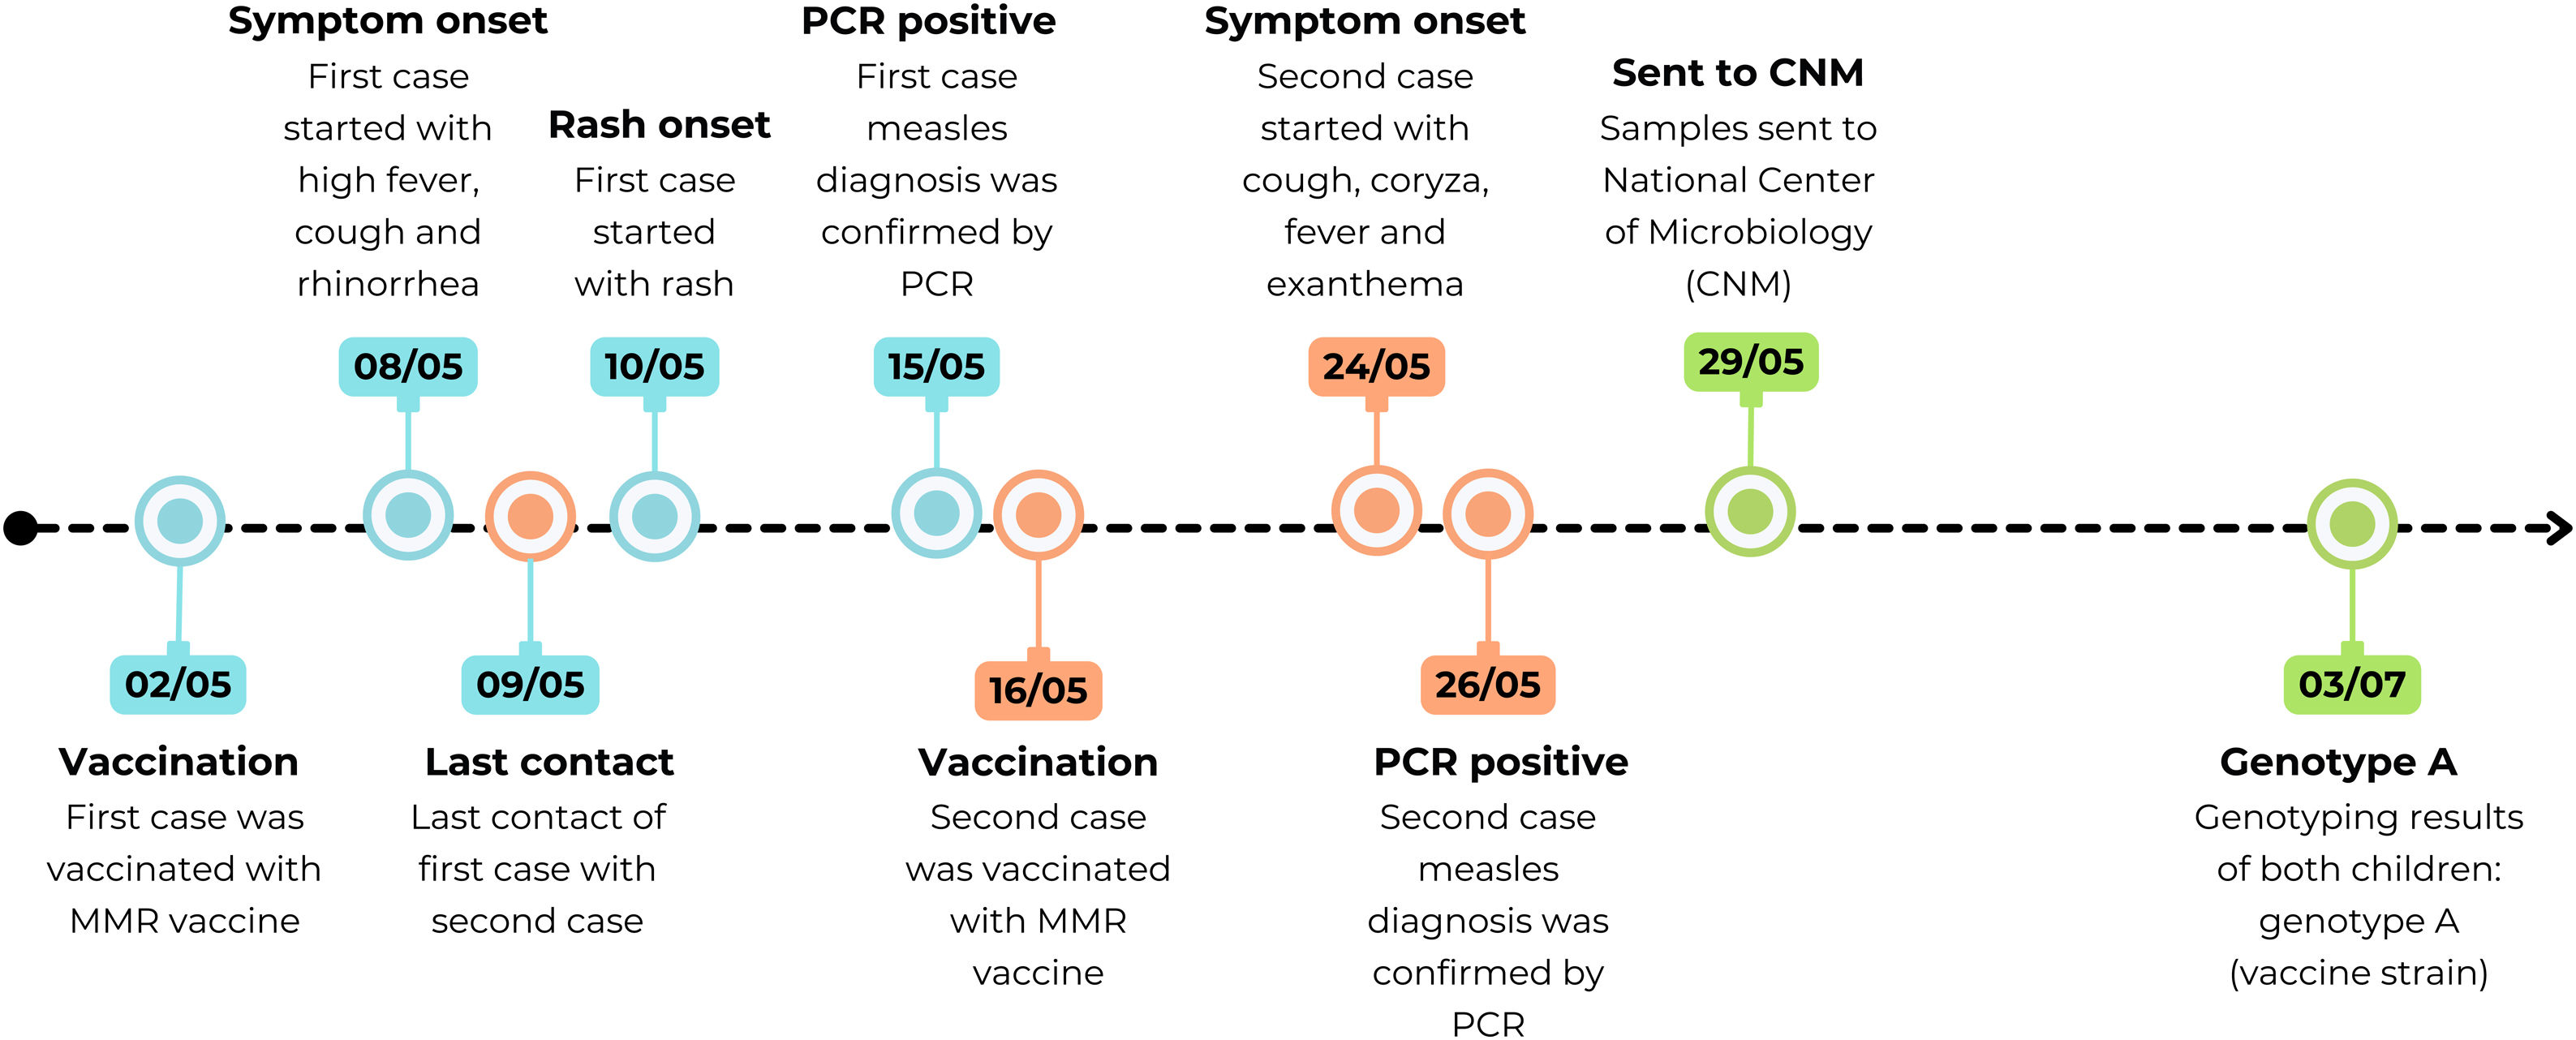
ResultsCases description (Fig. 1)The initial case involved a 12-month-old female patient who received the vaccination on May 2nd. On May 8, the patient exhibited symptoms including high fever, cough, and rhinorrhea. On May 10th, she exhibited a pruritic rash in the retroauricular region that progressed craniocaudally. On May 13, the patient was admitted to the emergency room of a local hospital, where her symptoms were documented as including erythematous papular exanthema with perilesional hypochromic halo, cervical and oropharyngeal hyperemic lymphadenopathy, and aphthous ulcers in the tonsillar pillars.

The second case was that of an unvaccinated 13-month-old boy who was considered to be a close contact of the first case, who was a student at the same nursery school. The date of the last documented contact with the case was May 9. Public health recommended the administration of a vaccination, which was carried out on May 16 (the same batch was used as for the index case). The onset of symptoms occurred 8 days after the administration of the vaccine, manifesting as cough, coryza, fever, and exanthema. The patient sought treatment at the hospital's emergency room (ER), where samples were taken.
Contact tracing and public health measuresFist case contact tracingThe nursery school was contacted to identify close contacts: 7 classroom contacts, 11 nursery school contacts (dining room and early and late reception activities) and 2 caregivers. Two children aged 11 months and 13 months, respectively, had not received the recommended vaccinations. The public health department recommended and arranged for the vaccination of the contacts, as well as three adult family members of the case.
A total of 64 close contacts were identified on May 6 and May 13, including 29 individuals who were identified in the hospital emergency room and waiting room, and 35 individuals who were identified at the healthcare center. For the hospital contacts, vaccination was recommended for two children aged 20 and 7 months, and for the close contacts at the health center, vaccination was proposed to an unvaccinated child aged 13 months. A message was disseminated to close contacts who were not susceptible to vaccination, i.e., those who had received two doses of the vaccine or were below the age of vaccination. The message emphasized the importance of active surveillance for symptoms over a 21-day period and the protocol to be followed in the event of symptoms manifesting.
Second case contact tracingA total of 23 close contacts were identified from the hospital ER waiting room (all of whom were minors). Of these 23 individuals, 20 were found to be adequately vaccinated according to their age, 2 were not vaccinated due to their age (5 days and 5 months, respectively), and 2 were tourist children whose vaccination schedules were not documented. Informative messages were disseminated to all close contacts, providing them with the hygienic measures to be followed for the 21 days following the last contact. In the nursery school, six close contacts were identified, coinciding with those of the first case.
As a result of the contact tracing process for both cases, a total of 107 close contacts were identified, and vaccination was administered to 10 individuals.
Laboratory investigationsThe first patient underwent a polymerase chain reaction (PCR) test on May 14 for the purpose of diagnosis. On May 15, the result of the PCR form measles in the patient's second urine sample and nasopharyngeal exudate sample. Molecular detection was negative for atypical bacteria (Bordetella pertussis, Bordetella parapertussis, Chlamydia pneumoniae, Mycoplasma pneumoniae) and respiratory viruses (influenza A virus, influenza B virus, respiratory syncytial virus and SARS-CoV-2) The specimen was subsequently dispatched to the National Center of Microbiology (CNM) on May 19, and a positive result for PCR test for measles was obtained on May 23.
The second child underwent a PCR test on May 26, yielding positive results in the pharyngeal exudate but negative in the urine sample. The specimen was dispatched to the CNM on May 29, and a positive result was received on June 4. The PCR result in both cases was negative for Parvovirus B19 and rubella virus.
The genotyping results of both children were obtained on July 3, and genotype A (vaccine strain) was confirmed in both cases.
DiscussionWe present a case of a child who exhibited measles symptoms six days after receiving the MMR vaccine, and the presentation of the same symptoms in another child attending the same nursery school, at 8 days after being vaccinated, and 15 days after being in contact with the first case during his contagious period. In most cases, the development of symptoms occurs within two weeks of vaccination.2,9 However, cases with longer incubation period have been documented.6 In our study, symptoms were observed in both children eight days after they received the vaccine. This timeframe is consistent with the possibility of post-vaccination viremia, which typically occurs five to 12 days after injection.
While the majority of cases of vaccine-associated measles have been reported in children or immunocompromised individuals, there have also been reports of cases in healthy adults.10,11 In the present case, the occurrence was identified in two immunocompetent children aged 12 and 13 months, respectively. Approximately 5% of children may experience low-grade fever or a mild rash following measles vaccination.12 Research indicates that symptoms associated with the common cold, such as cough, coryza, and conjunctivitis, are observed less frequently in VARI cases.2,13,14 However, the presence of these symptoms alone is not sufficient to rule out VARI, as some authors have described, and as was observed in the present case, where both children had.12 Similarly, even if symptoms are present one week after vaccination and there are no sick close contacts, tests should be performed to confirm vaccine-associated measles. Pending the arrival of genotyping results, cases must be managed as wild-type.2,6,15 Given the children's numerous interactions with healthcare center and nursery school personnel, their immunological status was examined, and susceptible contacts were vaccinated. No further cases were documented among individuals who received the same batch of vaccine, nor among the close contacts of the two children. Although no further samples were tested from the other children who were vaccinated with the same batch, no cases with symptoms were reported among them.
Genotyping results indicated that both children had genotype A (vaccine strain). Both children received the same batch of vaccine at the same healthcare facility. No further cases were reported among people who had received the same batch of the vaccine.
Conversely, given that a 15-day period had elapsed since the second child's last interaction with the index case before the onset of symptoms, it is conceivable that transmission had occurred. The second child received the vaccination seven days after the last contact with the index case. It is important to note that a measles-containing vaccine has been demonstrated to be ineffective in providing protection following exposure after 72h.16 Consequently, the protective role of the vaccine in this particular case would be rendered null.
To the best of our knowledge, the only documented instance of vaccine-associated measles transmission was reported by Millson in 1989. In this study, Millson observed an apparent case of measles transmission between a 4-year-old male child who had recently received the MMR vaccine and his 8-month-old sister who had not received the vaccine.17 In response to this letter, it was recalled that experience with measles vaccine and MMR vaccine has not shown evidence of vaccine virus transmission.18 Subsequent literature on the subject has largely concurred that contact-tracing or emergency vaccination is not necessary in cases of vaccine-associated measles.9 A multitude of studies have documented cases of vaccine-associated measles, wherein, despite a high probability of exposure, no subsequent cases of measles were identified.19 Kaic et al., describe the excretion of the Schwarz strain (genotype A) of the measles vaccine in a child who developed a febrile rash illness eight days after primary immunization with MMR.20 Although live attenuated vaccines are not generally regarded as being infectious, Churchill et al. also posit a theoretical risk of viral shedding and potential transmission, particularly among susceptible immunocompromised contacts.11,15
Notably, cases of vaccine-associated mumps have been documented subsequent to transmission to close contacts of children who had received primary vaccination with this MMR vaccine in Croatia, where the mumps virus (vaccine strain L-Zagreb) was isolated from the salivary gland duct swab of the mother of the index case.21,22 This led Hau et al. to suggest that transmission of vaccine-associated measles could be theoretically possible.15
The vaccine-associated cases published in the literature mostly refer to vaccination with MMR (a mixture of three attenuated viral components). However, other cases have been reported in Japan associated with the measles–rubella (MR) vaccine9 and measles vaccine (without rubella or mumps).10 Regarding the two published cases of vaccine-associated measles transmission, one case referred to vaccination with a live attenuated MMR vaccine containing the Schwartz strain,17 and the other with the Edmonston-Zagreb strain.21
Regarding rubella, there have been no reported cases of vaccinia virus transmission with RA 27/3 rubella strains.23,24 In 1971, Wilkins described the transmission of HPV-77-derived rubella vaccine virus from vaccinated persons to two susceptible contacts. While neither of these individuals exhibited clinical symptoms of rubella, an increase in rubella hemagglutination-inhibiting (HI) antibody titers was observed.25 Two other studies reported the possibility of HPV-80 vaccines shedding the virus.26,27 In one of the studies, subjects who were susceptible to placebo were exposed to siblings with evidence of infection with the vaccine strain of rubella virus (HPV80). One of the subjects had an increased titer of HI antibodies.26 In the Wilkins et al. study, no spread of HPV-77 vaccine was observed to any susceptible contacts. However, serologic evidence of vaccine virus spread was detected in one of the contacts of HPV-80 vaccinees.
ConclusionTwo children enrolled in the same daycare facility were diagnosed with vaccine-associated measles (genotype A) two weeks apart. The onset of the disease occurred six and eight days, respectively, after administration of the same batch of vaccine. While the likelihood of vaccine-associated measles is a very rare event, the probability of two coincident cases is higher than the probability of transmission from one child to another. Nevertheless, it is not possible to definitively rule out the possibility of transmission.
CRediT authorship contribution statementAll authors have made substantial contributions to all of the following:
- (1)
Conception and design of the study: Ana Hernandez-Aceituno, Álvaro Torres Lana, Eneko Larumbe-Zabala. Acquisition of data: Diana Sanabria Curbelo, Isabel Falcón García, Roque Abián Montesdeoca Melián. Analysis and interpretation of data: Ana Hernandez-Aceituno, Álvaro Torres Lana, Eneko Larumbe-Zabala.
- (2)
Drafting the article or revising it critically for important intellectual content: all authors.
- (3)
Final approval of the version to be submitted: all authors.
Not necessary (routine surveillance).
Informed consentNot necessary (routine surveillance).
Declaration of generative AI and AI-assisted technologies in the writing processNo.
FundingThis research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors.
Declaration of competing interestsThe authors report there are no competing interests to declare.
Data availabilityNot applicable.
We would like to express our gratitude to the Hospital and Primary Care professionals of Gran Canaria, without whom this work would not have been possible. In particular, we would like to thank the Microbiology Department, Rosa Pedraza, María Aroca, and Carmen Piña; the Preventive Medicine Department, especially Eva Álvarez; and the Pediatric Emergency Room Department of the Complejo Hospitalario Materno-Insular de Gran Canaria. We would also like to thank the Occupational Risk Prevention Department of both Primary Care and the hospital. Finally, we would like to thank the nursery school caregivers and the children's families for their constant cooperation.



