


Human parvovirus B19 (PVB19) is associated with diverse clinical manifestations. While acute infection in immunocompetent adults is generally considered mild, recent European outbreaks and an increase in severe cases highlight the need to always keep this virus in mind. This study aimed to describe the clinical and epidemiological features of acute PVB19 infection in immunocompetent adults requiring hospital care.
MethodsWe conducted a retrospective study of immunocompetent patients over 14 years old diagnosed with acute PVB19 infection at a Gran Canaria tertiary hospital (2014–2024). Diagnosis was based on detection of viral DNA and/or specific IgM.
ResultsForty-three patients were included (mean age 40.6±13.9 years; 44.2% male). A marked increase in cases was observed in 2024 (51.2% of total). Clinical manifestations included acute polyarthritis (37.2%), cardiac involvement (34.9%), erythema (16.3%), fever of unknown origin, meningitis, and gastrointestinal symptoms. Cardiac involvement, mostly in males, included dilated cardiomyopathy, pericarditis, and myocarditis, and was associated with two deaths. Hematological abnormalities were frequent (up to 80% in cardiac patients). Two additional patients developed systemic inflammatory diseases. Serological testing alone failed to confirm diagnosis in several cases, needing molecular testing of alternative samples.
ConclusionsOur findings underscore the diverse and potentially severe presentation of PVB19 infection in immunocompetent adults. The high incidence of cardiac involvement and diagnostic challenges highlight the need for enhanced surveillance and clinical awareness. Incorporating PVB19 into differential diagnoses for hospitalized patients with unexplained inflammatory or hematological syndromes may improve timely recognition and management.
El parvovirus B19 humano (PVB19) se asocia con diversas manifestaciones clínicas. Aunque la infección aguda en adultos inmunocompetentes se considera leve, los brotes recientes en Europa y el aumento de los casos graves hacen necesario tener siempre presente este virus. Este estudio tuvo como objetivo describir las características clínico-epidemiológicas de la infección aguda por PVB19 en adultos inmunocompetentes que requirieron atención hospitalaria.
MétodosEstudio retrospectivo de pacientes inmunocompetentes >14 años diagnosticados de infección por PVB19 en un hospital de Gran Canaria (2014–2024). El diagnóstico se basó en la detección del ADN viral y/o en la presencia de IgM específica.
ResultadosSe incluyeron 43 pacientes (edad media: 40,6±13,9 años; 44,2% hombres). Se observó un aumento de los casos en 2024 (51,2% del total). Las manifestaciones clínicas incluyeron poliartritis (37,2%), afectación cardíaca (34,9%), eritema (16,3%), fiebre de origen desconocido, meningitis y síntomas gastrointestinales. La afectación cardíaca incluyó miocardiopatía dilatada, pericarditis y miocarditis, con dos fallecimientos. Las alteraciones hematológicas fueron frecuentes (80% de los pacientes con afectación cardíaca). Dos pacientes desarrollaron enfermedades inflamatorias sistémicas. Las pruebas serológicas no permitieron confirmar el diagnóstico en varios casos, lo que hizo necesario recurrir a pruebas moleculares.
ConclusionesNuestros hallazgos subrayan la presentación diversa y potencialmente grave de la infección por PVB19 en adultos inmunocompetentes. La alta incidencia de afectación cardíaca y las dificultades diagnósticas resaltan la necesidad de una vigilancia y mayor conciencia clínica. Incluir al PVB19 en los diagnósticos diferenciales de pacientes con síndromes inflamatorios o hematológicos puede mejorar el reconocimiento y el manejo.
Human parvovirus B19 (PVB19) is a virus that causes a wide range of clinical manifestations, from asymptomatic infections to potentially life-threatening conditions.1 The most common clinical presentation is erythema infectiosum in children, while the most severe forms primarily occur in patients with underlying hematological diseases and immunocompromised individuals, in whom it often triggers transient aplastic crisis and chronic anemia due to its tropism for erythroid precursors in the bone marrow.2 Additionally, in pregnant women, transplacental infection can lead to fetal hydrops and intrauterine death.3 However, the impact of PVB19 is not limited to the hematopoietic system, as it is known to cause small joint arthritis, neurological disorders, kidney damage, and, in the most severe cases, cardiac involvement.4–6 Furthermore, it can mimic certain autoimmune diseases, such as lupus.7,8
PVB19 infection is not a notifiable disease. Although it has historically caused epidemic outbreaks every 3–5 years,9 an unusual increase in cases has been observed in Europe in 2024,10–12 possibly due to reduced exposure resulting from decreased virus circulation during pandemic-related restrictions, leading to a more susceptible population with lower immunity. In response to this increase in cases and the lack of routine surveillance for this virus, the European Centre for Disease Prevention and Control (ECDC) has issued an alert and urged enhanced surveillance to assess the impact of the outbreak,13 compared to pre-pandemic periods.
In immunocompetent adults, acute infection is usually mild or asymptomatic. However, it can also present with a broad and nonspecific clinical spectrum, making it difficult to differentiate from other infectious or autoimmune diseases, often posing a diagnostic challenge.14 Moreover, since 2020, an increase in severe and fatal cases among young adults and adolescents has been reported,15 generating greater interest in this population group. Additionally, while serological diagnosis is a useful tool, it does not always confirm acute infection; therefore, molecular techniques are needed to detect viral DNA in samples such as biopsies and bone marrow, which may not always be readily available.16
Despite its clinical relevance, PVB19 infection in immunocompetent adults has been less studied compared to other population groups. Therefore, this study aims to describe the clinical and epidemiological features of acute PVB19 infection in immunocompetent adults who required hospital care in our setting between 2014 and 2024, as well as to compare the magnitude of cases before and after the COVID-19 pandemic.
Patients and methodsA retrospective, descriptive study was conducted including all immunocompetent adults over 14 years old who were treated at a tertiary care hospital on the island of Gran Canaria (assigned population: 350,000 people) and diagnosed with acute PVB19 infection from January 1, 2014 to December 31, 2024. The immunocompetent status was defined as the absence of underlying immunosuppressive conditions, no history of immunosuppresive therapy, and normal lymphocyte counts.
The variables collected from medical records included the year of diagnosis, age, gender, medical history, clinical presentation, laboratory abnormalities (presence of anemia, leukopenia, thrombocytopenia, biochemical alterations), microbiological diagnosis, treatment, and clinical outcomes.
The diagnosis of PVB19 infection was established through detection of viral DNA in serum or plasma, bone marrow, pericardial fluid, endomyocardial biopsy and/or cerebrospinal fluid (CSF) using nucleic acid amplification test (NAAT). Until September 2018, qualitative NAAT was performed using the LightMix™ Parvovirus B19E kit (TIB-MOLBIOL) following DNA extraction with the EasyMag™ system (BioMérieux). From that date onward, quantitative NAAT was performed using the Parvovirus B-19 ELITe MGB™ system (ELITech Group Molecular Diagnostic). The analytical sensitivity of both techniques (qualitative and quantitative) was comparable; however, the qualitative assay did not allow for the determination of viral load levels (low versus high). Additionally, specific IgG and IgM detection was carried out using indirect immunofluorescence (Biotrin) or chemiluminescence (Parvovirus VIRCLIA™ IgM Monotest and Parvovirus VIRCLIA™ IgG Monotest – Vircell).
Categorical variables are presented as absolute numbers and percentages, whereas continuous variables are presented as means and standard deviations (SD). The study was approved by the Hospital Ethics Committee (CEIm Code 2025-110-1).
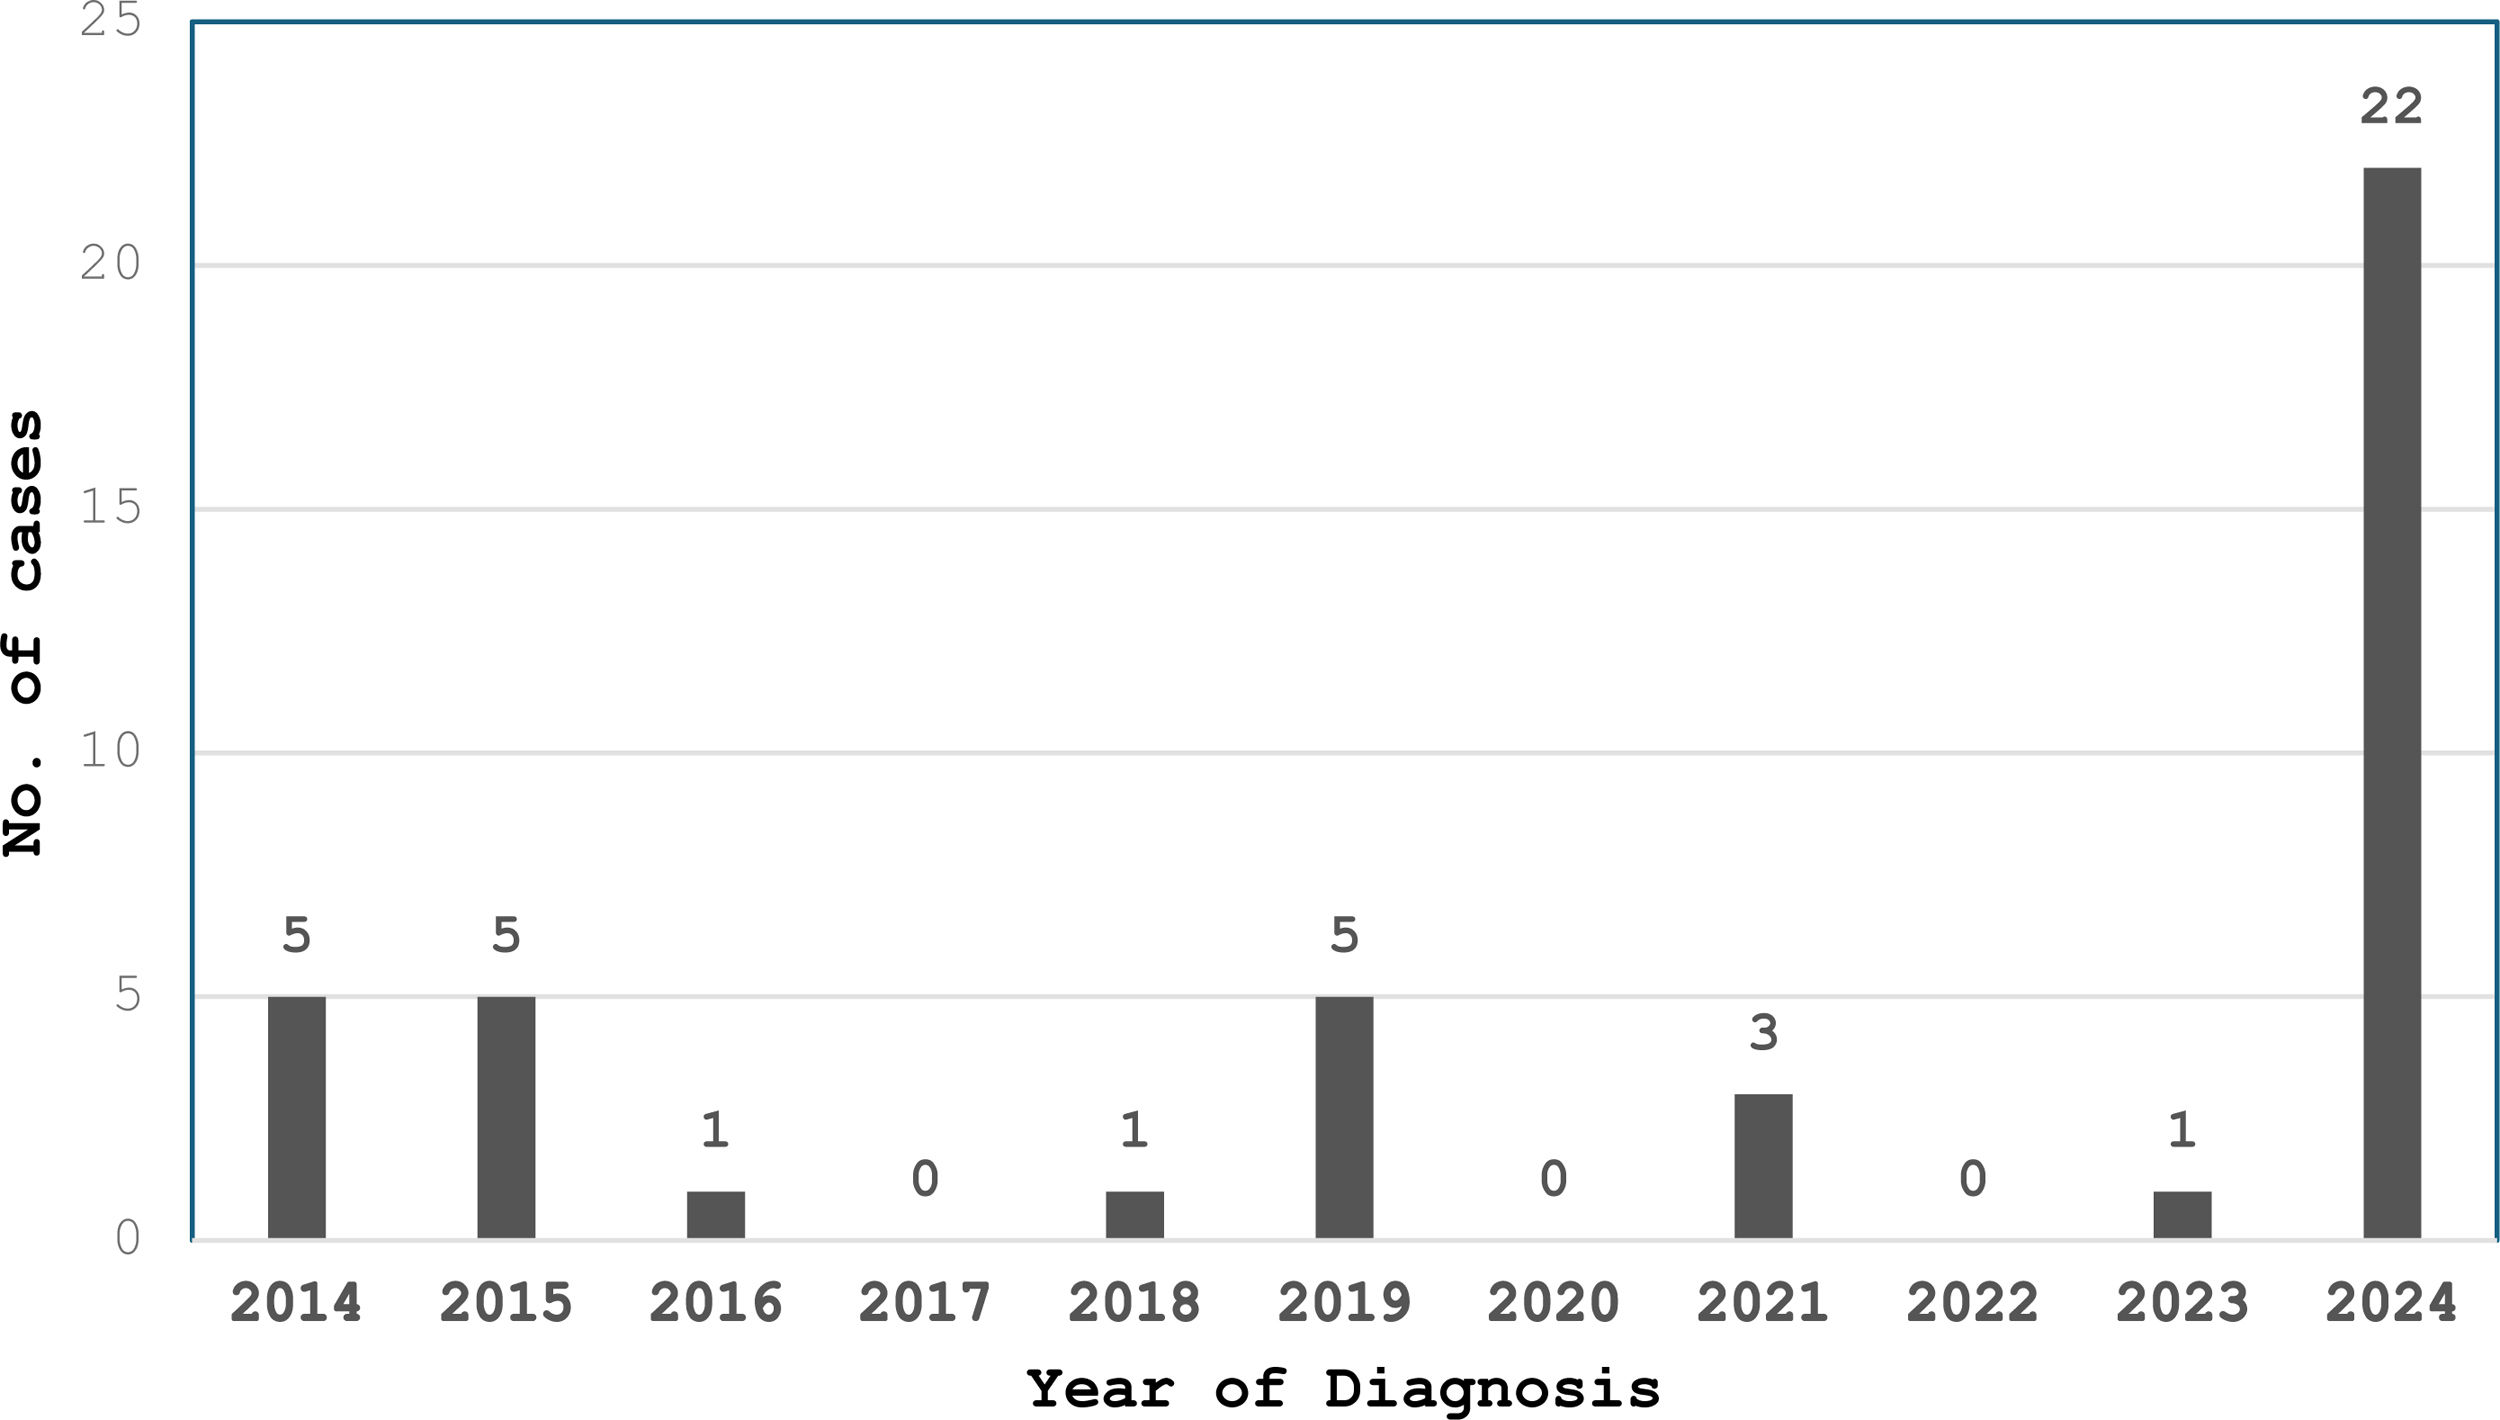
ResultsA total of 43 patients were included, with a mean age of 40.6±13.9 years (range: 15–74), of whom 19 (44.2%) were men. Fig. 1 presents the number of patients diagnosed per year, with 51.2% of cases occurring in 2024.

The clinical presentation when patients attended the consult included acute polyarthritis affecting small joints of the hands, wrist, knees, and feet in 16 patients (37.2%, 95% CI: 24.4–52.1), cardiac involvement in 15 (34.9%, 95% CI: 22.4–49.8), erythema in 7 (16.3%, 95% CI: 8.1–30.0), fever of unknown origin in 3 (7.0%, 95% CI: 2.4–18.6), meningitis in 1 (2.3%, 95% CI: 0.4–12.1), and digestive manifestations in 1 (2.3%, 95% CI: 0.4–12.1).
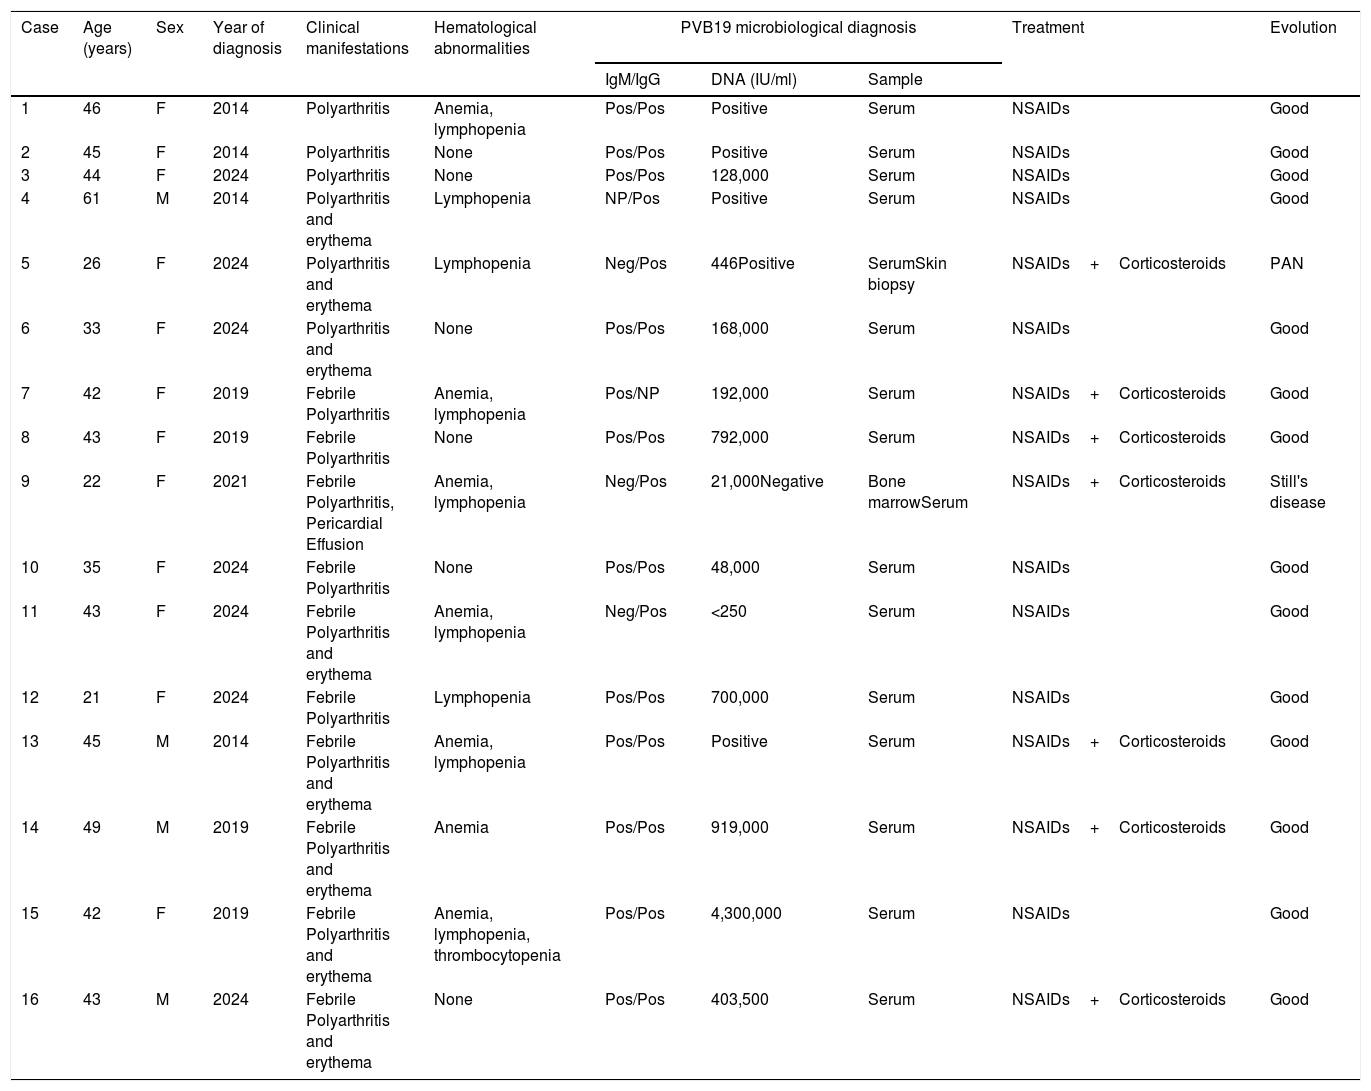
Table 1 details the clinical characteristics of the 16 patients who presented with acute polyarthritis. Twelve (75%) were women, with a mean age of 40.0±7.8 years. Fever was present in 62.5% of cases, erythema in 50.0%, and hematologic abnormalities in 62.5%, mainly lymphopenia and transient normocytic anemia. All patients received nonsteroidal anti-inflammatory drugs (NSAIDs) and glucocorticoids were administered in 43.7% of cases, with favorable outcome. However, two patients (12.5%) developed specific rheumatic diseases: one developed Still's disease, and another experienced cutaneous polyarteritis nodosa. In three patients, IgM was negative, and viral load in serum was low or undetectable (in patient 9, viral DNA detection was negative in serum but positive in bone marrow).
Clinical characteristics of patients with acute polyarthritis.
| Case | Age (years) | Sex | Year of diagnosis | Clinical manifestations | Hematological abnormalities | PVB19 microbiological diagnosis | Treatment | Evolution | ||
|---|---|---|---|---|---|---|---|---|---|---|
| IgM/IgG | DNA (IU/ml) | Sample | ||||||||
| 1 | 46 | F | 2014 | Polyarthritis | Anemia, lymphopenia | Pos/Pos | Positive | Serum | NSAIDs | Good |
| 2 | 45 | F | 2014 | Polyarthritis | None | Pos/Pos | Positive | Serum | NSAIDs | Good |
| 3 | 44 | F | 2024 | Polyarthritis | None | Pos/Pos | 128,000 | Serum | NSAIDs | Good |
| 4 | 61 | M | 2014 | Polyarthritis and erythema | Lymphopenia | NP/Pos | Positive | Serum | NSAIDs | Good |
| 5 | 26 | F | 2024 | Polyarthritis and erythema | Lymphopenia | Neg/Pos | 446Positive | SerumSkin biopsy | NSAIDs+Corticosteroids | PAN |
| 6 | 33 | F | 2024 | Polyarthritis and erythema | None | Pos/Pos | 168,000 | Serum | NSAIDs | Good |
| 7 | 42 | F | 2019 | Febrile Polyarthritis | Anemia, lymphopenia | Pos/NP | 192,000 | Serum | NSAIDs+Corticosteroids | Good |
| 8 | 43 | F | 2019 | Febrile Polyarthritis | None | Pos/Pos | 792,000 | Serum | NSAIDs+Corticosteroids | Good |
| 9 | 22 | F | 2021 | Febrile Polyarthritis, Pericardial Effusion | Anemia, lymphopenia | Neg/Pos | 21,000Negative | Bone marrowSerum | NSAIDs+Corticosteroids | Still's disease |
| 10 | 35 | F | 2024 | Febrile Polyarthritis | None | Pos/Pos | 48,000 | Serum | NSAIDs | Good |
| 11 | 43 | F | 2024 | Febrile Polyarthritis and erythema | Anemia, lymphopenia | Neg/Pos | <250 | Serum | NSAIDs | Good |
| 12 | 21 | F | 2024 | Febrile Polyarthritis | Lymphopenia | Pos/Pos | 700,000 | Serum | NSAIDs | Good |
| 13 | 45 | M | 2014 | Febrile Polyarthritis and erythema | Anemia, lymphopenia | Pos/Pos | Positive | Serum | NSAIDs+Corticosteroids | Good |
| 14 | 49 | M | 2019 | Febrile Polyarthritis and erythema | Anemia | Pos/Pos | 919,000 | Serum | NSAIDs+Corticosteroids | Good |
| 15 | 42 | F | 2019 | Febrile Polyarthritis and erythema | Anemia, lymphopenia, thrombocytopenia | Pos/Pos | 4,300,000 | Serum | NSAIDs | Good |
| 16 | 43 | M | 2024 | Febrile Polyarthritis and erythema | None | Pos/Pos | 403,500 | Serum | NSAIDs+Corticosteroids | Good |
F: female; M: male; NSAIDs: nonsteroidal anti-inflammatory drugs; NP: not performed; PAN: polyarteritis nodosa.
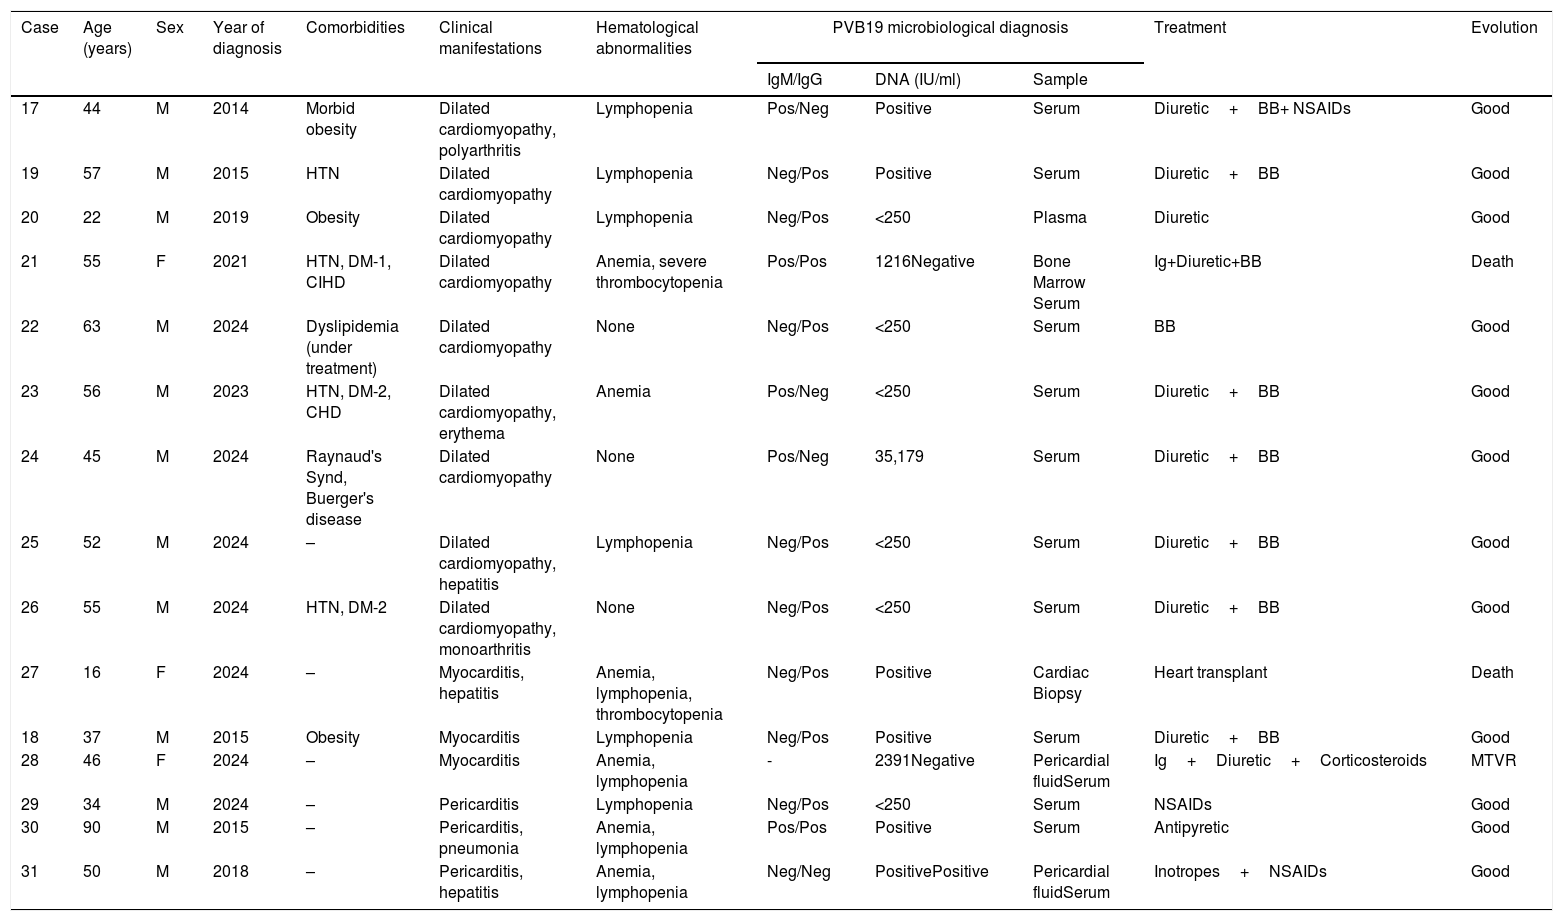
Table 2 presents the characteristics of the 15 patients with cardiac involvement, of whom 9 (60.0%) underwent dilated cardiomyopathy with ventricular dysfunction, 4 (26.7%) had pericarditis, and 2 (13.3%) had myocarditis. Of these 15 patients, 11 (73.3%) were men, with a mean age of 48.1±12.4 years. Hematologic abnormalities, mainly lymphopenia and transient anemia, were observed in 80% of cases; and only those who developed thrombocytopenia died (two patients). In 9 (60%) patients, IgM was negative, and the diagnosis was confirmed by an endomyocardial biopsy in one patient, pericardial fluid in two patients, and bone marrow in one. Eight of the nine patients (88.9%) with dilated cardiomyopathy had concurrent comorbidities, primarily metabolic disorders.
Clinical characteristics of patients with cardiac involvement.
| Case | Age (years) | Sex | Year of diagnosis | Comorbidities | Clinical manifestations | Hematological abnormalities | PVB19 microbiological diagnosis | Treatment | Evolution | ||
|---|---|---|---|---|---|---|---|---|---|---|---|
| IgM/IgG | DNA (IU/ml) | Sample | |||||||||
| 17 | 44 | M | 2014 | Morbid obesity | Dilated cardiomyopathy, polyarthritis | Lymphopenia | Pos/Neg | Positive | Serum | Diuretic+BB+ NSAIDs | Good |
| 19 | 57 | M | 2015 | HTN | Dilated cardiomyopathy | Lymphopenia | Neg/Pos | Positive | Serum | Diuretic+BB | Good |
| 20 | 22 | M | 2019 | Obesity | Dilated cardiomyopathy | Lymphopenia | Neg/Pos | <250 | Plasma | Diuretic | Good |
| 21 | 55 | F | 2021 | HTN, DM-1, CIHD | Dilated cardiomyopathy | Anemia, severe thrombocytopenia | Pos/Pos | 1216Negative | Bone Marrow Serum | Ig+Diuretic+BB | Death |
| 22 | 63 | M | 2024 | Dyslipidemia (under treatment) | Dilated cardiomyopathy | None | Neg/Pos | <250 | Serum | BB | Good |
| 23 | 56 | M | 2023 | HTN, DM-2, CHD | Dilated cardiomyopathy, erythema | Anemia | Pos/Neg | <250 | Serum | Diuretic+BB | Good |
| 24 | 45 | M | 2024 | Raynaud's Synd, Buerger's disease | Dilated cardiomyopathy | None | Pos/Neg | 35,179 | Serum | Diuretic+BB | Good |
| 25 | 52 | M | 2024 | – | Dilated cardiomyopathy, hepatitis | Lymphopenia | Neg/Pos | <250 | Serum | Diuretic+BB | Good |
| 26 | 55 | M | 2024 | HTN, DM-2 | Dilated cardiomyopathy, monoarthritis | None | Neg/Pos | <250 | Serum | Diuretic+BB | Good |
| 27 | 16 | F | 2024 | – | Myocarditis, hepatitis | Anemia, lymphopenia, thrombocytopenia | Neg/Pos | Positive | Cardiac Biopsy | Heart transplant | Death |
| 18 | 37 | M | 2015 | Obesity | Myocarditis | Lymphopenia | Neg/Pos | Positive | Serum | Diuretic+BB | Good |
| 28 | 46 | F | 2024 | – | Myocarditis | Anemia, lymphopenia | - | 2391Negative | Pericardial fluidSerum | Ig+Diuretic+Corticosteroids | MTVR |
| 29 | 34 | M | 2024 | – | Pericarditis | Lymphopenia | Neg/Pos | <250 | Serum | NSAIDs | Good |
| 30 | 90 | M | 2015 | – | Pericarditis, pneumonia | Anemia, lymphopenia | Pos/Pos | Positive | Serum | Antipyretic | Good |
| 31 | 50 | M | 2018 | – | Pericarditis, hepatitis | Anemia, lymphopenia | Neg/Neg | PositivePositive | Pericardial fluidSerum | Inotropes+NSAIDs | Good |
F: female; M: male; BB: beta-blockers; MTVR: mitral and tricuspid valve replacement; CIHD: chronic ischemic heart disease; HTN: hypertension; CHD: chronic heart disease; Ig: immunoglobulin; DM: diabetes mellitus.
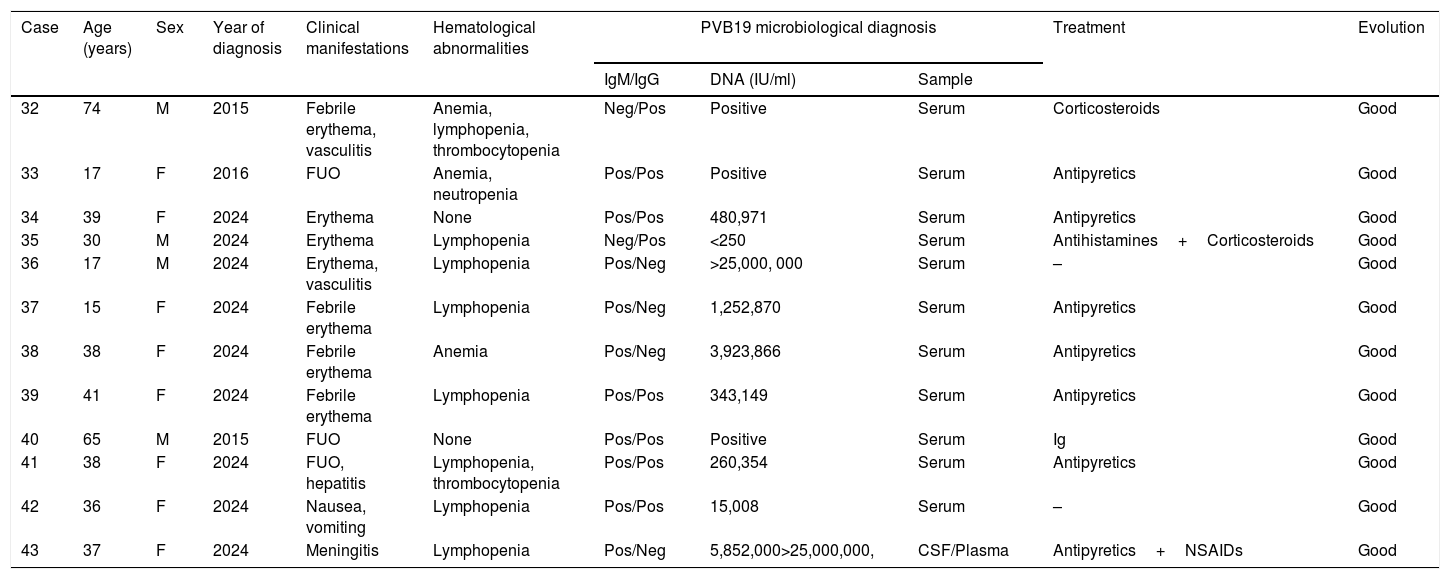
Table 3 describes the characteristics of the remaining 12 patients. Seven patients presented with erythema affecting the upper and lower extremities, accompanied by fever in 57.1% of cases. Laboratory abnormalities were present in 83.3% of patients.
Clinical characteristics of the remaining 12 patients.
| Case | Age (years) | Sex | Year of diagnosis | Clinical manifestations | Hematological abnormalities | PVB19 microbiological diagnosis | Treatment | Evolution | ||
|---|---|---|---|---|---|---|---|---|---|---|
| IgM/IgG | DNA (IU/ml) | Sample | ||||||||
| 32 | 74 | M | 2015 | Febrile erythema, vasculitis | Anemia, lymphopenia, thrombocytopenia | Neg/Pos | Positive | Serum | Corticosteroids | Good |
| 33 | 17 | F | 2016 | FUO | Anemia, neutropenia | Pos/Pos | Positive | Serum | Antipyretics | Good |
| 34 | 39 | F | 2024 | Erythema | None | Pos/Pos | 480,971 | Serum | Antipyretics | Good |
| 35 | 30 | M | 2024 | Erythema | Lymphopenia | Neg/Pos | <250 | Serum | Antihistamines+Corticosteroids | Good |
| 36 | 17 | M | 2024 | Erythema, vasculitis | Lymphopenia | Pos/Neg | >25,000, 000 | Serum | – | Good |
| 37 | 15 | F | 2024 | Febrile erythema | Lymphopenia | Pos/Neg | 1,252,870 | Serum | Antipyretics | Good |
| 38 | 38 | F | 2024 | Febrile erythema | Anemia | Pos/Neg | 3,923,866 | Serum | Antipyretics | Good |
| 39 | 41 | F | 2024 | Febrile erythema | Lymphopenia | Pos/Pos | 343,149 | Serum | Antipyretics | Good |
| 40 | 65 | M | 2015 | FUO | None | Pos/Pos | Positive | Serum | Ig | Good |
| 41 | 38 | F | 2024 | FUO, hepatitis | Lymphopenia, thrombocytopenia | Pos/Pos | 260,354 | Serum | Antipyretics | Good |
| 42 | 36 | F | 2024 | Nausea, vomiting | Lymphopenia | Pos/Pos | 15,008 | Serum | – | Good |
| 43 | 37 | F | 2024 | Meningitis | Lymphopenia | Pos/Neg | 5,852,000>25,000,000, | CSF/Plasma | Antipyretics+NSAIDs | Good |
F: female; M: male; FUO: fever of unknown origin; CSF: cerebrospinal Fluid; NSAIDs: nonsteroideal anti-inflammatory drugs; Ig: immunoglobulin.
Two patients (4.7%) died: a 16-year-old girl with fulminant myocarditis, who died 7 days after diagnosis following heart transplantation, and a 54-year-old woman with severe refractory thrombocytopenia who did not respond to immunoglobulin treatment and died 38 days after diagnosis.
DiscussionThe broad clinical spectrum of PVB19 infection, along with the recent increase in cases in Europe, underscores the importance of conducting additional studies. In this context, our study detected a marked increase in diagnoses in 2024 compared to the prior ten years, suggesting an atypically high incidence among immunocompetent adults requiring hospitalization. This increase may be linked to reduced virus circulation during the COVID-19 pandemic, followed by a resurgence after the relaxation of isolation measures, a phenomenon previously observed with other viruses. Some epidemiological studies support this hypothesis.17,18 However, the lack of systematic PVB19 surveillance makes it dificult to establish a direct correlation. Furthermore, given that PVB19 follows epidemic cycles of 3–5 years, the observed increase could also reflect its natural transmission pattern.
Approximately 25 percent of infected individuals will be completely asymptomatic during their infection, while 50 percent will have only nonspecific flu-like symptoms. The remaining 25 percent of infected individuals present with the rash of erythema infectiosum and/or arthralgias, two classic syndromes associated with parvovirus B19 infection.19 Increased clinical awareness and enhanced diagnostic vigilance in the post-pandemic period may have also contributed to the rise in reported atypical cases. Our study confirms this variability and identifies clinical patterns characterized by the involvement of multiple organs, including the skin, joints, heart, and central nervous system (CNS). Additionally, we observed a high frequency of hematologic abnormalities associated with these manifestations, highlighting the complexity of the clinical presentation.
Among these manifestations, polyarthritis was a common feature, particularly in women, aligning with previous studies that identify arthritis as a frequent presentation of PVB19 infection in adults. IgM antibodies were detected in the majority of our cases, consistent with recent infection. Viremia typically begins 5–10 days after exposure and lasts for about five days, with virus titers peaking during the first few days of infection. During this period, immunocompetent adults may be asymptomatic or present with nonspecific flu-like symptoms, but they may develop characteristic clinical manifestations (e.g., arthralgia, arthritis, and/or exanthem) due to the formation of antigen-antibody immune complexes. Importantly, individuals are no longer considered infectious once these symptoms appear. Beyond typical joint involvement, we identified cases where PVB19 appeared to trigger uncommon systemic inflammatory diseases. In one patient, PVB19 triggered the development of Still's disease, a rare systemic inflammatory disorder, though previously described in association with this virus.20 Similarly, another patient developed cutaneous polyarteritis nodosa, a vasculitis with a poorly understood pathophysiology. While viral infections, including hepatitis B virus and HIV, have been linked to this condition, prior studies suggest a possible association with PVB19.21 These findings emphasize the need for continued research on PVB19's role in autoimmunity and systemic inflammation, as well as its potential involvement in the development of rare inflammatory diseases.
The clinical diversity of PVB19 extends beyond joint and systemic inflammatory involvement to include skin and heart involvement with variable occurrence rates and presentations. In our cohort, 18.6% of patients presented with erythema on their limbs, which differed from the characteristic malar rash seen in erythema infectiosum. While erythema infectiosum is a classic presentation in children, it is less common in adults, consistent with our findings. However, as our study focused on hospitalized patients, milder cases managed outside the hospital may have been overlooked.
Of particular note was the high incidence of cardiac involvement, observed in 34.9% of patients, including cases of dilated cardiomyopathy, myocarditis, and pericarditis. Cardiac manifestations were more frequent in men, and a significant proportion of heart-related cases were associated with other comorbidities. Although previous literature has described the relationship between PVB19 and cardiac complications, a definitive causal link has not been established in all cases, and PVB19 could represent an incidental finding in this clinical scenario. However, the high proportion observed in our study may reflect both a true increase within our population and heightened clinical suspicion. Diagnosing PVB19-related cardiac involvement remains challenging. IgM negativity and low or undetectable viral loads in serum are common in patients with dilated cardiomyopathy, complicating etiological confirmation. In such cases, molecular testing using alternative samples, such as bone marrow, endomyocardial biopsy, or pericardial fluid, is essential for accurate diagnosis. Previous studies have emphasized the need for complementary diagnostic tools in cases with inconclusive serology, particularly given that PVB19-associated cardiomyopathy has often been diagnosed post-mortem.22 It is known that the virus does not establish classical viral latency; however, it can persist with low levels of viral replication, which clinically manifests as a prolonged clinical latency. Clinical outcomes of PVB19-related cardiac involvement can vary widely, ranging from mild to fatal cases. In no case of cardiomyopathy was any underlying immunodeficiency identified that could explain the progression of the infection at the myocardial level and one case of myocarditis was fatal.
The severity of PVB19 infection in certain cases with hematological involvement, such as the fatal outcome observed in our study due to severe thrombocytopenia, underscores the need for a deeper understanding of the hematologic complications associated with this virus. Fulminant thrombocytopenia is a rare condition linked to PVB19 infection, which can manifest in two main forms: one form preceding rash onset due to bone marrow suppression, and another probably immune-mediated.23 This abnormality may appear in isolation or alongside other hematologic complications, being more common in individuals with compromised immune function. The mechanisms underlying these changes remains uncertain, but several hypotheses have been proposed to explain the relationship between PVB19 and thrombocytopenia,23 including chronic inflammation, autoantibody production, molecular mimicry and haemophagocytosis. Further research is needed to fully elucidate the causes and predisposing factors behind this uncommon course of infection.
The overall mortality observed in our study was 4.7%, attributed to one case of fulminant myocarditis and another of severe thrombocytopenia refractory to available treatments. The higher incidence of cardiac involvement compared to earlier studies highlights the potential severity of PVB19 infection, even in immunocompetent adults, emphasizing the importance of early diagnosis and appropriate management in severe cases. Additionally, conducting prospective studies is crucial to identifying factors predisposing to severe forms of infection,24,25 as well as evaluating biomarkers and exploring new diagnostic strategies.
Limited knowledge of atypical presentations in immunocompetent adult populations, combined with wide variability in symptomatology—ranging from asymptomatic cases to self-limiting or potentially fatal outcomes—has hindered the systematic development of therapeutic approaches. Treatment selection depends on whether symptoms are caused by the virus's direct cytopathic effect, the cytotoxic action of viral proteins, the inflammatory response to these proteins, or the formation of immune complexes. Currently, management of severe cases primarily focuses on enhancing humoral immunity through the administration of immunoglobulins. No specific antiviral treatments are currently approved for parvovirus B19 infection.
In conclusion, our findings highlight the need to strengthen epidemiological surveillance and maintain a high index of suspicion for PVB19 in hospitalized patients with undifferentiated symptoms, particularly in the context of emerging outbreaks. This is crucial, as underdiagnosis may occur in adults presenting with nonspecific symptoms. Given the potential for severe manifestations in some immunocompetent adults, incorporating PVB19 into differential diagnostic protocols for hospitalized patients with compatible symptoms may also improve early detection and appropriate disease management.
Our study contributes to a more comprehensive understanding of the clinical spectrum and diagnostic challenges of PVB19 infection in immunocompetent adults. While similarities with previous studies reinforce current knowledge of the disease, the differences observed—such as the high incidence of cardiac involvement—highlight the need for further research to elucidate these findings and optimize diagnostic and therapeutic strategies.
FundingThis research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors.
Conflict of interestThe authors declare no conflict of interest.



