



Currently, diagnosis of dermatophyte onychomycosis relies on direct microscopic examination (DME) and fungal cultures of nail material. Herein, we aim to evaluate the clinical performance of the rapid antigen detection (RAD) assay PreventID Dermatophyte in comparison to conventional methods for the diagnosis of tinea unguium.
MethodsBetween February and July 2024, 48 nail samples, collected at the Navarra University Hospital, Spain, were included in the evaluation. In addition to DME and culture, the RAD test was executed. In case of discrepancies, the qPCR assay Novaplex™ Dermatophyte was utilized.
ResultsOverall, the RAD test performed well, comparable to DME or culture, with concordances of 80.9% and 80.0%, respectively. The existence of falsely-negative and falsely-positive results reinforces the use of complementary diagnostic procedures, such as DME and culture, for confirmatory testing.
ConclusionsIn conclusion, the PreventID Dermatophyte test provides rapid and reliable results with acceptable performance.
Actualmente, el diagnóstico de la onicomicosis por dermatofitos se basa en el examen microscópico directo (EMD) y el cultivo fúngico de material ungueal. Este estudio evalúa el rendimiento clínico del ensayo de detección rápida de antígeno (DRA) PreventID Dermatophyte, en comparación con los métodos convencionales para el diagnóstico de tinea unguium.
MétodosEntre Febrero y Julio de 2024, 48 muestras ungueales, recogidas en el Hospital Universitario de Navarra, España, fueron incluidas en la evaluación. Además del EMD y del cultivo, se realizó la DRA. En caso de discrepancias, se empleó la qPCR Novaplex™ Dermatophyte.
ResultadosLa DRA mostró un rendimiento comparable al del EMD y el cultivo, con concordancias del 80,9% y el 80,0%, respectivamente. La detección de resultados falsamente negativos y positivos subraya la necesidad de recurrir a procedimientos complementarios, como el EMD y el cultivo.
ConclusionesEn conclusión, la prueba PreventID Dermatophyte proporciona resultados rápidos y fiables, con un desempeño aceptable.
Currently, diagnosis of dermatophyte onychomycosis (also called tinea unguium) relies on direct microscopic examination (DME) and fungal cultures of nail material.1 In this regard, evidence reinforce the need for confirmatory testing before antifungal therapy.1
DME, usually using potassium hydroxide, provides a rapid preliminary result. However, performance is poor (and highly influenceable by the experience of the laboratory technician) and a positive result hardly discriminates between dermatophytes, non-dermatophyte molds and yeast filaments.2 Despite culture is widely used in clinical laboratories as the reference method for the diagnosis of dermatomycoses, it may require up to six weeks incubation.2 Furthermore, the procedure demands certain level of laboratory specialization and sensitivity is usually low, limiting rapid and optimal clinical guidance. Recently, qPCR methods have emerged for the detection of dermatophyte fungi.3 Despite the potential performances with very high predictive values, clinical validation with these molecular techniques is scarce and the cost is considerable.4 In this scenario, point-of-care tests (POCTs) have been developed to provide rapid results and impact clinical decision making.
Herein, we aim to evaluate the clinical performance of the CE-IVD-branded rapid antigen detection (RAD) assay PreventID Dermatophyte (lmmundiagnostik AG, Germany; previously manufactured by JNC, Japan, under the name Diafactory Tinea Unguium) in comparison to conventional methods (these are, DME and culture) for the diagnosis of tinea unguium.
MethodsSample selection and laboratory proceduresBetween February and July 2024, samples collected for the investigation of dermatophyte fungi at the Navarra University Hospital in Pamplona, Spain, were prospectively selected and included in the evaluation. In addition to DME – using potassium hydroxide – the RAD test PreventID Dermatophyte was executed following the manufacturer's instructions. Of note, this POCT, based on immunochromatography, reacts against certain Trichophyton spp. (including T. rubrum and T. mentagrophytes), certain Microsporum spp., and Epidermophyton floccosum. Also, culture for the routine identification of fungi responsible for cutaneous infections was performed in Sabouraud agar with chloramphenicol, and Sabouraud agar with chloramphenicol and cycloheximide. These culture media were incubated at 30°C for five weeks and inspected weekly. For the identification of fungal colonies, MALDI-TOF MS (Bruker Daltonics, USA) methods, and biochemical and microscopical procedures were utilized.
Discrepant analysesThe results yielded by the qPCR assay Novaplex™ Dermatophyte (Seegene, South Korea) were used in case of discrepancies. To specify, the Novaplex™ Dermatophyte assay targets Candida albicans, Microsporum spp. (this is; M. canis and M. audouinii) and E. floccosum; but also, Trichophyton rubrum complex (this is; T. rubrum, T. violaceum and T. soudanense), and Trichophyton mentagrophytes complex (this is; T. mentagrophytes, T. verrucosum, T. interdigitale, T. tonsurans, T. erinacei and T. benhamiae). Notably, during the study period this qPCR assay was prospectively performed, following the manufacturer's instructions, since the Navarra University Hospital already incorporated this molecular solution into the diagnostic workflow of dermatomycoses. The positivity of the Novaplex™ Dermatophyte assay was always considered as a reference in the discrepant analyses.
Statistical analysesStatistical analyses were performed using GraphPad Prism version 8.0.1 (GraphPad Software Inc., USA). Confidence intervals (CI) were calculated by exact methods. Ethical approval was obtained from the Navarra University Hospital Ethics Committee, PI_2023/36.
Sensitivity, specificity and likelihood ratio values were calculated for the RAD test and DME, and these estimates are displayed in the Supplementary material (Table S1). For this purpose, any positive result for culture or qPCR was considered definitive of dermatophytosis, while this infection was considered discarded with a consistent negative result for both assays.
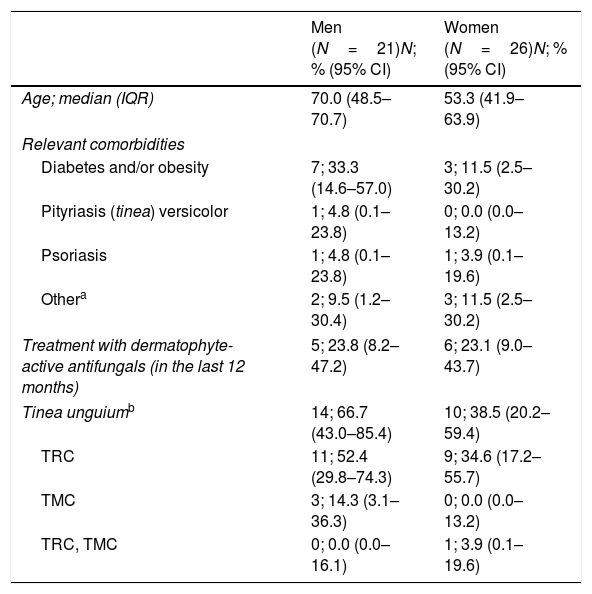
ResultsCharacterization of study individualsDuring the study period, 48 nail samples from 47 patients were included in the evaluation. Of the samples, two were nail material from hands and 20 from feet. The clinical characteristics of the individuals are described in Table 1. Briefly, 26 women and 21 men were included; with a median age of 56.1 years-old interquartile range (IQR), 46.2–64.9. Notably, none had had recent history (last year) of onychomycoses.
Clinical characteristics of the study patients; N=47.
| Men (N=21)N; % (95% CI) | Women (N=26)N; % (95% CI) | |
|---|---|---|
| Age; median (IQR) | 70.0 (48.5–70.7) | 53.3 (41.9–63.9) |
| Relevant comorbidities | ||
| Diabetes and/or obesity | 7; 33.3 (14.6–57.0) | 3; 11.5 (2.5–30.2) |
| Pityriasis (tinea) versicolor | 1; 4.8 (0.1–23.8) | 0; 0.0 (0.0–13.2) |
| Psoriasis | 1; 4.8 (0.1–23.8) | 1; 3.9 (0.1–19.6) |
| Othera | 2; 9.5 (1.2–30.4) | 3; 11.5 (2.5–30.2) |
| Treatment with dermatophyte-active antifungals (in the last 12 months) | 5; 23.8 (8.2–47.2) | 6; 23.1 (9.0–43.7) |
| Tinea unguiumb | 14; 66.7 (43.0–85.4) | 10; 38.5 (20.2–59.4) |
| TRC | 11; 52.4 (29.8–74.3) | 9; 34.6 (17.2–55.7) |
| TMC | 3; 14.3 (3.1–36.3) | 0; 0.0 (0.0–13.2) |
| TRC, TMC | 0; 0.0 (0.0–16.1) | 1; 3.9 (0.1–19.6) |
Abbreviations: CI, confidence interval; TRC, Trichophyton rubrum complex; TMC, Trichophyton mentagrophytes complex.
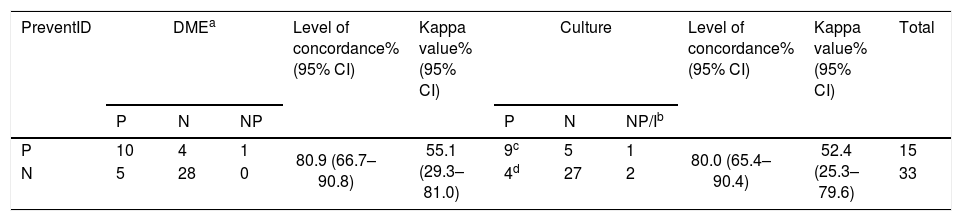
The overall comparison between the RAD test and DME, and the RAD test and fungal culture, is displayed in Table 2A. The level of concordance between methods was 80.9% (95% CI, 66.7%–90.8%) and 80.0% (95% CI, 65.4%–90.4%), respectively. Notably, seven samples tested positive for all three methods while 25 were negative.
Comparison between the rapid antigen detection test (PreventID Dermatophyte) and conventional methods (these are, direct microscopic examination and culture); N=48.
| PreventID | DMEa | Level of concordance% (95% CI) | Kappa value% (95% CI) | Culture | Level of concordance% (95% CI) | Kappa value% (95% CI) | Total | ||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| P | N | NP | P | N | NP/Ib | ||||||
| P | 10 | 4 | 1 | 80.9 (66.7–90.8) | 55.1 (29.3–81.0) | 9c | 5 | 1 | 80.0 (65.4–90.4) | 52.4 (25.3–79.6) | 15 |
| N | 5 | 28 | 0 | 4d | 27 | 2 | 33 | ||||
Abbreviations: DME, direct microscopic examination; P, positive; N, negative; NP, not performed; CI, confidence interval; I, inconclusive.
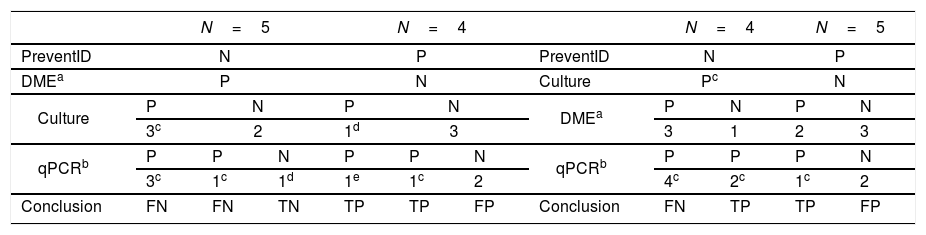
Discrepant analyses are detailed in Table 2B. Of the nine discrepancies detected between the RAD test and DME, one case and two cases were classified as true-negative and true-positive results of the RAD test, respectively. Contrary, four cases and two cases concluded as false-negative and false-positive results of the RAD test, respectively. On the other hand, of the nine discrepancies found between the RAD test and fungal culture, three cases were classified as true-positive results of the RAD test. Contrary, four cases and two cases concluded as false-negative and false-positive results of the RAD test, respectively. No clinical characteristic was associated with the yield of falsely-negative or falsely-positive results.
Discrepant analyses.
| N=5 | N=4 | N=4 | N=5 | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|
| PreventID | N | P | PreventID | N | P | ||||||
| DMEa | P | N | Culture | Pc | N | ||||||
| Culture | P | N | P | N | DMEa | P | N | P | N | ||
| 3c | 2 | 1d | 3 | 3 | 1 | 2 | 3 | ||||
| qPCRb | P | P | N | P | P | N | qPCRb | P | P | P | N |
| 3c | 1c | 1d | 1e | 1c | 2 | 4c | 2c | 1c | 2 | ||
| Conclusion | FN | FN | TN | TP | TP | FP | Conclusion | FN | TP | TP | FP |
Abbreviations: DME, direct microscopic examination; P, positive; N, negative; FN, false-negative; TP, true-positive; FP, false-positive.
Overall, the RAD test PreventID Dermatophyte performed well for the rapid diagnosis of tinea unguium in nail material. Our findings correlate with those provided in the literature.5,6 Thus, the performance of the RAD test for the detection of dermatophytes is comparable to the one achieved by DME or culture, with concordances of 81% and 80%, respectively.
Incorporating the qPCR assay Novaplex™ Dermatophyte, the comprehensive discrepant analysis executed in this evaluation underlines the complementary performances of these diagnostic methods. Nine discrepancies were detected between the RAD test and DME, and also nine (five of which were also discrepancies between the RAD test and DME) were detected between the RAD test and culture. Of these, an important proportion were ultimately confirmed as true-positives (5/18) or true-negatives (1/18) by the qPCR assay. Contrary, 8/18 resulted false-negative results and 4/18 were ultimately confirmed as false-positives. Notably, no clinical factors were associated with the yield of falsely-negative or falsely-positive results of the PreventID Dermatophyte test.
The existence of falsely-negative results reinforces the use of complementary diagnostic procedures, such as DME and culture, for confirmatory testing. This conservative approach does not only amend sensitivity issues with the RAD test, but also provides diagnosis for non-dermatophyte onychomycosis. Also, since false-positives may occasionally occur, positive RAD results should be ideally confirmed with culture methods.
In summary, the effective incorporation of these novel microbiological procedures in the diagnosis of dermatophyte onychomycosis should be further explored.7 Of note, PreventID Dermatophyte test provides a positive reaction but it does not specify the species detected in the assay. While this could be an important limitation in other fungal infections, clinical management of tinea unguium is not usually species-dependent. Nevertheless, the proper identification of dermatophytes among onychomycosis cases may have an important epidemiological value. Additionally, it should be noted again that some onychomycosis may be caused by non-dermatophyte fungi.8,9 In conclusion, the PreventID Dermatophyte test performs well for the diagnosis of tinea unguium. Acknowledging the need for microbiological confirmatory testing prior treatment, this POC test may provide rapid and reliable results with acceptable performance, refining clinical management. However, this assay should not replace standard procedures such as DME or culture.
CRediT authorship contribution statementLucía Argente-Colás: Data curation, Formal analysis, Investigation, Writing – original draft. Miren Urmeneta: Methodology, Writing – review and editing. Sayoa Herán-Gómez: Methodology, Writing – review and editing. Ana Navascués-Ortega: Funding acquisition, Resources, Validation, Writing – review and editing. María-Eugenia Portillo: Funding acquisition, Resources, Supervision, Validation, Writing – review and editing. Miguel Fernández-Huerta: Conceptualization, Data curation, Formal analysis, Funding acquisition, Investigation, Resources, Supervision, Validation, Writing – original draft, Writing – review and editing.
Ethical considerationsEthical approval was obtained from the Navarra University Hospital Ethics Committee, PI_2023/36.
Informed consentPatient data present in the article do not violate patient privacy or confidentiality, nor allow identification. Waiver of informed consent was obtained from the Navarra University Hospital Ethics Committee.
Declaration of generative AI and AI-assisted technologies in the writing processNothing to disclose.
FundingMaster-Labor, distributor of the test in Spain, supplied the antigen detection kits utilized for this study. Master-Labor did not have any role in the clinical evaluation, including data collection and analysis, decision to publish, or preparation of the manuscript.
Conflicts of interestNone declared.
We thank Leire Beramendi and Carmen Ezpeleta-Baquedano for their valuable contribution.
The following are the supplementary data to this article:




