



The application of PET/CT with radiopharmaceuticals targeting PSMA is significantly transforming the diagnostic and therapeutic strategies of patients with prostate cancer. In Spain, the availability and access to positron-emitting radiopharmaceuticals targeting Prostate-Specific Membrane Antigen (PSMA) have significantly changed in recent months. These changes are affecting their use in diagnostic procedures. As a result, its use within diagnostic protocols for patients with prostate cancer is undergoing significant modifications. In this collective and cooperative document, the authors have selected the most robust evidence accumulated to date to generate a clinical guide to achieve appropriate use of this technology. A format that presents the most frequent clinical situations and the patient profiles in which PSMA PET/CT plays a significant role or will do so in the immediate future has been chosen. It should be taken into account that regulatory restrictions mediate the current indications for its use in Spain, as well as its current cost and the production capacity of radiopharmaceuticals. The guideline presents a review of the established methodology for optimized imaging with each of the radiopharmaceutical variants targeting PSMA and recommendations for structured and accurate reporting of metabolic findings in combination with CT.
La aplicación de la PET/TC con radiofármacos dirigidos al PSMA está transformando notablemente las estrategias diagnósticas y terapéuticas de los pacientes con cáncer de próstata. En España, la disponibilidad y el acceso a los radiofármacos emisores de positrones dirigidos al antígeno de membrana específico de la próstata (PSMA) han experimentado cambios significativos en los últimos meses. Como resultado, su uso dentro de los protocolos diagnósticos para pacientes con cáncer de próstata está sufriendo modificaciones significativas. En este documento colectivo y cooperativo, los autores han seleccionado la evidencia más robusta acumulada hasta el momento para generar una guía clínica orientada a alcanzar un uso apropiado de esta tecnología. Se ha escogido un formato que presenta las situaciones clínicas más frecuentes y los perfiles de pacientes en los que la PET-PSMA juega un papel trascendente, o lo hará en un futuro próximo. Debe tenerse en cuenta que las indicaciones actuales de su uso en España están mediatizadas por restricciones regulatorias, por su coste actual y por la capacidad de producción de los radiofármacos. La guía presenta una revisión de la metodología consolidada para la obtención optimizada de las imágenes con cada una de las variantes radiofarmacéuticas dirigidas al PSMA y recomendaciones para un informe estructurado y preciso de los hallazgos metabólicos en combinación con la TC.
Prostate cancer (PC) is the second most frequently diagnosed cancer worldwide and the fourth most common in Spain. The five-year survival rate of PC is high. However, nearly 20% of cases progress to a metastatic stage.1 In the early phases of PC, there is a high probability of cure by surgery (radical prostatectomy, RP) or by radiotherapy (RT) or brachytherapy. These treatments can be applied alone or in combination with hormonal therapy, which is based on a reduction of androgens, known as androgen deprivation therapy (ADT)).2
Following initial intention to cure treatment, up to 50% of the patients may present biochemical recurrence (BR), which manifests as an increase in prostate-specific antigen (PSA) levels. This phenomenon indicates a potential reactivation of the cancer, although it does not always lead to immediate clinical manifestations of metastatic disease.3 Therapeutic management is defined by the localization and extension of the disease. If localized or with minimal extension, targeted therapies may be considered. Classical staging with computerized tomography (CT) and bone scintigraphy (BSc) have been reoriented towards the introduction of positron emission tomography (PET)/CT with the prostate-specific membrane antigen (PSMA) based on superior results compared to conventional imaging techniques, especially within the context of low PSA levels.5
The PSMA is a type II membrane glycoprotein with a large extracellular domain where the antibodies bind and it is physiologically expressed in prostate tissue, salivary glands and the duodenum.6 The PSMA is overexpressed in most PC, fundamentally in adenocarcinoma.7 Capromab pendetide labeled with indium-111 (111ln) was the pioneer in the evolution of PSMA radiopharmaceuticals, being characterized by its intracellular binding. Afterwards, J591 was investigated, which joins the extracellular domain of the PSMA and can be labeled with 111ln and technetium-99 m (99mTc) for diagnostic purposes, as well as yttrium-90 (90Y), lutetium-177 (177Lu) and actinium-225 (225Ac) for therapeutic applications.7 The transforming advances in this field began with the development of [68Ga]Ga-PSMA-11, which binds to PSMA at an extracellular level and facilitates obtaining detailed PET images of its distribution. The innovation continued with the introduction of agents labeled with fluor-18 (18F), especially DCFPyL (2-(3-{1-carboxy-5-[(6-18F-fluoro-pyridine-3-carbonyl)-amino]-pentyl}-ureido)-pentanedioic acid, [18F]DCFPyL, which represented an important improvement due to its centralized production and its capacity to be distributed to PET centers without access to cyclotrons or 68Ge/ 68Ga generators.5 At present, the radiopharmaceuticals most commonly used are [68Ga]Ga-PSMA-11 and [18F]DCFPyL and their choice depends on local factors, such as authorizations and availability or access.8
Within a setting of constant evolution, albeit influenced by regulatory restrictions, but clearly aimed at the increasing use of PSMA-PET and the progressive replacement of conventional techniques of diagnosis and staging in the management of PC, we propose a rapid guide on the use of PSMA-PET.
The objective is to establish clear guidelines based on scientific evidence and clinical experience on the use of PSMA-PET to improve diagnostic accuracy, personalize treatment and ensure effective integration of this technology in the management of PC.
Diagnosis and staging of prostate cancerStaging of PC is fundamental to be able to perform adequate treatment. With the progressive incorporation of new generation imaging techniques to the usual practice, new potential for PSMA-PET as a guide for biopsy in patients with high clinical suspicion of PC and repeatedly negative biopsies has opened.5
The last guidelines of the European Association of Urology recommend the use of CT and BSc in distant staging of patients with intermediate risk and PSMA-PET in high-risk and locally advanced cancer.9
PSMA-PET is a last generation imaging technique that is highly sensitive for the staging of patients with high-risk PC. In addition, it is especially useful in BR and for selecting patients who are candidates for targeted therapy with radiopharmaceuticals (radioligand therapies – RLT).10,11 One of the main advantages of PSMA-PET is that the primary tumor can be evaluated as well as lymph node, visceral and bone involvement. In addition, this technique is especially promising for detecting oligometastatic disease, offering the possibility of targeted and less toxic treatments.12 At present, studies are ongoing to analyze the accuracy of PSMA-PET and its capacity of identification of patients with PC as well as specifically direct combined treatments by the evaluation of tumoral volume and RLT.13
Profile of patients after prostate cancer treatmentThe use of PSMA-PET is recommended in patients with BR after intention to cure treatment, in patients in whom the PSA values did not become negative after treatment or when subsequent BR is detected.
Following the initial intention to cure treatment, determination of PSA levels is fundamental for staging and personalizing therapeutic management. Patients are classified based on PSA dynamics:
- •
Patients whose PSA levels do not descend to undetectable levels following primary treatment (persistent disease).
- •
Patients who achieve an undetectable PSA level which is later detectable (PSA recurrence). This differs based on the primary treatment received.
- •
Patients with persistent, albeit low, PSA levels due to slow tumoral metabolism or benign residual tissue.3
It is of great importance to understand the type of profile a patient with disease, which may be found after initial treatment (RP or RT), since this may influence the positivity of the test.
Patients with biochemical persistence after radical prostatectomy (RP)These are patients with PSA levels ≥0.1 ng/mL at 4–8 weeks after surgery, suggesting the possibility of residual or more advanced disease.3,14 In this setting, the PSA values do not diminish to undetectable levels or to the expected levels after surgery (PSA = 0 ng/mL). In this scenario, conventional techniques have a low sensitivity for detecting the presence of tumoral tissue, while PSMA-PET can identify residual tumoral tissue or metastasis, even with low PSA levels (especially with PSA > 0.2 ng/mL).15
Provided that the results have implications for the selection of posterior treatment, international guidelines recommend performing PSMA-PET in patients presenting a persistent post-operative PSA > 0.2 ng/mL (in at least two determinations) after RP.16
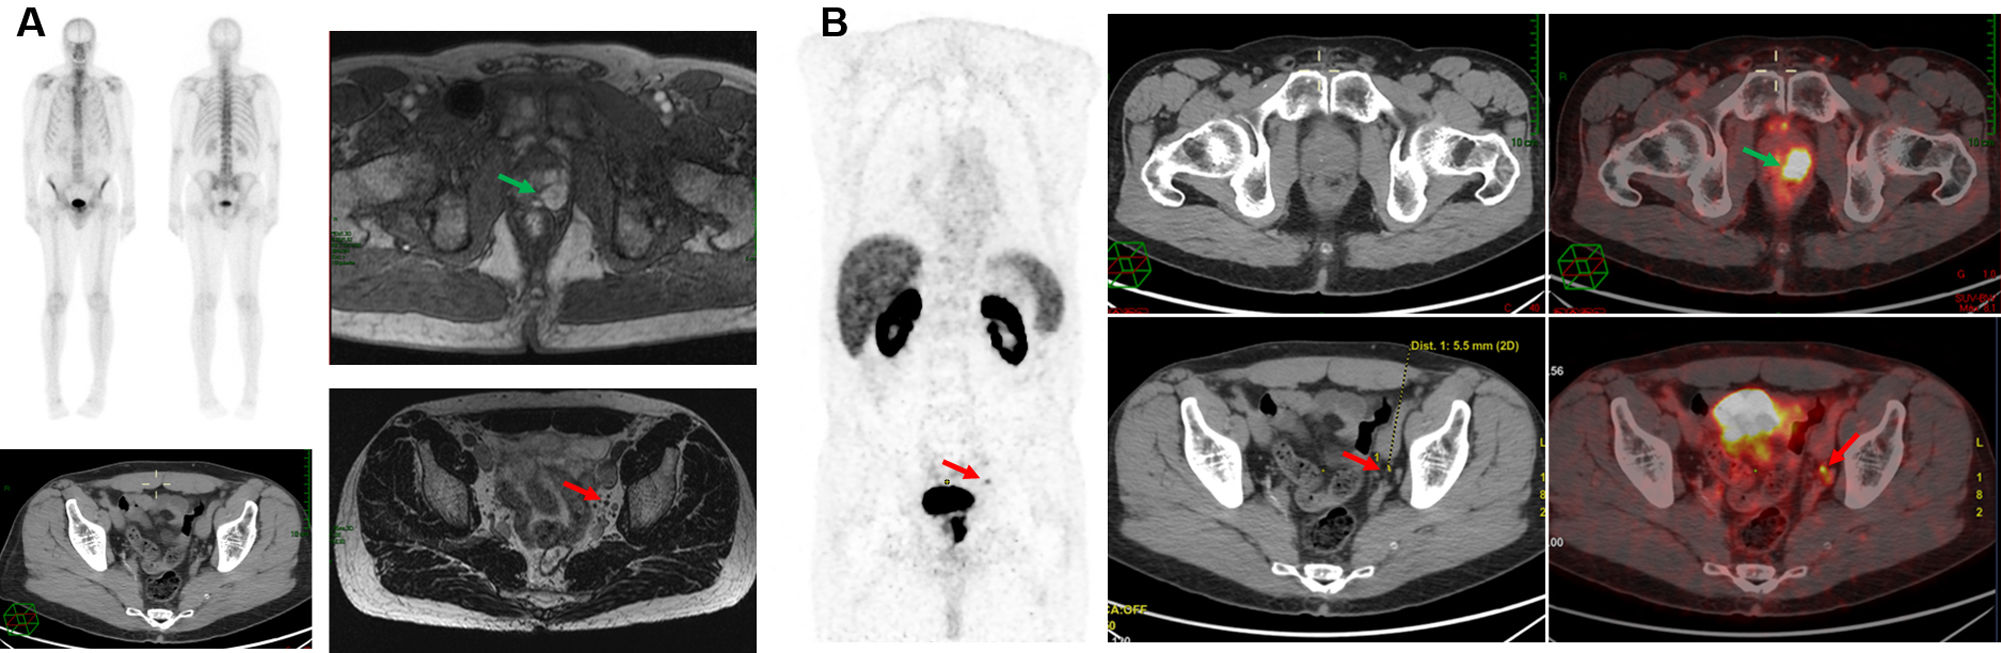
Patients with biochemical recurrence (BR) after radical prostatectomy (RP)These are patients who, after RP present a confirmed and sustained increase in PSA values after having achieved undetectable levels after surgery. PSMA-PET is the test of choice in patients with BR (Fig. 1), since it has shown to be superior to conventional imaging techniques in the exact localization of recurrent disease, independently of PSA values.10,17

This technique is particularly effective even when the PSA levels are low (<0.5 ng/mL). Several studies, including systematic reviews and meta-analyses, have shown that the percentage of positive results in PSMA-PET studies increases with an increase in PSA values.17,18
PSMA-PET positive rate:
- •
PSA ≤0.2 ng/mL, 33–43%.
- •
PSA >0.2 and ≤0.5 ng/mL, 45–58%.
- •
PSA >0.5 and ≤1 ng/mL, 59–72%.
- •
PSA >1 and ≤2 ng/mL, 75–84%.
- •
PSA >2 ng/mL, 90–95%.
This pattern suggests that an increase in PSA levels not only raises the probability of having a positive PSMA-PET result, but it is also associated with a higher frequency of detection of disease in multiple localizations. In addition, some studies have found that the rate of detection is influenced by other clinical parameters, such as the PSA doubling time (PSA-DT) and the Gleason score/International Society of Urological Pathology with which a lower PSA-DT and high scores are correlated with a greater probability of positive detection.19
Patients with biochemical recurrence (BR) after radiotherapy (RT) with intention to cureTo consider BR following RT, a specific reference point known as nadir (level lower than PSA achieved following treatment) +2 ng/mL is used.20
In patients presenting BR after RT, it is recommended to perform PSMA-PET (strong level of recommendation according to European guidelines). If PSMA radiopharmaceuticals are not available, fluciclovine or [18F]fluorocholine PET/CT is a reliable alternative for accurate diagnosis21 in patients with PSA values >2 ng/mL.16
Patients with a new biochemical recurrence (BR) after salvage surgery or radiotherapy (RT)These patients present a new BR after the use of salvage therapies by surgery or RT. The tumoral disease reappears, often localized outside the prostatic fossa and most of the patients have a limited number of metastases. There is increasing interest in developing metastasis-targeted treatments (MTT) guided by PSMA-PET images. The objective of MTT is to treat all the visible metastases of PC to prevent or delay greater metastatic dissemination. This therapeutic approach potentially improves the results of the patients in comparison with conventional techniques of active surveillance or systemic treatments, such as ADT or chemotherapy.22 Nonetheless, at present, there is insufficient scientific evidence regarding an increase in overall survival of patients treated in this scenario (guideline of MTT by PSMA-PET).
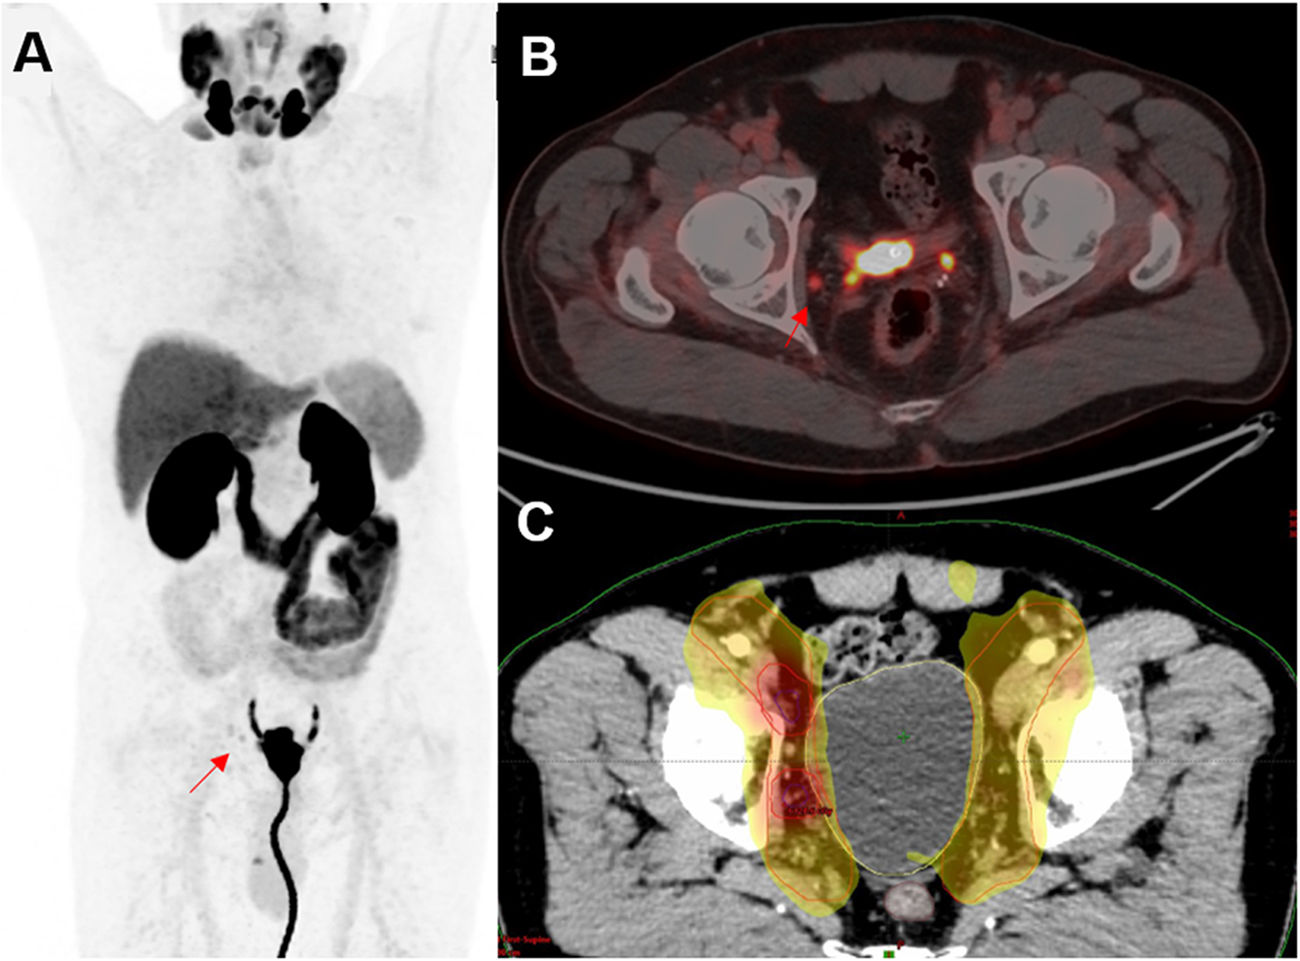
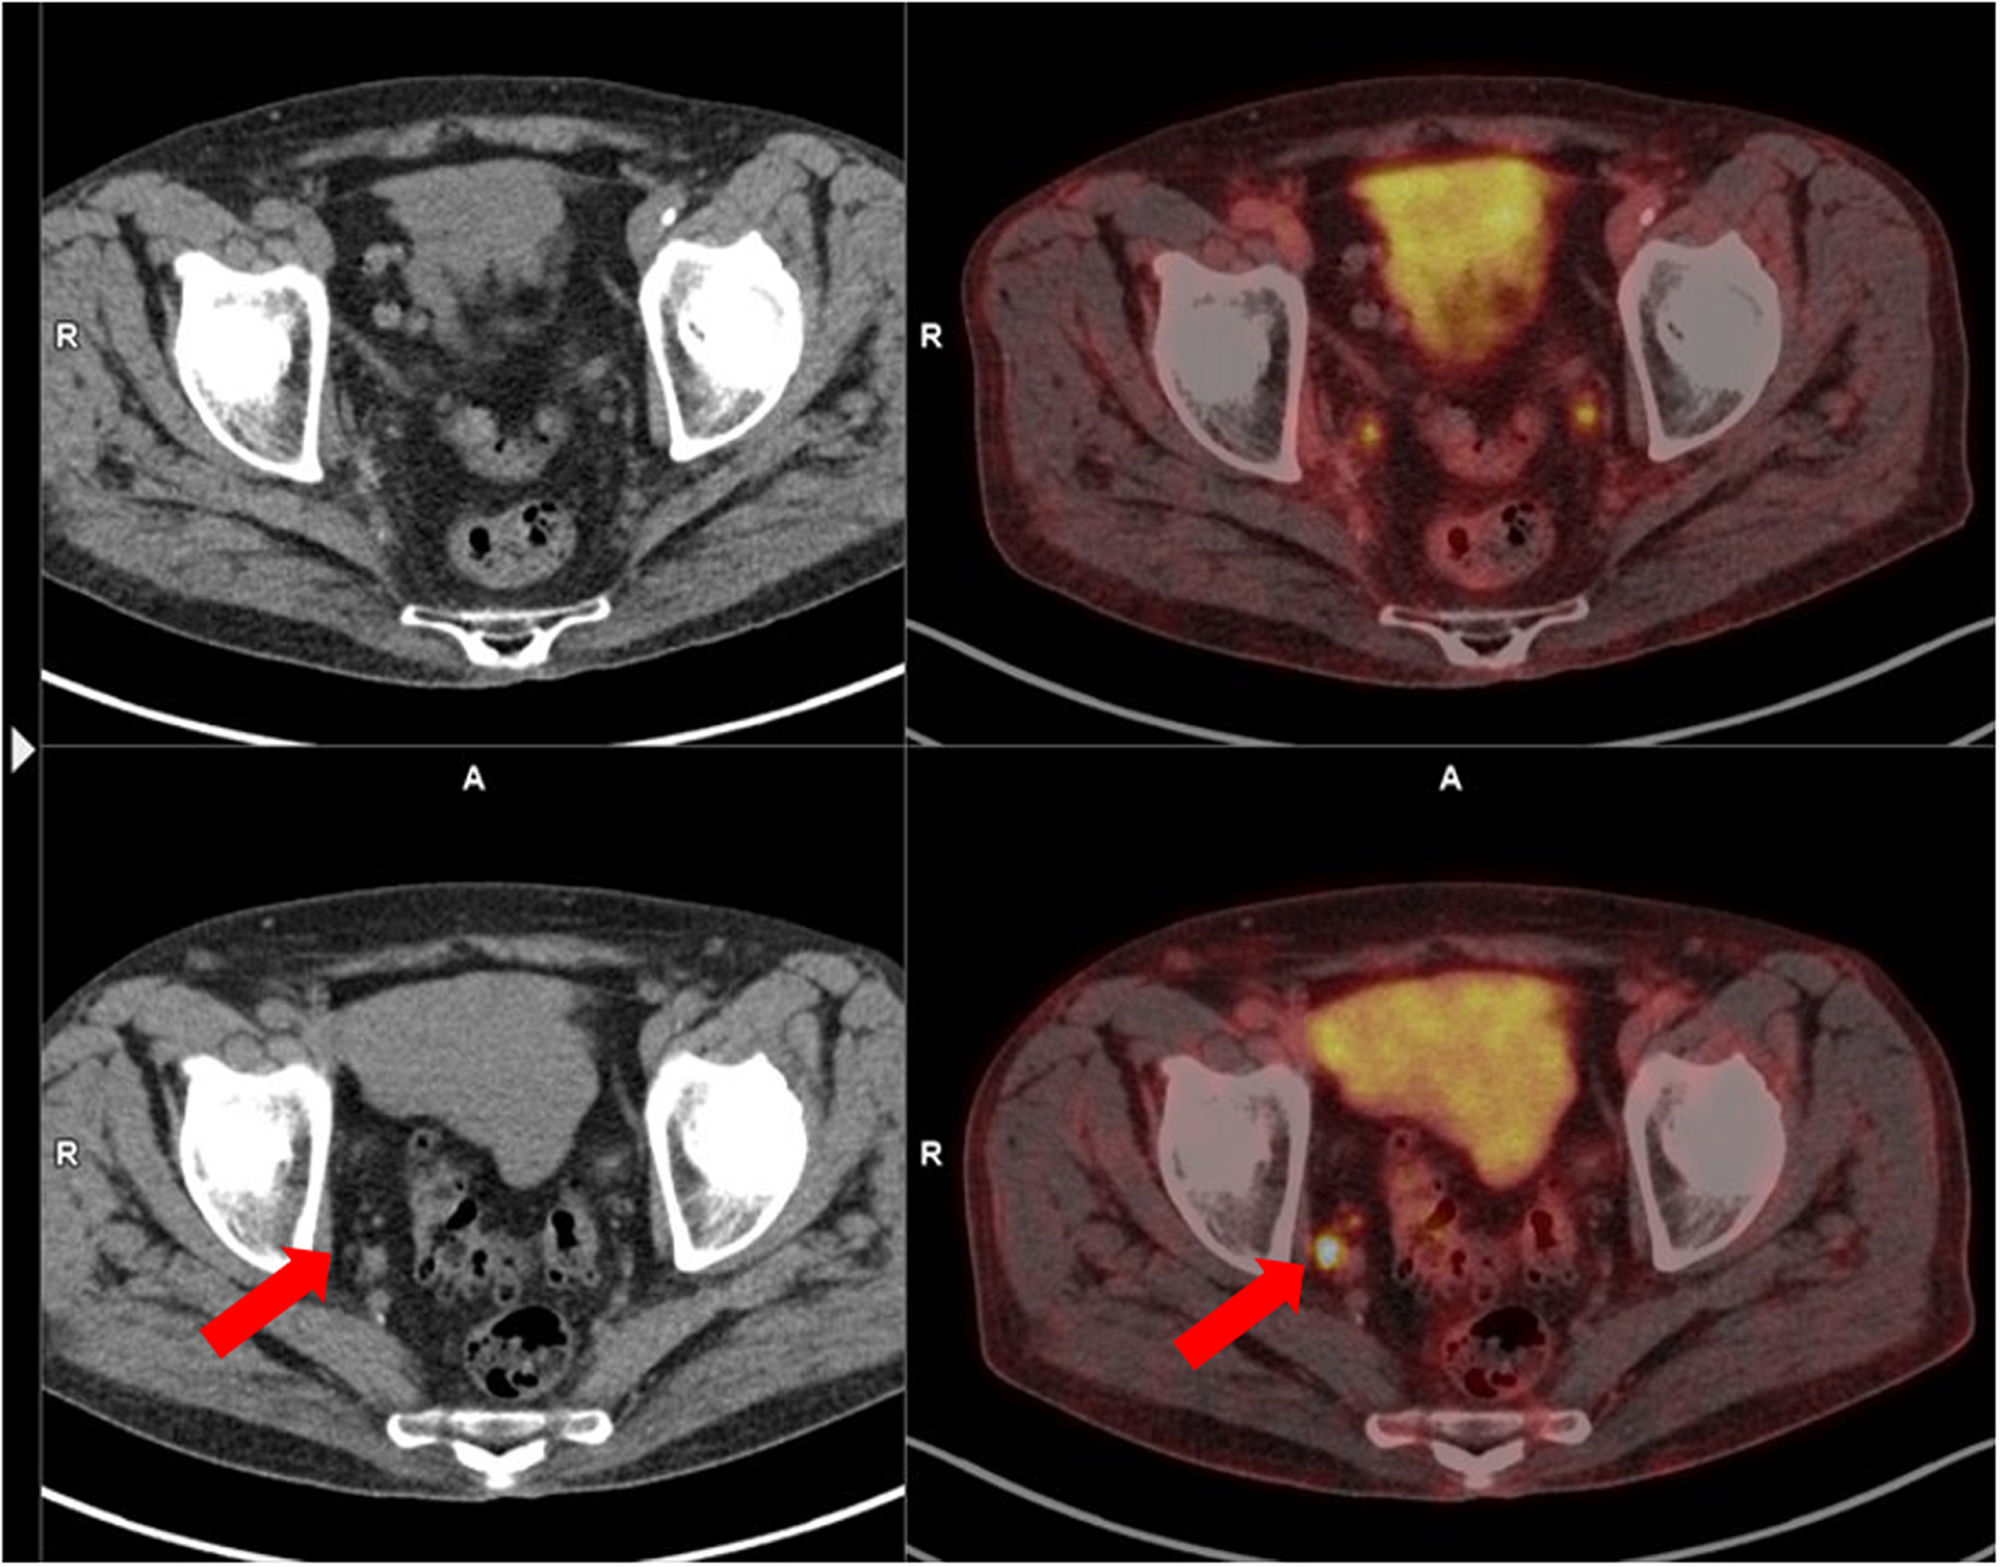
Fig. 2 shows a case of lymph node recurrence with a notable positive response to stereotactic body radiation therapy, and Fig. 3 shows a case of local lymph node recurrence treated with surgery.

Lymph node recurrence with positive response to radiotherapy.
Lymph node recurrence with positive response to radiotherapy. 57-year-old patient with PC, Gleason 7, RP R0. BR with PSA 0.26 ng/mL with PSA doubling time: 10 months (CT, bone scan, MRI and PET-CT [18F]fluorocholine negative).
PET-PSMA shows right obturator adenopathy (red arrow). (A) MIP image and (B) Axial fusion slice. (C) Change in RT planning, overprint adds irradiation volumes on the right side to the standard RT planning.

Lymph node recurrence rescued with surgery.
Lymph node recurrence rescued with surgery. A 70-year-old patient with a history of Gleason 8 (4 + 4) PC treated with RP. Two years after surgery, PSA level was elevated (0.2 ng/mL), so PET-PSMA was performed, which showed lymph node recurrence in a 3 mm right internal iliac adenopathy (bottom row). The lesion was rescued with surgery. A follow-up PET/CT (top row) confirmed complete excision of the lesion.
To decide whether a patient is a candidate for RLT, PSMA-PET is used to evaluate PSMA expression in the tumoral lesions. If these lesions show significant uptake of the radiopharmaceutical, this indicates that treatment with RLT could be effective. The use of specific radiopharmaceuticals, such as Locametz® [68Ga]68-PSMA23 or Pluvicto® [177Lu]Lu-PSMA-617,24 allows accurate targeted therapy, since these agents seek and bind to the cancerous cells that express PSMA, thereby facilitating focalized treatment and minimizing the impact on surrounding healthy tissue.
Locametz® [68Ga]68-PSMA was approved by the Food and Drug Administration (FDA)23 and the European Medicines Agency25 in 2022. Locametz® is indicated for:
- •
The initial staging of patients with high-risk PC.
- •
The detection of BR after initial intention to cure therapy.
- •
The identification of patients with PSMA positive metastatic castration-resistant prostate cancer (mCRPC) patients who are candidates for RLT.
On the other hand, Pluvicto® ([177Lu]Lu-vipivotide tetraxetan or [177Lu]Lu-PSMA) was approved by the FDA in 2022.24 Pluvicto® combined with ADT with or without androgen receptor pathway inhibitors is indicated for the treatment of adult patients with mCRPC in progression, positive to PSMA, who have received androgen receptor pathway inhibitors and chemotherapy with taxanes.23
The criteria for selecting patients who are candidates for RLT is closely aligned with those established in the multicenter VISION clinical trial.26 Patients should have at least one positive metastatic lesion and the absence of any PSMA negative lesion. A positive lesion is defined with uptake greater than that of the liver, while a negative lesion is a suspicious lesion showing PSMA uptake less than or equal to that of hepatic parenchyma. Negative lesions also include lymph nodes with a minimum diameter of 2.5 cm, lesions of at least 1.0 cm in solid organs or metastatic bone lesions with a soft tissue component of at least 1.0 cm. Patients with a single lesion considered as negative do not fulfill the criteria for RLT.24
Evaluation of therapeutic response with radioligand therapy (RLT) in patients with metastatic castration-resistant prostate cancer (mCRPC)The therapeutic approach to mCRPC has been transformed by RLT, particularly with PSMA labeled with 177Lu. Several prospective studies26–28 have demonstrated that this treatment provides high rates of effectiveness, scarce secondary effects and notable improvements in the reduction of pain and quality of life of patients with mCRPC who do not respond to other systemic treatments.
At present, the evaluation of response in mCRPC follows the guidelines of the Prostate Cancer Clinical Trials Working Group 3 (PCWG3),29 which include the determination of PSA and the use of conventional imaging techniques such as CT, magnetic resonance (MR) and BSc. According to the results of these tests, disease progression is established considering two of the following three criteria: biochemical, clinical or radiological progression.
Although PSMA-PET surpasses conventional studies15 and [18F]fluciclovine PET/CT in the evaluation of response,30 until more evidence is available, the European recommendations do not currently support a change of treatment based only on PSMA-PET findings.4
The incorporation of PSMA-PET in the evaluation of response to RLT has led to the development of new criteria and parameters to assess patient response:
Criteria of progression by PSMA-PET (PPP): these criteria adapt the recommendations of the PCWG3 to determine progression, identifying new PSMA-positive lesions or significant changes together with clinical evidence of disease progression. These are preferably used in patients with oligometastatic disease.
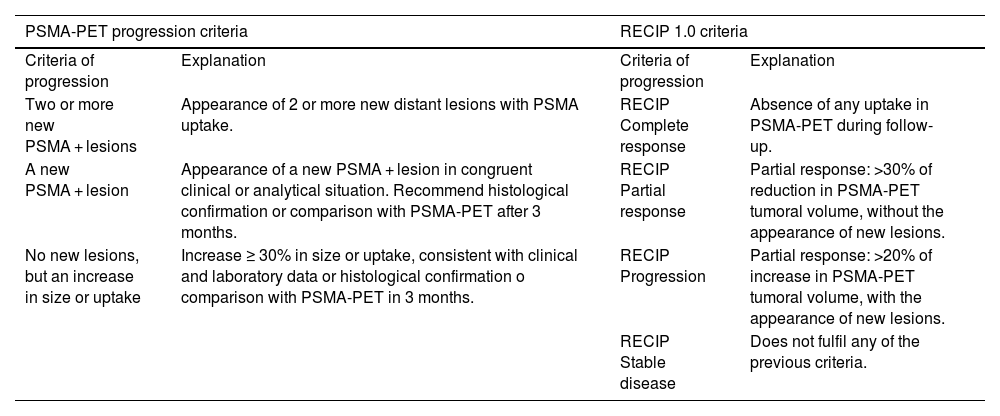
The PPP criteria31 are defined based on disease progression (Table 1).
Progression by PSMA-PET (PPP) and Response Evaluation Criteria in Prostate-specific Membrane Antigen (PSMA) PET/CT (RECIP 1.0) criteria.
| PSMA-PET progression criteria | RECIP 1.0 criteria | ||
|---|---|---|---|
| Criteria of progression | Explanation | Criteria of progression | Explanation |
| Two or more new PSMA + lesions | Appearance of 2 or more new distant lesions with PSMA uptake. | RECIP Complete response | Absence of any uptake in PSMA-PET during follow-up. |
| A new PSMA + lesion | Appearance of a new PSMA + lesion in congruent clinical or analytical situation. Recommend histological confirmation or comparison with PSMA-PET after 3 months. | RECIP Partial response | Partial response: >30% of reduction in PSMA-PET tumoral volume, without the appearance of new lesions. |
| No new lesions, but an increase in size or uptake | Increase ≥ 30% in size or uptake, consistent with clinical and laboratory data or histological confirmation o comparison with PSMA-PET in 3 months. | RECIP Progression | Partial response: >20% of increase in PSMA-PET tumoral volume, with the appearance of new lesions. |
| RECIP Stable disease | Does not fulfil any of the previous criteria. | ||
Response Evaluation Criteria in Prostate-specific Membrane Antigen (PSMA) PET/CT (RECIP 1.0) criteria: these criteria consider the changes in tumoral metabolic volume and the appearance of new lesions detected (tumoral load) by PSMA, providing a quantitative and qualitative measure of response to treatment. The RECIP criteria32 facilitate standardized interpretation of the results considering four criteria of response (Table 1).
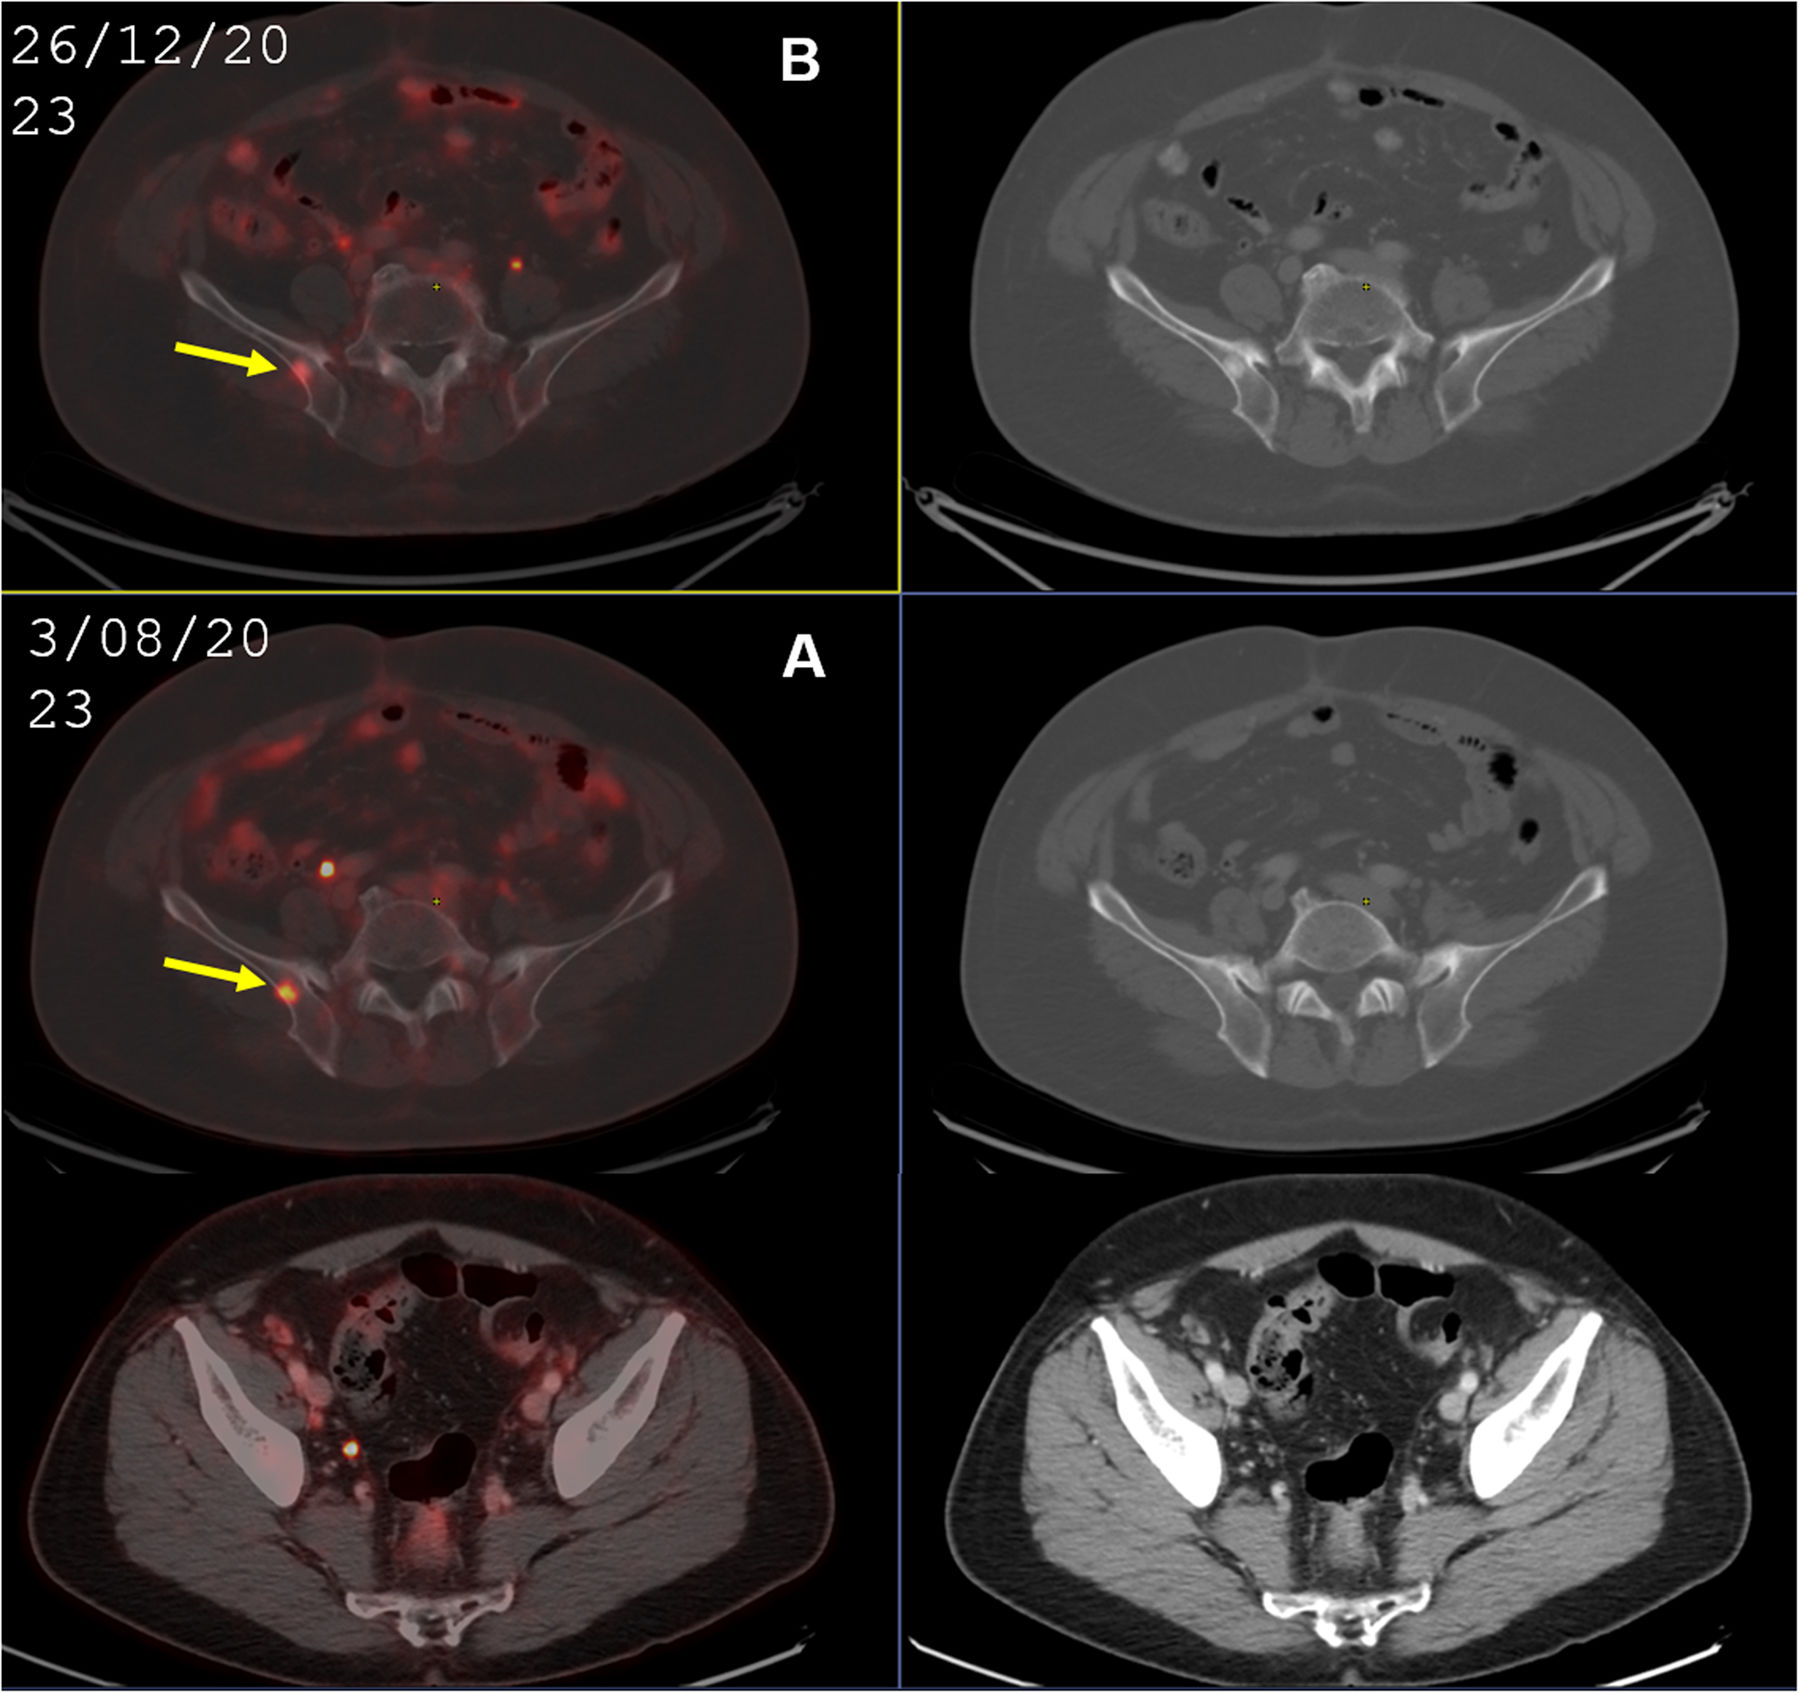
Fig. 4 presents images showing the presence of bone metastasis M1b with PSMA-PET.

PET-PSMA detection of oligometastases.
A 53-year-old patient with Gleason 9 (5 + 4) PC, 100% cylinders. Negative CT and bone scan (cT4N1M0.). (A) Axial images of PET/CT with [18F]DCFPyL detect lymph node involvement in the right external iliac and a single bone metastasis in the right iliac bone with no findings on CT.
(B) Follow-up PET/CT with [18F]DCFPyL confirms a metastatic bone lesion with sclerotic changes on CT.
A request for a Nuclear Medicine study should include all the clinical data necessary for the Nuclear Medicine specialist to select the most appropriate study to carry out and correctly interpret the images acquired.
For the initial staging of PC, the request should include:
- •
Date of diagnosis.
- •
Specific diagnosis, including biopsy and Gleason score results.
- •
Current PSA value and its evolution.
- •
Summary of previous imaging studies.
- •
Description of relevant symptoms, such as bone pain and urinary disorders.
- •
List of comorbidities and previous surgical interventions.
To collect information on the localization of BR or in patients with advanced PC after the initial treatment, the following are essential:
- •
Description of the initial therapy.
- •
Other treatments administered, such as surgery, RT or hormonal therapy.
- •
Dates of the treatments performed.
- •
Detailed evolution of the PSA (initial values, nadir, current value and the kinetics).
- •
Summary of the imaging tests performed.
- •
Specific treatments administered: ADT, androgen receptors, therapy with 223Radium, therapy with radiopharmaceuticals with PSMA (PSMA-RLT).
- •
Relevant symptoms, such as bone pain or urinary disorders.
- •
Comorbidities.
For patient preparation the following aspects should be taken into account:
- •
The patients can continue with their usual medication, and fasting before the study is not necessary.
- •
Hydration of the patient is necessary before image acquisition as a measure of radioprotection.
- •
It is recommended that patients empty their bladder just before beginning image acquisition to improve the quality of the images.
- •
The use of diuretics or bladder catheterization is generally not necessary, but their application remains at the discretion of the center according to specific needs.
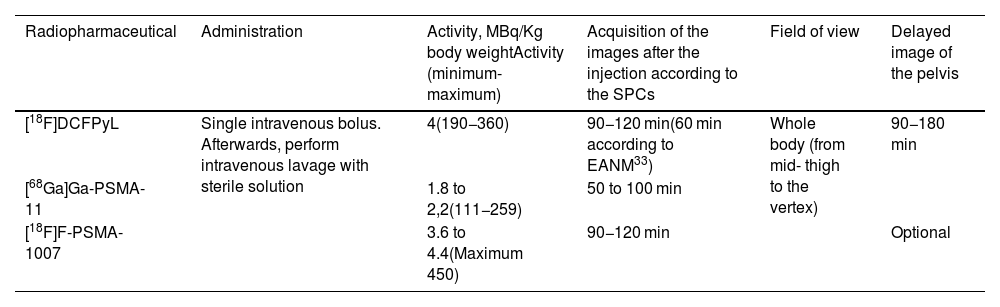
Radiopharmaceuticals such as [18F]DCFPyL and [68Ga]Ga-PSMA-11 require reconstitution and radioactive labeling prior to intravenous administration, adjusting the dose according to patient body weight and the type of PET applied. Table 2 shows the different protocols of administration of the radiopharmaceuticals used in PSMA PET/CT.
Comparison of the protocols of administration and acquisition of images for PSMA-PET radiotracers. EANM: European Association of Nuclear Medicine; SPCs: Summary of product characteristics.
| Radiopharmaceutical | Administration | Activity, MBq/Kg body weightActivity (minimum-maximum) | Acquisition of the images after the injection according to the SPCs | Field of view | Delayed image of the pelvis |
|---|---|---|---|---|---|
| [18F]DCFPyL | Single intravenous bolus. Afterwards, perform intravenous lavage with sterile solution | 4(190−360) | 90−120 min(60 min according to EANM33) | Whole body (from mid- thigh to the vertex) | 90−180 min |
| [68Ga]Ga-PSMA-11 | 1.8 to 2,2(111−259) | 50 to 100 min | |||
| [18F]F-PSMA-1007 | 3.6 to 4.4(Maximum 450) | 90−120 min | Optional |
The patient should be supine with their arms above the head to avoid truncation artifacts in the CT component, with the field of view being from the mid-thigh to the vertex. In addition, inclusion of the extremities in the study is considered based on the clinical symptoms presented and/or previous findings.
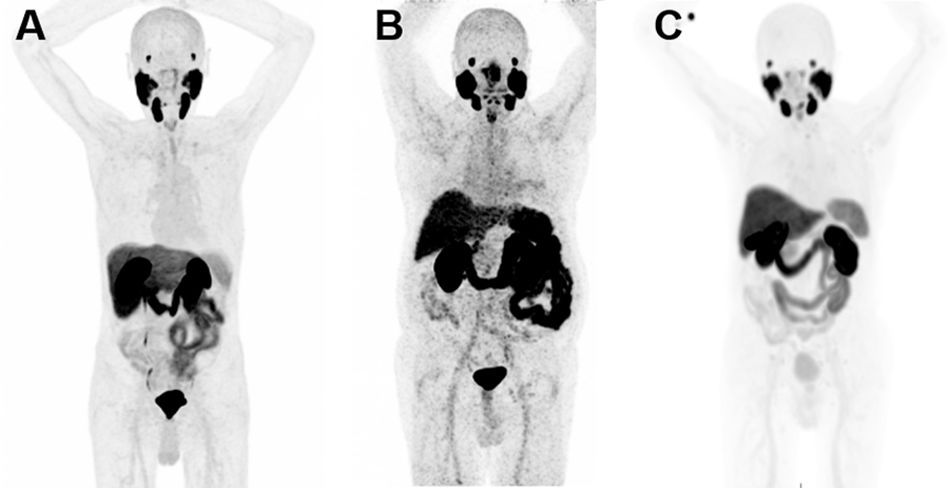
In image acquisition, the use of radiopharmaceuticals, such as [18F]DCFPyL, [68Ga]Ga-PSMA-11 and [18F]F-PSMA-1007, require an ideal period of time after the injection to optimize radiotracer uptake and visualization of lesions. The specific protocols for each radiopharmaceutical are shown in Table 2. Fig. 5 shows minimum intensity projection (MIP) images with the three radiopharmaceuticals.
[18F]DCFPyL and [68Ga]-Ga-PSMA-11
Since these two radiopharmaceuticals are eliminated by the urinary system, obtainment of early dynamic images made during the first eight minutes after the administration of the radiopharmaceutical may be useful, although this is left to the discretion of each center. This approach may be of interest in patients previously treated with RP in whom a frequent site of recurrence is localized in the ureterovesical anastomosis. It is sometimes difficult to distinguish these foci of recurrence due to the proximity of the urinary elimination of the radiopharmaceutical. In this scenario, the performance of a dynamic study may help localize tumoral foci in the prostatic bed before there is accumulation of the radiopharmaceutical at the vesical level.
The CT component of the study should provide images of diagnostic quality and attempt to minimize the radiation dose to the lowest possible. CT can be performed with endovenous contrast. In this sense, the use of 50 ml of intravenous contrast 10−15 min before initiating the acquisition of the standard study allows accurate identification of lymph nodes close to the ureters and evaluation of any change in the urethral pathway that may occur after RP.
The whole body imaging protocol in the PET/MR study methodology integrates DIXON sequences for the correction of attenuation, as well as morphological (T1, T2, short tau inversion recovery) and functional sequences (apparent diffusion coefficient) to provide detailed characterization of the tissues. For selective examination of the pelvic region, a multiparametric prostatic MR that includes T1 and T2 sequences, studies of diffusion and post-contrast sequences with gadolinium, which are personalized according to the specific objectives of the study, are added to the DIXON sequences for correction of attenuation.34,35
[18F]PSMA-1007In this type of study the greatest tumoral uptake is visualized between 1−3 hours after administration of the radiotracer. Although obtainment of delayed pelvic images is considered optional, they are not often needed due to the minimal urinary excretion of the radiotracer, which also reduces the relevance of the use of diuretics. To complement the PET component, a CT or MR study is simultaneously performed, which facilitates correction of attenuation, applying identical protocols to those used for the [18F]DCFPyL and [68Ga]Ga-PSMA-11 radiotracers.36
PET/CT studiesFor the reconstruction of images, it is recommended to use an iterative method complemented with time of flight (TOF) technology. Although each image device may have its optimal protocol, especially in comparisons between digital and analogic equipment, it is recommended to follow the specifications proposed by each manufacturer. Likewise, it is suggested to use a reconstruction matrix of 256 × 256 pixels or greater to ensure the optimal image quality and resolution.
For correct interpretation of the images, it is fundamental to know the physiological distribution of the radiopharmaceutical as well as its ranges of normality and possible causes of false positives.
Normal distribution of the radiopharmaceutical with urinary excretion ([18F]F-DCFPyL and [68Ga]Ga-PSMA-11) usually includes:
- •
The kidneys, which show significant uptake specifically in the proximal convoluted tubule and secondary to the time of its elimination by the urinary system, being the organ with the greatest effective dose.
- •
Urinary elimination of the radiopharmaceutical through the ureters, bladder and urethra can make image interpretation difficult in the pelvic lymph node regions as well as in the prostate or prostatic bed after RP.
- •
The salivary and lacrimal glands show significant individual variability, showing intensities that vary in the order of the parotid, submandibular, lacrimal and sublingual, and finally, extending to the mucosa.
- •
In contrast to other solid organs, the liver present less variability. [18F]DCFPyL has slightly greater uptake compared to [68Ga]Ga-PSMA-11, but less uptake than other fluorinated PSMA tracers, except [18F]PSMA-1007.
- •
The spleen is another organ that presents high individual variability in radiotracer uptake.
- •
In the case of the duodenum, there is greater uptake in the proximal region and mainly in the intestinal villi.
- •
The intensity of uptake in the blood vessels is moderate, except during the first minutes after administration. The muscles and the bone marrow also present uptake of moderate intensity, except if there is underlying disease.
- •
Lastly, in the prostate, physiological glandular and benign disease (such as prostatic hypertrophy and prostatitis) uptake of the radiopharmaceutical is considerably lower in comparison to that observed in PC.
The distribution and elimination of the radiopharmaceutical can present patterns of uptake which, albeit normal, require careful interpretation for differentiation from pathological signs:
- •
Esophageal, laryngeal, gastric and tracheobronchial tree uptake: salivary elimination may induce activation of these zones.
- •
Hepatobiliary elimination: activity in the biliary tree is observed.
- •
Variability in pancreatic uptake: the intensity of uptake in the pancreas may fluctuate due to the natural presence of PSMA in the islets of Langerhans, a phenomenon that must not be confounded with tumoral pathology.
- •
Gynecomastia: this phenomenon may manifest as increased uptake in male breast tissue.
- •
Uptake in sympathetic lymph nodes: the visualization of sympathetic lymph nodes, including the stellate, celiac, hypogastric and presacral lymph nodes may be variable and tend to be more notable in tomographs equipped with TOF or digital systems.
The uptake of a radiopharmaceutical with marked hepatobiliary excretion and discrete urinary excretion ([18F]PSMA 1007) is intense in the salivary glands, especially the parotids and submaxillary glands, as well as the kidneys. Despite significant renal retention of the tracer, its elimination in urine is notably reduced, being only 1.2%, 0.7% and 0.5% at the time intervals of 0–2, 2–4 y and 4–6 h, respectively.37 The low level of urinary excretion results in less accumulation in the bladder, thereby reducing the dosimetry in this organ compared to other PSMA tracers. The uptake is moderate in lacrimal glands, the liver, spleen and intestine. Notable hepatobiliary excretion of [18F]PSMA 1007 may lead to elevated observable activity in the gallbladder.
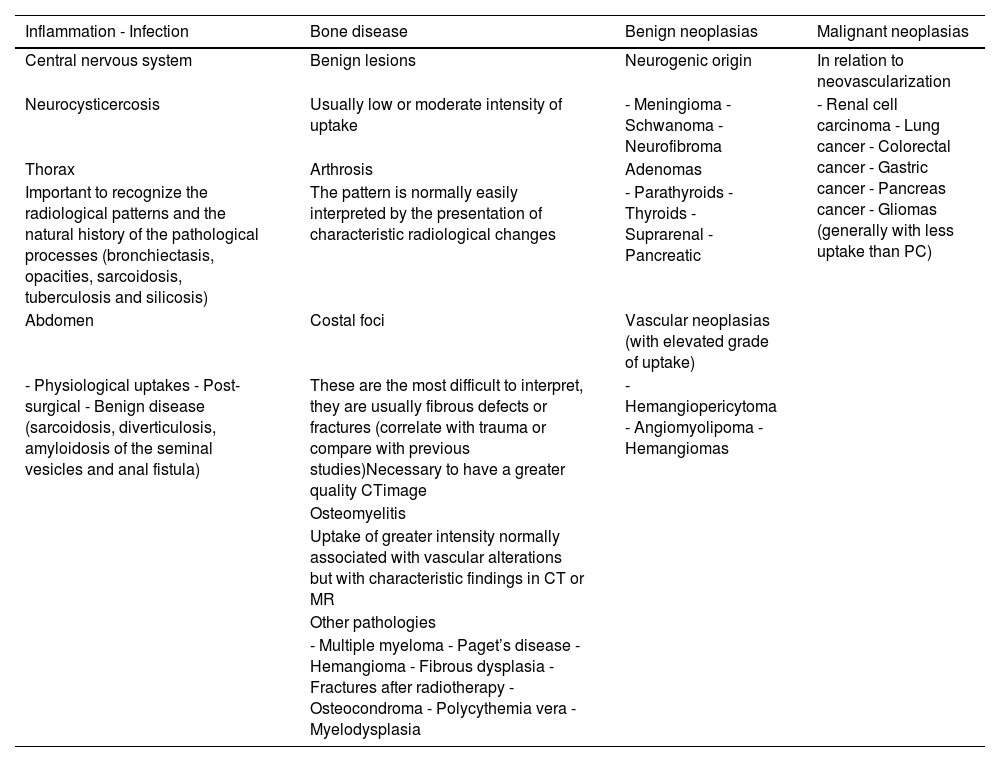
In general, the potential sources of false positives that can be found with radiopharmaceuticals are shown in Table 3. These sources include different anatomical localizations in which non-neoplastic uptake of the tracer may be misinterpreted as indicative of disease.
Main causes of false positive results with PSMA radiopharmaceuticals.
| Inflammation - Infection | Bone disease | Benign neoplasias | Malignant neoplasias |
|---|---|---|---|
| Central nervous system | Benign lesions | Neurogenic origin | In relation to neovascularization |
| Neurocysticercosis | Usually low or moderate intensity of uptake | - Meningioma - Schwanoma - Neurofibroma | - Renal cell carcinoma - Lung cancer - Colorectal cancer - Gastric cancer - Pancreas cancer - Gliomas (generally with less uptake than PC) |
| Thorax | Arthrosis | Adenomas | |
| Important to recognize the radiological patterns and the natural history of the pathological processes (bronchiectasis, opacities, sarcoidosis, tuberculosis and silicosis) | The pattern is normally easily interpreted by the presentation of characteristic radiological changes | - Parathyroids - Thyroids - Suprarenal - Pancreatic | |
| Abdomen | Costal foci | Vascular neoplasias (with elevated grade of uptake) | |
| - Physiological uptakes - Post-surgical - Benign disease (sarcoidosis, diverticulosis, amyloidosis of the seminal vesicles and anal fistula) | These are the most difficult to interpret, they are usually fibrous defects or fractures (correlate with trauma or compare with previous studies)Necessary to have a greater quality CTimage | -Hemangiopericytoma - Angiomyolipoma - Hemangiomas | |
| Osteomyelitis | |||
| Uptake of greater intensity normally associated with vascular alterations but with characteristic findings in CT or MR | |||
| Other pathologies | |||
| - Multiple myeloma - Paget’s disease - Hemangioma - Fibrous dysplasia - Fractures after radiotherapy - Osteocondroma - Polycythemia vera - Myelodysplasia |
Before evaluating the images of a nuclear medicine study, it is important to verify that the procedure has been done correctly, revising essential parameters, such as the administered activity of the radiopharmaceutical, the time of distribution, the acquisition times, the specifications of the CT component, and the administration of contrast. In addition, it is necessary to check that the processing of the images is adequate, including the correction of true/randoms, TOF, correction of attenuation and the reconstruction method used.
The presentation of the images is also fundamental, since it reflects the quality of the study. Thus, the presentation should be standardized to maintain coherence, and this includes the processing station, the display, color scale and window levels.
Revision of the studies should be meticulous and systematic, including analysis of the MIP image, the PET (corrected and uncorrected), CT (in different windows) and the fusion PET/CT in the three planes. Evaluation of the findings is done visually using a scale based on the intensity of PSMA expression.38 The intensity of uptake is classified in a scale from 0 to 3, based on comparison with anatomical reference structures (Table 4):
Score for evaluating the intensity of PSMA expression. For radiopharmaceuticals with predominantly hepatic excretion, such as [18F]PSMA 1007, splenic uptake should be considered instead of hepatic uptake.
| Score | PSMA expression | Uptake |
|---|---|---|
| Score 0 | No | Less than or equal to the vascular pool |
| Score 1 | Low | Less than or equal to the liver and greater than the vascular pool |
| Score 2 | Intermediate | Less than or equal to the parotid gland and greater than the |
| Score 3 | HIgh | Greater than the parotid gland |
The report is a bidirectional act of communication between the clinician and the nuclear medicine specialist. The clinician must provide relevant clinical information and the specific question. In the performance of the exploration, the nuclear medicine physician must answer this question with a clear, concise, complete and clinically relevant response.
The fundamental parts that a report must have are:
- •
Data of the patient: include basic information such as name, date of birth, sex and identifying code. It should also include the measures of radioprotection, allergies and informed consent.
- •
Data related to the procedure: details of the center, the physician, the name of the procedure, date of the study and the report.
- •
Relevant clinical history: initial staging: date of diagnosis, result of the biopsy/definitive histology, Gleason score, PSA value, previous imaging tests, comorbidities. RB: treatment performed, initial PSA; nadir PSA, current PSA and PSA kinetics, imaging tests performed and comorbidities.
- •
Description of the procedure: specifications of the radiopharmaceutical used (name, activity administered, administration site). Imaging technique: time from radiotracer injection until image acquisition, use of diuretic (if used, specify dose), parameters of PET reconstruction, CT data (correction of attenuation, diagnosis, intravenous contrast used) as well as the acquisition or not of delayed images.
- •
Findings: evaluation of the quality of the study (findings, artifacts that may compromise quality), description of the physiological distribution of the radiopharmaceutical, pathological findings (localization, extension, visual or quantified uptake) and comparison with previous studies.
- •
Diagnostic impression: interpretation of the findings in relation to the clinical consultation, identification of a normal or pathological study: it is recommended to give a definitive diagnosis (local disease, lymph node, bone visceral involvement).
- •
Provide alternative or possible differential diagnoses.
- •
Recommend other explorations: in some circumstances or even carry out another control to clarify the findings.
- •
Indicate the limitations of the study.
- •
Presentation of the images: include the original images, the processed images of the findings described.
To ensure reproducibility and accuracy, a standardized report is proposed, especially for the interpretation of the PSMA-PET studies. This includes classification of the foci of uptake by visual evaluation (the foci of uptake should be classified by comparison with the activity in the target organs and the use of a system similar to radiological studies (BI-RADS, LI-RADS, PI-RADS) called Prostate-specific Membrane Antigen Reporting and Data System (PSMA-RADS 2.0),39 which allows establishing a reliable evaluation into 5 categories, as per consensus with the clinicians:
- •
PSMA-RADS 1 (Benign): Although these lesions may show PSMA uptake, they are recognized as benign based on their pathognomonic appearance in anatomical imaging studies or by histological confirmation following biopsy.
- •
PSMA-RADS 2 (Probably benign): Equivocal uptake (focal, but of low intensity such as the vascular pool) in an area of atypical PC involvement of soft tissue (i.e., axillary or hilar lymph nodes) or equivocal uptake in an atypical PC bone lesion involvement (i.e., uptake in bone lesion and high suspicion of being degenerative or of another benign etiology).
- •
PSMA-RADS 3 (Equivocal): PSMA -RADS 3A: Equivocal uptake in typical PC sites at the level of small lymph nodes with focal, albeit low, uptake. PSMA-RADS 3B: Equivocal uptake in bone with focal uptake that could represent metastasis. PSMA-RADS 3C: Intense uptake in atypical localization, except in patients with advanced PC, requiring differential diagnosis with other types of tumoral lesions by biopsy. PSMA-RADS 3D: Includes all the abnormal and suspicious lesions that do not show PSMA uptake.
- •
PSMA-RADS 4 (Probably malignant): Intense uptake in typical PC site, but without confirmation in conventional images. Given the elevated specificity of PSMA, biopsy is not required.
- •
PSMA-RADS 5 (Malignant): Intense uptake in typical PC site, with confirmation in conventional images. Given the elevated specificity of PSMA, biopsy is not required. PSMA-RADS 5 T (T for treatment): Includes previously identified metastasis or malignant lesions that have undergone specific treatment.
The Prostate Cancer Molecular Imaging Standardized Evaluation (PROMISE)38 criteria have also been proposed for optimizing the description and organization of the findings in the molecular imaging of PC. These criteria include a specific TNM system for molecular imaging (miTNM) that improves the accuracy and reliability of the findings. This approach is particularly useful for the inclusion of patients in clinical trials, allowing standardized and detailed evaluation of disease extension based on advanced imaging techniques.
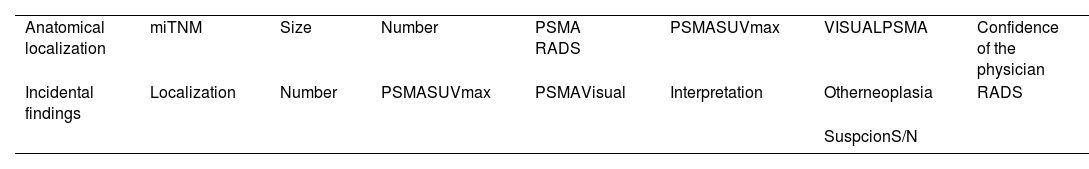
To optimize the structure of the report, it is recommended to use a template40 (Table 5) which includes the clinical history of the patient, technical details of the procedure and a meticulous description of the findings, classified by their anatomical localization and accompanied by a visual evaluation, PSMA-RADS and, when applicable, miTNM. The conclusion of the report should include a reliable scale of evaluation, thereby ensuring clear and detailed reporting of the results, following the assessment below:
- •
Score 1: Benign lesion without PSMA uptake.
- •
Score 2: Probably benign lesion, mild uptake (≤ blood pool) in an atypical PC site.
- •
Score 3: Doubtful finding of mild uptake in a typical PC site or intense uptake in an atypical PC site.
- •
Score 4: Probable PC, intense uptake in a typical PC site but without clear findings in the CT.
- •
Score 5: Definitive PC, intense uptake in a typical PC site, with clear findings in the CT.
The introduction of PSMA-PET has been a turning point in the diagnosis and management of PC, particularly in the contexts of BR and biochemical persistence following intention to cure therapies. This document analyzes the evidence available and the clinical experience for evaluating the efficacy of this imaging modality, demonstrating its superiority in the detection of occult disease, especially at low PSA levels, representing a considerable advantage over conventional imaging techniques.
The capacity of PSMA-PET for identifying lesions at low PSA levels, contrasts notably with the limited efficacy of MR and CT, which have a significantly diminished sensitivity at PSA levels < 0.2 ng/mL. In this sense, the PRIMARY41 study is emblematic and demonstrates that the combination of PSMA-PET and MR significantly improves the sensitivity and negative predictive value for the detection of localized PC, with a notable improvement in the identification of adequate sites for taking biopsy samples.
Moreover, the ProPSMA4 and OSPREY11 studies have demonstrated the superiority of PSMA-PET in initial staging and the detection of pelvic lymph node and distant metastasis in comparison with CT and BSc, respectively. These results are promising since they potentiate the development of precision medicine in which exact identification of the stage of the disease is fundamental for therapeutic management.
The systematic review by Chow et al.,42 provides a direct comparison between PSMA-PET and conventional imaging techniques, demonstrating clear superiority of the former, allowing the detection of lymph node metastasis with a significantly higher specificity and sensitivity. This evidence emphasizes the important role of PSMA-PET in the redefinition of tumoral load and disease volume. These are key predictors of response to treatment and patient survival.
In view of this panorama, the implications for clinical practice are clear. PSMA-PET not only improves diagnostic accuracy, but also allows more individualized management of PC, facilitating more effective and less invasive therapeutic strategies, such as ADT in patients with oligometastatic disease.
Looking towards the future, prospective and randomized clinical studies must continue to evaluate the impact of PSMA-PET on clinical results, including overall survival and quality of life. In addition, its integration with new therapeutic modalities, such as poly (ADP ribose) polymerase inhibitors (olaparib and rucaparib) and immunotherapy agents, is a promising field of investigation which could lead to more effective and personalized treatment strategies for advanced PC.
In conclusion, PSMA-PET is becoming established as an indispensable tool in the arsenal against PC, allowing not only greater diagnostic accuracy but also opening new therapeutic pathways based on precise localization and disease load.
FundingAdvanced Accelerator Applications Ibérica S.L.U. (ADACAP) has collaborated as a sponsor of the project from which this publication originated.
ADACAP has not participated in any way in the content of this publication, which has been developed independently by the authors.
Conflicts of interestJose Muñoz-Iglesias: Declares that he has received honoraria as a speaker in training activities promoted by Bayer, Johnson&Johnson, Astellas, AAA, Novartis company, Roche and Takeda, and for his participation in advisory boards promoted by AAA, Novartis company and Bayer.
Antonio Rodríguez-Fernández: Declares that he has received fees as a speaker in training activities promoted by Astellas, AAA, a Novartis company, Curium Pharma, Siemens, Boston Scientific, Janssen and Johnson&Johnson company and for his participation in the advisory boards promoted by AAA, a Novartis company.
Pilar Paredes: Declares having received honoraria as speaker in training activities promoted by Bayer, Astellas, AAA, a Novartis company, Janssen, a Johnson&Johnson and for the participation in advisory boards promoted by AAA, a Novartis company.
Macarena Rodríguez-Fraile: Declares that she has received honoraria as a speaker in training activities promoted by Astellas, AAA, Novartis company and Janssen, a Johnson&Johnson company.
Adolfo Gómez: Declares that he has received honoraria as a speaker in training activities promoted by Bayer, Johnson&Johnson, Astellas, AAA, Novartis, Bayer, GSK and GE.
Marc Simó: Declares that he has received fees as a speaker in training activities promoted by Astellas, AAA, Novartis company and Johnson & Johnson.
Joan Castell: Declares that he has no conflict of interest.
We would like to thank Luzán CINCO Health Consulting for their technical and methodological support for the development of this collaboration. Also Dr. Rosa Rojo (ScarletMed, Madrid) for her support as medical writer for the development of this medical writer for the development of this article.


