


This article critically reviews the available evidence on the role of PSMA-PET in evaluating therapeutic response in metastatic prostate cancer (mPC), comparing it with conventional criteria —serum PSA levels, Response Evaluation Criteria in Solid Tumours (RECIST 1.1), Prostate Cancer Working Group 3 (PCWG3)— and analyzing its integration into clinical practice. It addresses the biological basis of PSMA and how different treatments —androgen deprivation therapy (ADT), androgen receptor pathway inhibitors (ARPI), taxanes, [¹⁷⁷Lu]Lu-PSMA-617, [²²³Ra], stereotactic body radiotherapy (SBRT)— modulate its expression, which influences image interpretation and phenomena such as flare.
This work describes specific assessment systems for PSMA-PET, including PSMA PET Progression Criteria (PPP), Response Evaluation Criteria in PSMA (RECIP 1.0), and EAU/EANM criteria, highlighting their superior prognostic value compared to RECIST and PCWG3, especially in metastatic castration-resistant prostate cancer (mCRPC). RECIP 1.0, initially validated for [¹⁷⁷Lu]Lu-PSMA-617, has demonstrated robust correlation with overall survival and interobserver reproducibility, improving risk stratification when combined with PSA. Quantitative parameters such as PSMA-VOL and TLP, key biomarkers for monitoring response and predicting outcomes, are analyzed.
Furthermore, the evidence is reviewed by therapeutic modality, proposing practical recommendations on the optimal timing for PSMA-PET (baseline, intermediate, or delayed depending on treatment) and the need for standardized reporting (PROMISE, E-PSMA). The article also identifies current limitations: variability among radiopharmaceuticals, a lack of universal criteria, a scarcity of prospective studies, and challenges in multimodal integration with PSA and other biomarkers.
El presente artículo revisa de forma crítica la evidencia disponible sobre el papel de la PET-PSMA en la evaluación de respuesta terapéutica en el cáncer de próstata metastásico (CPm), comparándola con los criterios convencionales —niveles de PSA sérico, Criterios de Evaluación de Respuesta en Tumores Sólidos (RECIST 1.1), Prostate Cancer Working Group 3 (PCWG3)— y analizando su integración en la práctica clínica. Se aborda la base biológica del PSMA y cómo diferentes tratamientos —terapia de privación de andrógenos (TDA), inhibidores de la vía del receptor de andrógenos (ARPI), taxanos, radioligandos [¹⁷⁷Lu]Lu-PSMA-617, [²²³Ra], radioterapia corporal estereotáctica (SBRT)— modulan su expresión, lo que condiciona la interpretación de la imagen y fenómenos como el flare.
El trabajo describe los sistemas de valoración específicos para la PET-PSMA, incluyendo los Criterios de Progresión PET-PSMA (PPP), Criterios de Evaluación de Respuesta en PSMA (RECIP 1.0) y criterios EAU/EANM, destacando su superioridad pronóstica frente a RECIST y PCWG3, especialmente en cáncer de próstata resistente a la castración metastásico (CPRCm). RECIP 1.0, validado inicialmente para [¹⁷⁷Lu]Lu-PSMA-617, ha demostrado correlación robusta con la supervivencia global y reproducibilidad interobservador, mejorando la estratificación del riesgo cuando se combina con el PSA. Se analizan parámetros cuantitativos como PSMA-VOL y TLP, biomarcadores clave para monitorizar respuesta y predecir desenlaces.
Además, se revisa la evidencia por modalidad terapéutica, proponiendo recomendaciones prácticas sobre el momento óptimo para realizar PET-PSMA (basal, intermedio o diferido según tratamiento) y la necesidad de informes estandarizados (PROMISE, E-PSMA). El artículo también identifica limitaciones actuales: variabilidad entre radiofármacos, falta de criterios universales, escasez de estudios prospectivos y retos en la integración multimodal con PSA y otros biomarcadores.
Evaluation of response in metastatic prostate cancer (mPC) continues to be predominantly based on serum prostate-specific antigen (PSA) levels and conventional imaging with computerized tomography (CT) and bone scintigraphy. However, these techniques have known limitations: low sensitivity for small volume disease, difficulty in adequately characterizing bone metastasis, or the flare phenomenon which may mask real response. On the other hand, they do not consider the biological heterogeneity or the forms with minimum PSA secretion.1–3
Expansion of the therapeutic arsenal in advanced disease has strengthened the need for quantitative and reproducible imaging biomarkers that allow better patient selection and early monitoring of treatment efficacy. In this scenario, prostate-specific membrane antigen-positron emission tomography (PSMA-PET) has gone from being a fundamental technique in initial staging, the detection of biochemical relapse and the selection of candidates for targeted therapy to accumulating increasingly more robust evidence on the evaluation of response, with semiquantitative parameters and specific criteria, demonstrating prognostic value and contributing to a most precise stratification of risk.4–7
The joint guidelines of the European and American Societies of Nuclear Medicine (EANM/SNMMI) published in 2023, explicitly recognize the potential of PSMA-PET for monitoring therapeutic response in prostate cancer (PC), although standardized application still requires additional prospective validation.8
In this context, the aim of the present article was to critically review the utility of PET-PSMA in the evaluation of response to the different treatment modalities in mPC, analyze its strengths and limitations versus conventional criteria and also propose practical recommendations of clinical use and integration in multidisciplinary interpretation.
Biological foundation and therapeutic effects on PSMABiological foundation of PSMAPSMA, also known as glutamate carboxypeptidase II (GCPII), is a transmembrane glycoprotein type II that is highly conserved and is involved in multiple cellular processes. Its structure is made up of a short intracytoplasmatic domain, a hydrophobic transmembrane segment and a wide extracellular domain with a catalytic site dependent on zinc, essential for its enzymatic function.9–11
In normal tissue, PSMA is mainly expressed in the prostatic epithelium, although it is also localized in a lesser proportion in the proximal renal tubule, choroid plexus, salivary glands and intestinal epithelium.10
In PC the FOLH1 gene that codifies PSMA shows epigenetic and transcriptional alterations that favor progressive overexpression as the disease advances. 11,12 PSMA expression is correlated with multiple indices of tumor aggressiveness, including a high Gleason score, elevated tumoral load, perineural infiltration and the presence of systemic metastasis, and is established as a phenotypic marker of progression.11
In addition, PSMA is also expressed in the neovascular endothelium of solid tumors where it contributes to cellular adhesion, invasion and signaling, favoring tumoral survial.11,13
Therapeutic modulation of PSMA expression and uptakeAndrogen deprivation therapy (ADT) and androgen receptor pathway inhibitors (ARPIs)Overexpression of the gene that encodes the PSMA has an inverse relationship with signaling of the androgenic receptor (AR): the activation of the AR represses the transcription of FOLH1 while pharmacological inhibition with ADT or ARPIs triggers an initial compensatory increase in PSMA expression during the first 2–4 weeks. This phenomenon, known as flare, explains the greater uptake of PSMA ligands after initiating androgenic blockades and the elevated expression observed in castration-resistant disease. Nonetheless, this should be interpreted with caution since elevated uptake may not be correlated with clinical or biochemical progression. After the first month, AR targeted therapies usually produce a progressive decrease in the standardized uptake value (SUV) and PSMA tumoral volume in hormone-sensitive tumors and remain elevated in those resistant to castration.12–14
Chemotherapy with taxanesThe reduction in PSMA uptake following chemotherapy with taxanes is mainly attributed to a decrease in tumoral load as a consequence of its cytotoxic effect and not to a negative regulation of the PSMA receptor. Thus, PSMA-PET should be interpreted as an indirect marker of the quantity of viable tumor more than as a reflection of molecular regulation of the receptor.15
Therapy with [177Lu]Lu-PSMA-617This therapeutic agent combines two components: a ligand targeting PSMA and the radioisotope lutetium-177. The ligand binds to the PSMA expressed on the surface of the tumoral cells, internalizes and the beta radiation emitted by the radionuclide produces irreparable damage to the DNA, leading to cell death by apoptosis or necrosis. PSMA-PET in responder patients shows a decrease in the SUV and tumoral volume, reflecting the direct cytotoxic effect of the radionuclide. The persistence of foci with uptake may indicate viable lesions, while the appearance of new lesions without avidity for the radiopharmaceutical suggest progression mediated by clones with low or null PSMA expression.16
[223Ra]Radium-223 dichloride (223Ra) is an alpha emitter that acts on the tumor bone microenvironment promoting bone remodeling independently of PSMA expression. This characteristic explains the possible discordance between the uptake observed in PSMA-PET and the bone markers such as alkaline phosphatase (AP). In responder patients, a reduction in AP may be observed while PET-PSMA remains stable or even increases, indicating that both parameters evaluate different biological processes.17
Imaging protocols and quantification parametersProtocol of PET/CT acquisition with PSMA ligandsThe acquisition of PET/CT with PSMA ligands should follow strictly standardized protocols to ensure their reproducibility, especially in scenarios of therapeutic response. The radiopharmaceuticals most frequently used in clinical practice are [68Ga]Ga-PSMA-11, [18F]F-PSMA-1007 and [18F]F-DCFPyL. All have good performance for the detection of metastatic disease. However, their profiles of excretion and biodistribution affect interpretation. For example, [18F]F-PSMA-1007, with minimum urinary elimination,18 facilitates evaluation of the prostatic bed, but produces more unspecific bone uptake (osteophytes, fractures, hemangiomas), particularly in the ribs and pelvis, requiring expert interpretation and rigorous use of PROMISE to avoid over staging.
For therapeutic monitoring, the EANM/SNMMI 2.0 guidelines and recent revisions recommend maintaining the same radiopharmaceutical between studies.
Robust quantification requires consistent reconstructions, cross PET/activimeter calibration and registry of changes in hardware or software. Multicentric studies demonstrate that small technical variations may significantly modify the total tumoral volume of lesions with avidity for PSMA (PSMA-VOL), the total PSMA-positive lesions (TPL) or the SUVmean, among others, highlighting the importance of intercenter harmonization.5,19
Quantification parametersAlthough the most universally used parameter of quantification is the SUVmax, it has inherent limitations (noise, reconstruction and dependence on a single voxel). To the contrary, the SUVmean provides better representation of the global expression of PSMA and more consistently predicts response to [177Lu]Lu-PSMA-617.20
PSMA-VOL measures tumoral load in terms of volume. It is obtained by segmentation of all the lesions with pathological uptake in PSMA-PET, applying recommended thresholds of SUV and using dedicated software (MIM, syngo.via, Hermes, ROVER).
The TPL measures the tumoral load considering both the volume and its activity (PSMA-VOL × SUVmean or SUVpeak).21
Different studies have demonstrated that these parameters are significantly correlated with overall survival, making them relevant prognostic biomarkers.1,2,22 In addition, they have shown to predict the response to taxanes15,21 and monitor therapy with [223Ra].17
The total lesion quotient (TLQ lesion) and the Tumor-to-Salivary Gland Ratio (PSG score) are emerging as integrated biomarkers: the first combines volume-intensity-distribution for characterizing intratumoral heterogeneity and the second normalizes tumoral uptake with respect to the parotid gland. Although the PSG score may be associated with better response to [177Lu]Lu-PSMA-617, neither has yet to have definitive validation or standardized thresholds and they remain under investigation.20
Finally, from an organizational perspective, the availability of solid, validated and accessible software is not a technical aspect but rather a structural requisite for guaranteeing reproducible segmentations, reducing the variability and allowing the quantitative biomarkers to be safely implemented in clinical practice.
Key point: Standardization of the protocols of acquisition and quantification in PSMA-PET, including the consistent use of volumetric biomarkers and activity (PSMA-VOL, TPL and SUVmean), is essential to ensure reproducibility, intercenter comparability and reliability in the evaluation of therapeutic response.
The Response Evaluation Criteria in Solid Tumours (RECIST) criteria are the international standard for evaluating response to treatment in solid tumors by morphological imaging, mainly CT with contrast.23 These criteria are adequate for soft tissues but present limitations in the evaluation of bone lesions, except in those that are lithic or mixed that include a component of measurable soft tissue.
Measurable lesions are tumors with a diameter ≥10 mm in CT (slices ≤5 mm) and malignant lymph nodes with a short axis ≥15 mm. To the contrary, non-measurable lesions are those that are < 10 mm, lymph nodes of between 10 and 14 mm as well as leptomeningeal disease, ascites, pleural effusions, lymphangitis and visceromegalies.
For follow-up, up to a maximum of five target lesions are selected (with a maximum of two per organ), prioritizing those of greater size and reproducibility. The lymph nodes are only included if the short axis is ≥15 mm. The sum of the diameters is the reference for evaluating response, considering the greatest diameter in non-lymph node lesions and the smallest diameter in lymph nodes.
The criteria of tumoral response are the following:
- •
Complete response (CR): total disappearance of the target lesions and reduction of pathological lymph nodes to <10 mm.
- •
Partial response (PR): reduction of ≥30% in the sum of diameters.
- •
Disease progression (DP): increase ≥20% in the sum of diameters, absolute increase ≥5 mm or the appearance of new lesions.
- •
Stable disease (SD): absence of criteria for PR or DP.
Although confirmation may not be obligatory in clinical practice, in clinical trials it is recommended to verify CR and PR with a second evaluation at least four weeks later.
PCWG3The Prostate Cancer Working Group 3 (PCWG3) has established recommendations for evaluating response to treatment in patients with metastatic castration-resistant PC (mCRPC) especially in clinical trials.24 These criteria integrate tumoral progression, clinical symptoms and biomarkers such as PSA, differentiating radiological progression from the clinical decision to suspend treatment.
In clinical practice and investigation, it is recommended to perform a thoracoabdominal CT with contrast (slices ≤5 mm) and a bone scintigraphy, which are standard techniques for evaluation of metastasis. Radiological evaluation follows the RECIST 1.1 criteria, with specifications: the lymph nodes are measurable if the short axis is ≥1.5 cm; nodes between 1.0 and 1.5 cm are considered non-measurable. Lymph node progression is defined as a growth ≥5 mm with respect to nadir and reaching ≥1.0 cm if they are normal. Visceral metastases must be reported per organ and are measurable if the greatest diameter is ≥1 cm.
For bone metastases the 2 + 2 rule is applied. This rule was designed to avoid confusing the flare phenomenon with real progression. Progression is only considered if ≥2 new lesions appear in the first post-treatment scintigraphy and are confirmed in a second scintigraphy with at least two additional lesions. If not confirmed, the first exploration is redefined as the new basal.
The frequency of explorations should be adjusted to minimize errors: every 8–9 weeks during the first 24 weeks and every 12 weeks thereafter, and every 16 weeks in non-metastatic CRPC (nmCRPC). The radiological report should describe the evolution by each site (bone, pelvic and extrapelvic lymph nodes, viscera) indicating whether the progression is due to growth, new lesions or both.
The transition from nmCRPC to mCRPC is defined by the appearance of an unequivocal new bone lesion or measurable viscera, confirmed according to the 2 + 2 rule. Mixed responses do not imply therapeutic failure. Global revision, possible biopsy and consideration of clinical and biological criteria are recommended.
Finally, the No Longer Clinically Benefiting (NLCB) concept underlines that radiological progression does not automatically determine treatment suspension. This may be maintained if there are symptomatic benefits, absence of clinical deterioration and locally treatable limited progression.25,26
Although PCWG3 does not formally include PSMA-PET, recent studies, such as the PRINCE trial,27 have proposed criteria based on this technique, defining progression as the appearance of two new positive lesions confirmed in posterior controls, without considering only the increase of the SUV due to risk of a metabolic flare.26
Criteria of response with the application of PSMA-PETDifferent specific criteria of response for PSMA-PET have been proposed.
Criteria of PSMA-PET progression (PPP)These were the first specific criteria for the evaluation of progression based on PSMA-PET. They are based on the variation of the number, size or uptake of PSMA (SUVmax) of the lesions as well as clinical (ECOG) and laboratory data (PSA levels before and after treatment, lactate dehydrogenase [LDH] and AP).
The PPP criteria are simple and reproducible. In addition, they define progression as any of the three following scenarios28:
- (a)
Appearance of two or more new distant PSMA-positive lesions.
- (b)
Appearance of a new PSMA-positive lesion in addition to consistent clinical and/or laboratory data. Nonetheless, confirmation of the findings by biopsy or correlative images in following three months after the PSMA-PET is recommended.
- (c)
Absence of new lesions, but an increase > 30 % in size or uptake in addition to coherent clinical or laboratory data. Confirmation by biopsy or correlative images are recommended in the following three months after the PSMA-PET.
Since these criteria are based on registered lesions, they are of special interest in cases of oligometastatic or limited systemic diseases. In addition, these criteria provide diagnostic information, distinguishing local from distant progression.29 Nonetheless, in cases of elevated tumoral load in the basal study, there is a risk of misinterpretation of small new lesions by PPP criteria in the post-treatment PSMA-PET.
EAU/EANM criteriaAn international panel of experts convened in 2021 by the European Association of Urology (EAU) and the EANM established criteria of evaluation of response by PSMA-PET in mPC.30
The consensus established that PSMA-PET may be used before and after any local or systemic treatment, provided that the results can modify clinical management. Nonetheless, routine use in localized disease is not recommended in patients with good biochemical response or in advanced stages without therapeutic options. To avoid errors due to the flare phenomenon, it is recommended to perform the exploration at least 3 months after the initiation of hormone therapy.
The criteria proposed classify the patients as responders (CR, PR or stable disease) and non-responders (progression) including, for the first time, the use of tumoral volume by PSMA-PET as a measure of therapeutic response:
- •
Complete response: disappearance of all uptake.
- •
Partial response: >30% reduction in tumoral volume or uptake.
- •
Stable disease: ≤30% of changes without new lesions.
- •
Disease progression: appearance of ≥2 new lesions or >30% increase in volume or uptake.
Nevertheless, the need to integrate clinical and analytical data as well as maintain the same radiopharmaceutical in successive studies was emphasized.
The panel concluded that the implementation of these criteria should be evaluated in clinical trials and prospective studies to validate their impact in clinical practice.
RECIP 1.0 criteriaWith the aim of establishing simple robust criteria for routine use, Gafita et al. designed the RECIP 1.0 criteria5 based on the evaluation of two parameters: response of PSMA-VOL and the appearance of new lesions, and established the following categories:
- •
Complete response: disappearance of all the lesions with PSMA uptake.
- •
Partial response: reduction of uptake and PSMA-VOL of > 30%.
- •
Stable disease: when the remaining criteria are not fulfilled.
- •
Disease progression: appearance of at least 1 new lesion together with an increase in PSMA-VOL ≥20%.
Among the different thresholds tested, those established reached the greatest prognostic value for overall survival in patients with biochemical recurrence in mCRPC.
One potential limitation of the RECIP 1.0 criteria is the need to calculate the tumoral volume in PSMA-PET and this is a laborious process if specific software is not available. To simplify this evaluation, Gafita et al. proposed a visual version of the RECIP, which has been validated in advanced PC and has shown high interobserver agreement.31 In parallel, advances in artificial intelligence, with segmentation tools and semiautomated analysis, provide promising perspectives for optimizing tumoral quantification and reducing operative burden.32
Although RECIP 1.0 was created and originally validated for the follow-up of treatment with [177Lu]Lu-PSMA-617, some studies evaluated its utility following the use of different treatment modalities, such as ADT and ARPIs, among others.
A meta-analysis that included eight studies and 516 patients demonstrated the prognostic value of RECIP 1.0 for predicting a higher risk of mortality in mCRPC in cases of progression to therapy.7 In a direct comparison with other frameworks of response applied to PSMA-PET, such as PCWG3, PERCIST and the PPP criteria, the RECIP 1.0 criteria achieved greater interobserver reproducibility and prognostic accuracy.5
Finally, RECIP 1.0 responses in interim PSMA-PET were combined with the PSA responses at 12 weeks to develop a new classification of combined response (PSA + RECIP),5 defining the following categories:
- •
Tumoral response: reduction in PSA ≥ 50% or RECIP-PR/CR.
- •
Tumoral progression: increase in PSA ≥ 25% or RECIP-DP.
The classification of combined response (PSA + RECIP) demonstrated prognostic accuracy for overall survival that was greater than that of the PSA measurements alone, presenting a potential benefit in the evaluation of the efficacy for clinical trials of mCRPC. In comparison with the PSA measurements, PSMA-PET provides additional information on the site of the metastasis and the pattern of dissemination, as well as possible bone complications (i.e., compression of the spinal cord or fractures).5
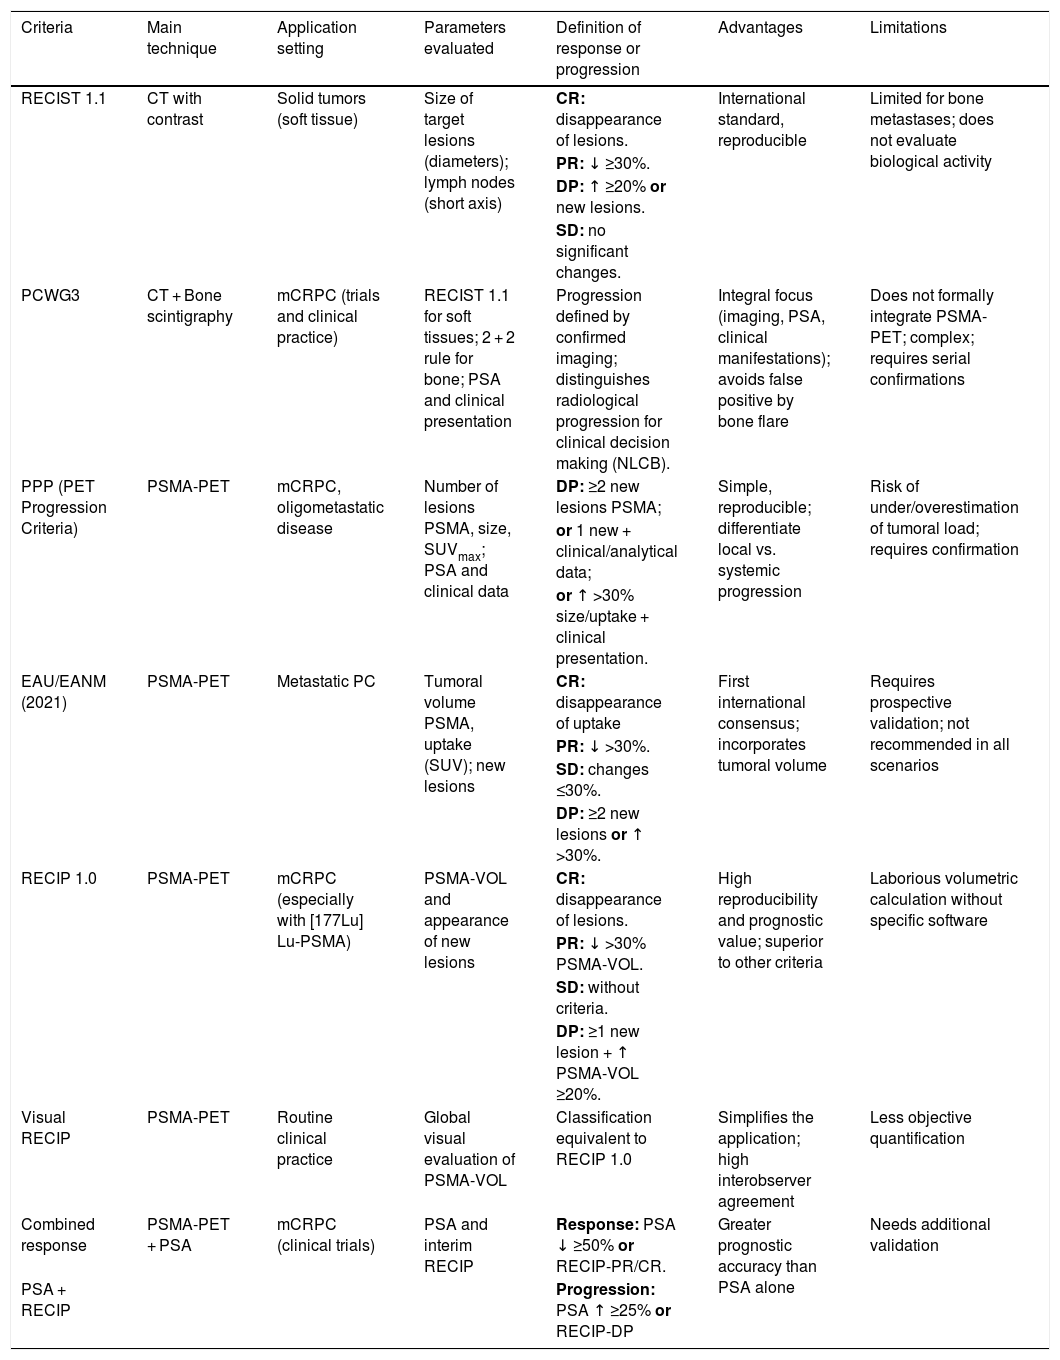
Below, Table 1 summarizes the most important aspects of the previously described criteria for the evaluation of response to treatment.
Table comparing the different criteria of evaluation of response to treatment in patients with prostate cancer.
| Criteria | Main technique | Application setting | Parameters evaluated | Definition of response or progression | Advantages | Limitations |
|---|---|---|---|---|---|---|
| RECIST 1.1 | CT with contrast | Solid tumors (soft tissue) | Size of target lesions (diameters); lymph nodes (short axis) | CR: disappearance of lesions. | International standard, reproducible | Limited for bone metastases; does not evaluate biological activity |
| PR: ↓ ≥30%. | ||||||
| DP: ↑ ≥20% or new lesions. | ||||||
| SD: no significant changes. | ||||||
| PCWG3 | CT + Bone scintigraphy | mCRPC (trials and clinical practice) | RECIST 1.1 for soft tissues; 2 + 2 rule for bone; PSA and clinical presentation | Progression defined by confirmed imaging; distinguishes radiological progression for clinical decision making (NLCB). | Integral focus (imaging, PSA, clinical manifestations); avoids false positive by bone flare | Does not formally integrate PSMA-PET; complex; requires serial confirmations |
| PPP (PET Progression Criteria) | PSMA-PET | mCRPC, oligometastatic disease | Number of lesions PSMA, size, SUVmax; PSA and clinical data | DP: ≥2 new lesions PSMA; | Simple, reproducible; differentiate local vs. systemic progression | Risk of under/overestimation of tumoral load; requires confirmation |
| or 1 new + clinical/analytical data; | ||||||
| or ↑ >30% size/uptake + clinical presentation. | ||||||
| EAU/EANM (2021) | PSMA-PET | Metastatic PC | Tumoral volume PSMA, uptake (SUV); new lesions | CR: disappearance of uptake | First international consensus; incorporates tumoral volume | Requires prospective validation; not recommended in all scenarios |
| PR: ↓ >30%. | ||||||
| SD: changes ≤30%. | ||||||
| DP: ≥2 new lesions or ↑ >30%. | ||||||
| RECIP 1.0 | PSMA-PET | mCRPC (especially with [177Lu] Lu-PSMA) | PSMA-VOL and appearance of new lesions | CR: disappearance of lesions. | High reproducibility and prognostic value; superior to other criteria | Laborious volumetric calculation without specific software |
| PR: ↓ >30% PSMA-VOL. | ||||||
| SD: without criteria. | ||||||
| DP: ≥1 new lesion + ↑ PSMA-VOL ≥20%. | ||||||
| Visual RECIP | PSMA-PET | Routine clinical practice | Global visual evaluation of PSMA-VOL | Classification equivalent to RECIP 1.0 | Simplifies the application; high interobserver agreement | Less objective quantification |
| Combined response | PSMA-PET + PSA | mCRPC (clinical trials) | PSA and interim RECIP | Response: PSA ↓ ≥50% or RECIP-PR/CR. | Greater prognostic accuracy than PSA alone | Needs additional validation |
| PSA + RECIP | Progression: PSA ↑ ≥25% or RECIP-DP |
mCRPC: metastatic castration-resistant prostate cancer; RECIST: Response Evaluation Criteria in Solid Tumours; PCWG3: Prostate Cancer Working Group 3; RECIP: Response Evaluation Criteria in PSMA PET/CT; PSA: prostate-specific antigen; NLCB: No Longer Clinically Benefiting; PSMA: prostate-specific membrane antigen; PSMA-VOL: PSMA-positive total tumoral volume; CR: complete response; PR: partial responses; DP: disease progression; SD: stable disease.
The current evidence supports the use of therapy with radioligands, especially lutetium-177 vipivotide tetraxetan ([¹⁷⁷Lu]Lu-PSMA-617), in patients with mCRPC. This approach was approved by the FDA in 2022 and by EMA in Europe in 2022, and has been used in Spain for therapeutic evaluation since 2024. Its indication is focused on adult patients with PSMA-positive mCRPC following progression to taxanes and inhibitors of the androgenic axis in combination with ADT, with or without inhibitors of the androgenic receptor. Selection requires a demonstration of high PSMA uptake in PET/CT greater than that of the hepatic parenchyma and the exclusion of significant PSMA-negative lesions (≥1 cm in solid organs or ≥2.5 cm in lymph nodes), which may reflect tumoral clones not susceptible to radioligands.34,35
The results of the TheraP trial, as well as the SNMMI and EANM guidelines confirm the value of the basal SUVmean as a key predictive biomarker. A SUVmean ≥6.9 (TheraP) and preferably >10 (EANM/SNMMI) in most of the lesions is associated with a greater probability of biochemical and radiological response as well as greater survival and disease control.35–39
Nonetheless, the prognostic value of the SUVmean may vary when [¹⁷⁷Lu]Lu-PSMA-617 is combined with agents such as enzalutamide, and thus, its interpretation should be contextualized in the therapeutic schedule.40 Visual tools, such as the Heterogeneity and Intensity of Tracer uptake (HIT) score, that integrates the intensity and heterogeneity of uptake, may complement the quantification of the SUVmean and facilitate selection in clinical practice.41
On the other hand, the total tumoral volume obtained in both the [¹⁸F]FDG PET and the PSMA-PET has been identified as an independent prognostic biomarker, associating elevated values with a worse overall survival.36 Interlesional heterogeneity, especially the coexistence of PSMA-negative and FDG-PET-positive lesions, indicates intratumoral resistance and fewer benefits of the treatment with [¹⁷⁷Lu]Lu-PSMA-617, which supports the combined use of the two techniques for optimizing patient selection.16,35
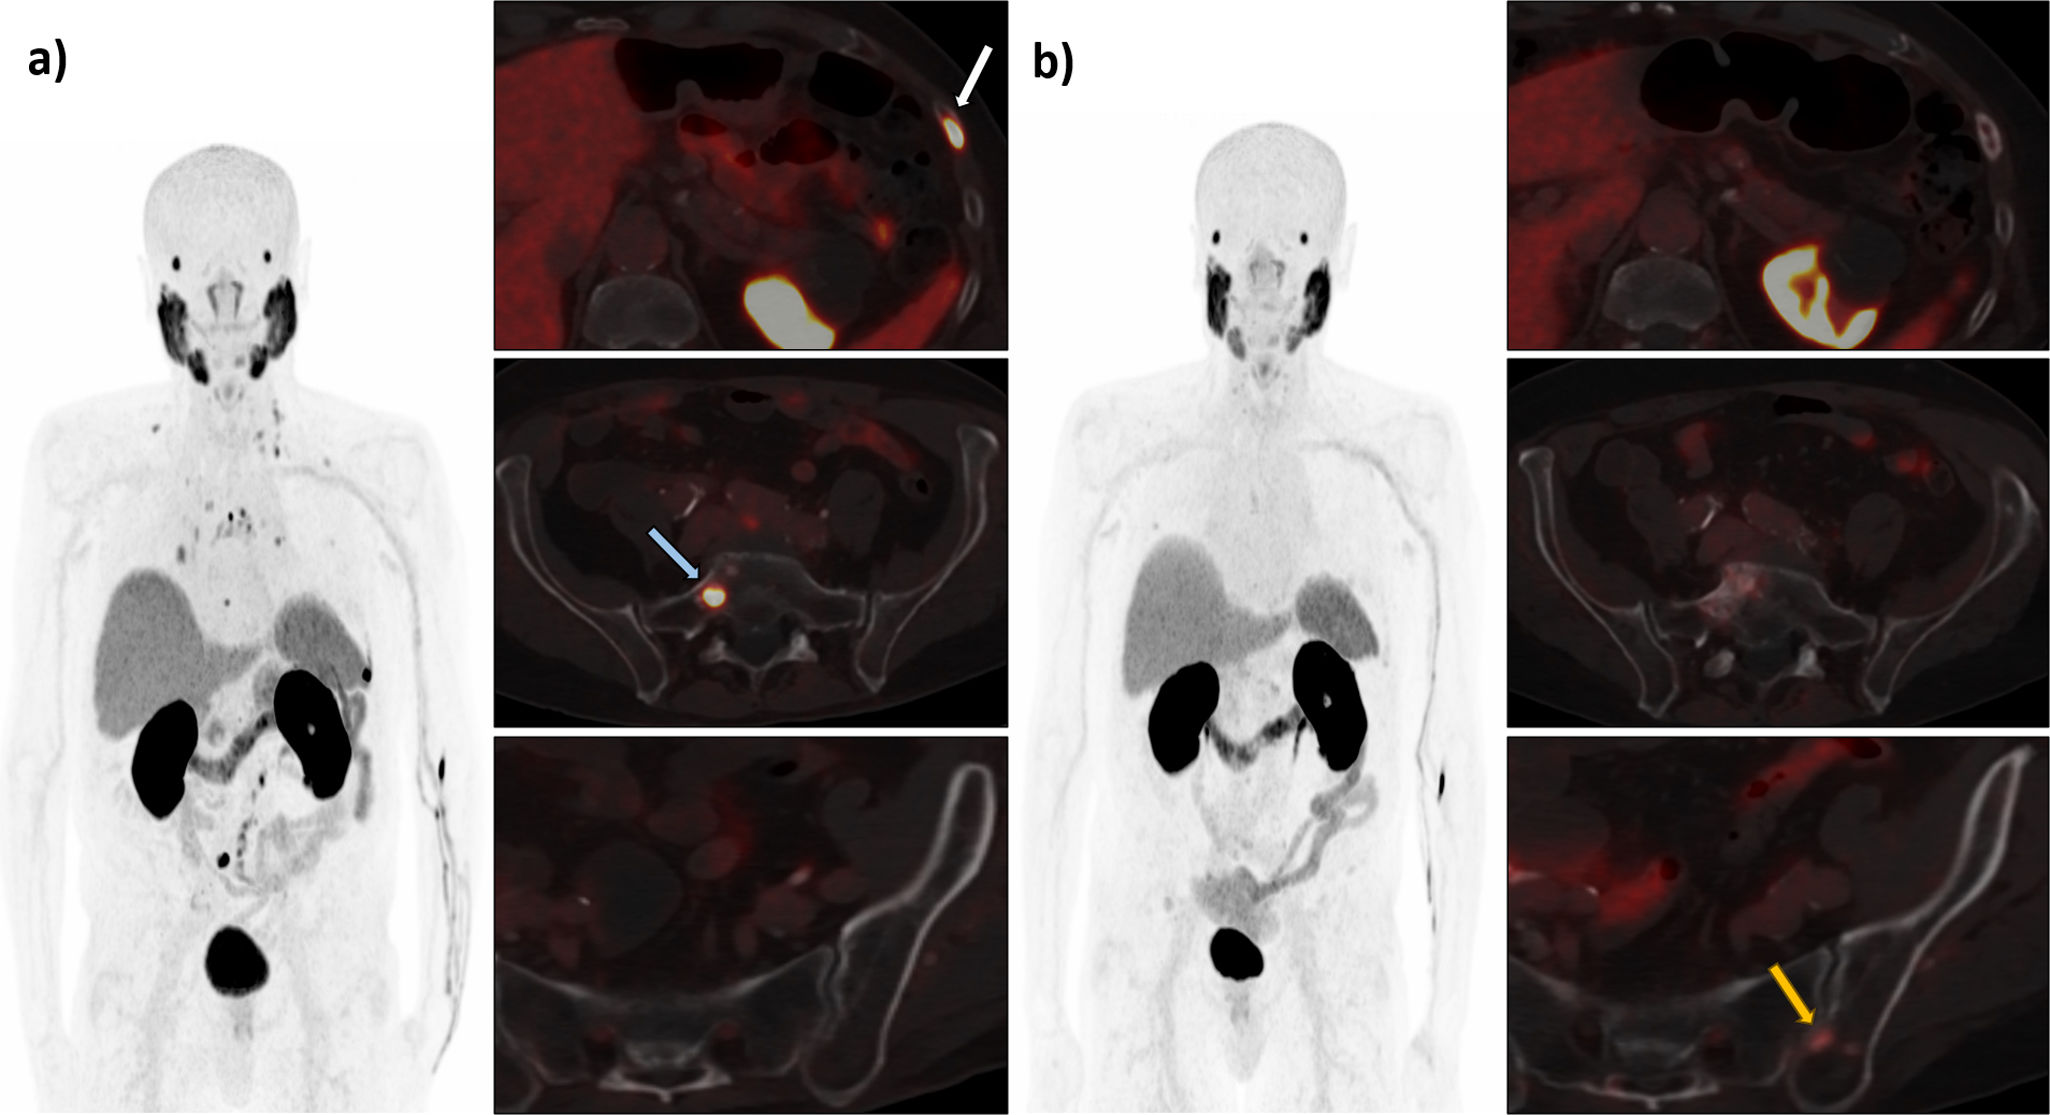
Finally, in addition to the basal biomarkers, the RECIP criteria allow early evaluation of efficacy after the first two cycles of [¹⁷⁷Lu]Lu-PSMA-617, usually at 12 weeks (Fig. 1).31,42–45

78-year-old male with mCRPC that has progressed to ARPI (abiraterone) and taxane (docetaxel) with poor tolerance. PSA 26.05 ng/mL. PSMA-PET was performed to evaluate the patient as a possible candidate for [177Lu]Lu-PSMA-617 (a), showing disseminated blastic metastatic bone disease, with lesions in the seventh left anterolateral costal arch with SUVmax 29.23; PSMA-RADS 5 (white arrow) in the right sacral/iliac crest with SUVmax of 32.12; PSMA-RADS 5 (blue arrow). Given the PSMA-PET findings and the adequate clinical-analytical profile of the patient, treatment with [177Lu]Lu-PSMA-617 was performed. After the second cycle of treatment (at 12 weeks) a new PSMA-PET for control was carried out (b) which despite showing complete response of the known metastatic bone lesions, four new metastatic bone lesions were observed with a SUVmax of up to 6.12 in one left iliac lesion (orange arrow), suggesting disease progression. The PSA levels at this time are 37.38 ng/mL. Due to the analytical and radiological progression, it was decided to suspend the treatment.
[223Ra] is an alpha particle-emitting radiopharmaceutical with a potent cytotoxic effect that was authorized based on the results of the ALSYMPCA clinical trial. It is approved for the treatment of patients with mCRPC with symptomatic bone metastases and with known visceral metastases. Prior to its administration, disease progression must be confirmed after at least two previous lines of systemic treatment, or the patient must not be a candidate for any available systemic treatment.46
Treatment with [²²³Ra] dichloride is generally well tolerated; however, it has important limitations in the evaluation of response since no reliable follow-up method has been identified, either by variations in the PSA values or with conventional imaging techniques.
The prospective Radium223Insight study led by Jong et al.17 assessed the utility of [⁶⁸Ga]Ga-PSMA PET/CT for monitoring the response to treatment with [²²³Ra] dichloride in patients with mCRPC and bone metastases. They performed studies at 3 time points: basal, after the third cycle and on completion of the sixth cycle. Extension of bone disease was quantified by the total tumoral volume (TTV) of bone, a semiquantitative biomarker that demonstrated correlation with clinical response. A low basal bone TTV and its reduction after the third cycle were associated with better response, while elevated values predicted the appearance of new lesions during treatment. Inter- and intra-patient heterogeneity limited the applicability of criteria such as PERCIST and the variation of AP did not show a correlation with response, questioning it utility as a marker.
These findings support the use of PSMA-PET as a promising tool for the monitoring of [²²³Ra], providing a more reliable alternative than AP or conventional imaging for therapeutic monitoring, although validation is required in larger cohorts and correlation with clinical outcomes.
Chemotherapy with taxanesAt present, chemotherapy with taxanes (docetaxel and cabazitaxel), that is used in both metastatic hormone-sensitive prostate cancer (mHSPC) and in mCRPC does not have specific criteria that are validated for the evaluation of response by PSMA-PET/CT.48 However, some studies have explored the application of principles derived from PERCIST, proposing that a reduction of the PSMA-VOL ≥30% could be considered indicative of PR.30 It is important to underline that this approach is not formally standardized and requires validation in prospective trials before its incorporation into clinical practice.
The evidence on the evaluation of response by PSMA-PET after systemic chemotherapy has mainly come from retrospective studies, with the work by Shagera et al.47 being of note. This study reported that the optimal time for performing PSMA-PET in patients with mPC treated with taxanes is early, after treatment cycles (approx. 6–8 weeks). Early changes in PSMA uptake (reduction or progression) are significantly correlated with overall survival and progression-free survival, allowing the identification of responders and non-responders before variations in PSA or conventional imaging are observed.
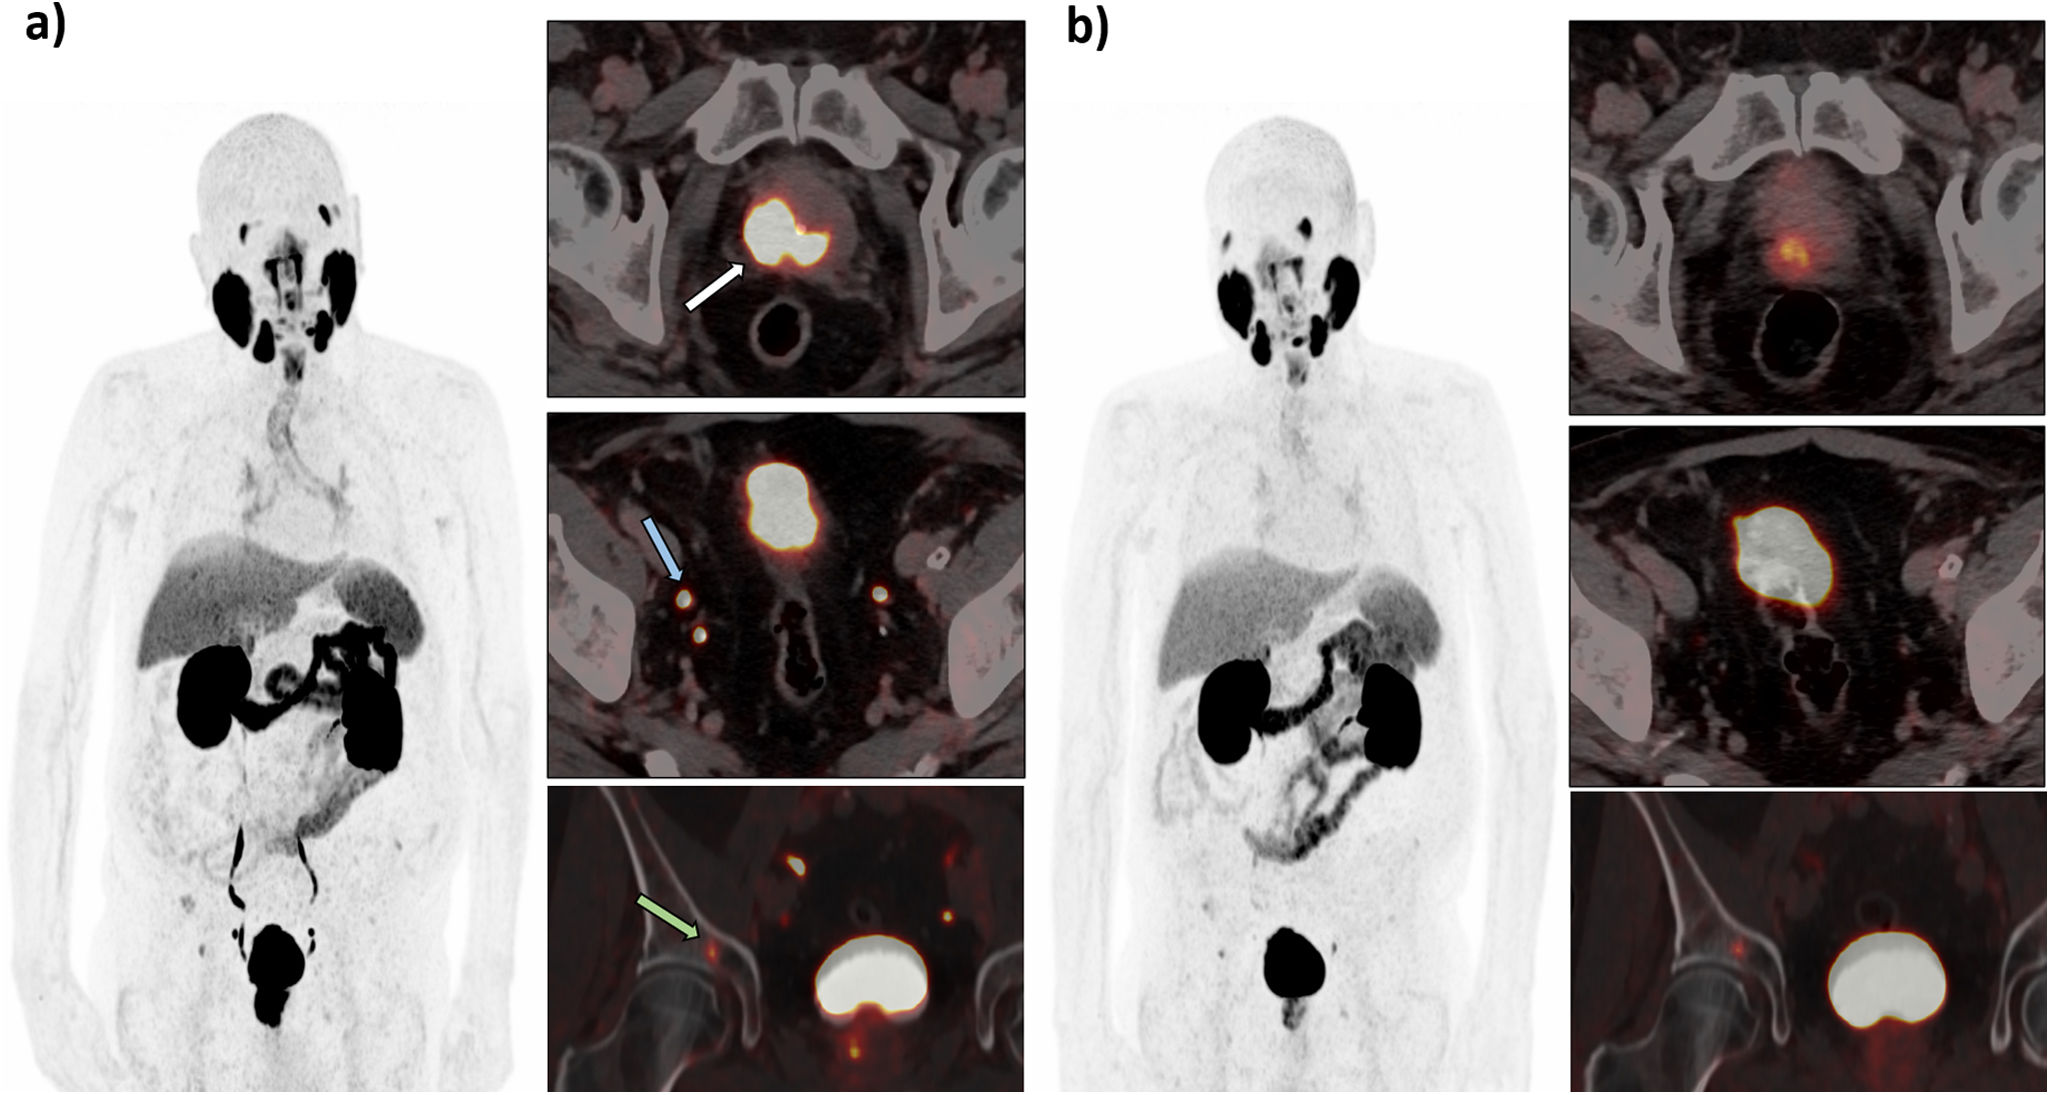
To the contrary, waiting for late evaluations based on RECIST 1.1 or PCWG3 may delay the detection of therapeutic failure, especially in predominant bone disease. Although PCWG3 recommends maintaining systemic treatment during the first 12 weeks, the introduction of early evaluation with PSMA-PET could facilitate early decisions, such as a change to other therapies in the absence of response (Fig. 2). These findings are promising but require validation in larger prospective studies.

82-year-old male with prostate adenocarcinoma Gleason 9 (5 + 4). Pretreatment PSA 8.49 ng/mL. PSMA-PET performed as staging study (a) identified pathological bilobar prostatic uptake invading the capsule and the right seminal vesicle and in contact with the bladder and the anterior region of the rectum with a SUVmax of 55.32; Score 3 (white arrow), in relation to the primary neoplasm (PSMA-RADS 5). Likewise, pelvic lymph node involvement was observed with a SUVmax of 30.88 in the right external lymph node chain; Score 3; PSMA-RADS 4 (blue arrow) and at least nine bone foci without morphological translation with SUVmax of 7.05 in the right acetabulum; Score 2 (green arrow) suggestive of bone metastases (PSMA-RADS 4). PROMISE miTNM: miT4 (PRIMARY 5) N2 (EIR, EIL) M1b (diss). Triple therapy with ADT + ARPI (darolutamide) + taxane (docetaxel) was initiated. Three months after beginning the therapy, a new control PSMA-PET was performed (b) showing partial response at the level of the prostatic neoplasm (SUVmax of 10.92) and bone involvement (SUVmax of 5.21), as well as complete response of the lymph node involvement. The PSA levels at this time are 0.16 ng/mL.
ADT constitutes the basis of systemic treatment of mPC, by the suppression testicular production of androgens by surgical or pharmacological castration with luteinizing hormone-releasing hormone (LHRH) analogs or antagonists. The ARPIs, such as abiraterone and enzalutamide, block the signaling of the androgenic receptor and are used in both hormone sensitive and castration-resistant disease.
Given that the expression of PSMA is regulated by androgenic signaling, PSMA-PET has gained interest as a tool for evaluating hormonal response, although its interpretation requires understanding the biological effects induced by ADT and ARPIs on the uptake of the radiopharmaceutical.7 As commented previously, the initiation of ADT may induce a heterogeneous increase in tumoral uptake, a phenomenon known as flare, which reflects a pharmacodynamic more than a real progression effect.49
Studies, such as those by Malaspina et al.50 and Ettala et al.,51 demonstrate that between 3–4 weeks after initiating ADT, a significant increase in the SUVmax is produced in multiple metastases, including a marked reduction in PSA and testosterone within the range of castration. Similarly, drugs such as enzalutamide may induce a transitory overexpression of PSMA. Van der Gaag et al. reported an increase in uptake in more than 50% of the lesions a few weeks after initiating ARPI, with no changes in healthy organs, thereby confirming a specific tumoral mechanism. This phenomenon may simulate radiological progression and underlines the need to avoid erroneous interpretations in early studies.
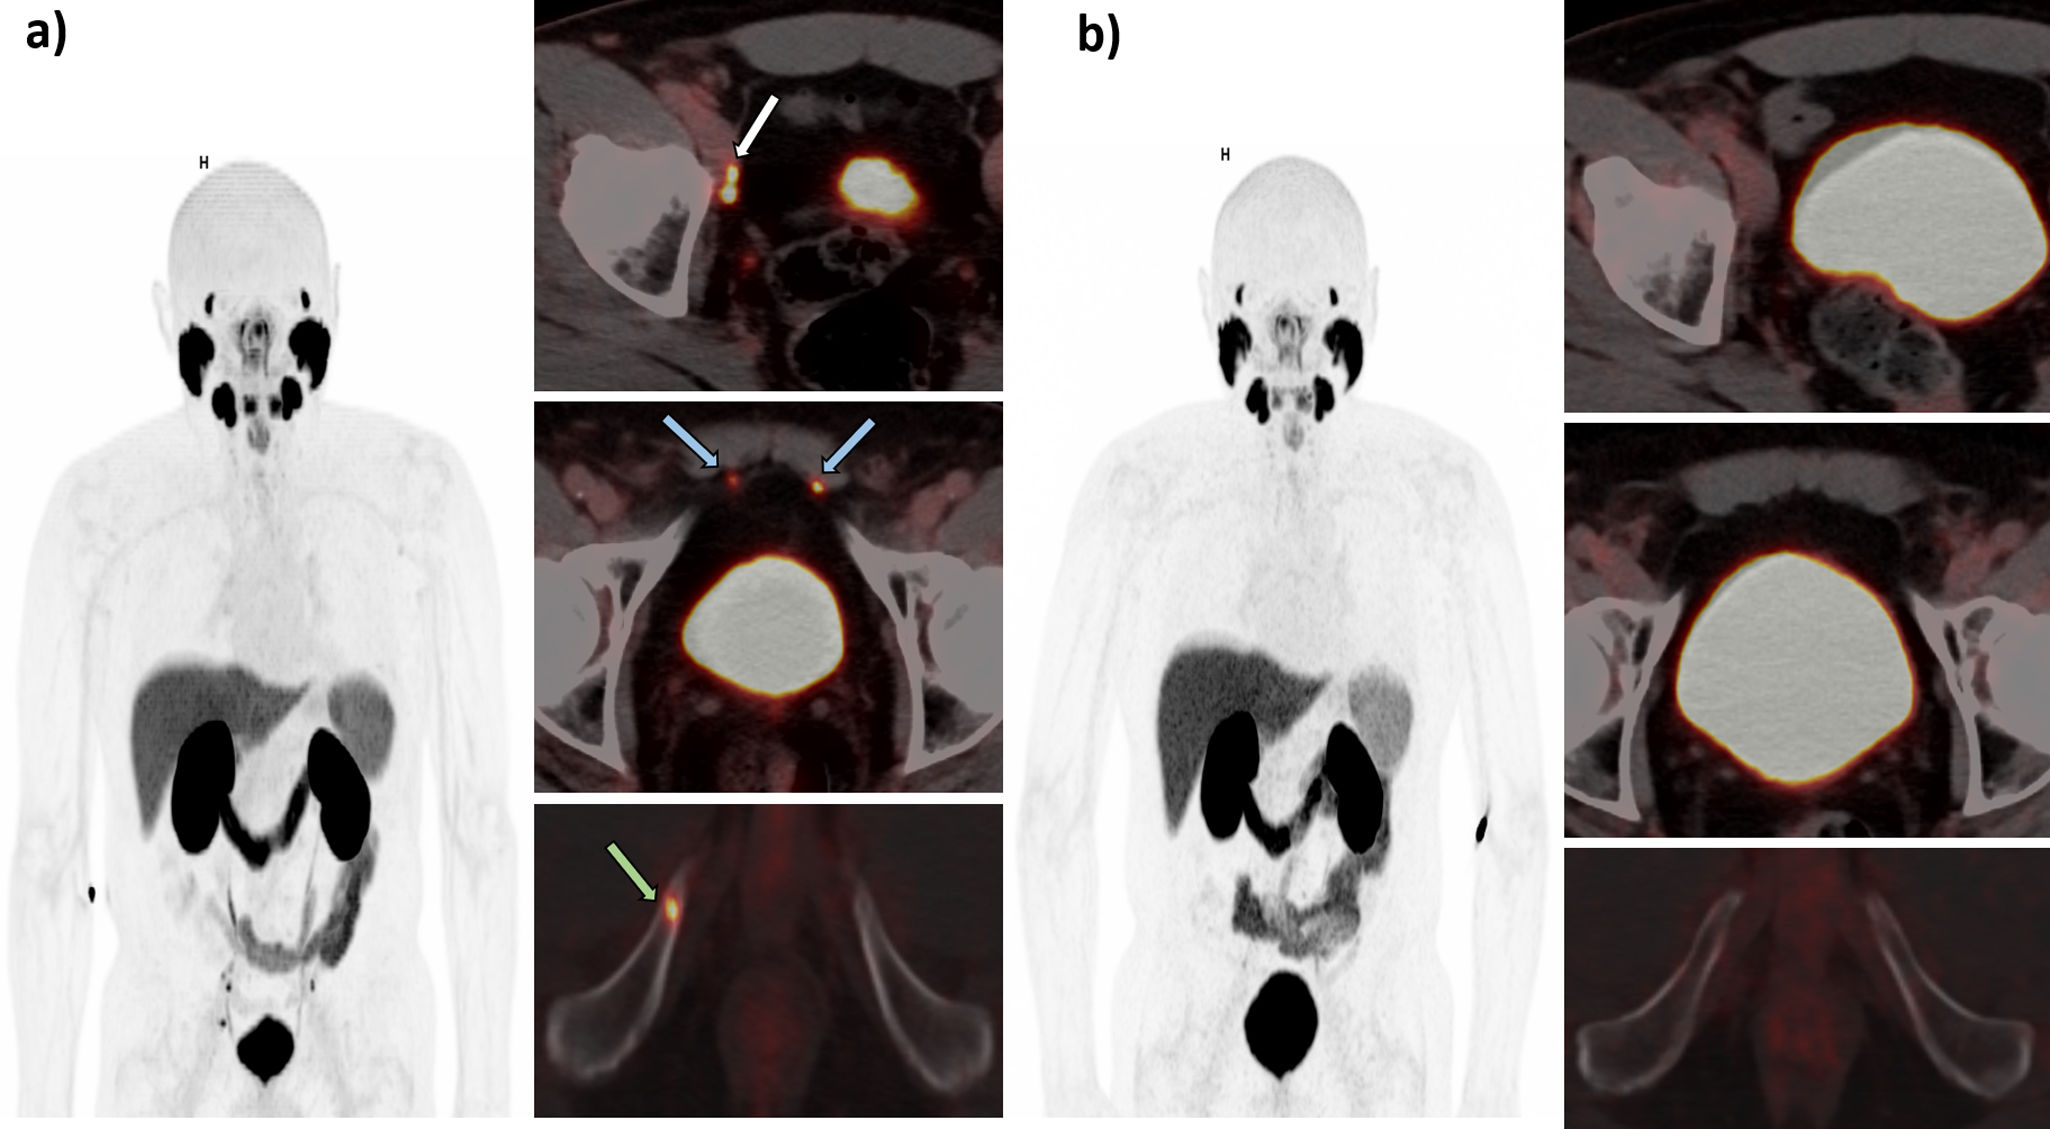
The evidence indicates that the evaluation of hormonal response by PSMA-PET should be deferred to approximately 8−12 weeks after the initiation of treatment (Fig. 3). Very early evaluations (1–4 weeks) present a high incidence of flare and transitory changes, limiting their utility.49–52 To the contrary, studies performed at 3 months show less interference of flare, greater uptake stability and a better correlation with PSA and survival. Thus, the joint EAN/SNMMI guidelines recommend a basal PET before the initiation and a deferred PET to optimize its values as a biomarker of response.8

60-year-old male with prostate adenocarcinoma Gleason 7 (3 + 4). Pretreatment PSA 7 ng/mL. Underwent radical prostatectomy and lymph node dissection. pT3aR1 pN0 cM0. Thereafter, salvage radiotherapy was performed in the prostatic bed due to biochemical recurrence (PSA 0.35 ng/mL). For biochemical progression (PSA 1.28 ng/mL), PSMA-PET was performed (a) observing pathological pelvic adenopathies with a SUVmax of 10.34 in the external right iliac chain; PSMA-RADS 4 (white arrow) and SUVmax of 12.18 located posterior to the rectal muscle of the abdomen; PSMA-RADS 4 (blue arrow) and single bone lesion in the right ischiopubic ramus with a SUVmax of 8.17; PSMA-RADS 4 (green arrow). The decision was made to perform treatment with ADT + ARPI (apalutamide). Four months after initiating therapy, a new control PSMA-PET was made (b) showing complete disease response. The PSA levels at this time are 0.04 ng/mL.
When PSMA-PET is performed at an adequate time, multiple studies have shown a good correlation with the clinical evolution and higher prognostic value than PSA alone. Shagera et al.53 and Kleiburg et al.54 Demonstrated that response according to the EAU/EANM or RECIP 1.0 criteria is significantly correlated with overall survival. Likewise, Giunta et al.55 confirmed that discordance between PSA and PET is frequent and that PET provides relevant additional prognostic information for decision making.
Stereotactic body radiation therapy (SBRT)Stereotactic body radiation therapy (SBRT), also called stereotactic ablative radiation therapy (SABR), is a modality of high precision radiotherapy that administers ablative doses in a reduced number of fractions to small tumoral volumes with the aim of eradicating limited metastatic disease and preserving the healthy surrounding tissues. In mPC, SBRT has become consolidated as a strategy of metastasis-directed therapy, especially in scenarios of oligometastasis or oligoprogression.56,57
In this context, PSMA-PET not only allows highly sensitive detection of lesions that are candidates for SBRT but also emerges as a promising tool for evaluating response to local treatment beyond conventional morphological criteria. This approach is described in the studies by Sadetski et al.56 and Gawish et al.,57 which analyze metabolic response after SBBRT guided by PSMA-PET in oligometastatic disease.
The first clinical data specifically evaluating the role of PSMA-PET in the response to SBRT show elevated rates of local metabolic control, with significant decreases in PSMA uptake in the irradiated lesions. In the study by Sadetski et al.,56 which included patients with bone metastasis treated with SBRT, the disappearance or marked reduction of avidity by PSMA in the volume irradiated was correlated with local control greater than 90%, with recurrence within the treated area during follow-up.
Similarly, Gawish et al.57 demonstrated that metabolic response evaluated with PSMA-PET, expressed as a reduction of the SUVmax, constitutes a sensitive marker of local control after SBRT in bone and lymph node metastases.
Temporal evolution of response in PSMA-PET after SBRT suggests that the reduction in PSMA expression may be progressive and maintained beyond the first control. Zang et al.58 performed a longitudinal evaluation of patients treated with SBRT guided by PSMA-PET and demonstrated that the percentage of lesions with complete metabolic response increased over time, reaching a rate of close to 90% in prolonged follow-ups. This finding is relevant, since it indicates that too early an evaluation could underestimate the real response to treatment. In addition, the authors noted that early residual uptake does not necessarily imply local failure but rather may reflect a transitory incomplete response after ablative irradiation.
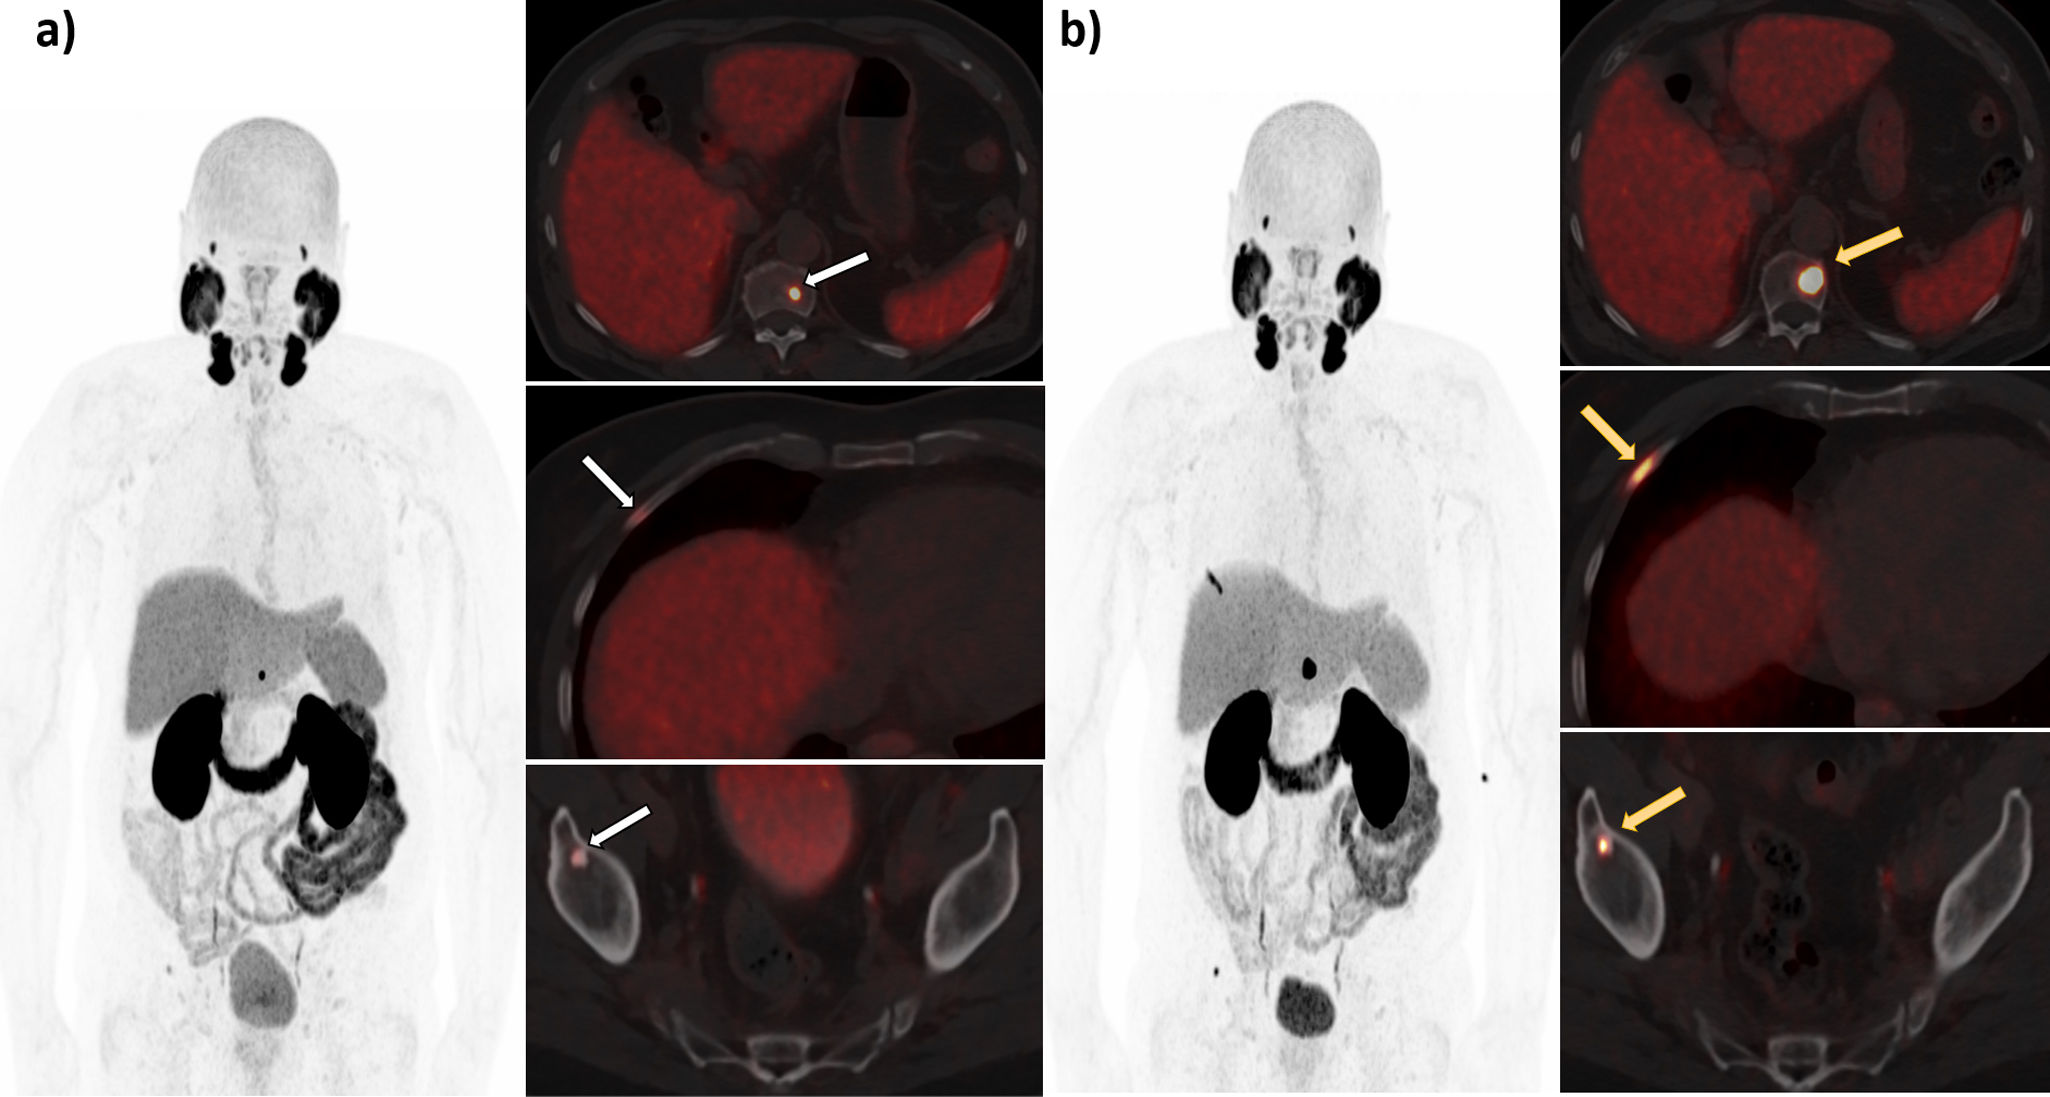
Beyond the purely local evaluation, PSMA-PET allows the identification of interlesional heterogeneity in patients with limited metastatic disease treated with SBRT. The multicenter study of Sutera et al.59 demonstrated that metabolic response in PSMA-PET after SBRT is significantly associated with metastasis-free survival, establishing the response in PSMA-PET as a biomarker with potential prognostic value. It is important to note that this study demonstrates that the absence of metabolic response in at least one irradiated lesion is associated with a greater risk of systemic progression, reinforcing the role of PSMA-PET in the detection of resistant clones and posterior therapeutic decisions (Fig. 4).

75-year-old male with prostate adenocarcinoma Gleason 9 (5 + 4). cT2 cN0-1 cM0. Pretreatment PSA 4 ng/mL. The patient was treated with prostatic radiotherapy and of the pelvic lymph node chains + ADT for 3 years. Due to biochemical progression (PSA 0.7 ng/mL; PSA doubling time of 5 meses), PSMA-PET was performed (a) observing three blastic bone lesions (white arrows) in the fifth right anterior costal arch (SUVmax of 9.03), vertebral body of D11 (SUVmax of 27.87) and right iliac (SUVmax of 8.32), compatible with bone metastases (PSMA-RADS 5). Given the PSMA-PET findings, oligometastatic CRPC was considered and the decision was made to treat these bone lesions with SBRT. Three months after the treatment with SBRT, a new control PSMA-PET was performed (b) observing progression of the lesions (orange arrows), in both size and uptake, in the fifth right anterior costal arch (SUVmax of 21.84), D11 (SUVmax of 46.86) and right iliac (SUVmax of 23.04). According to RECIP criteria, increase in total tumoral volume of 110% (> 20%). The PSA levels at this time were 1.21 ng/mL. The patient has currently started a new line with (abiraterone), with descent in PSA (PSA 0.09 ng/mL).
Altogether, the evidence available coincides in that the evaluation of response to treatment with PSMA-PET after SBRT should be deferred, avoiding excessively early controls that may be influenced by inflammatory changes or by incomplete metabolic response. The studies analyzed consistently used basal PSMA-PET prior to SBRT and a posterior control performed at least, 2–3 months after treatment, considering this interval as the most adequate for reliable evaluation of local metabolic response. Sadetski et al.,56 Gawish et al.57 and Zang et al.58 support this temporal approach that allows more robust interpretation of PSMA-PET and reduces the risk of erroneously classifying lesions with response as persistent disease.
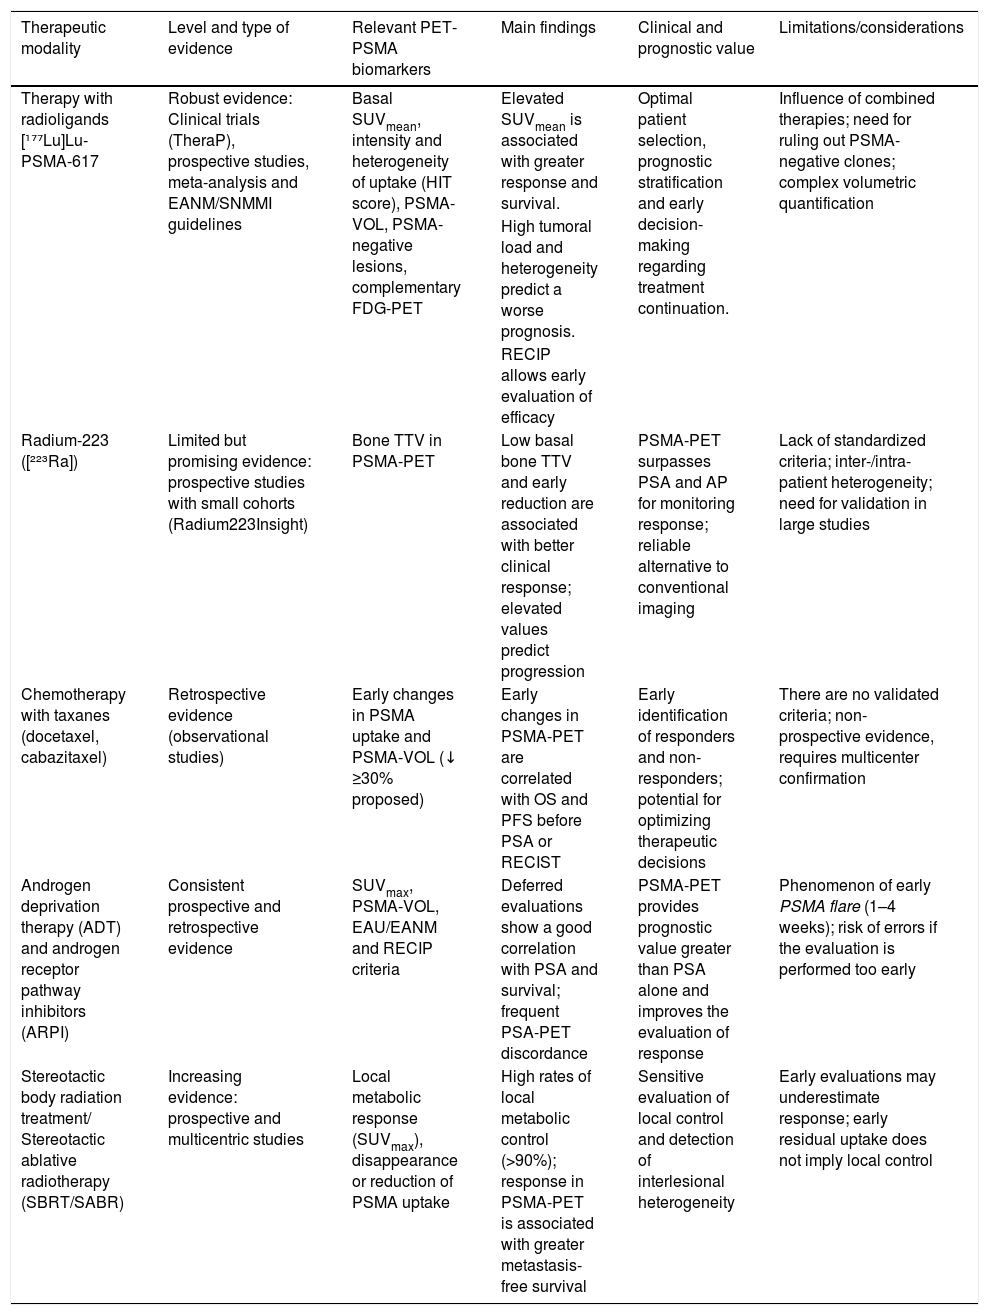
The following table (Table 2) shows a comparison of the scientific evidence available on the evaluation of response with PSMA-PET according to the therapeutic modality.
Scientific evidence of PSMA-PET for evaluating response to treatment in prostate cancer according to the treatment received.
| Therapeutic modality | Level and type of evidence | Relevant PET-PSMA biomarkers | Main findings | Clinical and prognostic value | Limitations/considerations |
|---|---|---|---|---|---|
| Therapy with radioligands [¹⁷⁷Lu]Lu-PSMA-617 | Robust evidence: Clinical trials (TheraP), prospective studies, meta-analysis and EANM/SNMMI guidelines | Basal SUVmean, intensity and heterogeneity of uptake (HIT score), PSMA-VOL, PSMA-negative lesions, complementary FDG-PET | Elevated SUVmean is associated with greater response and survival. | Optimal patient selection, prognostic stratification and early decision-making regarding treatment continuation. | Influence of combined therapies; need for ruling out PSMA-negative clones; complex volumetric quantification |
| High tumoral load and heterogeneity predict a worse prognosis. | |||||
| RECIP allows early evaluation of efficacy | |||||
| Radium-223 ([²²³Ra]) | Limited but promising evidence: prospective studies with small cohorts (Radium223Insight) | Bone TTV in PSMA-PET | Low basal bone TTV and early reduction are associated with better clinical response; elevated values predict progression | PSMA-PET surpasses PSA and AP for monitoring response; reliable alternative to conventional imaging | Lack of standardized criteria; inter-/intra-patient heterogeneity; need for validation in large studies |
| Chemotherapy with taxanes (docetaxel, cabazitaxel) | Retrospective evidence (observational studies) | Early changes in PSMA uptake and PSMA-VOL (↓ ≥30% proposed) | Early changes in PSMA-PET are correlated with OS and PFS before PSA or RECIST | Early identification of responders and non-responders; potential for optimizing therapeutic decisions | There are no validated criteria; non-prospective evidence, requires multicenter confirmation |
| Androgen deprivation therapy (ADT) and androgen receptor pathway inhibitors (ARPI) | Consistent prospective and retrospective evidence | SUVmax, PSMA-VOL, EAU/EANM and RECIP criteria | Deferred evaluations show a good correlation with PSA and survival; frequent PSA-PET discordance | PSMA-PET provides prognostic value greater than PSA alone and improves the evaluation of response | Phenomenon of early PSMA flare (1–4 weeks); risk of errors if the evaluation is performed too early |
| Stereotactic body radiation treatment/ Stereotactic ablative radiotherapy (SBRT/SABR) | Increasing evidence: prospective and multicentric studies | Local metabolic response (SUVmax), disappearance or reduction of PSMA uptake | High rates of local metabolic control (>90%); response in PSMA-PET is associated with greater metastasis-free survival | Sensitive evaluation of local control and detection of interlesional heterogeneity | Early evaluations may underestimate response; early residual uptake does not imply local control |
HIT score: Heterogeneity and Intensity of Tracer uptake; PSMA-VOL: PSMA-positive total tumoral volume; RECIP: Response Evaluation Criteria in PSMA PET/CT; RECIST: Response Evaluation Criteria in Solid Tumours; OS: overall survival; AP: alkaline phosphatase; PFS: progression-free survival; PSA: prostate-specific antigen; TTV: total tumoral volume.
Although the PSA has classically been used for the follow-up of PC, it presents important limitations as a marker of response, especially in advanced disease. Its value may not reflect the real tumoral load due to biological heterogeneity (some metastases secrete little PSA), the presence of little productive phenotypes, such as dedifferentiated tumors or those with neuroendocrine transformation, and the flare phenomenon, which produces transitory increases in the PSA after initiating hormone treatment. In addition, the PSA does not provide information regarding tumor localization or tumoral extension, making it an insufficient indicator for evaluating global response.2
In this context, PSMA-PET provides significant value since it allows direct visualization of tumoral load and its changes over time. Moreover, it provides other advantages: it detects progression before and with greater prognostic value tan PSA; better predicts survival in patients treated with [¹⁷⁷Lu]Lu-PSMA-617, allows the quantification of tumoral load by PSMA-VOL (reductions ≥30% are associated with a better prognosis) and it is fundamental for selecting and reevaluating candidates for PSMA-directed therapies.60
The European guidelines (EAU) continue to use PSA as the principal axis of follow-up, but they recognize the high diagnostic value of PSMA-PET and recommend it even with low PSA values when the therapeutic management can be changed. Its integration in radiotherapy planning and systemic decisions is increasingly greater. In practice, the PSA continues to be a routine marker, while PSMA-PET is used in situations of clinical discordance, changes in treatment or the evaluation of response in metastatic disease.2
PSMA-PET clearly surpasses the PSA in several clinical settings. In mCRPC under systemic treatment, it predicts survival better and detects progression that may remain unrecognized with a stable PSA.54 Nonetheless, joint interpretation of the PSA and PSMA-PET improves decision making: when both are favorable the response is usually good; if the PSA improves but PET shows progression, real progression should be considered; and if the PSA increases but the PET remains stable, it is advisable to repeat the studies and assess other causes or phenotypes with low PSMA expression.54
The study of Kuten et al.61 provides relevant evidence regarding the added value of PSMA-PET versus conventional follow-up in patients with mPC: in two thirds of the patients studied there was concordance between the PSA and PSMA-PET, but in one third, significant discrepancies were observed. In many cases, the PET detected progression not reflected by the PSA or showed stability despite ambiguous values. These discrepancies were frequent when the PSA appeared as stable, a situation that PET clarified as progression or response. In addition, this information influenced therapeutic decisions in more than 70% of the patients.
In summary, PSMA-PET adds real value to standard follow-up, especially when the PSA is ambiguous or the disease is heterogeneous. At present, the combination of RECIP + PSA is proposed as integrated criteria in clinical trials, given its greater prognostic accuracy.
PSMA-PET versus PCWG3/RECISTIn the evaluation of therapeutic response in mPC, PSMA-PET has become consolidated as a highly sensitive imaging biomarker and with prognostic value. However, the PCWG3 and RECIST 1.1 criteria continue to be the regulatory standard, especially in mCRPC, despite its limitations. These criteria are based on morphological changes in soft tissue and on indirect criteria for bone disease, thereby reducing their sensitivity within a context dominated by the presence of bone metastasis and greater biological heterogeneity.
The current trend is to integrate PSMA-PET using specific criteria, such as RECIP 1.0 and PPP, and even PCWG4 in the future, given that multiple studies have demonstrated that it better predicts survival and detects progression before the classical criteria. In contrast to RECIST and PCWG3, which do not formally consider molecular imaging, PSMA-PET allows evaluation of total tumoral load and the biological activity of the disease, providing a more accurate characterization of therapeutic response.
Gafita et al.33 demonstrated that RECIP 1.0 presents a greater prognostic value and better interobserver concordance than adapted RECIST 1.1 or PCWG3. In their analysis, the category of progression according to RECIP was associated with a significantly greater risk of death versus no progression, indicating that the conventional criteria tend to under-stratify risk. In a complementary manner, Di Franco et al.2 noted that the criteria based on PSMA-PET capture metabolic and molecular changes early, even in the absence of anatomical modifications, which is especially useful in patients with extensive bone involvement or advanced metastatic disease.
These findings reinforce the assertion that PSMA-PET not only improves the detection of active disease but also constitutes a superior tool for monitoring response in mCRPC. In addition, it allows the quantification of tumoral load using parameters such as PSMA-VOL, with which reductions ≥30% are correlated with a better prognosis and facilitate the selection and reevaluation of candidates for PSMA-directed therapies such as [¹⁷⁷Lu]Lu-PSMA-617.
In summary, although RECIST and PCWG3 continue to be the regulatory reference, their dependence on morphological criteria limit their utility in complex scenarios. The integration of PSMA-PET in clinical practice and trials by criteria, such as RECIP and PPP, represent a significant advance with the potential for redefining the current standards of therapeutic follow-up in mPC.
Practical considerationsBelow we present some practical considerations regarding the use of PSMA-PET in the evaluation of therapeutic response.
Although some recommendations on the optimal time and the indications for performing PSMA-PET are promising, they still lack sufficient evidence for their inclusion in the guidelines of clinical practice. Thus, they should only be considered as preliminary orientations and not as standards established for clinical use.
When to perform PSMA-PET- •
Basal: before initiating any treatment in metastatic disease to quantify the total tumoral volume (PSMA-VOL), a relevant prognostic biomarker.
- •
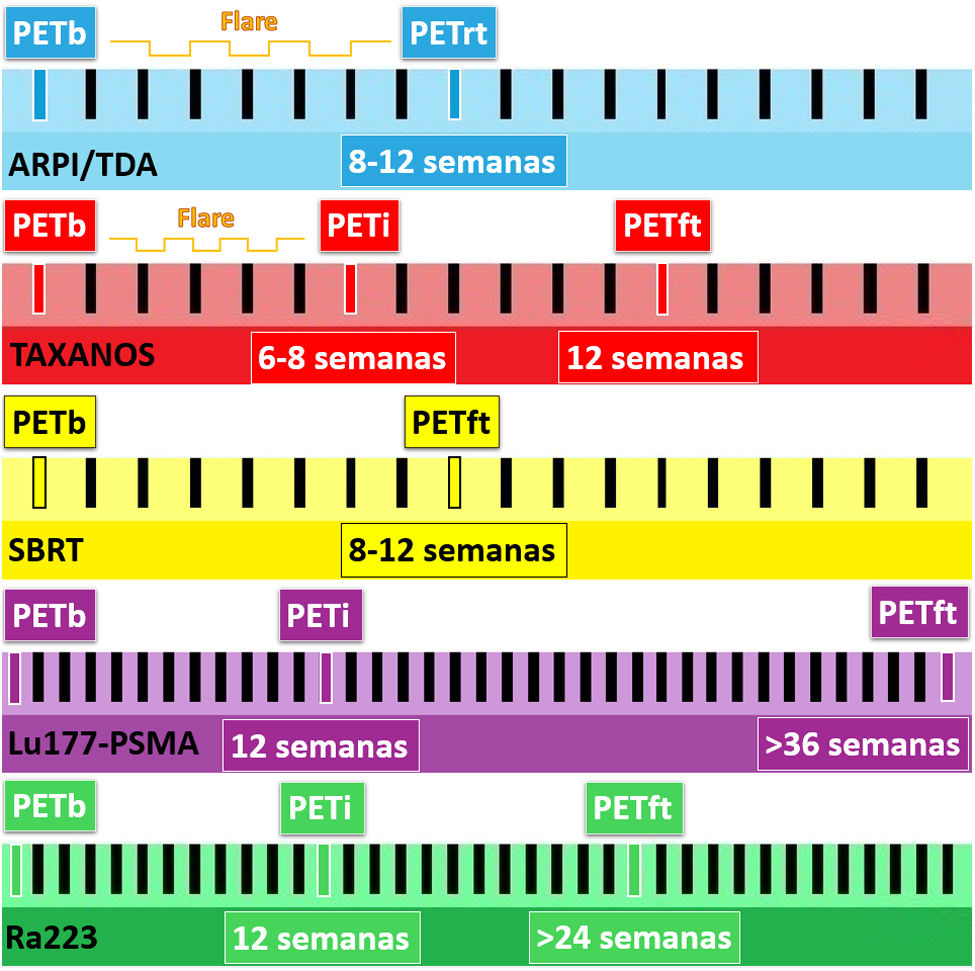
During [¹⁷⁷Lu]Lu-PSMA-617 (RLT): perform an intermediate PET at 12 weeks for applying the RECIP 1.0 criteria.33
- •
After chemotherapy with taxanes: perform an intermediate PET after 2 cycles (6–8 weeks), since it reflects early response better.47,21
- •
After [223Ra]: PSMA-PET every 3 cycles to evaluate heterogeneous bone response (superior to CT and bone scintigraphy).17
- •
After ADT or ARPIs: avoid early studies (<8 weeks) due to possible flare; the optimal time is 8–12 weeks after initiation.49–51
- •
After SBRT: perform deferred PSMA-PET, at least 2–3 months after to avoid confusion with inflammatory changes post-radiotherapy.
Fig. 5 provides a schematic presentation of the optimum chronogram for performing PSMA-PET to evaluate response according to the therapeutic modality.

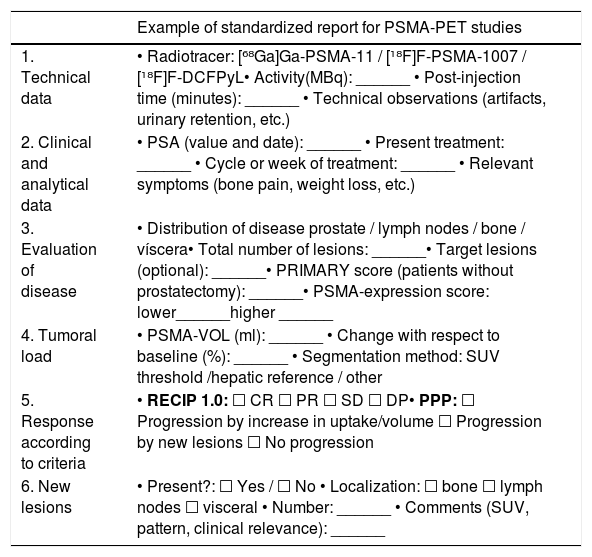
The report should follow the standardized RECIP 1.0, PPP and/or PROMISE criteria,5,62,64 including (Table 3):
- •
Radiopharmaceutical and technique: type, dose and post-injection time.
- •
PSA at the time of PET: PSA + RECIP improves prognostic accuracy.
- •
Tumoral load: PSMA-VOL, method of segmentation and changes vs. basal PET.
- •
Classification of response: RECIP 1.0 (CR/PR/SD/DP) and PPP for risk and progression.
- •
New lesions: register number, localization and clinical relevance.
- •
Atypical findings and pitfalls:
▪False positive bones with ¹⁸F-PSMA-1007.
▪Physiological uptake.
▪Urinary activity may simulate lesions. Delayed acquisition or multiplanar revision should be considered.
▪Discordant aggressive disease.
▪Artifacts.
Example of standardized report for PSMA-PET studies in the evaluation of response to treatment in prostate cancer.
| Example of standardized report for PSMA-PET studies | |
|---|---|
| 1. Technical data | • Radiotracer: [⁶⁸Ga]Ga-PSMA-11 / [¹⁸F]F-PSMA-1007 / [¹⁸F]F-DCFPyL• Activity(MBq): ______ • Post-injection time (minutes): ______ • Technical observations (artifacts, urinary retention, etc.) |
| 2. Clinical and analytical data | • PSA (value and date): ______ • Present treatment: ______ • Cycle or week of treatment: ______ • Relevant symptoms (bone pain, weight loss, etc.) |
| 3. Evaluation of disease | • Distribution of disease prostate / lymph nodes / bone / víscera• Total number of lesions: ______• Target lesions (optional): ______• PRIMARY score (patients without prostatectomy): ______• PSMA-expression score: lower______higher ______ |
| 4. Tumoral load | • PSMA-VOL (ml): ______ • Change with respect to baseline (%): ______ • Segmentation method: SUV threshold /hepatic reference / other |
| 5. Response according to criteria | • RECIP 1.0: ☐ CR ☐ PR ☐ SD ☐ DP• PPP: ☐ Progression by increase in uptake/volume ☐ Progression by new lesions ☐ No progression |
| 6. New lesions | • Present?: ☐ Yes / ☐ No • Localization: ☐ bone ☐ lymph nodes ☐ visceral • Number: ______ • Comments (SUV, pattern, clinical relevance): ______ |
PSA: prostate-specific antigen; PSMA-VOL: PSMA-positive total tumoral volume; RECIP: Response Evaluation Criteria in Solid Tumours; CR: complete response; PR: partial response; SD: stable disease; DP: disease progression; PPP: PSMA-PET progression criteria.
- •
Use consistent thresholds: the SUVmean best reflects the global expression of PSMA. Use the liver as the organ of reference. 22
- •
Emerging parameters: PSMA-VOL and TPL as parameters of prognostic value.
- •
Parameters being investigated: TLQ lesion reflects intralesional heterogeneity and the PSG score normalizes the tumoral uptake with respect to the parotid gland.
- •
Maintain the same radiopharmaceutical and method between studies.
- •
Perform manual correction to exclude physiology and urinary activity.
- •
Tumors with aggressive biology or low PSMA expression (the FDG+/PSMA− phenotype implies a worse prognosis) 2
- •
Hepatic or lytic metastasis.
- •
Suspicion of neuroendocrine dedifferentiation/lineage.
- •
Maintain the same radiopharmaceutical in serial studies.
- •
Take into account the differences of distribution of the different radiopharmaceuticals.
- •
Interpret the PET image taking into account the PSA values, the clinical presentation, possible symptoms and specific biomarkers (AP, LDH).61
- •
Report new lesions due to their high prognostic value.
The systematic use of PSMA-PET for evaluating therapeutic response in mPC has several limitations.
The first is the variability of radiopharmaceuticals. Although they share the same principle active substance, they differ in pharmacokinetic properties that affect biodistribution and interpretation. For example, [¹⁸F]F-PSMA-1007 generates more unspecific bone lesions, while [⁶⁸Ga]Ga-PSMA and [¹⁸F]F-DCFPyL present greater difficulty for assessing local recurrence due to their urinary elimination.8,22,63 In addition, the PSMA ligands are not exclusive of the prostatic tissue: they are expressed in other tumors (hepatocarcinoma, renal carcinoma, neuroendocrine tumors, lymphomas, multiple myeloma, among others) and in benign lesions (fractures, hemangiomas), which may produce false positives.8,22 To this we must add the absence of direct comparative studies among radiopharmaceuticals, which limits the optimal selection of the same, despite the individual data showing similar performance in sensitivity and specificity.22
The second great challenge is the lack of standardized criteria for evaluating response. Although systems such as PPP and RECIP 1.0, which include metabolic parameters, have been proposed, their validation is mainly based on retrospective studies.33 There are no prospective randomized studies that confirm their utility in the long term. Neither is there consensus regarding their interpretation: from visual evaluations65 to the PROMISE criteria64 or the E-PSMA report of the EANM.62 A uniform method thar allows comparing results between centers and radiopharmaceuticals is essential.
On the other hand, most studies have been focused on patients treated with [¹⁷⁷Lu]Lu-PSMA-617, while the evidence on their application in other therapies, such as androgen deprivation, is scarce.7 Prospective studies are necessary to define their role in these contexts.
Lastly, there continues to be questions regarding biological factors that influence interpretation, such as the integration of PSA with the PSMA-PET image or the impact of ADT on the overexpression of PSMA.66,67 These aspects are future challenges for optimizing the clinical utility of PSMA-PET as a monitoring tool.
ConclusionsPSMA-PET has become consolidated as a more sensitive and prognostic imaging biomarker for the evaluation of response in mPC, especially within the scenario of mCRPC. With respect to the conventional criteria based on PSA, CT and bone scintigraphy (RECIST 1.1, PCWG3), PSMA-PET allows direct evaluation of total tumoral load, its distribution and the biology of the disease, detecting progression or response earlier and with better correlation with survival.
The specific criteria based on PSMA-PET, such as PPP and RECIP 1.0, represent a change of paradigm in the evaluation of response. RECIP 1.0, in particular, has demonstrated robust prognostic value for overall survival and progression-free survival and elevated interobserver reproducibility, becoming the most solid criteria of reference within the context of [177Lu]Lu-PSMA-617. The combination of PSA + RECIP improves the stratification of risk with respect to the use of PSA alone and has become the criteria of choice for future clinical trials.
The quantification of PSMA-positive total tumoral volume (PSMA-VOL/TTV) and parameters derived from TPL should be considered a central component in the interpretation of PSMA-PET. Significant reductions of tumoral load are consistently associated with a better prognosis in different therapeutic scenarios (radioligands, taxanes, [223Ra], SBRT), while elevated volumes and phenotypic heterogeneity (low or negative PSMA lesions, especially FDG-positive lesions) identify subgroups with a worse survival and fewer benefits from PSMA directed therapy.
The value of PSMA-PET is clearly dependent on the therapeutic context and requires integrated and standardized interpretation. The modulation of PSMA expression by ADT/ARPI (early flare), the differences of biodistribution among radiopharmaceuticals ([68Ga]Ga-PSMA-11, [18F]F-PSMA-1007, [18F]F-DCFPyL) and the specific physiopathology of treatments, such as [223Ra], require adaptation of the time for performing the studies, maintaining the same radiopharmaceutical in serial controls and following EANM/SNMMI 2.0 guidelines and structured reading systems such as PROMISE or E-PSMA.
Despite the increasing robustness of the evidence, PSMA-PET has not yet been completely incorporated into the standard regulatory criteria of response and there continues to be relevant challenges: the need for intercenter harmonization, availability of validated segmentation software, definition of universal thresholds of response and prospective validation of the existing criteria (RECIP 1.0, PPP) in different therapeutic lines and combinations.
All in all, PSMA-PET should already be considered a central tool in decision making in mPC, particularly in mCRPC treated with radioligands, taxanes, ADT/ARPIs, [223Ra] and SBRT. Systematic integration of its information with PSA, clinical context and other biomarkers, together with the adoption of standardized quantitative criteria, constitutes the necessary evolution for advancing towards true precision medicine guided by imaging in PC.


