




Thoracic surgical procedures are increasing in recent years, and there are different types of lung resections. Postsurgical complications vary depending on the type of resection and the time elapsed, with imaging techniques being key in the postoperative follow-up. Multidisciplinary management of these patients throughout the perioperative period is essential to ensure an optimal surgical outcome. This pictorial review will review the different thoracic surgical techniques, normal postoperative findings and postsurgical complications.
Los procedimientos quirúrgicos torácicos están aumentando en los últimos años, existiendo diversos tipos de resecciones pulmonares. Las complicaciones postquirúrgicas varían dependiendo del tipo de resección y del tiempo transcurrido, siendo las técnicas de imagen claves en el seguimiento postoperatorio. El manejo multidisciplinar de estos pacientes durante el periodo perioperatorio es esencial para asegurar un resultado quirúrgico óptimo. En esta revisión pictórica se revisarán las distintas técnicas quirúrgicas torácicas, los hallazgos postoperatorios normales y las complicaciones postquirúrgicas.
Lung cancer is the second most prevalent cancer in the world after breast cancer, and has the highest rate of mortality.1 Early-stage diagnosis corresponds to a better prognosis, especially for patients who are suitable for surgery. Lung cancer is one of the main indications for lung resections.
Thoracic surgery has made some significant advances in recent years, and minimally invasive techniques are being increasingly used which enable optimum clinical results with lower rates of morbidity and mortality. Post-surgical complications vary depending on the type of resection and the time elapsed since surgery.2
Imaging techniques are key in the post-operative follow-up of patients. Chest radiograph is enough in most cases and computed tomography (CT) is only used if a complication is suspected.3
Communication between the radiologist and surgeon, as well as familiarisation with the surgical protocol and with predisposing risk factors are essential for an adequate interpretation of the imaging findings, early diagnosis and optimal care.
The main aim of this image-based article is to go over the different thoracic surgery techniques (both invasive and minimally invasive) as well as the different types of lung resection and their indications, with the goal of enabling the reader to recognise expected radiological findings for each type of lung resection. Likewise, it will explain the radiological findings that correspond with potential post-surgical complications.
Surgical techniquesThe main factors that affect the choice of surgical technique are the location of the lesion, its size, the locoregional disease and the patient’s baseline condition.
Among the minimally invasive techniques (Fig. 1 A–B), the most common is video-assisted thoracoscopic surgery (VATS) which consists of making one or two incisions of less than 3 cm through which a thoracoscope and surgical tools enter.4 Another minimally invasive technique is robot-assisted thoracic surgery which provides the advantage of a better surgical field view and a wider range of movement. However, the disadvantage of this technique is the loss of tactile sensation.5 Both techniques have proven to be as effective as open thoracotomy, involving shorter hospitalisation and fewer complications.6

Surgical techniques: minimally invasive (A, B) and invasive (C–E). A) Video thoracoscopy showing the small incisions (see detail above left) which the thoracoscope and surgical material go through. B) Robotic surgery in which multiple incisions of less than 1 cm are made (5–7). C) Posterolateral approach through the fifth intercostal space. D) Extended posterolateral Shaw-Paulson variant (arrow). E) Anterolateral approach in which an incision is made through the fifth intercostal space below the nipple.
Among the invasive techniques (Fig. 1 C–E) the posterolateral approach is the most common, providing greater exposure of the surgical field. It is carried out through the fifth intercostal space and in some cases, a portion of a rib is resected to facilitate access. The Shaw-Paulson incision is a variant which extends cranially and medially to the scapular rim, and is used to resect tumours of the pulmonary apex. The anterolateral approach is less common, and is usually reserved for procedures which start with VATS but have to change to open surgery due to access problems or complications.
Types of lung resection, indications and normal findingsLung resections can be categorised as anatomical (segmentectomy, lobectomy and pneumonectomy) or non-anatomical (wedge resection); or partial (wedge lobectomy, segmentectomy, lobectomy) or full (pneumonectomy). For a description of the different resection types, their indications and descriptions of normal imaging findings, see Table 1 and Figs. 2 and 3.
Types of lung resection, indications and normal imaging findings.
| Lung resection | Description | Indication | Normal imaging findings |
|---|---|---|---|
| Wedge or atypical resection | Non-anatomical resection in which clear surgical margins are followed | Small tumours, multifocal ground-glass opacities, previous lung surgeries or elderly patients with impaired cardiopulmonary function | Faint increase in density around clips or surgical material and associated soft tissue/laminar atelectasis (Fig. 2) |
| Typical segmentectomy | Anatomical resection of a lung segment that follows the vascular anatomy and segment area | ||
| Lobectomy | Resection of an entire lung lobe, its visceral pleura, airway, vasculature and regional lymph nodes. | First-choice method for early stage non-small cell carcinomas with curative intent | Immediate postoperative period: air and/or fluid in the surgical site, with progressive fluid refilling. |
| Variant: sleeve lobectomy, performed on central tumours that involve the lobar bronchus, with end-to-end bronchial anastomosis | Late postoperative period: mild volume loss of the operated hemithorax with elevated hemidiaphragm, hyperexpansion of the remaining lung and displacement of the mediastinum towards the side of the lobectomy (Fig. 3) | ||
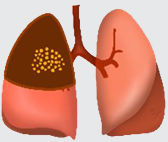
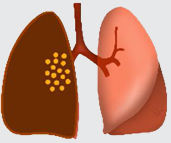
| Pneumonectomy | Complete resection of the lung with ligation of the main bronchus and pulmonary vessels. | Intrapleural: multilobar disease, central tumours or recurrences after previous partial resections. | Immediate postoperative period: almost complete hyperclarity of the involved hemithorax due to the exclusive presence of air. |
| Intrapleural: lung and visceral pleura. | Extrapleural: malignant mesothelioma | Later, progressive accumulation of fluid in the cavity, completely filling within weeks. Gradual mediastinal to ipsilateral shift and hyperinflation of the contralateral lung (Fig. 3) | |
| Extrapleural: en bloc resection of lung, visceral and parietal pleura, hemidiaphragm and pericardium. | |||
| Variants: | |||
| Intrapericardial pneumonectomy, which involves intrapericardial resection of the tumour. | |||
| Sleeve pneumonectomy, resection of central tumour affecting the main bronchus with anastomosis between the residual airway and trachea. |

Normal findings after different sublobar resections. A) Radiograph and B) Axial CT scan of the chest after wedge resection of the left upper lobe showing soft tissue material associated with the surgical material (arrows). C) Radiograph and D) Coronal CT of the chest after an apical left lower lobe segmentectomy showing soft tissue thickening around the post-surgical changes (arrowheads), with minimal lung volume reduction and preservation of the residual bronchus (arrow).

Normal findings after lobectomy and pneumonectomy. A) Chest radiograph after right upper lobectomy showing volume loss of the hemithorax with elevated hemidiaphragm (asterisk), hyperexpansion of the remaining lung (star) and laminar atelectasis adjacent to the surgical material (arrow). B) CT axial view of the same patient showing the surgical material with associated atelectasis (white arrow) and bronchial stump (black arrow). C) Radiography 24 h after right pneumonectomy showing an air-fluid cavity with more air (asterisk) than fluid (arrow). Days later (D), the gas is progressively replaced by fluid (arrow), with an expected mediastinal to ipsilateral shift.
Most postoperative complications happen in the first two weeks after surgery.2 The most common are: atelectasis, aspiration, pneumonia, pleural and pericardial fluid collections, pulmonary oedema and pneumothorax.
Lung and airway complicationsAtelectasis is due to retained bronchial secretions or surfactant impairment.7 Chest radiographs show volume loss, mediastinal shift, and/or an elevated hemidiaphragm in the operated hemithorax, as well as a pulmonary opacity with no air bronchograms (Fig. 4 A–B).

Common lung complications. A) Radiography and B) Coronal CT scan of the chest after left lower lobectomy showing complete upper lobe atelectasis (asterisk) due to mucus impaction (arrows). C) Axial CT in a patient with a wedge resection of the left upper lobe (not shown), showing consolidations in both lower lobes compatible with bronchoaspiration pneumonia (asterisks). D) Chest radiograph 24 h after right pneumonectomy (star) showing signs of acute pulmonary oedema in the left lung (asterisk).
The aspiration of gastric secretions and bacterial colonisation are the most common causes of postoperative pneumonia. Prolonged intubation and mechanical ventilation also make it more likely. Post-surgical pneumonias can manifest radiologically in various ways,8,9 including patterns of bronchopneumonia (bilateral patchy opacities, poorly defined nodules, ‘tree-in-bud’ imaging) or a pattern of lobar or segmental pneumonia (Fig. 4C).
Pulmonary oedema is a potentially life-threatening complication which usually begins two to three days after the intervention. It is more common after a right pneumonectomy given that the left lung receives only 45% of the total pulmonary blood flow, therefore tolerating a rise in blood volume less well.7,9 Imaging findings include smooth thickening of the interlobular septa, ground-glass opacities, peribronchial thickening and pleural effusion (Fig. 4D).
Lobar torsion is a surgical emergency in the immediate postoperative period, nowadays rare due to prophylactic pneumopexy. Lobar torsion consists of the residual lung rotating around its bronchovascular axis, causing vascular and airway compromise. Torsion most commonly affects the middle lobe after a right upper lobectomy, followed by the lingula after lingular-sparing left upper lobectomy.10 Reported risk factors include complete interlobar fissures, a large pleural effusion in the operated hemithorax and transection of the lower pulmonary ligament. Lobar torsion can make the patient more prone to atelectasis secondary to airway occlusion and haemorrhagic infarction due to vascular compromise (first, venous and then arterial).11 It usually manifests on radiographic images as a consolidation that rapidly increases in volume (due to the oedema and vascular congestion). CT is especially useful as it can show a hypoattenuating consolidation, rotation of the twisted bronchovascular structures at the level of the pulmonary hilum and a tapering or interruption of the affected pulmonary vessels (these last two findings can be better observed on MIP reconstructions) (Fig. 5).12

Lobar torsion. A) Chest radiograph 24 h after right upper lobectomy showing parahilar opacity (asterisk) with clear margins and no air bronchograms. B) The following day there is a clear increase in the size of the opacity and subcutaneous emphysema (‘ginkgo leaf’ sign). C) Coronal MIP CT image showing hypoattentuated (ischaemic) middle lobe with no bronchogram and no vessel enhancement. D) 3D reconstruction of the airway demonstrating amputation at the level where the middle lobe bronchus originates (arrow).
Bronchopleural fistulas (BPF) can appear early or late in the postoperative period. They consist of an abnormal connection between the proximal bronchus and the pleural space.11 It is more common after a right pneumonectomy, given that the right main bronchus is shorter, with less mediastinal surface and is more prone to ischaemia as it only has one bronchial artery. The biggest risk factor is prolonged positive pressure ventilation.13 If it does not resolve quickly enough, BPFs can complicate with pleural empyemas and/or recurrent pneumonias. Suspicion should be raised if radiographs show an increase in the air chamber in the postsurgical cavity. CT studies (Fig. 6) can reveal a connection between the airway and pleural space, and facilitate endoscopic management of these fistulas (sealed with coils, endobronchial valves or biological glues). If the patient does not respond to these measures or pleural drainage, surgical intervention may be required (stump coverage with a vascularised flap).10

Bronchopleural fistula. A) Axial CT scan after right pneumonectomy showing small gas bubbles (circle) surrounding the bronchial stump and an air-fluid level (arrows) in the pleural space. Four weeks later, a large defect in the bronchial stump is visible (short arrow). The patient underwent a thoracotomy with gauze packing of the pleural space (asterisks). Note the left subpleural opacity (long arrow) of an infectious nature. C) Axial CT scan in a different patient, who had undergone right upper lobectomy 10 weeks earlier, showing a fistulous tract (arrows) between the bronchial stump and the pleural space (asterisk) compatible with a bronchopleural fistula.
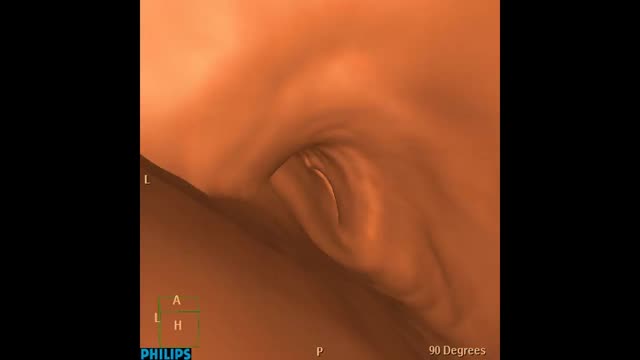
Post-pneumonectomy syndrome is a rare and late complication typical of patients operated on during childhood or adolescence.3,14 It almost always occurs following right pneumonectomies (given the greater right lung volume). It involves a dynamic obstruction of the airway secondary to displacement of mediastinal structures, with strangulation and compression of the airway against the descending aorta and spine (Fig. 7 Appendix B, video 1). Left post-pneumonectomy syndrome occasionally occurs in patients who have a right aortic arch. Patients present with dyspnoea, inspiratory stridor and recurrent pulmonary infections. Expiratory CT and bronchoscopy assess the degree of airway compression. Treatment usually consists of airway stents and/or tissue implants/expanders in the pneumonectomy space.15

Post-pneumonectomy syndrome. Patient with right pneumonectomy who years later presented with dyspnoea and stridor. A) Axial CT, B,C) 3D reconstructions. The left main bronchus (black arrows in A, white in B and C) is stretched and compressed against the left main pulmonary artery (white star in A and C), against the descending aorta (arrowhead in A) and against the spine (black star in A and C). Note the marked hyperinflation of the left lung (asterisk in A and B).
Lung hernias are late-onset complications that involve lung tissue protruding through an intercostal space. They usually occur in patients with a history of thoracotomy, minimally invasive surgery or in connection with previous drainage tubes. They can be better assessed through CT (Fig. 8), and the main complications are strangulation and pulmonary infarction. In patients with symptoms and risk of strangulation, surgery with polypropylene mesh and/or titanium prostheses may be indicated.16

Lung hernia. Patient operated on for right upper lobectomy. A) Coronal CT scan showing protrusion of lung tissue into the intercostal space that the thoracoscope went through (arrow), with signs of vascular congestion. B) 3D volumetric reconstruction identifying pulmonary herniation through the intercostal space (arrow).
Mediastinal and cardiovascular complications include mediastinal haematoma, mediastinal infections, pneumopericardium, cardiac herniation, pulmonary artery pseudoaneurysm (PAP) and vascular stump thrombosis.
Mediastinal haematoma is an early-onset postsurgical complication (Fig. 9). On postoperative radiographs, the mediastinum is usually wider, in part due to the anterior-posterior projection. However, an increase of more than 60%–70% of mediastinal width and a failure to recover the preoperative diameter after the third day mean that this possible complication has to be explored. The CT easily reveals and confirms the presence of a heterogeneous mediastinal collection.

Mediastinal haematoma. A) Chest radiograph three days after hilar and mediastinal lymphadenectomy, showing mediastinal widening (arrow). C) Six days later, the mediastinal widening is more evident (black arrows). Note the newly placed chest tube (white arrow). D) Axial CT confirms a heterogeneous collection (asterisk) in the anterior mediastinum adjacent to the surgical clips (arrowhead) consistent with a mediastinal haematoma.
Acute mediastinitis is a life-threatening, but rare, postoperative complication.17 Radiographs show an obliteration of mediastinal lines, mediastinal widening and/or pneumomediastinum. CT images (Fig. 10 A–B) show an increase in mediastinal fat attenuation and trabeculation, reactive lymphadenopathy, collections (with hyperenhancing walls and bubbles inside) and/or pneumomediastinum. There may also be a pleural or pericardial effusion. Surgical treatment is indicated in cases of mediastinitis with osteomyelitis or pleural/pericardial involvement.18

Complications of the mediastinum and pericardium. A) Patient underwent right apical segmentectomy with fever and leukocytosis. Axial CT showing mediastinal fat trabeculation (black asterisk) with a small incipient collection (white asterisk) compatible with mediastinitis. B) Patient underwent right upper lobectomy with infectious symptoms. Axial CT scan shows a hypodense mediastinal collection (white asterisk), thickening and enhancement of both pericardial sheets (white arrows) and pericardial effusion, findings compatible with mediastinal abscess with secondary pericarditis. Note the moderate left pleural effusion (black asterisk). C) Chest radiograph in patient who underwent right posterior basal segmentectomy revealing pneumopericardium (white arrow) with ‘continuous diaphragm’ sign (black arrows).
Pneumopericardium can occur in the context of a bronchopericardial fistula related to positive pressure ventilation,19 or as a consequence of infection by gas-producing germs. The appearance on radiograph and CT characteristically features a pericardium clearly delineated by air density, which when located caudally gives rise to the ‘continuous diaphragm’ sign (Fig. 10 C).
Cardiac herniation is a rare and serious complication (mortality of 40%–50%) which usually happens within 24 h of an intrapericardial pneumonectomy. It is usually triggered by extubation, coughing, postural changes or application of negative pressure through a chest tube.17 Imaging findings differ according to the side affected by the herniation (Fig. 11)21:
- •
Left cardiac herniation. The heart penetrates into the left pleural space, lying completely to the left of the midline. The ventricles can partially prolapse due to the pericardiac defect and strangulate. Furthermore, when the herniated ventricles lie horizontally on the diaphragm, they adopt a ‘flattened boot’ shape.
- •
Right cardiac herniation. The herniated heart rotates anticlockwise around the superior vena cava (SVC), which it can compress, leading to SVC syndrome. The outline of the herniated heart is usually visualised in the empty right pleural space, angled upwards, giving rise to the ‘ice-cream cone’ sign.

Cardiac herniation. A,B) Left heart hernia. A) The chest radiograph shows a cardiac silhouette completely to the left of the midline (asterisk), horizontal with a ‘flattened boot’ morphology. B) Axial CT scan confirms rotation of the heart, with indentation in the free wall of the right ventricle (arrow) revealing the point of strangulation by the edges of the pericardial defect. Note the air-fluid content in the pneumonectomy chamber (asterisk). C–D) Right heart hernia. C) The illustration shows the anomalous situation of the cardiac silhouette, revealing indentation of the residual pericardium where the heart is herniated (arrow), adopting the ‘ice-cream cone’ morphology. D) Axial CT scan reveals complete displacement of the heart to the right.
Pulmonary artery pseudoaneurysm (PAP) is a serious complication and accounts for less than 20% of the causes of bleeding after thoracic surgery. It corresponds to a contained rupture of the pulmonary artery. Clinically it may manifest as haemoptysis or haemothorax, and is diagnosed using chest CT angiography (Fig. 12). Treatment can be surgical or endovascular; PAPs affecting the pulmonary artery trunk or proximal main pulmonary arteries are more severe and difficult to treat.22

Pseudoaneurysm of the pulmonary artery. A) Axial CT scan of the chest two weeks after a left upper lobectomy showing a small alteration of the contour of the left pulmonary artery (arrow). B, C) Three weeks later, the patient presents with dyspnoea and poor general condition. Axial (B) and coronal (C) MIP CT images show a left main pulmonary artery-dependent saccular pseudoaneurysm (arrow) and a bulky left haemothorax due to rupture of the pseudoaneurysm (asterisk).
Arterial stump thrombosis is usually observed as an opacification defect adjacent to the sutures of the main pulmonary artery or the ligated lobar artery. Due to its low embolic risk, anticoagulation is only necessary in cases of rapid growth, convex morphology towards the lumen, or late development (Fig. 13 A–B).23,24

Arterial and venous stump thrombosis. A) Axial CT demonstrates a repletion defect in the pulmonary arterial stump (arrow) in a patient undergoing right lower lobectomy. C) Coronal CT scan of a patient undergoing left upper lobectomy showing a small thrombus in the stump of the left upper pulmonary vein (arrow).
Pulmonary vein stump thrombosis occurs more frequently after left upper lobectomy due to the increased turbulent flow of the left upper pulmonary vein (Fig. 13 C–D). Treatment with anticoagulants is necessary in all cases due to the risk of systemic arterial embolism.2
Pleural complicationsHaemothorax is an early post-surgical complication, with a very low incidence when there are no coagulation disorders. It may occur as a consequence of inadequate haemostasis of the bronchial artery or chest wall vessels, or a suture failure in a main pulmonary vessel. Suspicion is raised when radiographs show the appearance and quick growth of a pleural effusion. On CT it is seen as a high-density pleural effusion (>50 HU), which may be heterogeneous due to the presence of clots7,8 (Fig. 14 A).

Pleural complications: haemothorax, chylothorax and postoperative empyema. A) Coronal MIP CT angiography showing abundant pleural fluid with high attenuation values and active contrast extravasation (arrow) compatible with haemothorax with evidence of active bleeding. B) Axial CT image showing moderate right pleural effusion with low attenuation values. Biochemical analysis revealed chylothorax. C) Radiography and D) Axial CT of different patients with post-surgical empyema. The radiograph shows a biconvex collection (arrowhead). CT shows bilateral fluid collections with gas bubbles (arrows), as well as pleural thickening and enhancement (arrowheads).
Chylothorax is the accumulation of chyle in the pleural space due to injury to the thoracic duct. The main risk factor is systematic lymphadenectomy.7,25 On radiograph, chylothorax does not have any specific manifestations but it should be suspected if there is a fast-growing pleural effusion. On CT, chylothorax has variable attenuation, contains proteins and fat, and has almost the same density as water.7,26 (Fig. 14 B).
Empyema is a potentially life-threatening complication, although its incidence has decreased due to advances in surgical techniques and the use of antibiotics (Fig. 14 C–D). It occurs more frequently after a pneumonectomy than after a lobectomy. This complication can be early (due to intraoperative contamination or residual infection in the pleural space) or late (usually as a consequence of a bronchopleural or oesophagopleural fistula).7,9 Suspicion is raised if radiographs show a fast-growing pleural effusion and lentiform morphology. CT is the best imaging tool as it can make visible the presence of a biconvex collection with pleural thickening and enhancement of its walls as well as separation of pleurae (‘split pleura’ sign).3
Oesophageal complicationsOesophagopleural fistulas (OPF) are rare complications consisting of an abnormal connection of the oesophagus and the pleural space (Fig. 15). In the early postoperative period, OPF are usually secondary to a direct oesophageal injury or ischaemia.20 In the late postoperative period, the causative mechanism is usually tumour recurrence or chronic infection.

Oesophagopleural fistula. Patient underwent right lower lobectomy with infectious symptoms. A) Radiograph three days later shows an air-fluid level in the right pleural space (arrow). Two days later (B), there was a rise in the air-fluid level (arrow). Axial CT scan (C) shows an air-fluid level in both pleural spaces, with a higher level in the right hemithorax (asterisks), and enhancement of the pleural sheets. Axial CT (D) reveals communication between the oesophagus and the right pleural space (arrow), compatible with an oesophagopleural fistula.
Radiographic features are similar to those of BPF and include a decreased fluid level and/or the reappearance of air in a previously opacified post-pneumonectomy space.20
The oesophagogram is a useful and specific diagnostic technique. However, it is not very sensitive when it comes to small-calibre fistulas. CT oesophagogram improves the detection of OPFs and enables the assessment of other complications, such as empyema or aspiration pneumonia in the contralateral lung.8,27 Patients with an OPF should discontinue all oral intake and undergo both drainage of the pleural space, and surgical or endoscopic closure of the OPF.21
ConclusionFamiliarity with the different surgical options for treating lung cancer, the normal post-surgical radiological findings and the early detection of complications with imaging techniques is crucial for proper interpretation and optimal care of patients undergoing thoracic surgery.
FundingThis study did not receive any funding.
Author contributions- 1
Research coordinators: S.V.-D.
- 2
Study concept: S.V.-D., J.A.-R., L.G.-S.
- 3
Study design: S.V.-D., J.A.-R., L.G.-S.
- 4
Data collection: S.V.-D., A.G.-H., M.A.G.-B., E.A.-M., J.A.-R., L.G.-S.
- 5
Data analysis and interpretation: S.V.-D., M.A.G.-B., E.A.-M., L.G.-S.
- 6
Data processing: S.V.-D.
- 7
Literature search: S.V.-D., A.G.-H., M.A.G.-B., L.G.-S.
- 8
Drafting of article: S.V.-D., A.G.-H., M.A.G.-B., E.A.-M., L.G.-S.
- 9
Critical review of the manuscript with intellectually relevant contributions: S.V.-D., L.G.-S.
- 10
Approval of the final version: S.V.-D., A.G.-H., M.A.G.-B., E.A.-M., J.A.-R., L.G.-S.
The authors declare that they have no conflicts of interest.
The following are Supplementary data to this article:
Virtual bronchoscopy of the patient from Fig. 7 with right pneumonectomy and post-pneumonectomy syndrome.



