



Corona mortis is a common vascular variant in the pelvis with significant clinical importance. While there is no standardised definition, the term generally refers to any anatomical situation where a vessel—either arterial or venous—crosses over the superior pubic ramus and is thus susceptible to injury. This anatomical course places it at high risk of injury in numerous clinical scenarios, including pelvic trauma and various surgical procedures. The aim of this article is to review the anatomy of arterial corona mortis using computed tomography angiography (CTA) and digital subtraction angiography and to use examples to illustrate the considerable clinical significance of this vascular variant. With its high prevalence and relevance, arterial corona stands out as the leading pelvic vascular variant. Radiologists should be familiar with its anatomy and high haemorrhagic risk, explicitly including it in radiological reports when the clinical situation means it could be of significance.
La corona mortis es una variante vascular frecuente de la pelvis, con una gran importancia clínica. Aunque no existe consenso en su definición, es un término que hace referencia a cualquier situación anatómica en la que un vaso, arterial o venoso, es susceptible de lesionarse en su recorrido al cruzar por encima de la rama iliopubiana. Este recorrido anatómico le confiere un alto riesgo de lesión en múltiples escenarios clínicos, como el trauma pélvico o diferentes procedimientos quirúrgicos. El objetivo de este artículo es revisar la anatomía de la corona mortis arterial mediante angiografía por tomografía computarizada (angio-TC) y arteriografía, e ilustrar con ejemplos la gran relevancia clínica de esta variante vascular. Por prevalencia e importancia, la corona mortis arterial puede considerarse la reina de las variantes vasculares de la pelvis. Es conveniente que el radiólogo esté familiarizado con su anatomía y alto riesgo hemorrágico, para incluirla de manera explícita en el informe radiológico en aquellas situaciones clínicas donde puede resultar crucial.
The vascular anatomy of the pelvis varies significantly between individuals, which has important implications for diagnostic imaging, surgical planning, and interventional procedures.
One of the most commonly encountered variants is the corona mortis. Although it is often classified as an “abnormal” or “aberrant” vessel, the corona mortis is a widely prevalent entity.1,2 Meta-analyses and systematic reviews establish an overall prevalence of approximately 50%. The venous variant is more common than the arterial.3,4
Due to its anatomy, the corona mortis is particularly susceptible to injury in common clinical situations: pelvic fractures, orthopedic surgery of the retropubic and acetabular region, inguinal hernioplasty, urological or gynecological procedures, and even postpartum hemorrhages.3,5–10 Furthermore, active bleeding from a corona mortis injury is often challenging to manage and can cause severe or even fatal hemorrhage, especially in cases where its arterial variant is affected.
This article aims to review the imaging diagnosis of the arterial corona mortis and to illustrate with case examples the important clinical implications of this common vascular variant.
AnatomyThere is no consensus on the definition of the corona mortis. This term is frequently used to describe different anatomical variants, such as the origin of the obturator artery (OA) in the external iliac artery (EIA) or inferior epigastric artery (IEA). It can also refer to any anastomotic connection —whether arterial or venous— between the external iliac system and the obturator vessels originating from the internal iliac system.3,6,11,12 However, an increasing number of authors consider that this term reflects a situation of increased hemorrhagic risk rather than a specific anatomical structure. Essentially, any vessel that crosses the iliopubic branch is at risk of injury and, therefore, may be classified as a corona mortis.13
Its ominous name (“crown of death”) refers to the high risk of life-threatening hemorrhage that exists when this vessel is injured as it crowns the iliopubic branch on its way to the obturator foramen, especially in the arterial variant.7,12,14,15
The variability in the definition of the corona mortis partly explains the significant heterogeneity that exists in the different series describing its prevalence. Generally, the venous type of the corona mortis is considered more common than the arterial type, occurring in approximately 50% of individuals.4,6,12 This distinction is important because although arterial injuries are typically associated with a higher risk of hemorrhage and hemodynamic instability,11 venous corona mortis can be more challenging to detect, whether intraoperatively or through CT angiography, and more difficult to manage if injured.3 In the case of the arterial corona mortis, the literature presents more heterogeneous results: CT studies indicate a prevalence of about 30%,16 while cadaver studies suggest it is closer to 50%.11,17
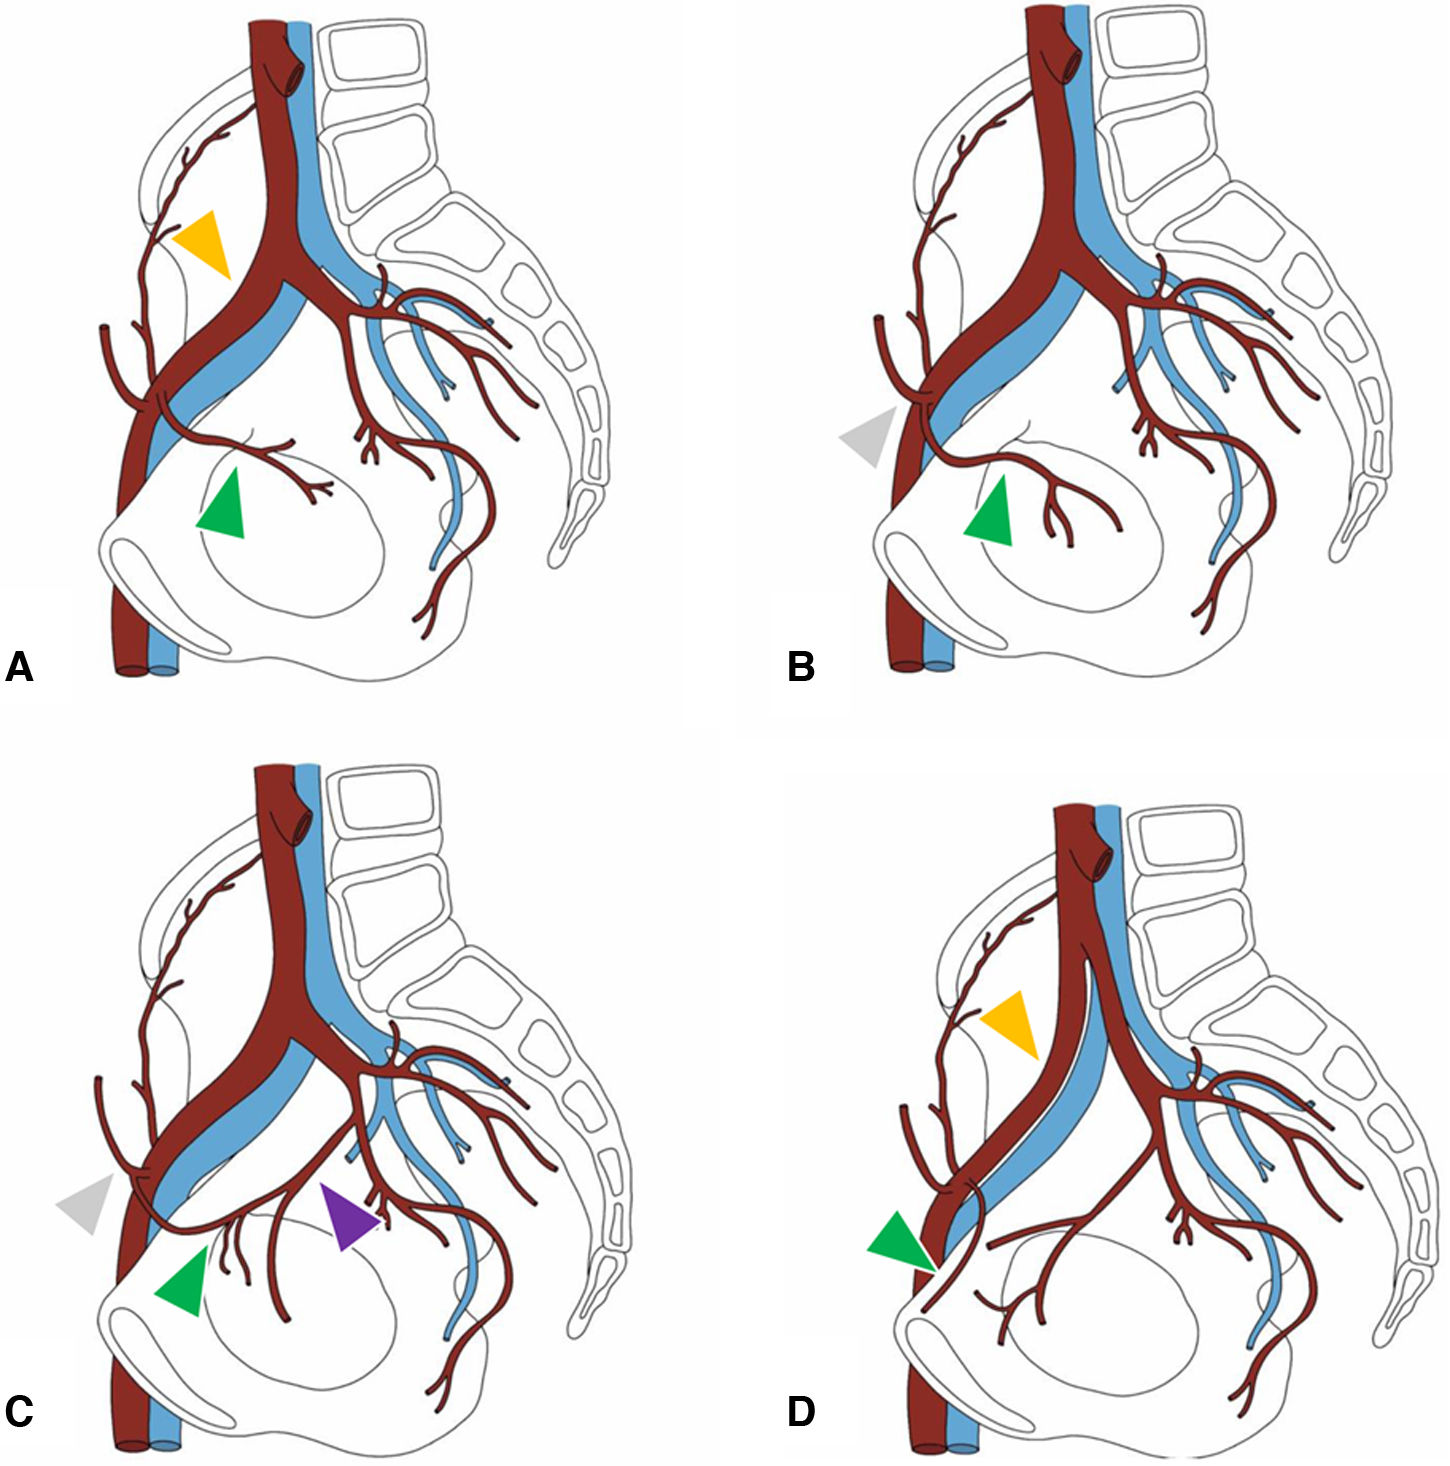
The different arterial patterns of the OA develop during embryonic growth. The development of certain capillary channels relative to others ultimately determines the nature of the anastomotic connection between the EIA and the internal iliac artery (IIA).18 Although there are several classifications for categorizing these types of connections,11,18 none are widely adopted. According to their origin and connection to the OA, four main patterns of the arterial corona mortis can be distinguished11,17 (Fig. 1):
- 1
Origin of the OA in the EIA (64.9%)
- 2
Origin of the OA in the IEA (26.3%)
- 3
Anastomotic connection between the IEA and the OA (7.0%)
- 4
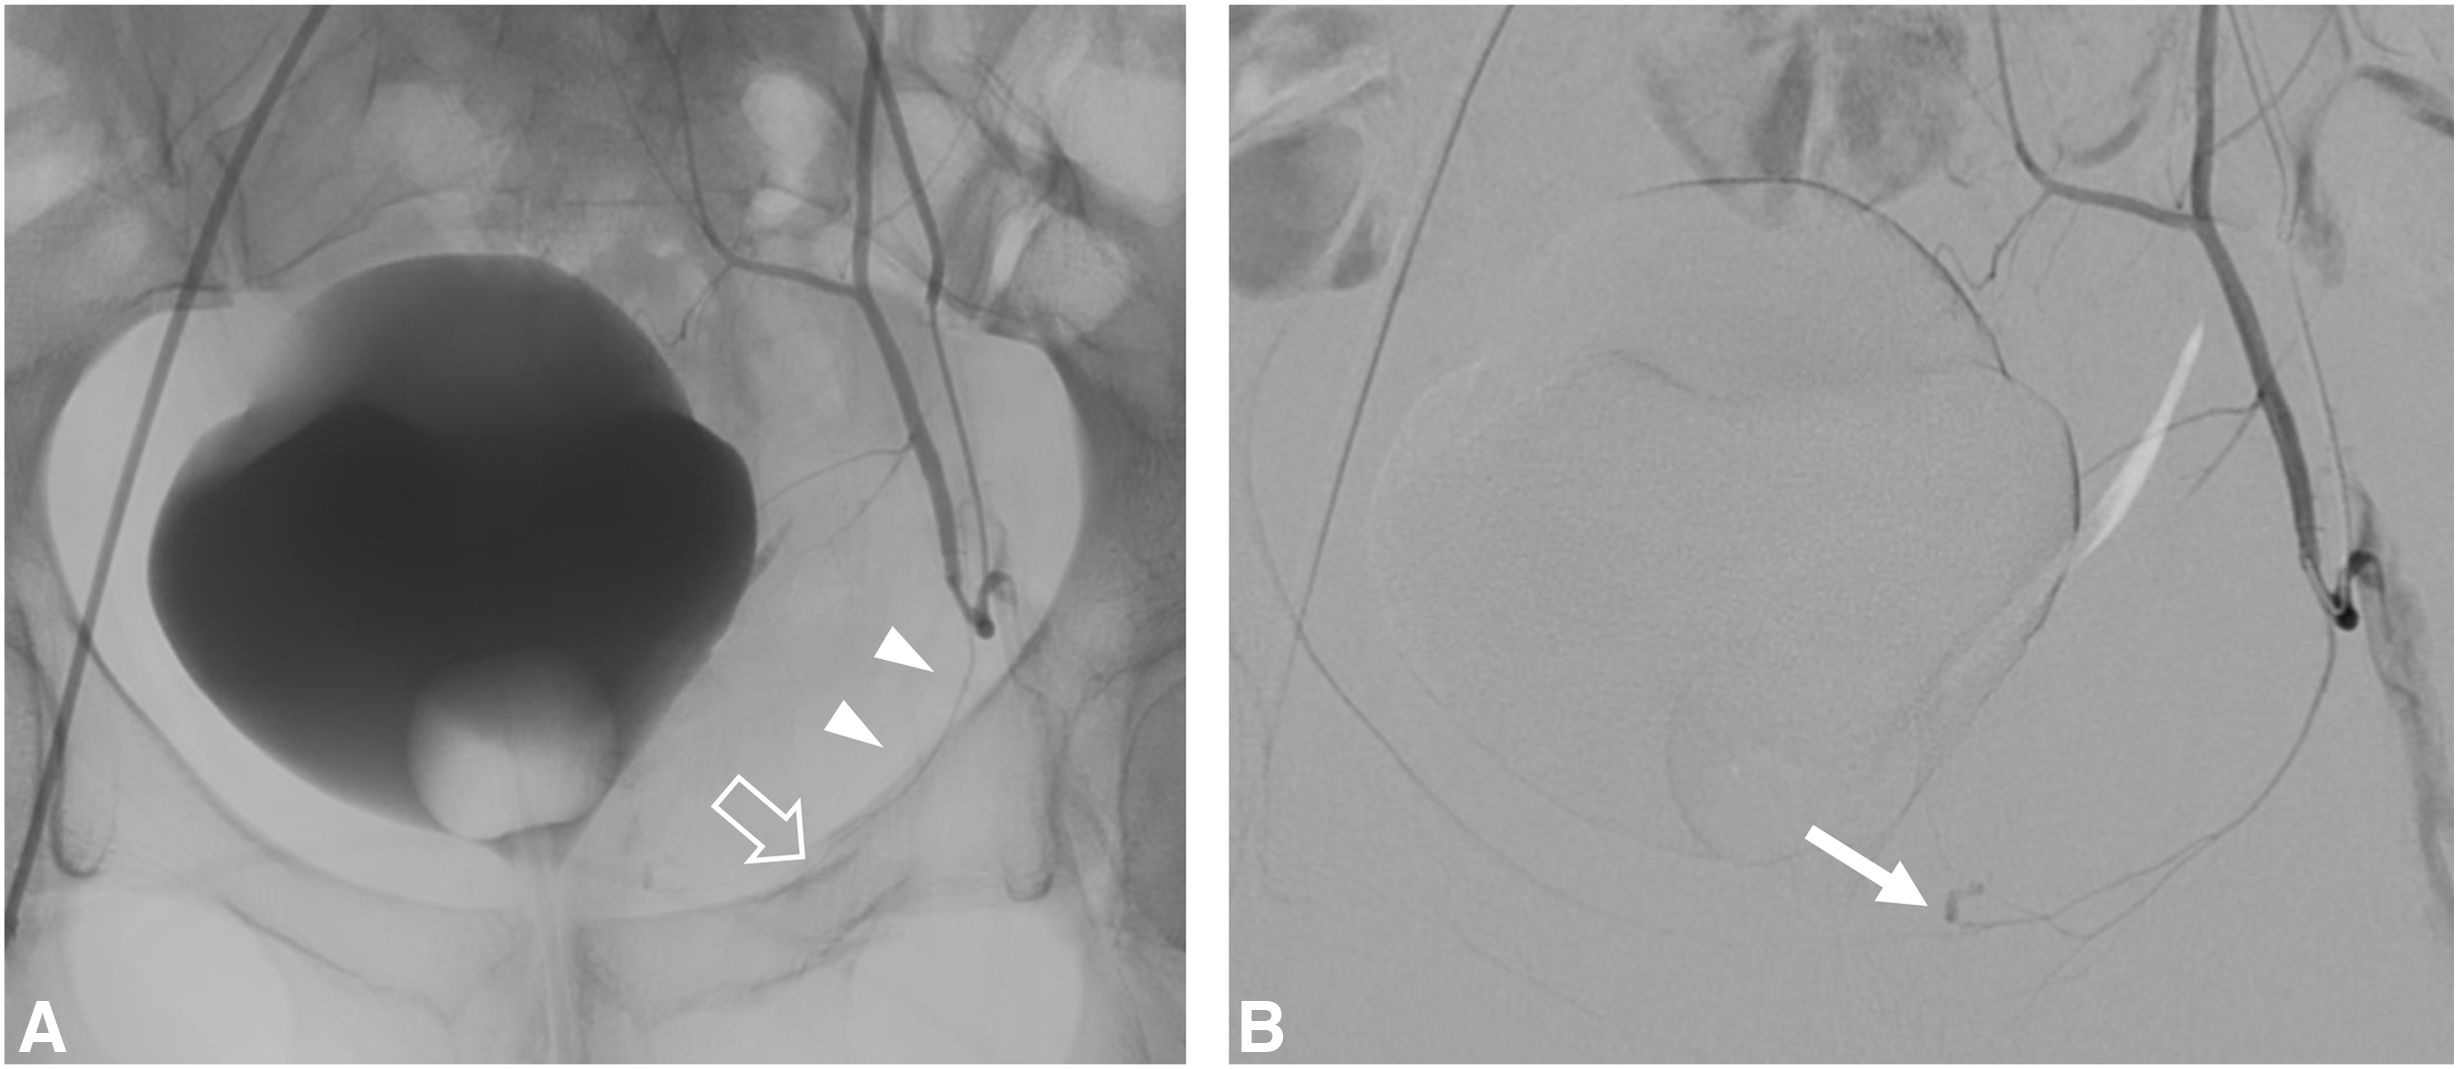
Arterial branch originating from the external or internal iliac arterial system, which crosses the iliopubic branch without forming an anastomotic connection between the two (1.8%) (Fig. 2).
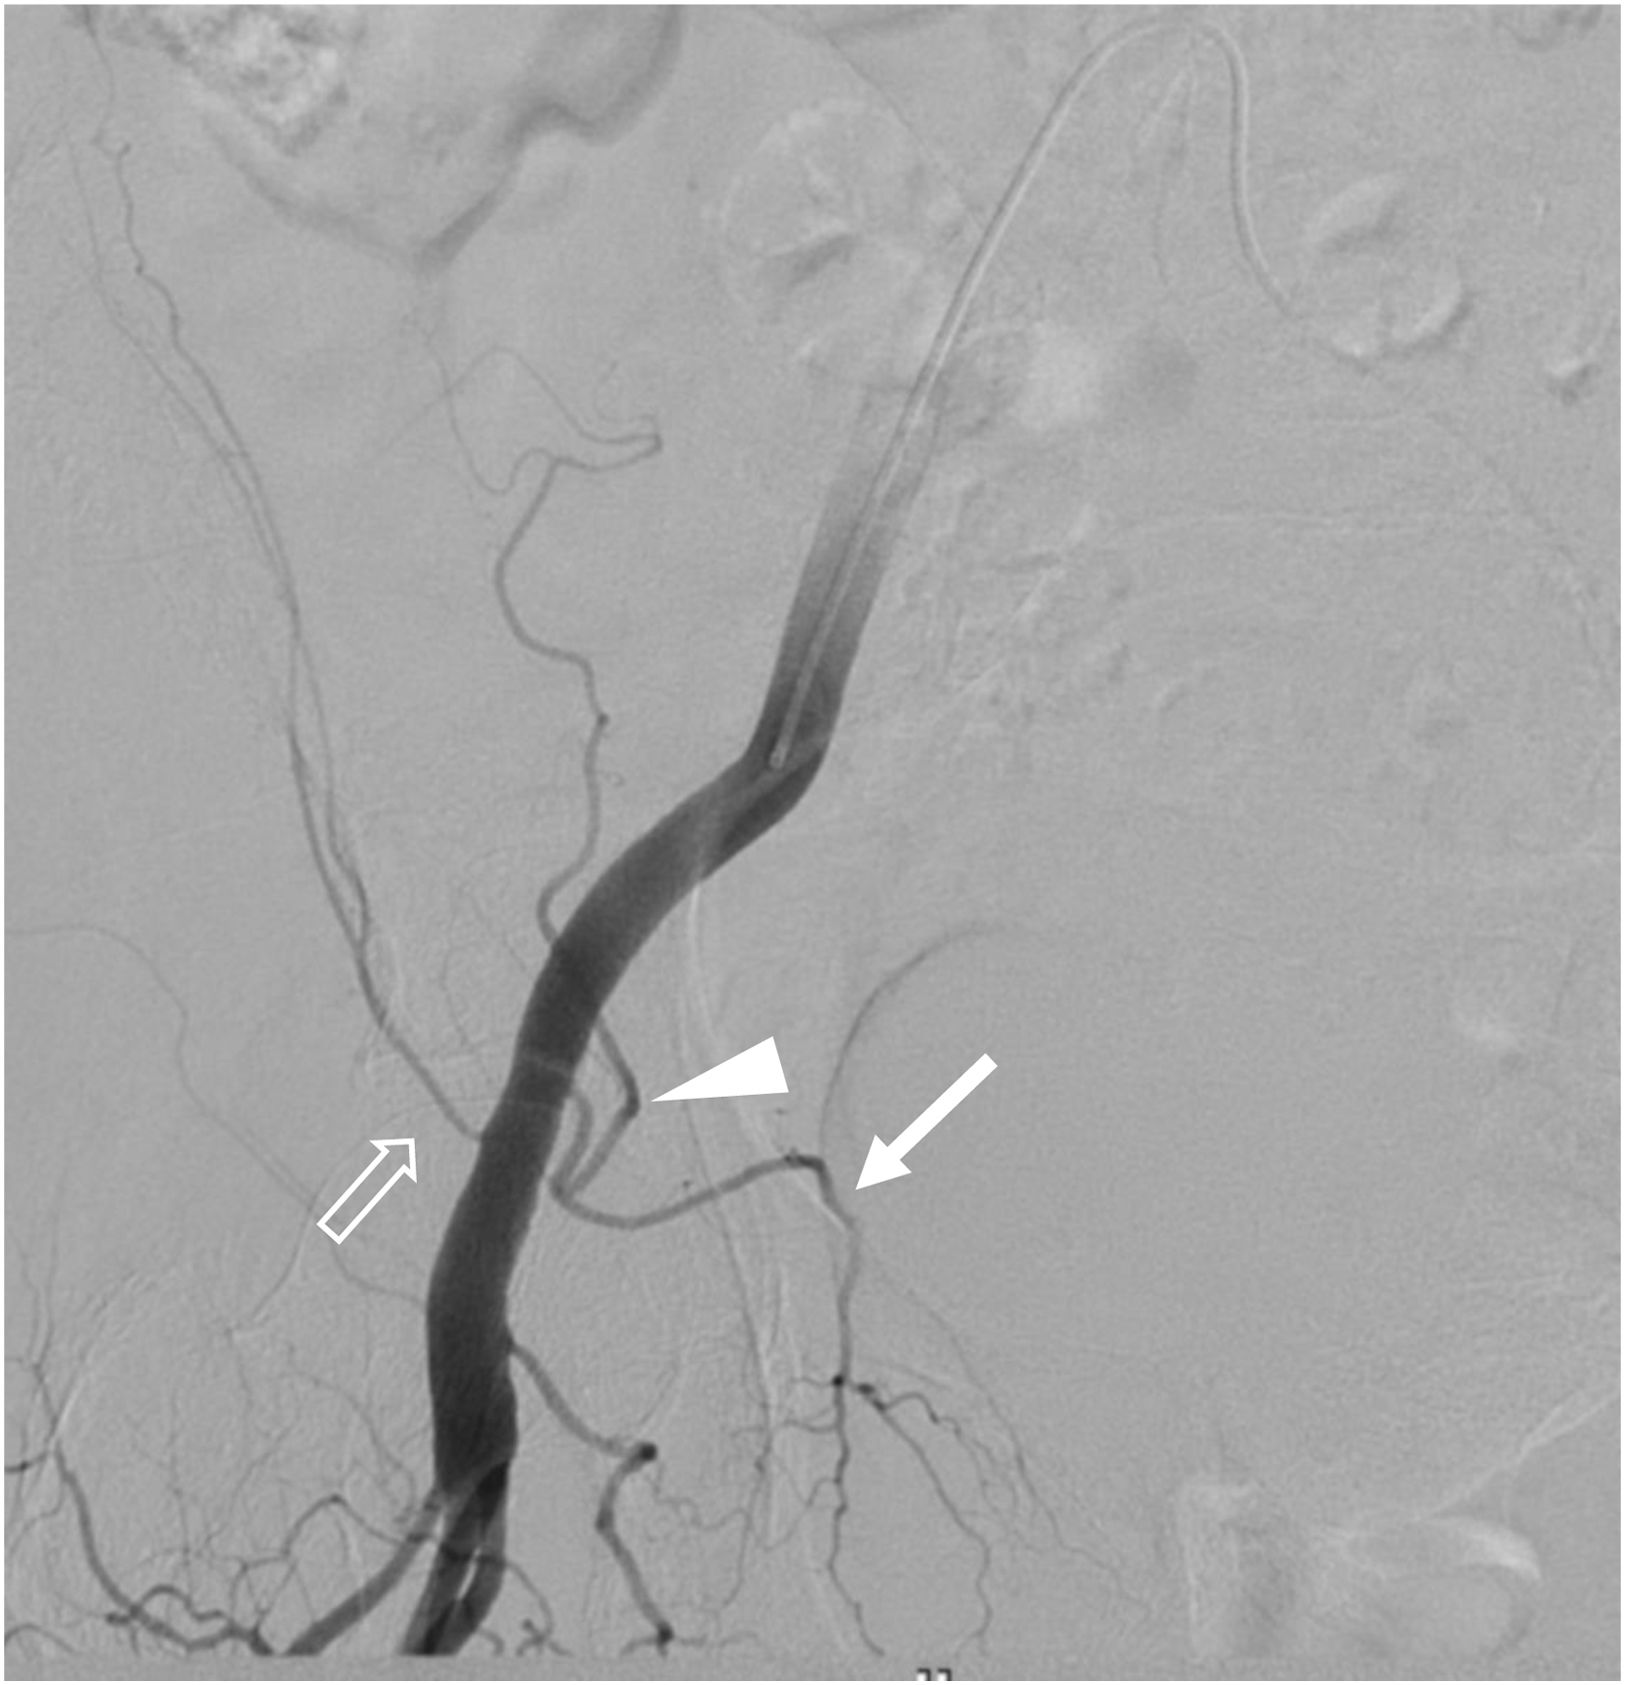
 Figure 2.
A 24-year-old woman who sustained pelvic trauma (hit by a vehicle). During the first hours of observation she developed pallor and diaphoresis. A 3 g/dL drop in hemoglobin was noted. An arterial corona mortis originating from the inferior epigastric artery crosses the superior pubic ramus but does not supply the obturator region or create a connection with the internal iliac system. (A) Non-subtracted arteriography showing the course of this arterial branch over the left superior pubic ramus (arrowheads) with an associated fracture line (hollow arrow). (B) Digital subtraction angiography (DSA) revealing a small focus of active bleeding (arrow) adjacent to the fracture line.


Main variants of the arterial corona mortis. (A) Origin of the obturator artery (green arrowhead) from the external iliac artery (orange arrowhead). (B) Origin of the obturator artery from the inferior epigastric artery (gray arrowhead). (C) Anastomotic connection (green arrowhead) between the inferior epigastric artery and the obturator artery originating from the internal iliac artery (purple arrowhead). (D) Arterial branch (green arrowhead) arising from the external iliac artery, which crosses the superior pubic ramus but does not connect the internal and external iliac arterial systems.
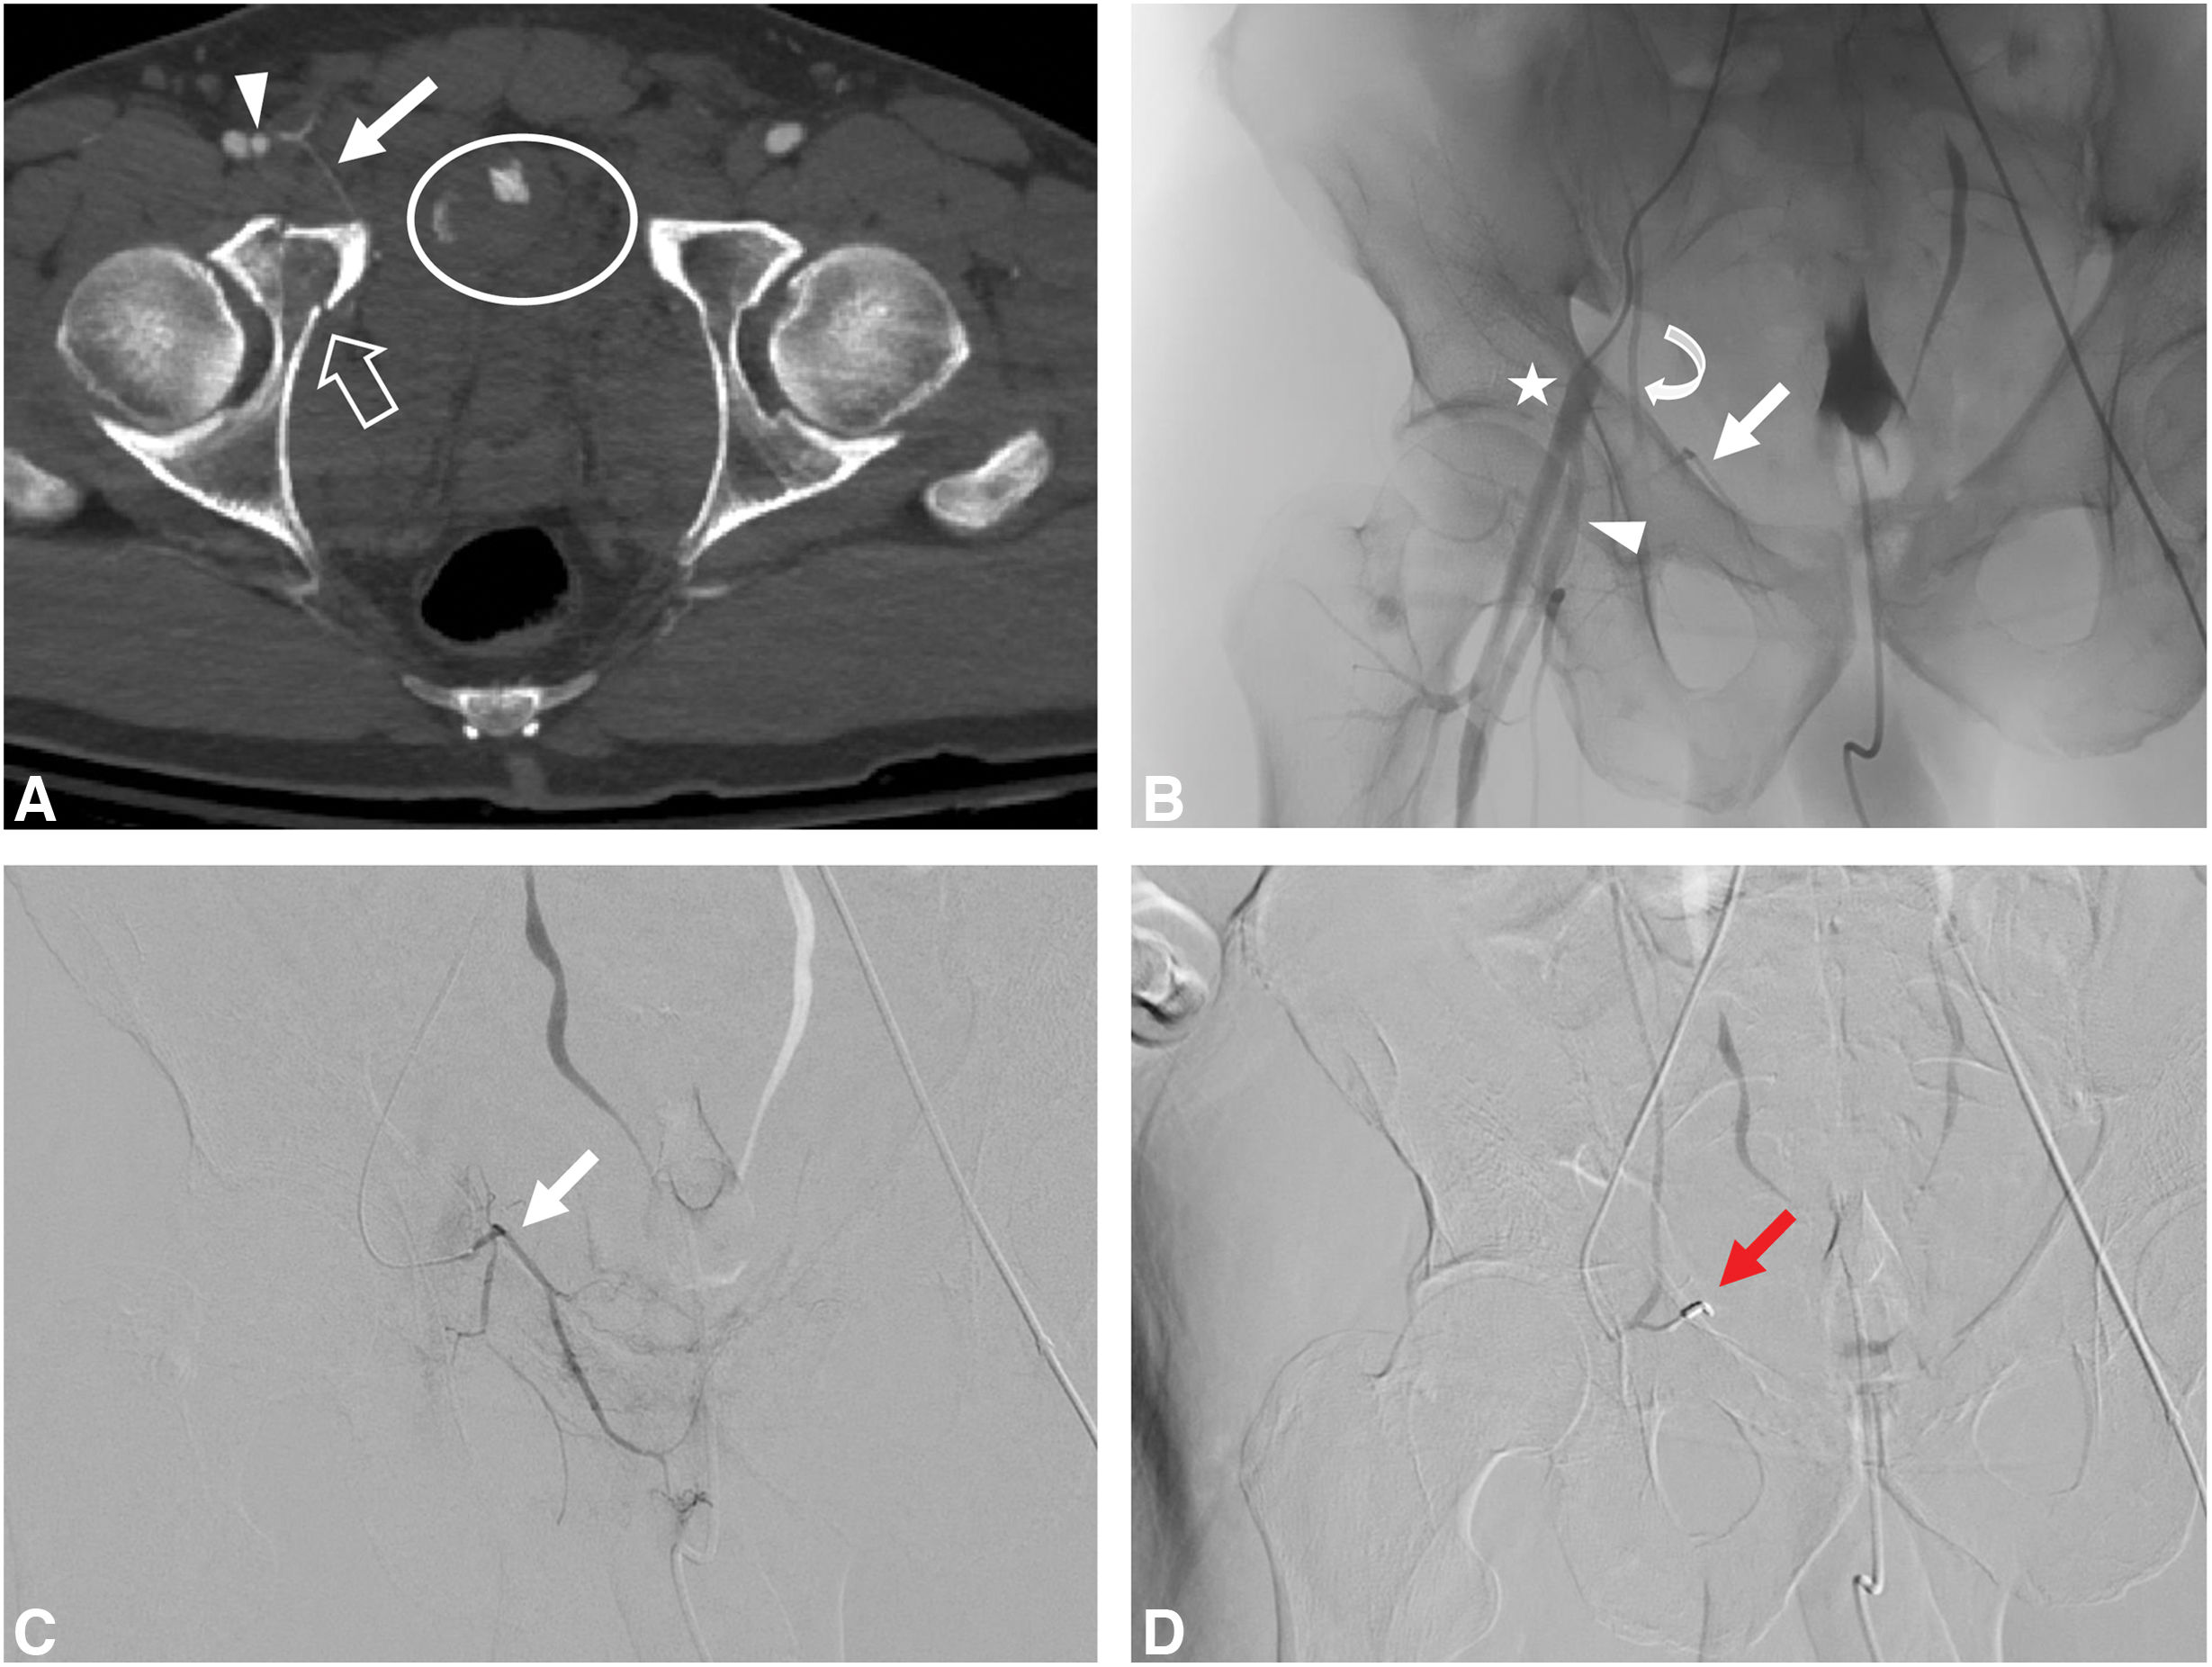
However, anatomical variants may not fit into any of these four main scenarios, so a detailed description in the radiological report is recommended (Fig. 3).

Polytrauma in a 47-year-old male with a 4 g/dL hemoglobin drop. (A) MIP reconstruction of an arterial-phase CTA shows a focus of contrast extravasation (circle) associated with a fracture of the anterior column of the right acetabulum (hollow arrow). Variant origin of the arterial corona mortis (arrow) and the inferior epigastric artery (IEA) from the deep femoral artery (DFA) (arrowhead). (B) Selective arteriography of the right common femoral artery (CFA) confirms the origin of the corona mortis and the IEA (curved arrow) from the DFA. A high bifurcation of the CFA above the femoral head (star) is also observed. (C) Supraselective DSA from the corona mortis shows no evidence of active bleeding at that moment. Empiric embolization is performed given the proximity of the fracture line to the corona mortis and the location of the bleeding focus on CTA. (D) Final control DSA after embolization with 500 µm spheres and microcoils (red arrow).
The arterial corona mortis has an average diameter of approximately 2.5 mm,2,16 which is comparable to that of the average OA19 and approaches the limit for reliable identification during conventional surgical procedures.3 Another important factor for surgical planning and the assessment of pelvic fractures is the distance from the corona mortis to the pubic symphysis, which is generally about 5 cm and tends to be slightly greater in women. Additionally, the arterial corona mortis is less common in patients with a small pelvis, specifically in individuals with inter-acetabular distances of less than 19−20 cm.2,16
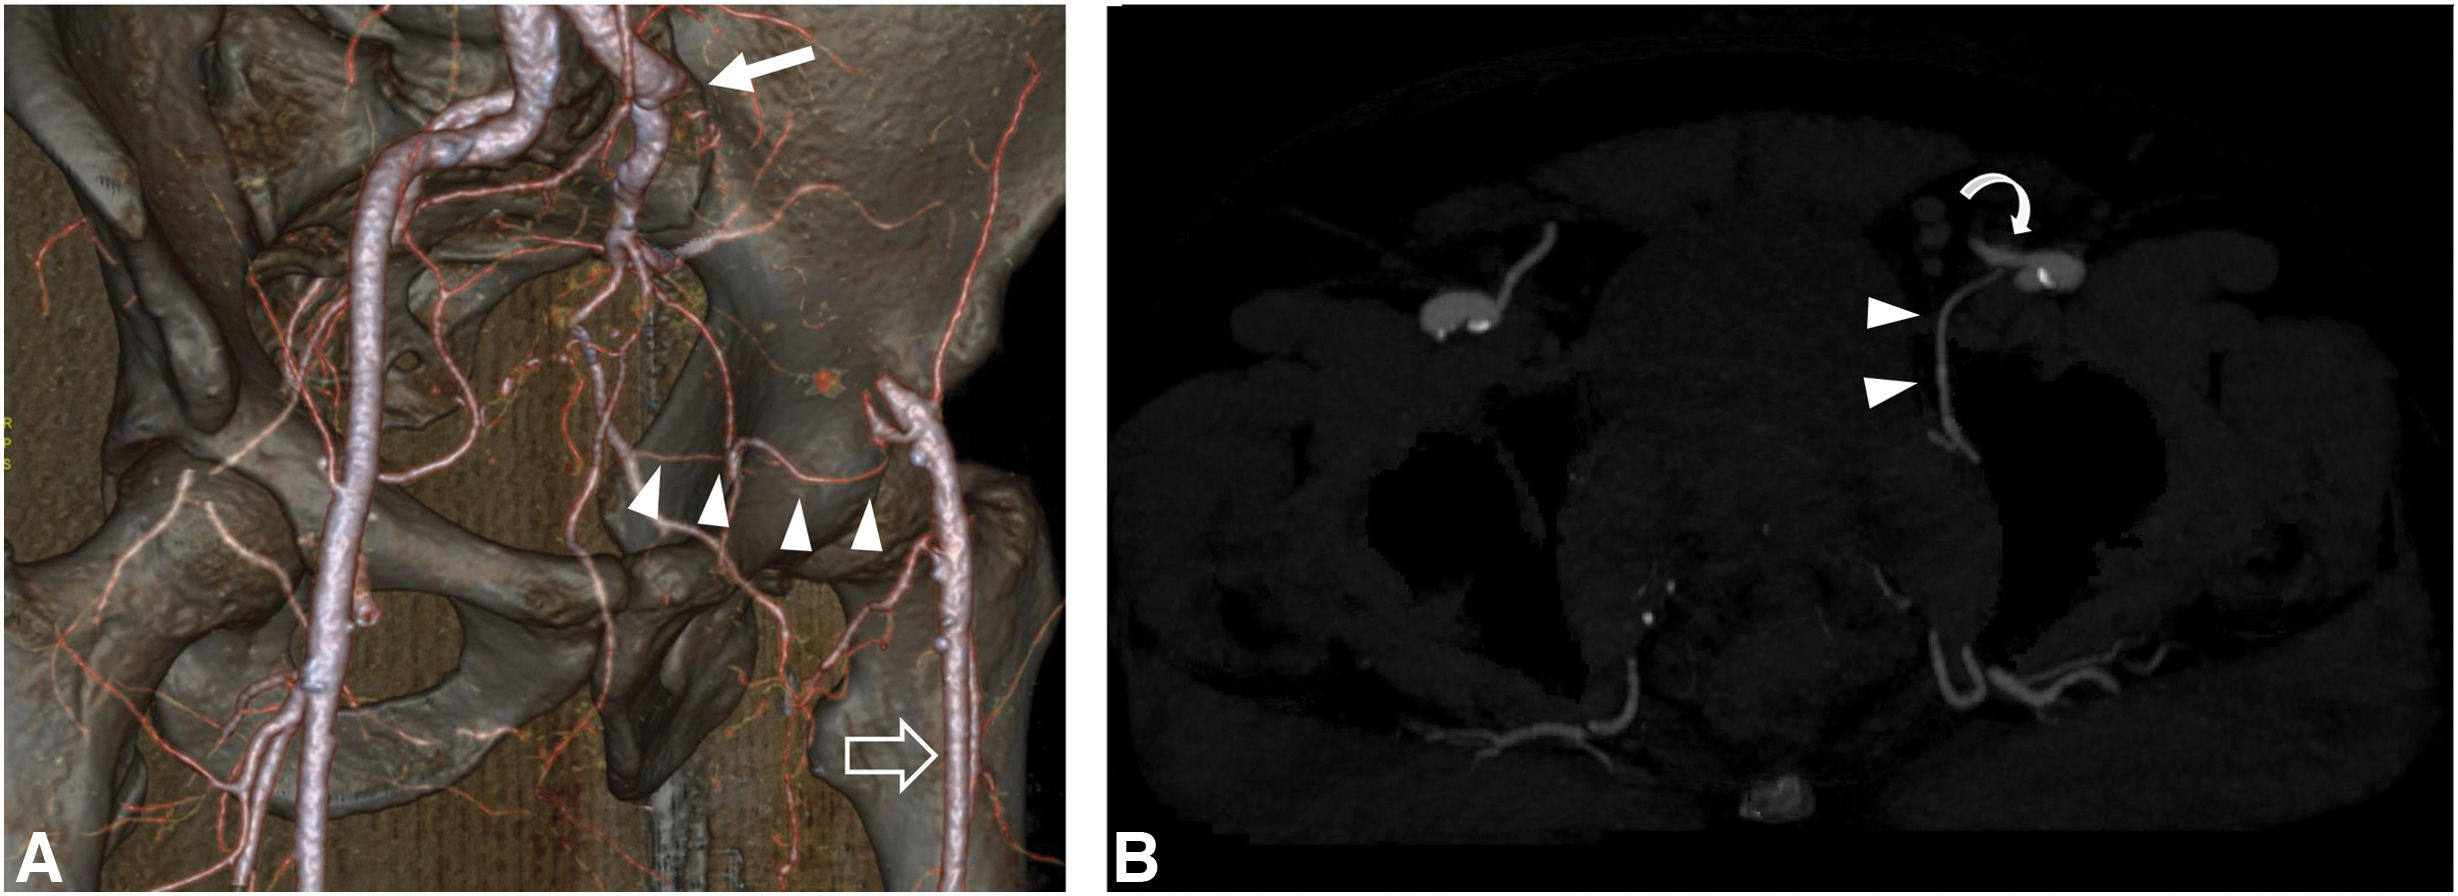
In patients with peripheral arterial disease, the corona mortis may be partially occluded,16 which can complicate its identification using CT angiography and make its catheterization difficult if embolization is required. Conversely, in some patients with occlusion of the iliac axis (EIA or common iliac artery), the corona mortis may be involved in a collateral pathway, acting as a natural bypass1 (Fig. 4).
IT SHOULD BE REMEMBERED THAT the corona mortis refers to any anatomical situation in which an artery or vein is susceptible to injury as it crosses over the iliopubic branch. It is most often used to refer to the arterial variant, which has a prevalence of 30–50%. There exist different arterial connection patterns between the EIA and IAA.

A 58-year-old woman with intermittent claudication (Fontaine stage IIA) in the left lower limb. Collateral pathway through an arterial corona mortis. (A) 3D reconstruction from CTA. An occlusion is identified at the origin of the left external iliac artery (arrow). The corona mortis creates an anastomotic connection between the internal iliac artery and the inferior epigastric artery (IEA) (arrowheads), achieving distal reperfusion of the femoral axis (hollow arrow). (B) MIP reconstruction with bone suppression from an arterial-phase CTA. The anastomotic connection with the origin of the IEA is visible (curved arrow).
The relevance of the arterial corona mortis in the surgical management of the inguinal and pelvic regions is widely recognized, and radiologists and surgeons should be familiar with it.16
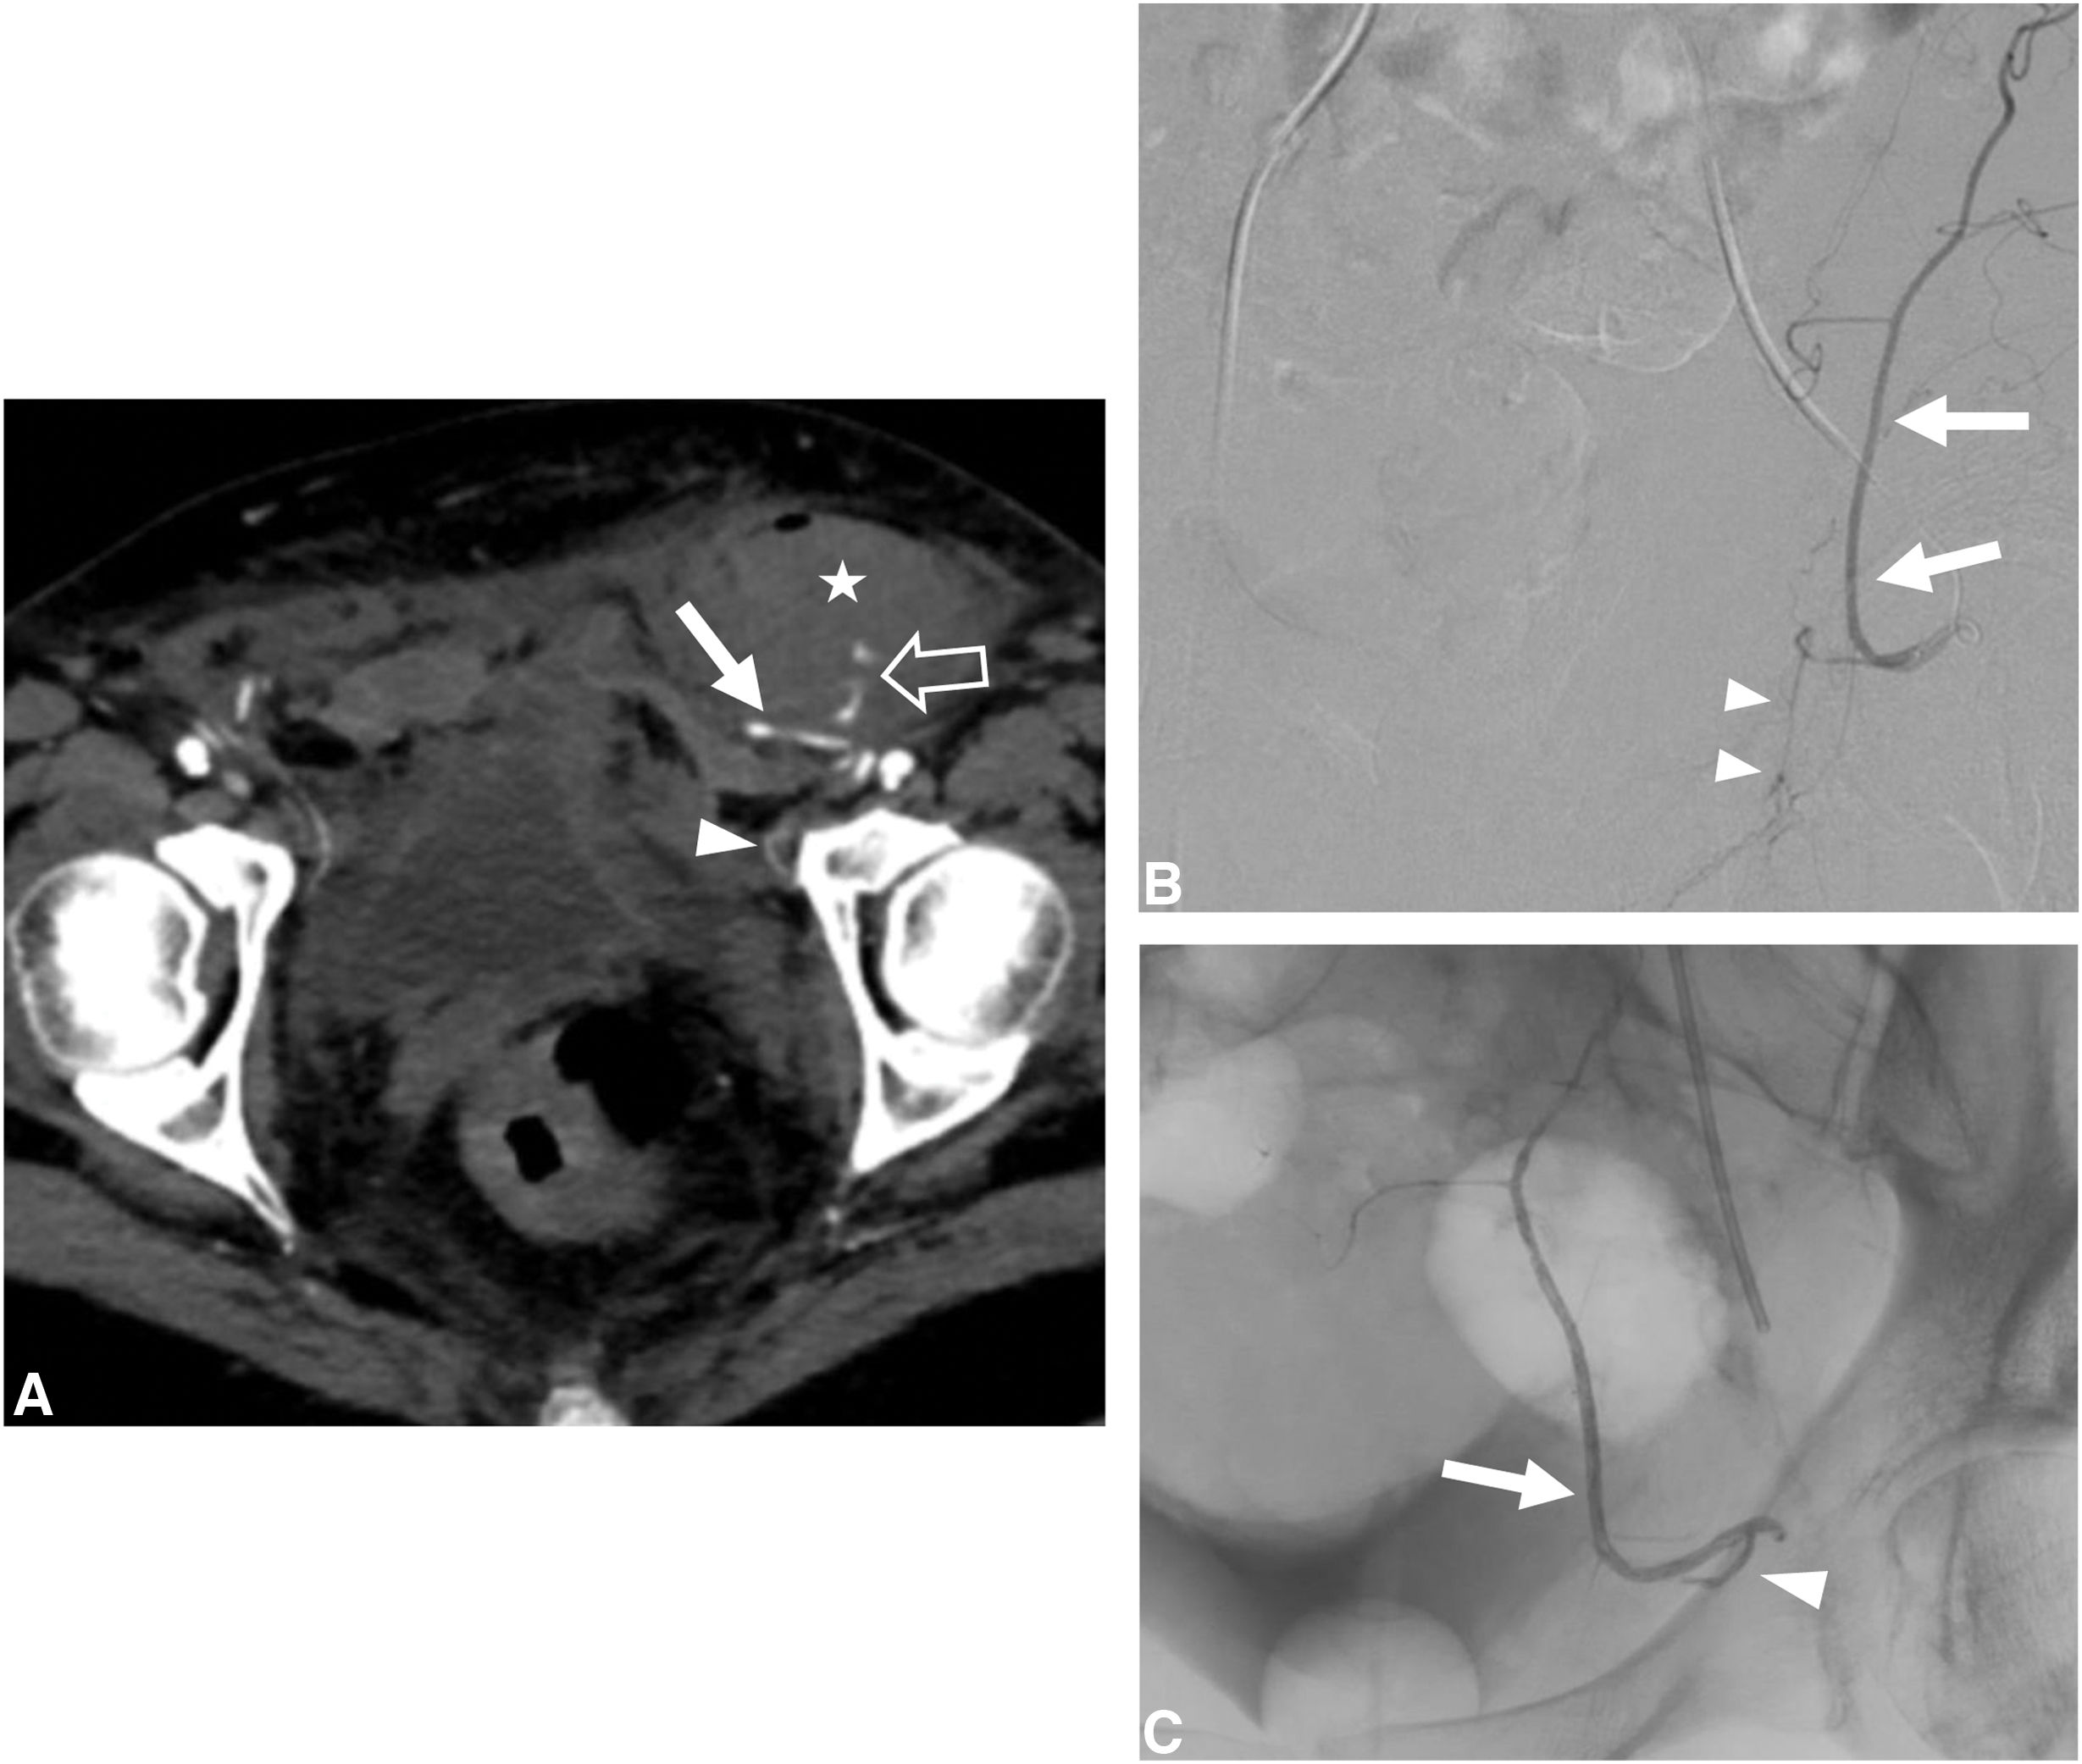
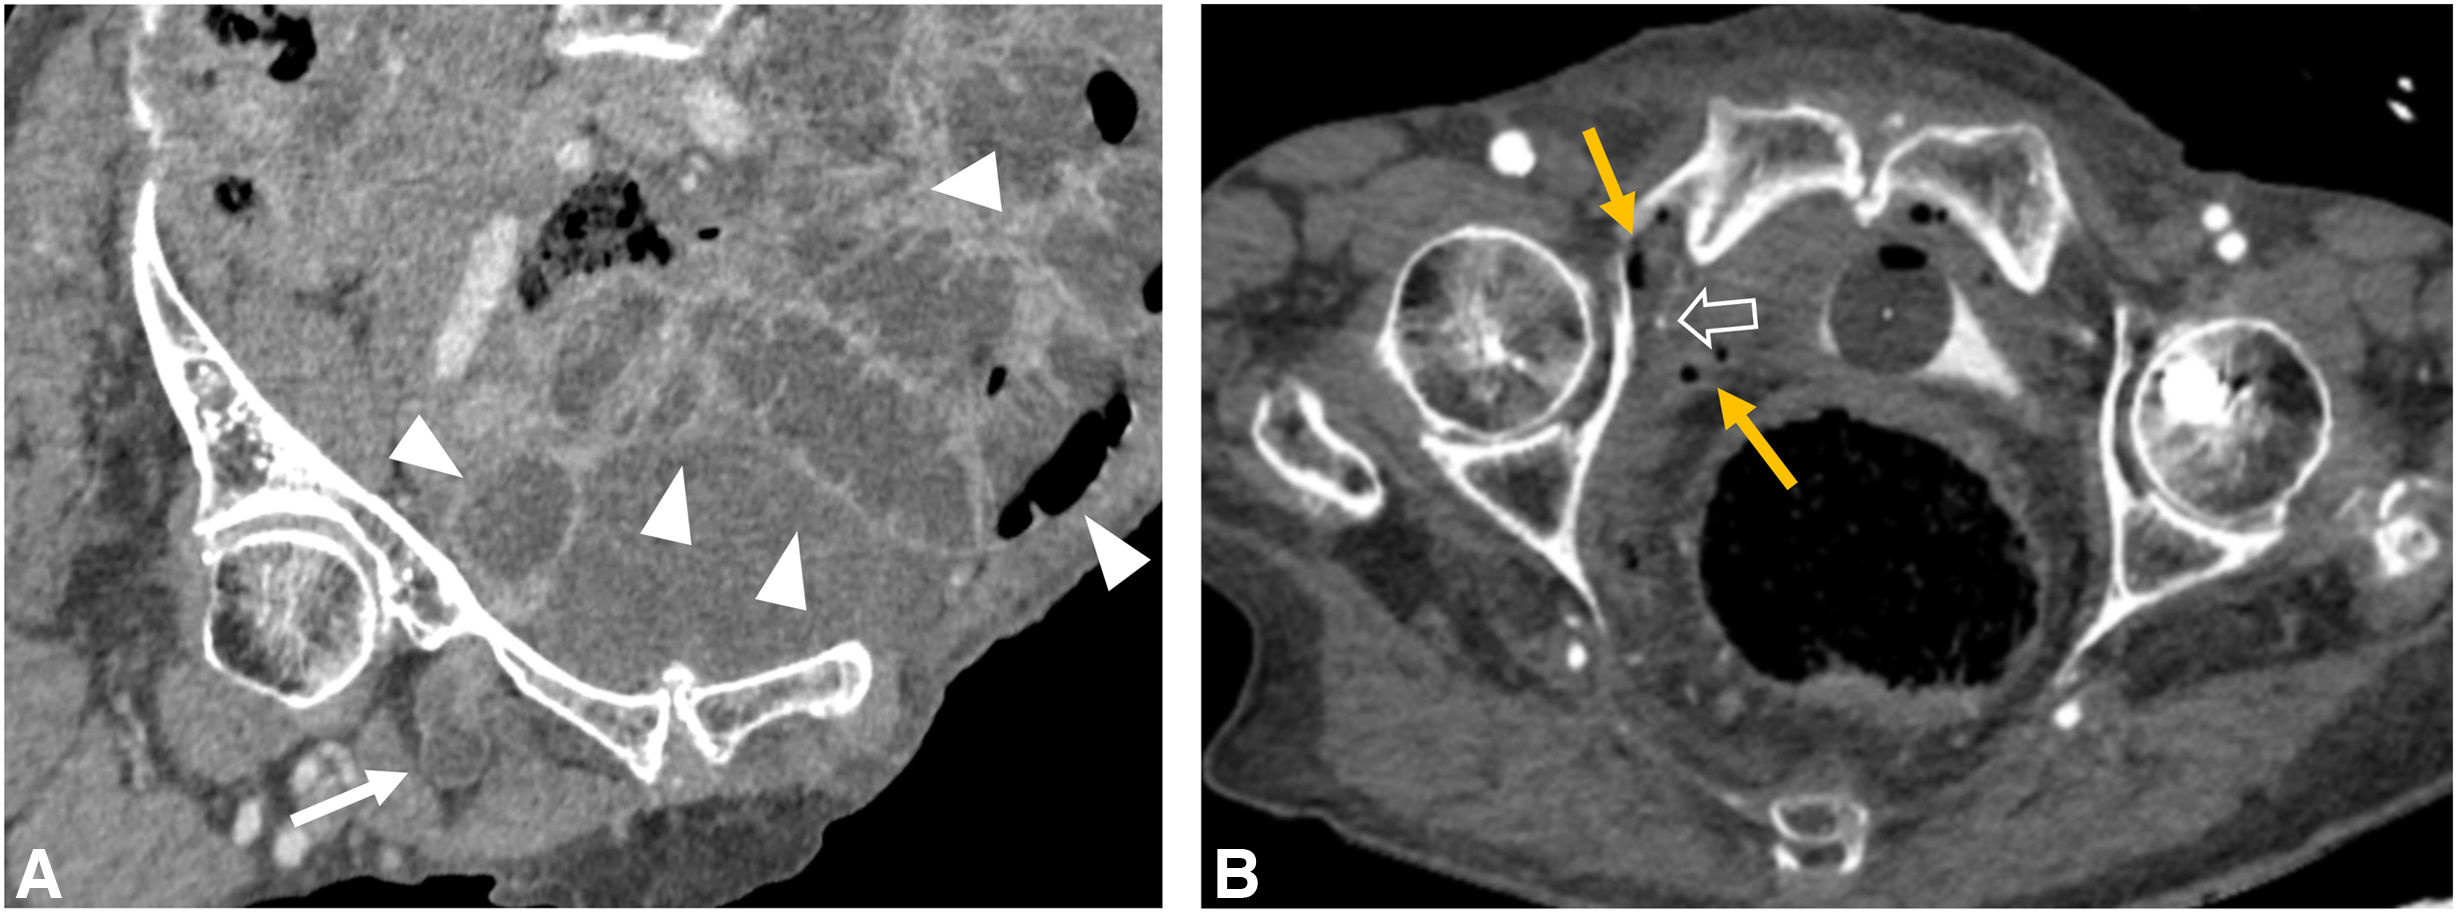
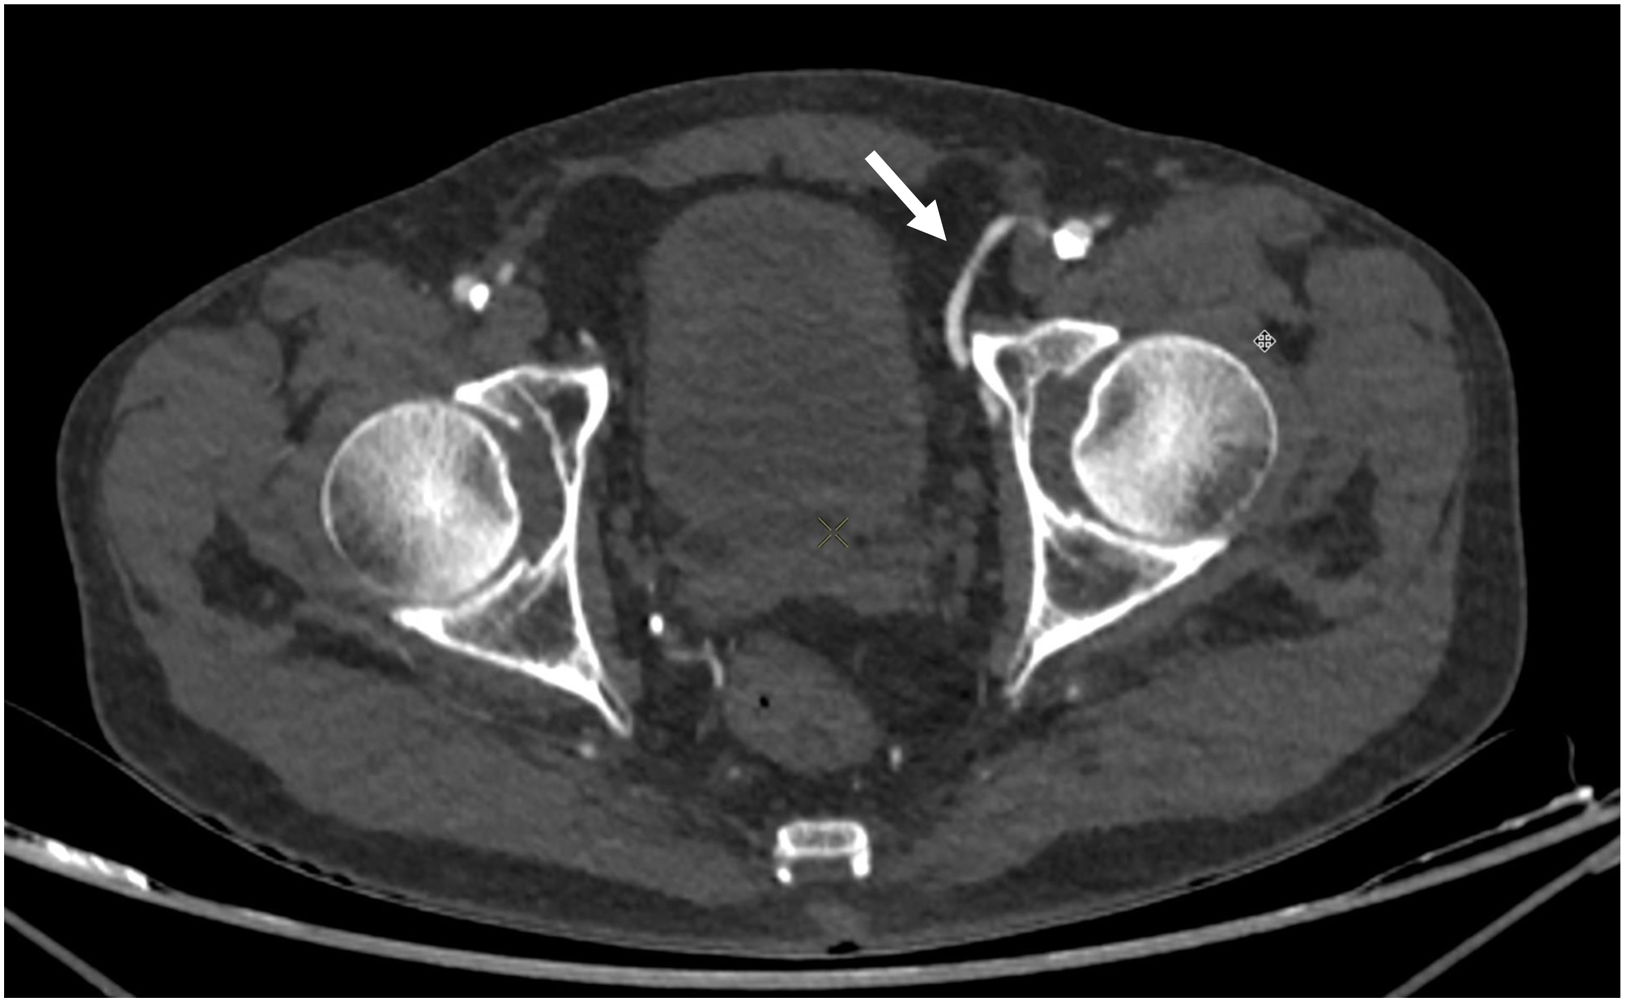
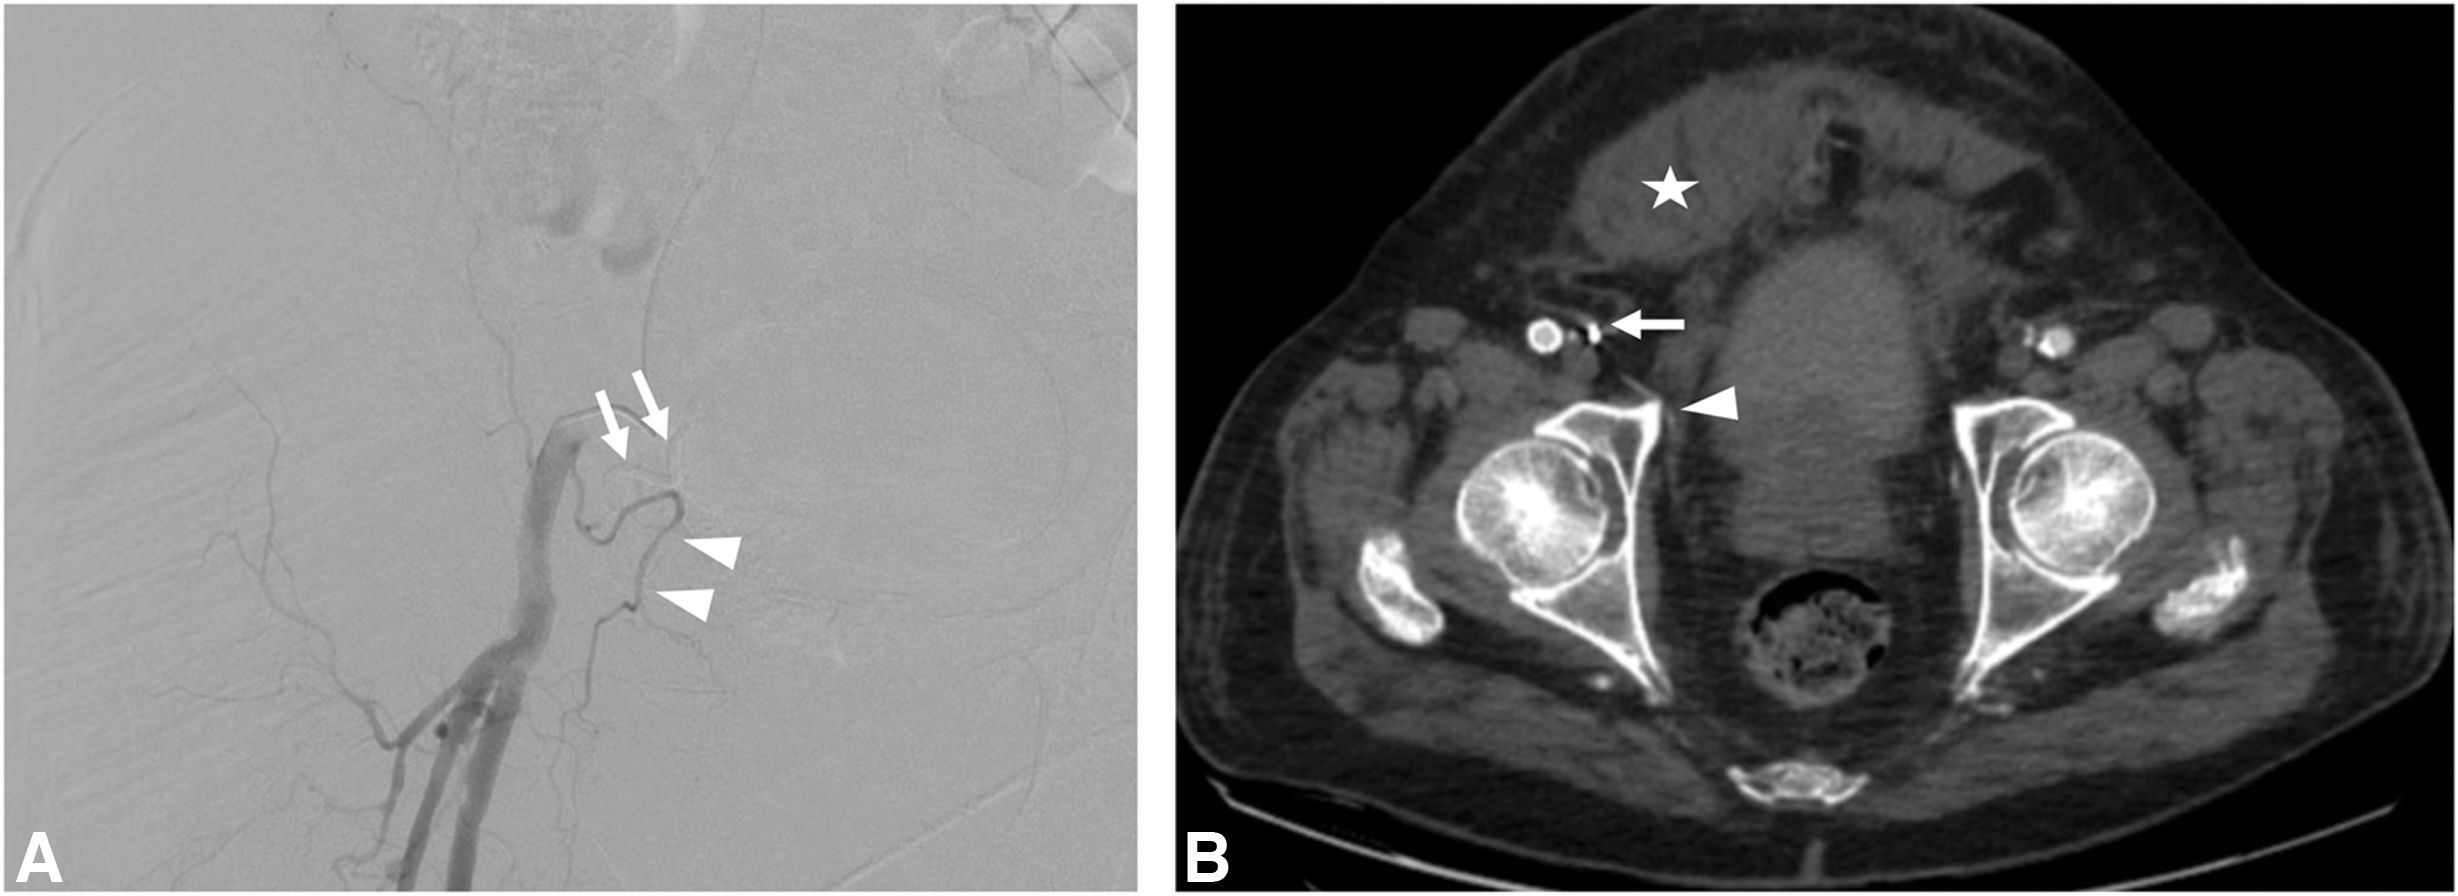
During the laparoscopic approach to inguinal hernia repair, there is a potential risk of injuring the arterial corona mortis during the dissection of the preperitoneal space or hernial sac, as well as from the use of the mesh fixation devices (tacker) (Fig. 5). The reported incidence of such injuries is approximately 1.5%.7,11,13 During the repair of an obturator hernia, the arterial corona mortis is also at risk of injury, although this situation is less frequent (Fig. 6).

A 72-year-old woman who underwent bilateral inguinal hernioplasty via a transabdominal preperitoneal (TAPP) laparoscopic technique. After surgery, a left inguinal hematoma appeared, and her hemoglobin dropped by 2 g/dL. (A) Arterial-phase CTA shows the left inguinal hematoma (star) with a focus of active bleeding (hollow arrow). The obturator artery (arrowhead) originates from the inferior epigastric artery (IEA) (arrow), forming an arterial corona mortis, which was likely injured by the fixation device (tacker) during surgery. (B) Selective DSA identified no extravasation or vascular lesions from the IEA or corona mortis, but empiric embolization was performed. C: Control fluoroscopy image showing the embolic cast using an Ethylene-Vinyl Alcohol copolymer in the IEA and the origin of the arterial corona mortis. Hemostasis was achieved.

A 90-year-old woman who underwent repair of a right obturator hernia. During surgery, bleeding from the corona mortis was noted and controlled. However, her hemoglobin levels continued to drop, and a CTA was requested for evaluation. (A) Preoperative coronal reconstruction of an abdominopelvic CT. A right obturator hernia with intestinal content (small bowel loop) (arrow) is causing bowel obstruction with an abrupt change in caliber and retrograde loop dilatation (arrowheads). (B) Postoperative arterial-phase axial CTA. Air bubbles from the recent procedure (orange arrows) are seen near the arterial corona mortis (arrowhead), which originates from the ipsilateral inferior epigastric artery (not shown). No bleeding foci are observed.
The arterial corona mortis may also be injured during urological and gynecological surgical procedures involving the retropubic region.8,9 Additionally, there are reported cases of arterial corona mortis injury in the context of postpartum hemorrhage.10 While injuries to the arterial corona mortis in these contexts are rare, with only a few cases reported, the consequences can be severe. Sometimes, the injury may not become evident until hours or even weeks after the procedure.
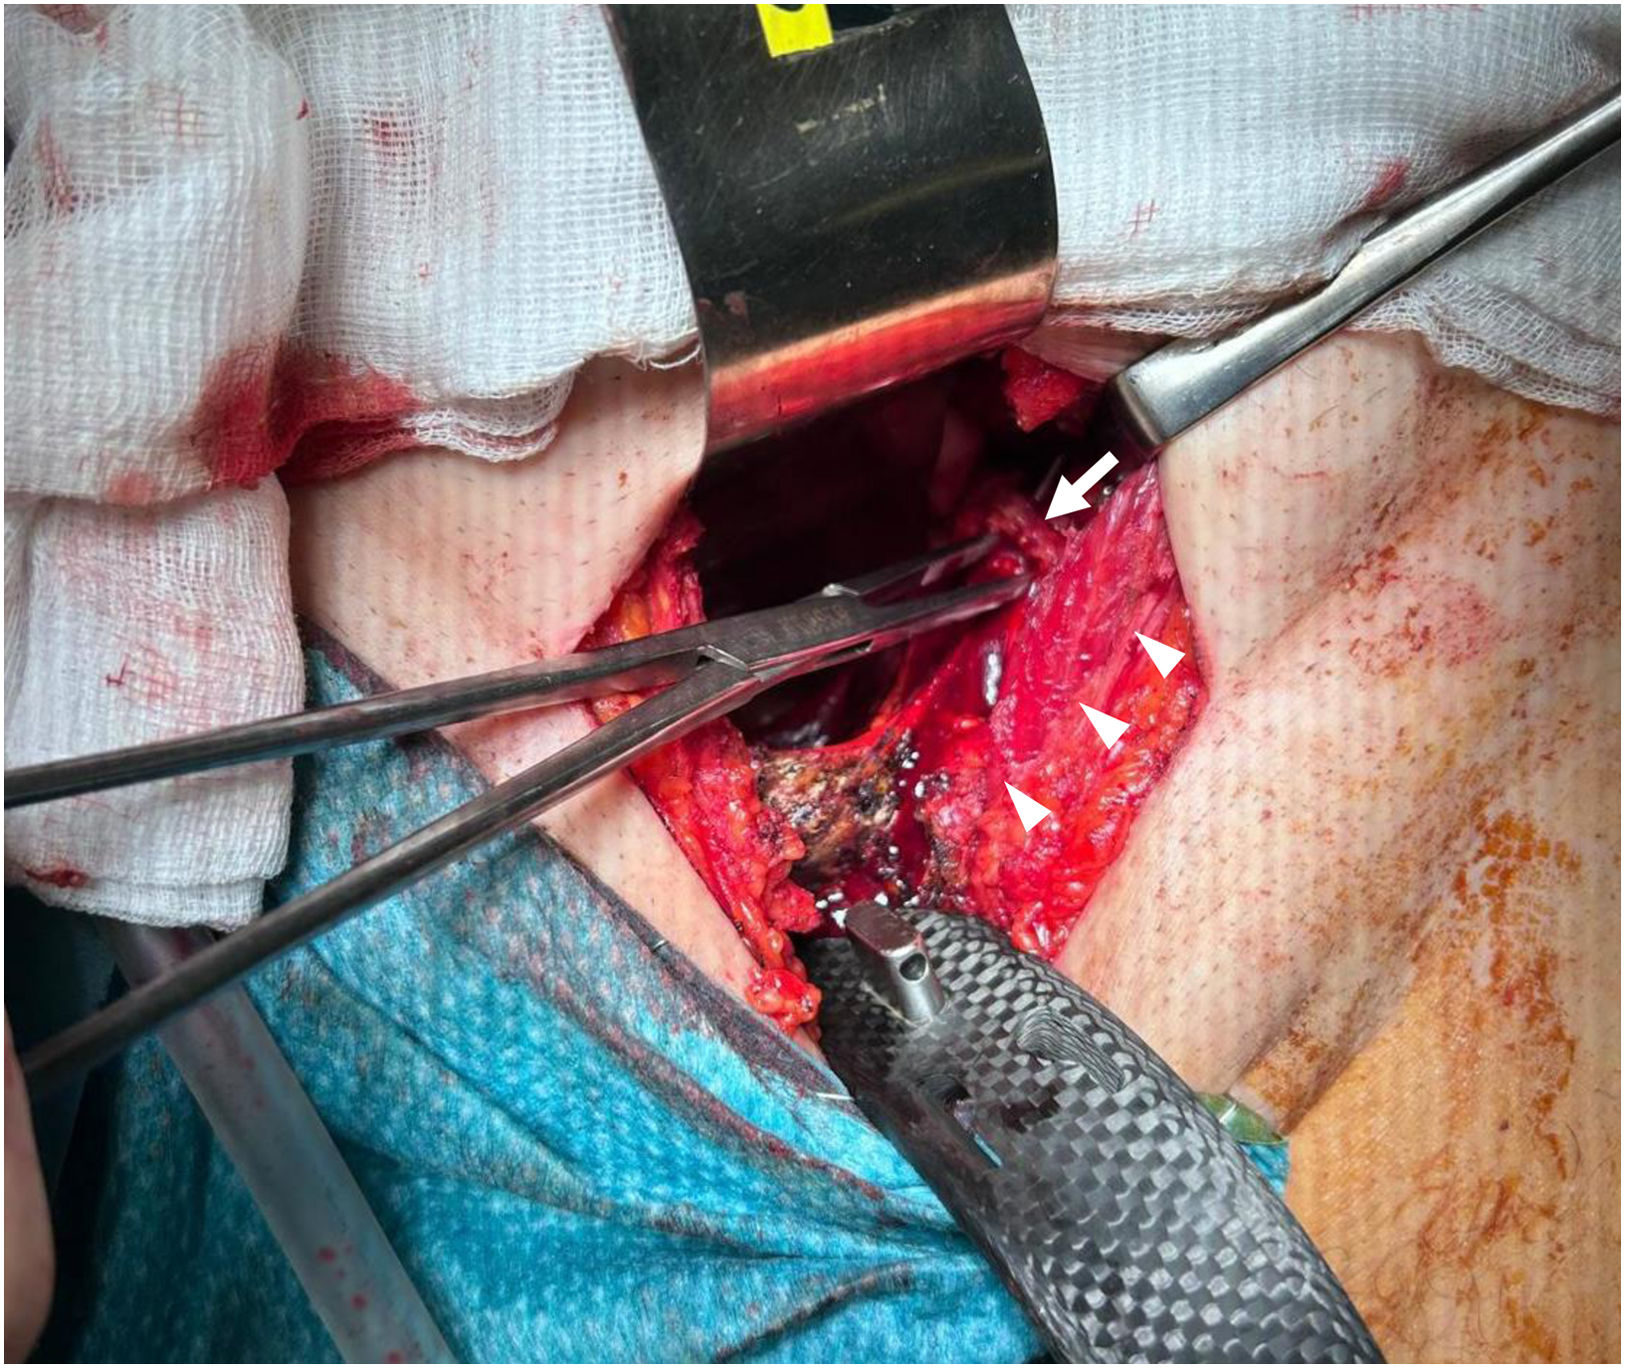
In orthopedic surgery, particularly in the retropubic and acetabular regions, injury to the arterial corona mortis is a rare but potentially significant complication when using modified Stoppa and ilioinguinal approaches. Preoperative identification, careful dissection, and preventive ligation can significantly reduce the risk of accidental injury to this artery during surgery, which likely explains its low incidence (<1%) despite the high prevalence of this variant20,21 (Fig. 7).

Pelvic trauma also represents a typical scenario of high injury risk. Although in this context most active bleedings have a venous origin (80–90%), the incidence of arterial bleeding increases significantly (as high as 60%) in the presence of hemodynamic instability.22–24 The exact incidence of arterial corona mortis involvement in cases of pelvic trauma is not well defined. However, many studies indicate that its presence in patients with pelvic fractures is associated with a higher risk of significant hemorrhage, sometimes with delayed onset.4,6,13 The anatomical path of the artery suggests that this risk is particularly high in fractures involving the iliopubic branch or the acetabulum.5 In addition, numerous reported cases establish that there is also risk of injury of the arterial corona mortis in patients suffering from osteoporotic, low-energy fractures, usually managed conservatively, and not only in high-energy trauma.25
IT SHOULD BE REMEMBERED THAT the arterial corona mortis can be injured in many clinical scenarios, including pelvic trauma and surgical procedures in the retropubic, inguinal, and acetabular regions. Although its injury is uncommon, the consequences can be severe, so radiologists should be familiar with this vascular variant.
As mentioned above, the presence of an arterial corona mortis can have a major impact in various post-surgical and post-traumatic scenarios, acting as a recognized risk factor for major hemorrhages and late-onset vascular complications.
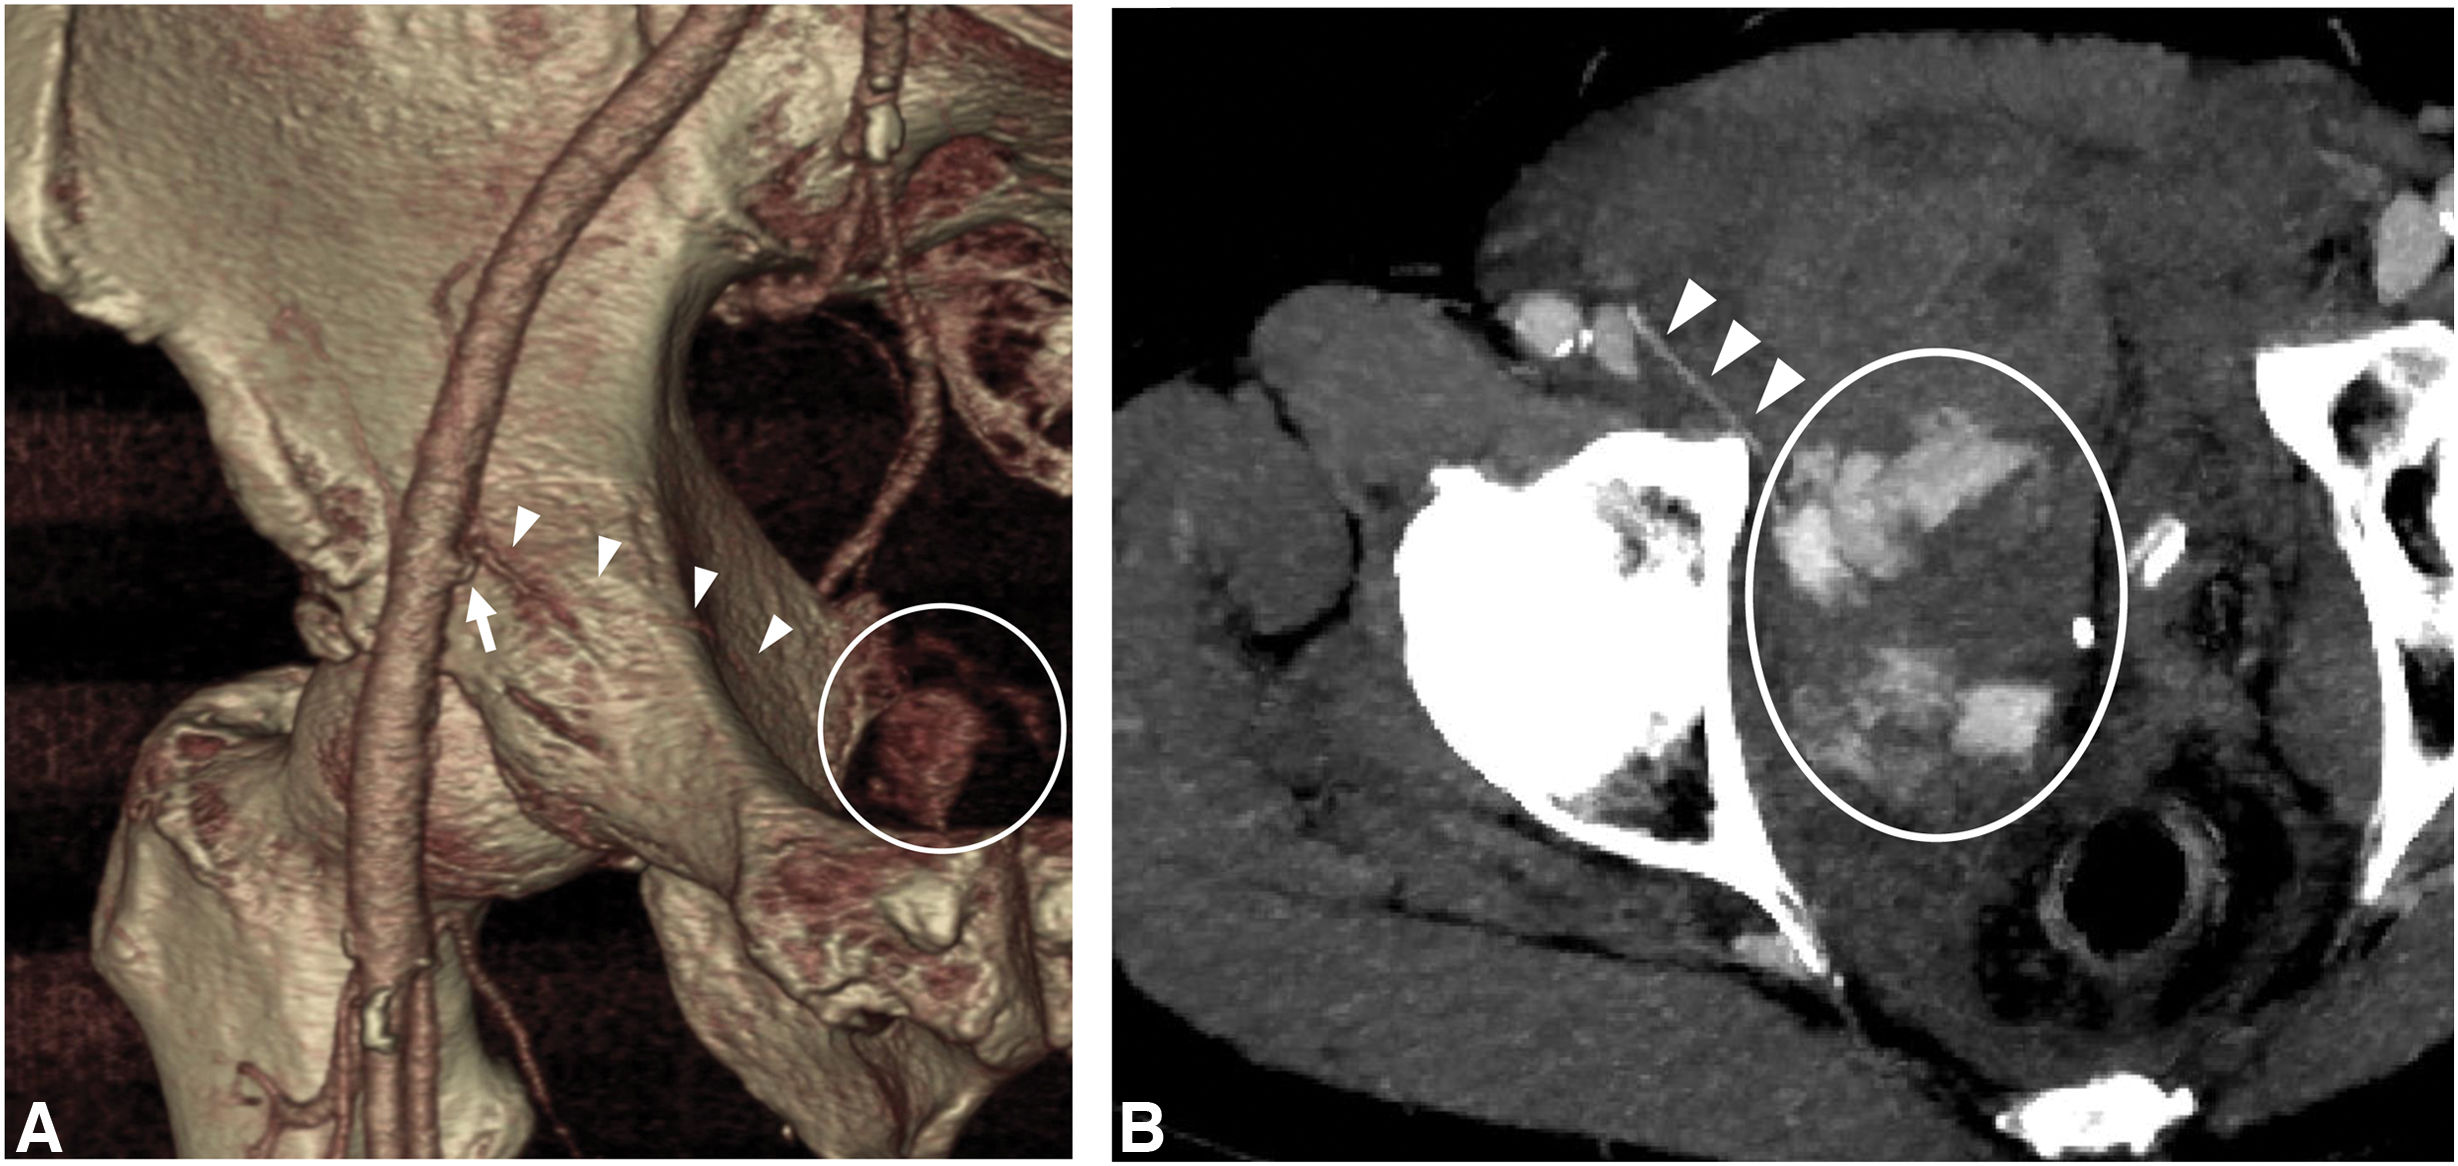
The spatial resolution of the current multidetector6,26 CT equipment allows for the detection of arterial corona mortis in most cases. To optimize its sensitivity, the CT angiography protocol used should include thin slices (collimation less than 1 mm) and, ideally, an arterial phase. Several clinical situations, such as vasospasm (Fig. 8) can reduce its sensitivity. Other sources of error in image interpretation must be considered too, including the presence of bone fragments in cases of fracture. Dual-energy CT technology, or the acquisition of non-contrast or late phases, can help distinguish bone fragments from true vascular lesions.

Vasospasm of the arterial corona mortis due to severe hemorrhage following pelvic trauma in a 69-year-old woman with associated fractures (not shown). (A) Magnified 3D reconstruction of the right hemipelvis. The presence of an arterial corona mortis (arrowheads) is observed, originating from the inferior epigastric artery (arrow) and heading towards the focus of contrast extravasation (circle). The artery is severely reduced in caliber due to vasospasm. (B) MIP reconstruction of an arterial-phase CTA showing a severely narrowed arterial corona mortis, with a prominent contrast extravasation in the lesser pelvis (circle).
This variant is identified by locating an arterial vessel, typically originating from the EIA or IEA, that crosses the superior pubic ramus and curves medially toward the anterior acetabulum (Fig. 9).

Identification of the arterial corona mortis on arterial-phase CTA. A 66-year-old male undergoing CTA for evaluation of peripheral arterial disease. The obturator artery originates from the left inferior epigastric artery (arterial corona mortis) and follows a medial trajectory, arching anterior to the acetabulum (arrows).
Identifying the arterial corona mortis before surgery in the retropubic or acetabular region can be very useful. Its relatively small size and deep location in the pelvis can make intraoperative detection and control challenging, especially when vasospasm occurs. Given the low frequency of injury in these procedures, preoperative identification is not standard practice. However, it is crucial to suspect and rule out the presence of an arterial corona mortis in cases of significant or delayed bleeding after surgery in this anatomical region.
On the other hand, in the context of pelvic trauma with vascular injury, it is essential to actively search for the presence of this variant, especially if there are fractures of the acetabulum or iliopubic branch.
IT SHOULD BE REMEMBERED THAT: Arterial corona mortis should be actively sought in cases of significant hemorrhage after surgery in the retropubic or acetabular region and after pelvic trauma with associated vascular injury, especially in the context of acetabular or iliopubic branch fractures. Sometimes, hemorrhage may have a delayed onset.
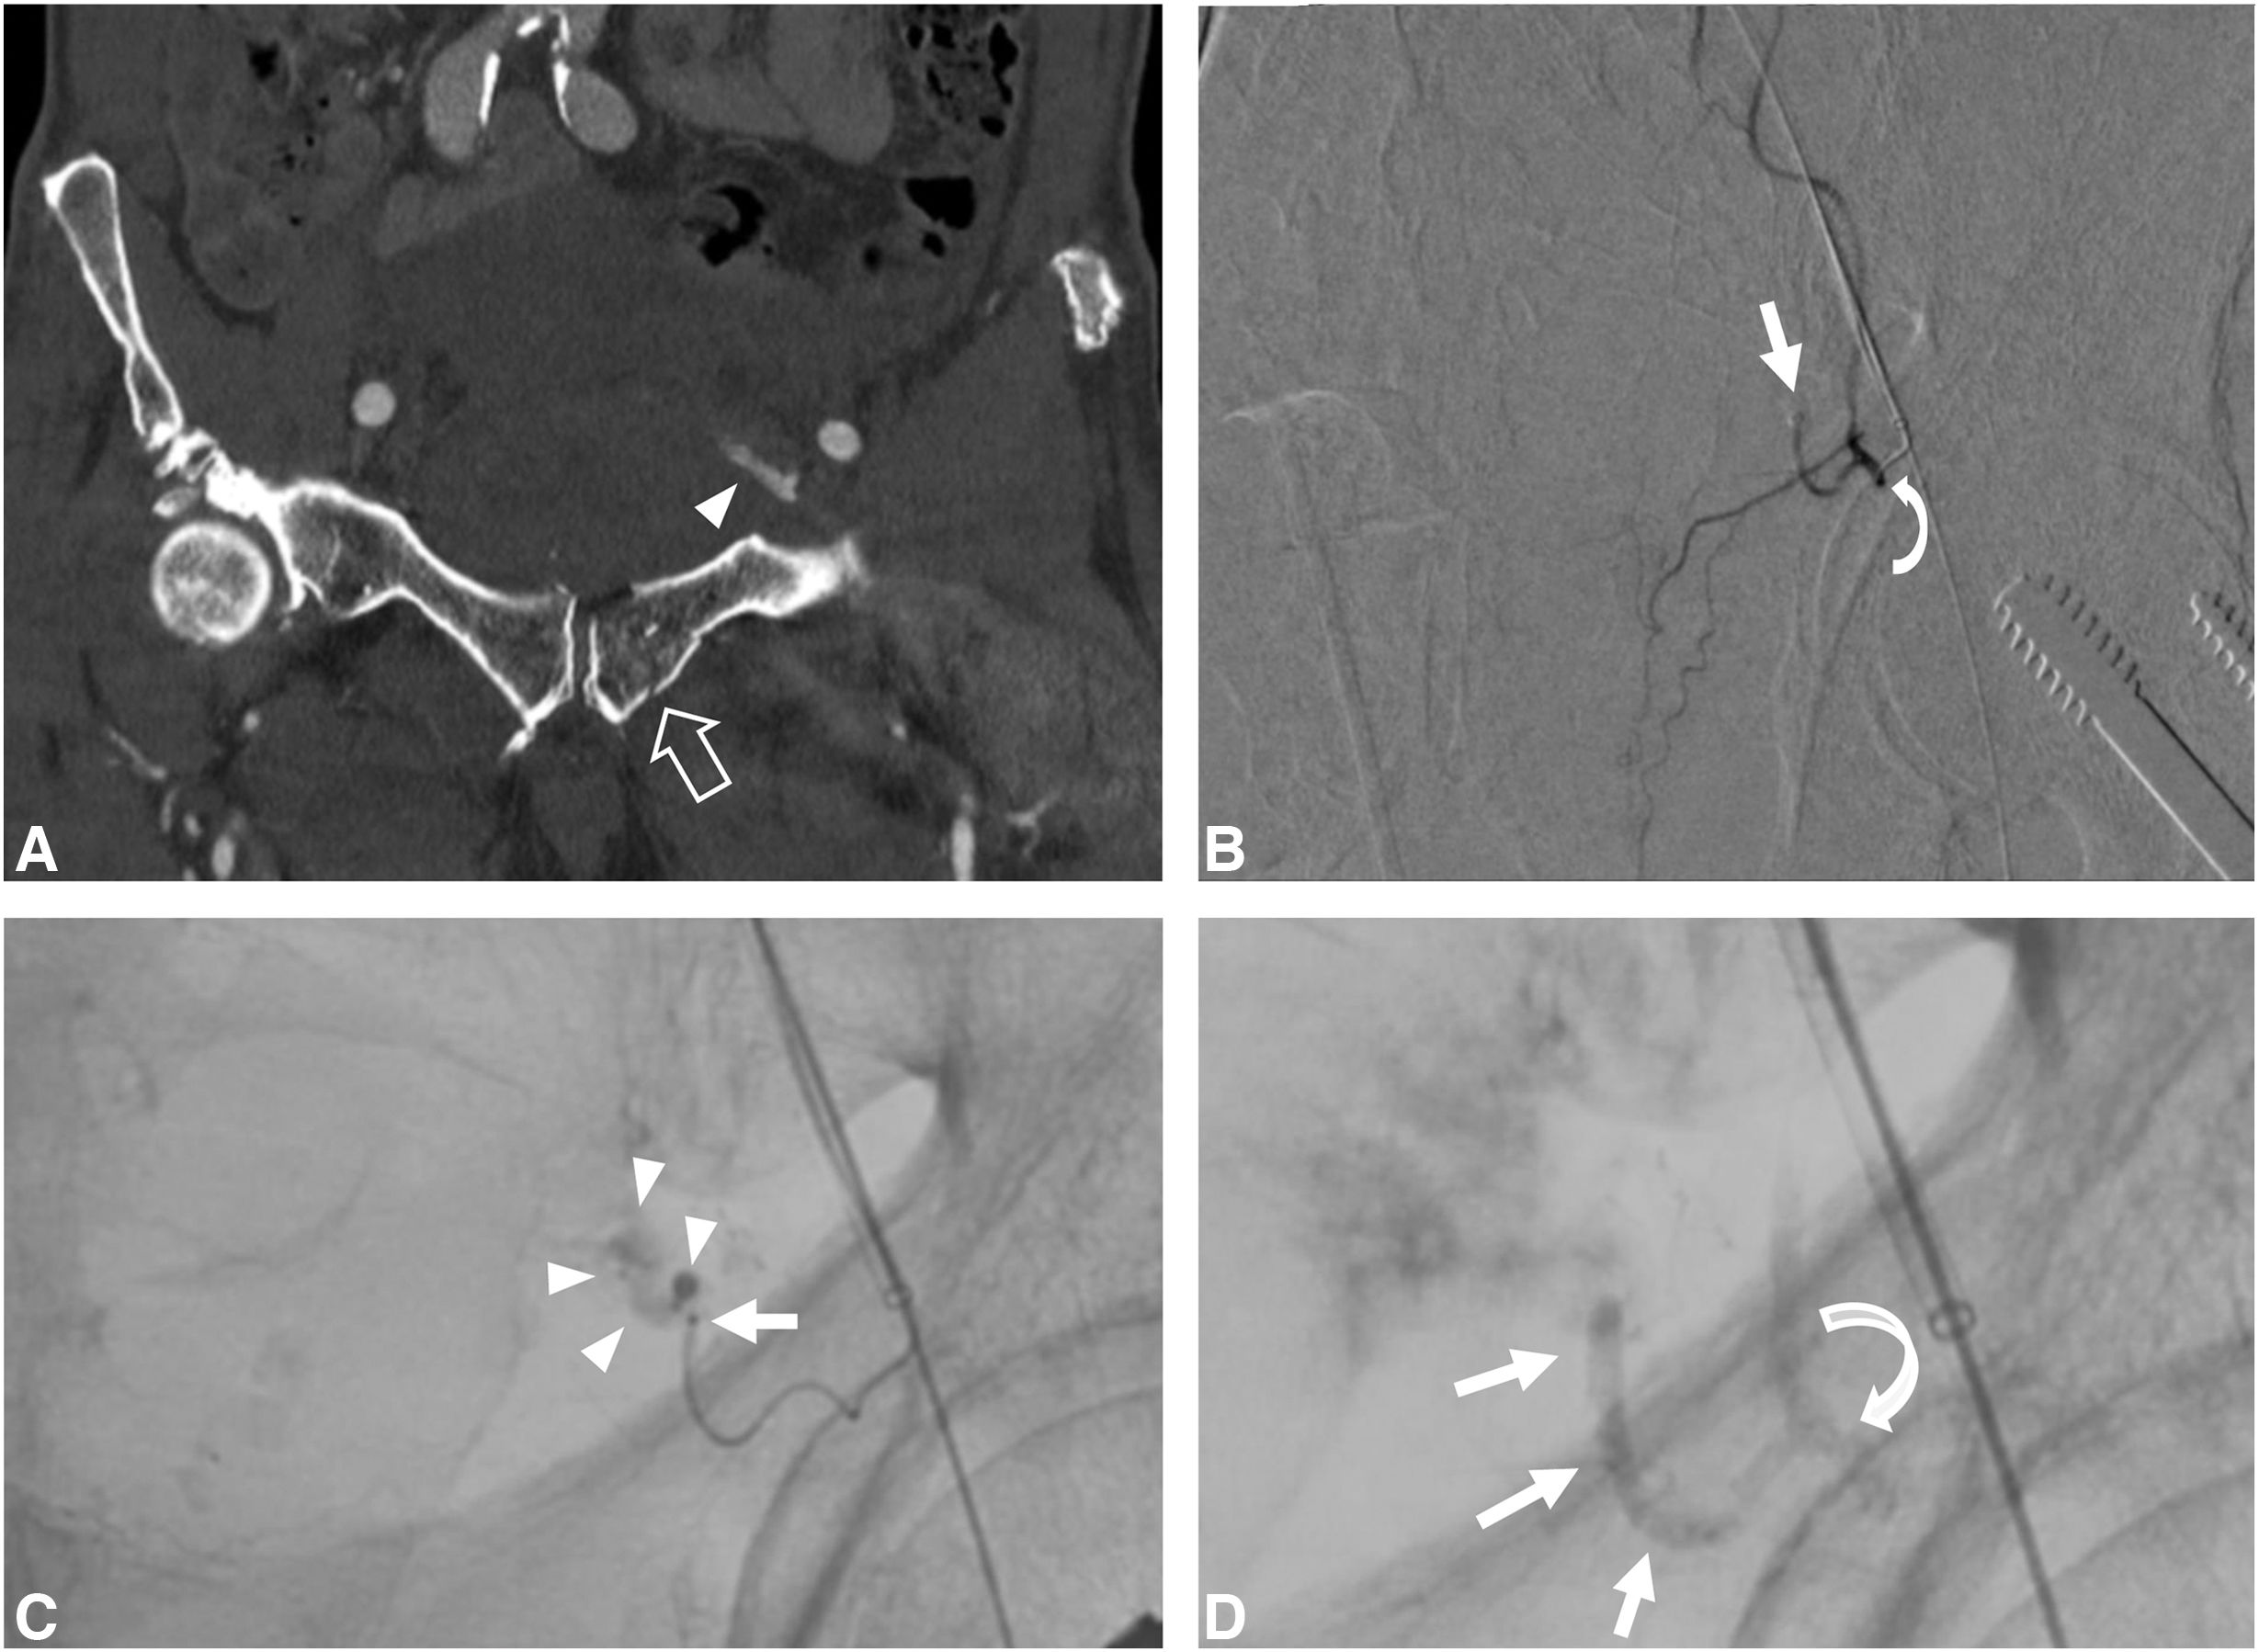
Arterial embolization is considered the treatment of choice for pelvic trauma with active arterial bleeding.27 Some authors report that the mortality rate is reduced fivefold when patients with pelvic fractures and active arterial bleeding undergo embolization within the first three hours, compared to patients who undergo the procedure beyond this time frame.28 Accurate radiological localization of the bleeding source before embolization is crucial for timely and effective management in this life-threatening context. Therefore, identification of the arterial corona mortis as the origin of hemorrhage is critical, guiding the selective catheterization of the EIA/IEA. This avoids an initial catheterization of the anterior trunk of the IIA, the more common origin in AO injuries (Fig. 10), an approach that would prove ineffective for achieving hemostasis when the corona mortis is the source of bleeding.

Polytrauma in an 80-year-old male (motor vehicle collision). The patient presented hemodynamically stable. He received two units of packed red blood cells due to hemorrhage. (A) Left superior pubic ramus fracture (hollow arrow) associated with contrast extravasation (arrowhead) from an amputated arterial corona mortis. (B) Selective DSA series confirms the amputation of the arterial corona mortis (arrow) at its origin from the inferior epigastric artery (IEA) (curved arrow). (C) Supraselective arteriography from the arterial corona mortis, showing its amputation and contrast extravasation, in keeping with a focus of active bleeding. (D) Control fluoroscopy image after embolization of the arterial corona mortis and the origin of the IEA, showing the n-butyl-2-cyanoacrylate cast with which hemostasis was achieved.
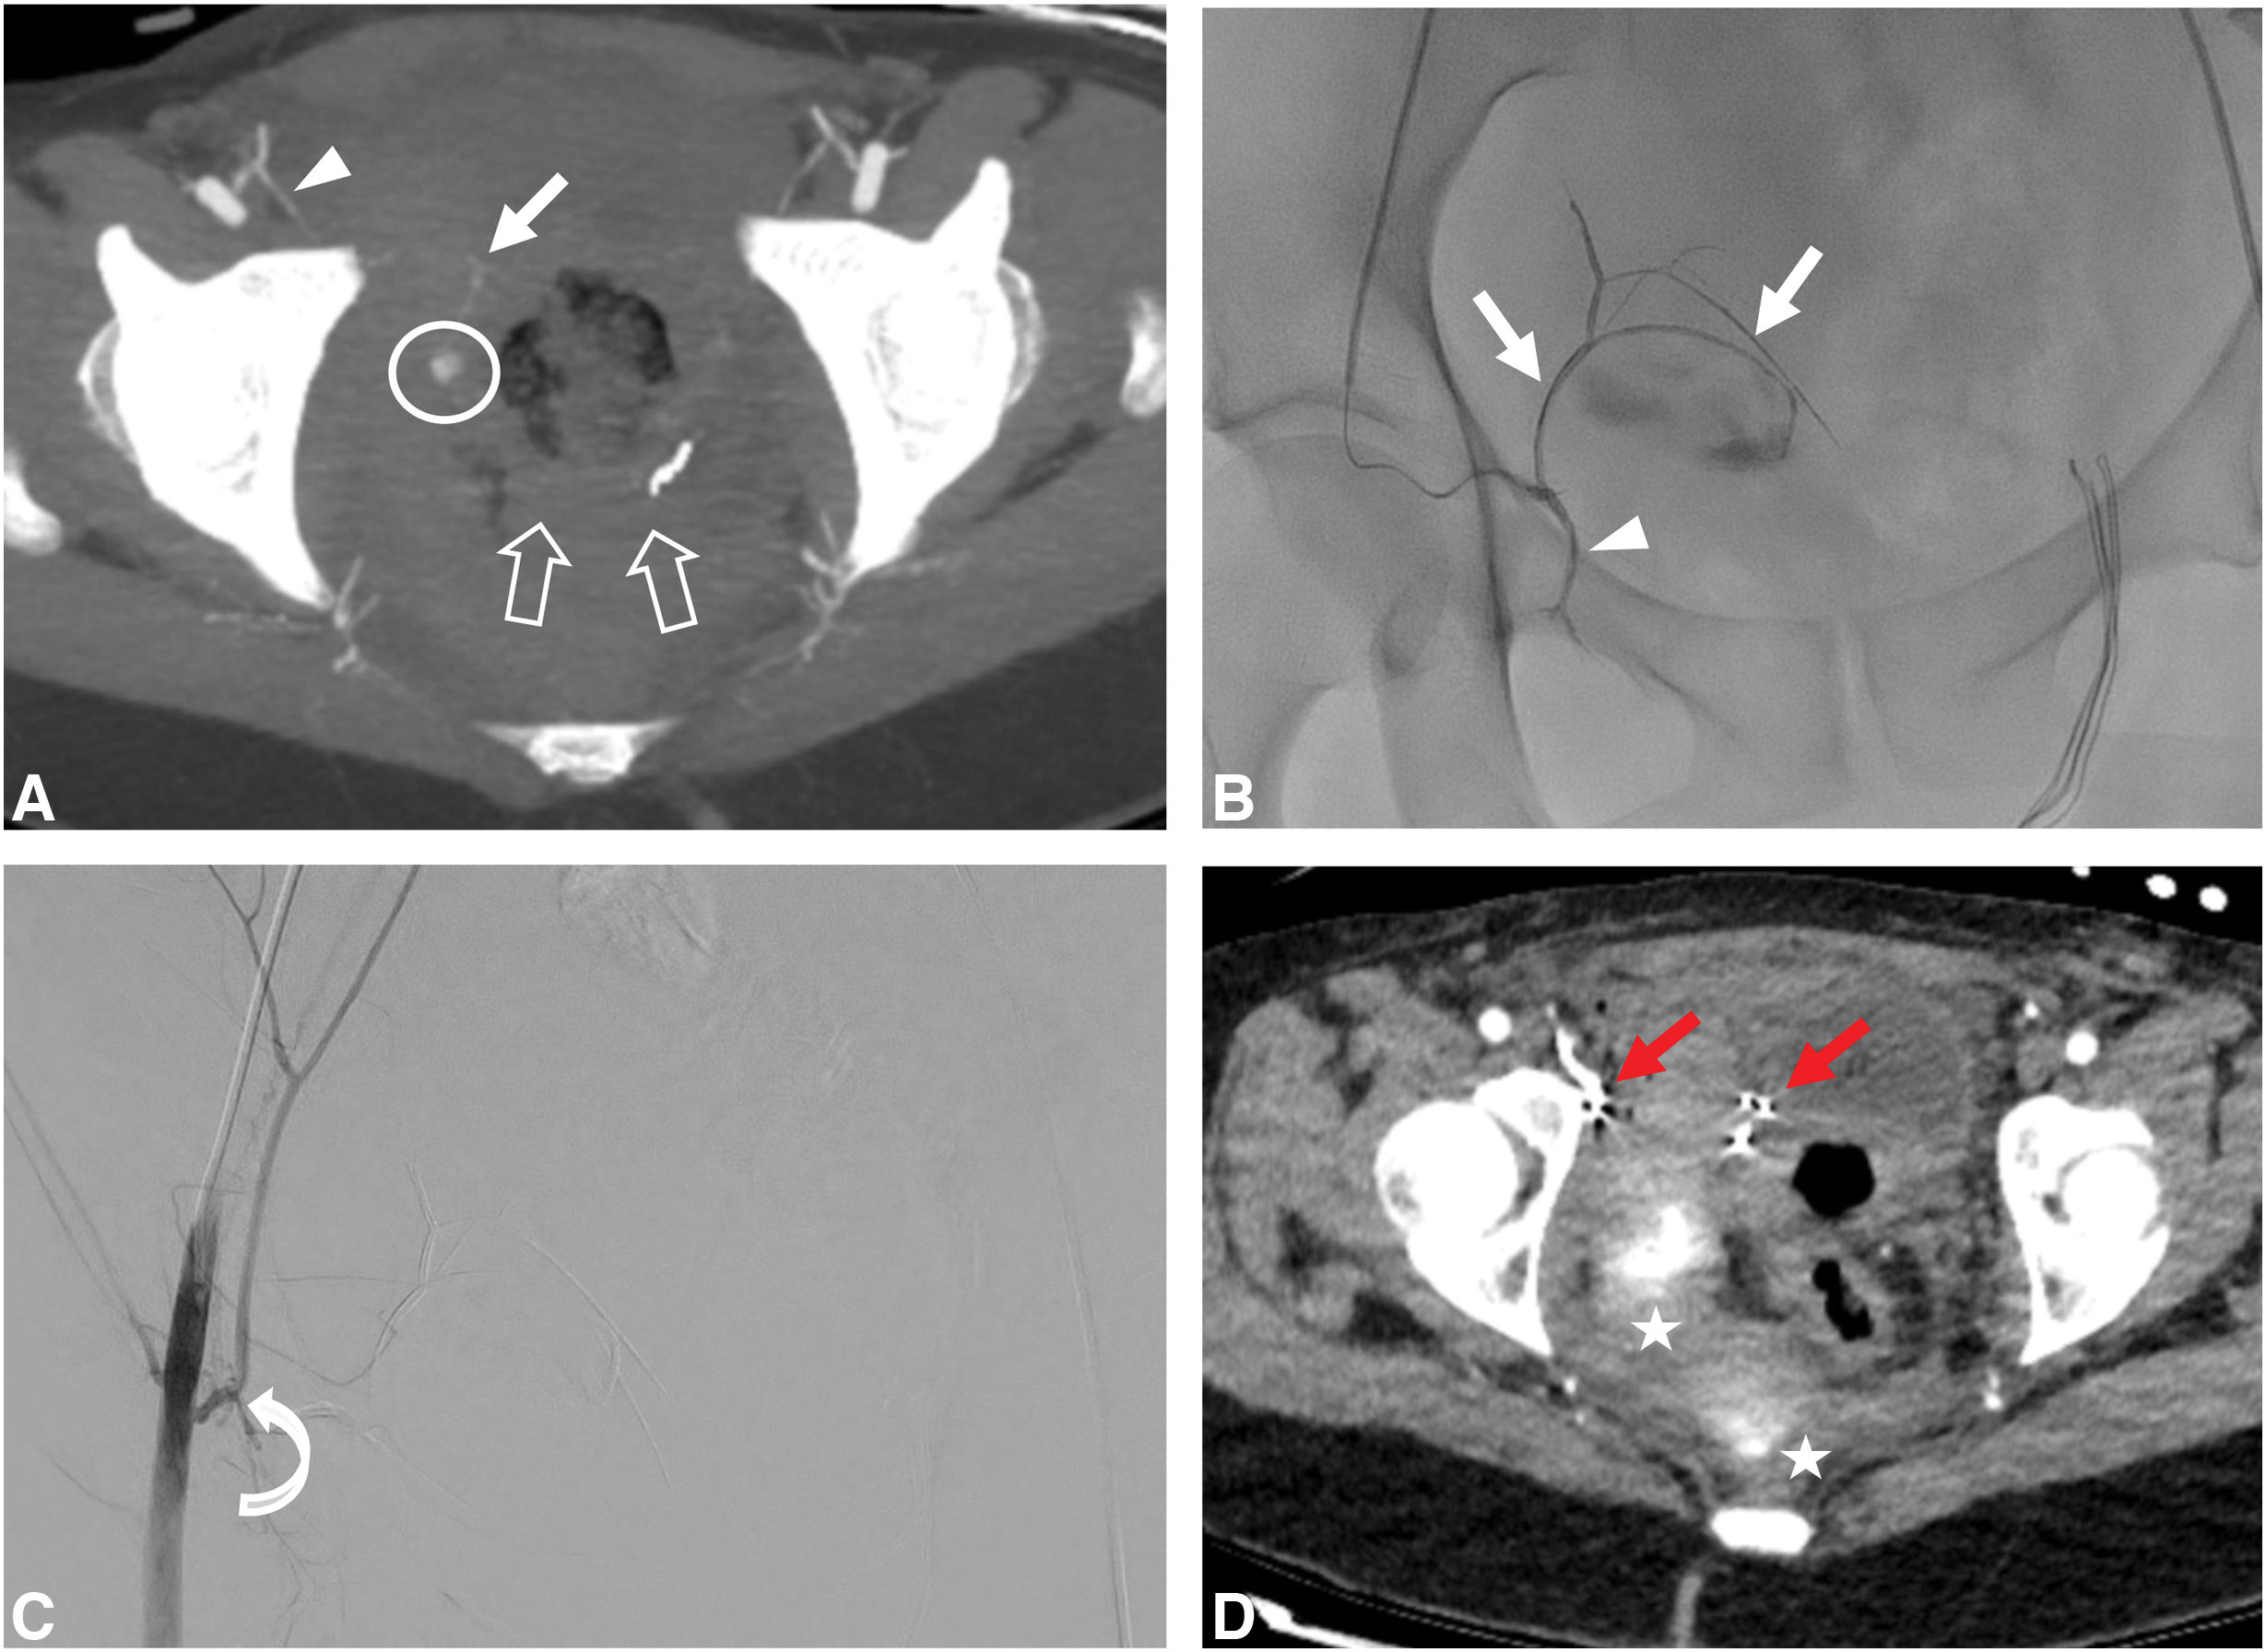
Beyond pelvic trauma, evaluation for an arterial corona mortis may be beneficial in other causes of acute hemorrhage, including select cases of postpartum hemorrhage. When no sources of extravasation from the uterine artery or other branches of the IAA are found, the origin may be found in the arterial corona mortis (Fig. 11). In fact, any pelvic bleeding from an injured arterial corona mortis warrants a prompt and appropriate diagnosis, which guides preferential embolization of the external iliac system to ensure hemostasis is achieved as quickly as possible.

Massive postpartum hemorrhage in a 37-year-old woman following a genital tract laceration during the expulsive stage of labor (eutocic delivery). (A) Arterial-phase axial CTA shows a focus of right paravaginal contrast extravasation (circle) originating from a branch (arrow) of the right arterial corona mortis (arrowhead). Vaginal packing (hollow arrows) fails to contain the hemorrhage. (B) Selective catheterization of the inferior epigastric artery (IEA). Control fluoroscopy image showing the embolic cast using an Ethylene-Vinyl Alcohol copolymer in the bleeding branch, which arises from the arterial corona mortis. The origin of the arterial corona mortis is also embolized. (C) Final control DSA series. Absence of extravasation is evident; the IEA is preserved (curved arrow). (D) Arterial-phase axial CTA showing the hyperdense embolic material (red arrows) and residual post-arteriography contrast media pooled within the right paravaginal hematoma (stars).
IT SHOULD BE REMEMBERED THAT in cases of pelvic hemorrhage, the absence of active bleeding from the IIA should raise suspicion of an injury to the arterial corona mortis. Promptly identifying this vascular variant allows for preferential catheterization of the external iliac system, leading to rapid and effective hemostasis.
In addition, some vascular lesions have a dual arterial supply from both the external (via EIA) and internal (via IIA) iliac systems. In such cases, embolization of both territories is essential for achieving effective hemostasis and, in the case of pseudoaneurysms, for preventing recanalization.15 During embolization planning, the anastomotic connection via the arterial corona mortis must be considered to prevent inadvertent embolization of the EIA territory and consequent acute ischemia of the lower limb.
The clinical relevance of the arterial corona mortis extends to other interventional radiology procedures, such as the embolization of rectus sheath hematomas (Fig. 12). This procedure is common in emergent settings, particularly in anticoagulated patients. In this context, anatomical awareness of the corona mortis is crucial to ensure its preservation when it is not the source of extravasation, thereby avoiding non-target embolization (Fig. 13)


Spontaneous rectus sheath hematoma in a 77-year-old male on anticoagulation therapy. (A) Post-embolization DSA of the inferior epigastric artery (IEA) (arrows) shows that the corona mortis has been preserved (arrowheads). (B) Arterial-phase CTA of the same patient. The IEA is occluded with hyperdense embolic material, but the corona mortis is preserved (arrowhead). Rectus sheath hematoma (star).
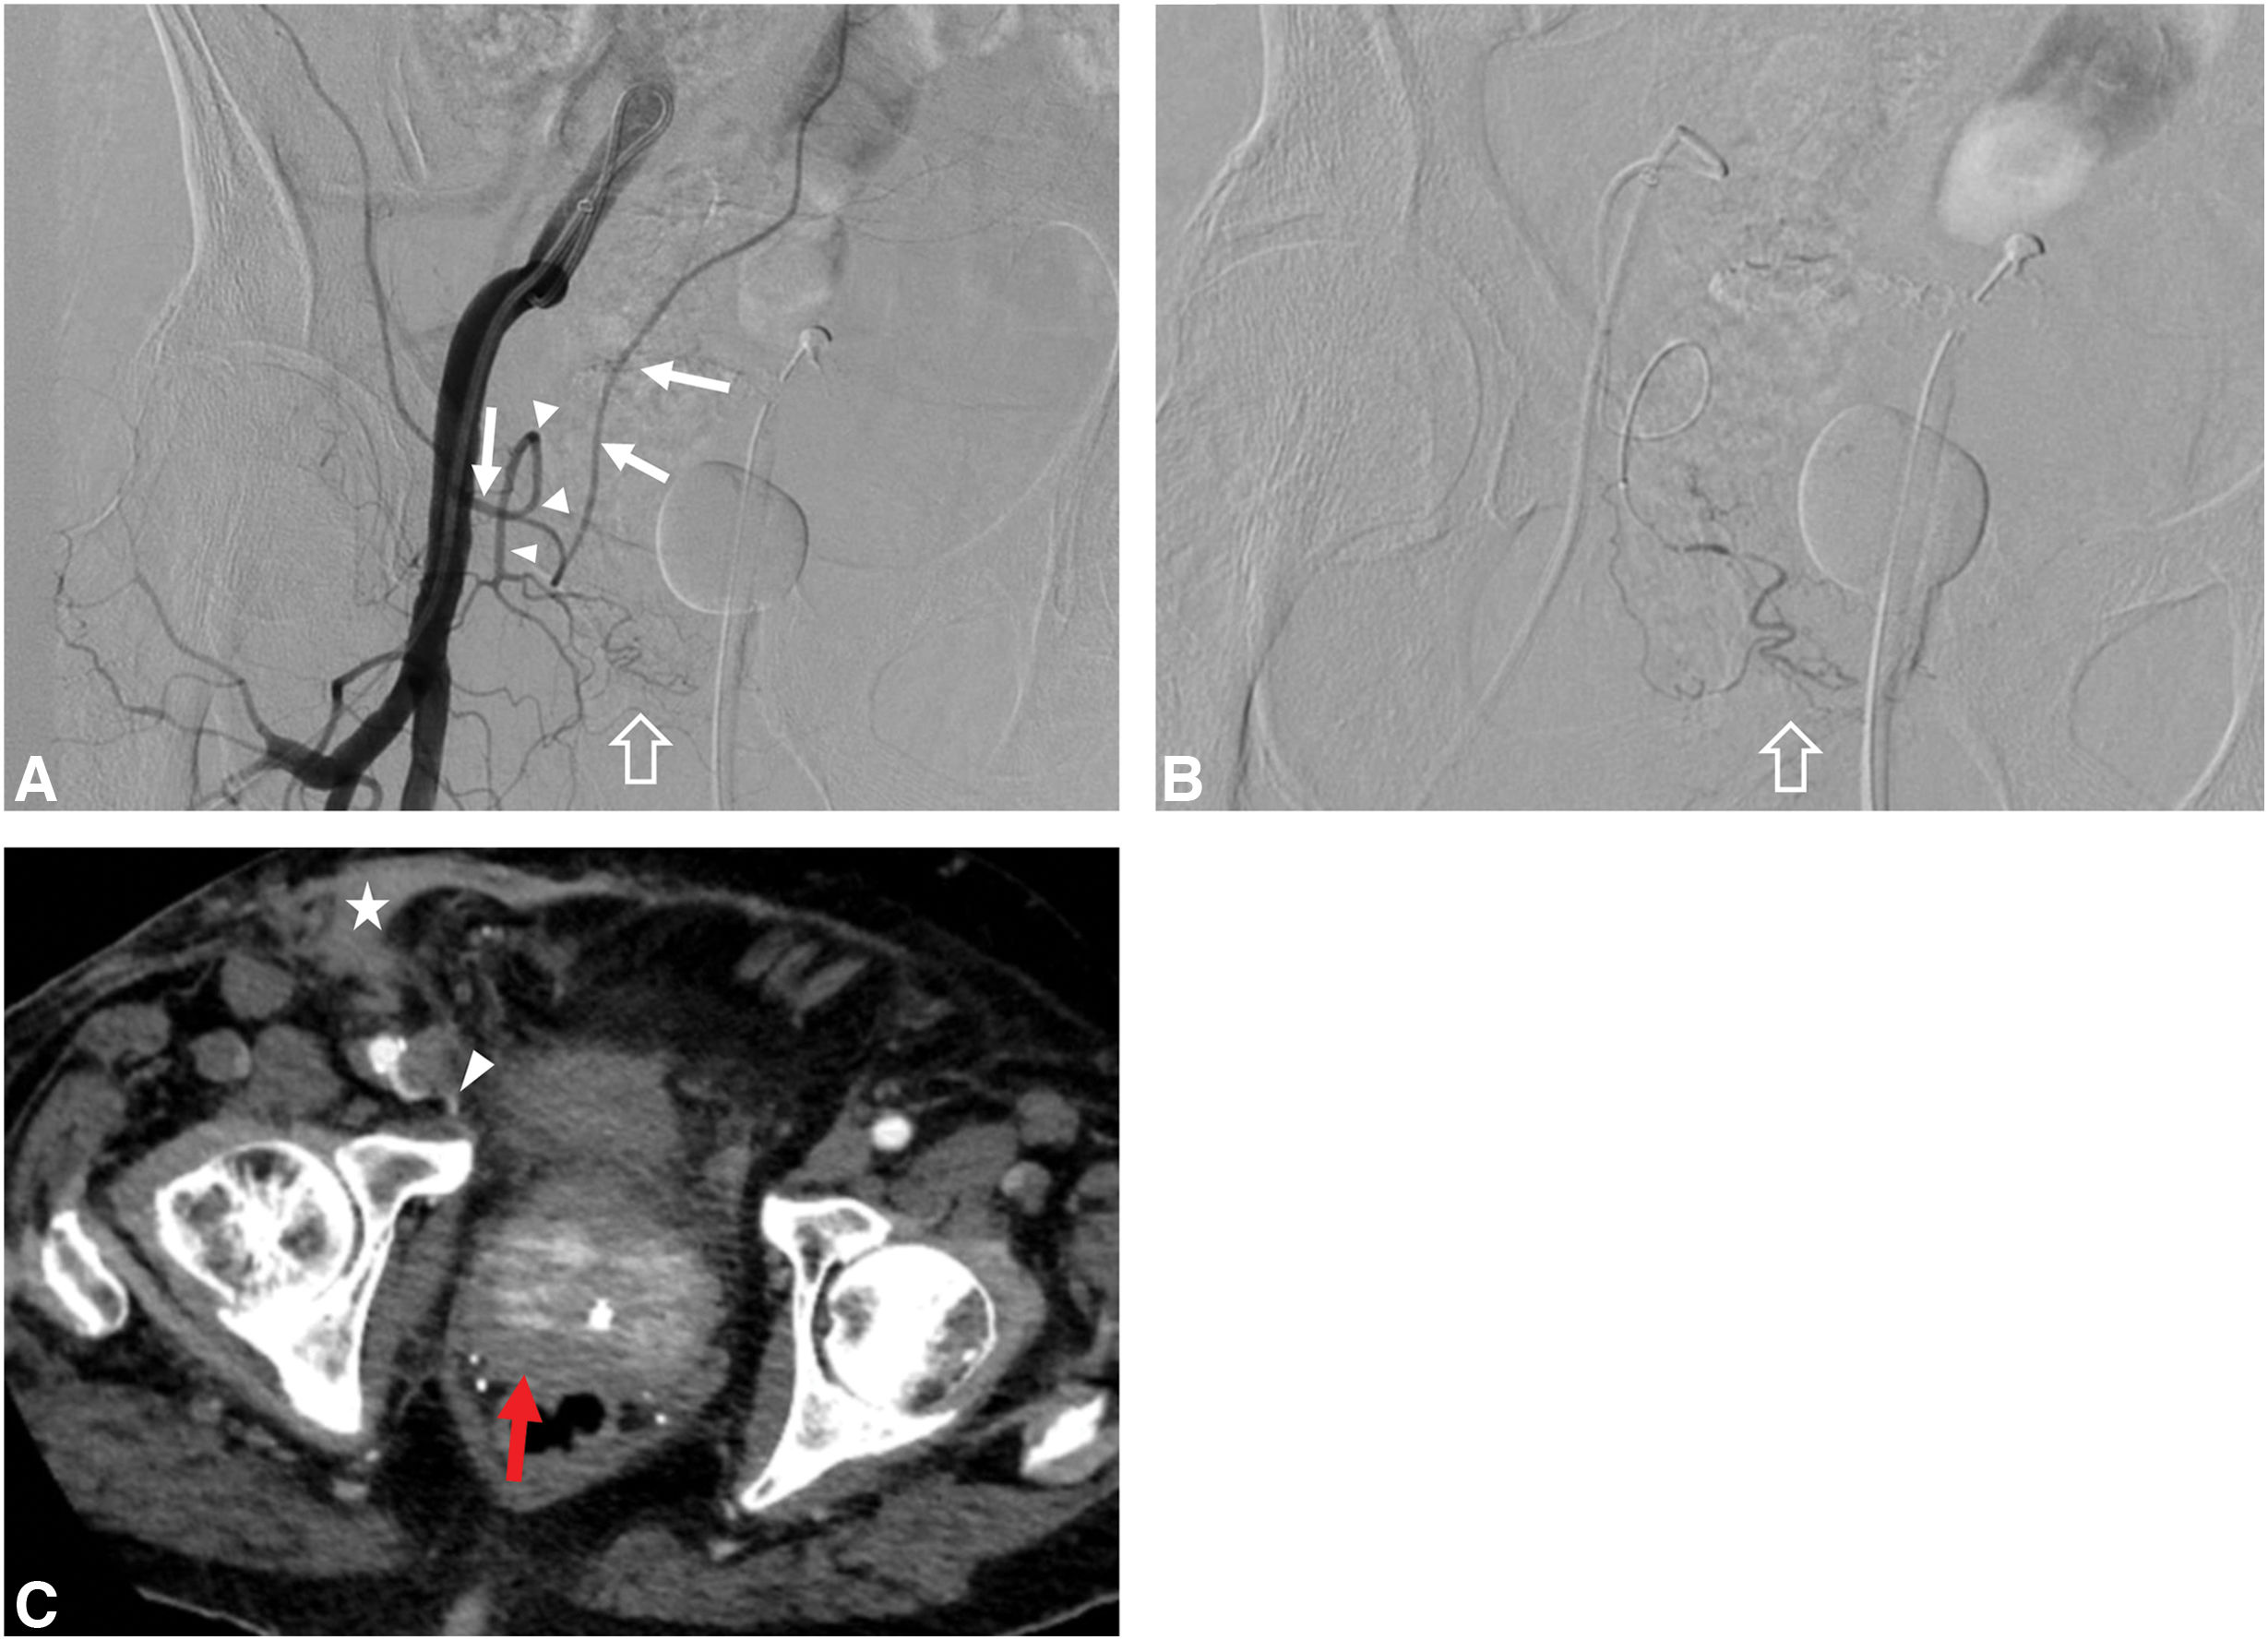
Minimally invasive treatment of benign prostatic hyperplasia (BPH) by arterial embolization is becoming increasingly widespread and has recently been included as a therapeutic alternative in the guidelines of the American Urological Association.29 In approximately 2% of patients, the prostatic artery originates from the IEA through an arterial corona mortis.30 This information is particularly relevant in cases of BPH embolization where it is not possible to identify prostatic branches originating from their usual anatomical origin in the anterior trunk of the IIA, as it will be necessary to search for them from the IEA (Fig. 14).

A 90-year-old male with hematuria secondary to benign prostatic hyperplasia (not a surgical candidate). Aberrant origin of the right prostatic artery from the arterial corona mortis. (A) Arteriography of the right external iliac artery shows a redundant arterial corona mortis (arrowheads) originating from the inferior epigastric artery (IEA) (arrows). A prostatic branch (hollow arrow) is seen arising from the corona mortis and supplying the right prostatic lobe. (B) Supraselective DSA from the right prostatic branch, originating from the corona mortis. Embolization with 300 µm particles is performed from this position. (C) Post-embolization arterial-phase CTA, performed for a suspected complication at the right femoral vascular access site. The presence of hyperdense embolic material (a mixture of particles with iodinated contrast media) in the right prostatic lobe (red arrow) is confirmed; the arterial corona mortis originates from the IEA; post-puncture hematoma of the right common femoral artery (star).
Other less frequent, yet clinically relevant, situations in vascular radiology include iatrogenic injury to the arterial corona mortis with a guidewire, and type II endoleaks that originate from this vessel in patients with IIA aneurysms treated with endoprostheses.12
ConclusionDue to its prevalence and importance, the arterial corona mortis can be considered the “queen” of vascular variants of the pelvis. Injury to this artery can lead to substantial hemorrhage after trauma or surgery, sometimes with a delayed onset. Prompt diagnosis is essential for early treatment. Therefore, it is crucial for radiologists to be familiar with its anatomy and to include this finding in their reports in situations where it may be clinically decisive.
Authorship- 1.
Responsible for study integrity: Rodrigo Alonso González.
- 2.
Study conception: Rodrigo Alonso González.
- 3.
Study design: Rodrigo Alonso González.
- 4.
Data acquisition: Rodrigo Alonso González.
- 5.
Data analysis and interpretation: Rodrigo Alonso González.
- 6.
Statistical processing: Rodrigo Alonso González.
- 7.
Literature search: Rodrigo Alonso González.
- 8.
Drafting of the manuscript: Rodrigo Alonso González and María Parra Calleja.
- 9.
Critical review of the manuscript with intellectually significant contributions: Rodrigo Alonso González, María Antonia Udaondo Cascante, José Miguel del Monte Díez, Javier Velasco Gómez, Marta Gallego Verdejo, and Israel Sánchez Lite.
- 10.
Approval of the final version: Rodrigo Alonso González, María Antonia Udaondo Cascante, José Miguel del Monte Díez, Javier Velasco Gómez, Marta Gallego Verdejo, and Israel Sánchez Lite.
There are no conflicts of interest on the part of any of the authors in the preparation of the update article.



