



Pulmonary hamartoma is the most common benign lung tumour and is usually detected as a peripheral pulmonary lesion. Endobronchial ultrasound-guided transbronchial needle aspiration (EBUS-TBNA) has emerged as a minimally invasive technique for mediastinal staging and diagnosis of thoracic lesions. We report the case of a 72-year-old man with an incidental right hilar lesion identified on computed tomography during follow-up after coronary surgery. Imaging revealed a partially calcified lesion with fatty density adjacent to the right main bronchus. Bronchoscopic examination showed no endobronchial abnormalities, while EBUS demonstrated a well-defined heterogeneous lesion with hyperechoic punctate areas and posterior acoustic shadowing. EBUS-TBNA was performed without complications. Cytological and cell block analysis demonstrated the diagnosis of pulmonary hamartoma. This case highlights the utility of EBUS-TBNA as a safe and effective diagnostic tool for centrally located pulmonary hamartomas.
El hamartoma pulmonar es el tumor pulmonar benigno más frecuente y suele detectarse como una lesión pulmonar periférica. La ecografía endobronquial con aspiración con aguja transbronquial (EBUS-TBNA) se ha consolidado como una técnica mínimamente invasiva para la estadificación mediastínica y el diagnóstico de lesiones torácicas. Presentamos el caso de un varón de 72 años con una lesión hiliar derecha incidental identificada en una tomografía computarizada durante el seguimiento tras una cirugía coronaria. Las pruebas de imagen revelaron una lesión parcialmente calcificada con densidad grasa adyacente al bronquio principal derecho. El examen broncoscópico no mostró anomalías endobronquiales, mientras que el EBUS mostró una lesión heterogénea bien definida con áreas puntiformes hipercogénicas y sombra acústica posterior. Se realizó un EBUS-TBNA sin complicaciones. El análisis citológico y del bloque celular confirmó el diagnóstico de hamartoma pulmonar. Este caso pone de manifiesto la utilidad del EBUS-TBNA como herramienta diagnóstica segura y eficaz para los hamartomas pulmonares de localización central.
Pulmonary hamartoma is the most common benign lung tumour and is usually located in the peripheral pulmonary parenchyma.1 Hilar, mediastinal, or endobronchial locations are uncommon and may require tissue sampling to exclude malignancy.1,2 Endobronchial ultrasound-guided transbronchial needle aspiration (EBUS-TBNA) is a minimally invasive technique widely used for mediastinal staging and diagnosis of thoracic lesions.2,3 However, its role in the diagnosis of benign tumours such as pulmonary hamartoma has been infrequently reported.4
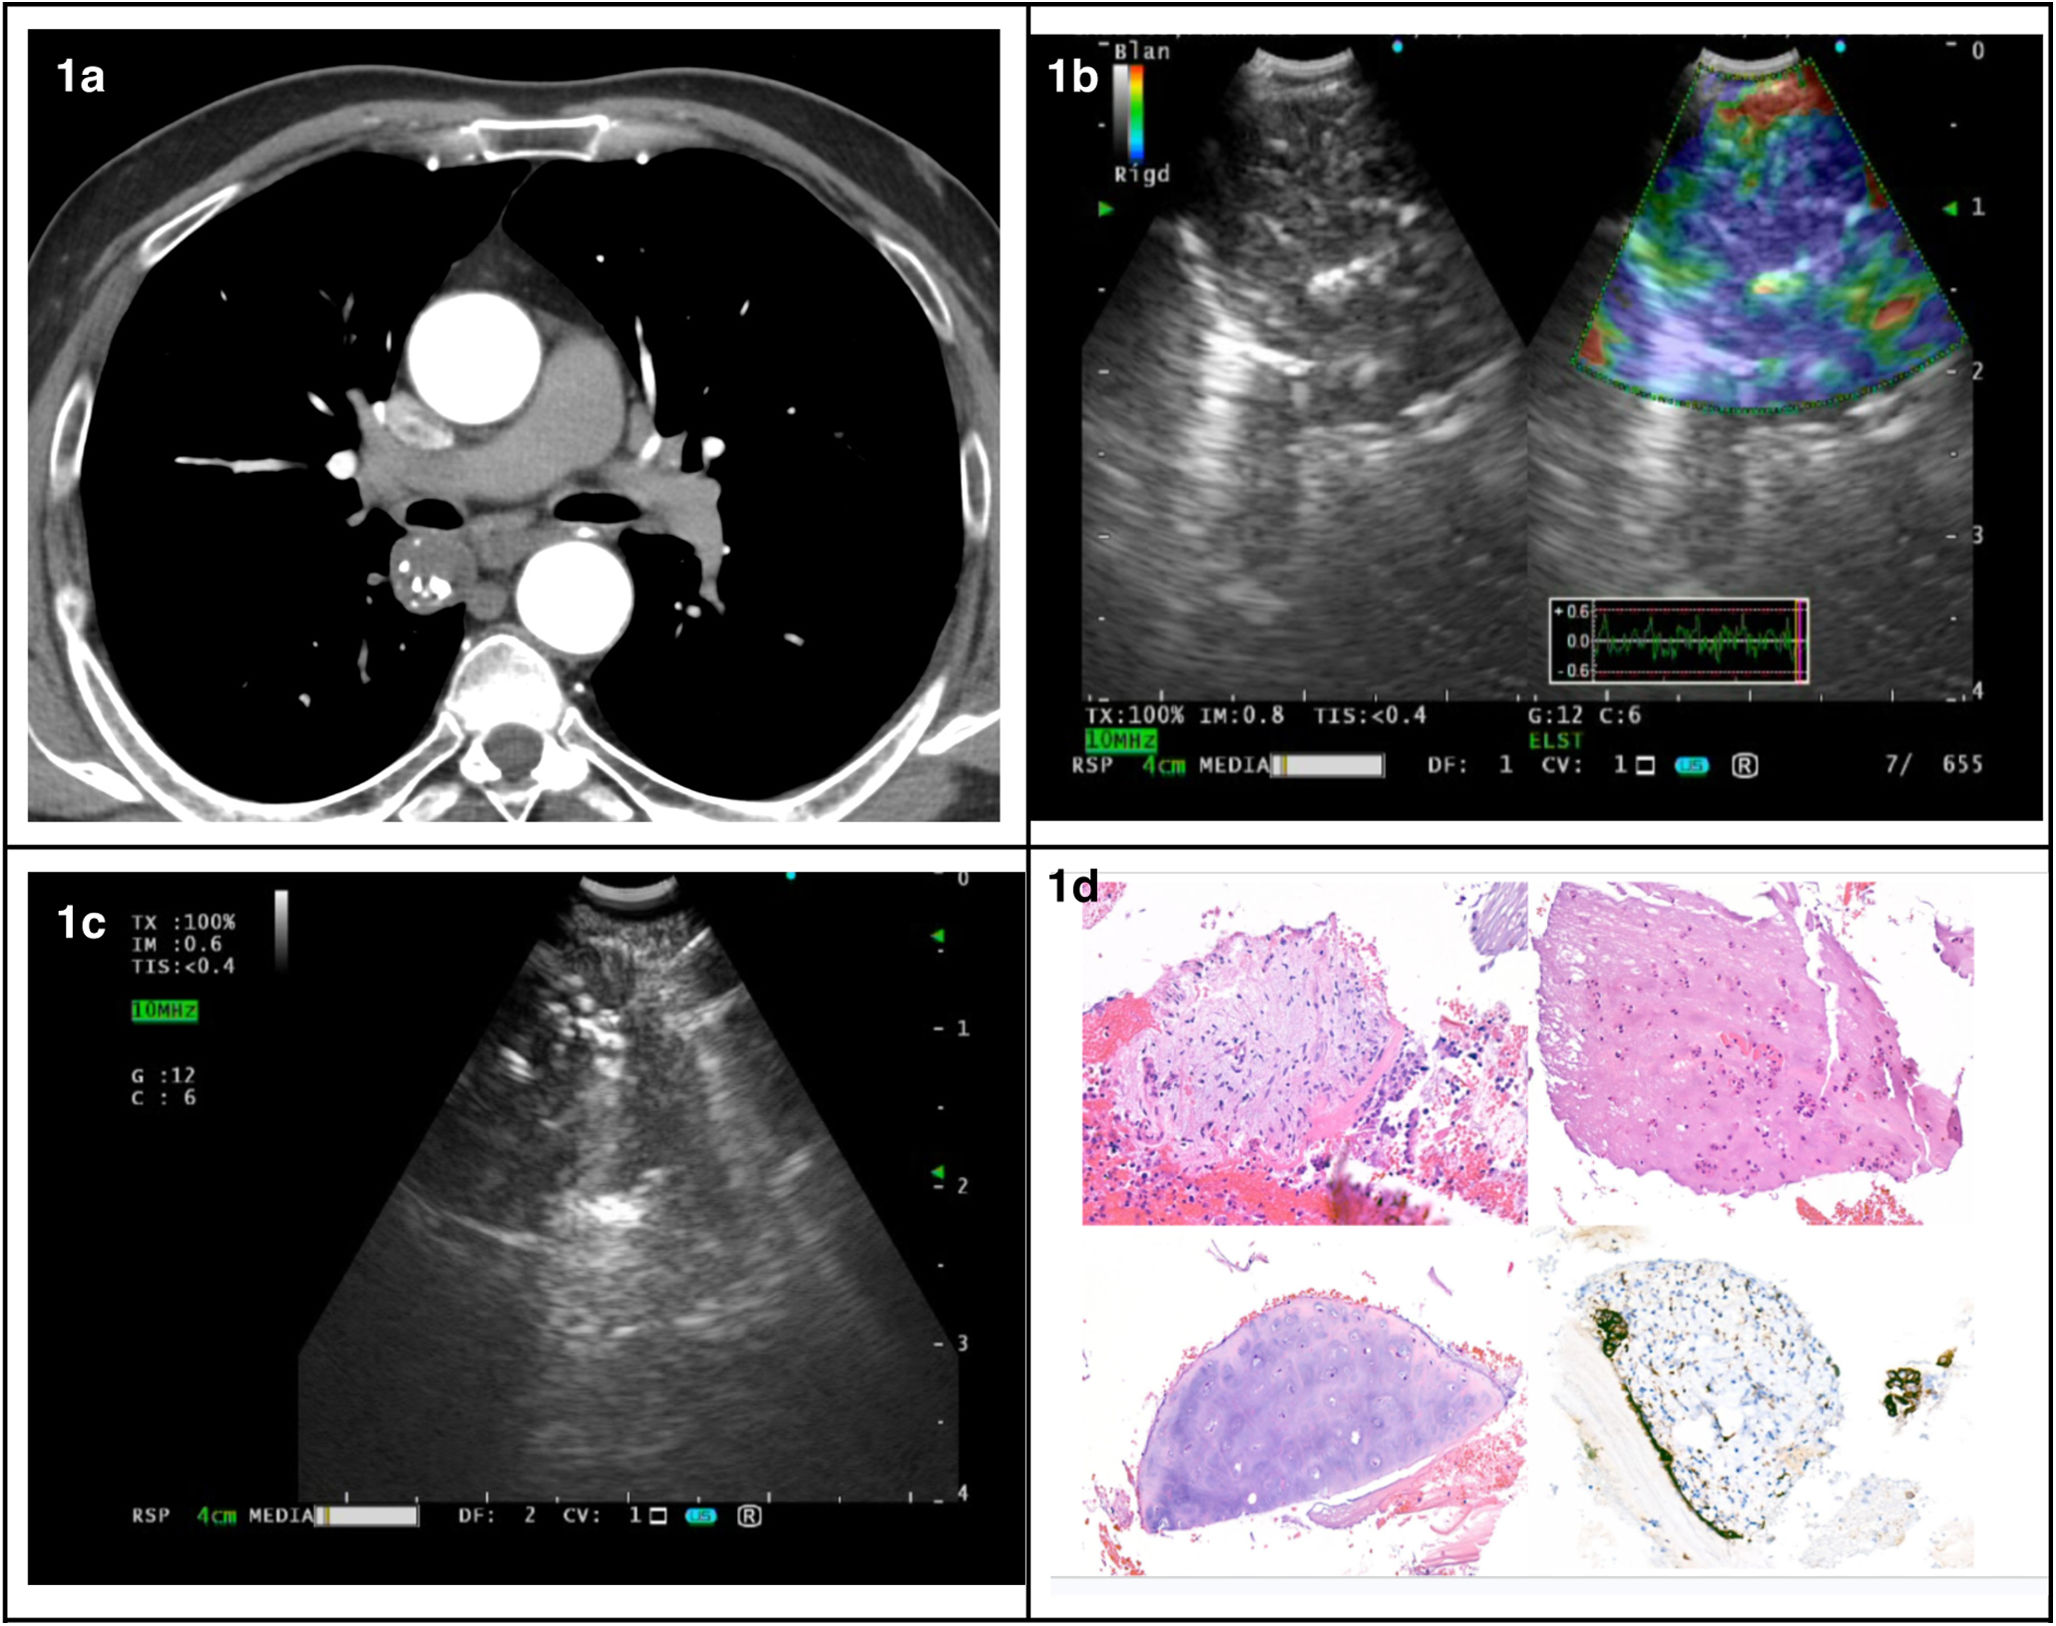
A 72-year-old patient was referred to our Pulmonology Department after a follow-up coronary computed tomography (CT) scan revealed a well-circumscribed, partially calcified right lower paramediastinal lesion measuring 25mm, containing areas of fat attenuation and located adjacent to the right main bronchus. The patient was a current smoker with a 26-pack-year smoking history and had a medical history of chronic ischaemic heart disease requiring stent placement in the left anterior descending artery in 2013, hiatal hernia, and gastric telangiectasias. The lesion caused mild extrinsic compression of the intermediate bronchus without significant stenosis (Fig. 1A).

(a) Axial CT image in the arterial phase demonstrating a nodular lesion located posterior to the right main bronchus. It contains areas of calcific density and shows minimal contrast enhancement, with hypodense areas suggestive of fatty density. (b) Endobronchial ultrasound image of the lesion, measuring over 2cm, showing internal hyperechoic punctate foci with posterior acoustic shadowing and an elastographic Score 4 pattern. (c) Fine-needle aspiration of the lesion performed by EBUS-TBNA. (d) Cell block images demonstrating fragments of finely vascularised fibromyxoid stroma lined by epithelial cells without atypia, together with fragments of mature cartilage. Immunohistochemical analysis with Napsin A confirms the pneumocytic lineage of the epithelial cells.
EBUS-TBNA was performed under conscious sedation using topical lidocaine, midazolam, and fentanyl. Bronchoscopic examination showed no endobronchial lesions or mucosal abnormalities. EBUS demonstrated a lesion larger than 2cm containing multiple hyperechoic foci with posterior acoustic shadowing, suggestive of calcified or cartilaginous tissue (Fig. 1B). Elastography demonstrated a predominantly blue heterogeneous pattern with scattered green areas, corresponding to a score 4 pattern, suggestive of increased tissue stiffness (Fig. 1C).
Three passes were performed using a 21-gauge needle. Rapid on-site cytological evaluation (ROSE) suggested cartilaginous tissue. Definitive cytological analysis demonstrated fragments of mature cartilage and finely vascularised fibromyxoid stroma lined by respiratory epithelial cells positive for napsin A, TTF-1, and CK7, without atypia. Scattered macrophages were also identified, and the overall findings were consistent with pulmonary hamartoma (Fig. 1D).
Pulmonary hamartomas are benign neoplasms typically identified as peripheral solitary pulmonary nodules. Central or hilar presentations are rare and may mimic malignant lesions, particularly when characteristic CT findings such as fat or “popcorn” calcifications are absent.1 EBUS-TBNA is primarily used for lung cancer staging and diagnosis of mediastinal lymphadenopathy, although its utility in selected benign lesions has increasingly been recognised.2,3 Because most pulmonary hamartomas are peripheral, diagnosis by convex probe EBUS-TBNA has only rarely been described in the literature.4–8 Previous reports have demonstrated that EBUS-TBNA can provide adequate cytological material for diagnosis in centrally located hamartomas.7,9
Characteristic ultrasound findings have also been reported.10 Hyperechoic foci with posterior acoustic shadowing may correlate with cartilaginous or calcified tissue within the lesion.10 Although heterogeneous echogenicity and increased stiffness on elastography are commonly associated with malignant lesions, these findings may also reflect the mixed internal composition of hamartomas, which includes cartilage, fibrous tissue, and entrapped respiratory epithelium.
Although EBUS-TBNA may have a lower diagnostic yield in benign lesions than in malignant disease because cytological samples can be insufficient, newer techniques such as mediastinal cryobiopsy (Cryo-EBUS) and EBUS-guided intranodal forceps biopsy (EBUS-IFB) may improve tissue acquisition in selected cases.11,12 In our patient, however, CT findings strongly suggested a hamartoma, and ROSE confirmed cartilaginous tissue after EBUS-TBNA, making additional sampling with Cryo-EBUS unnecessary.
In conclusion, EBUS-TBNA may represent a useful and minimally invasive diagnostic tool for selected centrally located pulmonary hamartomas. Recognition of characteristic EBUS ultrasound features, particularly hyperechoic foci with posterior acoustic shadowing, may facilitate diagnosis and minimally invasive confirmation of these uncommon lesions.
Ethical considerationsThis work was conducted in accordance with institutional ethical standards and the Declaration of Helsinki.
Artificial intelligence involvementNo artificial intelligence tools were used in the preparation of this manuscript.
Informed consentWritten informed consent was obtained from the patient for publication of this case report and accompanying images.
FundingThe authors received no specific funding for this work.
Authors’ contributionsAll authors contributed substantially to the conception, drafting, revision, and approval of the final manuscript.
Conflicts of interestsThe authors declare no conflicts of interest.


