


The purpose of this study is to determine whether certain personality traits may predict response to anti–calcitonin gene–related peptide (anti-CGRP) monoclonal antibodies (mAb) in patients with migraine.
MethodsWe conducted an observational, prospective study of a cohort of patients with chronic migraine (CM) or high-frequency episodic migraine (HFEM) treated with anti-CGRP mAbs according to Spanish national healthcare system reimbursement criteria at the headache unit of a tertiary hospital. We gathered clinical and demographic data. Treatment response was defined as a ≥ 50% decrease in the number of headache days per month at 3 months of treatment. The Salamanca Screening Test was used to evaluate personality traits.
ResultsWe included 104 patients, 88 of whom were women (84.6%), with a mean age (standard deviation) of 46.5 years (10.3) at treatment onset. A total of 88 patients (84.6%) had a diagnosis of CM. Fifty-two patients received galcanezumab and the remaining 52 were treated with fremanezumab. Response was achieved in 75 patients (72.1%). Compared to non-responders, responders presented a younger age at treatment onset (44.1 [10.6] vs 49.7 [9.1]; P = .006), shorter latency from migraine onset to treatment onset (22.4 [12.2] vs 28.2 [14.4] years; P = .029), and shorter latency from CM or HFEM diagnosis to treatment onset (90.4 [51.9] vs 118.5 [61.2] months; P = .013). The most prevalent personality traits in our sample were histrionic (64.4%), anankastic (52.9%), and anxious (50%). Borderline personality was found to predict lack of response to treatment (OR = 0.24 [0.09−0.64]).
ConclusionsPersonality traits, along with other clinical and demographic variables, may predict response to treatment with anti-CGRP mAbs in patients with migraine.
Determinar si determinados rasgos de personalidad podrían predecir la respuesta a los anticuerpos monoclonales (AcM) frente al péptido relacionado con el gen de la calcitonina (CGRP) en pacientes con migraña.
MétodoEstudio observacional con diseño de cohortes prospectiva. Pacientes con migraña crónica (MC) o episódica de alta frecuencia (MEAF) tratados de acuerdo con los criterios nacionales de reembolso con AcM frente al CGRP en una unidad de cefaleas de un hospital terciario. Se recabaron variables clínicas y demográficas. Se consideró respuesta la reducción de al menos un 50% en el número de días al mes de cefalea a los 3 meses de tratamiento. Se administró el test de Salamanca para evaluar los rasgos de personalidad.
ResultadosSe incluyeron 104 pacientes, 88 (84,6%) mujeres con 46,5 ± 10,3 años en el momento del inicio del tratamiento. En 88 (84,6%) diagnóstico de MC. Tratamiento con Galcanezumab y Fremanezumab (52 casos cada fármaco). Respuesta en 75 pacientes (72,1%). En el grupo de pacientes respondedores se observó menor edad al inicio del tratamiento (44,1 ± 10,6 vs 49,7 ± 9,1, p:0,006), menor latencia en años inicio migraña-tratamiento (22,4 ± 12,2 vs 28,2 ± 14,4, p:0,029) y menor latencia en meses inicio MC o MEAF-tratamiento (90,4 ± 51,9 vs 118,5 ± 61,2, p:0,013). Los rasgos de personalidad más presentes en la muestra fueron: histriónico (64,4%), anancástico (52,9%) y ansioso (50%). Predijo la ausencia de respuesta al tratamiento la presencia del rasgo inestabilidad emocional subtipo límite (OR:0,24 (0,09-0,64)).
ConclusionesLos rasgos de personalidad, junto a otras variables clínicas y demográficas, pueden ser factores predictores de respuesta al tratamiento con AcM frente al CGRP.
Interest in the personality traits of patients with migraine dates back to the early 20th century.1 Initially, a correlation was suggested between migraine and rigid, ambitious personalities.2 However, with the development of objective personality questionnaires, no single personality trait was found to be associated with the condition.3
Personality, defined as a set of psychological traits including feelings, thoughts, and behaviours, has been studied through different models. Among these, the Five-Factor Model of Personality is the most widely used in contemporary psychology. This model establishes 5 dimensions of personality: neuroticism, extraversion, openness to experience, agreeableness, and conscientiousness.4 Neuroticism, characterised by a tendency to nervousness and greater susceptibility to negative emotions, has been found to be more prevalent among patients with migraine.5
In the fifth edition of the American Psychiatric Association’s Diagnostic and Statistical Manual of Mental Disorders (DSM-5), these domains are structured in a more categorical manner. Innate patterns of behaviour and emotional regulation constitute the foundation of basic personality traits. When these traits reflect significant maladaptation to the environment, they are classified as personality disorders.6 Although contemporary psychiatry increasingly integrates the dimensional perspective of the Five-Factor Model into the DSM-5 classification,7 the subdivision of personality disorders/traits into 3 subgroups remains: A) eccentric, B) dramatic and emotional, and C) anxious.6 Cluster C traits have more frequently been observed in patients with chronic migraine (CM) and medication overuse headache (MOH).8
CH, MOH, and mood disorders are closely interconnected. The bidirectional relationship between CM and anxiety and depression has been recognised for decades, leading to the consideration of these traits as predictors of disease course and treatment response.9 A recent paradigm shift in mental health has led to the consideration of other psychological factors, such as personality traits, as predictors of response to various preventive drugs for CM.10
Monoclonal antibodies (mAb) were the first treatments specifically developed for migraine prevention. Their efficacy and safety have been demonstrated in multiple randomised clinical trials,11 as has their effectiveness in real-world observational studies.12
However, despite their undeniable advantages, mAbs fail to provide clear benefits for some patients. Response to these treatments may be influenced by demographic and clinical variables, including psychiatric comorbidities.13 In any case, no consensus has been reached on the predictors of response to these drugs.
Our study aims to determine whether personality traits can predict response to anti-CGRP mAbs and whether any other clinical or demographic factors are associated with treatment outcomes.
Material and methodsRecruitment and eligibility criteriaWe conducted a single-centre, prospective, observational study between June 2020 and May 2023. The study included patients evaluated at the headache unit of Hospital Clínico Universitario de Valladolid who were over the age of 18 years, had a diagnosis of CM or high-frequency episodic migraine (HFEM) according to the third edition of the International Classification of Headache Disorders (ICHD-3),14 and were treated with anti-CGRP mAbs for the first time, and according to the Spanish national healthcare system reimbursement criteria, for at least 12 weeks. According to these criteria, anti-CGRP mAbs are indicated in patients with CM or HFEM with previous lack of adequate response to at least 3 preventive drugs, one of which must be onabotulinumtoxinA in the case of CM.15 We excluded patients with other concomitant headache disorders (except for MOH) and those presenting adverse drug reactions leading to treatment discontinuation.
The project was approved by the medical research ethics committee of the Valladolid East healthcare district (project no. PI 22-2694). All patients gave written informed consent prior to inclusion.
The choice of anti-CGRP mAb was determined by the hospital’s pharmacy committee, based on their prioritisation within this drug class: galcanezumab was initially used, and subsequently replaced by fremanezumab after its approval.
Procedures and questionnairesWe obtained a complete clinical history for each patient, systematically recording demographic and clinical data, as well as the anti-CGRP mAb used (galcanezumab or fremanezumab).
Demographic variables included sex, age, migraine type (CM or HFEM), age at migraine onset, latency (in years) from migraine onset to treatment onset, and latency (in months) from CM or HFEM diagnosis to treatment onset.
Clinical variables included mean headache intensity, predominant migraine location (hemicranial/holocranial), presence of periocular pain, pain quality (pulsating, pressing, or piercing), presence of aura, number of headache (HDM) and migraine days per month (MDM), frequency of analgesic and triptan use (days per month) before treatment onset, and number of preventive treatments previously tried with poor response.
We used the official calendar established by the health department of our regional government, which is mandatory for patients receiving this treatment, both for baseline assessment and for follow-up. This calendar is used to record the number of headache or migraine days, pain intensity, symptomatic treatments used, and the need for emergency care.
Treatment response was defined as a ≥ 50% decrease in the number of HDM after 3 months of treatment.
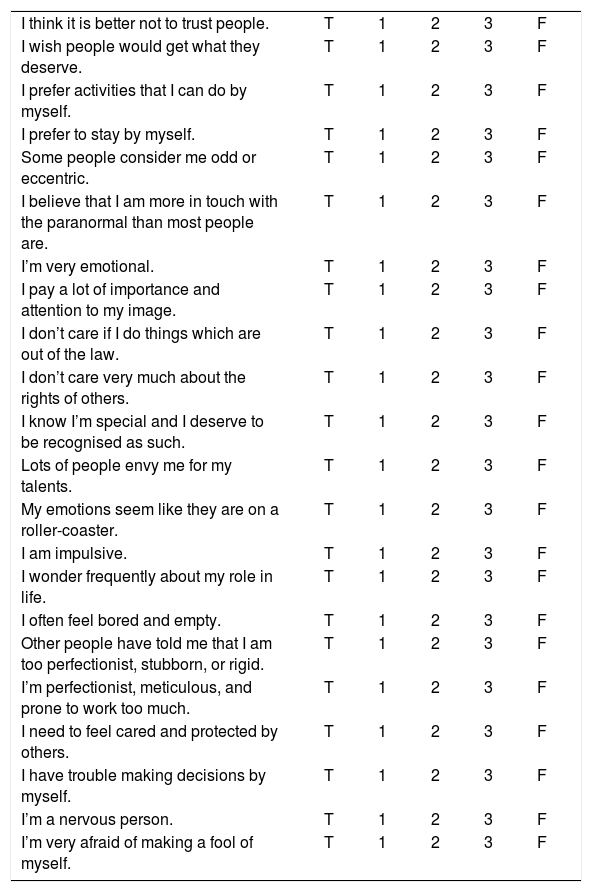
Personality traits were evaluated with the Salamanca Screening Test (Table 1), which was administered between January and May 2023. The Salamanca Screening Test is a brief, simple, and highly sensitive tool, validated in 2007 for the early detection of personality traits according to the nomenclature of the fourth edition of the Diagnostic and Statistical Manual of Mental Disorders (DSM-4) and the 10th edition of the International Classification of Diseases (ICD-10). The DSM-5 nomenclature has remained unchanged with respect to that of the DSM-4. The test includes 22 items evaluating 11 specific personality traits (2 items per trait). Each question has 4 possible answers, with a maximum score of 3 points. The presence of a personality trait is evaluated on a scale from 0 to 6 points, with scores above 2 points indicating a tendency toward the personality trait evaluated.16
Salamanca Screening Test for personality disorders.
| I think it is better not to trust people. | T | 1 | 2 | 3 | F |
| I wish people would get what they deserve. | T | 1 | 2 | 3 | F |
| I prefer activities that I can do by myself. | T | 1 | 2 | 3 | F |
| I prefer to stay by myself. | T | 1 | 2 | 3 | F |
| Some people consider me odd or eccentric. | T | 1 | 2 | 3 | F |
| I believe that I am more in touch with the paranormal than most people are. | T | 1 | 2 | 3 | F |
| I’m very emotional. | T | 1 | 2 | 3 | F |
| I pay a lot of importance and attention to my image. | T | 1 | 2 | 3 | F |
| I don’t care if I do things which are out of the law. | T | 1 | 2 | 3 | F |
| I don’t care very much about the rights of others. | T | 1 | 2 | 3 | F |
| I know I’m special and I deserve to be recognised as such. | T | 1 | 2 | 3 | F |
| Lots of people envy me for my talents. | T | 1 | 2 | 3 | F |
| My emotions seem like they are on a roller-coaster. | T | 1 | 2 | 3 | F |
| I am impulsive. | T | 1 | 2 | 3 | F |
| I wonder frequently about my role in life. | T | 1 | 2 | 3 | F |
| I often feel bored and empty. | T | 1 | 2 | 3 | F |
| Other people have told me that I am too perfectionist, stubborn, or rigid. | T | 1 | 2 | 3 | F |
| I’m perfectionist, meticulous, and prone to work too much. | T | 1 | 2 | 3 | F |
| I need to feel cared and protected by others. | T | 1 | 2 | 3 | F |
| I have trouble making decisions by myself. | T | 1 | 2 | 3 | F |
| I’m a nervous person. | T | 1 | 2 | 3 | F |
| I’m very afraid of making a fool of myself. | T | 1 | 2 | 3 | F |
Each item must be marked “T” if the statement is true, or “F” if the statement is false. If the statement is true, the degree of intensity of the response must be indicated: 1 = sometimes; 2 = frequently; 3 = always.
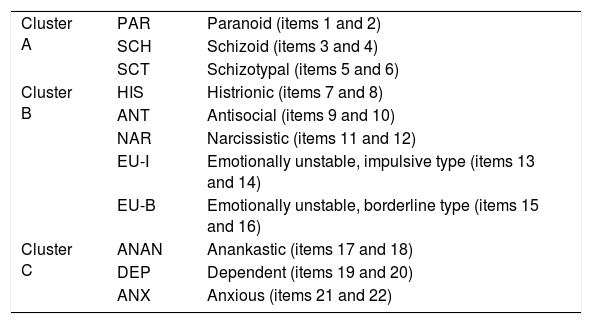
Personality traits in our sample were grouped into 3 clusters according to the DSM-4 and ICD-10 nomenclature (Table 2). Cluster A includes paranoid, schizoid, and schizotypal traits; cluster B includes antisocial, narcissistic, histrionic, borderline, and impulsive traits; and cluster C includes dependent, anankastic, and anxious traits.17,18
Personality traits and clusters according to the Salamanca Screening Test.
| Cluster A | PAR | Paranoid (items 1 and 2) |
| SCH | Schizoid (items 3 and 4) | |
| SCT | Schizotypal (items 5 and 6) | |
| Cluster B | HIS | Histrionic (items 7 and 8) |
| ANT | Antisocial (items 9 and 10) | |
| NAR | Narcissistic (items 11 and 12) | |
| EU-I | Emotionally unstable, impulsive type (items 13 and 14) | |
| EU-B | Emotionally unstable, borderline type (items 15 and 16) | |
| Cluster C | ANAN | Anankastic (items 17 and 18) |
| DEP | Dependent (items 19 and 20) | |
| ANX | Anxious (items 21 and 22) |
Statistical analysis was performed using SPSS statistics software, version 20.0 (SPSS Inc., Chicago, IL, USA). No statistical power calculation was performed before study initiation.
In the descriptive analysis of baseline variables, we calculated means, medians, standard deviation (SD), and range. Qualitative variables are expressed as frequencies and percentages, whereas continuous variables are expressed as means (SD) or median and quartiles 1 and 3 (Q1–Q3), depending on the normality of data distribution, which was assessed with the Kolmogorov-Smirnov test.
In the univariate analysis, the t test was used for normally-distributed quantitative variables, the chi-square test for qualitative variables, and the Mann–Whitney U test for non–normally distributed quantitative variables. Statistical significance was set at P < .05. The main hypothesis was tested with a logistic regression model, using personality traits as predictors of response to anti-CGRP mAbs. Logistic regression models were used to calculate odds ratios (OR) with 95% confidence intervals (CI).
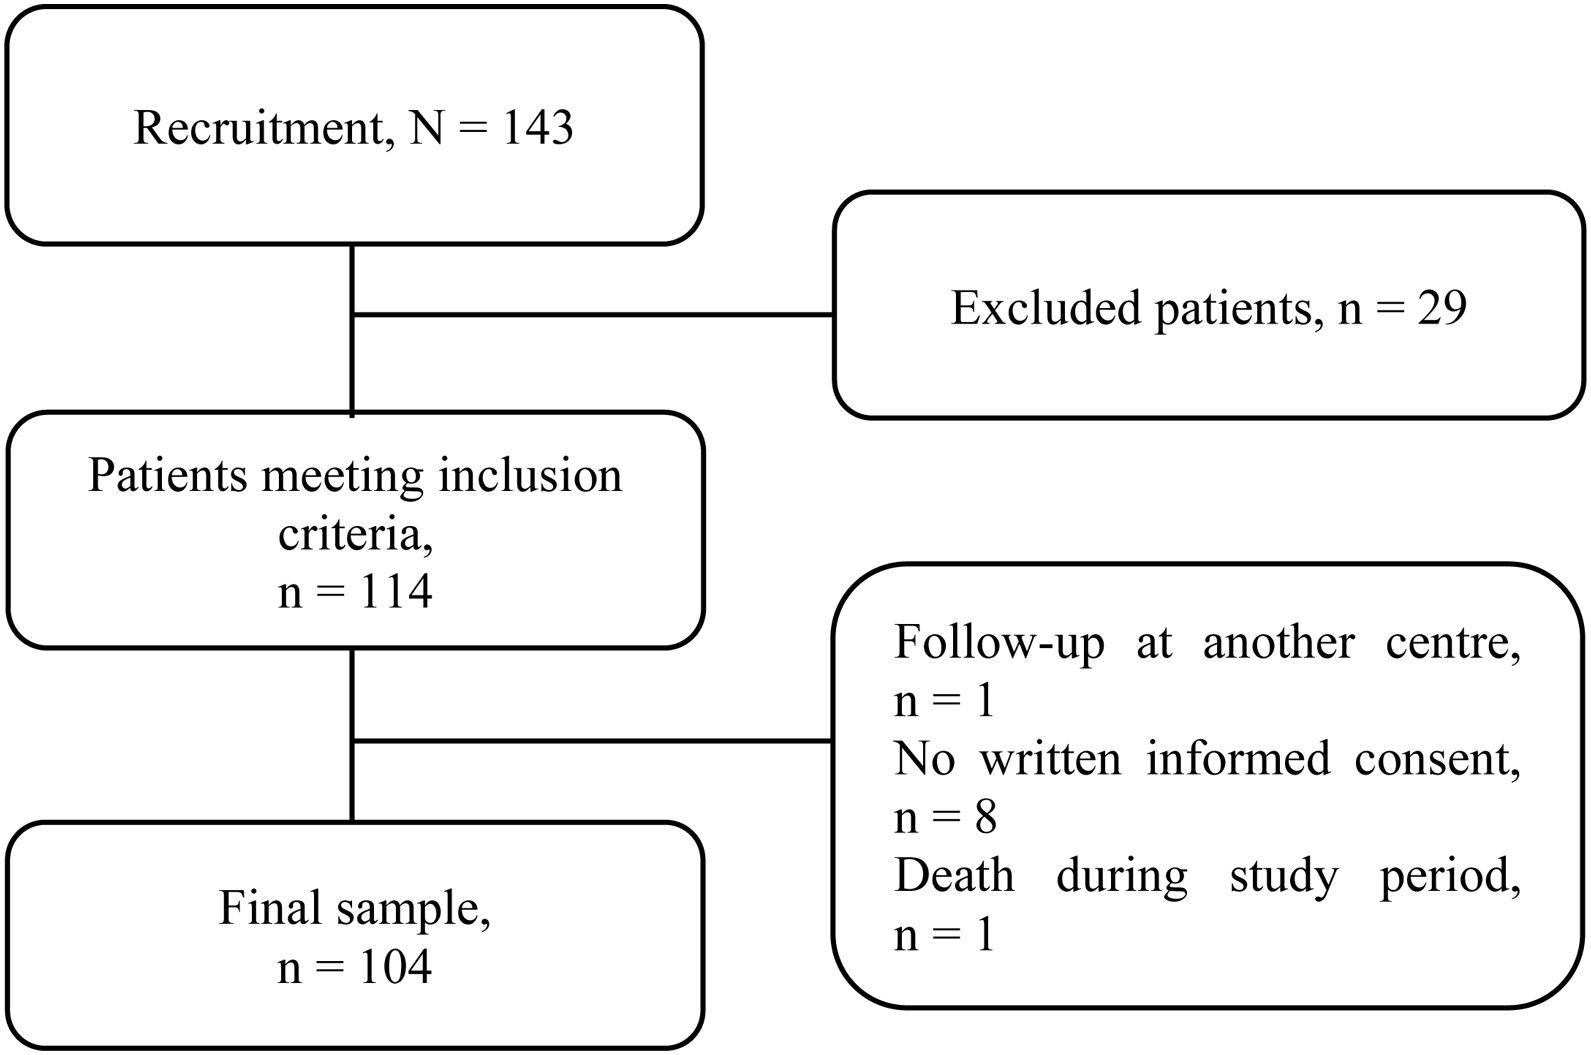
ResultsA total of 143 patients were initially recruited, 29 of whom did not meet the inclusion criteria. Of the remaining 114 patients, 10 were excluded from the study (Fig. 1). Therefore, the final sample comprised 104 patients, 88 of whom were women (84.6%). CM was the most frequent type of migraine in our sample, affecting 88 patients (84.6%), whereas HFEM was observed in 16 patients (15.4%). Regarding the monoclonal antibody used, 52 patients were treated with galcanezumab and 52 with fremanezumab. Treatment response was achieved in 75 patients (72.1%).

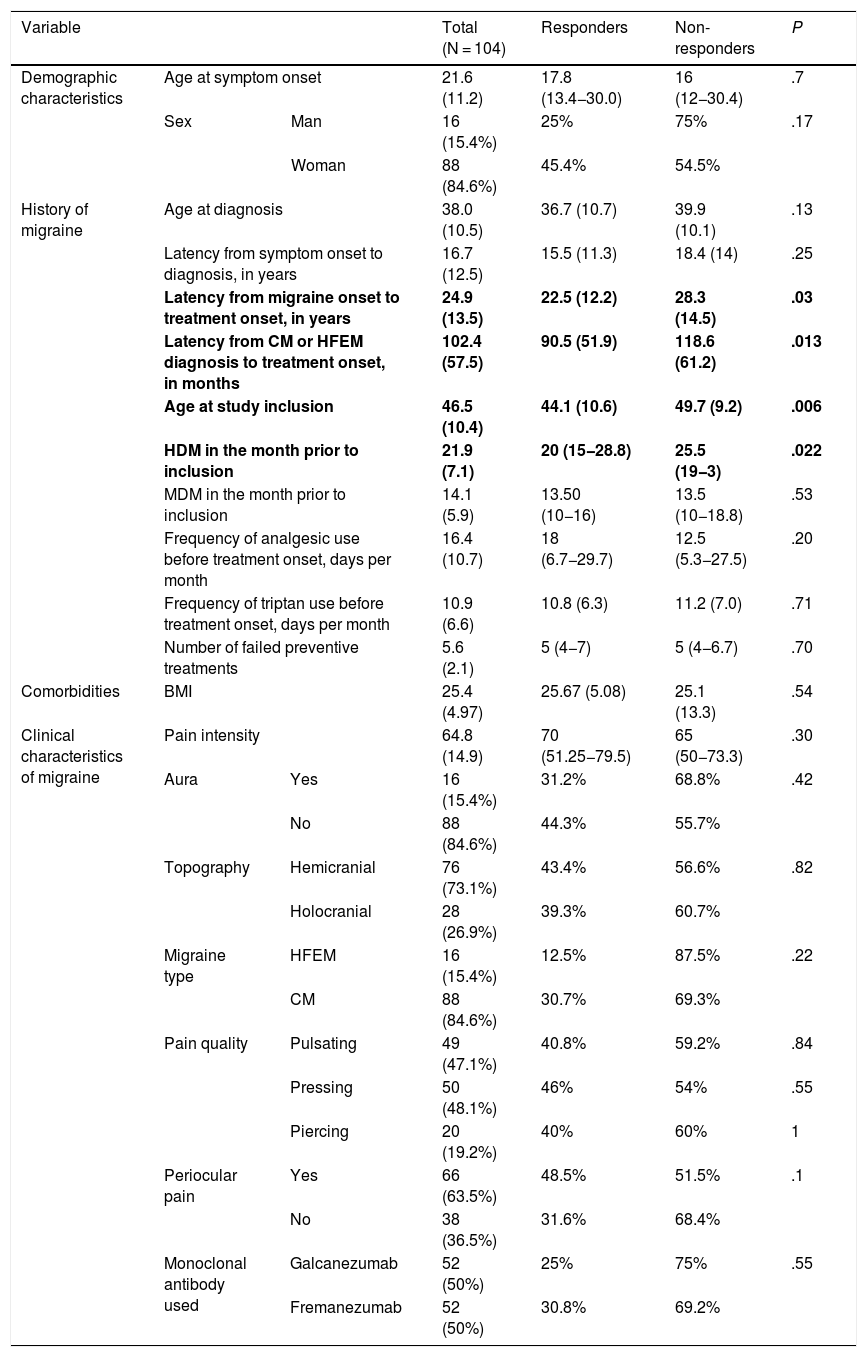
Patients’ demographic and clinical characteristics are summarised in Table 3.
Comparison of demographic and clinical characteristics between responders and non-responders.
| Variable | Total (N = 104) | Responders | Non-responders | P | |||
|---|---|---|---|---|---|---|---|
| Demographic characteristics | Age at symptom onset | 21.6 (11.2) | 17.8 (13.4−30.0) | 16 (12−30.4) | .7 | ||
| Sex | Man | 16 (15.4%) | 25% | 75% | .17 | ||
| Woman | 88 (84.6%) | 45.4% | 54.5% | ||||
| History of migraine | Age at diagnosis | 38.0 (10.5) | 36.7 (10.7) | 39.9 (10.1) | .13 | ||
| Latency from symptom onset to diagnosis, in years | 16.7 (12.5) | 15.5 (11.3) | 18.4 (14) | .25 | |||
| Latency from migraine onset to treatment onset, in years | 24.9 (13.5) | 22.5 (12.2) | 28.3 (14.5) | .03 | |||
| Latency from CM or HFEM diagnosis to treatment onset, in months | 102.4 (57.5) | 90.5 (51.9) | 118.6 (61.2) | .013 | |||
| Age at study inclusion | 46.5 (10.4) | 44.1 (10.6) | 49.7 (9.2) | .006 | |||
| HDM in the month prior to inclusion | 21.9 (7.1) | 20 (15−28.8) | 25.5 (19−3) | .022 | |||
| MDM in the month prior to inclusion | 14.1 (5.9) | 13.50 (10−16) | 13.5 (10−18.8) | .53 | |||
| Frequency of analgesic use before treatment onset, days per month | 16.4 (10.7) | 18 (6.7−29.7) | 12.5 (5.3−27.5) | .20 | |||
| Frequency of triptan use before treatment onset, days per month | 10.9 (6.6) | 10.8 (6.3) | 11.2 (7.0) | .71 | |||
| Number of failed preventive treatments | 5.6 (2.1) | 5 (4−7) | 5 (4−6.7) | .70 | |||
| Comorbidities | BMI | 25.4 (4.97) | 25.67 (5.08) | 25.1 (13.3) | .54 | ||
| Clinical characteristics of migraine | Pain intensity | 64.8 (14.9) | 70 (51.25−79.5) | 65 (50−73.3) | .30 | ||
| Aura | Yes | 16 (15.4%) | 31.2% | 68.8% | .42 | ||
| No | 88 (84.6%) | 44.3% | 55.7% | ||||
| Topography | Hemicranial | 76 (73.1%) | 43.4% | 56.6% | .82 | ||
| Holocranial | 28 (26.9%) | 39.3% | 60.7% | ||||
| Migraine type | HFEM | 16 (15.4%) | 12.5% | 87.5% | .22 | ||
| CM | 88 (84.6%) | 30.7% | 69.3% | ||||
| Pain quality | Pulsating | 49 (47.1%) | 40.8% | 59.2% | .84 | ||
| Pressing | 50 (48.1%) | 46% | 54% | .55 | |||
| Piercing | 20 (19.2%) | 40% | 60% | 1 | |||
| Periocular pain | Yes | 66 (63.5%) | 48.5% | 51.5% | .1 | ||
| No | 38 (36.5%) | 31.6% | 68.4% | ||||
| Monoclonal antibody used | Galcanezumab | 52 (50%) | 25% | 75% | .55 | ||
| Fremanezumab | 52 (50%) | 30.8% | 69.2% | ||||
BMI: body mass index; CM: chronic migraine; HDM: number of headache days per month; HFEM: high-frequency episodic migraine; MDM: number of migraine days per month; Q1–Q3: quartiles 1 and 3; SD: standard deviation. Data are expressed as number (%), mean (SD), or median (Q1-Q3).
Regarding demographic characteristics in the total sample, mean latency from migraine onset to treatment onset was 24.9 years (SD: 13.5), and mean latency from CM or HFEM diagnosis to treatment onset was 102.4 months (57.5). The mean number of HDM and MDM in the month prior to inclusion was 21.9 (7.1) and 14.1 (5.9), respectively. The frequency of analgesic use before treatment onset was 16.4 (10.7) days per month, whereas the frequency of triptan use was 10.9 (6.6) days per month.
Table 3 compares clinical and demographic variables between responders and non-responders to anti-CGRP monoclonal antibodies. The bivariate analysis showed significantly older age at treatment onset (49.7 [9.2] vs 44.1 years [10.6]; P = .06), greater latency from migraine onset to treatment onset (28.3 [14.2] vs 22.5 years [12.2]; P = .013), greater latency from CM or HFEM diagnosis to treatment onset (118.6 [61.2] vs 90.5 months [51.9]; P = .03), and more HDM prior to study inclusion (20 [15−28.8] vs 25.5 [19–3]; P = .022) among non-responders as compared to the group of responders.
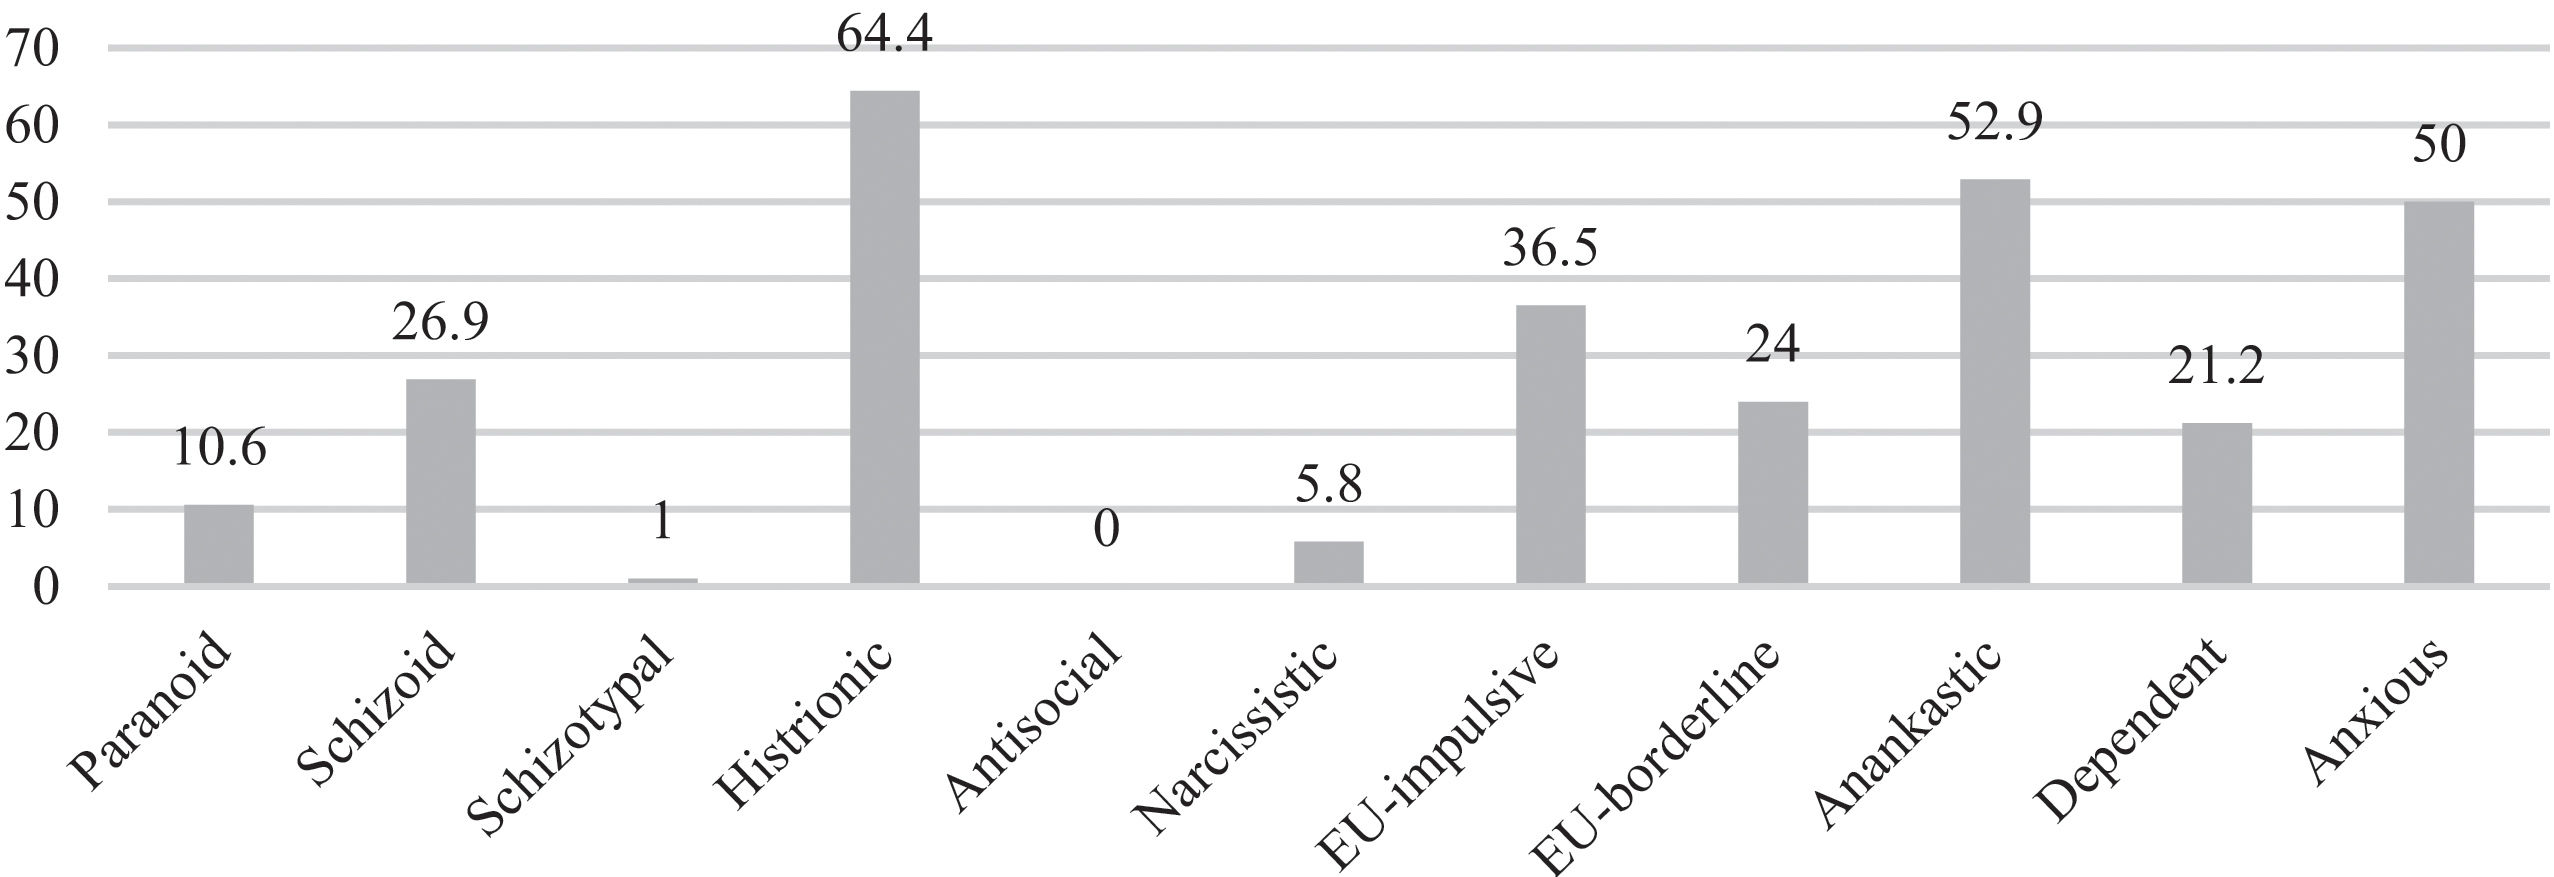
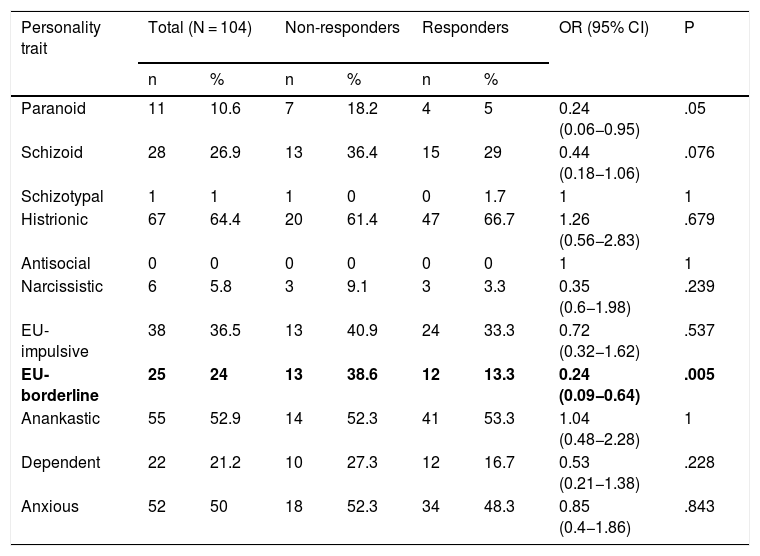
The distribution of personality traits was based on the DSM-4 nomenclature (Fig. 2). Table 4 shows the influence of personality traits in responders and non-responders to anti-CGRP monoclonal antibodies. In the univariate analysis, the trait emotionally unstable, borderline type was found to be significantly more frequent among non-responders (68 vs 32; P = .005). A statistically significant association remained between this trait and non-response to treatment in the logistic regression model (OR: 0.2 [0.1−0.64]).

Associations between personality traits and response to anti-CGRP monoclonal antibodies in the univariate analysis and the logistic regression model.
| Personality trait | Total (N = 104) | Non-responders | Responders | OR (95% CI) | P | |||
|---|---|---|---|---|---|---|---|---|
| n | % | n | % | n | % | |||
| Paranoid | 11 | 10.6 | 7 | 18.2 | 4 | 5 | 0.24 (0.06−0.95) | .05 |
| Schizoid | 28 | 26.9 | 13 | 36.4 | 15 | 29 | 0.44 (0.18−1.06) | .076 |
| Schizotypal | 1 | 1 | 1 | 0 | 0 | 1.7 | 1 | 1 |
| Histrionic | 67 | 64.4 | 20 | 61.4 | 47 | 66.7 | 1.26 (0.56−2.83) | .679 |
| Antisocial | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 1 |
| Narcissistic | 6 | 5.8 | 3 | 9.1 | 3 | 3.3 | 0.35 (0.6−1.98) | .239 |
| EU-impulsive | 38 | 36.5 | 13 | 40.9 | 24 | 33.3 | 0.72 (0.32−1.62) | .537 |
| EU-borderline | 25 | 24 | 13 | 38.6 | 12 | 13.3 | 0.24 (0.09−0.64) | .005 |
| Anankastic | 55 | 52.9 | 14 | 52.3 | 41 | 53.3 | 1.04 (0.48−2.28) | 1 |
| Dependent | 22 | 21.2 | 10 | 27.3 | 12 | 16.7 | 0.53 (0.21−1.38) | .228 |
| Anxious | 52 | 50 | 18 | 52.3 | 34 | 48.3 | 0.85 (0.4−1.86) | .843 |
CI: confidence interval; EU: emotionally unstable; OR: odds ratio.
Our study identified a specific personality trait, emotionally unstable, borderline type, that acts as a potential predictor of poor response to anti-CGRP monoclonal antibodies in patients with migraine.
Other factors including older age at treatment onset, greater latency from migraine onset to treatment onset, and greater latency from migraine diagnosis to treatment onset, were also found to predict poor response. Furthermore, the subgroup of responders presented fewer HDM before study inclusion.
Personality is a central topic in the study of human behaviour.19 The recent societal recognition of mental health has led to a growing interest in this topic beyond the psychological sphere. This study adds to the growing body of evidence acknowledging mental health as an integral component in several research fields, and supports the current trend toward a more personalised therapeutic approach.20
The most frequently used model in clinical psychology for structuring personality is the Five-Factor Model of Personality.4 However, other models also describe personality according to a series of dimensions, although with differences in the number of these dimensions. The most widely recognised models are Cloninger’s psychobiological model, which includes 7 dimensions,21 and Eysenk’s three-factor model, which establishes 3 personality domains: extroversion, neuroticism, and psychoticism.22
These 3 theories have been used to define the personality traits of patients with migraine. Studies using the psychobiological model more frequently describe these patients as avoidant, with poor tolerance to uncertainty and low self-directedness.23 On the other hand, when personality is evaluated with Eysenk’s three-factor model or the Five-Factor Model, patients with migraine more frequently display a tendency to emotional insecurity and instability, a key characteristic of neuroticism.5 Neuroticism has also been associated with poorer prognosis and quality of life in CM, and has been proposed as a risk factor for MOH in patients with migraine and associated depression.24
To evaluate personality from this dimensional perspective, several questionnaires are used, such as the Eysenck Personality Questionnaire4 and the Minnesota Multiphasic Personality Inventory,21 which require specific training for their correct administration and interpretation.22 Although several authors support this dimensional approach to personality, its application in clinical practice may lead to misinterpretation if the assessment is not performed by a trained professional.25
On the other hand, the DSM-5 adopts a more categorical perspective,6 in which personality traits are defined by patterns of perceiving, relating to, and interacting with the environment; these traits reflect a personality disorder when they become maladaptive or resistant to change.6 Patterns of inner experience and behaviour develop during adolescence and remain stable over time.6 There is controversy over whether personality should be studied from a dimensional or a categorical perspective. While the dimensional model provides a continuity that is lacking in the categorical model, it is unable to correctly represent some personality disorders. The current trend is to develop assessments that integrate both models.7
The relationship between migraine and personality has been analysed from both perspectives. The advantage of evaluating personality using the DSM-5 is the ease of interpretation using simple questionnaires (e.g., the Salamanca Screening Test16) that can be applied in the clinical setting.25 Using this taxonomy, some studies suggest that cluster C personality traits are more prevalent among patients with CM.26 The relationship between personality traits and other headache disorders has also been analysed. Timidity and introversion, characteristic of cluster C, have been associated with tension-type headache,27 whereas eccentricity and rigidity, typical of cluster A, have been associated with cluster headache.26
In our sample, the most frequent personality trait was histrionic (cluster B) (64.4%), followed by anankastic (52.9%) and anxious (50%), both from cluster C; these findings are comparable to those reported in other studies using the same tools.10
A total of 72.1% of patients presented treatment response, defined as a ≥ 50% decrease in the number of HDM. The response rate in our series is higher than that observed in clinical trials,11 and similar to that reported in more recent real-world studies.12
An analysis of the role of personality traits in response to anti-CGRP mAb treatment revealed a significant association between borderline personality and poor treatment response. This trait belongs to cluster B6 and is characterised by impulsive behaviour and feelings of emptiness.28 It has been associated with poor response to other preventive treatments for CM, such as onabotulinumtoxinA.10
A recent study supports our hypothesis, but using other measurement instruments, and reports that depressive mood and anhedonia may act as predictors of poor response to mAbs.29 Rigid, obsessive, dysfunctional behaviours, associated with obsessive-compulsive personality disorder (cluster C), are also reported to be associated with poor response to erenumab.30
A psychopathological explanation has been proposed for this phenomenon, integrating the relationship between certain personality traits and poor response to preventive treatments for CM. One hypothesis in the case of cluster C personality traits/disorders is that obsessive behaviour is associated with low pain tolerance.31 On the other hand, in individuals with cluster B personality traits, lack of treatment response may be due to uncontrolled fear to anticipated pain, which tends to be managed with such impulsive behaviours as overuse of analgesic medications.32
Regarding the clinical and demographic characteristics of our sample, older age at treatment onset and longer latency from migraine onset or CM/HFEM diagnosis to onset of mAb therapy were significantly associated with poor treatment response, whereas a lower number of HDM prior to treatment was associated with better response. No significant association was observed between age at symptom onset and response to anti-CGRP monoclonal antibodies; this finding is comparable to those of other demographic studies specifically designed to assess this association.33 However, the duration of CM or HFEM prior to treatment did show a significant association with treatment response in our study; similar results are reported in the 2022 study by Iannone et al.34
The widely reported association between a lower number of HDM at treatment onset and response to mAb therapy is controversial. While some authors believe that this factor may be considered a predictor of good treatment response,34,35 others have failed to observe such an association.36 In the study by Barbanti et al.,37 a higher number of HDM at baseline was associated with good response to erenumab in patients with CM; this variable was also defined as a predictor of response to galcanezumab in the study by Obach et al.38
In our study, no significant association was observed between any clinical characteristic of migraine and lack of response. However, both trigeminal sensitisation (unilateral pain and unilateral cranial parasympathetic autonomic symptoms) in patients with HFEM and central sensitisation (allodynia) in patients with CM have been described as predictors of response to these treatments.13 A recent meta-analysis identified presence of unilateral pain associated with allodynia and autonomic symptoms as predictors of good response to anti-CGRP mAbs.13
Lastly, although our study did not observe a significant association with such other comorbidities as obesity, high BMI has been found to predict poor response to mAb therapy in other studies.39
Our study is not without limitations. Firstly, personality was assessed after onset of mAb therapy. Although personality traits are considered to be stable, we cannot guarantee that the personality traits observed before treatment onset would have been identical. Furthermore, the drugs used in our centre were galcanezumab and fremanezumab, and our results cannot be extrapolated to other mAbs. Lastly, our study did not include a control group of healthy individuals, and our sample was small and recruited from a single hospital. These factors should be taken into consideration when interpreting our results and in the planning of future studies.
ConclusionOur study shows that non-responders to mAbs present different personality traits compared to responders. Specifically, borderline personality was associated with poor response to anti-CGRP mAbs in patients with refractory migraine. This finding underscores the need to consider psychological factors in the assessment and management of patients with refractory migraine.
Certain demographic and clinical factors, such as older age at treatment onset and greater latency from diagnosis to treatment, were also associated with poorer response to anti-CGRP mAbs. In contrast, patients presenting fewer HDM prior to study inclusion responded better to treatment.
Our findings support the consideration of personality assessment and certain clinical factors in the management of patients with refractory migraine, providing a foundation to improve clinical decision-making and optimise treatment outcomes.
CRediT authorship contribution statementStudy conception and design: Ángel Luis Guerrero Peral, María del Mar López Navarro.
Data collection: Ángel Luis Guerrero Peral, María del Mar López Navarro, Andrea Recio García.
Data analysis and interpretation: Isabel Ros González, María del Mar López Navarro, David García Azorín.
Manuscript drafting: Isabel Ros González.
Critical review of the manuscript: Ángel Luis Guerrero Peral, David García Azorín.
Approval of the final version of the article: all authors.
Ethical approval and patient consentThe study complies with the principles established in the Declaration of Helsinki and was approved by the medical research ethics committee of the Valladolid East health district (project no. PI 22-2964). It was conducted in compliance with Spanish Organic Law 3/2018 of 5 December, on personal data protection and digital rights. All patients were informed that they retain the rights to access, correction, cancellation, and objection with regard to their personal data at all times.
Consent to publicationNot applicable.
Sources of fundingThis study has received no specific funding from any public, commercial, or non-profit organisation.
None.


