


Seizures are one of the main neurological reasons for admission to paediatric emergency departments (ED). The early, appropriate management of acute seizures is crucial to improving patient outcomes, with prehospital care playing a critical role in this matter.
MethodsWe conducted a retrospective cross-sectional study of patients under 18 years of age admitted due to seizures to a metropolitan paediatric ED during a period of one year (June 2023-May 2024). Prehospital management and its association with clinical progression were analysed.
ResultsA total of 697 emergency episodes of seizures were identified: 328 epileptic seizures (47.1%), 290 febrile seizures (41.6%), 47 convulsive status epilepticus (SE) (6.7%), and 32 febrile SE (4.6%). Patients were referred to the ED by the emergency medical services (EMS) in 73.5% of episodes (n = 512). A first dose of an antiseizure medication (ASM) was administered in the prehospital setting in 29.4% of episodes (n = 205), using a benzodiazepine in 99.5% (n = 204). Prehospital ASM administration was more frequent in patients attended by the EMS (P < .001). Prehospital protocol compliance was verified in 71.7% of episodes (n = 114). Patients attended by EMS had a higher likelihood of prehospital seizure control and hospital discharge after the episode (P < .05).
ConclusionsPrehospital care was associated with higher prehospital seizure control and lower rates of hospitalisation. These findings emphasise the relevance of studying prehospital management, enabling the identification of opportunities for improvement, not only related to EMS procedures, but also to caregivers’ knowledge about paediatric seizures.
Las crisis epilépticas son una de las principales causas neurológicas de admisión en los servicios de urgencias pediátricas. El manejo adecuado y precoz de las crisis agudas es fundamental para mejorar los resultados clínicos, siendo la atención prehospitalaria un elemento clave en este proceso.
MétodosSe realizó un estudio transversal retrospectivo de pacientes menores de 18 años atendidos por crisis epilépticas en un servicio de urgencias pediátricas de ámbito metropolitano durante un año (junio de 2023 a mayo de 2024). Se analizó la atención prehospitalaria y su asociación con la evolución clínica.
ResultadosSe identificaron 697 episodios de urgencia por crisis: 47,1% (n = 328) crisis epilépticas; 41,6% (n = 290) crisis febriles; 6,7% (n = 47) estado epiléptico convulsivo (EEC); y 4,6% (n = 32) EEC febril. En el 73,5% (n = 512) de los episodios, los pacientes fueron derivados al servicio de urgencias por los servicios médicos de emergencia (SME). En el 29,4% (n = 205) de los casos se administró una primera dosis de medicación antiepiléptica (MAE) en el entorno prehospitalario, utilizándose benzodiacepinas en el 99,5% (n = 204). La administración de MAE fue más frecuente en los pacientes atendidos por los SME (p < 0,001). Se observó cumplimiento del protocolo prehospitalario en el 71,7% (n = 114) de los episodios. Los pacientes atendidos por los SME presentaron una mayor probabilidad de control de la crisis antes del ingreso y de alta hospitalaria (p < 0,05).
ConclusionesLa atención prehospitalaria mostró una asociación con un mayor control de las crisis antes del ingreso hospitalario y una menor tasa de hospitalización. Estos hallazgos destacan la importancia de analizar el abordaje prehospitalario, permitiendo identificar oportunidades de mejora, tanto en los procedimientos de los SME como en el conocimiento de los cuidadores sobre las crisis epilépticas pediátricas.
Seizures are a frequent cause of admission to paediatric emergency departments (ED) and are among the main neurological reasons for emergency care.1,2 Approximately 5% of children will experience a seizure before the age of 16, with risk being higher in children younger than 3 years old.3 Additionally, one in 150 children is diagnosed with epilepsy within the first 10 years of life.3,4
Prolonged seizures, lasting longer than 5 minutes, or recurrent seizures without returning to the baseline are classified as status epilepticus (SE), which is considered the most severe form of seizure.5 The overall incidence of SE is 17-23 cases per 100 000 children per year.6 This condition can lead to neuronal injury, affecting both functional and cognitive development and significantly impacting quality of life. The associated mortality rate may be as high as 20%.7 Although aetiology is a key factor in long-term prognosis, observational studies have shown that delayed treatment and prolonged seizure time are independently associated with both increased morbidity and mortality.7–9
Early, appropriate management of acute seizures is crucial, with prehospital emergency care playing a critical role in early intervention.10–12 Worldwide, several protocols have been published to guide the in-hospital management of these patients. However, their implementation at the prehospital level may be challenging due to limited resources or due to the limited experience of the emergency professionals attending paediatric patients with seizures.13–15 Current international research on paediatric acute seizures and SE management mainly focuses on in-hospital care, with reduced awareness of prehospital practices. We lack data on the real-world prehospital management of paediatric patients with seizures, with or without status epilepticus.16 Better understanding of prehospital seizure management could make it possible to gauge compliance with current recommendations and to identify strategies for improving these procedures.
The aim of this study was to describe the prehospital management of patients with seizures admitted to a tertiary healthcare centre, as well as to analyse factors associated with their clinical progression.
MethodsStudy designWe conducted a retrospective, cross-sectional, observational study, evaluating patients admitted to the paediatric ED of a tertiary hospital over a period of one year (1 June 2023 to 31 May 2024) due to an acute seizure episode. This multicentre ED, designated as Urgência Pediátrica Integrada do Porto (Porto Integrated Paediatric Emergency Department), admits paediatric patients from the referral areas of 3 hospitals (2 tertiary and one secondary), mainly from the north of Portugal, constituting a metropolitan ED. The study protocol was approved by the Clinical Research Ethics Committee and by the data protection officer of the São João local healthcare unit. Data were collected and stored in a pseudo-anonymised, coded database.
ParticipantsPatients between one month and 18 years of age with at least one admission to the paediatric ED coded under the “neurological” category and the “seizure” subgroup were included. We excluded the episodes in which: 1) the final diagnosis was not a seizure, 2) presentation was non-convulsive status epilepticus, 3) the patient left the ED after admission without receiving hospital care, and 4) seizure onset occurred in hospital.
Since the prevalence of the condition in the target population was unknown, the required sample size was estimated using the formula for proportion estimation with an unknown prevalence:
where:
- •
Z represents the critical value for a 95% confidence level (1.96); and
- •
E is the margin of error, set at 5% (0.05).
Applying these parameters, the minimum required sample size was estimated at 384 patients, ensuring a reliable estimation of the studied outcomes within the predefined margin of error. However, during the study period, 697 seizure-related emergency episodes were identified, exceeding the initially estimated sample size.
Data collectionData were extracted from the electronic records of emergency episodes using the JOne® V6 software, the platform used in the ED for clinical records.
For each episode, we obtained data on patient demographics (age, sex), clinical characteristics (previous diagnosis of epilepsy, current antiseizure medication [ASM], neurological comorbidities), prehospital and in-hospital interventions (emergency services activated, therapeutic management, airway management, intravenous [IV] cannulation, and IV fluid administration), and seizure characteristics (type of seizure and classification in accordance with the criteria of the International League Against Epilepsy). To evaluate in-hospital progression, data were collected on the in-hospital management of the seizure, treatment response, and patient referral (discharge, hospitalisation, or admission to an intensive care unit [ICU]).
Febrile seizure was defined as a seizure occurring in a child aged between 6 months and 5 years during a febrile episode not caused by an acute central nervous system (CNS) disease, in the absence of previous neurological deficits (i.e., with no pre-, peri-, or postnatal brain damage, with normal psychomotor development, and with no previous afebrile seizures).17 Convulsive SE was defined as prolonged seizure, lasting longer than 5 minutes for tonic-clonic SE or longer than 10 minutes for focal SE, or a series of seizures without full recovery of consciousness between seizures.5 Febrile SE was defined as a prolonged febrile seizure, lasting longer than 30 minutes, or a series of seizures without full recovery of consciousness between seizures.17 Epileptic seizures were classified as focal, focal to bilateral, and generalised.18
The protocol established by the Portuguese Society of Neuropediatrics was regarded as the reference standard.14 To evaluate prehospital protocol compliance and assess dose appropriateness, weight-for-age was estimated using the Best Guess Method for the episodes where weight was unavailable.19
OutcomesThe key outcome variable was prehospital ASM administration for seizure management, focusing on compliance with the established protocol. Secondary outcomes included seizure control (the need for additional ASMs in the hospital setting) and patient referral after the episode (home discharge, paediatric ward admission or ICU admission).
Statistical analysisStatistical analysis was performed using the IBM SPSS Statistics software, version 29.0.0.0 (IBM Corp.; Armonk, New York, USA).
For the descriptive analysis, continuous variables with a normal distribution are reported as mean (standard deviation) and continuous variables with a non-normal distribution are presented as median (range). Normality was assessed using the Kolmogorov-Smirnov test. Categorical variables are reported as absolute values (n) and relative frequencies (%).
For comparative analysis, the association between categorical variables was assessed using the chi-square test. The association between continuous variables was analysed using parametric tests (for normally distributed variables) and non-parametric tests (for non-normally distributed variables). Multivariate analysis was performed using a multinominal logistic regression. P values <.05 were considered statistically significant.
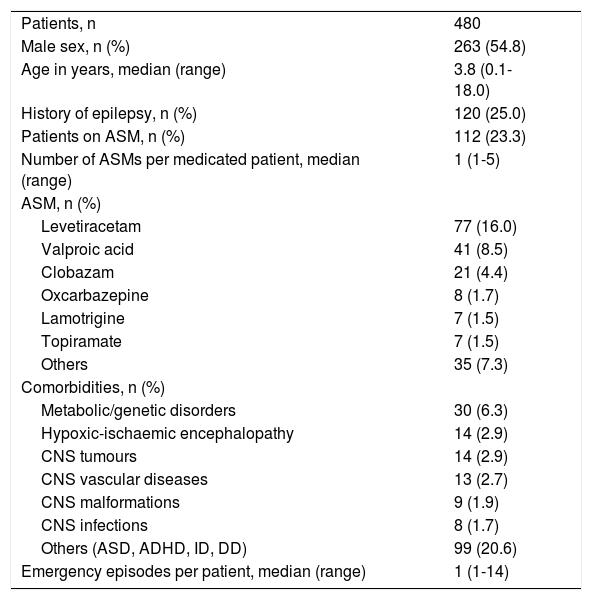
ResultsSample characteristicsOver a period of 366 days, 697 emergency episodes due to seizures were identified. These episodes corresponded to 480 different patients. The number of episodes per patient ranged from one to 14, with 374 patients (77.9%) having only one admission and 3 patients having more than 5 admissions. Among the 480 patients, 54.8% (n = 263) were boys, and the median age was 3.8 years (range: 1 month to 17 years and 11 months). Among patients presenting with epileptic seizures or convulsive SE, a previous diagnosis of epilepsy was identified in 50.2% (n = 120) of patients. Before the event, 46.9% (n = 112) were receiving at least one ASM, with the most frequently used drugs being levetiracetam (68.7%, n = 77) and valproic acid (36.6%, n = 41). Some 7.9% (n = 19) were receiving 3 or more ASMs. Neurological comorbidities were reported in patients with afebrile seizures in 187 cases (Table 1).
Demographic and clinical characteristics of the 480 patients admitted to the emergency department due to seizures.
| Patients, n | 480 |
| Male sex, n (%) | 263 (54.8) |
| Age in years, median (range) | 3.8 (0.1-18.0) |
| History of epilepsy, n (%) | 120 (25.0) |
| Patients on ASM, n (%) | 112 (23.3) |
| Number of ASMs per medicated patient, median (range) | 1 (1-5) |
| ASM, n (%) | |
| Levetiracetam | 77 (16.0) |
| Valproic acid | 41 (8.5) |
| Clobazam | 21 (4.4) |
| Oxcarbazepine | 8 (1.7) |
| Lamotrigine | 7 (1.5) |
| Topiramate | 7 (1.5) |
| Others | 35 (7.3) |
| Comorbidities, n (%) | |
| Metabolic/genetic disorders | 30 (6.3) |
| Hypoxic-ischaemic encephalopathy | 14 (2.9) |
| CNS tumours | 14 (2.9) |
| CNS vascular diseases | 13 (2.7) |
| CNS malformations | 9 (1.9) |
| CNS infections | 8 (1.7) |
| Others (ASD, ADHD, ID, DD) | 99 (20.6) |
| Emergency episodes per patient, median (range) | 1 (1-14) |
ADHD: attention-deficit/hyperactivity disorder; ASD: autistic spectrum disorder; ASM: antiseizure medication; CNS: central nervous system; DD: developmental delay; ID: intellectual disability.
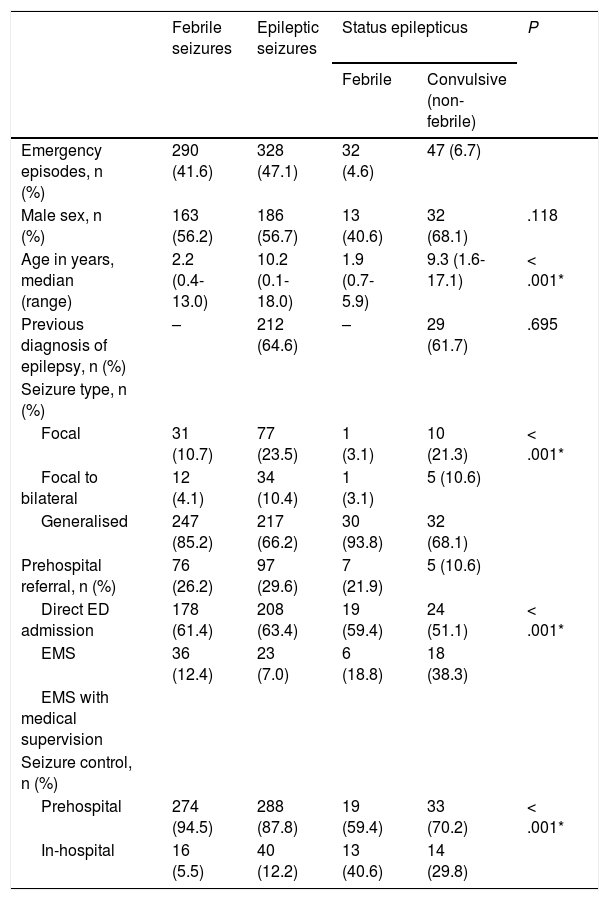
Among the 697 emergency episodes identified, 47.1% (n = 328) were classified as epileptic seizures, 41.6% (n = 290) as febrile seizures, and 11.3% (n = 79) as SE, with 6.7% (n = 47) classified as convulsive SE and 4.6% (n = 32) as febrile SE. The data displayed in Table 2 describe seizure type classification in the patient sample.
Demographic and clinical characteristics of the 697 emergency episodes according to seizure classification. Comparative group analysis.
| Febrile seizures | Epileptic seizures | Status epilepticus | P | ||
|---|---|---|---|---|---|
| Febrile | Convulsive (non-febrile) | ||||
| Emergency episodes, n (%) | 290 (41.6) | 328 (47.1) | 32 (4.6) | 47 (6.7) | |
| Male sex, n (%) | 163 (56.2) | 186 (56.7) | 13 (40.6) | 32 (68.1) | .118 |
| Age in years, median (range) | 2.2 (0.4-13.0) | 10.2 (0.1-18.0) | 1.9 (0.7-5.9) | 9.3 (1.6-17.1) | < .001* |
| Previous diagnosis of epilepsy, n (%) | – | 212 (64.6) | – | 29 (61.7) | .695 |
| Seizure type, n (%) | |||||
| Focal | 31 (10.7) | 77 (23.5) | 1 (3.1) | 10 (21.3) | < .001* |
| Focal to bilateral | 12 (4.1) | 34 (10.4) | 1 (3.1) | 5 (10.6) | |
| Generalised | 247 (85.2) | 217 (66.2) | 30 (93.8) | 32 (68.1) | |
| Prehospital referral, n (%) | 76 (26.2) | 97 (29.6) | 7 (21.9) | 5 (10.6) | |
| Direct ED admission | 178 (61.4) | 208 (63.4) | 19 (59.4) | 24 (51.1) | < .001* |
| EMS | 36 (12.4) | 23 (7.0) | 6 (18.8) | 18 (38.3) | |
| EMS with medical supervision | |||||
| Seizure control, n (%) | |||||
| Prehospital | 274 (94.5) | 288 (87.8) | 19 (59.4) | 33 (70.2) | < .001* |
| In-hospital | 16 (5.5) | 40 (12.2) | 13 (40.6) | 14 (29.8) | |
ED: emergency department; EMS: emergency medical services.
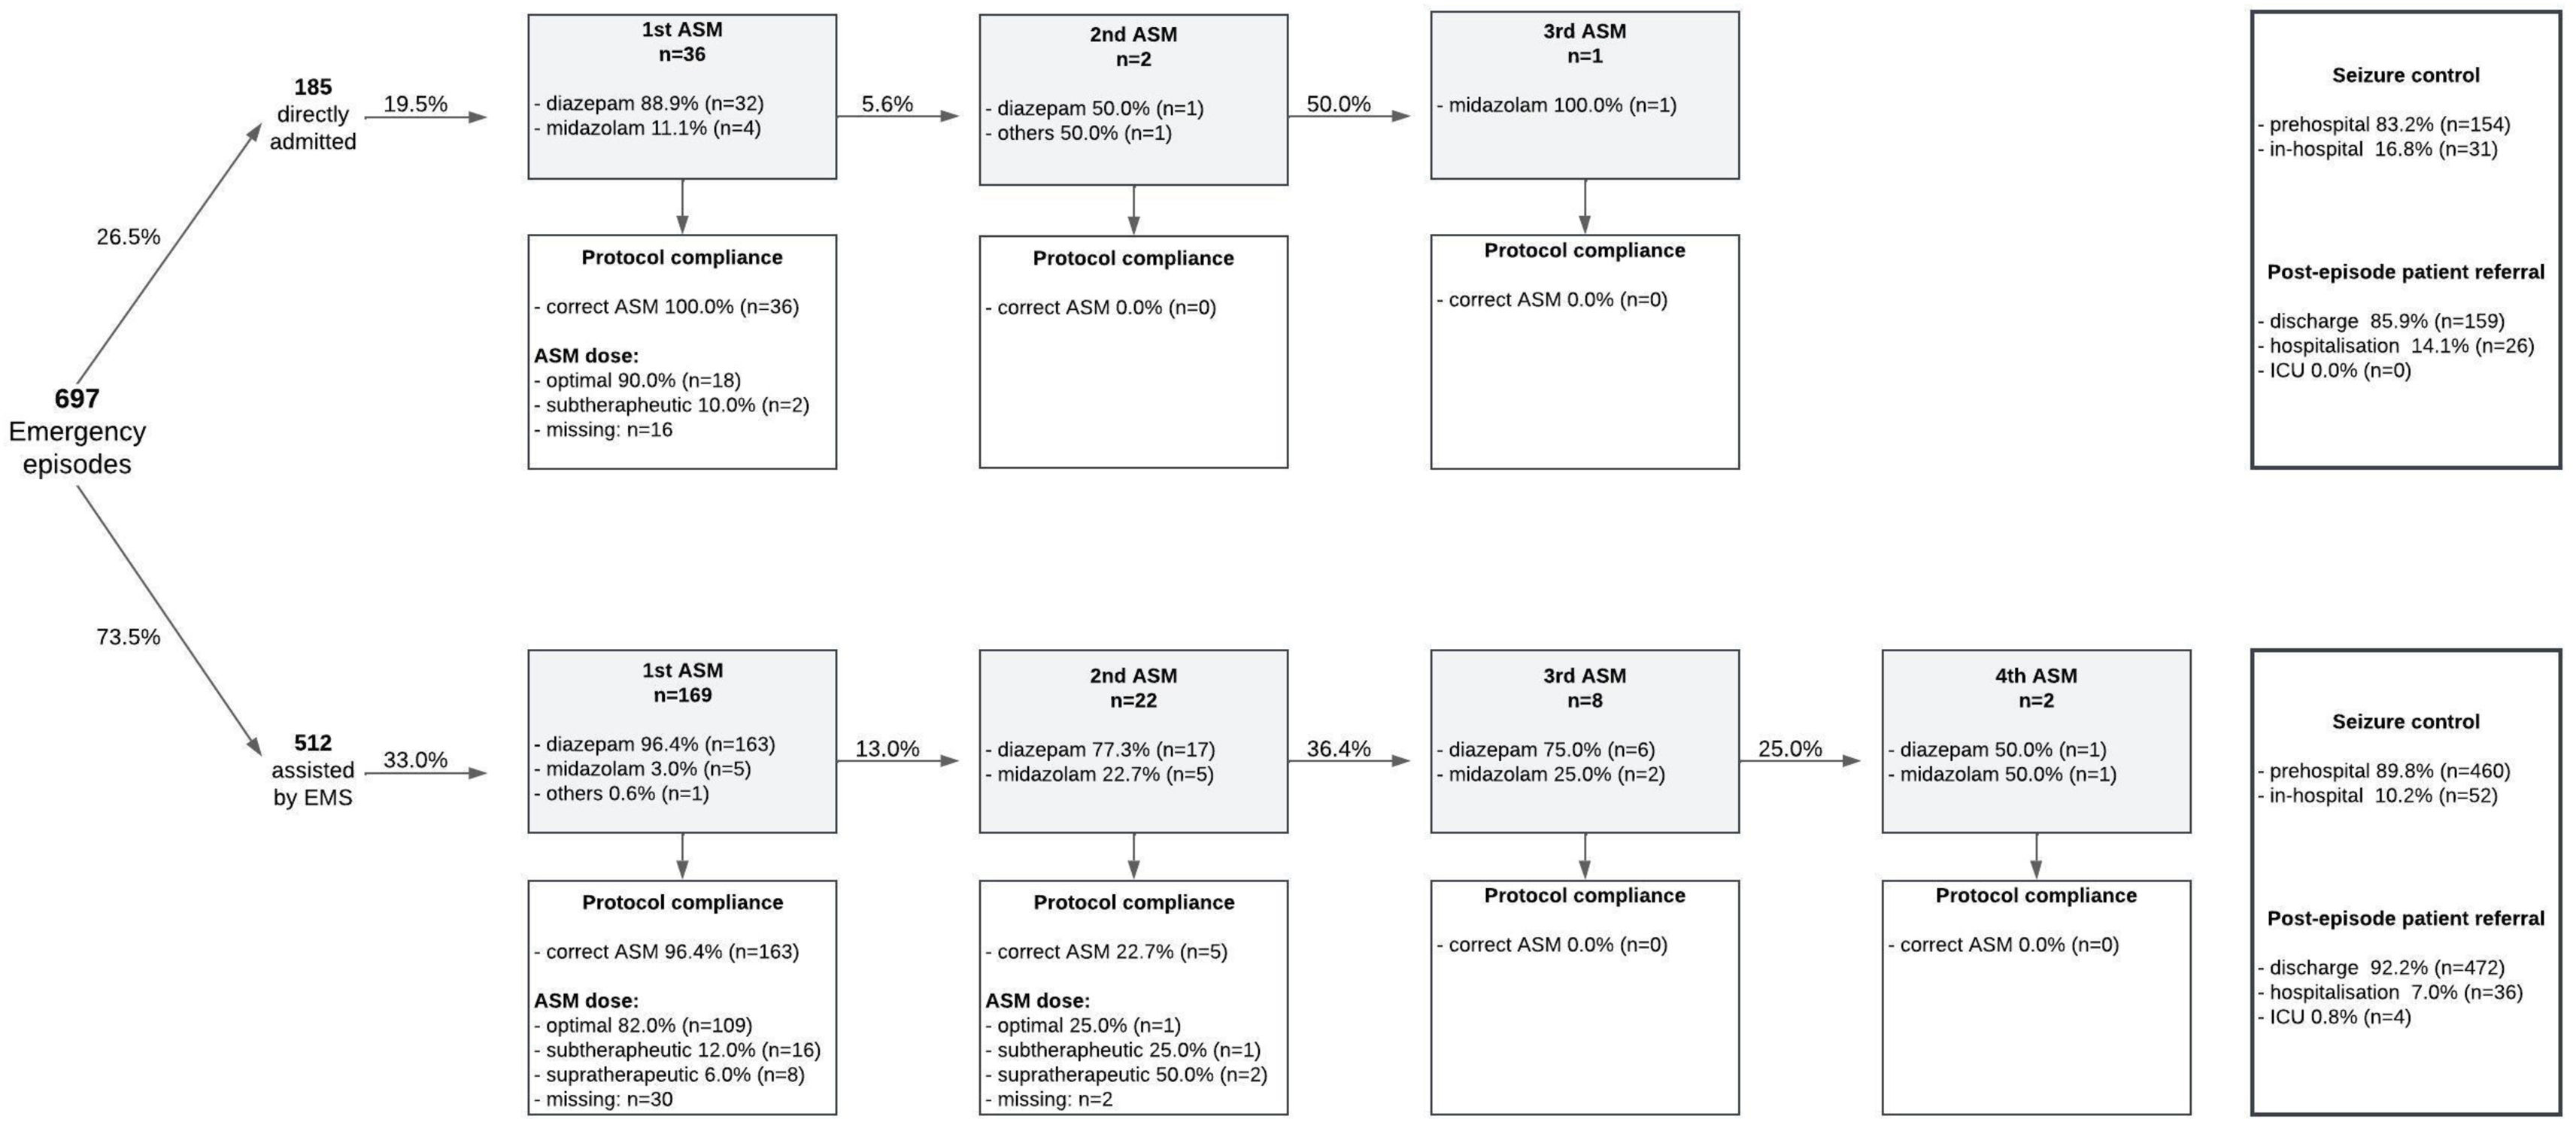
In 73.5% of episodes (n = 512), patients were assisted to the ED by the national emergency medical services (EMS). Within this group, 16.2% (n = 83) received prehospital medical care with subsequent transportation supervised by a medical emergency vehicle. The remaining 83.8% (n = 429) were attended by nurses, emergency medical technicians, or firefighters. In 26.5% of episodes (n = 185), patients were directly admitted to the ED, without prehospital referral (Fig. 1).

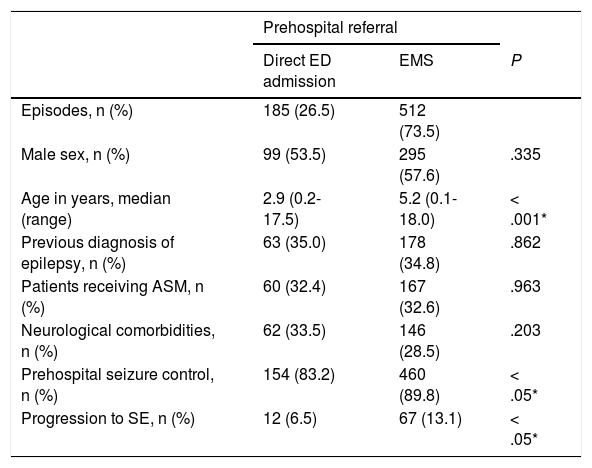
Direct admissions to the ED due to a seizure were more frequent in younger patients (P < .001). Patients with SE were more often attended by the EMS (P < .05). Furthermore, seizure resolution in the prehospital setting was more frequent among patients attended by the EMS (P < .05). No other differences were identified, particularly with regard to history of epilepsy, other neurological comorbidities, or type of seizure (Table 3).
Characterisation of the patients admitted due to seizure according to prehospital referral. Comparative group analysis.
| Prehospital referral | |||
|---|---|---|---|
| Direct ED admission | EMS | P | |
| Episodes, n (%) | 185 (26.5) | 512 (73.5) | |
| Male sex, n (%) | 99 (53.5) | 295 (57.6) | .335 |
| Age in years, median (range) | 2.9 (0.2-17.5) | 5.2 (0.1-18.0) | < .001* |
| Previous diagnosis of epilepsy, n (%) | 63 (35.0) | 178 (34.8) | .862 |
| Patients receiving ASM, n (%) | 60 (32.4) | 167 (32.6) | .963 |
| Neurological comorbidities, n (%) | 62 (33.5) | 146 (28.5) | .203 |
| Prehospital seizure control, n (%) | 154 (83.2) | 460 (89.8) | < .05* |
| Progression to SE, n (%) | 12 (6.5) | 67 (13.1) | < .05* |
ASM: antiseizure medication; SE: status epilepticus.
In the group of the 185 patients without prehospital referral, 13.5% (n = 25) were admitted to the ED without seizure control and did not receive any prehospital ASM. These were mainly patients with a first episode of seizure (n = 16, 64.0%). At least one dose of an ASM was administered in the prehospital setting in 19.5% of episodes (n = 36), most commonly rectal diazepam (88.9%, n = 32). A correct first-line therapy was used in all of these 36 episodes. We were able to analyse the ASM dose in 55.6% of these episodes (n = 20), observing correct doses in 90.0% of cases (n = 18) and subtherapeutic doses in 2 (Fig. 1).
In the group of patients who received EMS care, prehospital seizure resolution was recorded in 89.8% (n = 460). Twenty-nine (5.6%) were admitted to the ED without seizure control and did not receive any prehospital ASM. A first dose of an ASM was given in 33.0% (n = 169), predominantly diazepam (88.7% rectal, 4.7% IV), which was used as the first-line therapy in 96.4% (n = 163). The dose of the first benzodiazepine (BZD) was appropriate in 82.0% of cases (n = 109), subtherapeutic in 12.0% (n = 16), and supratherapeutic in 6.0% (n = 8). We were unable to ascertain the ASM dose in 30 episodes. In 22 episodes, a second drug was administered to control the seizure, mostly diazepam (77.3%), with 31.8% receiving diazepam rectally while 40.9% received it intravenously. Fig. 1 provides information on the use of 3 or 4 drugs.
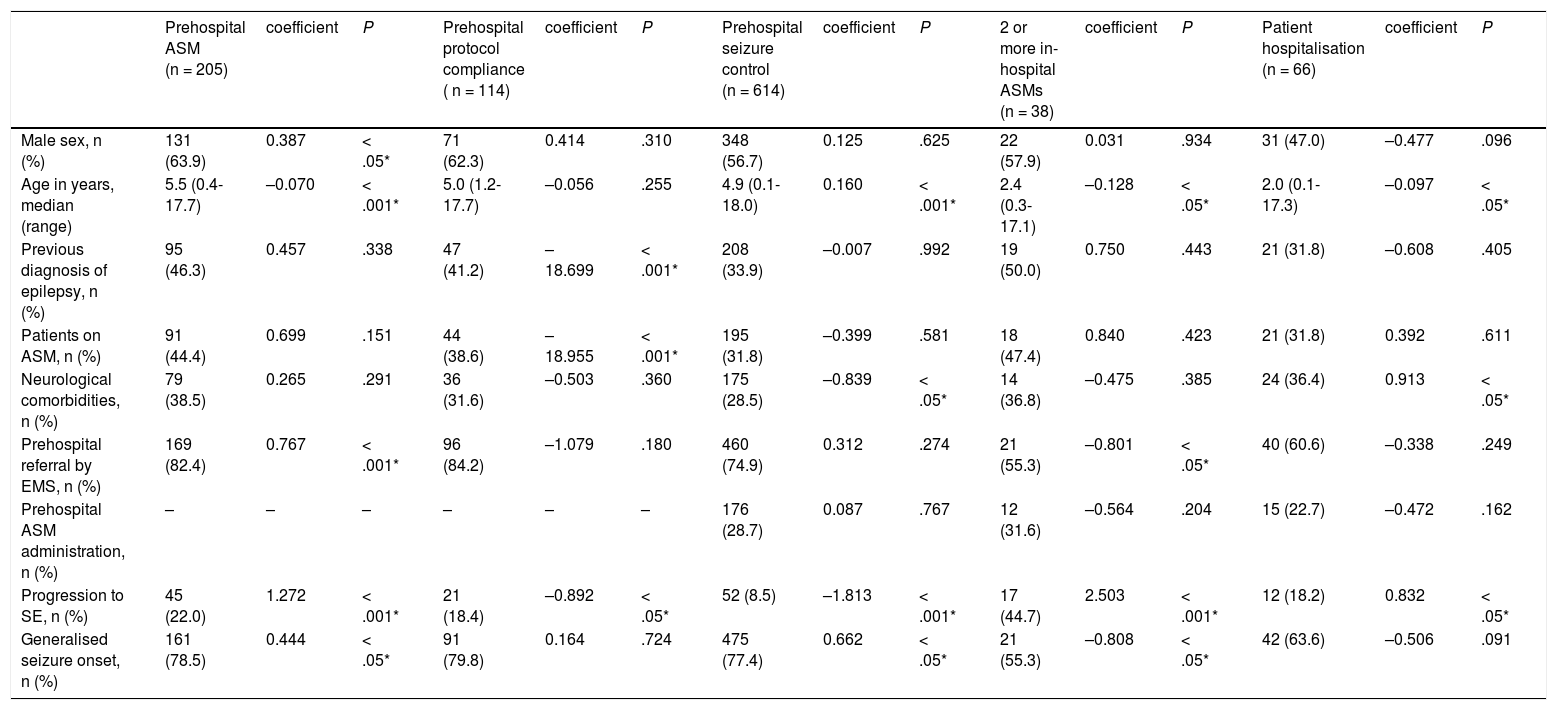
The use of an ASM in the prehospital setting was more frequent in patients with male sex (P < .05), younger age (P < .05), previous diagnosis of epilepsy (P < .001), prior use of ASM at home (P < .001), and previous neurological comorbidities (P < .001). Additionally, it was more frequent among patients attended by the EMS (P < .001) and in those presenting with SE comparing to non-SE episodes (P < .001). In the multivariate analysis, prehospital ASM administration remained independently associated with male sex (P < .05), younger age (P < .001), referral through the EMS (P < .001), and occurrence of SE (P < .001). Patients with generalised seizure onset were more likely to receive an ASM in the prehospital setting (P < .05).
In the prehospital setting, airway support was required in a small percentage of cases. Non-invasive ventilation was used in only one patient, while invasive mechanical ventilation was necessary in 3 episodes (with sedation). Intravenous access was established in 5.7% (n = 29) and IV fluids were administered in 4.6% (n = 24). Among the 322 febrile episodes, an antipyretic drug was administered at the prehospital setting in at least 55.3% of cases (n = 178).
In-hospital managementAt least one ASM was administered in the hospital setting in 11.5% of episodes (n = 80), with the number of drugs administered per patient ranging from one to 6. Of the 151 drug doses administered, 61.5% (n = 93) corresponded to a first-line drug, with the most used ASM being diazepam (58.9%, n = 89). Some 38.4% (n = 58) were second-line drugs, including levetiracetam, valproic acid, phenytoin, phenobarbital, and lacosamide.
Sedation in the hospital setting was performed in 3 episodes. The drugs used for this purpose included midazolam, fentanyl, and propofol. For airway support, non-invasive ventilation was used in 3 episodes and invasive ventilation in 2.
Protocol complianceRegarding protocol compliance, the national guidelines for prehospital management of seizures were completely applied in 71.7% of episodes (n = 114). Failures of the protocol are illustrated on Fig. 1. Greater adherence to treatment guidelines was more frequent in younger patients (P < .05), patients without previous diagnosis of epilepsy (P < .05), without existing ASM treatment (P < .05), without neurological comorbidities (P < .05), and who did not progress to SE (P < .05). However, after the multivariate analysis, only absence of history of epilepsy, lack of previous ASM treatment, and episodes without progression to SE remained significantly associated with greater protocol compliance (P < .001, P < .001, and P < .05, respectively) (Table 4).
Multivariate analysis of factors related to prehospital antiseizure medication administration, prehospital protocol compliance, prehospital seizure control, in-hospital administration of 2 or more antiseizure medications, and patient hospitalisation.
| Prehospital ASM (n = 205) | coefficient | P | Prehospital protocol compliance ( n = 114) | coefficient | P | Prehospital seizure control (n = 614) | coefficient | P | 2 or more in-hospital ASMs (n = 38) | coefficient | P | Patient hospitalisation (n = 66) | coefficient | P | |
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Male sex, n (%) | 131 (63.9) | 0.387 | < .05* | 71 (62.3) | 0.414 | .310 | 348 (56.7) | 0.125 | .625 | 22 (57.9) | 0.031 | .934 | 31 (47.0) | –0.477 | .096 |
| Age in years, median (range) | 5.5 (0.4-17.7) | –0.070 | < .001* | 5.0 (1.2-17.7) | –0.056 | .255 | 4.9 (0.1-18.0) | 0.160 | < .001* | 2.4 (0.3-17.1) | –0.128 | < .05* | 2.0 (0.1-17.3) | –0.097 | < .05* |
| Previous diagnosis of epilepsy, n (%) | 95 (46.3) | 0.457 | .338 | 47 (41.2) | –18.699 | < .001* | 208 (33.9) | –0.007 | .992 | 19 (50.0) | 0.750 | .443 | 21 (31.8) | –0.608 | .405 |
| Patients on ASM, n (%) | 91 (44.4) | 0.699 | .151 | 44 (38.6) | –18.955 | < .001* | 195 (31.8) | –0.399 | .581 | 18 (47.4) | 0.840 | .423 | 21 (31.8) | 0.392 | .611 |
| Neurological comorbidities, n (%) | 79 (38.5) | 0.265 | .291 | 36 (31.6) | –0.503 | .360 | 175 (28.5) | –0.839 | < .05* | 14 (36.8) | –0.475 | .385 | 24 (36.4) | 0.913 | < .05* |
| Prehospital referral by EMS, n (%) | 169 (82.4) | 0.767 | < .001* | 96 (84.2) | –1.079 | .180 | 460 (74.9) | 0.312 | .274 | 21 (55.3) | –0.801 | < .05* | 40 (60.6) | –0.338 | .249 |
| Prehospital ASM administration, n (%) | – | – | – | – | – | – | 176 (28.7) | 0.087 | .767 | 12 (31.6) | –0.564 | .204 | 15 (22.7) | –0.472 | .162 |
| Progression to SE, n (%) | 45 (22.0) | 1.272 | < .001* | 21 (18.4) | –0.892 | < .05* | 52 (8.5) | –1.813 | < .001* | 17 (44.7) | 2.503 | < .001* | 12 (18.2) | 0.832 | < .05* |
| Generalised seizure onset, n (%) | 161 (78.5) | 0.444 | < .05* | 91 (79.8) | 0.164 | .724 | 475 (77.4) | 0.662 | < .05* | 21 (55.3) | –0.808 | < .05* | 42 (63.6) | –0.506 | .091 |
In 46 episodes, protocol compliance could not be assessed due to missing drug dose values.
ASM: antiseizure medication; EMS: emergency medical services; SE: status epilepticus.
Seizure control in the prehospital setting was associated with older age (P < .001), absence of neurological comorbidities (P < .05), generalised seizure onset (P < .05), non-SE presentation (P < .001), and EMS care (P < .05). In the multivariate analysis, the association with EMS care lost statistical significance (Table 4).
During the emergency episode, 38 patients needed 2 or more ASMs to control the seizure; this was associated with younger age (P < .05), history of epilepsy (P < .05), existing ASM treatment at home (P < .05), direct admission to the ED (P < .05), focal-onset seizures (P < .05), and SE presentation (P < .001). After multivariate analysis, the need for 2 or more ASMs to control the seizure at the in-hospital setting was associated with younger age, direct transport to hospital by caregivers, progression to SE, and focal seizures.
Patient hospitalisationHospital admission occurred in 8.9% of patients (n = 62), with 631 being discharged home. Admission to the paediatric ICU occurred in 4 episodes: 2 epileptic seizures, one febrile SE, and one convulsive SE.
Hospitalisation was more probable among younger patients (P < .001), those admitted without prehospital EMS care (P < .05), and those presenting with focal-onset seizures (P < .05). However, after multivariate analysis, the only statistically significant associations were with younger age (P < .05), SE presentation (P < .05), and neurological comorbidities (P < .05) (Table 4).
DiscussionPrehospital managementIn this retrospective study conducted at the multicentre paediatric ED of a tertiary hospital, we were able to characterise the prehospital management of seizures and to explore possible factors associated with better outcomes.
One of the aims of this study was to analyse how paediatric patients with seizures arrive at the ED and whether those who are attended by the EMS behave differently from patients brought there by their caregivers. We observed that most patients received prehospital care from the EMS, with this proportion being slightly lower than that found in similar studies.20,21 The few remaining published studies selected patients who are attended by the EMS.8,21 Patients brought directly to hospital by their caregivers were younger, which we might expect considering that many of them presented first-time febrile seizures and the caregivers might not have been aware of how to proceed. This finding reinforces the need to educate parents and education professionals on how to proceed in the event of a seizure, with or without fever, namely to follow safety precautions and to contact the EMS. Furthermore, it should be noted that patients with SE were more often attended by EMS; this is consistent with the findings of previous research.22
In this study, most of the seizures ceased in the prehospital setting without the need for an ASM, in accordance with the literature.8 Of the one-third that received at least one ASM dose, a BZD represented the vast majority of first-line drugs chosen, in accordance with the first-line therapy recommended by the national management protocol.14 In almost 80% of cases, this corresponded to rectal diazepam, while midazolam was chosen in a small proportion of cases. In fact, at the time of this study, rectal diazepam was the prescribed drug for the management of acute seizure episodes in patients with seizures in Portugal. Buccal midazolam was also recently made available for home prescription.
In a limited number of episodes, BZD were repeatedly administered without IV access, although these represent an insignificant number of episodes. This prehospital management pattern is similar to those reported in other studies.23,24 Amengual-Gual et al.,16 in a retrospective study on paediatric SE management by EMS, reported the use of more than 2 BZDs in one-fifth of patients, without escalating to non-BZD (second line) drugs; this was a widespread issue.
Prehospital protocol compliance, including the appropriate therapeutic regimen at the optimal dose, was recorded in more than half of cases. However, of the 240 cases of ASM administration, more than 10% were at subtherapeutic doses and 4% were at supratherapeutic doses. Among the episodes where more than 2 ASMs were administered, the proportion of non-optimal doses was higher, suggesting that this factor may impact seizure control. Ramgopal and Martin-Gill,21 in a retrospective study of prehospital seizure management, reported that insufficient doses of BZD were administered in 43% of children with seizures; this was associated with an increased need for additional ASM doses and a higher risk of airway interventions.21 Inappropriate management results in prolonged seizure episodes, leading to progressive tolerance to BZD and worse outcomes.12 As the seizure persists, the postsynaptic membrane availability for chemical receptors changes, resulting in the internalisation of GABA receptors and gradual resistance to this class of drugs.6,14 Therefore, repeated doses of BZDs offer limited effectiveness, and the pharmacological management of acute seizure episodes should follow the current recommendations.10 Despite the high compliance rate observed, the significant number of non-optimally dosed ASMs administered and incorrect drug sequence constitutes an opportunity to review and potentially improve dosing practices or protocols.
Clinical courseAlmost 90% of episodes were controlled before hospital arrival. In two-thirds of the episodes where patients arrived at the hospital in active seizure, no prehospital ASM was administered; this was primarily observed in the group without prehospital referral by the EMS.
When comparing febrile and epileptic seizures, prehospital resolution was more common in the former, which is as we would expect, given their benign nature. Febrile seizures are typically self-limited and often resolve before the patient arrives at the hospital.25 However, in episodes of SE, the opposite trend is observed, with prehospital resolution being more frequent in convulsive SE. Data on the time until seizure control were not available, limiting the interpretation of the results regarding seizure resolution. Further research should consider this key factor.
Prehospital seizure control, the need for 2 or more in-hospital ASMs, and hospitalisation were more frequent in younger patients, those without prehospital referral by the EMS, and in focal-onset seizures. This aligns with previous reports. Seizures with focal onset are more difficult to recognise, delaying treatment initiation and worsening patients’ outcomes.26 Moreover, previous studies indicate that patient age is a major determinant of long-term prognosis, with the youngest (mainly those younger than one year) having poorer outcomes and higher mortality rates.7 The better outcomes in patients with prehospital care emphasises the significant role of the EMS in patient management. Moreover, the higher likelihood of receiving 2 or more in-hospital ASMs in patients with a previous diagnosis of epilepsy or those previously receiving an ASM may be attributed to the greater complexity of these patients.
Strengths and limitationsThis is a retrospective study based on data collected from electronic records, with the limitations inherent to this method. Missing information in many patients receiving prehospital care from the EMS, including the exact seizure duration and a detailed account of the supportive care administered (such as airway support and intravenous access), hindered deeper analysis of prehospital determinants of patient outcomes. Data on treatment timings, a well-known key factor for the successful management of seizures, were not analysed. This may constitute a confounding factor in the identified associations. Data on response timings and seizure aetiology were also unavailable. Additionally, only patients admitted to the ED were enrolled, whereas convulsive SE episodes with in-hospital onset or patients transferred from other units and directly admitted to the ICU were not included. Furthermore, patients managed exclusively in the prehospital setting without subsequent ED admission were also excluded from our study population. Therefore, the study population may not be fully representative of all children with seizures.
Nevertheless, a high number of episodes were included, with a large dataset, enhancing the precision of estimates and allowing for more detailed subgroup analysis, with greater generalisability of the results. The study was conducted in a multicentre ED of a tertiary hospital, admitting paediatric patients from the referral areas of 3 hospitals, and is therefore highly representative of the national situation. This is a unique study, one of the few in the paediatric field to focus on prehospital management, including patients without prehospital care, which allows analysis of management by patients’ caregivers. Several studies have focused on the management of SE, whereas this one also includes non-SE episodes. The current study provides valuable insights on the current state of prehospital seizure management.
This preliminary study underscores the need for further research, which should be conducted through prospective studies in cooperation with the EMS. Future studies should address the impact of additional variables on prehospital care, including the timings of prehospital intervention and treatment, the correlation of prehospital management with the exact seizure duration, and the influence of aetiology on patient outcomes. The underlying factors promoting these associations warrant deeper investigation in additional studies.
ConclusionClinical outcomes of prehospital management may be improved with a joint effort from caregivers, EMS professionals, and clinicians. Health education for acute seizure management among families and emergency professionals, self-management plans, inclusion and training for second-line therapy administration by first responders, and raising awareness of the complications of inappropriate management are simple measures that may improve disease prognosis.
The prehospital management of seizures in paediatric patients remains a significant determinant in patient prognosis and should be subject to continuous optimisation. Improving first responders’ awareness to ensure early, appropriate management constitutes an essential strategy in this process. Further investigation is needed to identify possible barriers in prehospital care.
FundingThis research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors.
None.


