


Amyotrophic lateral sclerosis (ALS) is a disease with a fatal course, often associated with unassessed cognitive-behavioural disturbances, and very relevant end-of-life care decisions. The aim of this study is to verify whether multidisciplinary team care for ALS patients in our setting has modified the cognitive assessment and the end-of-life decision making, compared to a model of uncoordinated specialist care.
MethodsAn observational, longitudinal, retrospective study was conducted on a cohort of patients with probable or definite ALS, in a referral hospital, between 1 January 2000 and 31 December 2022, differentiating whether they were treated before or after the implementation of a multidisciplinary model. We analysed the performance of cognitive assessment, the use of riluzole, gastrostomy, non-invasive ventilation and invasive ventilation, and the recording of patients’ decisions regarding the care they wished to receive. Comparisons between variables were performed using the chi-square test or Fisher exact test.
ResultsWe evaluated 47 patients seen by uncoordinated specialists and 146 with a multidisciplinary model. Patients cared for using the multidisciplinary model were more frequently cognitively assessed (55.48% vs 12.8%, P < .001), diagnosed with dementia (11.6% vs 2.3%, P < .048), and had their advance directives recorded (56.8% vs 23.4%, P < .001). We found no differences in the use of advanced interventions, except for invasive ventilation, which was only performed in the context of multidisciplinary care.
ConclusionsThe multidisciplinary model of care for ALS patients in our setting has improved cognitive assessment, promoted the registration of their advance directives, and thus helped to improve respect for their autonomous decisions and dignity.
La esclerosis lateral amiotrófica (ELA) es una enfermedad que asocia frecuentemente alteraciones cognitivo-conductuales, frecuentemente no evaluadas, y decisiones muy relevantes sobre los cuidados al final de la vida. Nuestro objetivo es comprobar si la atención por un equipo multidisciplinar a pacientes con ELA en nuestro medio ha mejorado la valoración cognitiva realizada y la toma de decisiones al final de la vida.
MetodologíaEstudio observacional, longitudinal, retrospectivo, de una cohorte de pacientes con ELA probable o definitiva, en un hospital de referencia, entre 01-01-2000 y 31-12-2022, diferenciando que fueran atendidos antes o después de la implementación de un modelo multidisciplinar (MM). Se analizó la realización de una valoración cognitiva, uso de riluzol, gastrostomía, ventilación no invasiva o invasiva, y el registro de las decisiones de los pacientes respecto a sus cuidado. Las variables se compararon mediante el test de chi-cuadrado o la prueba exacta de Fisher.
ResultadosEvaluamos 47 pacientes atendidos por especialistas no coordinados y 146 con un MM. Los paciente atendidos mediante el MM fueron más frecuentemente valorados cognitivamente (55.48% vs 12.8%, P < .001), diagnosticados de demencia (11.6% vs 2.3%, P < .048) y registradas sus voluntades anticipadas (56.8% vs 23.4%, P < .001). No encontramos diferencias en el uso de intervenciones avanzadas, salvo para la ventilación invasiva, que sólo se realizó en el contexto multidisciplinar.
ConclusionesEl modelo multidisciplinar de atención a pacientes con ELA en nuestro medio ha mejorado la valoración de aspectos cognitivos, ha favorecido el registro de sus voluntades anticipadas y así ha promovido el respeto a sus decisiones autónomas.
Amyotrophic lateral sclerosis (ALS) is a neurodegenerative motor neuron disease with an invariably fatal outcome, typically within a period of 5 years.1 Although the disease is characterised by motor involvement, 35%-50% of patients also present cognitive and/or behavioural alterations, with 10%-15% progressing to frontotemporal dementia.1–5
As a result of the growing disability and dependence associated with the disease, patients with ALS require highly complex care. Currently, the majority of centres have implemented multidisciplinary care teams for the management of the disease; this approach has been shown to improve patient quality of life and survival.3–6 Management focuses on symptomatic treatment and the implementation of support measures in response to the patient’s real wishes and values; this involves highly significant decisions about care over the disease course and at the end of life.2–6
In this context, we must prioritise preserving patients’ dignity and safeguarding their fundamental right to autonomy.2 Therefore, it is necessary to detect and assess cognitive alterations from the time of disease onset: lack of recognition of these alterations represents an obstacle to the real exercise of this fundamental right.2
The domains that must be assessed in cognitive impairment screening studies include executive function, language, visuospatial skills, and emotional function.7–11 Over the course of the disease, patients present considerable limitations to motor and verbal capacity, which represent a barrier to correct assessment of cognitive status. They may even cause a patient with intact cognitive function to score low on screening tests, leading us to think that their decision-making capacity is limited and depriving them of recognition of their autonomy.
This review aims to establish whether multidisciplinary ALS care in our setting is guaranteeing correct cognitive assessment over the course of the disease, promoting reliable recording of patients’ wishes and thus promoting the exercise of their right to autonomy and safeguarding their dignity. A literature search identified few studies contributing data on cognitive/behavioural assessment of patients with ALS in our setting.12–17 Few analytical studies have confirmed the benefits of multidisciplinary care for these patients, particularly in relation to the early implementation of non-invasive ventilation (NIV) and gastrostomy17–21; no study analysed the specific effects in safeguarding patient autonomy.
Material and methodsWe conducted a descriptive, analytical, observational, longitudinal, retrospective study of all patients diagnosed with ALS from 1 January 2000 to 31 December 2022 at the neurology department of Hospital Universitario Virgen de la Victoria (HUVV), in Malaga. A database was created on 1 January 2000 to record the care provided to patients with ALS, with prospective collection of the main clinical and care-related variables. On 14 October 2011, a multidisciplinary ALS care team was created, which developed protocols for joint and specialised care provision and for access to this care in patients with suspected ALS, as well as the pathway for admission of these patients into the healthcare system.
Inclusion and exclusion criteriaThe inclusion criterion was diagnosis of definite or probable ALS according to the El Escorial criteria, established during the study period. Patients diagnosed with possible ALS were excluded.
The total cohort was divided into 2 groups:
- •
Patients receiving non-coordinated care from the neurology department and other specialties, from 1 January 2000 to 13 October 2011.
- •
Patients who were only attended by the multidisciplinary ALS care team, from 14 October 2011 to 31 December 2022.
Data were gathered from the ALS database of the HUVV neurology department; patients’ medical records, accessed through the Andalusian Healthcare Service’s DIRAYA program to follow up patients receiving specialised care; and the unique healthcare user record, which includes data on primary care and emergency consultations. We analysed the following demographic and clinical variables: vital status, sex, age at diagnosis, form of onset, presence of cognitive/behavioural disorders, clinical and test-based cognitive/behavioural assessment, treatment with riluzole, gastrostomy performance, and use of invasive or non-invasive ventilatory support. We investigated whether patients had completed an advance directives document and/or whether their clinical records included their decisions related to care during the disease course and at the end of life.
Statistical analysisInformation was anonymised and exported to a spreadsheet (Excel 2023, version 16.73; Microsoft Corporation). Data were analysed with the IBM SPSS Statistics software, version 29.
The descriptive analysis is presented in tables summarising the study variables in each of the 2 groups.
Categorical variables are expressed as absolute frequencies and percentages. Results for the variable age at diagnosis are expressed with measures of central tendency (mean and median) and dispersion (standard deviation). Percentages were compared using the chi-square test or Fisher exact test, as appropriate.
Ethics approvalThe study was approved by the Research Ethics Committee of the Province of Malaga. The study complied with the principles of the Declaration of Helsinki and normalised working procedures ensuring compliance with the norms of good clinical practice, as described in the ICH Harmonised Tripartite Guideline for Good Clinical Practice (CPMP/ICH/135/95).
The informed consent of patients or their legal representatives was sought wherever possible, although the majority were deceased by the time the study was performed.
ResultsThe study cohort included a total of 197 patients diagnosed with definite or probable ALS. The first group (2000-2011) included 47 patients, and the second (2011-2022) included 150, although 6 were lost to follow-up (2 are listed as deceased in the database of the Andalusian Healthcare System and vital status was unknown for 4; these patients were excluded from the analysis).
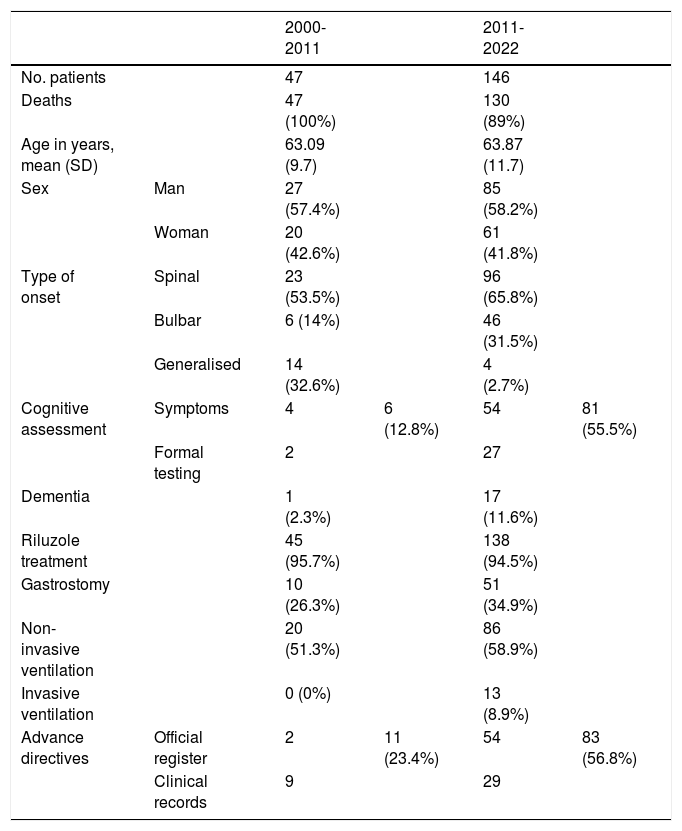
The demographic and clinical data from both groups are shown in Table 1.
Clinical and demographic characteristics.
| 2000-2011 | 2011-2022 | ||||
|---|---|---|---|---|---|
| No. patients | 47 | 146 | |||
| Deaths | 47 (100%) | 130 (89%) | |||
| Age in years, mean (SD) | 63.09 (9.7) | 63.87 (11.7) | |||
| Sex | Man | 27 (57.4%) | 85 (58.2%) | ||
| Woman | 20 (42.6%) | 61 (41.8%) | |||
| Type of onset | Spinal | 23 (53.5%) | 96 (65.8%) | ||
| Bulbar | 6 (14%) | 46 (31.5%) | |||
| Generalised | 14 (32.6%) | 4 (2.7%) | |||
| Cognitive assessment | Symptoms | 4 | 6 (12.8%) | 54 | 81 (55.5%) |
| Formal testing | 2 | 27 | |||
| Dementia | 1 (2.3%) | 17 (11.6%) | |||
| Riluzole treatment | 45 (95.7%) | 138 (94.5%) | |||
| Gastrostomy | 10 (26.3%) | 51 (34.9%) | |||
| Non-invasive ventilation | 20 (51.3%) | 86 (58.9%) | |||
| Invasive ventilation | 0 (0%) | 13 (8.9%) | |||
| Advance directives | Official register | 2 | 11 (23.4%) | 54 | 83 (56.8%) |
| Clinical records | 9 | 29 |
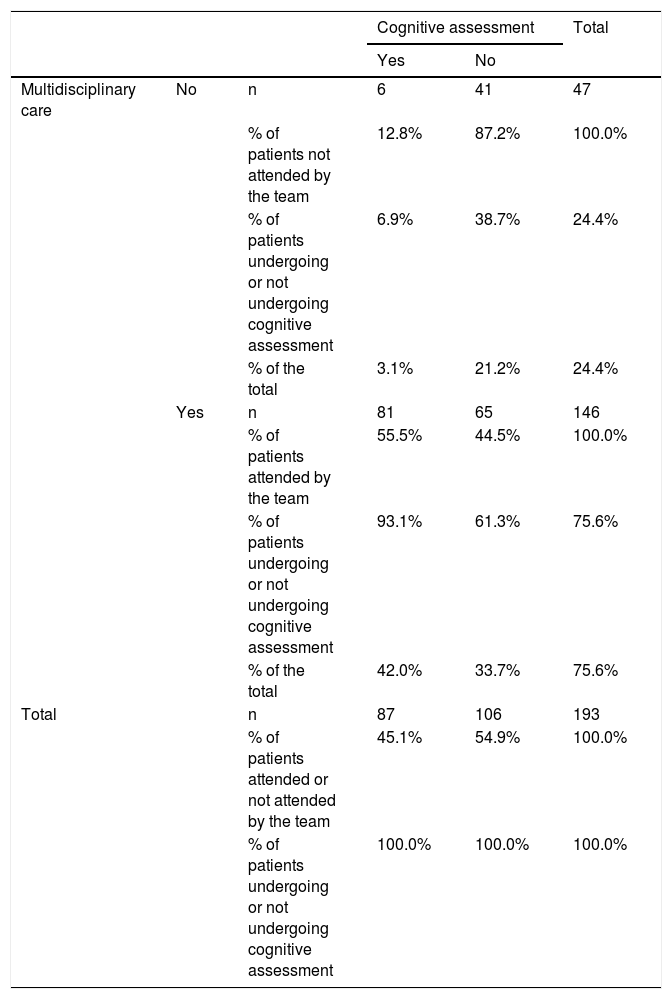
We analysed whether there was an association between the performance of any kind of cognitive/behavioural assessment (clinical or with formal testing) and the provision of care by the multidisciplinary team, finding a highly significant association between this care model and cognitive/behavioural assessment (P < .001) (Table 2).
Cognitive assessment of patients under each care model.
| Cognitive assessment | Total | ||||
|---|---|---|---|---|---|
| Yes | No | ||||
| Multidisciplinary care | No | n | 6 | 41 | 47 |
| % of patients not attended by the team | 12.8% | 87.2% | 100.0% | ||
| % of patients undergoing or not undergoing cognitive assessment | 6.9% | 38.7% | 24.4% | ||
| % of the total | 3.1% | 21.2% | 24.4% | ||
| Yes | n | 81 | 65 | 146 | |
| % of patients attended by the team | 55.5% | 44.5% | 100.0% | ||
| % of patients undergoing or not undergoing cognitive assessment | 93.1% | 61.3% | 75.6% | ||
| % of the total | 42.0% | 33.7% | 75.6% | ||
| Total | n | 87 | 106 | 193 | |
| % of patients attended or not attended by the team | 45.1% | 54.9% | 100.0% | ||
| % of patients undergoing or not undergoing cognitive assessment | 100.0% | 100.0% | 100.0% | ||
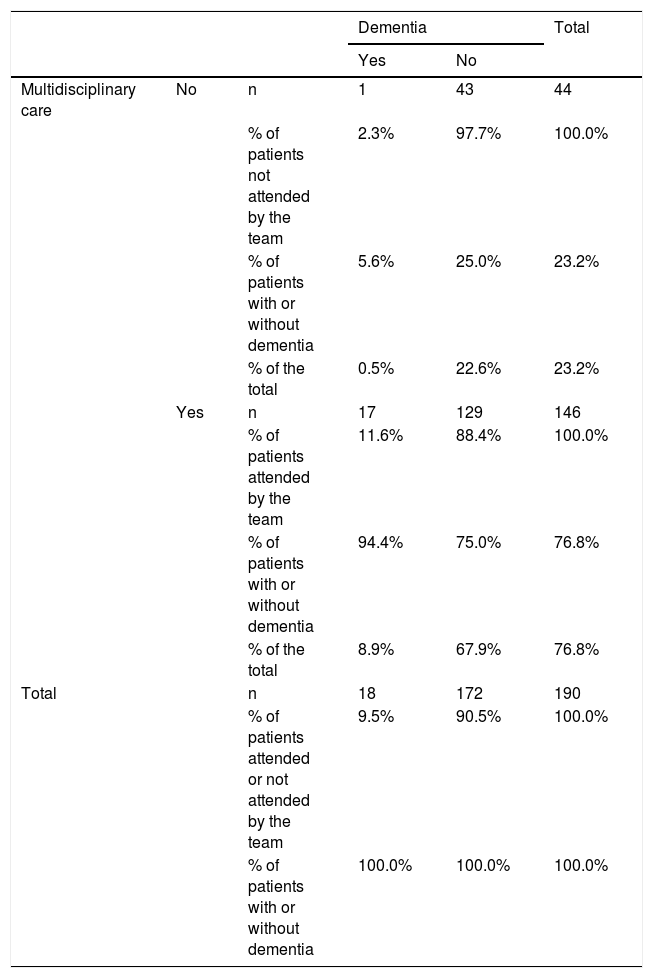
Diagnosis of dementia also showed a significant association with multidisciplinary assessment in our population of patients with ALS (P < .048) (Table 3).
Dementia diagnoses under each care model.
| Dementia | Total | ||||
|---|---|---|---|---|---|
| Yes | No | ||||
| Multidisciplinary care | No | n | 1 | 43 | 44 |
| % of patients not attended by the team | 2.3% | 97.7% | 100.0% | ||
| % of patients with or without dementia | 5.6% | 25.0% | 23.2% | ||
| % of the total | 0.5% | 22.6% | 23.2% | ||
| Yes | n | 17 | 129 | 146 | |
| % of patients attended by the team | 11.6% | 88.4% | 100.0% | ||
| % of patients with or without dementia | 94.4% | 75.0% | 76.8% | ||
| % of the total | 8.9% | 67.9% | 76.8% | ||
| Total | n | 18 | 172 | 190 | |
| % of patients attended or not attended by the team | 9.5% | 90.5% | 100.0% | ||
| % of patients with or without dementia | 100.0% | 100.0% | 100.0% | ||
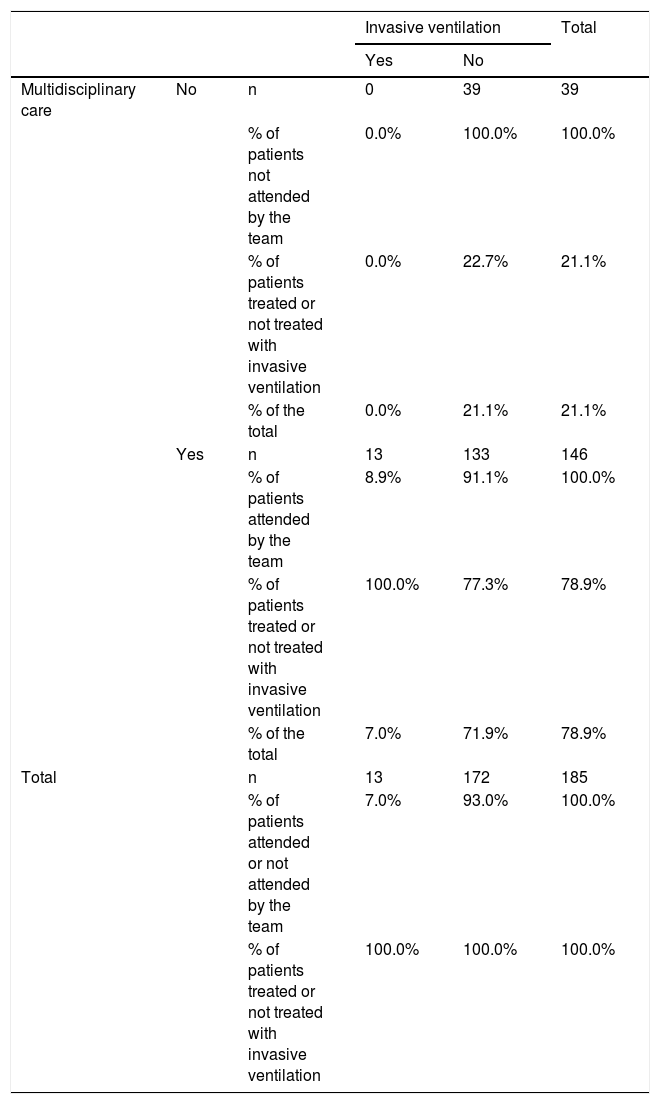
No association was found between riluzole treatment and care model. The performance of gastrostomy or NIV also showed no association with either care model. However, the analysis did identify a statistically significant difference between care models in the use of invasive ventilatory support (P < .041) (Table 4).
Use of invasive ventilation under each care model.
| Invasive ventilation | Total | ||||
|---|---|---|---|---|---|
| Yes | No | ||||
| Multidisciplinary care | No | n | 0 | 39 | 39 |
| % of patients not attended by the team | 0.0% | 100.0% | 100.0% | ||
| % of patients treated or not treated with invasive ventilation | 0.0% | 22.7% | 21.1% | ||
| % of the total | 0.0% | 21.1% | 21.1% | ||
| Yes | n | 13 | 133 | 146 | |
| % of patients attended by the team | 8.9% | 91.1% | 100.0% | ||
| % of patients treated or not treated with invasive ventilation | 100.0% | 77.3% | 78.9% | ||
| % of the total | 7.0% | 71.9% | 78.9% | ||
| Total | n | 13 | 172 | 185 | |
| % of patients attended or not attended by the team | 7.0% | 93.0% | 100.0% | ||
| % of patients treated or not treated with invasive ventilation | 100.0% | 100.0% | 100.0% | ||
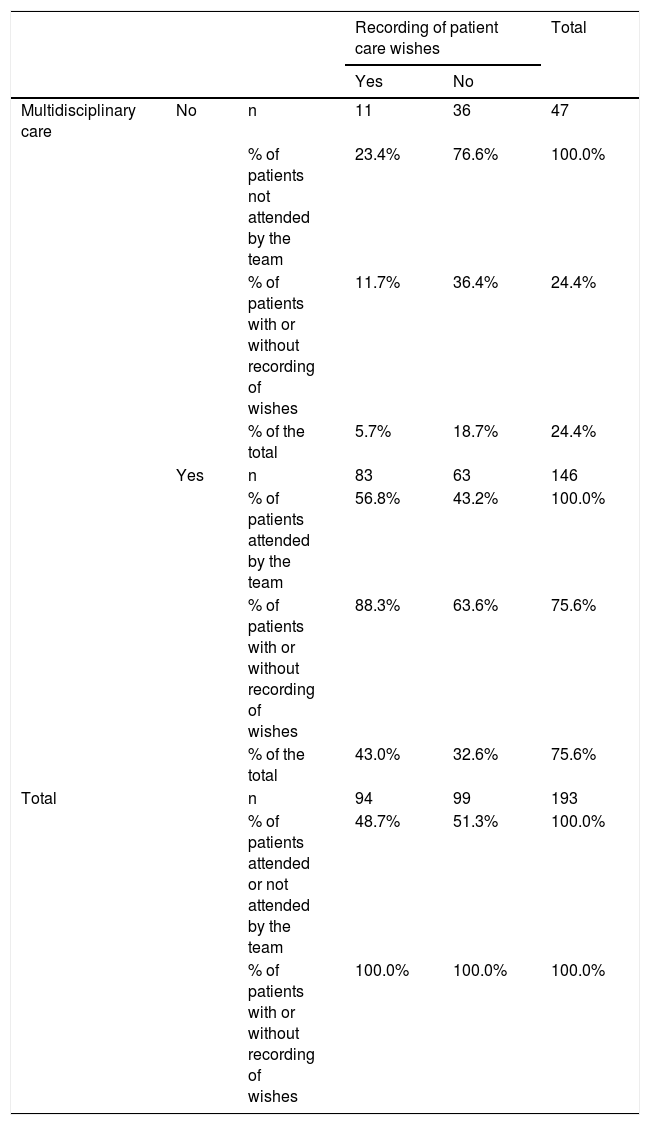
We also observed a significant association between the care model and whether patients’ instructions about the healthcare they wished to receive had been recorded, either in their clinical records or in an advance directives document (P < .001) (Table 5). During the study period, euthanasia was requested and performed in one case.
Recording of advance directives under each care model.
| Recording of patient care wishes | Total | ||||
|---|---|---|---|---|---|
| Yes | No | ||||
| Multidisciplinary care | No | n | 11 | 36 | 47 |
| % of patients not attended by the team | 23.4% | 76.6% | 100.0% | ||
| % of patients with or without recording of wishes | 11.7% | 36.4% | 24.4% | ||
| % of the total | 5.7% | 18.7% | 24.4% | ||
| Yes | n | 83 | 63 | 146 | |
| % of patients attended by the team | 56.8% | 43.2% | 100.0% | ||
| % of patients with or without recording of wishes | 88.3% | 63.6% | 75.6% | ||
| % of the total | 43.0% | 32.6% | 75.6% | ||
| Total | n | 94 | 99 | 193 | |
| % of patients attended or not attended by the team | 48.7% | 51.3% | 100.0% | ||
| % of patients with or without recording of wishes | 100.0% | 100.0% | 100.0% | ||
It is noteworthy that the number of patients diagnosed with ALS was much greater in 2011-2022 (146 cases) than in 2000-2011 (47 cases).
Although this study does not aim to analyse trends in incidence and prevalence, we consider it relevant to reflect briefly on this observation, as it is probably related to the model of care provision. No reliable statistics are available on the incidence or prevalence of ALS in our setting. However, given the uniform geographical distribution of ALS, we may refer to studies on the trends in its prevalence and incidence in other regions of Spain. A study performed in Catalonia reported an incidence rate of 1.4 cases/100 000 person-years, with prevalence of 5.4 cases/100 000 population in the period 1999-2001,22 similar to the rate reported in another study conducted in Catalonia and Valencia in the period 2011-2019, reporting an incidence of 1.35-1.7 cases/100 000 person-years and prevalence of 3.2-5.1 cases/100 000 population.23 Given the lack of significant change in ALS incidence in these regions, there is no reason to think that such a change has occurred in our area.
The lower number of patients attended in 2000-2011 may be due to barriers to access to specialised care, or to problems with diagnosis or recording of information. The neurology department at HUVV has increased its capacity to meet the care needs of the population, with a greater number of neurologists, greater specialisation of care, and improvements in case recording and follow-up. The creation of the multidisciplinary ALS care team in 2011 enabled the implementation of protocols for suspected ALS, streamlining the diagnostic process; as a result, patients would undergo appropriate assessment earlier and with greater effectiveness.
This hypothesis is supported by the high percentage of patients diagnosed with generalised-onset ALS (32.6%) in the period 2000-2011. The percentage of generalised forms observed in 2011-2022 is more in line with international data. This may be because patients attended in the first period were assessed by neurologists at more advanced stages of disease progression, as a result of delays in accessing specialised care; thus, the disease was less likely to be characterised and attended by non-specialist neurologists.
Cognitive/behavioural assessment and diagnosis of dementiaBefore the creation of the multidisciplinary ALS team, only one case of dementia was recorded. This may be attributed to the fact that neurologists were less aware of aspects unrelated to the strict motor alteration. After implementation of multidisciplinary assessment, the percentage of patients diagnosed with dementia associated with ALS increased to 11.6%, closer to the rates reported in the majority of series1–5; however, only 2 cases were expressly characterised as frontotemporal dementia. Dementia was not classified according to the different forms of cognitive and/or behavioural involvement.
We also observed a considerable increase in the percentage of patients undergoing cognitive/behavioural assessment at some point over the disease course (55.48%). This suggests greater understanding and concern about the need to attend this fundamental aspect of the quality of life, survival, and autonomy of patients with ALS. However, this percentage remains far lower than we would desire. On the majority of occasions, this assessment was purely clinical, with the attending neurologist considering the patient’s symptoms. Occasionally, neuropsychological tests were used, nearly always the Short Portable Mental Status Questionnaire. This screening test was typically administered by nursing staff, and mainly explores short- and long-term memory, orientation, and calculation; therefore, it is not appropriate for assessing possible frontotemporal dementia, as alterations are only detected in advanced stages, due to the more generalised involvement. Only the 2 patients diagnosed specifically with ALS-frontotemporal dementia underwent more structured evaluation, probably because the disease presented symptoms of frontotemporal dementia at onset, which were very disruptive. As part of the multidisciplinary ALS team, a psychologist has always been responsible for assessing adaptive and anxiety/depressive disorders, but not for neuropsychological assessment.
Other Spanish studies also report a lack of systematic assessment of cognitive/behavioural alterations.14,15,21 The only Spanish study reporting systematic cognitive assessment of these patients identified cognitive impairment in 35.71%.17 The authors do not distinguish between different diagnoses on the spectrum of cognitive/behavioural disorders. The only test used for this assessment was the Mini-Examen Cognoscitivo, which is more appropriate for diagnosing cognitive impairment with predominance of memory alterations. Recent studies conducted in Catalonia, which researched correlations between cognitive/behavioural problems and neuropathological changes14,15 or between clinical characteristics and prognosis,16 report that in a considerable percentage of cases, diagnosis of dementia or cognitive impairment was established according to the global impression of the neurologist; patients assessed in the more recent period underwent formal neuropsychological assessment, although the tests used are not reported.
Implementation of advanced interventionsIn our study, a very high percentage of patients received riluzole in both periods. This demonstrates the awareness among neurologists in our setting, since the regulatory approval of riluzole, of the drug’s potential to improve patient survival.
We did not find statistically significant differences in the percentage of gastrostomies performed, although the figure was higher among patients treated by the multidisciplinary team (26.3% vs 34.9%). In a study performed at Hospital de Bellvitge, gastrostomies were only performed in 3.7% of patients attended by a general neurologist, versus 32.3% of patients attended by a multidisciplinary team.21 This is similar to the 30.95% reported at a hospital in Madrid, compared to 8.6% in the period prior to the implementation of multidisciplinary care.17 The lack of differences in the percentage of gastrostomies performed at our hospital may be due to several factors. Firstly, our data probably present a bias due to the loss of information from the period 2000-2011, as 9 patients (19.1%) were excluded from the analysis due to the lack of definitive information about whether they underwent this operation. Secondly, the main consultant for ALS care in the period 2000-2011 was a neurologist specialising in neuromuscular disorders, who advised the general neurologists; this may have contributed to better referral of these patients to other specialties.
Analysis of the implementation of NIV reveals similar findings. We did not find statistically significant differences in the percentage of patients receiving NIV, although the rate was higher among patients treated by the multidisciplinary team. In the aforementioned study conducted at Hospital de Bellvitge, a significant difference was observed in the percentage of patients receiving NIV before and after the implementation of multidisciplinary care (29.6% vs 48.8%).21 The study conducted in Madrid reported rates of 11.5% and 54.76%, respectively.17 In both cases, the results reported are very similar to our own. This lack of significant differences in our study is probably due to similar reasons to those mentioned above with regard to gastrostomy: exclusion from the analysis of patients without conclusive documentation of NIV treatment (17%), and appropriate referrals by the neuromuscular diseases specialist in the first period.
No patient received invasive ventilatory support in the first period. In the second period, 8.9% of patients received this intervention. This demonstrates how the provision of such highly complex care requires a coordinated team. The use of invasive mechanical ventilation varies greatly between countries. For instance, it is practically never indicated in the United Kingdom, whereas it is prescribed to 2%-5% of patients in France and 27%-45% in Japan.24 We found no data on the use of this intervention in Spain.
Recording of advance directivesRegarding the use of patients’ clinical records or the official register of advance directives to record their preferences about care over the course of the disease and at the end of life, this information was recorded for 23.4% of patients attended in the first period and 56.8% of those attended by the multidisciplinary care team.
It was not possible to officially record advance directives until the implementation of the advance directives register contemplated in the 2002 law on patient autonomy.25 In Andalusia, this practice was implemented by virtue of Law 5/2003, of 9 October, on the declaration of advance directives.26 However, the obligation to record patients’ care wishes in their clinical records had already been recognised. The 1981 Statute of Autonomy27 establishes the right of patients to declare their advance directives. It was subsequently developed in Law 2/1998, on Healthcare in Andalusia.28 Although advance directives were only recorded for 23.4% of patients in the period 2000-2011, we understand that patients were consulted throughout the care process to establish their wishes about the interventions to be performed. However, recording these wishes in the patient’s clinical records is an obligation of healthcare professionals, as the only effective way of ensuring that the other professionals attending a patient are made aware of and act in accordance with their wishes. This is particularly relevant when the care process involves multiple specialties at different levels of care, including emergency care.
We may conclude that our centre’s multidisciplinary ALS team has contributed with a proactive attitude, inviting patients to express their preferences, though it should be noted that these wishes were not recorded for 43.2% of patients.
We should reflect on the clinical situation in which this declaration of patient preferences was recorded. Ideally, this would take place following correct assessment of cognitive/behavioural status and of clinical progression. This would be the only way to ensure that patients’ decisions on their care preferences were informed and freely made by individuals with the capacity to understand their scope, benefits, and potential risks. The same issue is considered in a review article by Foley at al.,29 who found that the majority of studies did not report assessment of patients’ cognitive status.
In this regard, a study performed at a hospital in Valencia is particularly interesting.13 The authors assessed moral reasoning and conflicts in a group of patients with ALS-frontotemporal dementia spectrum and in controls. Participants were assessed with neuropsychological and behavioural tests and asked to consider 8 moral conflicts. The authors suggest that their findings support the capacity of patients with ALS without dementia to make complex moral choices; the same was not true in the dementia group, with patients giving more utilitarian responses and showing less moral conflict. A study of a large cohort of patients with ALS found that the majority of patients are able to make independent decisions, even if they have moderate cognitive deficits.30 Numerous authors argue that patients with mild-to-moderate cognitive deficits should not be excluded from the decision-making process.31,32 Decision-making capacity would only be impaired in patients with frontotemporal dementia.
We may conclude that, as the percentage of patients with ALS and dementia in the period 2011-2022 is close to that reported in the majority of studies, neurologists specialising in the management of this disease at our centre were probably able, through a fundamentally clinical approach, to recognise which patients were not competent to make autonomous decisions, even in the absence of formal neuropsychological testing.
We should underscore the fact that one patient from the cohort attended by the multidisciplinary team requested euthanasia, and that this request was granted. Besides other types of considerations, the options available to our patients indisputably represent a very high level of suffering. Healthcare professionals must be aware of and work to improve survival, quality of life, living conditions, and respect for the dignity of our patients.
Study limitationsThe main limitations of this study are related to its retrospective design, which may have resulted in bias in the information collected. The data from before the implementation of multidisciplinary ALS care is less complete, similarly to the results reported at other Spanish centres.14,15,21
ConclusionsWe believe that the implementation of multidisciplinary ALS care in our setting has contributed to improving the assessment of cognitive status in patients with ALS, despite this assessment having been primarily clinical, enabling the diagnosis of dementia associated with ALS in a similar percentage of cases to the rates reported by other researchers.
Furthermore, it has led to a considerable increase in the recording of the care wishes of patients with ALS in the official register of advance directives or in patient clinical records, thus increasing respect for patients’ autonomous decisions and dignity.
The authors have no conflicts of interest to declare.
The authors thank all current and past members of the multidisciplinary ALS team at Hospital Universitario Virgen de la Victoria, Malaga.


