



Stroke represents a major public health challenge in Spain, with approximately 120 000 cases per year and a significant impact on mortality, disability, and dependency. Elevated low-density lipoprotein cholesterol (LDL-C) is a key modifiable causal factor in preventing vascular recurrences. This consensus statement aims to provide a comprehensive framework for the practical management of lipid-lowering therapy in patients with stroke or transient ischaemic attack (TIA).
MethodsA panel of experts in neurology, specialised in the management of patients with stroke/TIA, participated in 3 sessions to review the latest evidence. Subsequently, they reached consensus on practical recommendations for the management of lipid-lowering therapy based on data from clinical trials, meta-analyses, and current clinical guidelines.
ConclusionsAchieving the therapeutic targets for LDL-C is essential to prevent recurrence in patients with stroke/TIA. To ensure comprehensive management of LDL-C in patients with stroke/TIA, the application of intensive therapeutic strategies, individualised approaches, and robust continuity of care are recommended to optimise secondary prevention. Treatment planning at discharge, neurologist-led risk factor control, and coordinated continuity of care between hospital and primary care settings are essential factors determining long-term outcomes. Inclisiran has emerged as a new key therapy to improve lipid control and treatment adherence in these patients, in alignment with national and international recommendations for achieving therapeutic targets and reducing the burden of vascular disease. Optimal implementation of this therapeutic approach may substantially contribute to improving the prognosis of patients with stroke/TIA.
El ictus constituye un problema de salud pública importante en España, con aproximadamente 120.000 casos anuales y un elevado impacto en mortalidad, discapacidad y dependencia. El colesterol LDL (c-LDL) elevado es un factor causal modificable clave para prevenir recurrencias vasculares. Este documento busca proporcionar un marco integral para el manejo práctico de la terapia hipolipemiante en pacientes con ictus o ataque isquémico transitorio (AIT).
MetodologíaUn panel de expertos en neurología, especializados en el manejo de pacientes con ictus/AIT, se reunieron en tres sesiones para revisar la evidencia científica actualizada y, posteriormente, consensuar las recomendaciones prácticas del manejo de la terapia hipolipemiante basadas en datos de ensayos clínicos, meta-análisis y guías actuales.
ConclusionesAlcanzar los objetivos terapéuticos de c-LDL es esencial para evitar recurrencias en el paciente con ictus/AIT. Para garantizar el manejo integral del c-LDL en el paciente con ictus/AIT, se propone implementar estrategias terapéuticas intensivas, enfoques individualizados y una continuidad asistencial sólida para optimizar la prevención secundaria. La planificación terapéutica al alta, el control de factores de riesgo liderado por el neurólogo y la continuidad asistencial coordinada entre atención hospitalaria y primaria son determinantes a largo plazo. Inclisirán surge como una nueva terapia clave para mejorar el control lipídico y la adherencia en estos pacientes, alineándose con las recomendaciones nacionales e internacionales para la consecución de los objetivos terapéuticos y reducir la carga de la enfermedad vascular. Integrar de forma óptima esta nueva herramienta terapéutica podría ayudar significativamente a mejorar el pronóstico del paciente afectado por ictus/AIT.
Stroke represents a significant public health challenge in Spain, with approximately 120 000 new cases per year.1 In fact, one in 4 Spaniards is expected to have a stroke at some point in their lifetime; this underscores the importance of implementing effective prevention and treatment strategies.2 According to the National Statistics Institute, nearly 23 000 deaths due to cerebrovascular disease were recorded in 2024, with stroke being the third leading cause of death in Spain, after ischaemic cardiomyopathy.3 Stroke is the leading cause of acquired disability in adults,4 with around 50% of patients presenting disabling sequelae or dying due to stroke.5,6 As a result, a significant percentage of patients are dependent after stroke, with approximately 62% presenting mobility problems and 59% having difficulties with everyday activities.7,8 Stroke also has a considerable socioeconomic impact. The costs associated with healthcare resource use in the first year after stroke amount to € 11 060, according to data from the regional health system of Catalonia9; the main cost is hospitalisation during acute stroke, with a mean cost of € 7599 per patient in Spain in 2021.1 Non-medical costs can reach € 29 484 per patient per year, with support from caregivers amounting to an additional € 10 508.10,11 Furthermore, stroke-related costs are expected to increase in future as a result of population ageing.6
In the light of the above, stroke prevention plays an essential role, as 90% of cases of stroke are estimated to be preventable through proper control of risk factors.12 Secondary prevention after a first stroke or transient ischaemic attack (TIA) aims to prevent recurrence, which continues to be a considerable challenge. Despite improvements in diagnostic methods and the availability of more effective treatments, recurrence rates appear not to have changed significantly over the last 20 years. Rates depend on the aetiological subtype of stroke, with atherosclerotic and cardioembolic strokes being associated with greater risk.1
Low-density lipoprotein cholesterol and vascular diseaseLow-density lipoprotein cholesterol (LDL-C) plays a central role in the pathogenesis of atherosclerosis, and constitutes a key aetiological factor in the development of ischaemic stroke and TIA. Progressive accumulation of LDL-C on the arterial wall contributes to the development and growth of atherosclerotic plaque, increasing the risk of vascular events. Furthermore, the impact of this modifiable causal factor is determined both by the absolute amount of LDL-C and by the duration of exposure to elevated levels.13–15 In this context, sustained reduction of LDL-C levels has been shown to decrease the risk of vascular events, minimising atherosclerotic load and the risk of thrombotic complications.13–17 The available evidence appears to support keeping LDL-C levels as low as possible, with no apparent lower limit.13–15 Therefore, implementation of treatment strategies aiming to intensively reduce LDL-C level (lipid-lowering therapies) is fundamental in secondary prevention to avoid recurrent stroke/TIA.16,17
With a view to promoting effective secondary prevention of stroke and TIA, this document presents a series of practical recommendations prepared by vascular neurology specialists with expertise in the management of patients with stroke/TIA, based on the available evidence and the clinical experience of these experts in the field.
MethodologyThis consensus statement was developed through meetings of a panel of vascular neurology experts, who evaluated the current scientific evidence and shared their experience with the management of patients with stroke/TIA. To gather the available evidence, a non-systematic review was conducted of the literature on stroke epidemiology, the objectives of lipid-lowering therapy, and therapeutic innovations.
The expert panel met on 3 occasions, between December 2024 and May 2025. Prior to the meetings, the panel defined the methodology, the working dynamic, and the objectives of the consensus statement. At the first session, the latest scientific evidence was presented, the suitable evidence for the scope and objectives of the consensus statement was selected, and the information for inclusion in each section was defined. At the second session, experts developed consensus recommendations on the management of lipid-lowering therapy, based on data from clinical trials, meta-analyses, and current guidelines, to support clinical staff in optimising the secondary prevention of stroke/TIA and minimising vascular complications in the long term. All consensus information was incorporated into the draft version of the recommendations and shared with the expert panel for several rounds of review. In the third session, all members of the expert panel reviewed and approved the document for publication.
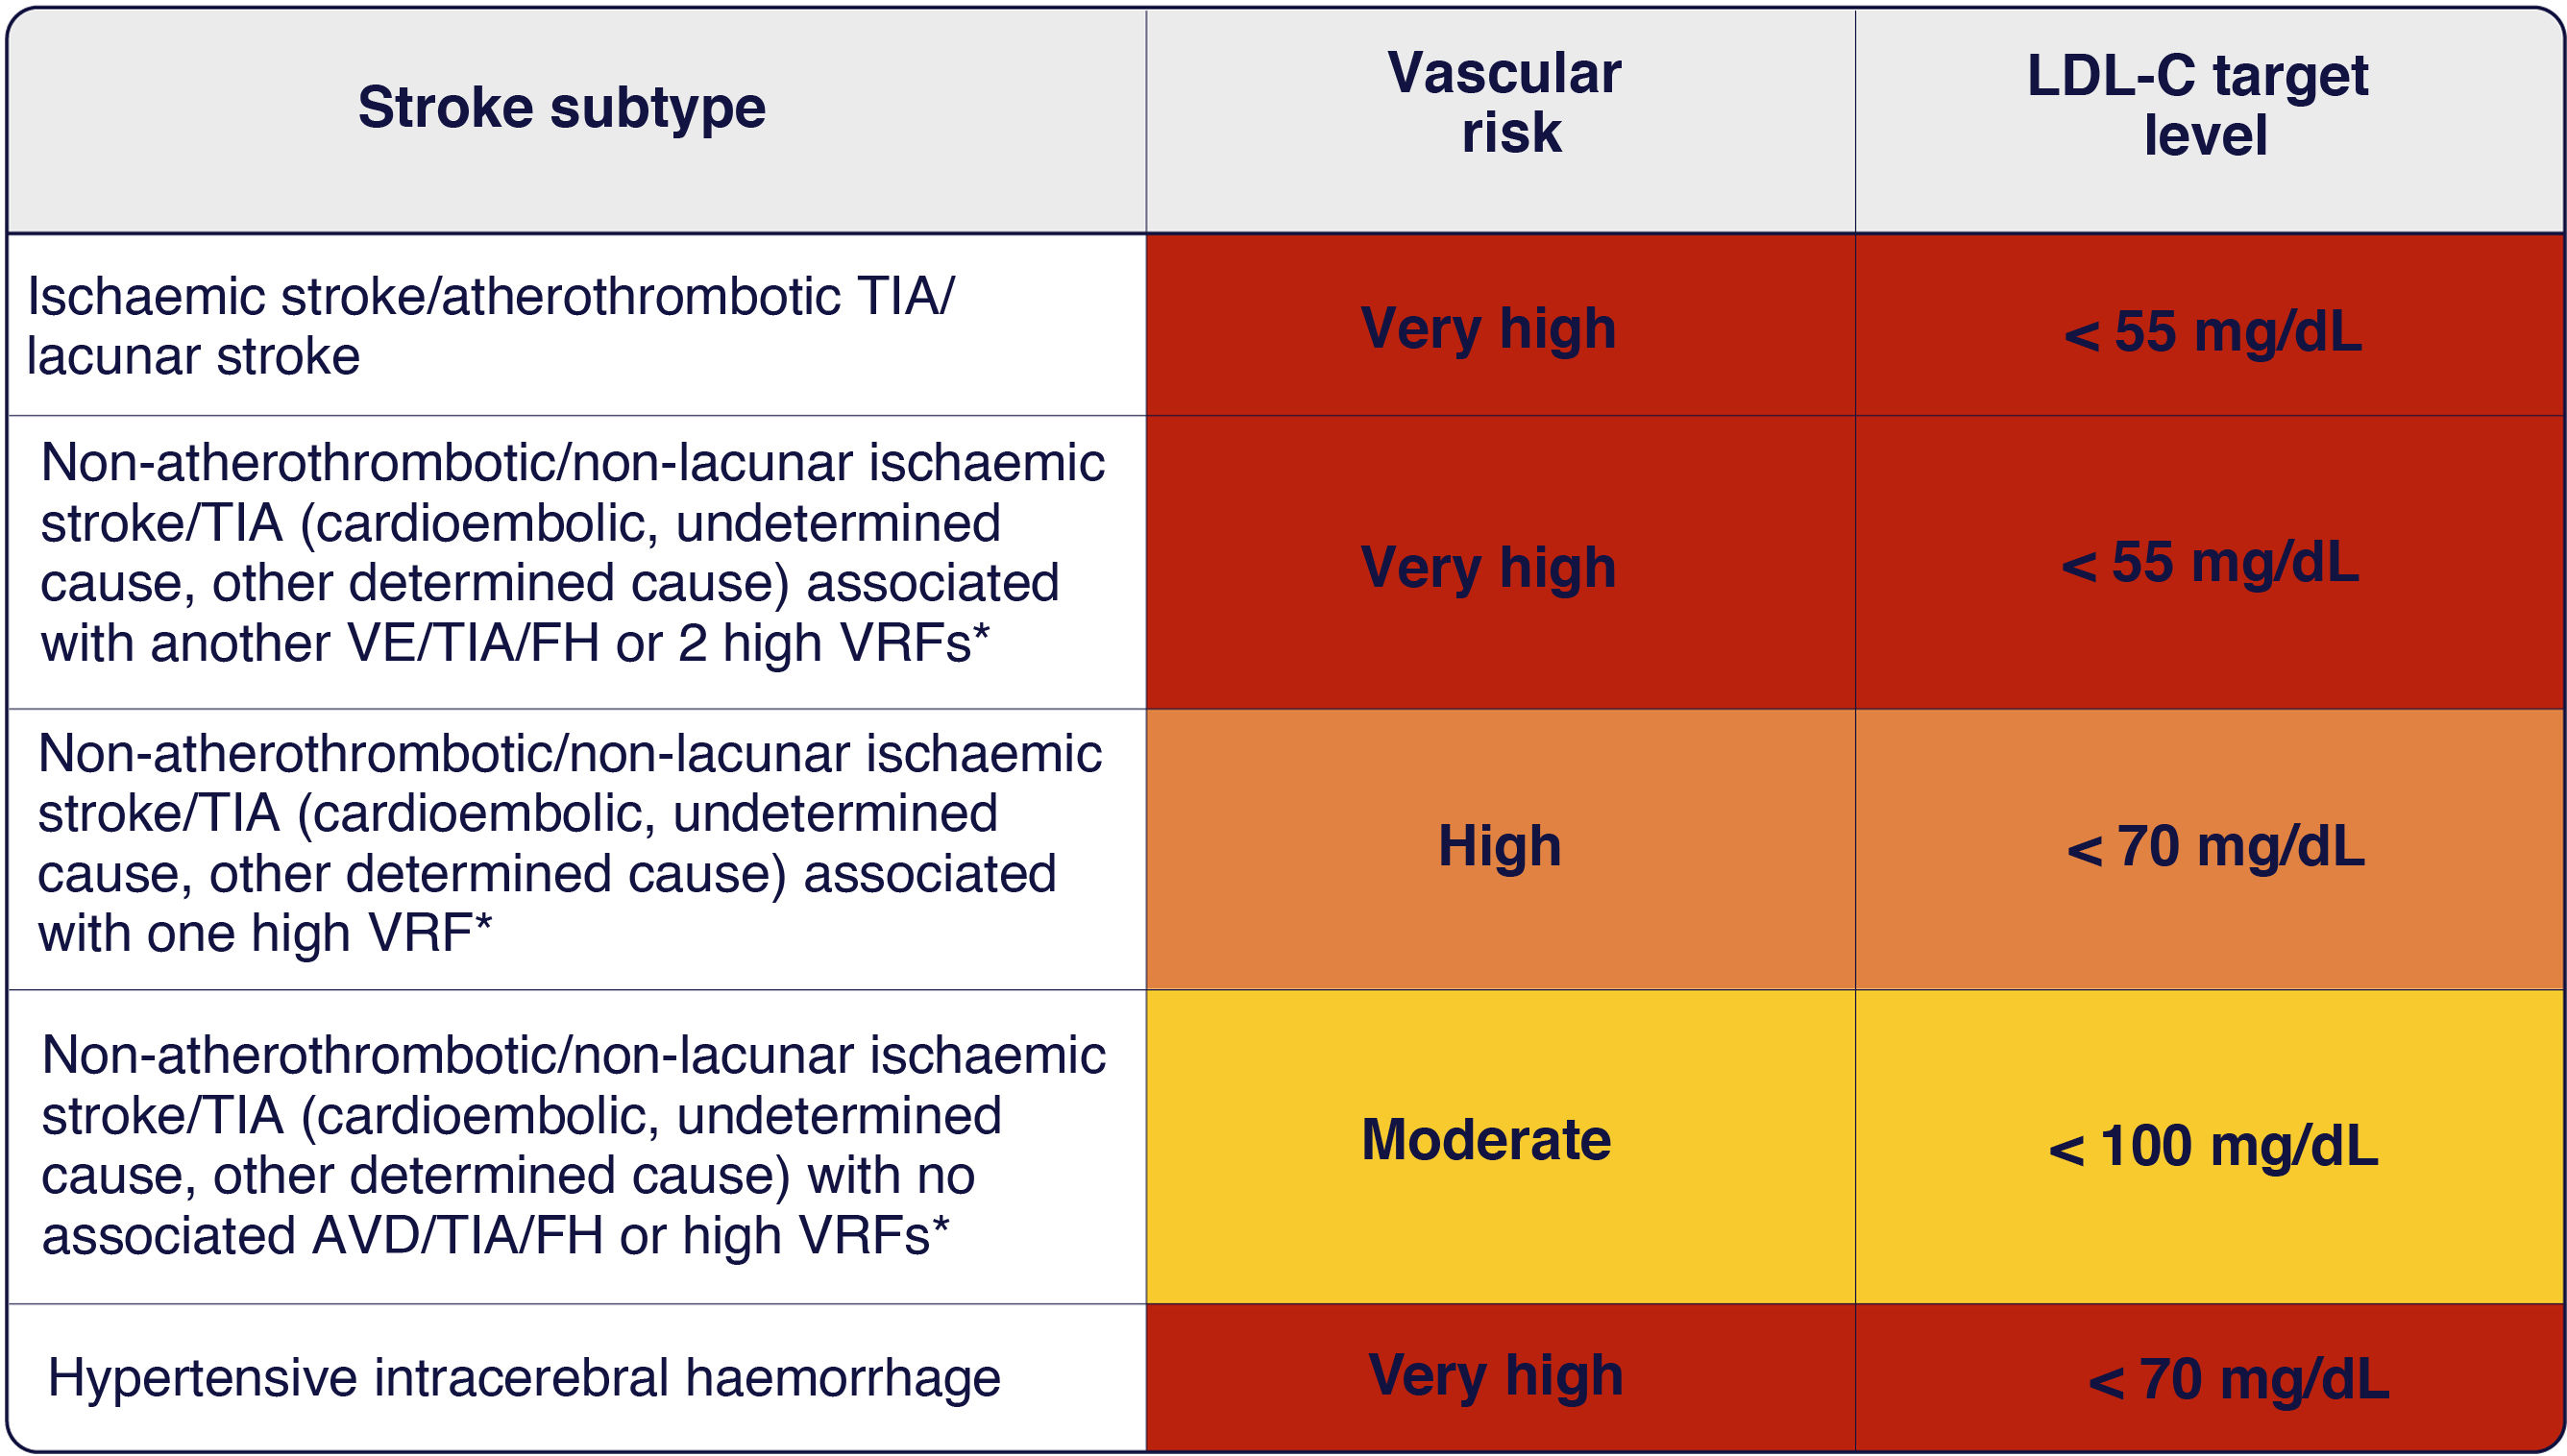
Treatment objectives for low-density lipoprotein cholesterol in stroke/transient ischaemic attackTarget LDL-C levels for patients with history of stroke/TIA should be established according to overall vascular risk. Therefore, the target LDL-C value in the majority of patients with stroke/TIA would be < 55 mg/dL,18 as these patients generally present very high vascular risk, independently of stroke aetiology. In rare cases, different target values will be established (Fig. 1). In patients with extreme vascular risk, lower values will be established19; a level of < 40 mg/dL is recommended, in accordance with evidence that lower LDL-C levels are associated with a significant risk of recurrence of vascular events.18,20–27 In patients with non-atherothrombotic/non-lacunar stroke/TIA, we should establish target LDL-C levels of < 55 mg/dL for patients with very high vascular risk or < 70 mg/dL for those with high risk. For patients with hypertensive intracerebral haemorrhage, an objective of < 70 mg/dL is recommended, although this should be established on an individual basis according to the patient’s comorbidities, and especially age and frailty.

Recommended low-density lipoprotein cholesterol levels according to the level of vascular risk in patients with stroke/transient ischaemic attack.
*High vascular risk factors: age > 65 years, diabetes mellitus, arterial hypertension, active smoking, chronic kidney disease (glomerular filtration rate: 15-59 mL/min/1.73 m²), history of coronary artery bypass surgery or percutaneous coronary intervention outside the main episode of atherosclerotic vascular disease, history of congestive heart failure, or persistently high levels of low-density lipoprotein cholesterol (> 100 mg/dL) despite statin treatment at the maximum tolerated dose ± ezetimibe.
AVD: atherosclerotic vascular disease; FH: familial hypercholesterolaemia; LDL-C: low-density lipoprotein cholesterol; TIA: transient ischaemic attack; VE: vascular event; VRF: vascular risk factors.
These recommendations are aligned both with the clinical guidelines of the European Society of Cardiology (ESC) and the European Atherosclerosis Society (EAS),27 as well as the consensus of several Spanish scientific societies (including the Spanish Society of Neurology) on the management of lipid-lowering therapies in clinical practice.26 These guidelines recommend not only the LDL-C target of < 55 mg/dL, but also a 50% reduction with respect to the baseline value in patients with documented atherosclerosis. This vascular pathology may be documented by clinical manifestations or unequivocal findings from specific vascular imaging studies (carotid artery stenosis and/or coronary artery calcification).26,27,32 To achieve the recommended treatment objectives, intensity of lipid-lowering therapy must be adjusted from onset, and subsequently during post-discharge follow-up.33
Intensive lipid-lowering therapy in patients with extreme risk factorsIn patients with stroke and presenting extreme vascular risk factors, intensive lipid-lowering therapy is recommended to reach a target LDL-C level < 40 mg/dL, aiming to reduce the high risk of recurrence and improve long-term prognosis.26,27 Factors associated with extreme vascular risk in patients with stroke/TIA include the following:
- •
History of atherosclerotic vascular events in the last 2 years (any vascular territory);
- •
Carotid or intracranial artery stenosis with haemodynamically significant alterations (stenosis > 50%)19 or showing progression34;
- •
Diagnosis of familial hypercholesterolaemia;
- •
Presence of at least 2 of the following high vascular risk factors: acute coronary syndrome in young patients (< 55 [men] or < 65 years [women]), history of coronary artery revascularisation, diabetes mellitus, moderate-severe chronic kidney disease, polyvascular disease, or elevated lipoprotein (a) (Lp(a)) levels (> 50 mg/dL).26
In these patients, intensive lipid-lowering therapy should be implemented early, from the time of hospital admission, to achieve the therapeutic target as early as possible; patients should also be followed up closely with periodic blood analyses to ensure that LDL-C levels remain within the target range, with treatment adjusted if necessary.27
Lipid-lowering therapy and controlling dyslipidaemiaReducing LDL-C levels through lipid-lowering therapy is a key strategy for optimising the prevention of new atherosclerotic cerebrovascular events. The SPARCL study35 found that high-intensity statin treatment (atorvastatin 80 mg/day) reduced the 5-year risk of recurrence of stroke/TIA by 23%. The authors also observed that a ≥ 50% reduction in LDL-C was associated with a 31% decrease in the risk of stroke (33% for ischaemic stroke) and a 37% decrease in the risk of major coronary events, with no increase in the risk of haemorrhagic stroke.21
Though all lipid-lowering therapies show benefits in secondary prevention by reducing LDL-C, the additional inhibition of proprotein convertase subtilisin/kexin type 9 (PCSK9) has improved the impact of statins in monotherapy.36 The FOURIER clinical trial37 found that the PCSK9 inhibitor evolocumab reduced the risk of ischaemic stroke by 25% in patients with history of vascular disease (myocardial infarction, ischaemic stroke, or symptomatic peripheral artery disease with LDL-C ≥ 70 mg/dL) and receiving statins. In fact, secondary prevention with evolocumab maintained a 56.3% reduction in LDL-C levels at 48 weeks of follow up in patients with history of ischaemic stroke.25 Furthermore, the subanalysis of patients with stroke in the ODYSSEY OUTCOMES study38 found that in patients with recent history of acute coronary artery syndrome and LDL-C ≥ 70 mg/dL despite intensive statin treatment, the PCSK9 inhibitor alirocumab reduced the risk of all types of stroke by 28%, independently of baseline LDL-C level and history of cerebrovascular disease, over a mean follow-up period of 2.8 years.39 None of these studies reports an increase in the risk of haemorrhagic stroke, even in patients with lower LDL-C levels.25,39
Nonetheless, the majority of patients do not achieve the recommended treatment objectives with current lipid-lowering therapies.26,27 The DA VINCI observational trial,40 conducted in 18 European countries, describes the use of lipid-lowering therapies in everyday clinical practice, and revealed that only 16% of patients with cerebrovascular disease achieved LDL-C levels < 55 mg/dL; this figure rose to 44% among patients receiving combination therapy that included a PCSK9 inhibitor.41 Dyslipidaemia is the worst controlled risk factor for stroke, despite its being the second most prevalent, and is only adequately treated in 37.2% of patients with the disorder (and with ischaemic stroke receiving very high- or extreme-intensity treatment at 2 years of follow-up).42 This therapeutic gap was also observed in the REALITY study,43 which analysed data from 1.8 million Spanish patients under secondary preventive treatment (including for ischaemic stroke), and observed that LDL-C was the only factor that was inadequately controlled at 2 years, unlike blood pressure and glycosylated haemoglobin.
This context underscores the need to implement more effective therapies; recently, the drug inclisiran has become available as a new lipid-lowering therapy, with very promising results in controlling dyslipidaemia.
InclisiranInclisiran is a double-stranded small interfering RNA (siRNA) conjugated to N-acetylgalactosamine to favour its uptake by hepatocytes through a process of endocytosis.44–46 This molecule specifically inhibits PCSK9 synthesis in the liver through degradation of the protein’s mRNA,44,45,47,48 resulting in a lasting decrease in levels of circulating PCSK9.47,48 Thus, LDL-C receptor availability in hepatocytes is increased, promoting greater uptake of circulating LDL-C and achieving an effective, sustained decrease in plasma levels of the substance.48,49
Inclisiran has demonstrated efficacy in achieving a sustained reduction in LDL-C level,50 with comparable results to PCSK9 inhibitors,51 while also presenting improvements as a therapeutic option. Given its highly selective action mechanism, it presents a favourable safety profile. No clinically significant interactions with other drugs are expected, and there is no need for dose adjustment for age, kidney failure in any stage (including haemodialysis, with a 72-h interval after the last dose), or mild to moderate liver failure. However, no data are available for patients with severe liver failure; therefore, the drug should be used with caution in these patients.52 Furthermore, inclisiran presents a simple dosing schedule, with 2 initial doses separated by an interval of 3 months and doses every 6 months thereafter. This schedule is convenient both for healthcare professionals and for patients, facilitating treatment adherence. The drug’s long half-life after entering hepatocytes enables semesterly administration; by 48 hours after subcutaneous administration, it is not detectable in the plasma.52 Compared to PCSK9 inhibitors, which require up to 26 injections per year, inclisiran enables a reduction in the annual treatment burden,52,53 as well as the number of trips made by patients with reduced mobility and hospital pharmacy appointments.54 Administration by a healthcare professional ensures that patients receive the drug correctly, minimising the risk of missed doses and improving the continuity of lipid control.52 At the same time, it offers an opportunity for follow-up and patient education about healthy lifestyles. Furthermore, it requires no special storage conditions, facilitating its use in clinical practice.52
Clinical evidence on inclisiran as a lipid-lowering therapyThe efficacy of inclisiran in achieving a sustained reduction in LDL-C levels in patients with vascular disease has been evaluated and demonstrated in numerous clinical trials. The evidence is presented below.
Subanalysis of patients with cerebrovascular disease from the ORION-9, ORION-10, and ORION-11 trialsIn the pooled post hoc analysis of the ORION trials, 90% of patients with cerebrovascular disease and treated with inclisiran had history of ischaemic stroke. Treatment achieved a sustained reduction in LDL-C levels of 55.2%; this is comparable to the effect seen in the population with atherosclerotic vascular disease in general.50 It also achieved a significant reduction of 17.6% in Lp(a) level.50 Regarding the drug’s safety profile, results from patients with cerebrovascular disease were generally consistent with those reported in the overall population in these trials. No intracranial haemorrhages were reported, and only one patient presented ischaemic stroke. Adverse events associated with inclisiran were infrequent and mild, generally at the injection site.50
Subanalysis of patients with atherosclerotic vascular disease from the ORION-10 and ORION-11 trialsIn the cohort of patients with history of atherosclerotic cardiovascular disease (coronary heart disease, cerebrovascular disease, or peripheral artery disease) in the ORION-10 and ORION-11 trials, inclisiran achieved a sustained reduction in LDL-C levels, with 52.1% and 87.6% of patients, respectively, presenting levels < 55 mg/dL after one or 2 visits.55 Furthermore, the safety profile of inclisiran was similar to that of placebo, and was homogeneous in all subgroups. The only adverse effect associated with inclisiran was injection site reactions.52 All adverse reactions were of mild to moderate severity, transient, and resolved without sequelae.55
Prospective study by Cherepianskii et al.56The study of real clinical data reported by Cherepianskii et al.56 included 12 patients with acute ischaemic stroke, treated with a first dose of inclisiran in combination with statins within 3 days after stroke. At 15 days after treatment onset, patients presented a 71.1% reduction in LDL-C levels; 66.7% of patients achieved the proposed target LDL-C level of < 55 mg/dL. No treatment-related adverse events were reported.56
CHOLINET ambispective studyThe CHOLINET study57 was a multicentre analysis performed at 31 centres in Italy, including a total of 659 patients with very high vascular risk and LDL-C levels ≥ 70 mg/dL under treatment with statins ± ezetimibe, who started inclisiran treatment under regular clinical management. In this cohort from a larger setting, LDL-C showed a sustained reduction of 51% at 3 months and 56% at 9 months. The reduction in LDL-C was more pronounced in patients receiving statins ± ezetimibe than those who were not receiving this treatment (58% vs 42% at 3 months; 61% vs 47% at 9 months; P < .0001). Among patients treated with statins at baseline, 71% achieved the target LDL-C level of < 55 mg/dL at 3 months, and 83% achieved it at 9 months.57
The available evidence on these effects suggests that inclisiran is a promising option for secondary prevention through control of dyslipidaemia, reducing the risk of recurrent vascular events.
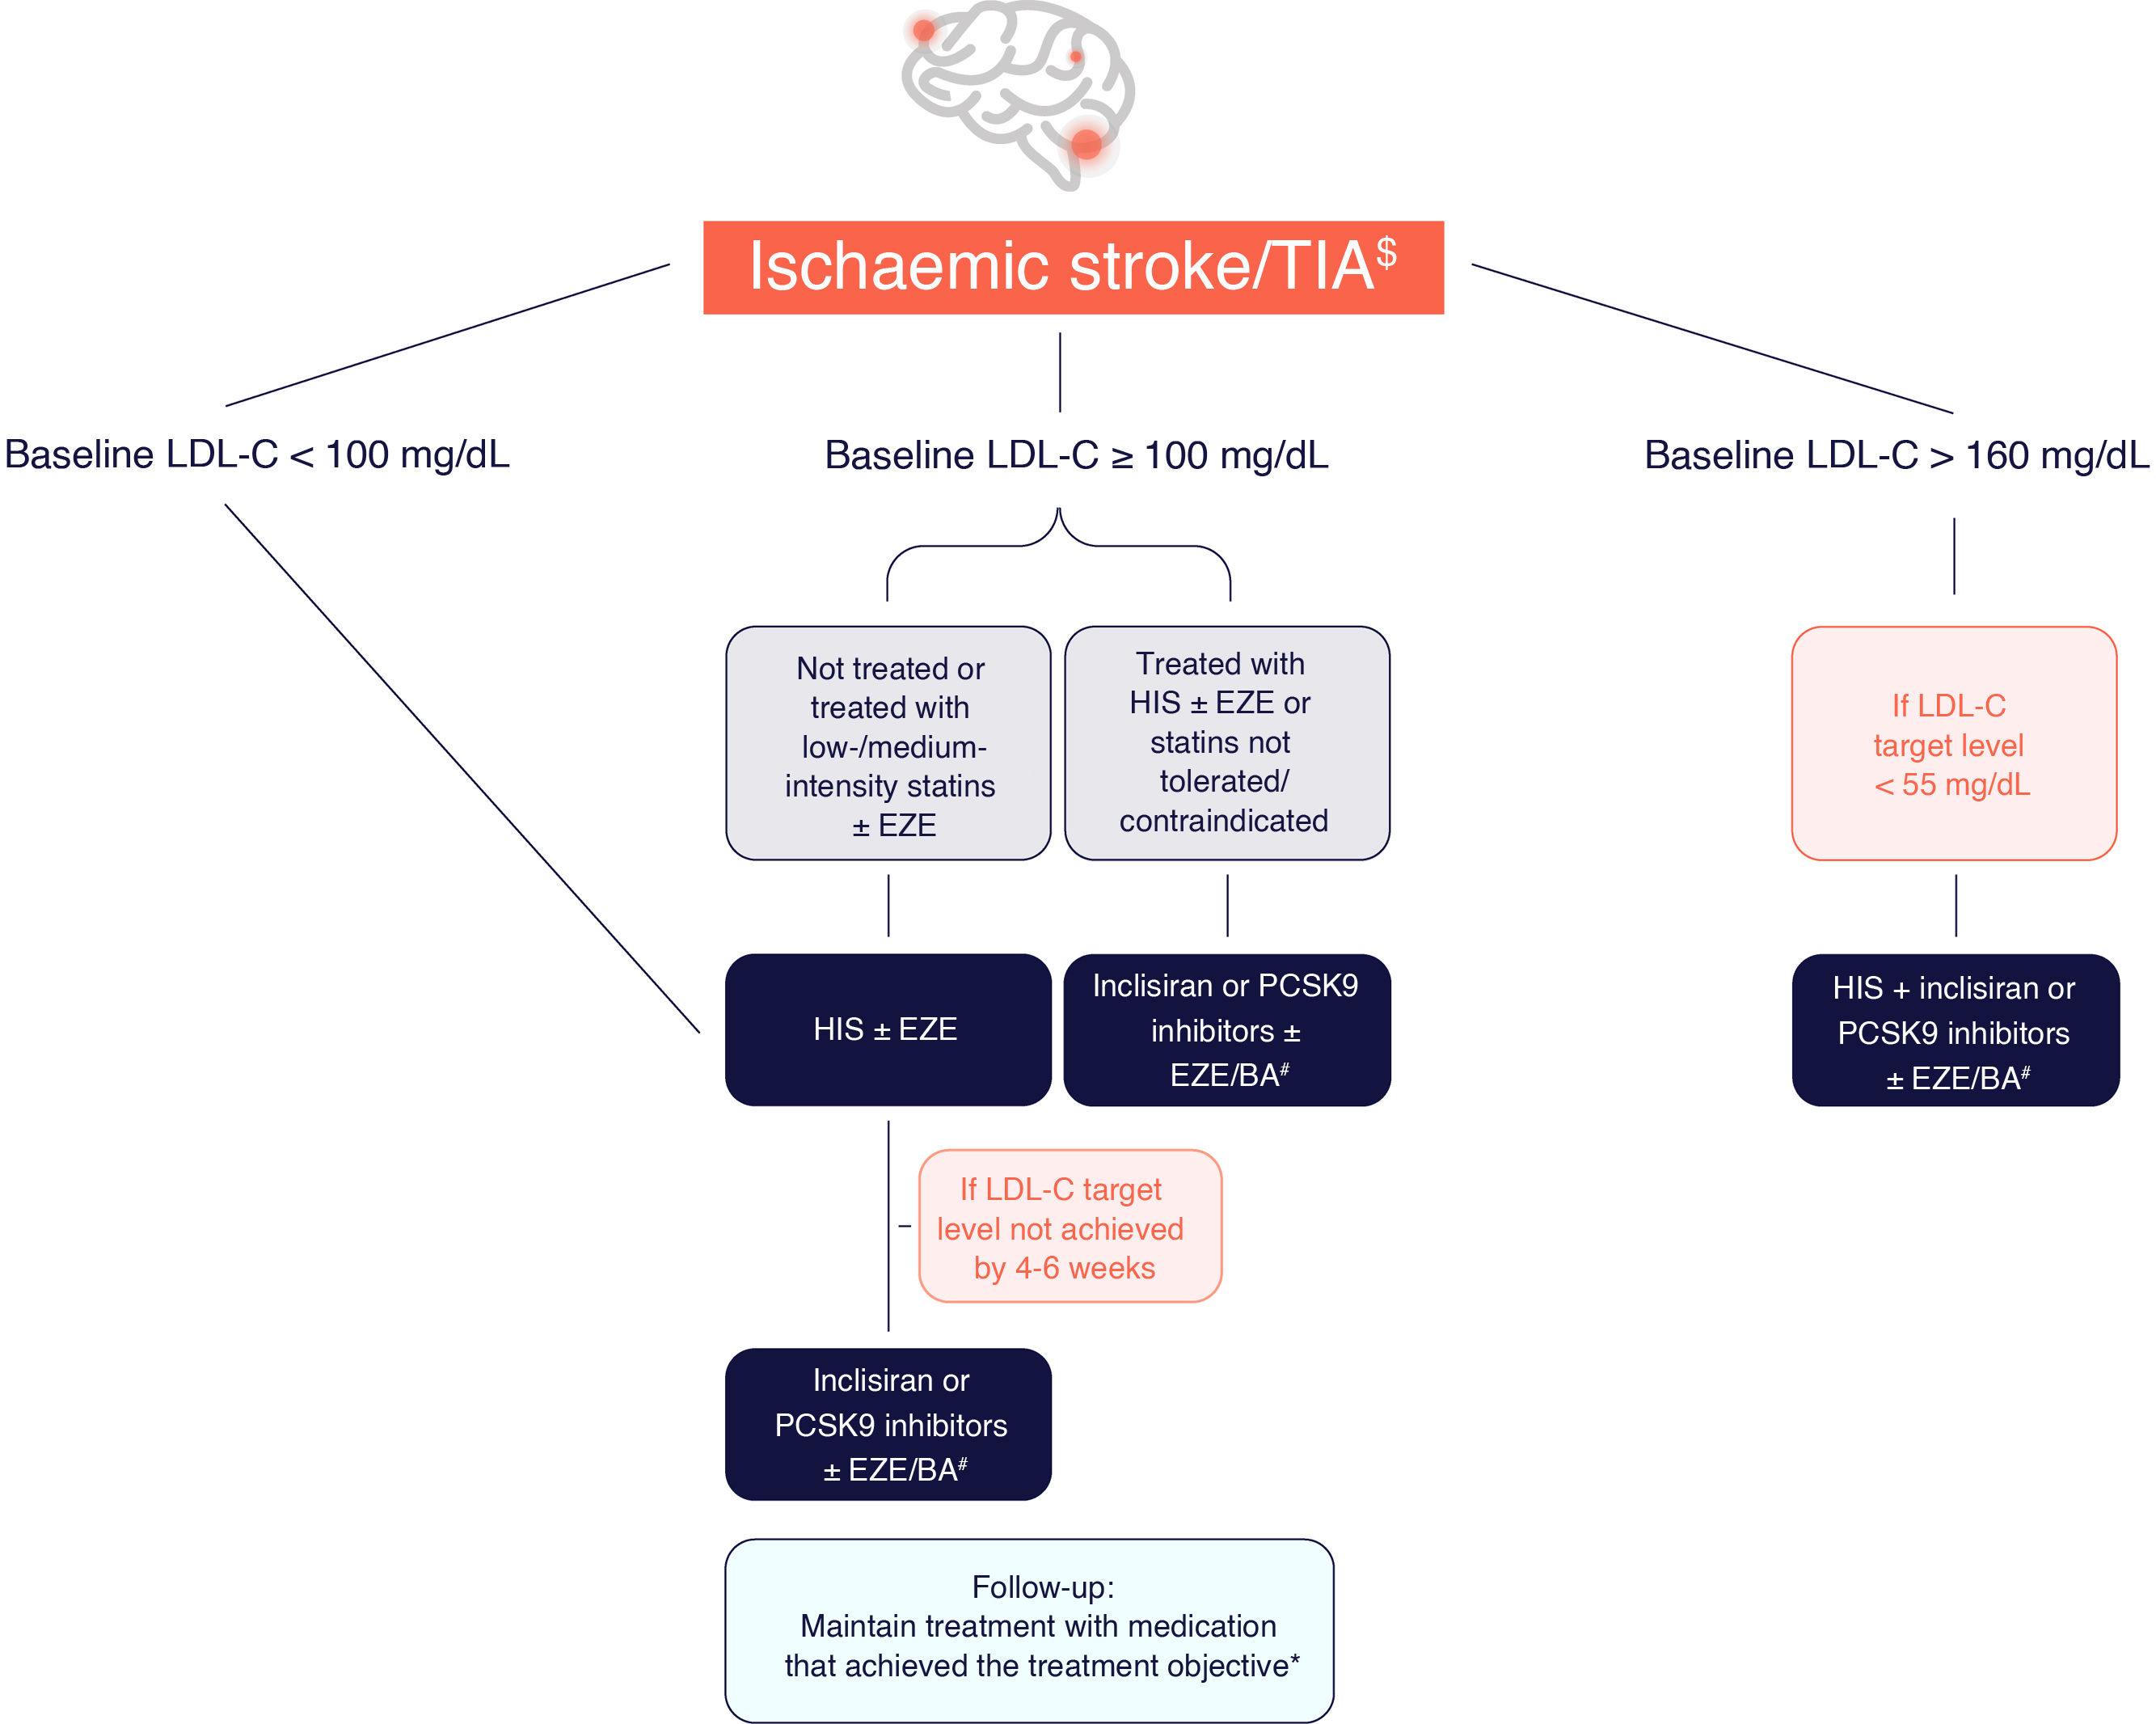
Positioning of lipid-lowering therapiesAccording to the Spanish multi-society consensus on the management of lipid-lowering therapies in clinical practice26 and on treatment planning,33 as well as the latest (2025) update of the ESC/EAS European guidelines,19 the traditional stepwise strategy should be abandoned in favour of an individualised approach, advocating for therapeutic planning and intensive treatment from onset in order to achieve LDL-C reduction objectives, regardless of the healthcare level. This strategy, known as “fire to target,” is fundamental in patients with very high or extreme cardiovascular risk and elevated baseline LDL-C level. We should not expect patients with LDL-C > 160 mg/dL to achieve the therapeutic objective of < 55 mg/dL with oral therapy alone, and onset of treatment with inclisiran or PCSK9 inhibitors is needed. Likewise, the addition of therapy targeting PCSK9 (inclisiran or PCSK9 inhibitors) is recommended in patients previously under high-intensity statin treatment ± ezetimibe, or with intolerance/contraindications for statins, and baseline LDL-C ≥ 100 mg/dL. Fig. 2 shows the recommendations for lipid-lowering therapy after stroke/TIA.

Recommendations for lipid-lowering treatment after stroke/transient ischaemic attack.
$Early implementation in patients with extreme risk (2 or more acute VEs, one acute VE plus FH, carotid or intracranial artery stenosis with significant haemodynamic alterations [stenosis > 50%] or in progression, or one acute VE plus at least 2 of the following conditions: ACS in young patients [< 55 years in men; < 65 years in women], previous coronary artery revascularisation, DM, moderate-severe CKD, polyvascular disease, or Lp(a) > 50 mg/dL).26
#Funding conditions for non-statin drugs may vary between regions.
*Due to differences in treatment response between individuals, LDL-C levels should be monitored at 4–6 weeks.
ACS: acute coronary syndrome; BA: bempedoic acid; CKD: chronic kidney disease; DM: diabetes mellitus; EZE: ezetimibe; FH: familial hypercholesterolaemia; HIS: high-intensity statins; LDL-C: low-density lipoprotein cholesterol; Lp(a): lipoprotein (a); PCSK9: proprotein convertase subtilisin/kexin type 9; TIA: transient ischaemic attack; VE: vascular event.
Hospital admission enables aetiological diagnosis of stroke/TIA and planning of treatment objectives for the various vascular risk factors, as well as the creation of a treatment and follow-up strategy to ensure continuity of care after discharge. During this hospital phase, optimisation of lipid-lowering treatment is essential in reducing the risk of recurrence and improving long-term outcomes.58,59 Targeted neurological examination should be performed to establish neurological status and functional prognosis. It is also important to closely monitor such vascular risk factors as LDL-C level, blood pressure, glycaemia, obesity, and atrial fibrillation, together with planning of antithrombotic therapy, depending on stroke/TIA aetiology.
A series of LDL-C–based treatment strategies are proposed to optimise lipid-lowering therapy (Fig. 3). Prior to hospital discharge, blood analysis should be performed to assess the patient’s lipid profile, including LDL-C, high-density lipoprotein cholesterol, triglycerides, and Lp(a).

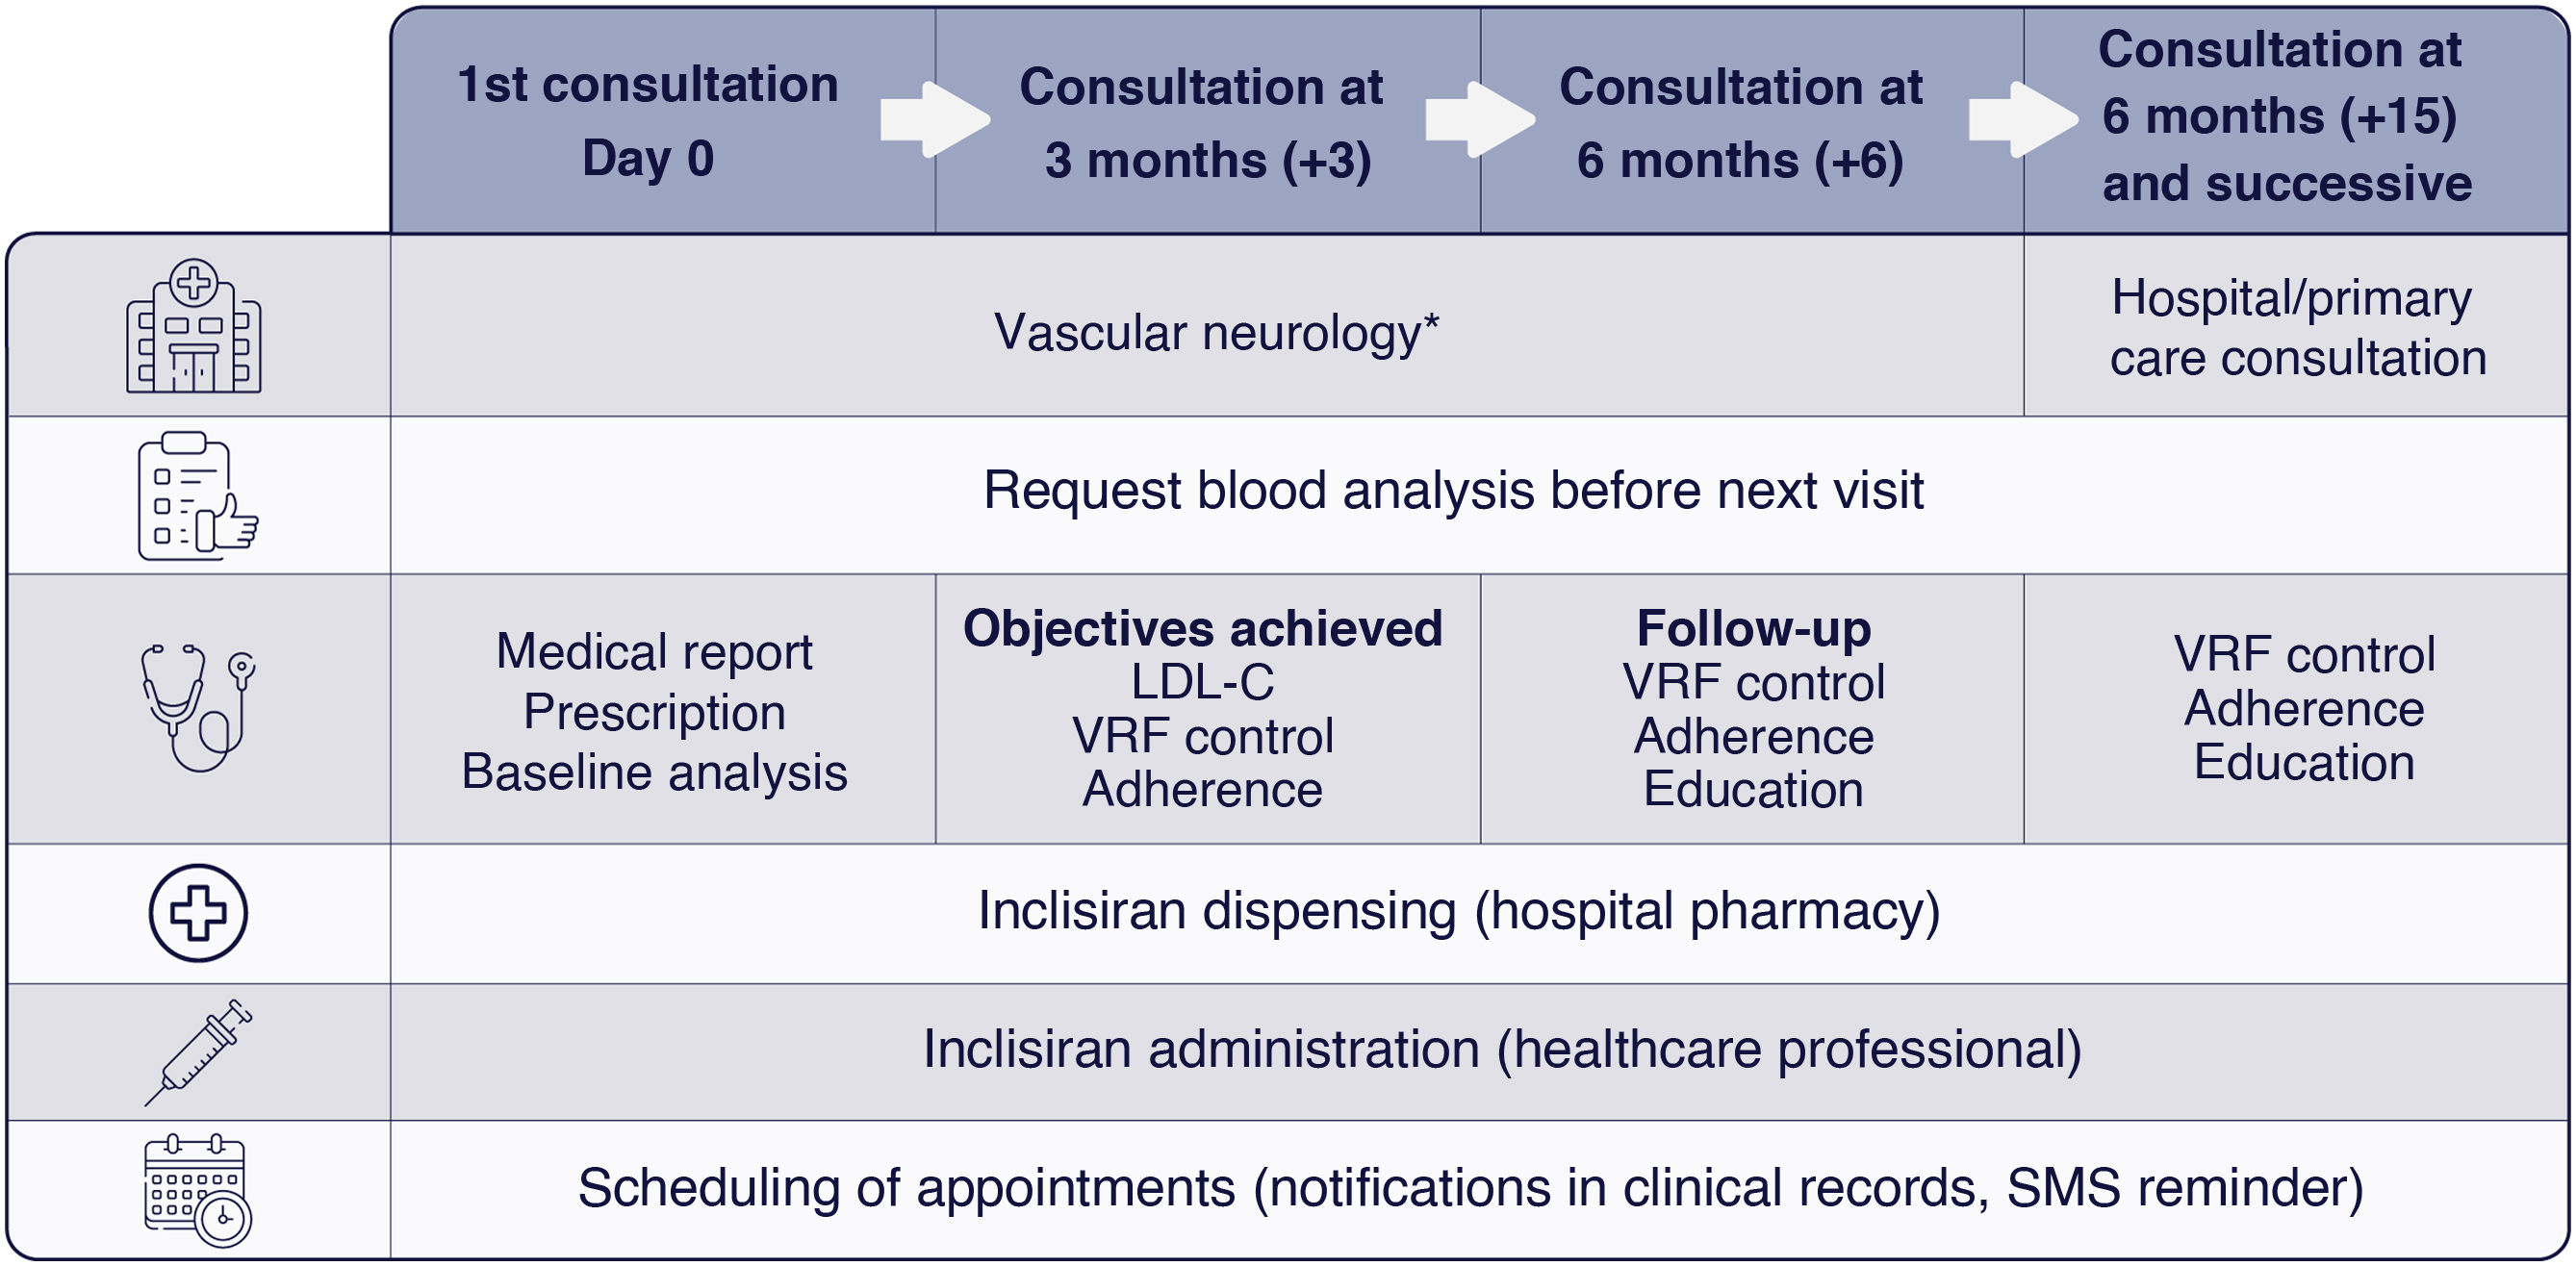
Recommendations for intra-hospital and post-discharge follow-up of stroke/transient ischaemic attack. Follow-up scheme based on references 27,48,58 and 60.
APN: advanced practice nurse; HDL-C: high-density lipoprotein cholesterol; HIS: high-intensity statins; LDL-C: low-density lipoprotein cholesterol; Lp(a): lipoprotein (a); PCSK9: proprotein convertase subtilisin/kexin type 9; VRF: vascular risk factor.
Outpatient follow-up after hospital discharge must follow a multidisciplinary approach. We propose that treatment adherence and clinical progression be monitored at primary care consultations within the first 7-14 days. Subsequently, a post-discharge follow-up consultation (either in person or virtual) with a vascular neurology specialist should be held at 4-6 weeks. During this consultation, the specialist should evaluate the patient’s lipid profile and liver function, confirm that LDL-C level has decreased by ≥ 50%, and verify that target LDL-C values have been met. In the event that therapeutic objectives are not met, treatment intensity should be increased according to the recommendations presented in Fig. 1.
LDL-C monitoring should follow a stepwise approach, with a first review at 4-6 weeks and subsequently at 3 months, then every 6-12 months thereafter, depending on lipid control. In the event that optimal in-person follow-up is not possible, teleconsultations are recommended to ensure continuity of follow-up. Fig. 3 presents the recommendations for post-discharge follow-up of patients with stroke/TIA.
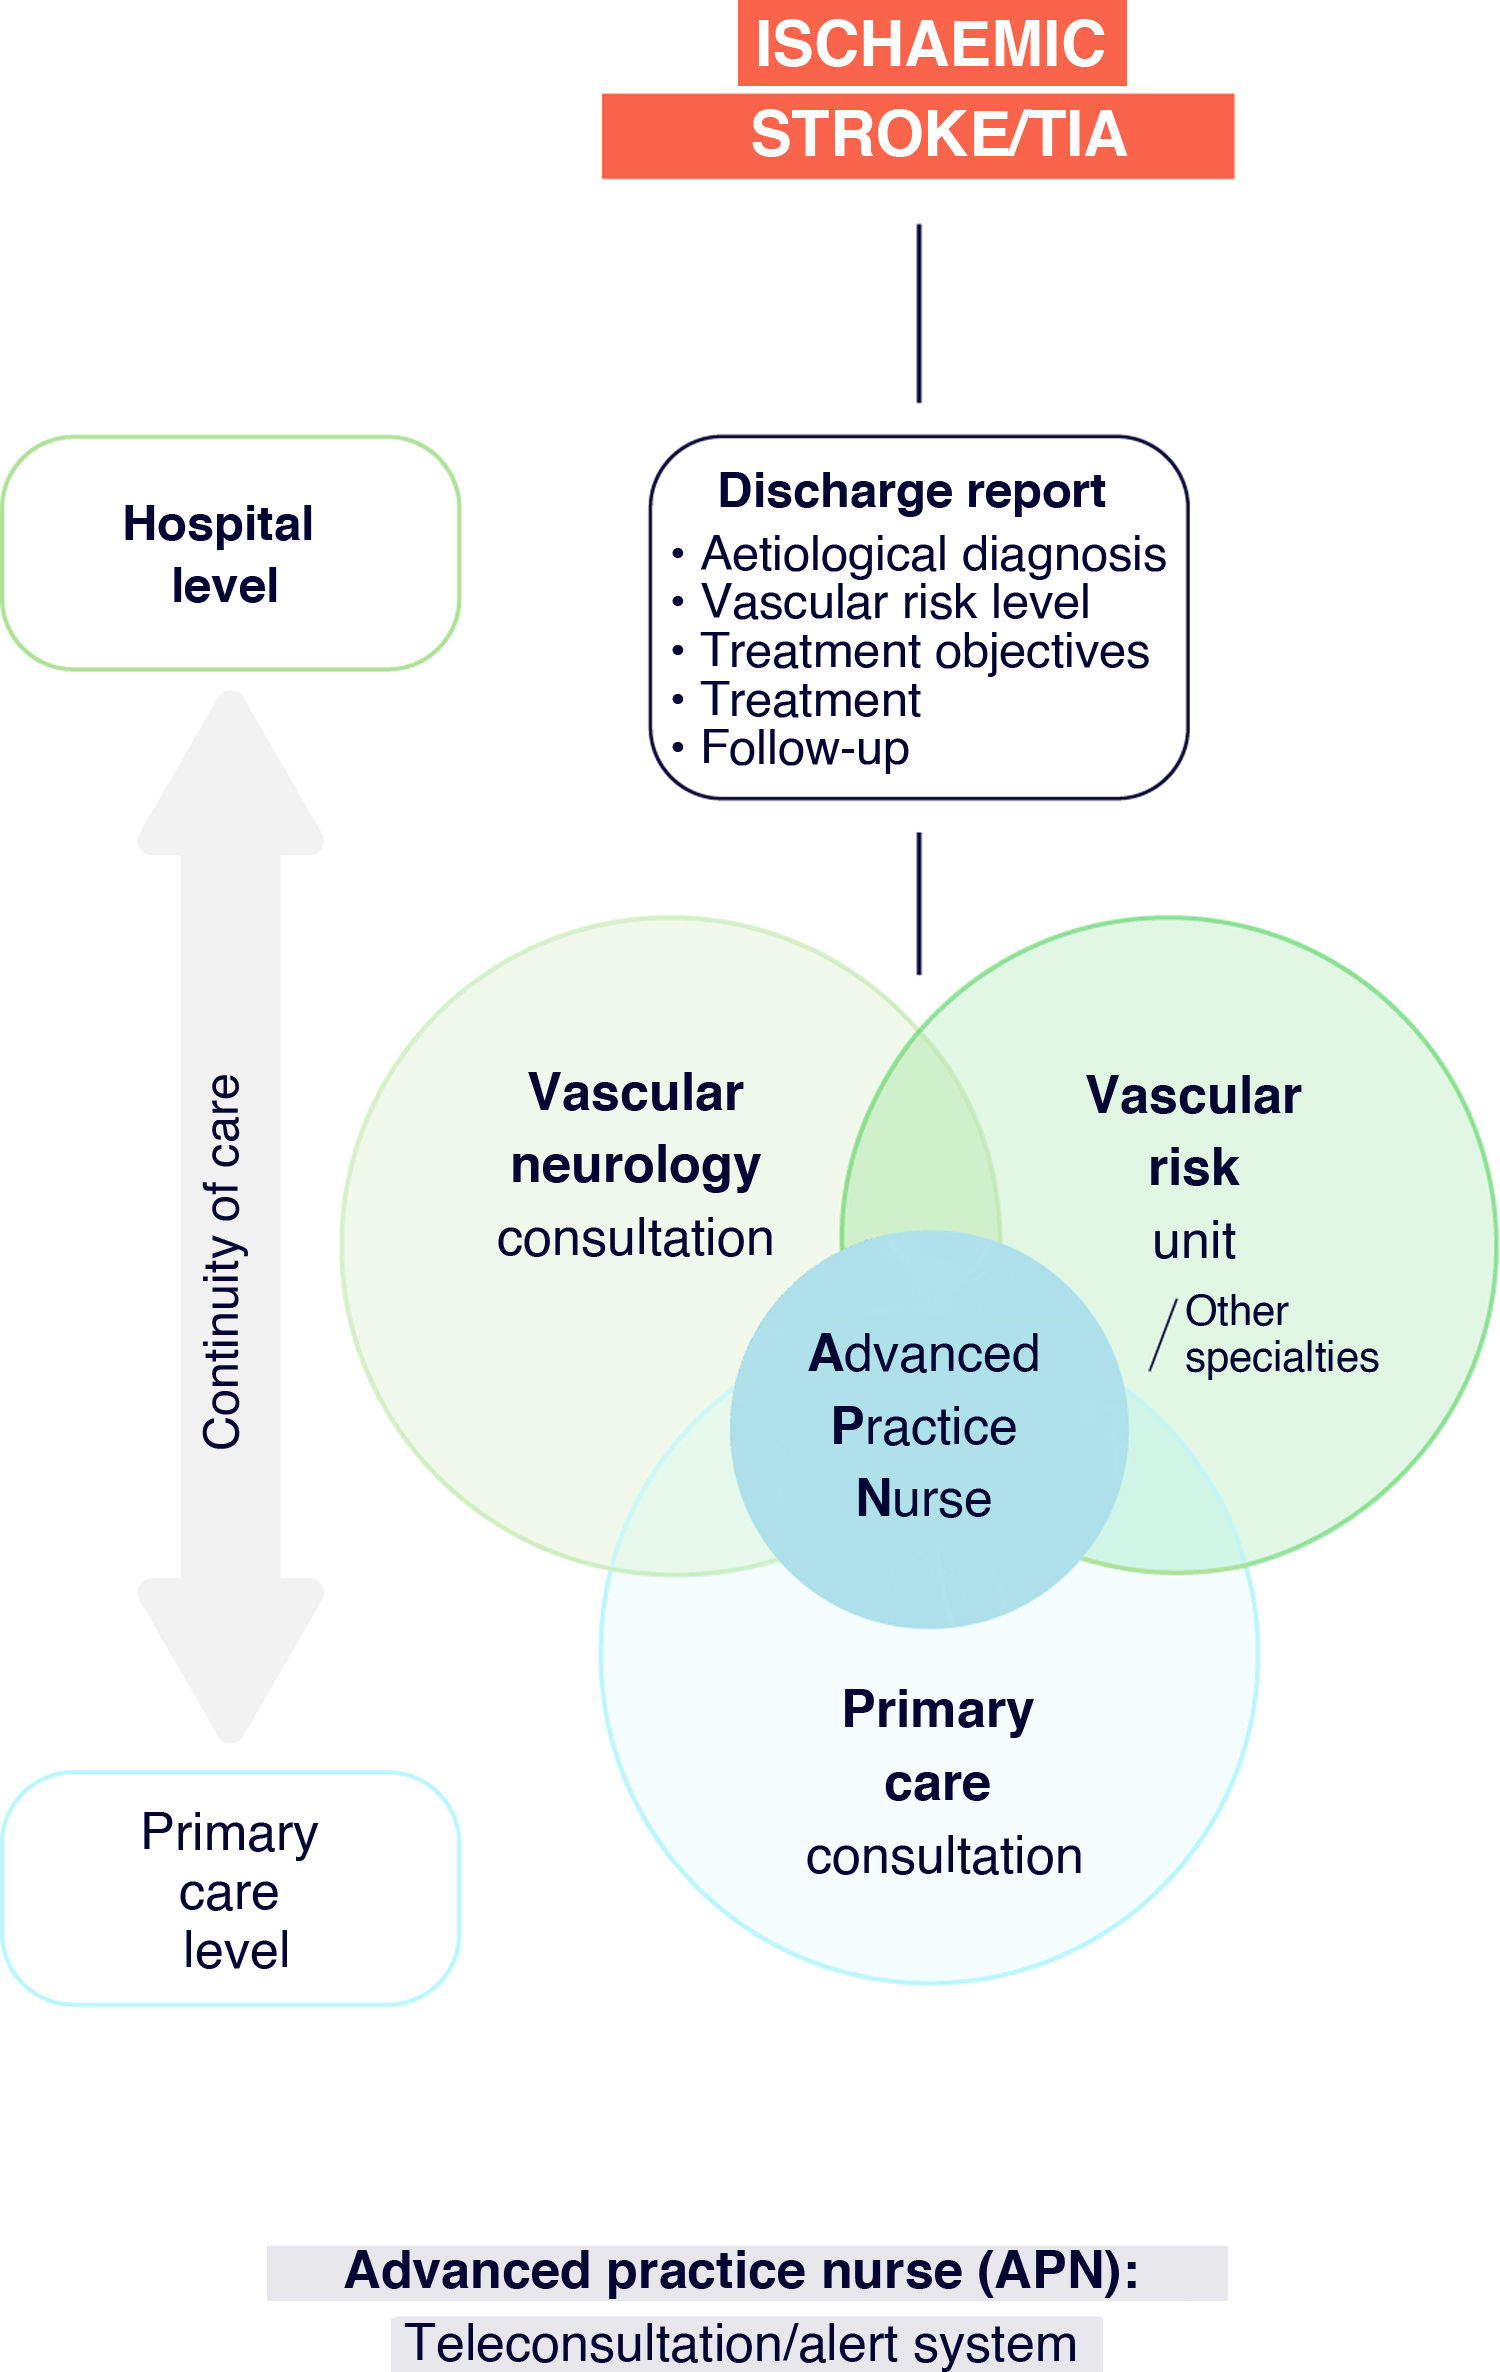
Patients with stroke/TIA should be followed up at a specialised vascular neurology consultation or by neurologists specialising in the management of patients with vascular disease (or stroke). When these options are not available, the ideal solution is to create a specialised clinic for this type of patients or, failing this, to refer patients to a vascular risk consultation or to other vascular specialties, when appropriate. Nonetheless, continuity of care is essential; to ensure this continuity from the primary care level, thus improving prevention and avoiding recurrent vascular events, it is crucial to issue a full discharge report including aetiological diagnosis, level of vascular risk, therapeutic objectives, treatment, and patient follow-up. Advanced practice nurses play a central role in coordinating follow-up and the treatments the patient receives from different professionals at different levels of care (Fig. 4).
Adherence to lipid-lowering therapy
Treatment adherence is a crucial aspect of the management and follow-up of patients with vascular disease. A considerable percentage of patients under secondary preventive treatment have been shown not to achieve LDL-C targets, despite evidence supporting intensive reduction of LDL-C levels to prevent vascular events.61 The recent update of the REALITY study reports that prescription of lipid-lowering therapies decreases constantly from treatment onset, suggesting a loss of adherence.42 This lack of treatment adherence has been linked to increased risk of recurrent vascular events and mortality. Despite the existence of efficacious lipid-lowering therapies, therapeutic inertia and low adherence represent obstacles to lipid control in these patients.62
To improve treatment adherence and ensure that therapeutic objectives are attained, the implementation of more effective strategies is recommended, such as the use of drugs that require less frequent administration53,62 and the optimisation of clinical follow-up.53,63 In this regard, it has been suggested that the introduction of long-duration therapies contributes to reducing the annual medication burden and may promote greater adherence and improve clinical outcomes.62 This would be beneficial for patients with limited mobility, who are dependent, or who live in remote areas. Furthermore, supervision of administration by a healthcare professional facilitates treatment adherence and provides an opportunity for continuing education of patients and their family/caregivers about the importance of treatment adherence. During administration of the drug, the healthcare professional may explain the benefits of treatment, answer any questions, and address potential obstacles to adherence. This reinforcement of education at the time of treatment administration has been shown to be an effective strategy to achieve a sustained improvement in treatment persistence and adherence in patients with vascular disease.52 We also recommend the use of specific lipid control checklists, as well as health education, at all follow-up visits, to ensure treatment compliance and patient safety. An example of such an instrument is included in the Supplementary Material. Furthermore, a stratified approach based on individual risks and treatment response enables better secondary prevention in patients with stroke/TIA, optimising the control of risk factors and reducing the likelihood of recurrent vascular events.
Inclusion of inclisiran in management pathways for patients with stroke/transient ischaemic attackAn optimal care pathway for the management of dyslipidaemia should include a structured register including the onset of inclisiran treatment, ensuring correct administration and follow-up. The pathway should also incorporate a programme for promotion of healthy lifestyles, encouraging sustainable, long-term changes in diet and physical activity. Finally, supervised administration of the drug twice per year offers an opportunity to promote treatment adherence, maximising treatment benefits and optimising lipid control (Fig. 5).
Safety of patients with stroke/transient ischaemic attack when lowering target low-density lipoprotein cholesterol levels
Multiple studies have assessed the safety of intensive lipid-lowering therapy in patients with ischaemic stroke, with no evidence contraindicating a target LDL-C value < 55 mg/dL. In the subanalysis of patients with cerebrovascular disease from the ORION-9, -10, and -11 trials,50 in which 90% of the treated population had history of ischaemic stroke, no adverse events associated with inclisiran were reported, with the exception of injection site reactions in 3.6% of patients. Furthermore, no cases of haemorrhagic stroke were reported. Similarly, the FOURIER study37 detected no significant differences in the frequency of adverse events between the placebo and evolocumab groups (19.5% of patients with non-haemorrhagic stroke). However, the reduction in LDL-C was associated with a 21% decrease in the risk of stroke, and no significant increase was observed in haemorrhagic strokes.37 Furthermore, the hypothesis of potential cognitive involvement associated with extremely low LDL-C levels has been largely disproved. The EBBINGHAUS study,64 a subanalysis of data from the FOURIER clinical trial including over 1900 patients with vascular disease (mean age: 63 years), rigorously assessed cognitive function using standardised neuropsychological tests. The results showed that intensive reduction of LDL-C, even to levels below 25 mg/dL, was not associated with impairment of memory of other cognitive functions.64 These results were subsequently confirmed in the EBBINGHAUS open-label extension period,65 in which a total of 473 patients were followed up for a mean of 5.1 years (maximum, 7.2). Therefore, there is no evidence that achieving very low LDL-C levels has a negative impact on cognitive function.
The risk of new vascular events after intensive LDL-C reduction has not been evaluated as exhaustively in patients with history of haemorrhagic stroke as in patients with ischaemic stroke. Only one clinical trial has evaluated the risk of haemorrhagic stroke in patients with previous history of this type of stroke, finding a non-significant increase in risk compared to high-dose statin treatment.66,67 However, in patients with history of cerebral haemorrhage of non-hypertensive aetiology, or in elderly patients (> 75 years), LDL-C target values should be determined on an individual basis, according to the vascular risk factors listed in Fig. 1.
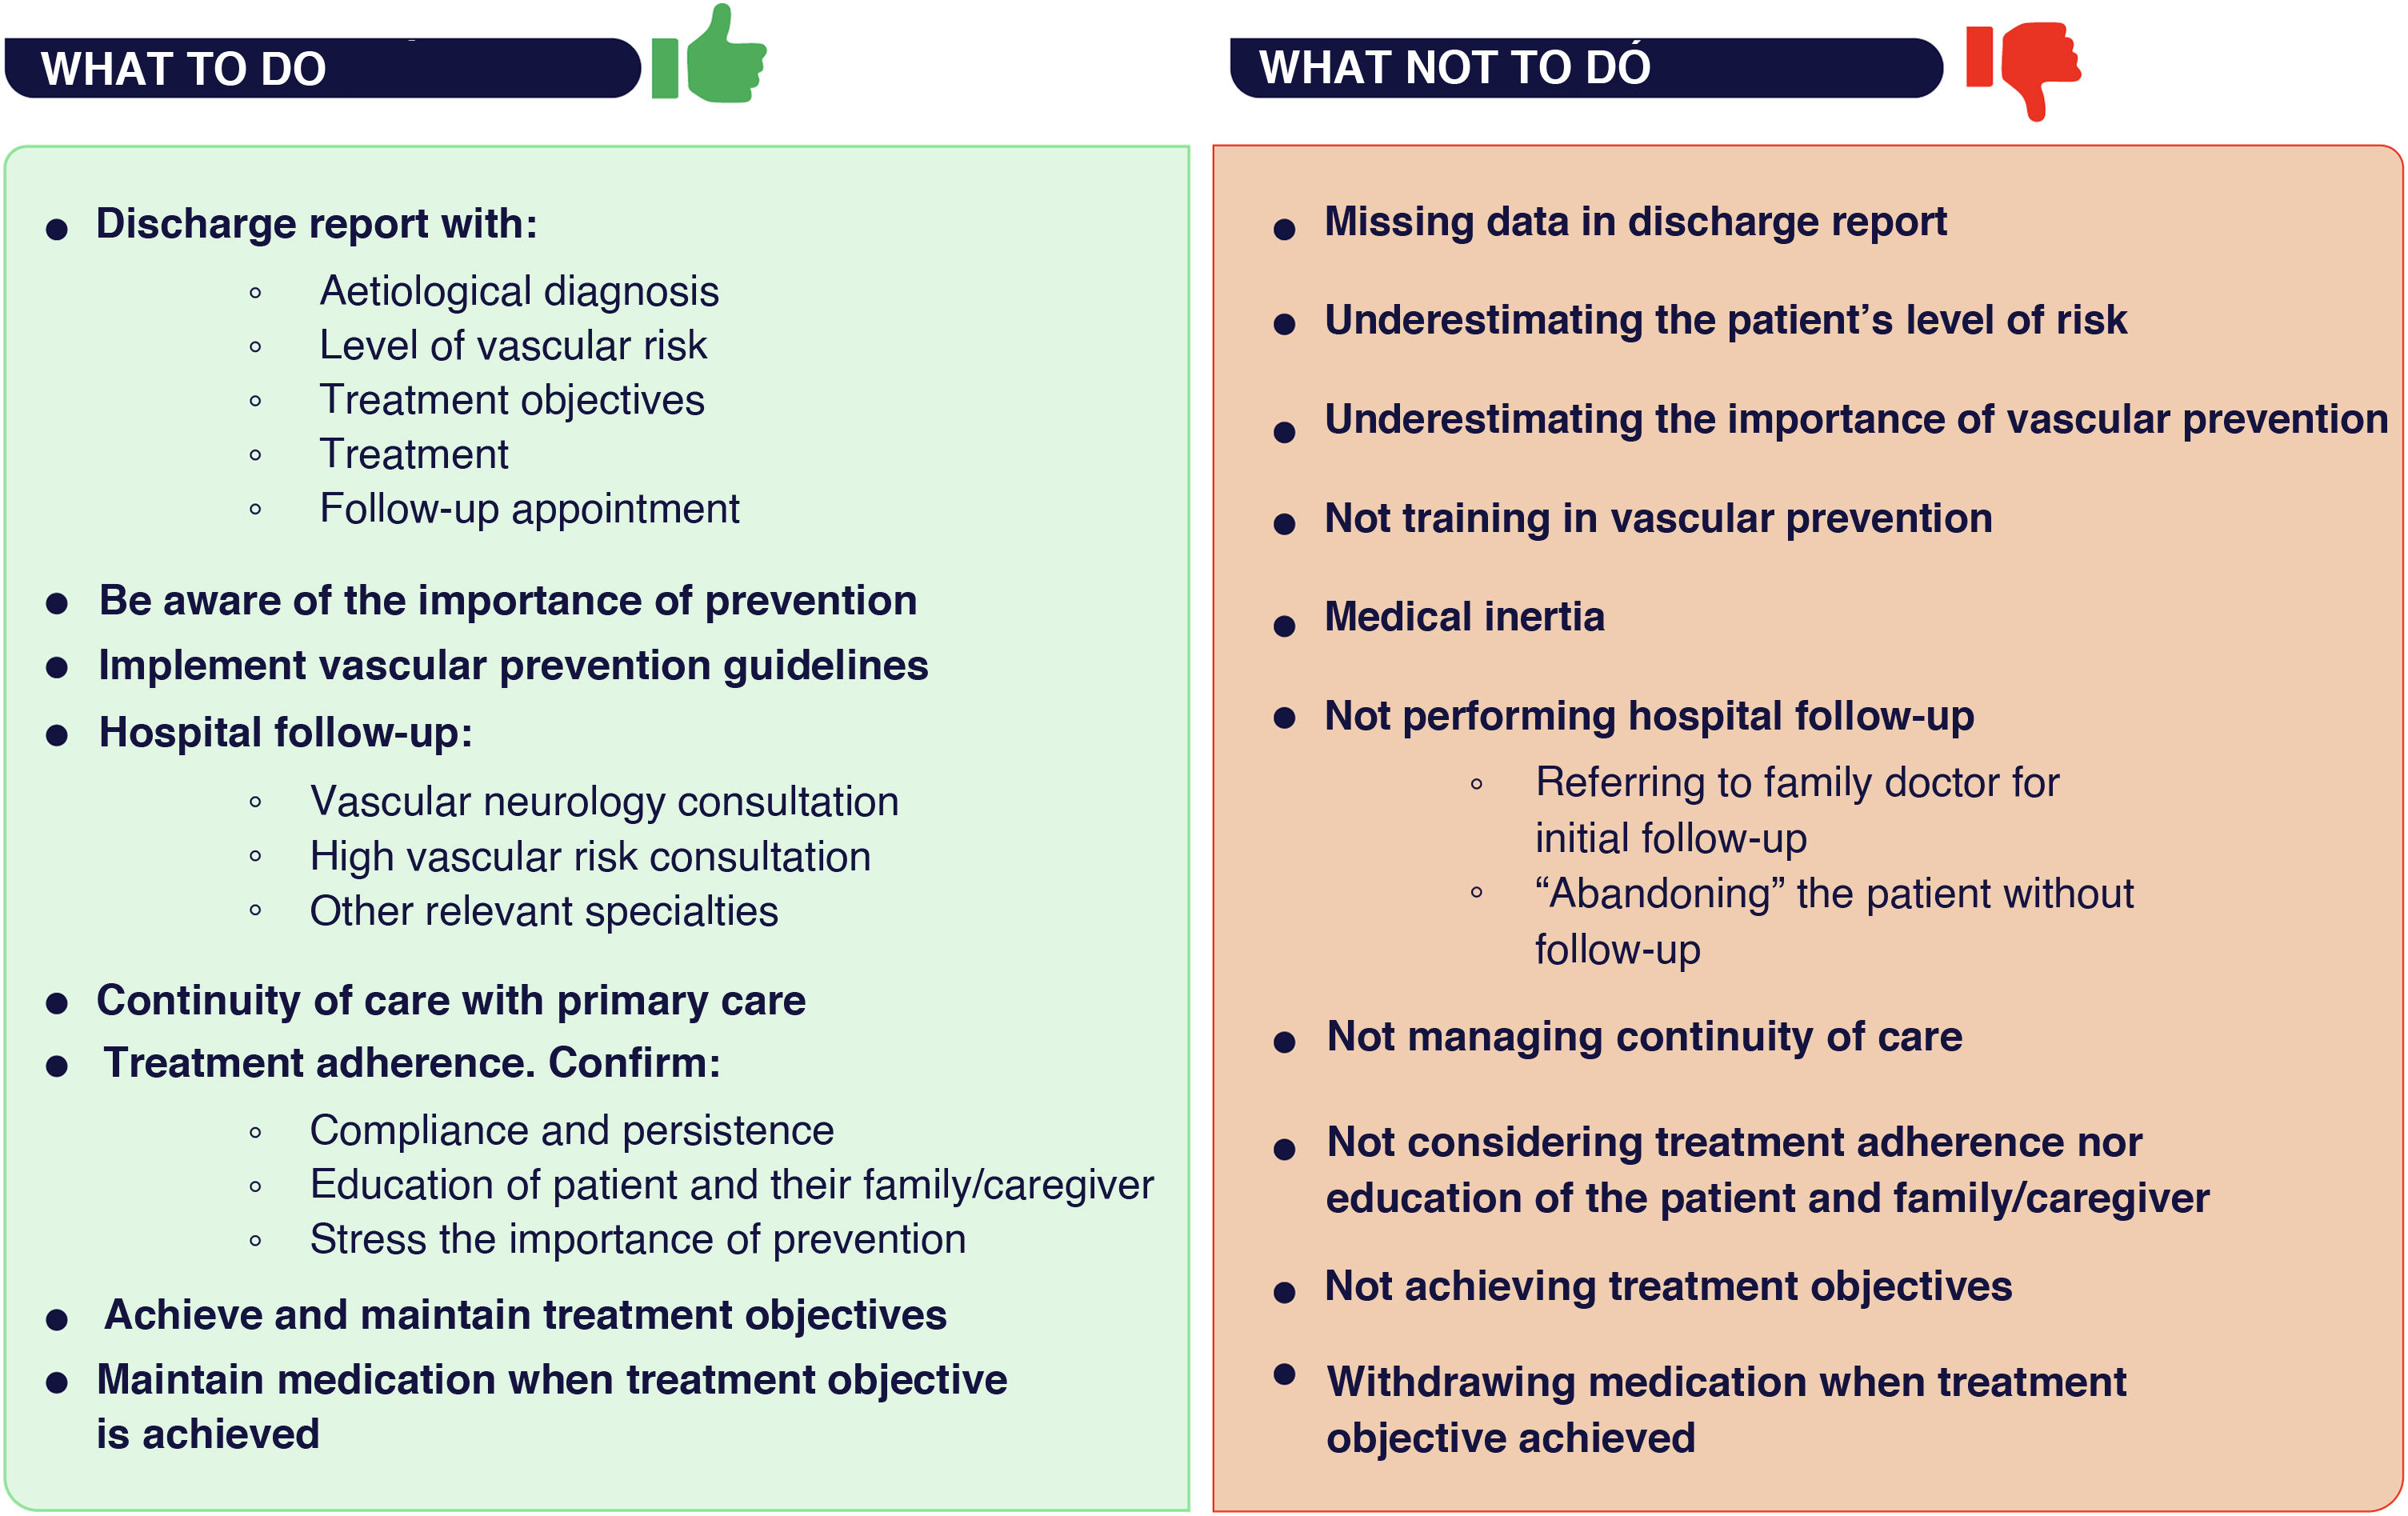
Key considerations for neurologists following up patients with stroke/transient ischaemic attackNeurologists attending patients with stroke/TIA should be aware of and trained in vascular event prevention, an essential pillar in secondary stroke prevention. These professionals are obliged to provide patients both with the most appropriate acute treatment and with suitable preventive treatment at hospital discharge, to control all vascular risk factors.
Increasing neurologists’ awareness of LDL-C targets is fundamental to improving the secondary prevention of ischaemic stroke. Given the demonstrated impact of intensive LDL-C reduction in decreasing the risk of recurrence, it is essential for neurologists to recognise the fundamental role of lipid control in the follow-up of these patients.26 Through awareness of this, specialists may assess the need for systematic monitoring of LDL-C levels, identify patients requiring greater treatment intensity, and prioritise achieving the target levels recommended in practice guidelines. Therefore, including dyslipidaemia management in neurological practice is a key step towards optimising long-term vascular prognosis. This requires long-term planning of preventive treatment; therefore, these patients should be referred to vascular neurology consultations, or failing this, to vascular risk consultations, and the appropriate vascular specialties. Continuity of care at primary care centres is fundamental to ensuring patients receive care and remain under follow-up.
Fig. 6 presents the recommendations for neurologists on how to proceed in the management of patients with stroke/TIA.
Conclusions
Stroke represents a priority public health problem in Spain, due to its high incidence and associated rates of mortality and disability. Controlling dyslipidaemia, the main causal factor of atherosclerosis, may prevent the recurrence of stroke/TIA. Based on current evidence, an LDL-C level < 55 mg/dL is generally recommended as a therapeutic objective for patients with stroke/TIA, although control of dyslipidaemia continues to be insufficient in clinical practice due to such factors as poor treatment adherence and therapeutic inertia. In this context, inclisiran, a small interfering RNA targeting PCSK9, enables a sustained reduction of LDL-C of up to 55%, with administration every 6 months (following the initial dose and the subsequent 3-month dose) and good tolerability, facilitating treatment adherence.
To guarantee the integrated management of LDL-C in patients with stroke/TIA, intensive treatment strategies, tailored approaches, and robust continuity of care are recommended to optimise secondary prevention. Inclisiran is a new therapy that plays a key role in improving lipid control and treatment adherence in these patients, in accordance with national and international recommendations on achieving treatment objectives and reducing the burden of vascular disease. Optimal integration of this new therapeutic tool may help to significantly improve outcomes in patients with stroke/TIA.
CRediT authorship contribution statementAll authors contributed substantially to data collection, analysis, and interpretation; drafting of the manuscript; and critical revision of its intellectual content; and approved the final version of the article.
Publication ethics1. Did your study involve animal experiments?
No
2. Did your study involve human participants or patients?
No
3. Did your study include a clinical trial?
No
4. Are all the data presented in the figures and tables reported in the results and conclusion sections?
Yes
FundingNovartis Farmacéutica S.A. provided funding for expert meetings and drafting of the manuscript. The opinions, interpretations, and conclusions expressed are solely the authors’ own.
M. Freijo-Guerrero has received fees from Daichii-Sankyo and Novartis. P. Cardona has been remunerated for contributions to training and materials for Amgen and Novartis. M. Castellanos has received consultancy fees from Amgen and Novartis, and lecture honoraria from Daichii-Sankyo. R. De Torres-Chacón has received consultancy fees from Amgen and Novartis. A. Gil-Núñez has received consultancy fees from Amgen and Novartis. M. Guillán has received fees for consulting and providing expert testimony for Amgen and Novartis. P. Martínez-Sánchez has received consultancy fees from Novartis. E.J. Palacio-Portilla has received consultancy fees and lecture honoraria from Amgen, Esteve, MSD, Novartis, and Rovi. F. Purroy has received consultancy fees from Novartis. T. Segura has received consultancy fees from Amgen, Boehringer Ingelheim, Laboratorios Ferrer, and Novartis.
The authors would like to thank Javier Rodríguez Cobos of Evidenze Health España S.L.U. for his editorial assistance and medical writing services.


