


Ischemic heart disease remains a leading cause of mortality, with women facing unique social and clinical challenges that impact outcomes. This study aimed to examine sex and gender specific differences in social and clinical predictors of long-term outcomes in coronary artery disease.
Materials and methodsThis prospective cohort study used the RECORVAL registry, including patients with coronary artery disease undergoing coronary angiography. Clinical data were extracted from electronic health records, and social determinants were collected via a structured questionnaire. Outcomes included all-cause mortality, cardiovascular mortality, myocardial infarction, revascularization, stroke, major bleeding and a composite endpoint (cardiovascular death, myocardial infarction or revascularization). Sex-stratified Kaplan–Meier curves, Fine–Gray competing risk models, and multivariate Cox regression models adjusted for social and clinical variables were used.
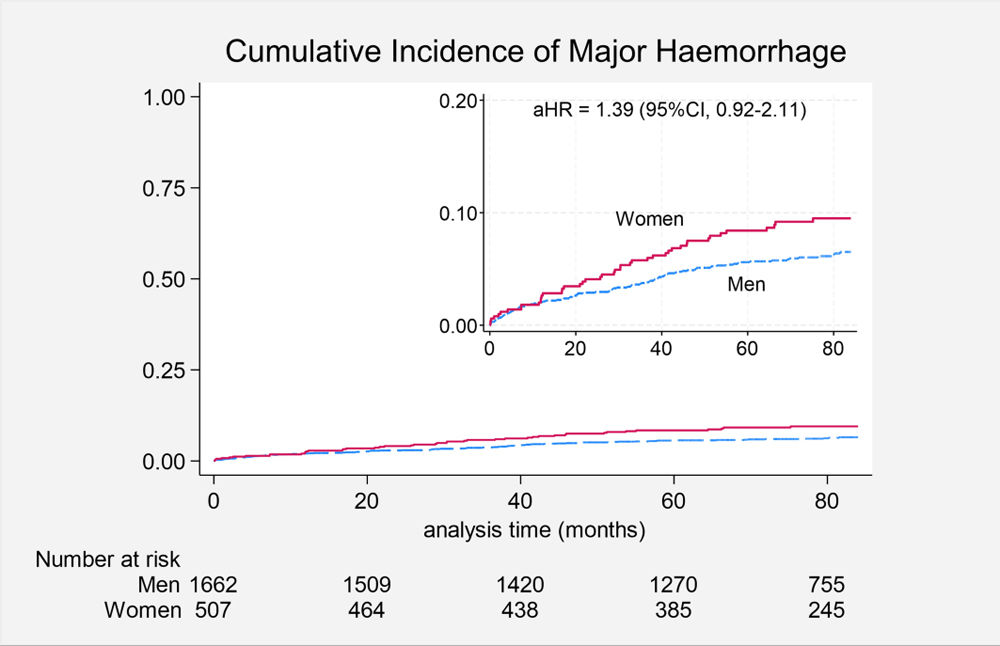
ResultsAmong 2219 patients (23.4% women) followed for a median of 2421 days, women were older (68.5 vs. 64.3 years) and had greater social disadvantages, including lower education, employment, and internet access. Percutaneous intervention rates were similar, but coronary artery bypass grafting was less frequent in women (3.5% vs. 6.0%). No significant differences were observed in all-cause or cardiovascular mortality (aHR 0.80; 95% CI 0.51–1.24). Women showed a non-significant trend toward lower composite endpoint risk (aHR 0.81; 95% CI 0.64–1.04), lower myocardial infarction and revascularization risk, and higher major bleeding (aHR 1.39; 95% CI 0.92–2.11).
ConclusionsWomen face significant social disadvantages requiring personalized prevention addressing gender-specific risks. Similar mortality rates suggest improving equity, while differing ischemic–haemorrhagic profiles call for sex-tailored therapy to improve outcomes.
La cardiopatía isquémica es una causa principal de mortalidad, y las mujeres se enfrentan a desafíos sociales y clínicos que afectan su pronóstico. Este estudio analiza las diferencias por sexo y género en predictores sociales y clínicos de resultados a largo plazo en enfermedad coronaria.
Materiales y métodosCohorte prospectiva del registro RECORVAL, de pacientes con enfermedad coronaria sometidos a coronariografía. Los datos clínicos se obtuvieron de registros electrónicos, y los sociales mediante cuestionario estructurado. Se evaluaron mortalidad global y cardiovascular, infarto de miocardio, revascularización, ictus, hemorragia mayor y un evento combinado (muerte cardiovascular, infarto o revascularización). Se utilizaron las curvas de Kaplan-Meier por sexo, modelos Fine-Gray para riesgos competitivos y la regresión de Cox multivariante ajustado por variables sociales y clínicas.
ResultadosDe 2.219 pacientes (23,4% mujeres) con seguimiento medio de 2.421 días, las mujeres eran mayores (68,5 vs. 64,3 años) y presentaban desventajas sociales: menor educación, empleo y acceso a Internet. La tasa de angioplastia fue similar, pero el bypass coronario fue menor (3,5 vs. 6,0%). No hubo diferencias en mortalidad global o cardiovascular (aHR: 0,80; IC 95%: 0,51-1,24). Se observó una tendencia no significativa a menor riesgo del evento combinado (aHR: 0,81; IC 95%: 0,64-1,04), de infarto y revascularización, y más riesgo de hemorragia mayor (aHR: 1,39; IC 95%: 0,92-2,11).
ConclusionesLas mujeres presentan desventajas sociales que requieren prevención personalizada. La igualdad en mortalidad sugiere mayor equidad, mientras que las diferencias en el riesgo isquémico-hemorrágico resaltan la necesidad de terapias específicas por sexo.
Cardiovascular disease (CVD) remains the foremost cause of morbidity and mortality worldwide, with ischemic heart disease (IHD) constituting its principal subtype. In Spain, according to the National Statistics Institute (INE), CVD accounted for 24.4% of deaths in 2023, with IHD causing 27,734 deaths.1 Although IHD remains more prevalent in men globally, the gap between sexes has narrowed over time, with women experiencing relatively greater increases in IHD burden, particularly in low-resource settings.2 In Spain, the mortality rate from IHD in 2023 was 73.4 per 100,000 in men compared to 41.6 per 100,000 in women.1 These differences highlight the need to explore sex and gender specific factors influencing IHD outcomes.
Beyond traditional clinical risk factors such as hypertension, diabetes, dyslipidemia, and smoking, social determinants of health, including socioeconomic status, psychosocial stressors, and social support, play a significant role in cardiovascular prognosis. Large prospective studies have shown that adverse social conditions are associated with worse outcomes, yet these factors are rarely integrated into clinical risk prediction models.3–10 Women face unique social challenges, including higher exposure to chronic stressors (e.g., caregiving, economic insecurity) and reduced access to healthcare. These factors may interact with biological processes, contributing to gender-specific vulnerabilities in cardiovascular outcomes.2,11,12
Despite increasing evidence, gender-specific interactions between social determinants and IHD outcomes remain insufficiently explored, with relatively few studies focusing on primary and secondary prevention from a policy perspective, highlighting a notable research gap.13 To address this, we leverage the RECORVAL registry, a prospective cohort of patients with coronary artery disease in Cantabria, Spain.3 Our aim is to elucidate sex and gender specific differences in clinical and social predictors of adverse outcomes, including mortality, myocardial infarction (MI), and major bleeding events, to improve risk stratification and inform the development of tailored secondary prevention strategies that reduce disparities and enhance prognosis.
MethodsStudy design and settingThis is a single-centre, prospective, observational cohort study conducted in Cantabria, Spain. It is based on the RECORVAL registry, which includes consecutive patients with coronary artery disease undergoing coronary angiography between 2016 and 2020. For the present analysis, follow-up was extended until 2025, with a median follow-up duration of 2421 days (interquartile range [IQR] 1954–2737 days). Clinical events were prospectively collected during follow-up and adjudicated by a panel of investigators (MR, JZ, EC, IC) according to predefined criteria (Supplementary Table 1). The study adhered to Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) guidelines of 201914 a was approved by the local Research Ethics Committee. Written informed consent was obtained from all participants prior to inclusion.
ParticipantsInclusion criteria were age >18 years; diagnosis of acute or chronic coronary artery disease according to the 2023 European Society of Cardiology (ESC) Guidelines for acute coronary syndromes15 and the 2019 ESC Guidelines for chronic coronary syndromes16 and survival to the diagnostic coronary angiography procedure. Exclusion criteria included major cognitive impairment or physical disability precluding questionnaire completion, as judged by the investigator. Patients were consecutively recruited. Coronary angiography was performed according to clinical indication by the referring cardiologist. All patients were interviewed face-to-face by the same investigator in order to complete a structured social and behavioural questionnaire.
Data sourceSocial and behavioural variables were collected using a bespoke, investigator-designed structured questionnaire, previously described in the supplementary material of the preceding RECORVAL publication.3 Clinical follow-up data were obtained from the electronic medical records of the regional health system, which integrates all levels of care, including primary care. For participants residing outside the region or lacking recent health records, additional efforts were made to complete follow-up through repeated telephone contact. These comprehensive strategies resulted in a very low rate of missing data (1.73%), which were managed using complete-case analysis.
Exposure variables- 1.
Clinical variables: Baseline clinical data included age, sex, weight, height, body mass index (BMI), diabetes mellitus (DM), and treatment type of DM, arterial hypertension, dyslipidaemia, smoking status and history, chronic kidney disease, left ventricular ejection fraction (LVEF), family history of IHD, previous MI, coronary artery bypass grafting (CABG), and percutaneous coronary intervention (PCI). The revascularization strategy: percutaneous, surgical, or conservative, was also recorded. The sex of participants was determined biologically and consistently matched their self-reported gender identity, with no discrepancies observed.
- 2.
Social and behavioural variables: A wide range of social determinants were recorded through a structured questionnaire. These included:
- -
Lifestyle: illicit drug use, alcohol consumption, diet (including sodium intake), and physical activity.
- -
Health literacy and self-care: treatment knowledge, adherence, self-management and number of planned annual medical visits.
- -
Socioeconomic status: educational attainment, employment status, marital status, household composition, living environment (urban/rural), and the recently added pharmaceutical co-payment category (TIS) as a proxy for socioeconomic level. Although postal code was also collected, it was not analysed in this study.
- -
Digital connectivity and social network: mobile phone ownership, internet access, social media use.
- -
Social environment and support: number of children, pet ownership, domestic responsibilities, availability of family support.
- -
Clinical outcomes were prospectively collected through electronic medical records and defined according to strict criteria detailed in Supplementary Table 1. A dedicated group of investigators, following a standardized and pre-specified adjudication protocol, systematically reviewed and adjudicated all clinical events to ensure consistency and accuracy. Outcomes included death from any cause, cardiovascular death, MI, coronary revascularization, stroke and major haemorrhage. A composite endpoint was defined as cardiovascular death, MI, or coronary revascularization.
Statistical analysisContinuous variables are presented as mean±standard deviation or median and IQR according to their distribution. Categorical variables are reported as frequencies (percentages). Baseline characteristics were compared by sex using Student's t-test for normally distributed continuous variables, the Wilcoxon–Mann–Whitney test for non-normally distributed continuous or ordinal variables, and the chi-square test for categorical variables. To compare outcomes between men and women, sex-stratified Kaplan–Meier survival curves and log-rank tests were used. Additionally, competing risks analyses were performed using the Fine–Gray subdistribution hazard model to account for competing events. Multivariate Cox proportional hazards regression models were built to identify independent predictors of outcomes, including sex as a main exposure variable and adjusting for both clinical and social variables. Variables with p<0.10 in univariate analysis and those considered clinically relevant were considered for inclusion in multivariable models. The proportional hazards assumption was assessed using Schoenfeld residuals. Interaction terms for sex were evaluated but were not statistically significant and therefore not included in the final models. To reduce the risk of overfitting, the number of predictors was limited based on the number of outcome events (events per variable >10). Multicollinearity was assessed using variance inflation factors (VIF), with no significant collinearity detected. Adjusted hazard ratios (aHRs) and 95% confidence intervals (CIs) were reported. All analyses were performed using Stata statistical software version 18.0 (StataCorp, College Station, TX, USA).
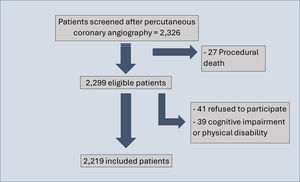
ResultsGeneral and clinical characteristicsThe cohort comprised 2219 patients (Supplementary Fig. 1), of whom 520 (23.4%) were women and 1699 (76.6%) were men. Women were significantly older than men (68.5±11.9 vs. 64.3±11.3 years; p<0.001). BMI was similar between sexes, and the prevalence of obesity (BMI ≥30kg/m2) did not differ significantly (36.5% vs. 33.9%, p=0.269). Smoking status showed marked sex and gender-based differences. A significantly higher proportion of women were never-smokers (50.1% vs. 20.3%; p<0.001), while former smoking was more frequent among men (22.4%; vs. 51.5%; p<0.001). Current smoking prevalence was similar between groups. Family history of IHD and prevalence of DM were similar across sexes. Women presented a slightly higher prevalence of hypertension (68.9% vs. 64.1%; p=0.046), whereas dyslipidaemia rates were comparable. Chronic kidney disease was more common among women (13.2% vs. 9.6%; p=0.021). Mean LVEF was higher in women, and they were less likely to have LVEF ≤40% (22.5% vs. 27.4%; p=0.025). Pre-treatment haemoglobin levels were significantly lower in women. History of prior acute MI was more frequent among men (15.6% vs. 20.3%; p=0.017), as were previous percutaneous interventions and revascularization surgeries. Regarding the management of the current ischemic event, both sexes were predominantly treated percutaneously (77.1% vs. 76.6%; p=0.816), but surgery was less frequent in women (3.5% vs. 6.0%; p=0.024), whereas conservative management did not differ significantly (Table 1).
General and clinical characteristics stratified by gender.
| Variable | Global(n=2,219) | Men(n=1,699) | Women(n=520) | p-Value |
|---|---|---|---|---|
| General variables | ||||
| Age (years) | 65.3±11.6 | 64.3±11.3 | 68.5±11.9 | <0.001 |
| Body mass index (kg/m2) | 28.5±4.5 | 28.6±4.3 | 28.4±5.2 | 0.333 |
| Obesity (BMI ≥30kg/m2) | 766 (34.5%) | 576 (33.9%) | 190 (36.5%) | 0.269 |
| Clinical variables | ||||
| Smoking (detail) | ||||
| Never smoker | 603 (27.3%) | 343 (20.3%) | 260 (50.1%) | <0.001 |
| Former smoker | 988 (44.7%) | 872 (51.5%) | 116 (22.4%) | <0.001 |
| Current smoker | 620 (28.0%) | 477 (28.2%) | 143 (27.6%) | 0.777 |
| Family history of ischemic heart disease | 888 (40.0%) | 665 (39.2%) | 223 (42.9%) | 0.130 |
| Diabetes mellitus | 616 (27.8%) | 482 (28.4%) | 134 (25.8%) | 0.247 |
| DM treatment | ||||
| Diet | 11 (1.9%) | 8 (1.7%) | 3 (2.4%) | 0.617 |
| Oral antidiabetic drugs | 454 (76.3%) | 356 (75.9%) | 98 (77.8%) | 0.661 |
| Insulin | 130 (21.9%) | 105 (22.4%) | 25 (19.8%) | 0.539 |
| Hypertension | 1,444 (65.19%) | 1,086 (64.07%) | 358 (68.85%) | 0.046 |
| Dyslipidaemia | 1,368 (61.96%) | 1,049 (62.14%) | 319 (61.35%) | 0.743 |
| Chronic kidney disease | 230 (10.43%) | 162 (9.60%) | 68 (13.15%) | 0.021 |
| Left ventricular ejection fraction (%) | 48.5±12.2 | 48.1±12.4 | 49.9±11.7 | 0.006 |
| Left ventricular ejection fraction ≤40% | 583 (26.3%) | 466 (27.4%) | 117 (22.5%) | 0.025 |
| Hemoglobin pre-treatment (g/dL) | 14.0±1.7 | 14.3±1.7 | 13.1±1.4 | <0.001 |
| History of previous AMI | 425 (19.2%) | 344 (20.3%) | 81 (15.6%) | 0.017 |
| Previous revascularization surgery | 50 (2.3%) | 45 (2.7%) | 5 (1.0%) | 0.022 |
| Previous angioplasty | 604 (27.3%) | 494 (29.2%) | 110 (21.2%) | <0.001 |
| Treatment performed | ||||
| Percutaneous | 1,699 (76.7%) | 1,298 (76.6%) | 401 (77.1%) | 0.816 |
| Surgery | 120 (5.4%) | 102 (6.0%) | 18 (3.5%) | 0.024 |
| Conservative | 395 (17.8%) | 294 (17.4%) | 101 (19.4%) | 0.281 |
This table summarizes general and clinical variables for a cohort of 2219 patients. Categorical variables are presented as frequency and percentage. Quantitative variables are presented as mean±standard deviation. AMI: acute myocardial infarction; BMI: body mass index; DM: diabetes mellitus.
Consumption of other toxic substances was less common in women (1.0% vs. 3.2%; p=0.005), and they also followed a salted diet less frequently (38.6% vs. 50.7%; p<0.001). Exercise habits differed significantly: men more often engaged in daily activity, whereas inactivity was more prevalent among women (46.4% vs. 33.2%; p<0.001). The average number of annual health check-ups was similar between sexes. Adherence to pharmacological treatment was high overall, though slightly higher in women (96.8% vs. 94.2%; p=0.031). Knowledge of and ability to manage their treatment did not significantly differ. Educational attainment varied markedly: a higher proportion of men had secondary or higher education, while women more frequently reported no formal education (13.0% vs. 3.8%; p<0.001). Women were significantly less likely to be actively employed (21.6% vs. 38.3%; p<0.001) and less likely to have a partner. They more frequently lived alone (19.5% vs. 12.9%; p<0.001) and were more often part of large households (≥3 children) compared to men (Table 2 and Fig. 1).
Social characteristics stratified by gender.
| Social variable | Global(n=2,219) | Men(n=1,699) | Women(n=520) | p-Value |
|---|---|---|---|---|
| Other toxic substances | 60 (2.7%) | 55 (3.2%) | 5 (1.0%) | 0.005 |
| Salted diet | 1,057 (47.8%) | 858 (50.7%) | 199 (38.6%) | <0.001 |
| Exercise | ||||
| Daily | 1,124 (50.7%) | 915 (54.0%) | 209 (40.3%) | <0.001 |
| 2–3 times/week | 287 (13.0%) | 218 (12.9%) | 69 (13.3%) | 0.793 |
| None | 804 (36.3%) | 563 (33.2%) | 241 (46.4%) | <0.001 |
| Number of annual check-ups | 1.2±0.4 | 1.2±0.4 | 1.2±0.4 | 0.100 |
| Knows their treatment | 1,736 (90.6%) | 1,310 (90.3%) | 426 (91.2%) | 0.574 |
| Manages their treatment | 1,739 (90.6%) | 1,306 (89.9%) | 433 (92.8%) | 0.074 |
| Adheres to treatment | 1,806 (94.8%) | 1,360 (94.2%) | 446 (96.8%) | 0.031 |
| Education | ||||
| Secondary or higher | 943 (42.8%) | 790 (46.7%) | 153 (29.7%) | <0.001 |
| Primary | 1,131 (51.3%) | 836 (49.4%) | 295 (57.3%) | 0.002 |
| None | 132 (6.0%) | 65 (3.8%) | 67 (13.0%) | <0.001 |
| Active occupation | 640 (29.0%) | 529 (38.3%) | 111 (21.6%) | <0.001 |
| Marital status (has a partner) | 1,559 (70.6%) | 1,278 (75.5%) | 281 (54.6%) | <0.001 |
| Urban residence | 949 (43.0%) | 715 (42.3%) | 234 (45.4%) | 0.202 |
| Lives alone | 317 (14.4%) | 217 (12.9%) | 100 (19.5%) | <0.001 |
| No family support | 57 (2.6%) | 49 (2.9%) | 8 (1.6%) | 0.091 |
| Household chores | ||||
| Themselves | 966 (44.1%) | 601 (35.8%) | 365 (71.3%) | <0.001 |
| Family | 1,107 (50.5%) | 1,013 (60.3%) | 94 (18.4%) | <0.001 |
| Caregiver | 118 (5.4%) | 65 (3.87%) | 53 (10.4%) | <0.001 |
| Large householda | 635 (28.8%) | 452 (26.8%) | 183 (35.6%) | <0.001 |
| Number of children | ||||
| None | 302 (13.7%) | 252 (15.0%) | 50 (9.7%) | 0.003 |
| 1–2 children | 1263 (57.4%) | 982 (58.2%) | 281 (54.7%) | 0.151 |
| 3–4 children | 548 (24.9%) | 396 (23.5%) | 152 (29.6%) | 0.005 |
| ≥5 children | 87 (4.0%) | 56 (3.3%) | 31 (6.0%) | 0.006 |
| Have a pet | 831 (37.8%) | 647 (38.4%) | 184 (35.8%) | 0.283 |
| Means of transport | ||||
| Walking | 1,077 (48.5%) | 799 (47.0%) | 278 (53.5%) | 0.010 |
| Public | 212 (9.6%) | 138 (8.1%) | 74 (14.2%) | <0.001 |
| Private | 930 (41.9%) | 762 (44.9%) | 168 (32.31%) | <0.001 |
| Uses social media | 655 (29.5%) | 520 (30.6%) | 135 (26.0%) | 0.042 |
| Mobile phone | 1,561 (70.7%) | 1,221 (72.2%) | 340 (66.0%) | 0.007 |
| Home internet access | 1,684 (77.3%) | 1,346 (80.6%) | 338 (66.3%) | <0.001 |
| Exempt from contributionb | 424 (19.8%) | 306 (18.7%) | 118 (23.4%) | 0.021 |
This table summarizes social variables for a cohort of 2219 patients. Categorical variables are presented as frequency and percentage. Quantitative variables are presented as mean±standard deviation.

Urban residence rates were similar between men and women. Significant differences were observed in household responsibilities: women more frequently performed household chores themselves (71.3% vs. 35.8%; p<0.001), whereas men relied more often on family support. Use of caregivers was higher among women (10.4% vs. 3.9%; p<0.001). Regarding mobility, women more commonly reported walking as their main mode of transportation and use of public transport (14.2% vs. 8.1%; p<0.001), while men predominantly used private vehicles. Use of digital tools differed by gender: women reported lower use of social media (26.0% vs. 30.6%; p=0.042), mobile phones (66.0% vs. 72.2%; p=0.007), and home internet access (66.3% vs. 80.6%; p<0.001). Finally, a higher proportion of women were exempt from pharmaceutical copayment due to socioeconomic criteria (23.4% vs. 18.7%; p=0.021) (Table 2 and Fig. 1).
Some social disparities between women and men were partially explained by the older age of women in our cohort. After adjusting for age, associations with other toxic substances, active occupation, and daily exercise were attenuated and no longer statistically significant, whereas most differences – such as educational attainment, household responsibilities, living alone, transport mode, digital access, and exemption from pharmaceutical copayments – remained significant (Supplementary Table 2).
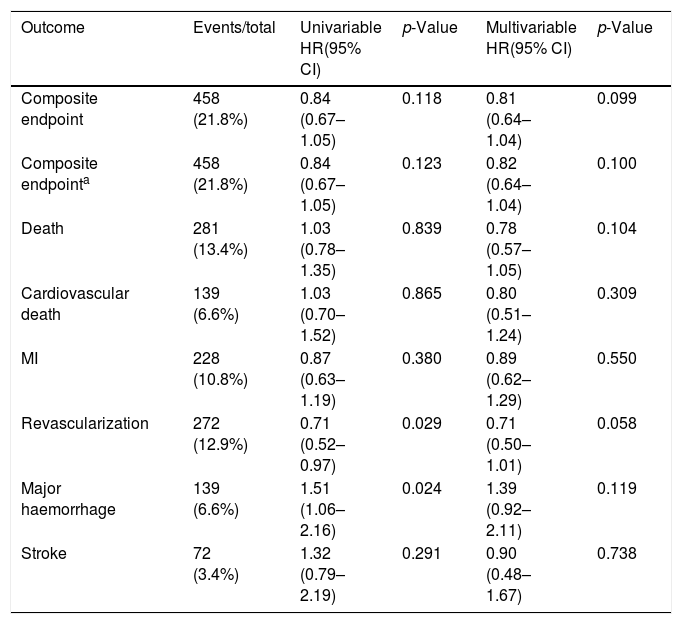
Clinical outcomes by sexDuring a median follow-up period of 2421 days (IQR 1956–2737), 95.0% of patients (n=2102) completed the follow-up, whereas 5.0% (n=111) were lost to follow-up. There were no statistically significant differences in loss to follow-up rates between women (4.24%) and men (5.25%) (p=0.354). During this period, 458 composite endpoint events (21.8%), 281 deaths (13.4%), 139 cardiovascular deaths (6.6%), 228 new infarctions (10.8%), 272 revascularizations (12.9%), 139 major haemorrhages (6.6%), and 72 strokes (3.4%) were recorded (Table 3).
Cox proportional hazards regression analysis for different clinical outcomes by female sex.
| Outcome | Events/total | Univariable HR(95% CI) | p-Value | Multivariable HR(95% CI) | p-Value |
|---|---|---|---|---|---|
| Composite endpoint | 458 (21.8%) | 0.84 (0.67–1.05) | 0.118 | 0.81 (0.64–1.04) | 0.099 |
| Composite endpointa | 458 (21.8%) | 0.84 (0.67–1.05) | 0.123 | 0.82 (0.64–1.04) | 0.100 |
| Death | 281 (13.4%) | 1.03 (0.78–1.35) | 0.839 | 0.78 (0.57–1.05) | 0.104 |
| Cardiovascular death | 139 (6.6%) | 1.03 (0.70–1.52) | 0.865 | 0.80 (0.51–1.24) | 0.309 |
| MI | 228 (10.8%) | 0.87 (0.63–1.19) | 0.380 | 0.89 (0.62–1.29) | 0.550 |
| Revascularization | 272 (12.9%) | 0.71 (0.52–0.97) | 0.029 | 0.71 (0.50–1.01) | 0.058 |
| Major haemorrhage | 139 (6.6%) | 1.51 (1.06–2.16) | 0.024 | 1.39 (0.92–2.11) | 0.119 |
| Stroke | 72 (3.4%) | 1.32 (0.79–2.19) | 0.291 | 0.90 (0.48–1.67) | 0.738 |
Univariable and multivariable Cox regression analyses assessing the association between female sex and various clinical outcomes. Multivariable models are adjusted for relevant clinical and social covariates. Hazard ratios are presented with 95% confidence intervals and corresponding p-values. The combined endpoint includes cardiovascular death, myocardial infarction, or coronary revascularization. CI: confidence interval; HR: hazard ratio; MI: myocardial infarction.
In univariable Cox regression analyses, female sex was associated with a non-significant trend toward a lower risk of the composite endpoint, which persisted after multivariable adjustment (aHR=0.81; 95% CI, 0.64–1.04; p=0.099) (Fig. 2). Competing risks analysis using Fine–Gray subdistribution hazard models yielded similar results, supporting the robustness of the findings. Overall mortality was comparable between sexes in univariable analysis, with a non-significant trend toward lower risk in women after adjustment (aHR=0.78; 95% CI, 0.57–1.05; p=0.104). Cardiovascular mortality did not differ significantly between sexes in either univariable or multivariable analyses (aHR=0.80; 95% CI, 0.51–1.24; p=0.309) (Table 3, Fig. 3 and Fig. 4).


Sex- and gender-related disparities in ischemic heart disease in the RECORVAL registry. Kaplan–Meier curves depict time-to-event analyses for the composite endpoint (cardiovascular death, myocardial infarction, or revascularization) and cardiovascular death, comparing women (red line) vs men (blue line). aHR, adjusted hazard ratio; CI, confidence interval; CV, cardiovascular; MI, myocardial infarction; PCI, percutaneous coronary intervention.
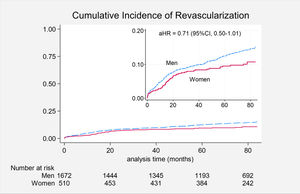
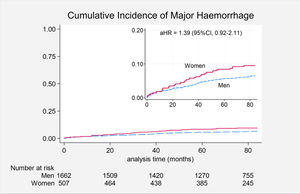
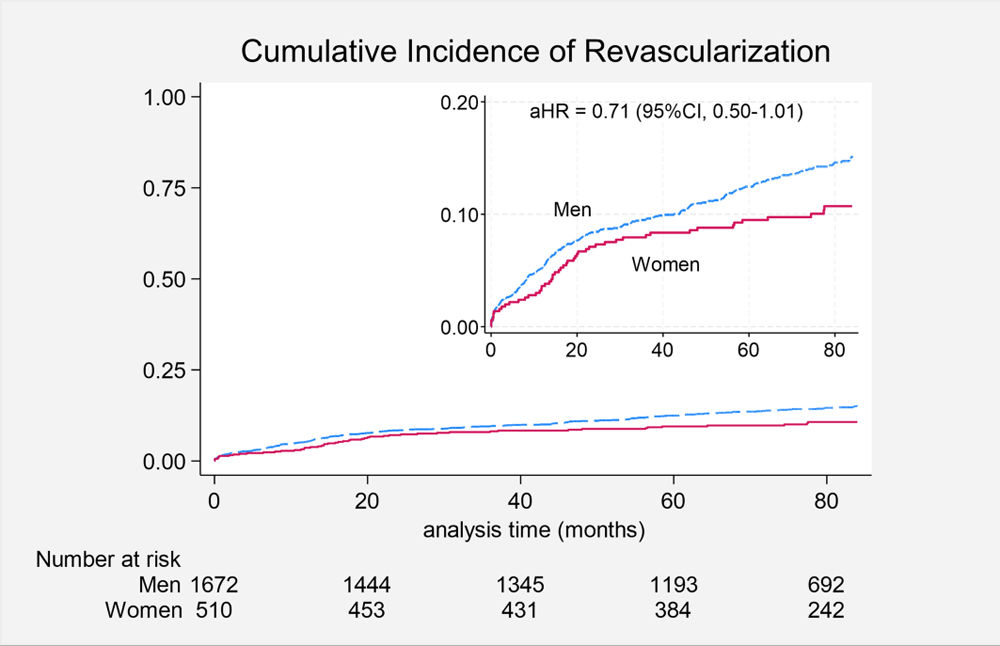
For MI, female sex showed a non-significant trend toward lower risk (aHR=0.89; 95% CI, 0.62–1.29; p=0.550). For revascularization, women had a significantly lower risk in univariable analysis, which became non-significant after adjustment (aHR=0.71; 95% CI, 0.50–1.01; p=0.058) (Table 3 and Supplementary Fig. 2). Conversely, women had a higher incidence of major haemorrhagic events in univariable analysis, although this association lost significance after adjustment (aHR=1.39; 95% CI, 0.92–2.11; p=0.119) (Supplementary Fig. 3). For stroke, no significant differences were observed (aHR=0.90; 95% CI, 0.48–1.67; p=0.738) (Table 3).
DiscussionIn this prospective cohort study based on the RECORVAL registry, we examined sex and gender differences in clinical and social predictors of long-term outcomes among patients with coronary artery disease in Cantabria, Spain, over an extended follow-up period. Our findings reveal significant disparities between men and women in baseline characteristics and social circumstances, with nuanced trends in clinical outcomes, underscoring the need for integrated approaches to risk assessment and management in IHD.
Women in our cohort were generally older than men and more likely to have hypertension and chronic kidney disease, but less likely to have a history of prior MI or revascularization procedures, such as PCI or CABG. These findings are consistent with global analyses showing that women with IHD tend to present at older ages and with a higher burden of comorbidities compared to men.2,17,18
Notably, our registry did not show sex-based differences in the likelihood of receiving PCI, nor in the proportion of patients managed conservatively, suggesting that men and women were similarly referred for invasive management overall. However, CABG was less frequently performed in women, even after adjusting for age. This selective disparity may reflect a more nuanced pattern of treatment inequity, where differences emerge primarily in the context of more invasive procedures. Prior literature has reported lower rates of invasive procedures among women, potentially influenced by factors such as advanced age, higher comorbidity burden, and atypical symptom presentation.12,17–21 Although these factors may partially explain the difference, the absence of disparities in PCI and conservative management in our cohort suggests a narrowing gap in access to invasive care, particularly among patients with established coronary artery disease. This more equitable access to guideline-recommended interventions may be helping to mitigate previously observed sex-based disparities in cardiovascular outcomes. Such evolution in clinical practice could reflect growing awareness of sex-specific risk, adherence to standardized protocols, and efforts to reduce unconscious bias in referral patterns.
From a social perspective, women experienced greater gender-related disadvantages, including lower educational attainment, reduced employment rates, a higher likelihood of living alone or without a partner, increased household responsibilities and a greater number of children. Additionally, women had less access to private vehicles and relied more frequently on public transportation or walking, along with reduced access to digital tools such as the internet and mobile devices, and more frequent exemptions from pharmaceutical copayments, an indicator of lower socioeconomic status. These disparities resonate with the growing body of literature highlighting women's greater exposure to psychosocial stressors, such as caregiving and economic insecurity, that contribute to increased cardiovascular risk.11,20,22,23 Some of these differences were partially influenced by the older age of women in our cohort, which affected factors such as employment rates or familiarity with digital tools. However, most social disparities persisted after accounting for age, indicating that gender-related disadvantages extend beyond age effects. For instance, a recent systematic review emphasized that women in low-resource settings face barriers to healthcare access and social support, contributing to poorer cardiovascular outcomes.13 Our previous work in this same population identified internet access as a protective factor in IHD prognosis,3 and the lower digital connectivity observed among women in the present study reinforces the potential for targeted, socially-aware interventions. Furthermore, dependence on public transportation or walking may indicate underlying socioeconomic limitations that could delay or restrict access to healthcare services.
In terms of outcomes, women exhibited a trend toward a lower risk of the composite endpoint (cardiovascular death, MI, or revascularization) and all-cause mortality, though these differences were not statistically significant after adjusting for confounders. It should be noted that social determinants were included in the multivariable models, which likely contributed to the adjustment of observed differences. While our study primarily focused on sex-based disparities, the role of these social variables in shaping cardiovascular outcomes is complex and warrants further dedicated investigation in future research. In contrast to studies suggesting worse post-MI outcomes in younger women,24–26 we did not observe this trend in our cohort, likely due to the underrepresentation of younger women in our sample. A similar trend was observed for MI and revascularization, where women had a significantly lower risk in univariable analysis but not after adjustment. Notably, women showed a higher incidence of major bleeding events in unadjusted analyses, though this difference diminished after adjustment. This finding is consistent with existing literature suggesting an elevated bleeding risk in women receiving antithrombotic therapies, potentially driven by factors such as increased platelet reactivity, sex-specific pharmacokinetics and pharmacodynamics, hormone replacement therapy, and gynecological conditions.19,27 Although this trend did not reach statistical significance, it underscores the importance of sex-specific considerations in bleeding risk management.
Taken together, these findings highlight the complex interplay between sex, social determinants, and clinical factors in IHD. The pronounced social disadvantages faced by women, combined with their distinct clinical profiles, suggest that risk stratification, treatment, and prevention strategies should incorporate both biological and social dimensions. Such an approach is essential to address disparities and improve long-term outcomes in both women and men with coronary artery disease.
This study shares some limitations with the previous analysis of the RECORVAL registry.3 Most notably, the social and behavioural variables were obtained using a non-validated, ad hoc questionnaire developed by the research team. Future studies should aim to validate social data collection instruments to improve comparability and generalizability, although interviews were conducted in person by a trained investigator to reduce variability and enhance accuracy, some responses may have been affected by social desirability or reluctance to disclose sensitive information. Additionally, several variables were categorised to facilitate analysis, which may have resulted in a loss of granularity.
Key socioeconomic indicators, such as personal income, were not included due to concerns about data accuracy and respondent discomfort, which could restrict evaluation of access to certain services. As a proxy, we incorporated the pharmaceutical co-payment tier (TIS), although it may not fully capture all dimensions of socioeconomic status. Postal code-based indicators could provide additional insight into area-level deprivation or contextual socioeconomic factors; however, they were not considered in the present analysis.
In addition, while the study focused on biological sex-based differences and included certain gender-related variables such as household roles and caregiving responsibilities, other important dimensions, including reproductive health or experiences of gender-based violence, were not assessed. These factors may influence cardiovascular outcomes and should be considered in future research. Moreover, other relevant dimensions such as mental health status and ethnic background were not captured, despite their recognised impact on cardiovascular health, particularly among women and vulnerable populations. Additionally, frailty was not directly assessed; however, age, comorbidities, and physical activity partially capture frailty-related aspects. Extreme frailty cases were not included, as all participants underwent invasive coronary procedures, limiting generalizability to the frailest populations.
Although the inclusion and exclusion criteria ensured a well-defined and cooperative cohort, they may have introduced selection bias by limiting participation of individuals with greater clinical or social vulnerability.
Finally, this was a single-centre study, which may limit the applicability of our findings to other settings. Despite a long-term follow-up and a high retention rate (95%), a small proportion of patients could not be tracked over time as they received care outside the regional health system. Nevertheless, rigorous and independent adjudication of clinical events was ensured to the greatest extent possible.
ConclusionsOur findings suggest that women with coronary artery disease may experience social disadvantages that could influence their clinical profile and outcomes. Although overall access to interventional treatments were comparable between men and women, differences in ischemic and haemorrhagic risk patterns were observed in unadjusted analyses but did not remain statistically significant after multivariable adjustment. These observations underline the potential relevance of sex-specific factors and social determinants in the evaluation and management of coronary artery disease, while acknowledging that the observed variations may be influenced by clinical and social confounders.
CRediT authorship contribution statementStudy conception and design: JM de la Torre Hernandez, J Zubiaur, Mi Rodríguez de Rivera, Itziar Cucurull Ortega, Elton Carreiro Da Cunha; interpretation of results: JM de la Torre Hernández, Mi Rodríguez de Rivera, J Zubiaur, Itziar Cucurull Ortega, Elton Carreiro Da Cunha; draft manuscript preparation: Mi Rodríguez de Rivera, J Zubiaur, JM de la Torre Hernández. All authors reviewed the results and approved the final version of the manuscript.
Ethical considerationsThis study was conducted in full accordance with the ethical principles established by the Declaration of Helsinki. Prior to initiation, the study protocol was reviewed and approved by the relevant institutional ethics committee. Informed consent was obtained in writing from all participants before inclusion.
Additionally, this research rigorously adhered to the Sex and Gender Equity in Research (SAGER) guidelines to ensure systematic consideration and transparent reporting of sex and gender variables throughout the study design, data collection, analysis, and interpretation phases.
Declaration of generative AI and AI-assisted technologies in the writing processDuring the preparation of this manuscript, the authors did not use artificial intelligence tools for processing, analysis, or content development. Only basic tools for grammar, spelling, and reference management were employed.
FundingNo funding declared.
Conflicts of interestsThe authors declared no competing interest related to this research.