




Chronic low back pain is one of the leading causes of disability. Current therapies offer limited efficacy and carry potential adverse risks. Vitamins B1, B6, and B12 have shown promise in the amelioration of musculoskeletal pain. The aim of this study was to evaluate the efficacy and safety of a combined injectable formulation of hydroxocobalamin (B12), thiamine hydrochloride (B1), and pyridoxine hydrochloride (B6) (TPH) as an adjunct treatment for chronic low back pain.
MethodsA randomized, double-blind, phase 3 clinical trial was conducted across six centres in Peru. A total of 163 patients with chronic mechanical lower back pain were included and assigned to receive TPH plus NSAIDs (n = 81) or placebo plus NSAIDs (n = 82). The primary outcome was the proportion of patients achieving ≥30% reduction in the NRS-11 score by day 28. Analyses were performed using an intention-to-treat approach and models adjusted for covariates.
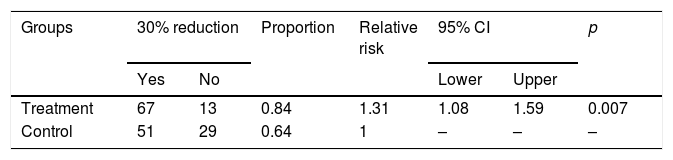
ResultsIn the treatment group, 84% of participants achieved ≥30% reduction in the NRS-11 score compared to 64% in the control group (RR = 1.31; 95% CI: 1.08–1.59; p = 0.007). This effect remained significant after adjusting for BMI and albumin. Improvements were also observed in the Patient Global Assessment (PGA) and a favourable trend in the Oswestry Disability Index. The incidence of adverse events was higher in the treatment group, but no significant differences in serious events were found.
ConclusionTPH as an adjunct to standard treatment was effective in reducing chronic low back pain and demonstrated an acceptable safety profile.
El dolor lumbar crónico es una de las principales causas de discapacidad a nivel mundial. Las terapias actuales presentan eficacia limitada y efectos adversos. Las vitaminas B1, B6 y B12 han mostrado potencial como coadyuvantes en el manejo del dolor musculoesquelético. El objetivo del estudio fue evaluar la eficacia y seguridad de una formulación inyectable combinada de hidroxocobalamina (B12), clorhidrato de tiamina (B1) y clorhidrato de piridoxina (B6) (TPH) como tratamiento adyuvante para el dolor lumbar crónico.
MétodosEnsayo clínico aleatorizado, doble ciego, de fase 3, realizado en seis centros de Perú. Se incluyeron 163 pacientes con lumbalgia mecánica crónica, asignados a tratamiento con TPH más AINEs (n = 81) o placebo más AINEs (n = 82). El desenlace primario fue la proporción de pacientes con ≥30% de reducción en la escala NRS-11 al día 35. Se aplicó análisis por intención a tratar y modelos ajustados por covariables.
ResultadosEl 84% del grupo tratamiento alcanzó reducción ≥30% en la escala NRS-11, comparado con 64% en el grupo control (RR = 1,31; IC 95%: 1,08–1,59; p = 0,007). El efecto se mantuvo tras ajustar por IMC y albúmina. También se observaron mejoras en la evaluación global del paciente (PGA) y una tendencia favorable en el índice de discapacidad de Oswestry. La incidencia de eventos adversos fue mayor en el grupo tratamiento, pero sin diferencias significativas en eventos graves.
ConclusiónTPH como adyuvante al tratamiento estándar fue eficaz para reducir el dolor lumbar crónico, con un perfil de seguridad esperado.
Low back pain remains one of the leading causes of years lived with disability (YLDs) worldwide. In 2020, more than 500 million prevalent cases of low back pain were estimated, and this figure is projected to increase by 2050.1,2 This condition is associated with population ageing, obesity, and sedentary lifestyles. Low back pain may be classified as specific, when an identifiable structural cause is present, or non-specific, when no clear cause is found; the latter accounts for approximately 90% of cases.3
Therapeutic options for the management of low back pain include non-pharmacological interventions such as physical rehabilitation, exercise, acupuncture, and psychotherapy, although the evidence supporting their effectiveness remains limited and heterogeneous.4,5 Conventional pharmacological treatment includes first-line analgesics such as paracetamol and non-steroidal anti-inflammatory drugs (NSAIDs), whose use is limited by potential adverse effects.6 Other medications, including muscle relaxants, benzodiazepines, and opioids, are used with caution due to their association with sedation, dependence, toxicity, and risk of misuse.
In this context, B-complex vitamins have been investigated as an adjuvant therapeutic option for the treatment of neuropathic and musculoskeletal pain. Thiamine, pyridoxine, and hydroxocobalamin (vitamins B1, B6, and B12) have demonstrated antioxidant, anti-inflammatory, and neuroprotective effects.7,8 The B complex has been shown to modulate the inflammatory response and may possess antioxidant properties.9,10 Several clinical studies have reported positive results with the use of these vitamins11,12; however, evidence regarding their combined use in a specific formulation containing hydroxocobalamin, thiamine hydrochloride, and pyridoxine hydrochloride remains scarce.
Therefore, the aim of this study was to evaluate the efficacy and safety of a combination of vitamins B1, B6, and B12 [thiamine–pyridoxine–hydroxocobalamin (TPH)] as an adjunct in the treatment of chronic low back pain.
Material and methodsTrial designThis was a phase 3, double-blind, multicentre, randomised, two-arm, superiority clinical trial, placebo-controlled and conducted alongside standard of care, designed to evaluate the efficacy and safety of hydroxocobalamin (vitamin B12) 10,000 μg + thiamine hydrochloride (vitamin B1) 100 mg + pyridoxine hydrochloride (vitamin B6) 50 mg (Bedoyecta® Tri) in patients with chronic low back pain. All procedures were conducted in accordance with the ethical standards of the 1964 Declaration of Helsinki and were planned a priori. The study protocol was approved by the Institutional Bioethics Committee of Vía Libre for each participating research site (protocol number GRP-001-2020). The Peruvian Ministry of Health (MINSA), through the National Institute of Health (INS), approved six research centres for this study.
ParticipantsThe study included patients aged >18 years who attended general medical consultation at participating centres. Participants were required to have a diagnosis of mechanical low back pain of 3–6 months’ duration, documented by computed tomography (CT) or magnetic resonance imaging (MRI) performed within the previous six months before the screening visit. Eligible patients had to present moderate-to-severe chronic low back pain (score 4–8) on the 11-point Numeric Rating Scale (NRS-11),13–15 be aged between 18 and 60 years, have a body mass index (BMI) <30 kg/m2, and have used NSAIDs for pain control during the month prior to enrolment. Assessment of low back pain included a detailed clinical history of symptoms, their relationship with physical exertion or prolonged fixed posture, and physical examination including the presence or absence of Lasègue, Wasserman, and Dandy signs, Valleix tender points, deep tendon reflexes, and lumbar range of motion. Participants were required to be able to read and understand the language and study content, be willing to attend follow-up visits, complete a study diary, and comply with study procedures. Only patients who had not previously used Bedoyecta® Tri and who had not taken antidepressants or benzodiazepines within the 60 days prior to study initiation were included. Women of childbearing potential were required to have a negative pregnancy test, to use contraceptive methods one month before screening and throughout the study, or to be surgically sterile or postmenopausal.
Patients with non-specific chronic low back pain, radicular pain, or pain secondary to spinal causes were excluded, as were those with low back pain of non-spinal origin (e.g. renal pathology such as lithiasis). CT or MRI confirmed the absence of findings explaining an alternative aetiology, such as disc herniation, Pott’s disease, or fractures. Pregnant or breastfeeding women, individuals unable to provide informed consent, and those with recent changes in pain severity or therapeutic management were excluded. Patients with primary bone diseases, cancer, active infections, inflammatory or vascular diseases that could interfere with interpretation of results, epilepsy, coagulopathies, unstable psychiatric conditions, or substance misuse were not eligible. Patients receiving physiotherapy or chiropractic treatment or participating in another clinical trial were also excluded. Eligible patients were informed that they would be randomly assigned in a 1:1 ratio using a central Interactive Web Response System (IWRS; https://sistemaweb.pcr.pe). Each centre’s designated staff member accessed the IWRS using a username and password to obtain the treatment allocation number and dispense the corresponding medication. Only the central unblinded statistician and the individual responsible for drug administration knew the treatment allocation (participant and investigator blinded).
InterventionsBoth groups received their assigned compound (A: TPH intramuscularly; B: placebo intramuscularly) every 72 h for at least 2 weeks and up to 4 weeks, in addition to standard of care (NSAIDs, oral, ≥4 times/week) during the study period, supplied by the study sponsor. Both compounds were prepared and administered by the designated unblinded individual at each research centre without unblinding the study.
OutcomesThe primary efficacy outcome was reduction in chronic low back pain assessed using the NRS-11.13–15 A reduction of ≥30% from baseline on the NRS-11 was considered a successful response, in line with methodological recommendations defining this threshold as clinically relevant.16 Changes in NRS-11 scores from day 0 to days 15 and 35 were analysed. As a secondary outcome, functional disability was measured using the Oswestry Disability Index (ODI)17 on days 0, 7, 14, 21, and 28. The Patient Global Assessment (PGA)17 was also recorded on the same dates, evaluating the participant’s perceived change in overall health status during the study. An additional exploratory outcome was change in depressive symptomatology, assessed using the Beck Depression Inventory-II (BDI-II)18 on days 0, 14, and 28.
Efficacy assessments were performed on days 7, 14, 21, 28, and 35, with a ±1-day window. The investigational product was administered within 24 h before efficacy evaluation and never assessed earlier than 6 h after administration. No standard-of-care treatment was to be used within 24 h before efficacy assessment.
Regarding safety outcomes, the incidence and frequency of adverse events (AEs) occurring during the observation period—from first dose administration until 7 days after the last dose—were evaluated.
Sample sizeSample size calculation was performed using Power and Sample Size version 3.2.1 for Windows 10. The primary analysis compared the proportion of participants achieving a successful response on day 28.16 Based on the literature, it was estimated that 63.2% of participants in group B would achieve a successful reduction in NRS-11,13–15,19 A minimum clinically relevant difference of 20% between groups was assumed, expecting 83.2% of participants in group A to achieve a successful response, in accordance with superiority trial design principles.20 Using the formula for comparison of two independent proportions, with a 5% significance level and 80% power, a sample size of 76 participants per group was calculated. Assuming a 10% loss to follow-up, this was adjusted to 84 patients per group.
Statistical methodsStatistical analyses were performed using R software (R Core Team, 2024) and SPSS v.29 for Windows. Results were presented with two-sided 95% confidence intervals (95% CI). Statistical superiority was declared when p ≤ 0.05 and the effect estimate favoured the TPH combination.
Efficacy analyses were conducted on the full analysis set, following the intention-to-treat principle. Safety analyses were conducted on the safety set, including subjects who received at least one dose of study product, using an “as-treated” approach.
Baseline characteristics were summarised and descriptively compared between groups. Continuous variables were reported as mean and standard deviation (SD) or median and interquartile range (IQR), depending on distribution and coefficient of variation (CV). A symmetric distribution was assumed when CV was <10%. Categorical variables were described as absolute frequencies and percentages. Baseline balance was assessed using standardised mean differences for continuous variables and absolute differences in proportions for categorical variables. Differences >10% prompted consideration of adjusted sensitivity analyses.
The proportion of patients achieving a successful response for the primary outcome was compared using the chi-square test. Missing data were handled using multiple imputation, generating 100 imputed datasets based on parameters estimated from group B. It was assumed that participants who discontinued without follow-up evaluations behaved similarly to those in the placebo group. This conservative strategy assumed a non-random missing pattern and applied a pattern-mixture model.
Sensitivity analyses included: a) an unadjusted analysis excluding prespecified covariates, and b) an as-treated analysis including only participants who received at least one dose of the assigned product. When expected cell counts for the chi-square test were <5, Fisher’s exact test was used.
Continuous secondary outcomes (changes in NRS-11,13–15 ODI,17 PGA and BDI-II18 scores) were modelled using ANCOVA or quantile regression, adjusted for centre, age, baseline score, and other stratification factors. When appropriate, ordinal logistic regression was used for ODI17 and PGA. No adjustment for multiplicity was performed; therefore, secondary results should be interpreted as exploratory.
Safety outcomes were analysed in the “as-treated” set. Odds ratios (ORs) were calculated using unadjusted simple exact logistic regression, along with differences in proportions between groups. Adverse event rates per 1000 person-days were estimated. For adverse events, Poisson regression was used when no overdispersion was observed; otherwise, negative binomial regression (NB2) was applied, and in cases of underdispersion, Poisson regression with robust variance was used. All safety analyses were unadjusted for covariates.
This clinical trial did not undergo any methodological changes after its initiation. There was no patient involvement in the design, conduct, analysis, or reporting of the study.
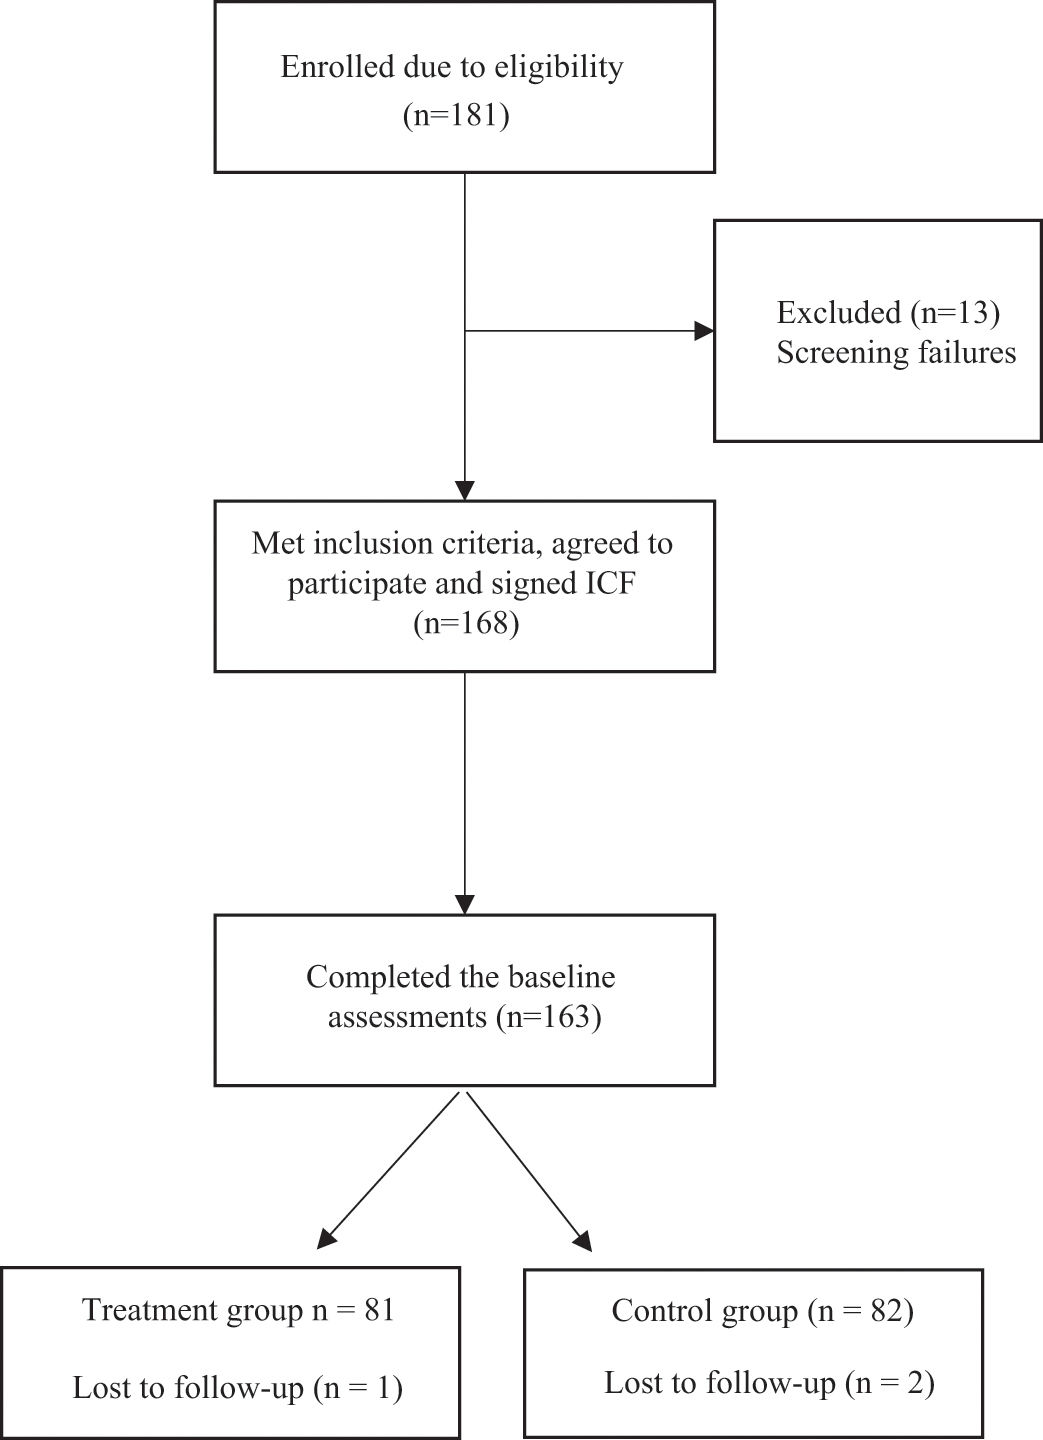
ResultsParticipant flowOf the 181 individuals invited, 13 were excluded for not meeting the selection criteria. The remaining 168 voluntarily agreed to participate in the study and signed informed consent. Of these, 5 did not complete the assessments; therefore, 163 participants were included in the initial analysis. Subsequently, 81 were randomly assigned to group A and 82 to group B. During follow-up, one participant in group A and two in group B were lost (Fig. 1).
Participant characteristics
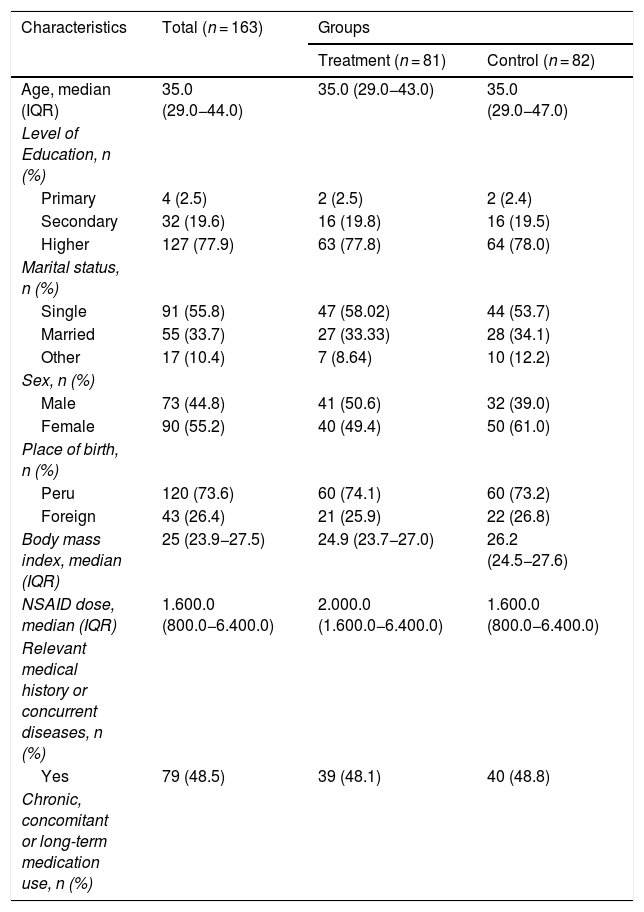
Table 1 presents the baseline characteristics of the participants. The median age was 35 years in both groups. Higher education was the most common level attained (77.8% in group A and 78% in group B). Most participants were single (58% in group A vs. 53.7% in group B). The proportion of women was higher in group B (49.4% vs. 61%), without statistical significance.
Baseline sociodemographic and clinical characteristics of participants according to treatment group.
| Characteristics | Total (n = 163) | Groups | |
|---|---|---|---|
| Treatment (n = 81) | Control (n = 82) | ||
| Age, median (IQR) | 35.0 (29.0−44.0) | 35.0 (29.0−43.0) | 35.0 (29.0−47.0) |
| Level of Education, n (%) | |||
| Primary | 4 (2.5) | 2 (2.5) | 2 (2.4) |
| Secondary | 32 (19.6) | 16 (19.8) | 16 (19.5) |
| Higher | 127 (77.9) | 63 (77.8) | 64 (78.0) |
| Marital status, n (%) | |||
| Single | 91 (55.8) | 47 (58.02) | 44 (53.7) |
| Married | 55 (33.7) | 27 (33.33) | 28 (34.1) |
| Other | 17 (10.4) | 7 (8.64) | 10 (12.2) |
| Sex, n (%) | |||
| Male | 73 (44.8) | 41 (50.6) | 32 (39.0) |
| Female | 90 (55.2) | 40 (49.4) | 50 (61.0) |
| Place of birth, n (%) | |||
| Peru | 120 (73.6) | 60 (74.1) | 60 (73.2) |
| Foreign | 43 (26.4) | 21 (25.9) | 22 (26.8) |
| Body mass index, median (IQR) | 25 (23.9−27.5) | 24.9 (23.7−27.0) | 26.2 (24.5−27.6) |
| NSAID dose, median (IQR) | 1.600.0 (800.0−6.400.0) | 2.000.0 (1.600.0−6.400.0) | 1.600.0 (800.0−6.400.0) |
| Relevant medical history or concurrent diseases, n (%) | |||
| Yes | 79 (48.5) | 39 (48.1) | 40 (48.8) |
| Chronic, concomitant or long-term medication use, n (%) | |||
IQR: interquartile range.
BMI showed a statistically significant difference between groups (median 24.9 in group A vs. 26.2 in group B, p = 0.031). Among laboratory parameters, only albumin showed significant differences (median 4.7 g/dL in group A vs. 4.6 g/dL in group B, p = 0.024). The remaining variables are presented in Appendix B Supplementary material 1.
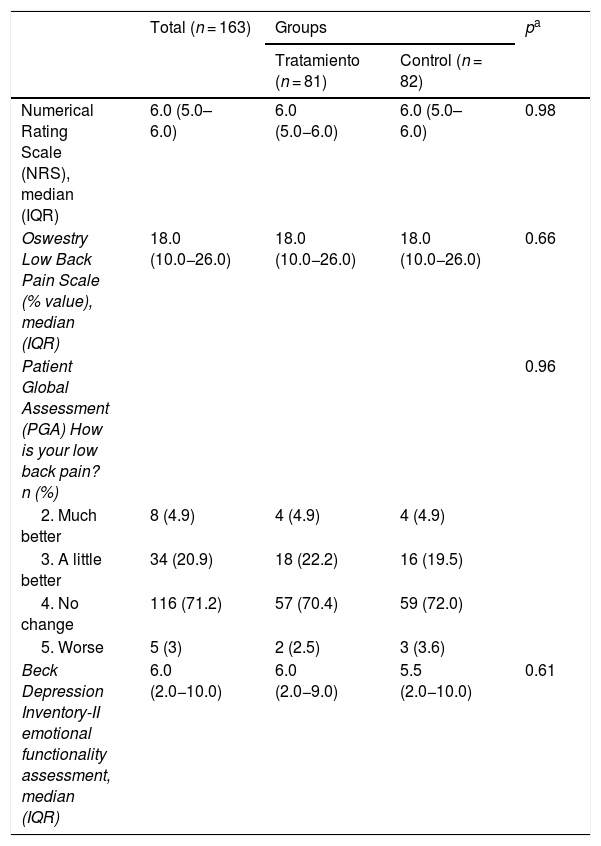
At baseline assessment, NRS-1113–15 and ODI17 scores were similar between groups. Regarding PGA, most participants reported no change in low back pain (70.4% in group A vs. 72% in group B). For BDI-II,18 a slightly higher score was observed in group A vs. group B (median 6 vs. 5.5). None of the pain-related variables showed statistically significant differences (Table 2).
Baseline pain assessment.
| Total (n = 163) | Groups | pa | ||
|---|---|---|---|---|
| Tratamiento (n = 81) | Control (n = 82) | |||
| Numerical Rating Scale (NRS), median (IQR) | 6.0 (5.0–6.0) | 6.0 (5.0−6.0) | 6.0 (5.0–6.0) | 0.98 |
| Oswestry Low Back Pain Scale (% value), median (IQR) | 18.0 (10.0−26.0) | 18.0 (10.0−26.0) | 18.0 (10.0−26.0) | 0.66 |
| Patient Global Assessment (PGA) How is your low back pain? n (%) | 0.96 | |||
| 2. Much better | 8 (4.9) | 4 (4.9) | 4 (4.9) | |
| 3. A little better | 34 (20.9) | 18 (22.2) | 16 (19.5) | |
| 4. No change | 116 (71.2) | 57 (70.4) | 59 (72.0) | |
| 5. Worse | 5 (3) | 2 (2.5) | 3 (3.6) | |
| Beck Depression Inventory-II emotional functionality assessment, median (IQR) | 6.0 (2.0−10.0) | 6.0 (2.0−9.0) | 5.5 (2.0−10.0) | 0.61 |
IQR: interquartile range.
The proportion of participants who achieved a reduction ≥ 30% on the NRS-11 scale13–15 was higher in group A vs. group B (Table 3).
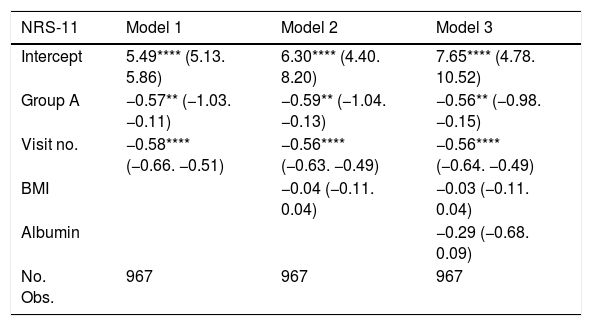
After adjusting for BMI (Model 2) and for albumin levels plus BMI (Model 3), the association between treatment and clinical response remained significant. In Model 2, the treatment group showed a relative risk of 1.31 (95% CI: 1.09–1.59; p = 0.005), indicating a higher probability of achieving a significant reduction on the NRS-1113–15compared with group B.
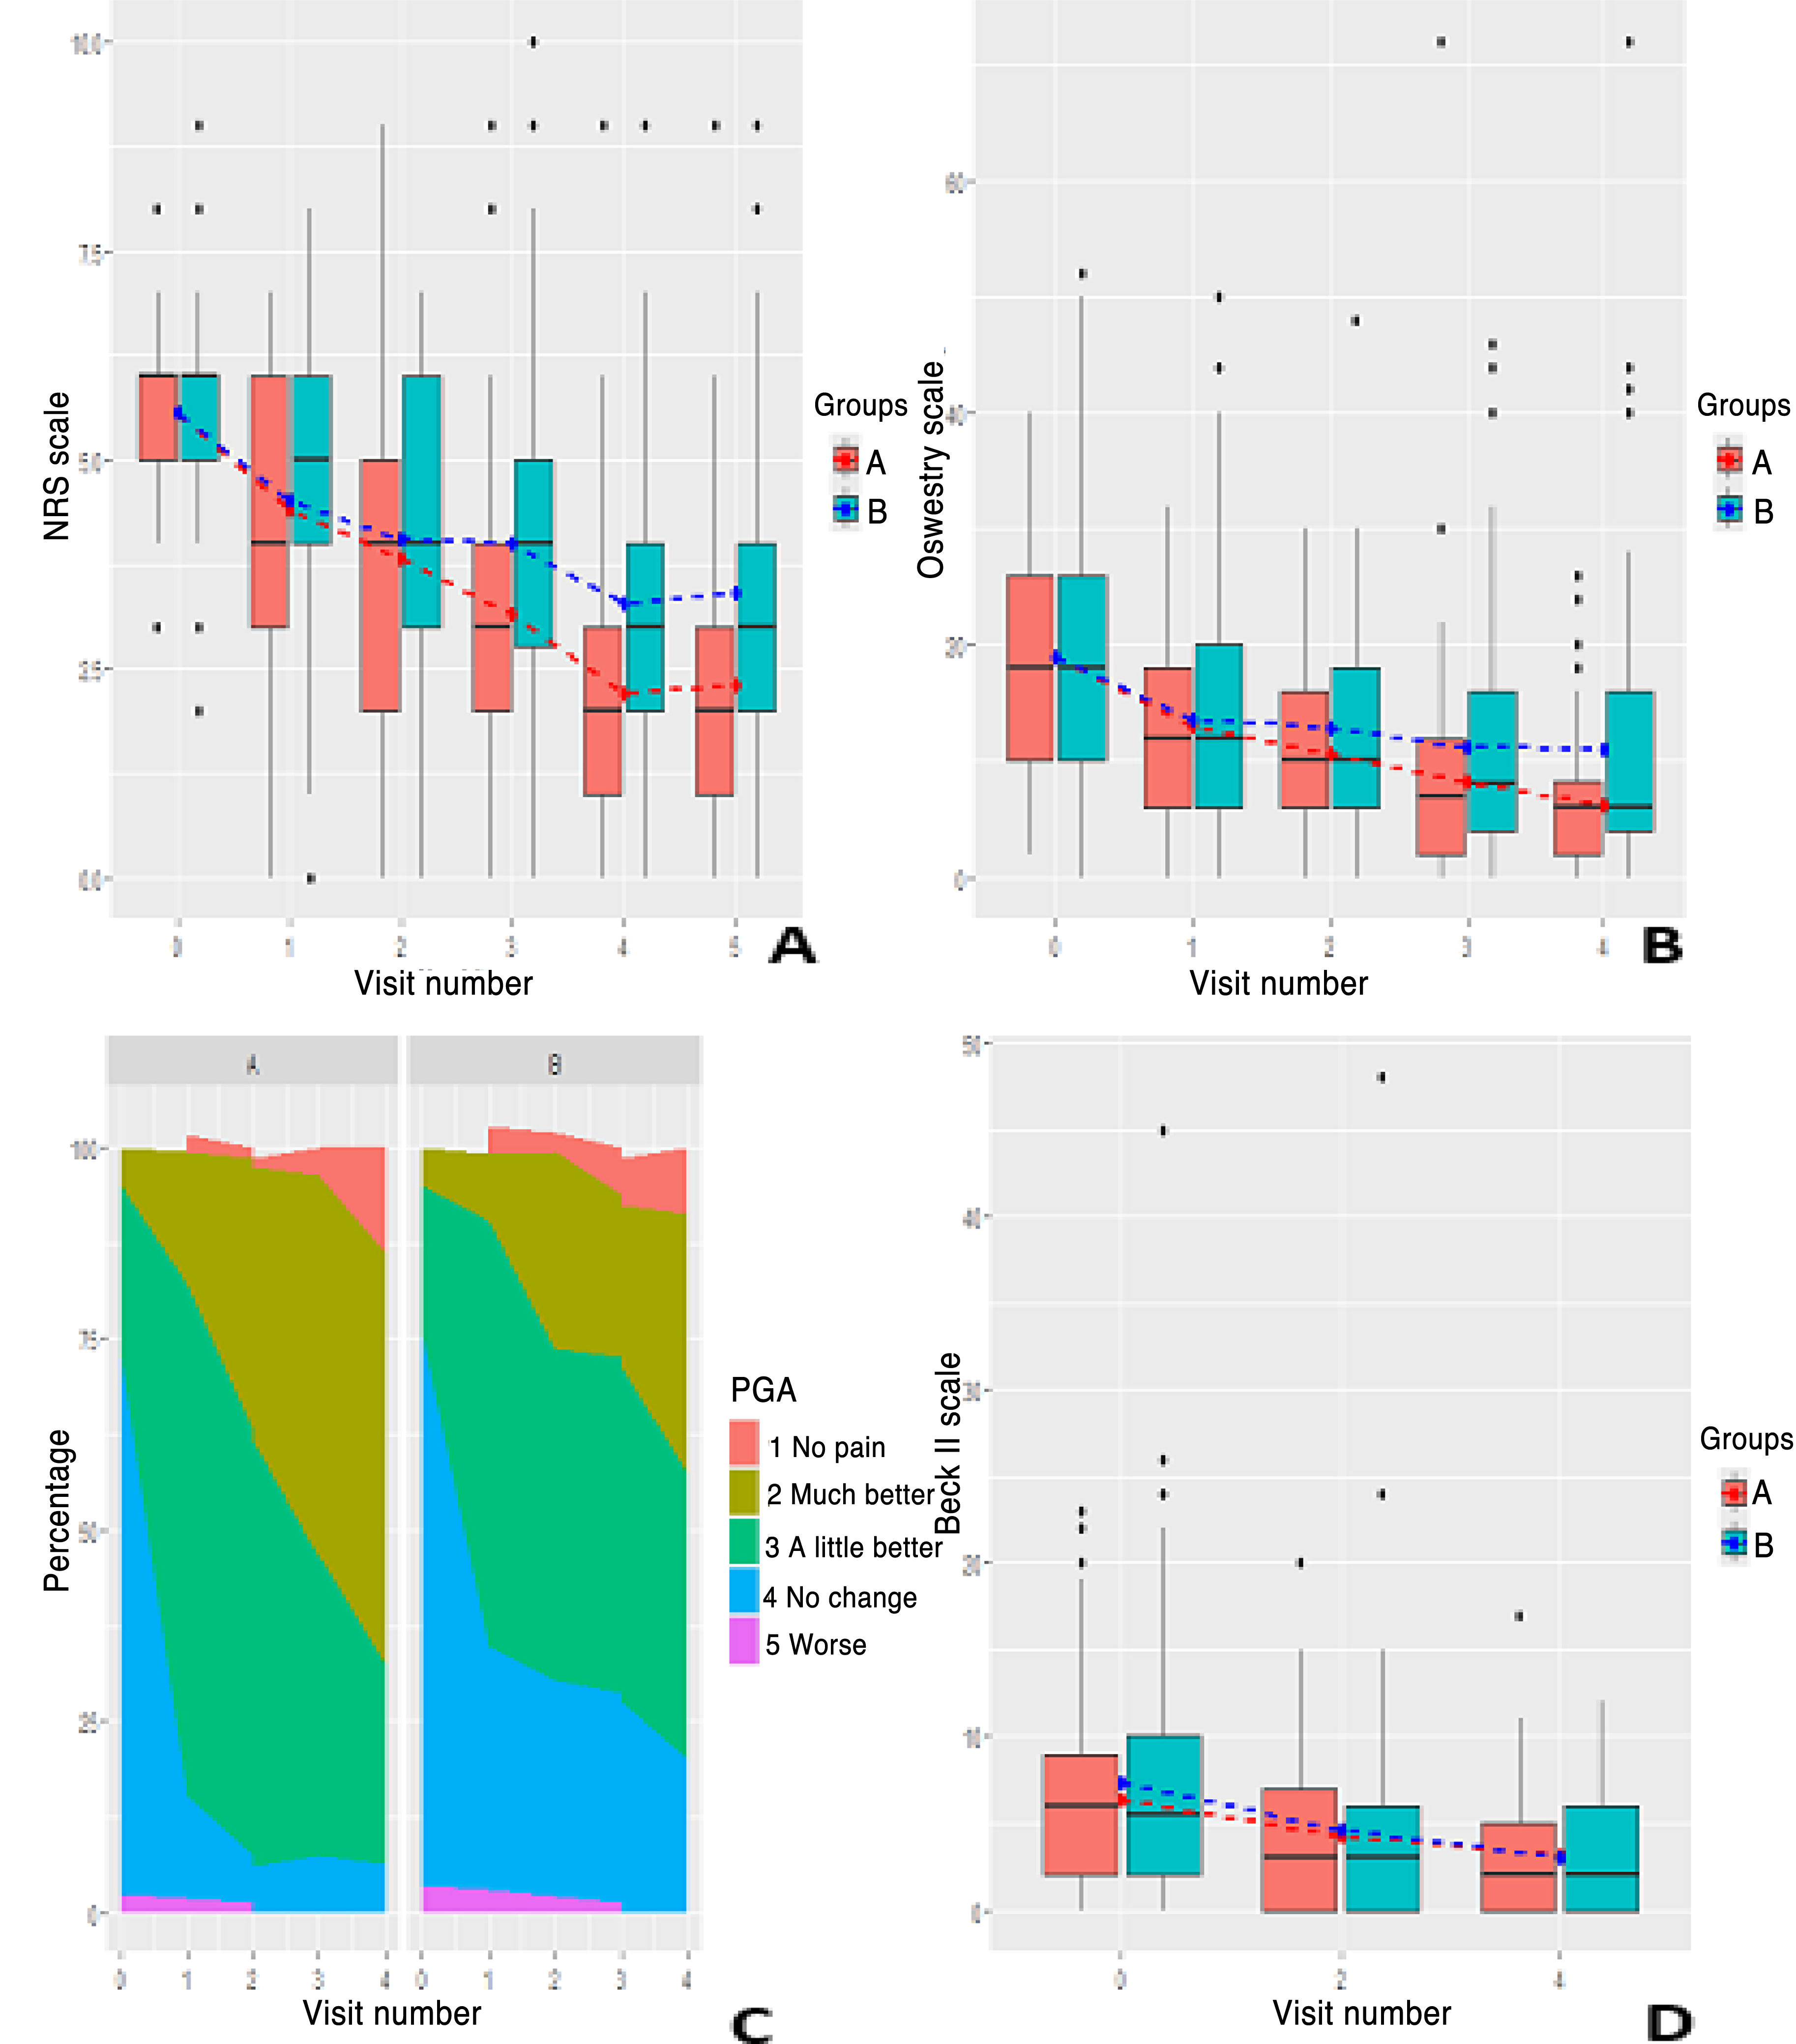
During follow-up, a downward trend was observed in NRS-1113–15 and ODI scores in both groups, with a greater reduction in group A from the second week onwards. In the PGA, the proportion of participants reporting “no change” (category 4) progressively decreased, particularly in group A, where the categories “a little better” (3) and “much better” (2) were reported more frequently. Additionally, “worse” is classified as 5 (Fig. 2).

Weekly evolution of clinical scales during follow-up: A) NRS-11 pain scale (Numerical Rating Scale), assessed over 5 weeks; B) Oswestry Disability Index, assessed over 4 weeks; C) Patient Global Assessment (PGA), categorised as 5 = worse, 4 = no change, 3 = a little better, 2 = much better, and 1 = no pain; and D) Beck Depression Inventory-II, also assessed over 4 weeks. Group A corresponds to the treatment group and group B to the control group.
Table 4 shows a negative effect in group A for NRS-1113–15 and PGA across the three models, and similarly for BDI-II18 and ODI.17 In all models and scales, the number of visits was associated with a decrease in scores.
Mixed or hierarchical models.
| NRS-11 | Model 1 | Model 2 | Model 3 |
|---|---|---|---|
| Intercept | 5.49**** (5.13. 5.86) | 6.30**** (4.40. 8.20) | 7.65**** (4.78. 10.52) |
| Group A | −0.57** (−1.03. −0.11) | −0.59** (−1.04. −0.13) | −0.56** (−0.98. −0.15) |
| Visit no. | −0.58**** (−0.66. −0.51) | −0.56**** (−0.63. −0.49) | −0.56**** (−0.64. −0.49) |
| BMI | −0.04 (−0.11. 0.04) | −0.03 (−0.11. 0.04) | |
| Albumin | −0.29 (−0.68. 0.09) | ||
| No. Obs. | 967 | 967 | 967 |
| ODI | Model 1 | Model 2 | Model 3 |
|---|---|---|---|
| Intercept | 17.68**** (15.15. 20.20) | 9.79* (−0.78. 20.36) | 11.78 (−4.19. 27.74) |
| Group A | − | −1.80 (−4.00. 0.40) | −1.73 (−4.25. 0.79) |
| Visit no. | −2.16**** (−2.57. −1.76) | −2.11**** (−2.43. −1.78) | −2.08**** (−2.54. −1.62) |
| BMI | 0.26 (−0.13. 0.65) | 0.24 (−0.18. 0.66) | |
| Albumin | −0.38 (−2.96. 2.21) | ||
| No. Obs. | 807 | 807 | 807 |
| PGA | Model 1 | Model 2 | Model 3 |
|---|---|---|---|
| 1/2 | −6.91**** (−7.64. −6.19) | −9.69**** (−12.37. −7.02) | −10.83**** (−14.43. −7.23) |
| 2/3 | −3.74**** (−4.27. −3.22) | −6.52**** (−9.13. −3.91) | −7.66**** (−11.21. −4.11) |
| 3/4 | −0.87**** (−1.30. 0.45) | −3.65*** (−6.22. −1.08) | −4.79*** (−8.30. −1.28) |
| 4/5 | 4.06**** (3.21. 4.92) | 1.29 (−1.34. 3.93) | 0.15 (−3.41. 3.71) |
| Group A | −1.00**** (−1.50. −0.49) | −1.09**** (−1.60. −0.59) | −1.07**** (−1.58. −0.56) |
| Visit no. | −0.92**** (−1.04. −0.80) | −0.92**** (−1.04. −0.80) | −0.92**** (−1.04. −0.80) |
| BMI | −0.11** (−0.20. −0.01) | −0.11** (−0.20. −0.01) | |
| Albumin | −0.25 (−0.77. 0.27) | ||
| Random intercept per participant | 1.34 | 1.31 | 1.31 |
| No. Obs. | 807 | 807 | 807 |
| BDI-II | Model 1 | Model 2 | Model 3 |
|---|---|---|---|
| Intercept | 6.35**** (5.16. 7.53) | 6.59* (−0.07. 13.24) | 16.75** (3.06. 30.44) |
| Group A | −0.51 (−1.62. 0.59) | −0.25 (−1.58. 1.08) | −0.08 (−1.51. 1.34) |
| Visit no. | −0.84**** (−1.12. −0.56) | −0.44** (−0.76. −0.11) | −0.47** (−0.81. −0.12) |
| BMI | −0.07 (−0.33. 0.19) | −0.08 (−0.34. 0.18) | |
| Albumin | −2.16* (−4.66. 0.34) | ||
| No. Obs. | 485 | 485 | 485 |
Adverse events were reported in both groups, most of them mild (75.3%). Group A had a higher proportion of cases of acne (11.3%), chromaturia (14.2%), and hypoesthesia (5.7%) vs. group B. The most common events in group B were pain at the application site (34.2%) and injection-related events (14.5%). No differences were identified in the occurrence of serious adverse events, and no participant in group A required hospitalisation or permanent discontinuation of the drug. The probability of developing adverse events was higher in group A vs. group B, although the evidence was not conclusive (RR = 1.27, 95% CI: 0.85–1.9).
Seventy-five point three per cent of events required no intervention. Most participants recovered completely (86.3%), without major differences between groups. Only 2 events (1.1%), both in the control group, were considered serious adverse reactions. The relationship with the intervention was rated as probable or definite in 47% of events in group A and 39.4% in group B. The findings support a favourable safety profile for the use of TPH as an adjunct in the treatment of low back pain. See Appendix B Table S2 in the Supplementary material.
DiscussionThis randomised, double-blind, placebo-controlled study demonstrated that intramuscular administration of TPH as an adjunct to standard NSAID therapy was effective in achieving a clinically significant reduction in pain in patients with chronic low back pain, in line with previous studies suggesting a possible analgesic benefit of TPH in musculoskeletal and neuropathic conditions.21 The combination used in this study includes hydroxocobalamin, associated with greater bioavailability and longer duration of effect compared with cyanocobalamin, and showing similar properties in these aspects to adenosylcobalamin and methylcobalamin.22 In addition, improvement was observed in PGA, and although the decrease in ODI was more pronounced in group A, it did not reach statistical significance. This trend contrasts with findings from other clinical trials reporting reductions of 27–87%, respectively.11,12 Depressive symptomatology assessed with BDI-II18 also showed a downward trend in both groups. The relationship between chronic pain and depression is widely recognised and may represent an avenue of interest for future studies.23 The safety profile observed was as expected. Most adverse events were mild, and no serious events related to the product were reported in the intervention group. The rate of reactions considered “probable” or “definite” was higher in the treated group, but without requiring hospitalisation or treatment discontinuation, which is consistent with various clinical trials and meta-analyses.11,12,24
This study has some limitations that should be considered when interpreting the results. First, although the sample size was calculated to detect differences in the primary outcome, the number of participants may have been insufficient to identify statistically significant effects in some secondary outcomes, particularly those related to functionality and emotional health. Second, follow-up duration was limited to 5 weeks, precluding evaluation of the sustainability of the analgesic effect, relapses, and the need for retreatment in the medium or long term. Moreover, no objective assessment of adherence to standard therapy or additional use of analgesics outside the protocol was included, which may have introduced adherence bias. Another relevant limitation is that participants were recruited from urban centres and selected by convenience sampling, which may limit generalisability to other populations. Despite this, the methodological robustness, double blinding, and multicentre design support the internal validity of the findings.
These findings suggest that TPH may be a safe and effective therapeutic option as an adjunct in the management of chronic low back pain, particularly in patients receiving standard NSAID therapy who have limitations regarding prolonged use of these drugs. Future research should evaluate durability of effect and explore its utility in other clinical contexts and patient subgroups.
RecommendationsIt is suggested that the TPH combination be considered a safe and effective adjunctive alternative in the management of chronic low back pain, particularly in patients without contraindications who require reduction of prolonged NSAID use. Nevertheless, its incorporation into clinical practice should be accompanied by individualised follow-up, especially in populations with comorbidities or receiving multiple medications. Future multicentre studies with larger sample sizes and longer follow-up will be necessary to evaluate durability of the analgesic effect, impact on quality of life, and potential prevention of recurrences. Likewise, studies exploring response biomarkers could help identify subgroups of patients who may derive greater benefit from this intervention.
ConclusionThe combination of hydroxocobalamin, thiamine, and pyridoxine, administered as adjunctive therapy in patients with chronic low back pain, proved effective by significantly increasing the proportion of patients achieving a clinically relevant reduction in pain, in addition to showing sustained improvement in functional indicators such as disability and patient global assessment. This effect persisted after adjustment for relevant clinical variables. Furthermore, the safety profile observed was favourable, with predominantly mild adverse events and no need for permanent discontinuations or hospitalisations in the intervention group. These findings support the use of Bedoyecta® Tri as a safe and effective therapeutic option in the comprehensive management of chronic low back pain.
Ethical considerationsThe study was approved by the Institutional Bioethics Committee of Vía Libre (CIB VL) (1) for each participating research site under protocol number GRP-001-2020. The Peruvian Ministry of Health (MINSA), through the National Institute of Health (INS), approved six research centres for this study. Informed consent was obtained from all patients included in the study.
FundingThis study was funded by Laboratorios Grossman S.A., which engaged the contract research organisation (CRO) Peruvian Clinical Research to manage and monitor the clinical study. The sponsor was responsible for the study design but had no role in the conduct or implementation of the protocol, data analysis, or preparation of the present manuscript.
Data availabilityThe protocol, databases, statistical analyses together with their code, and de-identified participant data including the data dictionary may be accessed upon reasonable request by entities interested in obtaining this material from the authors.
This study was sponsored by Laboratorios Grossman. María Teresa Reyes-Alvarez, Victoria Chávez Miñano, and Boris Garro-Barrera received fees for conducting the clinical study at their respective sites from Laboratorios Grossman through Peruvian Clinical Research. Neri Alvarez-Villalobos received fees for writing, editing, and statistical analysis services from Laboratorios Grossman. The sponsor did not participate in data collection or reporting of research results.
The following are Supplementary data to this article:




