



Perioperative care is associated with a substantial risk of preventable harm, yet evidence on effective non-clinical safety strategies remain fragmented. This umbrella review, conducted within the framework of the European SAFEST project, aims to synthesise evidence of non-clinical interventions to improve patient safety in adult perioperative care.
MethodsPubMed, Scopus, PsycINFO, CINAHL, and the Cochrane Library were searched for systematic reviews and meta-analyses published between January 2012 and April 2025. Eligible reviews included studies meeting Cochrane Effective Practice and Organisation of Care (EPOC) criteria. Methodological quality was assessed using the Joanna Briggs Institute Critical Appraisal Checklist, and findings were synthesised narratively.
ResultsOne hundred systematic reviews were included. Most interventions targeted patients (n=55) and included integrative medicine and strategies for preoperative preparation and education. Forty-one reviews evaluated coordinated perioperative care programmes, mainly Enhanced Recovery After Surgery (ERAS); three evaluated surgical safety checklists and one evaluated simulation training for healthcare professionals. Ninety reviews reported improvement in at least one patient safety outcome. Patient-targeted interventions were most consistently associated with reductions in pain and anxiety, while ERAS programmes and surgical safety checklists were associated with fewer complications, infections, mortality, and shorter hospital stay. Methodological quality was generally moderate to high, however, GRADE was reported in only 23 reviews and most commonly indicated low-to-moderate certainty of evidence.
ConclusionNon-clinical interventions have the potential to improve perioperative patient safety. However, confidence in many findings is limited by substantial heterogeneity and predominantly low-to-moderate certainty of evidence. More rigorous research, standardised outcome reporting, and greater attention to healthcare professional-targeted and intraoperative interventions are needed.
La atención perioperatoria conlleva un alto riesgo de daños prevenibles; sin embargo, la evidencia sobre la efectividad de las intervenciones no clínicas de seguridad sigue siendo fragmentada. Esta revisión de revisiones sistemáticas, realizada en el marco del proyecto europeo SAFEST, tuvo como objetivo identificar y sintetizar la evidencia sobre intervenciones no clínicas destinadas a mejorar la seguridad del paciente en la atención perioperatoria de los adultos.
MétodosSe realizaron búsquedas en PubMed, Scopus, PsycINFO, CINAHL y la Biblioteca Cochrane para identificar revisiones sistemáticas y metaanálisis publicados entre enero de 2012 y abril de 2025, que incluyeran estudios con diseños elegibles según los criterios de la Cochrane Effective Practice and Organisation of Care (EPOC). La calidad metodológica se evaluó mediante la lista de verificación del Instituto Joanna Briggs. También se extrajeron las evaluaciones de certeza comunicadas por las revisiones y se realizó una síntesis narrativa según el destinatario de la intervención, la fase perioperatoria y el resultado en seguridad de la atención.
ResultadosSe incluyeron 100 revisiones sistemáticas. La mayoría evaluó intervenciones aplicadas durante todo el periodo perioperatorio, mientras que solo tres se centraron en el periodo intraoperatorio. La mayoría de las intervenciones se dirigieron a los pacientes (n=55), incluyendo intervenciones de medicina integrativa y estrategias de preparación y educación preoperatoria. Cuarenta y una revisiones evaluaron programas coordinados de atención perioperatoria, principalmente programas de recuperación mejorada después de la cirugía (Enhanced Recovery After Surgery, ERAS); tres evaluaron intervenciones organizativas basadas en listas de verificación de seguridad y una evaluó la formación mediante simulación dirigida a profesionales sanitarios. Noventa revisiones comunicaron una mejoría estadísticamente significativa en al menos un resultado, aunque la evidencia procedía de revisiones con solapamiento de estudios primarios. Las intervenciones dirigidas a los pacientes se asociaron con reducciones del dolor y la ansiedad, mientras que las intervenciones coordinadas y organizativas mostraron potencial para reducir complicaciones, infecciones, mortalidad y estancia hospitalaria. La calidad metodológica fue, en general, de moderada a alta, pero solo 23 revisiones informaron evaluaciones GRADE, que mayoritariamente indicaron una certeza de le evidencia baja o moderada y la heterogeneidad fue considerable.
ConclusiónLas intervenciones no clínicas tienen potencial para mejorar la seguridad del paciente a lo largo del proceso asistencial perioperatorio, pero la evidencia sigue siendo insuficiente para formular recomendaciones firmes. Se necesitan investigaciones más rigurosas, especialmente sobre intervenciones dirigidas a los profesionales sanitarios y en el periodo intraoperatorio.
The perioperative care process, which encompasses the entire patient journey before, during, and after surgery, is crucial to patient safety.1 Harm is more likely to occur in perioperative care than in other healthcare settings due to the complexity of surgical environments and procedures. Over 300 million surgical procedures are performed every year worldwide, and at least 4.2 million people die within 30 days of surgery.2 Patient safety incidents are events that could have or did cause unnecessary harm to patients, such as errors, violations, patient abuse, negligence, and unsafe acts.3 Around 10% of patients admitted to hospitals experience harm due to patient safety incidents.4 Most reported adverse events relate to perioperative care.4 Adverse events have been found to cause serious complications for patients, with approximately 12% of preventable harm incidents resulting in permanent disability or patient death,5 and to increase healthcare costs.6 In developed countries, the cost of treating patients who have been harmed accounts for some 13% of health spending.7 Adverse events also cause distress to healthcare professionals.8 Around half of adverse events are considered avoidable,9 highlighting the need for patient safety interventions.10
Although many interventions have been widely implemented to reduce patient harm,11–16 their success rates vary15,17 and they have not led to significant large-scale improvement.18,19 As several factors influence patient safety, improving it requires many types of intervention.20 Interventions can be classified into clinical, such as medical procedures and treatments, and non-clinical, referring to any work by care providers and patients that focuses on supporting clinical interventions in the patient's care and service pathway.21 Non-clinical interventions target patients through education and information, healthcare professionals through clinical practice guidelines, and healthcare organisations by improving structures, processes, the environment, and organisational culture.21,22
Recent systematic reviews on perioperative patient safety have tended to focus separately on non-clinical interventions for patients,23–25 healthcare professionals,26,27 and organisations.28–30 Given the numerous reviews on the nature and effectiveness of single non-clinical interventions for improving perioperative patient safety, there is a need to summarise the available evidence.
This umbrella review was conducted within the framework of the European Union-funded SAFEST project, with the aim of supporting the implementation of evidence-based patient safety practices across the perioperative care pathway. The aim of this umbrella review is to summarise the evidence from these numerous existing reviews of non-clinical interventions on patient safety in the perioperative care process in adult patients, and identify effective evidence-based interventions for use in clinical practice.
The research questions are:
- •
What evidence-based non-clinical interventions are available to improve patient safety in the perioperative care process for adult patients?
- •
How effective are these interventions?
We followed the guidance of Aromataris et al.31 on umbrella reviews to systematically assess and summarise findings from multiple systematic reviews and meta-analyses.31–33 The data were analysed using the narrative synthesis method.34 A protocol for the umbrella review was registered in PROSPERO (CRD42023397419).35
Search strategyWe applied an electronic and manual search strategy to ensure comprehensive coverage of the relevant literature. For the electronic searches, we searched five databases: PubMed, Scopus, PsycINFO, the Cumulative Index to Nursing and Allied Health Literature (CINAHL), and the Cochrane Library. With the help of an information specialist, a search strategy was developed and adapted to each database. This consisted of four core concepts and terms relating to: (1) perioperative care, (2) patient safety outcomes, (3) non-clinical interventions, and (4) systematic reviews (Appendix 1). We conducted an initial search in November 2022, covering scientific peer-reviewed papers published between 01.01.2012 and 14.11.2022. We did not set limits on the publication language. To ensure the umbrella review reflected the most current evidence, we performed an updated search in April 2025, including scientific peer-reviewed papers published between 01.11.2022 and 07.04.2025. Both searches were conducted in the same databases using the same search strategy and eligibility criteria. Manual searches were performed on the reference lists from the included papers, using the same limitations and inclusion criteria as those for the electronic searches.
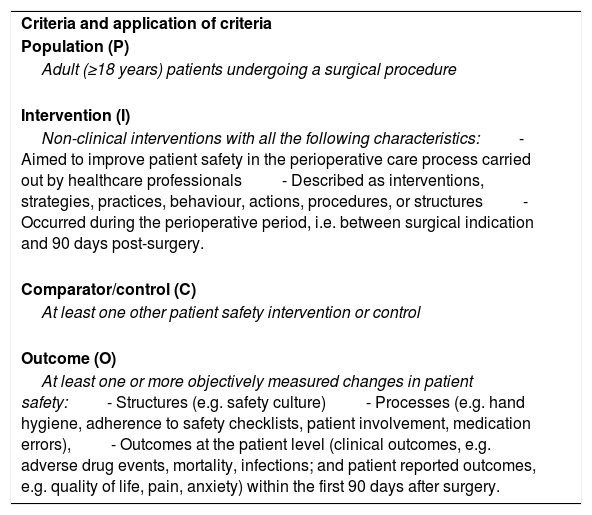
Selection of papersOur inclusion criteria were based on the PICO (Population, Intervention, Comparator/Control, Outcome) framework (Table 1). Systematic reviews were included if they included studies meeting the Cochrane Effective Practice and Organisation of Care (EPOC) criteria (possibly combined with observational studies if the results were analysed separately). EPOC criteria include four types of study design: randomised trials, non-randomised trials, controlled before-after studies, and interrupted time series studies and repeated measures studies.36 Other criteria for including reviews were that they: studied effect evaluations of non-clinical patient safety interventions, and involved more than one single surgical subspecialty (unless there is no doubt that the method used is applicable to other surgical specialities); provided a clear description of the methodology (design of the included studies), population of interest, intervention, and results; and reported quantitative effect measure(s) or outcome(s).
Inclusion criteria based on the PICO framework.
| Criteria and application of criteria |
| Population (P) |
| Adult (≥18 years) patients undergoing a surgical procedure |
| Intervention (I) |
| Non-clinical interventions with all the following characteristics:- Aimed to improve patient safety in the perioperative care process carried out by healthcare professionals- Described as interventions, strategies, practices, behaviour, actions, procedures, or structures- Occurred during the perioperative period, i.e. between surgical indication and 90 days post-surgery. |
| Comparator/control (C) |
| At least one other patient safety intervention or control |
| Outcome (O) |
| At least one or more objectively measured changes in patient safety:- Structures (e.g. safety culture)- Processes (e.g. hand hygiene, adherence to safety checklists, patient involvement, medication errors),- Outcomes at the patient level (clinical outcomes, e.g. adverse drug events, mortality, infections; and patient reported outcomes, e.g. quality of life, pain, anxiety) within the first 90 days after surgery. |
We excluded papers if they focused on patient-safety interventions prior to surgical indication (screening and diagnosis); concerned a specific population or procedure which was not generally applicable to other patient groups or in other surgical procedures; or lacked a full description of the intervention or information on components of the intervention.
Studies were selected in stages based on title, abstract, and full-text assessment. Initial screening based on title and abstract was carried out independently by two researchers from a team of three (JK, JP, KP). Selection based on full texts was also conducted independently by two researchers from the wider research team (JK, JP, MK, AHC, YE, HC, KP), with one researcher (JK) leading the process in both phases and two researchers (JP, KP) participating in both to ensure consistency and coherence. Disagreements were resolved through discussion between the two reviewers or by a third reviewer where consensus was not reached. The Rayyan online screening application37 was utilised to support the screening process.
Quality assessmentThe methodological quality of each included study was assessed independently by two reviewers from the research team (JK, JP, MK, AHC, YE, HC, KP) using the Joanna Briggs Institute (JBI) Critical Appraisal Checklist for Systematic Reviews and Research Synthesis.31 The JBI checklist was suitable for this review as it fits the aim and character of our research. The checklist consists of eleven criteria, each assessed dichotomously as yes/no (1/0 point). If information was inadequate or unknown, it scored 0. Disagreements as to whether the criteria were met were resolved by the third reviewer.
Additionally, we extracted the certainty of evidence assessments reported by each included review, including the Grading of Recommendations Assessment, Development, and Evaluation (GRADE)38 assessment (high/moderate/low/very low/not reported), assessment of the risk of bias (low/mixed/high/not reported), heterogeneity (low/moderate/high/not reported) and publication bias (no evidence detected/suspected/present/not reported).
Data extractionA data extraction form based on The National Institute for Health and Clinical Excellence (NICE) Glossary39 was used to extract the data. For each selected study, we extracted author(s), year, country, aim of the study, and study design. We also extracted the perioperative phase of the study, target group, sample size, type of intervention, patient outcome, and statistical data on effectiveness. Data from each study included in the review were extracted independently by two researchers from the research team (JK, JP, MK, AHC, YE, HC, KP) independently. Disagreements were resolved through discussion and the research team was consulted if necessary.
Data synthesis and analysisWe analysed the data using the narrative synthesis method.34 Interventions were deductively classified according to the World Health Organisation (WHO) framework for non-clinical interventions21 as targeting patients, healthcare professionals, or organisations. Outcomes were grouped into (1) clinical outcomes, such as complications, infections, other adverse events, mortality, morbidity, readmission, re-operation, length of hospital stay, and operation time; and (2) patient-reported outcomes such as quality of life, pain, and anxiety. Within these categories, the individual outcomes were retained and reported according to the terminology used in the original systematic reviews. To improve conceptual clarity, outcomes were classified using mutually exclusive definitions. Complications referred to postoperative clinical complications reported by the original reviews. Infections were treated as a specific subgroup of complications and reported separately when explicitly identified. Morbidity referred to composite measures of postoperative disease burden or overall morbidity indices. Other adverse events were defined as unintended harmful events not classified as complications or infections. Where reviews used different terminology, the original definitions were retained and reported accordingly. We present the results as a narrative synthesis due to the heterogeneity in participants, contexts, interventions, and effect measures, making meta-analysis impractical.34 Effect estimates are reported together with their statistical significance, where available.
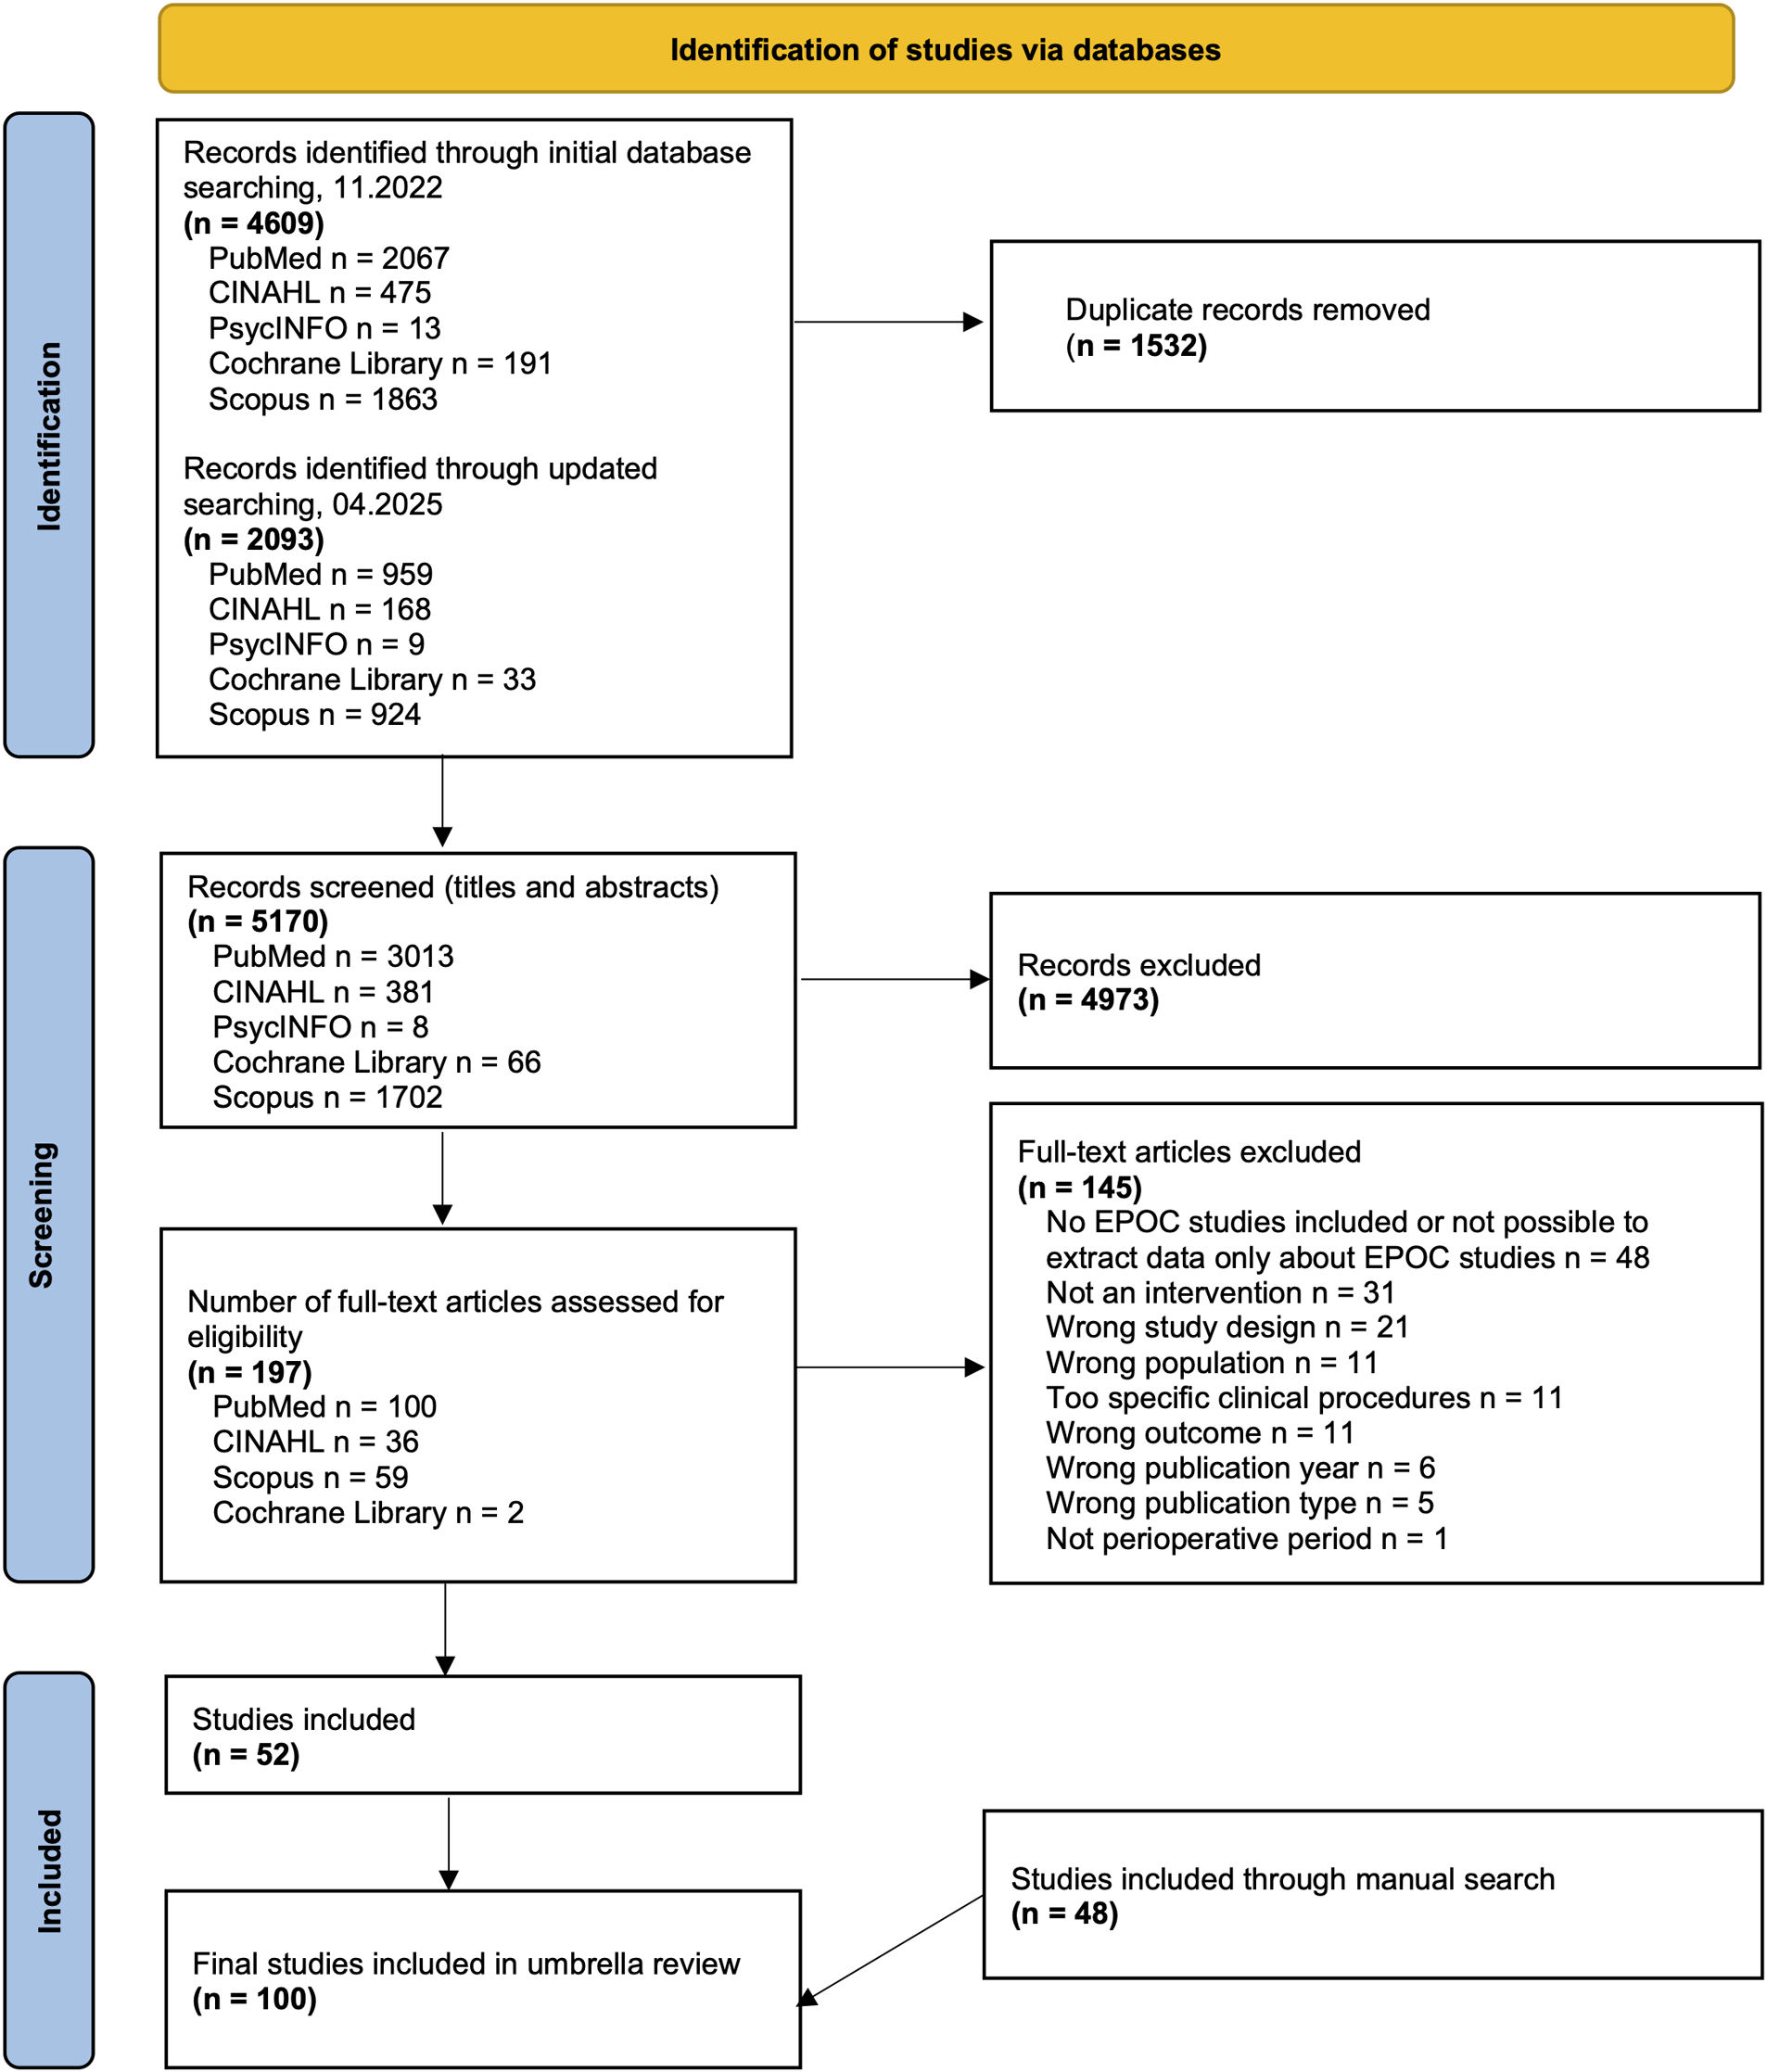
ResultsStudy screeningThe initial search (November 2022) identified 4609 records, and the updated search (April 2025) identified 2093 additional records. After deduplication, this yielded 5170 records for title/abstract screening, then full-text screening of 197 records from which 52 studies met the inclusion criteria and were thus included in the umbrella review (Fig. 1). The main reasons for excluding studies were that no EPOC studies were present in the data, it was not possible to extract the EPOC studies from the data, and that no intervention was conducted (Appendix 8). An additional 48 studies were selected through a manual search of the reference lists of the included studies (Appendix 1). In total, 100 systematic reviews and meta-analyses were included in the umbrella review. All included studies were in English.
Description of the included reviews
The 100 included reviews incorporated 33 meta-analyses,40–72 57 meta-analyses and systematic reviews,24,26,73–127 and 10 systematic reviews.128–137 The number of primary EPOC criteria studies included in reviews ranged from 1 to 105. The total number of primary studies included in this umbrella review was 1782 (with overlaps). The primary studies were conducted between 2012 and 2025 and encompassed regions across Europe, North and South America, Asia, the Middle East, Australia and Oceania, and Africa. The sample size for the intervention group ranged from 30 to 10,283, and for the control group, from 28 to 6704 (Appendix 2).
Methodological quality of the included reviewsOverall, the methodological quality of the included reviews was moderate to high (mean (±SD) fulfilled criteria 8.85±1.63) with total scores ranging from 4–11. One review26 received the lowest score (4), while 6 reviews57,58,68,96,128,133 received the highest score (11). Most studies (n=61)24,26,43–48,50,54,56,60,62–64,66,67,69–74,78,79,82–84,86,88,90–93,95,98,99,101–104,106–109,111,113–120,124,126,127,130–132,135 lacked clearly stated review questions. No reviews were excluded on the basis of methodological quality (Appendix 3).
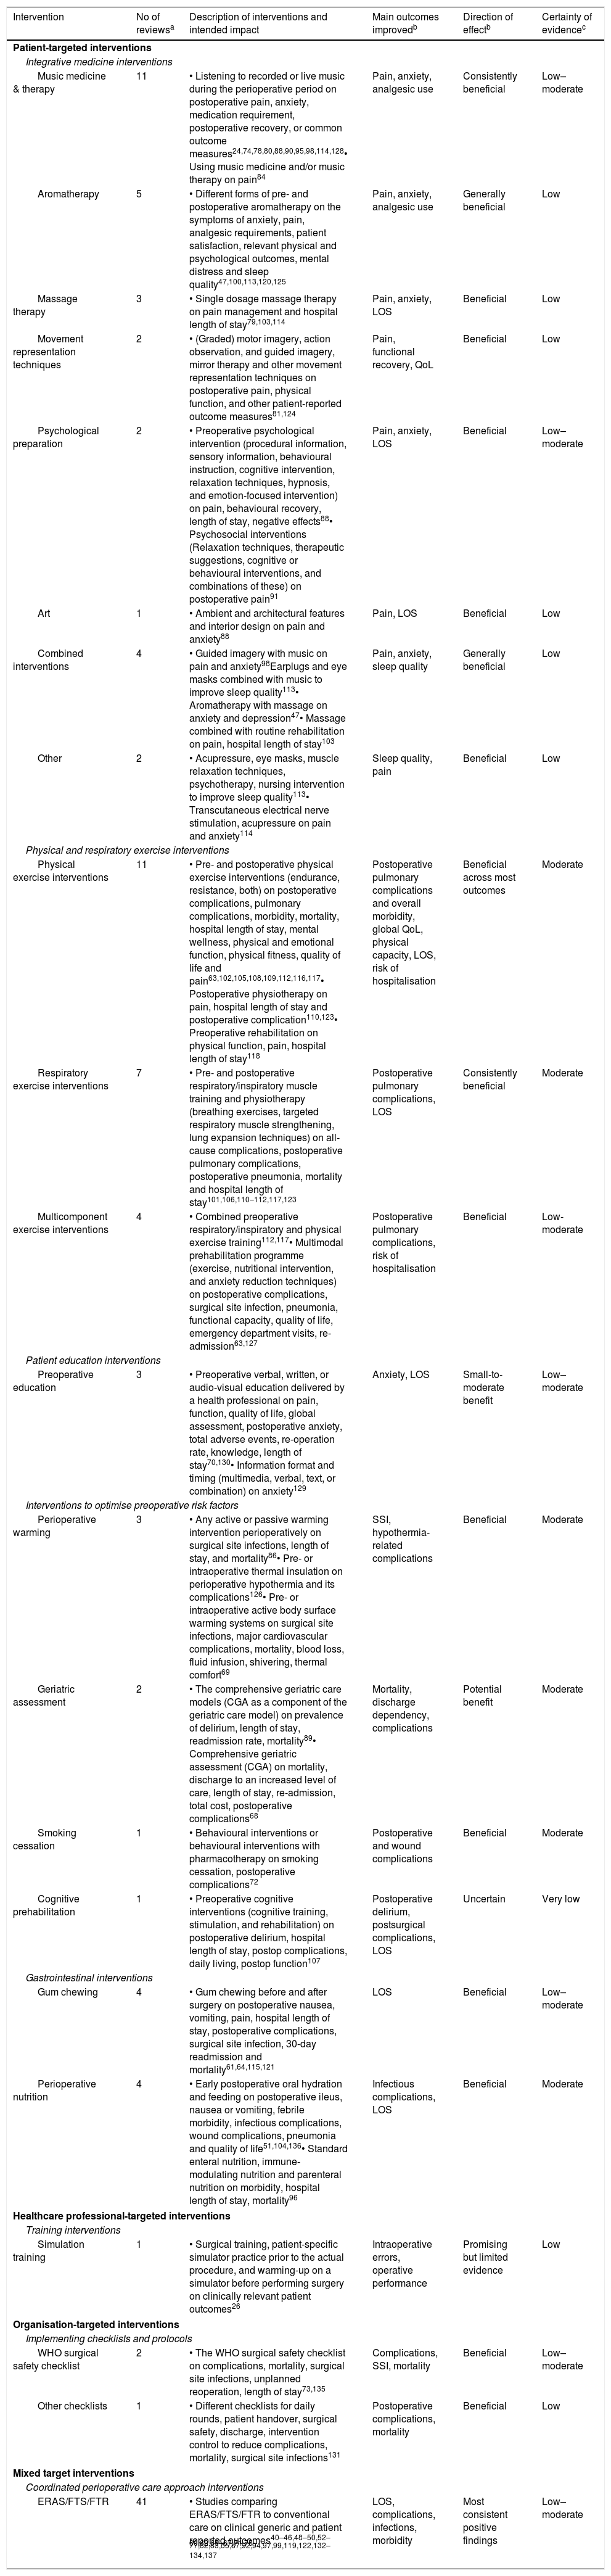
Certainty of evidence of the included reviewsCertainty of evidence was generally limited. Most reviews (n=77) did not report GRADE assessments, while among those that did (n=23),58,61,68–70,72,77,88–91,101,102,104,105,107,124–128,133,136 ratings most commonly ranged from low to moderate. Downgrading was primarily due to methodological limitations of included studies, substantial heterogeneity in interventions and outcomes, imprecision arising from small study sizes, and limited assessment of publication bias. Exercise-based prehabilitation, smoking cessation, perioperative warming and comprehensive geriatric assessment generally showed the highest certainty of evidence, whereas music, aromatherapy, checklist implementation and ERAS interventions were supported predominantly by low-to-moderate certainty evidence. Risk of bias was assessed in the majority of reviews, with most (n=77) reporting mixed risk of bias across included studies. Heterogeneity was predominantly high across the included reviews, with most reporting consistently high, moderate-to-high, or low-to-high, depending on the outcome. Publication bias was not reported or assessed in approximately half of the included reviews (n=55), with several noting that formal assessment was not feasible due to the small number of included studies. Overall, the certainty of evidence across included reviews was predominantly low to moderate, with considerable methodological heterogeneity and risk of bias representing important limitations when interpreting the findings of this umbrella review. The certainty of evidence across patient safety intervention categories is summarised in Table 2, with detailed certainty of evidence assessments for all included reviews reported in Appendix 4.
Summary of patient safety interventions for perioperative care, their effectiveness and certainty of evidence (n=100 systematic reviews).
| Intervention | No of reviewsa | Description of interventions and intended impact | Main outcomes improvedb | Direction of effectb | Certainty of evidencec |
|---|---|---|---|---|---|
| Patient-targeted interventions | |||||
| Integrative medicine interventions | |||||
| Music medicine & therapy | 11 | • Listening to recorded or live music during the perioperative period on postoperative pain, anxiety, medication requirement, postoperative recovery, or common outcome measures24,74,78,80,88,90,95,98,114,128• Using music medicine and/or music therapy on pain84 | Pain, anxiety, analgesic use | Consistently beneficial | Low–moderate |
| Aromatherapy | 5 | • Different forms of pre- and postoperative aromatherapy on the symptoms of anxiety, pain, analgesic requirements, patient satisfaction, relevant physical and psychological outcomes, mental distress and sleep quality47,100,113,120,125 | Pain, anxiety, analgesic use | Generally beneficial | Low |
| Massage therapy | 3 | • Single dosage massage therapy on pain management and hospital length of stay79,103,114 | Pain, anxiety, LOS | Beneficial | Low |
| Movement representation techniques | 2 | • (Graded) motor imagery, action observation, and guided imagery, mirror therapy and other movement representation techniques on postoperative pain, physical function, and other patient-reported outcome measures81,124 | Pain, functional recovery, QoL | Beneficial | Low |
| Psychological preparation | 2 | • Preoperative psychological intervention (procedural information, sensory information, behavioural instruction, cognitive intervention, relaxation techniques, hypnosis, and emotion-focused intervention) on pain, behavioural recovery, length of stay, negative effects88• Psychosocial interventions (Relaxation techniques, therapeutic suggestions, cognitive or behavioural interventions, and combinations of these) on postoperative pain91 | Pain, anxiety, LOS | Beneficial | Low–moderate |
| Art | 1 | • Ambient and architectural features and interior design on pain and anxiety88 | Pain, LOS | Beneficial | Low |
| Combined interventions | 4 | • Guided imagery with music on pain and anxiety98Earplugs and eye masks combined with music to improve sleep quality113• Aromatherapy with massage on anxiety and depression47• Massage combined with routine rehabilitation on pain, hospital length of stay103 | Pain, anxiety, sleep quality | Generally beneficial | Low |
| Other | 2 | • Acupressure, eye masks, muscle relaxation techniques, psychotherapy, nursing intervention to improve sleep quality113• Transcutaneous electrical nerve stimulation, acupressure on pain and anxiety114 | Sleep quality, pain | Beneficial | Low |
| Physical and respiratory exercise interventions | |||||
| Physical exercise interventions | 11 | • Pre- and postoperative physical exercise interventions (endurance, resistance, both) on postoperative complications, pulmonary complications, morbidity, mortality, hospital length of stay, mental wellness, physical and emotional function, physical fitness, quality of life and pain63,102,105,108,109,112,116,117• Postoperative physiotherapy on pain, hospital length of stay and postoperative complication110,123• Preoperative rehabilitation on physical function, pain, hospital length of stay118 | Postoperative pulmonary complications and overall morbidity, global QoL, physical capacity, LOS, risk of hospitalisation | Beneficial across most outcomes | Moderate |
| Respiratory exercise interventions | 7 | • Pre- and postoperative respiratory/inspiratory muscle training and physiotherapy (breathing exercises, targeted respiratory muscle strengthening, lung expansion techniques) on all-cause complications, postoperative pulmonary complications, postoperative pneumonia, mortality and hospital length of stay101,106,110–112,117,123 | Postoperative pulmonary complications, LOS | Consistently beneficial | Moderate |
| Multicomponent exercise interventions | 4 | • Combined preoperative respiratory/inspiratory and physical exercise training112,117• Multimodal prehabilitation programme (exercise, nutritional intervention, and anxiety reduction techniques) on postoperative complications, surgical site infection, pneumonia, functional capacity, quality of life, emergency department visits, re-admission63,127 | Postoperative pulmonary complications, risk of hospitalisation | Beneficial | Low-moderate |
| Patient education interventions | |||||
| Preoperative education | 3 | • Preoperative verbal, written, or audio-visual education delivered by a health professional on pain, function, quality of life, global assessment, postoperative anxiety, total adverse events, re-operation rate, knowledge, length of stay70,130• Information format and timing (multimedia, verbal, text, or combination) on anxiety129 | Anxiety, LOS | Small-to-moderate benefit | Low–moderate |
| Interventions to optimise preoperative risk factors | |||||
| Perioperative warming | 3 | • Any active or passive warming intervention perioperatively on surgical site infections, length of stay, and mortality86• Pre- or intraoperative thermal insulation on perioperative hypothermia and its complications126• Pre- or intraoperative active body surface warming systems on surgical site infections, major cardiovascular complications, mortality, blood loss, fluid infusion, shivering, thermal comfort69 | SSI, hypothermia-related complications | Beneficial | Moderate |
| Geriatric assessment | 2 | • The comprehensive geriatric care models (CGA as a component of the geriatric care model) on prevalence of delirium, length of stay, readmission rate, mortality89• Comprehensive geriatric assessment (CGA) on mortality, discharge to an increased level of care, length of stay, re-admission, total cost, postoperative complications68 | Mortality, discharge dependency, complications | Potential benefit | Moderate |
| Smoking cessation | 1 | • Behavioural interventions or behavioural interventions with pharmacotherapy on smoking cessation, postoperative complications72 | Postoperative and wound complications | Beneficial | Moderate |
| Cognitive prehabilitation | 1 | • Preoperative cognitive interventions (cognitive training, stimulation, and rehabilitation) on postoperative delirium, hospital length of stay, postop complications, daily living, postop function107 | Postoperative delirium, postsurgical complications, LOS | Uncertain | Very low |
| Gastrointestinal interventions | |||||
| Gum chewing | 4 | • Gum chewing before and after surgery on postoperative nausea, vomiting, pain, hospital length of stay, postoperative complications, surgical site infection, 30-day readmission and mortality61,64,115,121 | LOS | Beneficial | Low–moderate |
| Perioperative nutrition | 4 | • Early postoperative oral hydration and feeding on postoperative ileus, nausea or vomiting, febrile morbidity, infectious complications, wound complications, pneumonia and quality of life51,104,136• Standard enteral nutrition, immune-modulating nutrition and parenteral nutrition on morbidity, hospital length of stay, mortality96 | Infectious complications, LOS | Beneficial | Moderate |
| Healthcare professional-targeted interventions | |||||
| Training interventions | |||||
| Simulation training | 1 | • Surgical training, patient-specific simulator practice prior to the actual procedure, and warming-up on a simulator before performing surgery on clinically relevant patient outcomes26 | Intraoperative errors, operative performance | Promising but limited evidence | Low |
| Organisation-targeted interventions | |||||
| Implementing checklists and protocols | |||||
| WHO surgical safety checklist | 2 | • The WHO surgical safety checklist on complications, mortality, surgical site infections, unplanned reoperation, length of stay73,135 | Complications, SSI, mortality | Beneficial | Low–moderate |
| Other checklists | 1 | • Different checklists for daily rounds, patient handover, surgical safety, discharge, intervention control to reduce complications, mortality, surgical site infections131 | Postoperative complications, mortality | Beneficial | Low |
| Mixed target interventions | |||||
| Coordinated perioperative care approach interventions | |||||
| ERAS/FTS/FTR | 41 | • Studies comparing ERAS/FTS/FTR to conventional care on clinical generic and patient reported outcomes40–46,48–50,52–60,62,65–67,71,75–77,82,83,85,87,92,94,97,99,119,122,132–134,137 | LOS, complications, infections, morbidity | Most consistent positive findings | Low–moderate |
Some reviews included interventions from more than one category. Therefore, a single review may appear multiple times in the table.
Based on the analysis presented in detail in Supplementary file. Infections were considered a subgroup of complications when reported separately by the original reviews (Appendices S6 and S7).
Overall certainty reflects reported GRADE assessments, risk of bias, heterogeneity, imprecision and publication bias across included reviews (Appendix 4).
LOS – length of stay, SSI – surgical site infections, QoL – quality of life.
Patient-targeted interventions were identified in 55 reviews and represented the largest intervention group included in this umbrella review. Reviews focused on interventions delivered across the entire perioperative pathway or during specific perioperative phases and targeted a range of surgical populations, most commonly patients undergoing gastric, colorectal, and orthopaedic surgery. Some reviews included interventions from multiple categories and are therefore reported under more than one intervention group (Table 2).
Integrative medicine interventionsIntegrative medicine interventions were reported in 22 reviews and included music therapy,24,74,78,80,88,90,95,98,114,128 aromatherapy,47,100,113,120,125 massage,79,103,114 movement representation techniques,81,124 psychological preparation,88,91 art,88 combined interventions,47,98,103,113 and other complementary approaches.113,114 This intervention category most consistently improved patient-reported outcomes. Meta-analyses demonstrated statistically significant reductions in pain,74,78–81,84,88,90,91,93,98,100,103,113,114,120,124,125 anxiety,47,70,78–80,84,91,93,95,100 and medication or analgesia use.24,78,120 Additional benefits were reported for quality of life,81 sleep quality,113 and postoperative recovery.88,91 Narrative syntheses supported these findings, reporting improvements in anxiety,90,91,128,129 pain,74,90,91,129 recovery,88,91 quality of life,91,116 opioid requirements,74 and infectious complications.136 One review also reported beneficial effects on hospital length of stay.116
Physical and respiratory exercise interventionsFifteen reviews examined physical exercise,63,102,105,108–110,112,116–118,123 respiratory exercise,101,106,110–112,117,123, and multicomponent exercise interventions.63,112,117,127 Exercise-based interventions showed some of the most consistent effects on clinical outcomes. Meta-analyses reported reductions in pulmonary and postoperative complications,51,69,72,96,102,106,108,109,111,112,117,123 shorter hospital length of stay,102,105,106,108,111,115,118,123 and improvements in quality of life.105,118 Narrative syntheses further suggested improvements in postoperative recovery, functional capacity, quality of life, and length of stay.116,127 Overall, physical and respiratory exercise interventions were associated with improved postoperative recovery and reduced postoperative morbidity, particularly among patients undergoing major abdominal, colorectal, and cardiothoracic procedures.
Patient education and risk optimisation interventionsEighteen reviews focused on patient education,70,129,130 optimisation of preoperative risk factors,68,69,72,86,89,107,126 and gastrointestinal recovery.51,61,64,96,104,115,121,136 Risk-optimisation interventions comprised perioperative warming,69,86,126 geriatric assessment,68,89 smoking cessation,72 and cognitive prehabilitation,107 while interventions targeting gastrointestinal recovery comprised gum chewing61,64,115,121 and perioperative nutrition.51,96,104,136 Meta-analyses demonstrated significant effects on hospital length of stay,61,64,68,70,96 postoperative complications,69,72,96 surgical site infections,69,86,96 mortality,68 discharge to an increased level of care,68 and anxiety.70 Additional positive effects were reported for nutrition-related outcomes and gastrointestinal recovery.51,61,64,96,104,115,121,136 Narrative syntheses suggested that educational interventions improved patient engagement, knowledge, and recovery experiences, although findings for clinical outcomes were less consistent.89,129,130 Reviews of comprehensive geriatric assessment additionally reported effects on functional status 30 days after surgery and on geriatric syndromes and events.89
Healthcare professional-targeted interventionsOnly one review focused exclusively on interventions targeting healthcare professionals.26 This review evaluated surgical simulation training and reported beneficial effects on intraoperative errors, postoperative complications, and overnight hospital stays. Although findings were promising, the evidence base for professional-targeted interventions was limited compared with the evidence available for patient- and organisation-targeted interventions.
Organisation-targeted interventionsThree reviews evaluated organisation-targeted interventions, all of which examined the implementation of surgical safety checklists.73,131,135 The only meta-analysis in this category reported statistically significant reductions in complications, mortality, and surgical site infections following implementation of the WHO Surgical Safety Checklist.135 Narrative syntheses additionally reported reductions in mortality,131,135 complications,135 and unplanned return to the operating theatre.131,135 Overall, checklist-based interventions appeared beneficial, although the evidence base was considerably smaller than that for patient-targeted and ERAS interventions.
Mixed-target interventions: Enhanced Recovery After Surgery (ERAS)Forty-one reviews evaluated interventions targeting both patients and healthcare organisations.40–46,48–50,52–60,62,65–67,71,75–77,82,83,85,87,92,94,97,99,119,122,132–134,137 All reviews in this category examined coordinated perioperative care pathways, including Enhanced Recovery After Surgery (ERAS), Fast Track Surgery (FTS), and Fast Track Recovery (FTR) programmes. These programmes share the same underlying multicomponent model – multidisciplinary teamwork, patient education, risk optimisation, minimally invasive surgical techniques, effective pain management, early mobilisation, and early nutrition139,140 – and are therefore reported together and referred to collectively as ERAS hereafter. This category produced the most extensive evidence base among all intervention categories. Meta-analyses most frequently reported reductions in hospital length of stay,40–44,46,48–50,52,53,55–60,62,65–68,71,76,77,83,87,92,94,97,99,119,122,133 complications,42,43,48–50,55,57–59,62,65–67,82,85,90,94,99,119,122 morbidity,52,54,77,87 infections,54,66,76 readmissions,41,58 and other adverse events.133 Narrative syntheses supported these findings, reporting improvements in length of stay,75,132,137 complications,132,134,137 pain,75,137 and quality of life.52 Taken together, ERAS pathways demonstrated the most consistent evidence of benefit across a broad range of clinical outcomes, particularly length of stay and postoperative complications. However, substantial heterogeneity existed across surgical specialities, programme components, outcome definitions, and implementation approaches.
Outcome measures across intervention categoriesPatient safety interventions were evaluated using both clinical and patient-reported outcomes (Appendix 5). The most frequently reported clinical outcomes were length of hospital stay (n=69) and complications or morbidity (n=57), whereas unplanned reoperation was rarely assessed (n=2). Among patient-reported outcomes, pain (n=30) and anxiety (n=18) were reported most frequently, while sleep quality was reported in only one review. Overall, 90 of the 100 reviews reported statistically significant improvements in at least one patient safety outcome, including 79 reviews containing meta-analyses. Length of stay, postoperative complications, pain, and anxiety were the outcomes most consistently associated with beneficial intervention effects across intervention categories (Table 2; Appendices 6–7). Evidence was most extensive for ERAS pathways and patient-targeted interventions, whereas evidence targeting healthcare professionals remained comparatively limited.
DiscussionThis umbrella review aimed to summarise the existing evidence about non-clinical interventions to improve patient safety in perioperative care for adult patients and to assess the effectiveness of these interventions. An umbrella review was appropriate for this study because it enabled us to systematically assess and summarise findings from multiple systematic reviews and meta-analyses.31,32 We identified interventions associated with improved outcomes across all three perioperative phases: pre-, intra-, and postoperative. However, most of the evidence we reviewed supports interventions that span the entire perioperative period, enabling a comprehensive approach. The intraoperative phase was the least studied in terms of relevant interventions. This taxonomy therefore provides a common conceptual language for future collaborative work within the COST Action BetterCare network and beyond.
According to our findings, most reviews focused on orthopaedic, gastric, and colorectal surgeries. The interventions identified targeted patients, organisations, and healthcare professionals, or involved a combination of these. The most common interventions applicable to patients involved integrative medicine interventions,24,47,74,78–81,84,88,90,91,93,95,98,100,103,113,114,120,124,125,128, such as music therapy, which was evaluated in 11 reviews.24,74,78,80,84,88,90,95,98,114,128 Integrative medicine interventions encompass interdisciplinary and evidence-based approaches of using a combination of traditional and complementary medical knowledge, skills and practices.138 Over the past decade, complementary medicine use in the United States has increased from 19% to 40%, with the most significant rise in pain management.141 While healthcare professionals previously viewed complementary medicine with disapproval, it is now accepted by up to 52% of them.142 However, healthcare professionals feel that they lack the knowledge and research-based education in complementary medicine to discuss it confidently with patients.143
Music therapy and other integrative medicine interventions were frequently associated with improvements in patient-reported outcomes, particularly pain, anxiety, and analgesic requirements.24,47,74,78–81,84,88,90,91,93,95,98,100,103,113,114,120,124,125,128 However, confidence in these findings is limited by substantial heterogeneity in intervention content, timing of delivery, outcome measurement, and study quality, as well as the generally low-to-moderate certainty of evidence reported across reviews. Exercise-based prehabilitation interventions were consistently associated with improved postoperative recovery, including reductions in pulmonary complications, shorter hospital stays, and improved functional outcomes.63,101,102,105,106,108–112,116–118,123,127 However, confidence in these findings is tempered by considerable variation in programme design, exercise intensity, duration, patient populations, and surgical procedures, which limits the ability to identify the most effective intervention components and may affect generalisability across clinical settings.
Interventions targeting organisations comprised checklists73,131,135 while mixed-target interventions used a coordinated perioperative care approach (ERAS/FTS/FTR).40–46,48–50,52–60,62,65–67,71,75–77,82,83,85,87,92,94,97,99,119,122,132–134,137 Simulation training26 was the sole intervention aimed at healthcare professionals, appearing in only one review. Patient safety relies heavily on the safety culture within a healthcare institution as this shapes healthcare professionals’ understanding of the appropriate actions, attitudes, and behaviours.144 We suggest that further investigation into interventions for healthcare professionals is warranted.
Addressing both patient-reported outcomes (PROs) and clinical outcomes is essential for measuring and improving patient safety. In this study, patient-targeted interventions were primarily evaluated in terms of PROs such as pain, anxiety and quality of life, while other interventions focused on clinical outcomes. Surgical safety checklists were associated with reductions in complications, surgical-site infections, and mortality across several reviews,73,131,135 while simulation training enhanced operative performance.26 Nevertheless, interpretation of these findings requires caution, as evidence is derived from diverse healthcare settings with varying levels of checklist implementation, adherence, and organisational support. These factors may influence both the effectiveness and transferability of checklist interventions.
Forty-one systematic reviews evaluated the effectiveness of the ERAS/FTS/FTR protocols,40–46,48–50,52–60,62,65–67,71,75–77,82,83,85,87,92,94,97,99,119,122,132–134,137 showing improvements in several patient safety outcomes, particularly reductions in complications, morbidity, infections, and length of hospital stay. ERAS programmes were consistently associated with improvements in patient safety outcomes; however, confidence in these findings is limited by substantial heterogeneity across populations, intervention components, implementation strategies, outcome definitions, and methodological quality. Given the complexity of ERAS pathways, it remains difficult to determine which individual components contribute most strongly to observed improvements.
Overall, the strongest and most consistent evidence was observed for reductions in length of stay, postoperative complications, pain, and anxiety. This is consistent with wider trends in surgical care, where length of stay has fallen over the past decade alongside a rising proportion of complications occurring after discharge.145 Evidence for mortality, readmissions, adverse events, and quality-of-life outcomes was more limited. While the findings suggest that several non-clinical interventions may improve perioperative patient safety, confidence in these effects is tempered by heterogeneity in outcome definitions, intervention components, and methodological quality across reviews.
Quality and certainty of evidencePatient safety interventions are implemented worldwide, despite incomplete evidence about their effectiveness. To enhance patient safety in an evidence-based way, interventions should be evaluated according to the most stringent standards for research. According to the JBI checklist for systematic reviews,31 most of the systematic reviews and meta-analyses included in our analysis were of moderate to high methodological quality (mean score±SD: 8.85±1.63; range: 4–11), enhancing the credibility and validity of our findings. They scored well in terms of using appropriate inclusion criteria, sources and resources, and methods for combining studies, but less well in terms of clarity of the review question and assessment of publication bias. Most studies lacked clearly stated review questions. We recommend paying more attention to these aspects in future systematic reviews. The highest-scoring reviews evaluated the effectiveness of ERAS, FTS and FTR, music interventions, and geriatric assessments. Meanwhile, the lowest-scoring reviews evaluated simulation training and smoking cessation interventions, highlighting the need for more robust review studies in this field.
The certainty of evidence across this umbrella review was predominantly low. GRADE assessments were absent in most included reviews, the risk of bias was mixed to high across studies, and publication bias was inconsistently evaluated. Although several interventions demonstrated beneficial effects, confidence in these findings remains limited by substantial heterogeneity across interventions, populations, outcome definitions, and measurement methods. A major challenge identified across the evidence base was the inconsistency in outcome reporting. Complications, adverse events, infections, and morbidity were frequently defined and measured differently across reviews, with considerable variation in measurement methods and follow-up periods. Although length of stay, complications, pain, and anxiety were the most frequently reported outcomes, their definitions and assessment approaches were often inconsistent, limiting comparability across studies and contributing to uncertainty in the evidence synthesis. This heterogeneity may partly explain the predominantly low-to-moderate certainty of evidence observed across intervention categories. Future studies would benefit from adopting standardised perioperative patient safety outcomes. The recently developed SAFEST Core Measure Set provides an internationally derived consensus framework for measuring perioperative patient safety and may improve consistency, comparability, and the quality of future evidence.146 Adoption of validated outcome definitions, standardised measurement instruments, and agreed reporting time points may further strengthen future evidence syntheses and support benchmarking across healthcare organisations.
These findings collectively suggest that while non-clinical interventions such as ERAS and music therapy interventions may show promising effects on patient safety outcomes in perioperative care, conclusions must be interpreted with considerable caution. The evidence does not yet support high-confidence recommendations, and future research should prioritise methodological rigour, standardised outcome reporting, and formal certainty-of-evidence grading.
LimitationsThis study should be considered in light of several limitations. One of our inclusion criteria was that reviews had to analyse studies with an EPOC design. EPOC includes randomised controlled trials, non-randomised controlled trials, controlled before-after studies, and interrupted time series, providing stronger evidence-based oversight of effective interventions than other study designs.36 We therefore excluded systematic reviews that included the results of qualitative research and observational studies that analysed non-clinical interventions e.g., pre-and postoperative phone calls,23,147 postoperative handovers,27,148 interdisciplinary collaborative work during surgical ward rounds,27 teamwork, safety climate,149 and the use of surgical checklists148–152 (Appendix 6). The effectiveness of the interventions covered in such qualitative and observational studies requires further research.
Including reviews about ERAS, FTS, and FTR is controversial due to their combination of clinical and non-clinical aspects. However, these protocols encompass several non-clinical elements, such as preadmission counselling, avoidance of prolonged fasting, prevention of intraoperative hypothermia, prevention of postoperative nausea and vomiting, and early oral nutrition and mobilisation.153 Therefore, excluding these reviews would have diminished the overall contribution of this review.
Another limitation of this review is the heterogeneity in interventions, control conditions, patient populations, outcome definitions, methods for measuring outcomes, and assessment times, in addition to a high degree of clinical diversity. This made meta-analysis impractical as a way of pooling study results, so we used narrative synthesis instead. A major limitation of narrative synthesis is subjectivity and a lack of transparency, making it difficult to follow the process and replicate findings or assess their validity.34 To overcome this limitation, we described the literature search, selection, assessment, data extraction, and synthesis processes in detail. The rigour of the study was improved using manual searches which identified almost half of the included studies. This raises a question as to whether the search terms used were appropriate. Based on our evaluation, systematic reviews identified through manual searching generally used similar terms but not the word “intervention”, which was one of our search terms, in their title or abstract.
A variety of outcomes were reported in the included reviews. These outcomes encompassed both patient safety and broader clinical outcomes, such as bleeding, time to first flatus, or pneumonia. Because our review focused on patient safety outcomes, some clinically relevant outcomes were not discussed in detail. The substantial diversity of reported outcomes also increased the complexity of evidence synthesis and interpretation.
Practical implications for perioperative careDespite limitations in certainty, several findings may inform practice. Healthcare organisations may consider structured perioperative pathways such as ERAS programmes and implementation of surgical safety checklists, as these interventions showed the most consistent associations with improved patient outcomes. Patient-centred interventions such as music therapy, psychological preparation and prehabilitation may be particularly useful for improving pain, anxiety and recovery experiences. Successful implementation requires multidisciplinary collaboration, local adaptation and ongoing evaluation.
Most interventions had multiple components, resulting in limited evidence about which specific components were responsible for the observed improvements, making it challenging to establish clear best practices. Policymakers and healthcare professionals should therefore remain cautious when implementing new interventions and may need to draw on a combination of evidence, clinical judgement, and patient preferences. To strengthen the evidence base, future research should prioritise well-designed multicentre trials with rigorous methodology, standardised intervention reporting and consistent outcome definitions. Greater use of core outcome sets, routine application of GRADE methodology, and assessment of publication bias would improve the certainty and comparability of evidence. Further research is particularly needed for interventions targeting healthcare professionals and intraoperative safety processes, areas that remain substantially underrepresented despite their potential importance for improving perioperative patient safety. Standardised definitions and reporting of safety outcomes are needed, alongside more comprehensive reporting of implementation outcomes and long-term sustainability. In addition, the methodological rigour of systematic reviews and meta-analyses should be strengthened through the routine use and reporting of GRADE assessments and evaluations of the certainty of evidence.
ConclusionThis umbrella review synthesised evidence on non-clinical interventions aimed at improving patient safety across the perioperative care pathway. The evidence base was extensive for patient-targeted approaches and coordinated ERAS/FTS/FTR pathways but sparse for healthcare professional-targeted and specifically intraoperative interventions.
Patient-targeted interventions, including music therapy and other integrative medicine approaches, prehabilitation and exercise programmes, and educational and risk-optimisation strategies, were associated with improvements in pain, anxiety, recovery, and selected clinical outcomes. Organisation-targeted interventions, particularly surgical safety checklists, were associated with reductions in complications, surgical-site infections, and mortality. The strongest and most extensive evidence base was observed for mixed-target interventions, especially ERAS programmes, which were consistently associated with shorter hospital stays and fewer postoperative complications and infections.
Despite these encouraging findings, the overall certainty of evidence was predominantly low to moderate. Interpretation of effectiveness is limited by substantial heterogeneity in intervention components, patient populations, outcome definitions, measurement methods, and methodological quality. Inconsistent reporting of complications, adverse events, infections, and morbidity further reduced comparability across studies and contributed to uncertainty in the evidence base.
Future research should prioritise rigorous multicentre studies, standardised intervention reporting, and consensus-based perioperative patient safety outcomes. Wider adoption of frameworks such as the SAFEST Core Measure Set may improve consistency and comparability across studies and strengthen the evidence supporting perioperative patient safety interventions.
Declaration of generative AI and AI-assisted technologies in the manuscript preparation processDuring the preparation of this work the authors used Microsoft 365 Copilot (version 4.0) for language editing to enhance clarity and coherence. After using this tool, the authors reviewed and edited the content as needed and take full responsibility for the content of the published article.
FundingThis work was supported by the European Union under the Horizon Europe Research and Innovation Programme under the grant agreement No. 101057825. The funder had no role in study design, data collection and analysis, decision to publish, or preparation of the manuscript.
Conflict of interestThe authors declare no conflict of interest.
We thank the information specialist of Medical Library of Radboud University Medical Centre Alice Tillema for providing feedback and help in developing our search strategy. The authors would also like to thank the SAFEST consortium members for their contribution: Ana Beatriz Nunes, Andreia Leite, Ashish Bartakke, Ayshe Seyfulayeva, Caroline Schlinkert, Cathy Weynants, Claudia Valli, Cordula Wagner, Daniel Arnal-Velasco, David Marx, Edoardo De Robertis, Eva Romero-Garcia, Frantisek Vlcek, Genis Carrasco, Helena Vall, Irene Leon, Ismael Martínez-Nicolás, Javier García-Silva, Joaquim Baneres, Joel Starkopf, Lilian Van Tuyl, Marie Nabbe, Marieke Voshaar, Nina van der Schoot, Neus Fabregas, Pascal Garel, Pedro Casaca-Carvalho, Rosa Sunol, Sandro Zamarian, Sophie Wang, Victor Soria-Aledo, Willemijn Schäfer, and Yolanda Sanduende-Otero.
The following are the supplementary data to this article:




