

Edited by: Assoc. Professor Joaquim Reis
(Piaget Institute, Lisbon, Portugal)
Dr. Luzia Travado
(Champalimaud Foundation, Lisboa, Portugal)
Dr. Michael Antoni
(University of Miami, Coral Gables, Florida, United States of America)
Last update: March 2026
More infoPrevious studies show positive results when acceptance and commitment therapy is used in the treatment of cancer patients.
ObjectivesTo establish the efficacy of acceptance and commitment therapy in the treatment of common symptoms in cancer patients using trials with an adequate level of control.
MethodsSixty-nine patients affected by different types of cancer (breast, gynecologic, lung, colorectal and ovarian) were recruited and randomly assigned to three experimental conditions defined as follows: the ACT group, the ACT+ACT-ON group, and the waitlist group. Data relating to psychological inflexibility, fatigue, insomnia, anxiety and depression, post-traumatic growth as well as quality of life were collected before (T0) and at the end of the intervention (T1).
ResultsResults showed better outcomes for the two intervention groups, but significant differences were only observed with regard to fatigue (ω2 = .074), where the ACT group obtained lower scores. This group also showed higher scores for post-traumatic growth (ω2 = .066). Similarly, in the quality-of-life subscales, results indicate significantly higher scores for physical role (ω2 = .062) and cognitive function (ω2 = .087), and lower scores for fatigue (ω2 = .118) than in the waitlist group.
ConclusionsPreliminary results suggest that acceptance and commitment therapy is effective in improving relevant aspects such as fatigue, post-traumatic growth and key aspects of quality of life in cancer patients. However, the benefits of using the mobile application need to be confirmed.
Cancer continues to be a global health problem today. An estimated 20 million new cases of cancer were diagnosed in 2022, a figure that is expected to reach an even higher number by 2045 at around 32 million new cancer cases worldwide (Ferlay et al., 2024a). Globally, the most common types of cancer in both sexes are lung (12.4%), breast (11.5%) as well as colon and rectum (9.6%) (Ferlay et al., 2024b). A similar pattern can be observed in Spain, with an estimated 296,103 new cancer cases in 2025, and a gradual increase expected to reach 350,000 cases by 2050 (Sociedad Española de Oncología Médica [SEOM], 2025). In Spain, colon and rectum (15%), breast (12.7%), and lung (11.6%) account for the highest number of new diagnoses (SEOM, 2025).
In cancer patients, it is common to observe psychological alterations such as higher levels of anxiety, depression and a poorer quality of life, as well as other related symptoms (Dinapoli et al., 2021; Hashemi et al., 2020; Zamani & Alizadeh-Tabari, 2021). Among the psychological interventions that have been tested to reduce the presence of these symptoms, cognitive behavioral therapy (CBT) and, more recently, acceptance and commitment therapy (ACT) have shown positive results in increasing psychological flexibility and reducing pain, anxiety, fear of recurrence, depression, and fatigue, but the results are currently inconsistent (Li et al., 2021; Salari et al., 2023; Semenenko et al., 2023; Zhao et al., 2021). In this sense, it is possible that the efficacy of ACT in this population derives from promoting in patients a realistic way to cope with their illness, rather than a change in dysfunctional thoughts, which is the core of traditional psychological interventions such as CBT (Fashler et al., 2018; Sauer & Weißflog, 2022).
On the other hand, in recent years there has been an increase in the use of psychological interventions in this type of patients using technological devices (i.e., smartphones), and they show promising results. The main advantage of these technologies is that they reduce the barriers of time and space, and increase the accessibility of the interventions, showing promising results in reducing depression, anxiety, and improving patients' quality of life (Luo et al., 2022; Willems et al., 2020; Yang et al., 2022). However, those results were obtained in trials that were characterized by certain limitations, such as reduced sample sizes, which suggests the need for more rigorous trials in order to provide accurate data about the impact of these techniques on the psychological wellbeing of cancer patients (Getu et al., 2021; Li et al., 2021; Richardson et al., 2019).
This article presents the preliminary results of a randomized controlled trial aimed to establish the greater efficacy of an ACT-based intervention that is complemented with the use of a smartphone application offering exercises and support activities (ACT-ON), when compared with a group that received a face-to-face ACT intervention without technological support, and with a waitlist control group. The starting hypothesis of this work is that the group receiving the face-to-face + ACT-ON intervention will achieve a greater reduction in anxiety, depression, insomnia and fatigue, and a greater improvement in quality of life at the end of the intervention, when compared to the group receiving the face-to-face ACT intervention, as well as the waitlist control group.
Material & methodsParticipantsThe participants were cancer patients (men and women) in stages I-III, who were aged 18–70, were suffering from different cancer types (breast, lung, colorectal and ovarian), were eligible for cancer treatment, fluent in Spanish, had a smartphone with internet access, and basic app skills. Individuals who were currently participating in other clinical trials or receiving other psychological interventions were excluded.
InstrumentsAcceptance and Action Questionnaire- II (AAQ-II). This questionnaire, designed to assess experiential avoidance and psychological inflexibility, uses 7 items that are answered on a Likert-type scale from 1 (never true) to 7 (always true). As for the results, a higher score indicates greater experiential avoidance. The questionnaire has proven to have good psychometric properties in both the original version (α = 0.84) and in the Spanish adaptation (α = 0.75 - 0.93) (Ruiz et al., 2013). It is also frequently used in ACT research in cancer patients (González-Fernández & Fernández-Rodríguez, 2019).
Hospital Anxiety and Depression Scale (HADS). This instrument is designed to assess anxiety and depression in hospital settings, and uses 14 items divided into two subscales (7 for anxiety and 7 for depression). The patients’ answers are measured on a scale ranging from 0 to 3, with maximum values of 21 for each of the subscales. The established cut-off points for anxiety and depression are a score of 8 (probable case) or above (Zigmond & Snaith, 1983). This scale shows good psychometric properties in the Spanish sample (α = 0.86) (Terol-Cantero et al., 2015).
Brief Fatigue Inventory (BFI). This inventory was developed to assess fatigue in cancer patients, using 10 items with a Likert-type scale in order to obtain scores for the fatigue experienced during the previous 24 h, ranging from 0 (no fatigue) to 10 (worst fatigue imaginable). In addition, the inventory includes questions relating to the level of interference of fatigue with patients’ daily lives during the previous 24 h, with the scale ranging from 0 (does not interfere) to 10 (completely interfered). In cancer patients, the suggested cut-off points are as follows: 1–3 (mild); 4–7 (moderate) and 8–10 (severe) (Chang et al., 2007). The scale has shown good psychometric properties in the original (α = 0.96) (Mendoza et al., 1999) and the Spanish version (α = 0.97) (Lorca et al., 2016).
Insomnia Severity Index (ISI). This is a questionnaire that has been developed to assess the severity of sleep onset, sleep maintenance, and early morning awakening problems, along with satisfaction with sleep pattern, interference with daily functioning, noticeability by others of impairment attributed to the sleep problem, and degree of distress or concern related to the sleep problem. The answers of the participants are scored on a scale ranging from 0 (not at all) to 4 (very severe / very dissatisfied / very much). The scores from the answers are added up to obtain a total score ranging from 0 to 28, with the following cut-off points: 0–7 (absence of clinical insomnia), 8–14 (subclinical insomnia), 15–21 (moderate clinical insomnia), and 22–28 (severe clinical insomnia). The psychometric properties of the instrument are adequate in its original (α = 0.91) and the Spanish version (α = 0.82) (Bastien et al., 2001; Fernandez-Mendoza et al., 2012).
EORTC QLQ C-30 (version 3). This is a questionnaire developed to assess the quality of life in cancer patients, which uses 30 questions that refer to the cancer-related symptoms experienced by patients during the previous week. It consists of twenty-eight questions answered on a scale from 1 (not at all) to 4 (a lot). The last two questions ask patients about their perception of their global health and quality of life on a scale from 1 (terrible) to 7 (excellent). The questions are grouped into different subscales: functional (physical / role / emotional / cognitive / social and global), and symptom (fatigue / nausea and vomiting / dyspnea / sleep problems / loss of appetite / constipation / diarrhea and financial impact). The raw scores are transformed into standardized scores that are interpreted as follows on a range of 0–100: the functional scales (higher score indicates better functioning), the symptom scales (higher score indicates greater presence of symptomatology), and the global quality of life scale, where a higher score indicates a better quality of life. This instrument has been designed to be used in cancer patients, demonstrating good psychometric properties in its Spanish version (α > 0.70) (Aaronson et al., 1993).
Post-traumatic Growth Inventory Short version (PTGI-SF). This is an instrument designed to assess the positive changes that people may experience after a traumatic event. It uses 10 items on a scale from 1 (have not experienced that change) to 6 (I have experienced that change to a great extent) where higher scores indicate greater post-traumatic growth. The instrument has adequate psychometric properties in the original and its adaptation to Spanish (0.83–0.90) (Castro et al., 2015; Tedeschi & Calhoun, 1996)
Participants also completed a questionnaire collecting information relating to clinical and sociodemographic data.
InterventionA detailed description of the interventions is included in the published protocol of this trial (García-Torres et al., 2022). In summary, the two ACT groups received the same interventions consisting of eight face-to-face sessions distributed as follows: 1. Basic principles of the intervention and establishment of the therapeutic alliance 2. Psychoeducation and first contact with mindfulness 3. Creative hopelessness 4. Understanding the importance of a value-based life 5. Defusion and deliteralisation of private events 6. Analyzing the problem of control and acceptance as an alternative 7. Analysis of personal values and the barriers to their realization and, in the last session, review of contents and resolution of doubts. The ACT+ACT-ON group, in addition to participating in the aforementioned face-to-face sessions, carried out activities and exercises using a mobile application (ACT-ON) designed by the research team for use on android devices. The feasibility, usability and description of the app was published previously (García-Torres et al., 2023). The waitlist control group received the usual care provided by the oncology services.
Statistical analysisFirst, only the participants who completed the interventions were included in the final analysis. One-Way ANOVA and chi squared (χ2) were used to analyze the differences in continuous and categorical variables respectively, and in sociodemographic and clinical variables before intervention (T0). In order to assess the differences between the groups after the intervention (T1), One-Way ANOVA and the Bonferroni post hoc test were used to establish which differences could be observed between the groups. The omega squared (ω2) was calculated to estimate the effect sizes of the differences with the following categories: 0.01 (small); 0.06 (medium) and 0.14 (large) (Field, 2013). Finally, significance level was established if p < .05
ProcedureThis article presents preliminary results including pre- and post-intervention measures for the ACT + ACT-ON, ACT only, and the waitlist control group. Participants were recruited between February 2022 and January 2024 at the [BLINDED FOR REVIEW]. Once patients agreed to participate in the study, they signed a written informed consent form, which informed them of the confidentiality of the results, indicating that the data obtained will be used for research purposes only, and that they were able to leave the trial at any time without the need to provide explanation, and without risking negative consequences of any sort. Subsequently, they were randomly assigned to one of the groups established in the design, and the planned one-hour interventions were carried out during a period of eight weeks. The therapists in charge of carrying out the interventions were previously trained in the use of the techniques to be applied, using a manual prepared by the research team. The interventions were carried out in a room prepared for this purpose, which included projectors, screens, and computers to perform the relaxation/mindfulness exercises. This study has obtained the approval from the Andalusian Biomedical Research Ethics Portal (ref. number: xxxx), and is registered under its international standard randomized controlled trial number: NCTxxxxxx. This research was conducted in accordance with the criteria for human experimentation established by the Declaration of Helsinki.
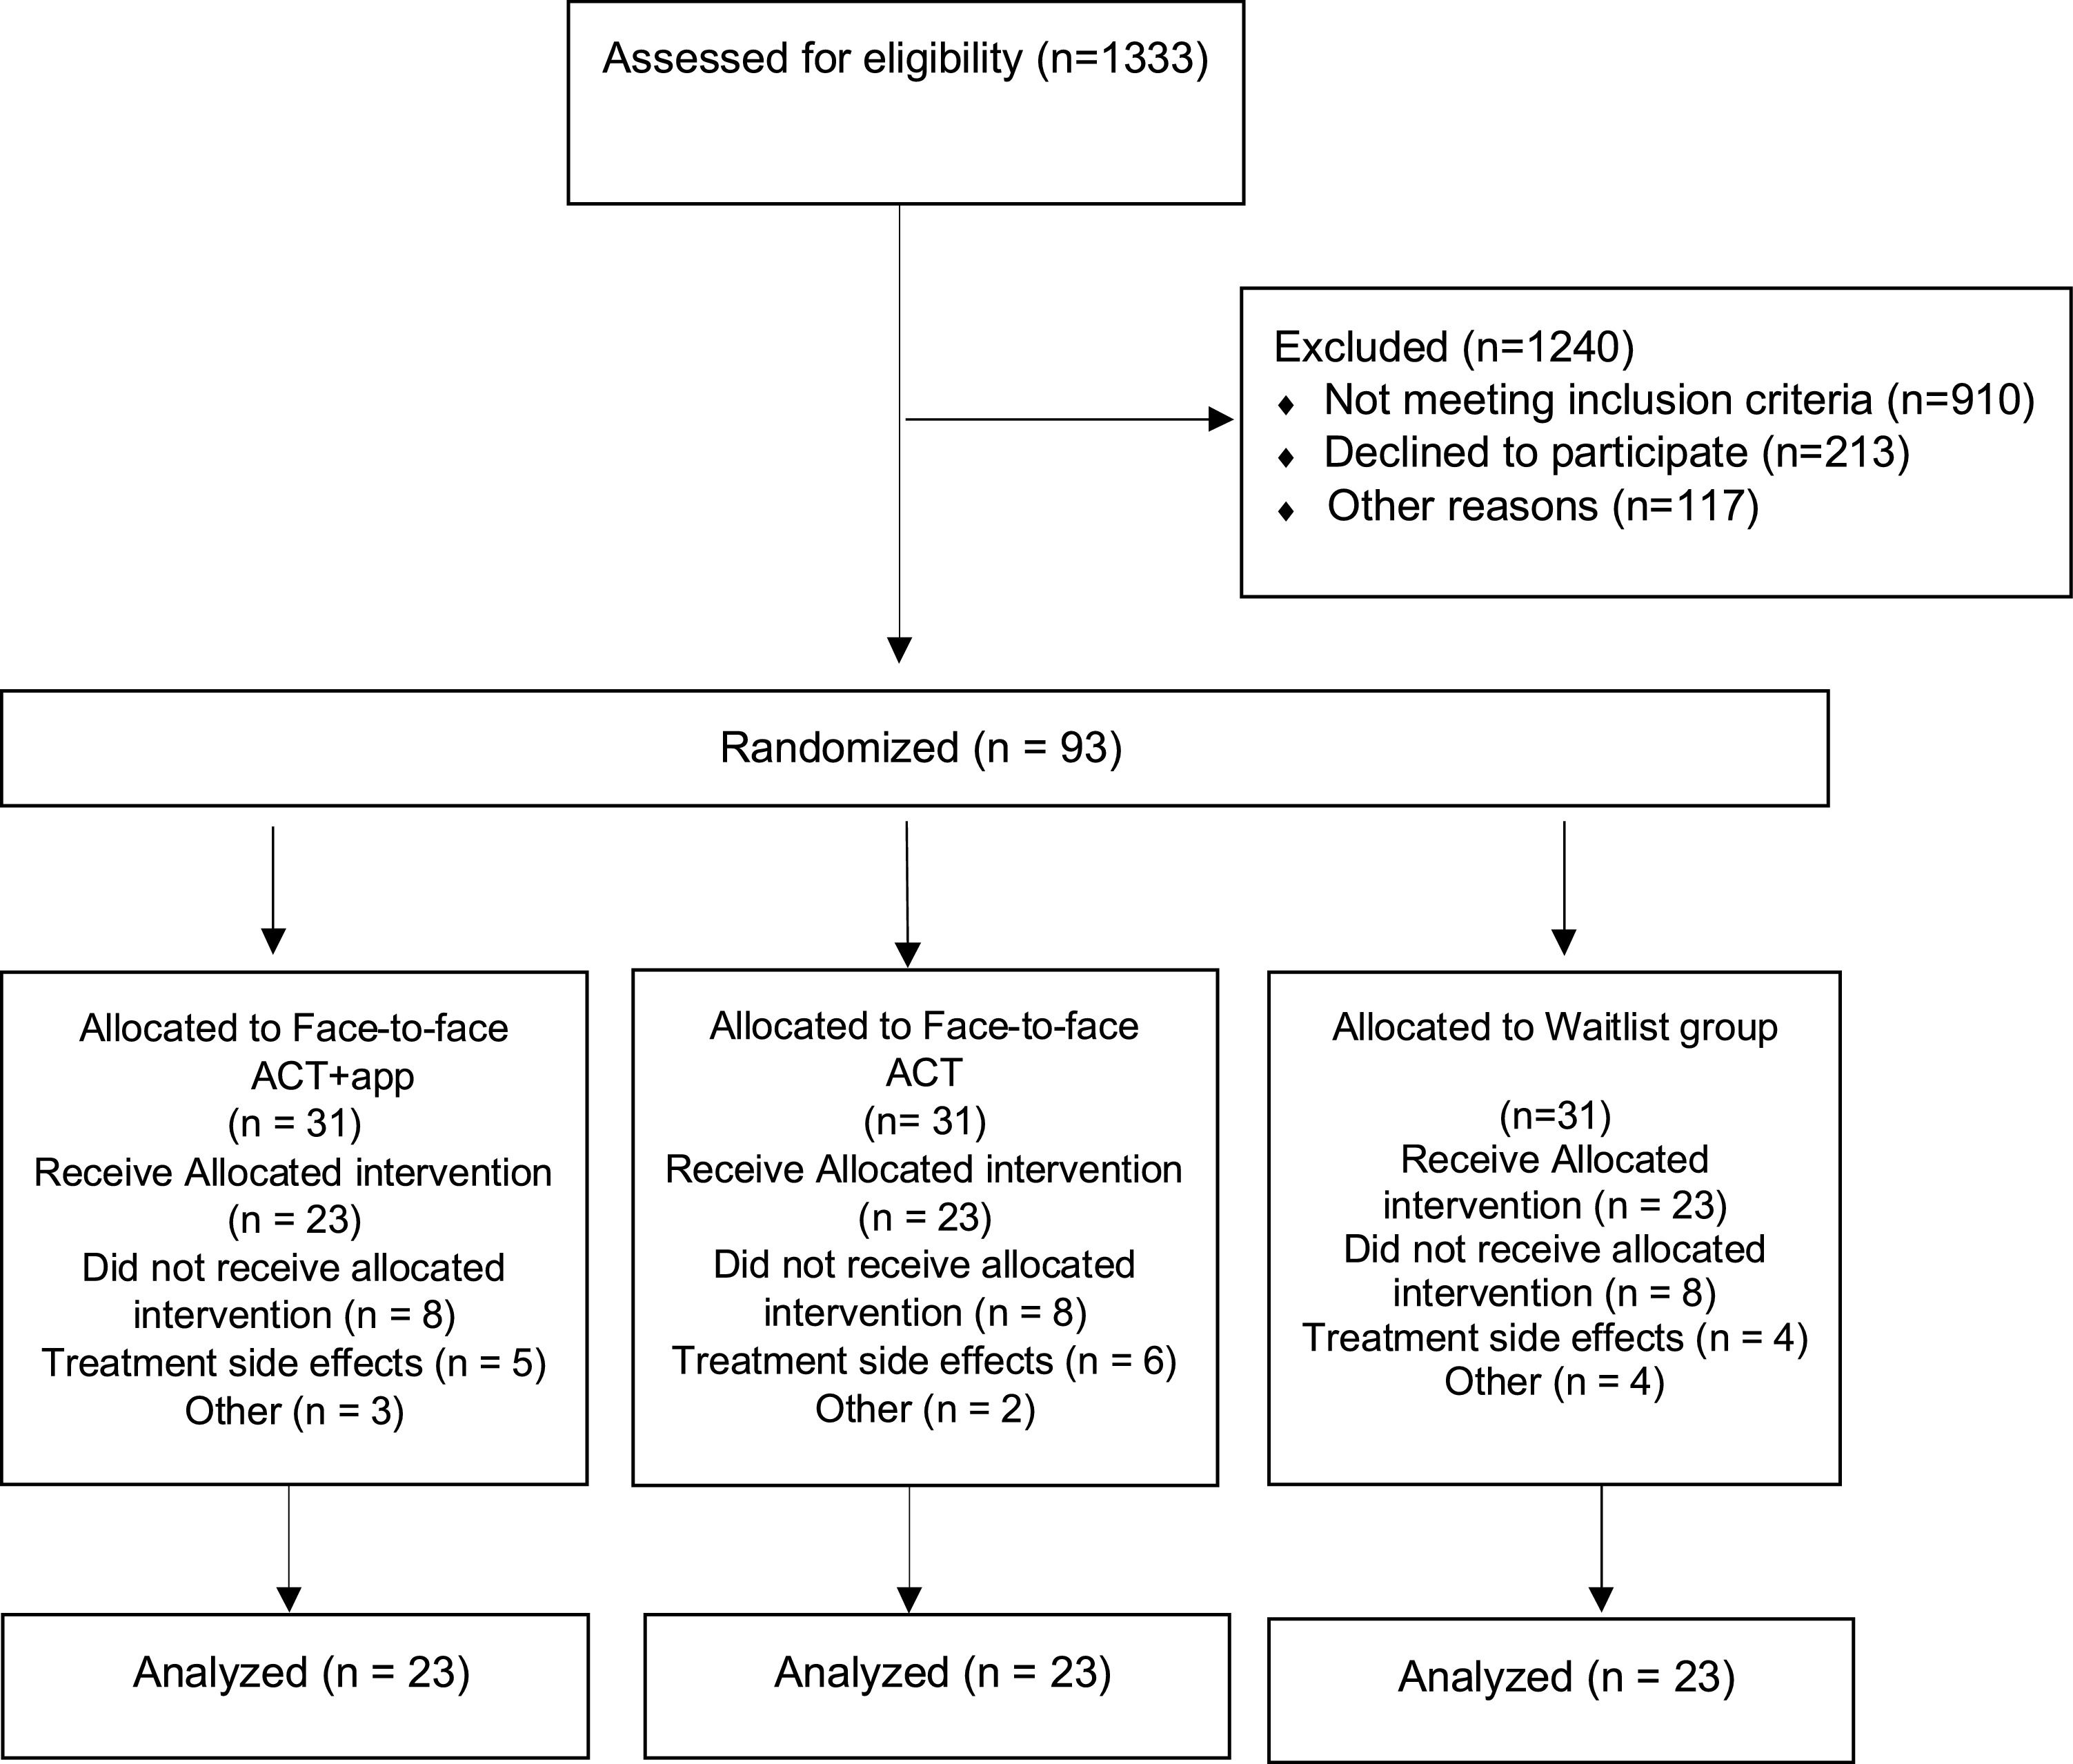
ResultsA total of 1.333 potential participants were approached and 164 of them accepted to participate in the trial. Sixty-nine participants completed the intervention and the two assessment points. The flowchart of the study can be found in Fig. 1.

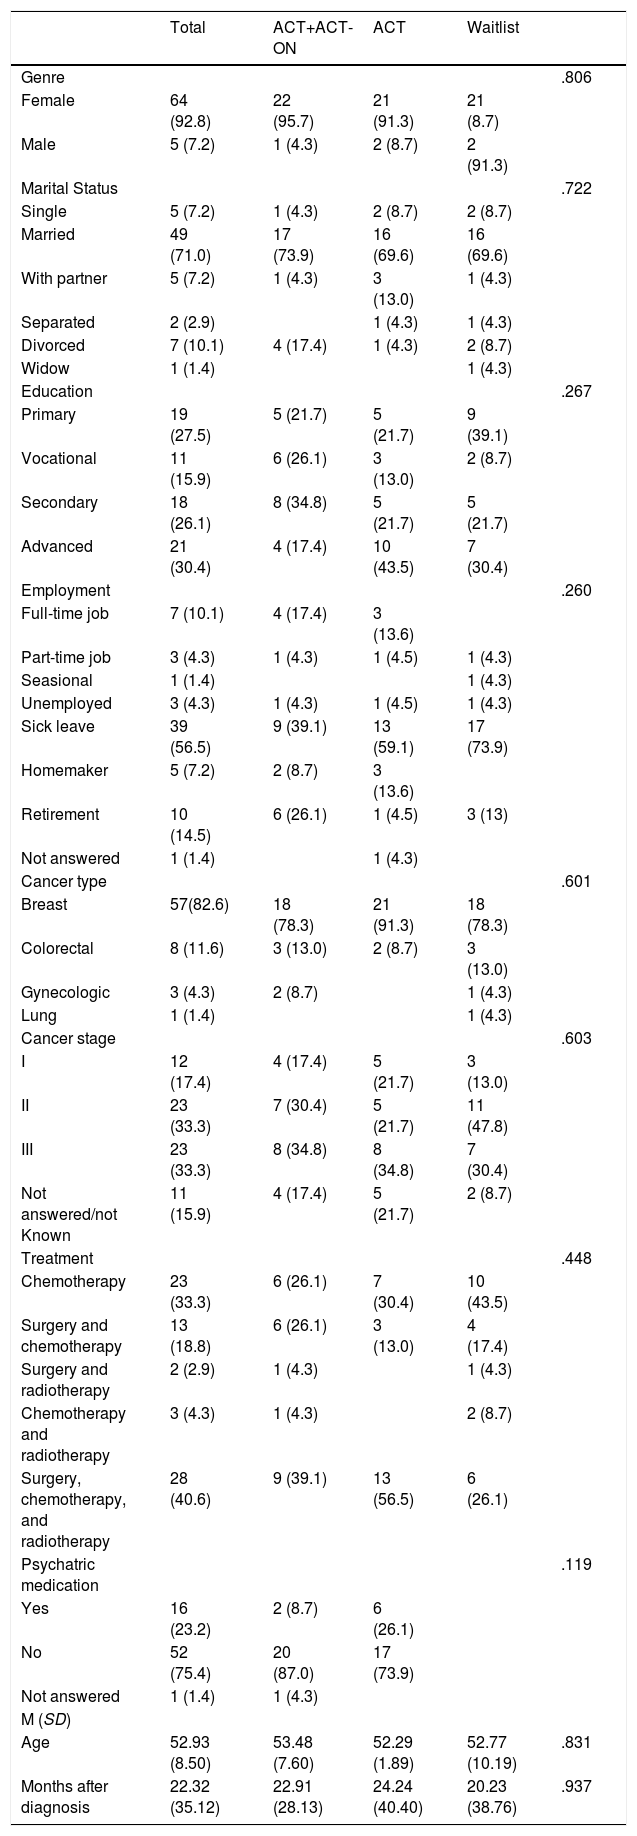
The clinical and sociodemographic characteristics of the sample are shown in Table 1. Most of the participants were women who were married, had a primary-level education, were on sick leave due to the treatment, had a stage II-III breast cancer diagnosis, with surgery, chemotherapy and radiotherapy being the most prevalent treatment combination, and were not taking any psychiatric medication. There were no differences between the groups with regard to these characteristics (Table 2).
Clinical and sociodemographic data of the participants.
M (mean), SD (Standard Deviation).
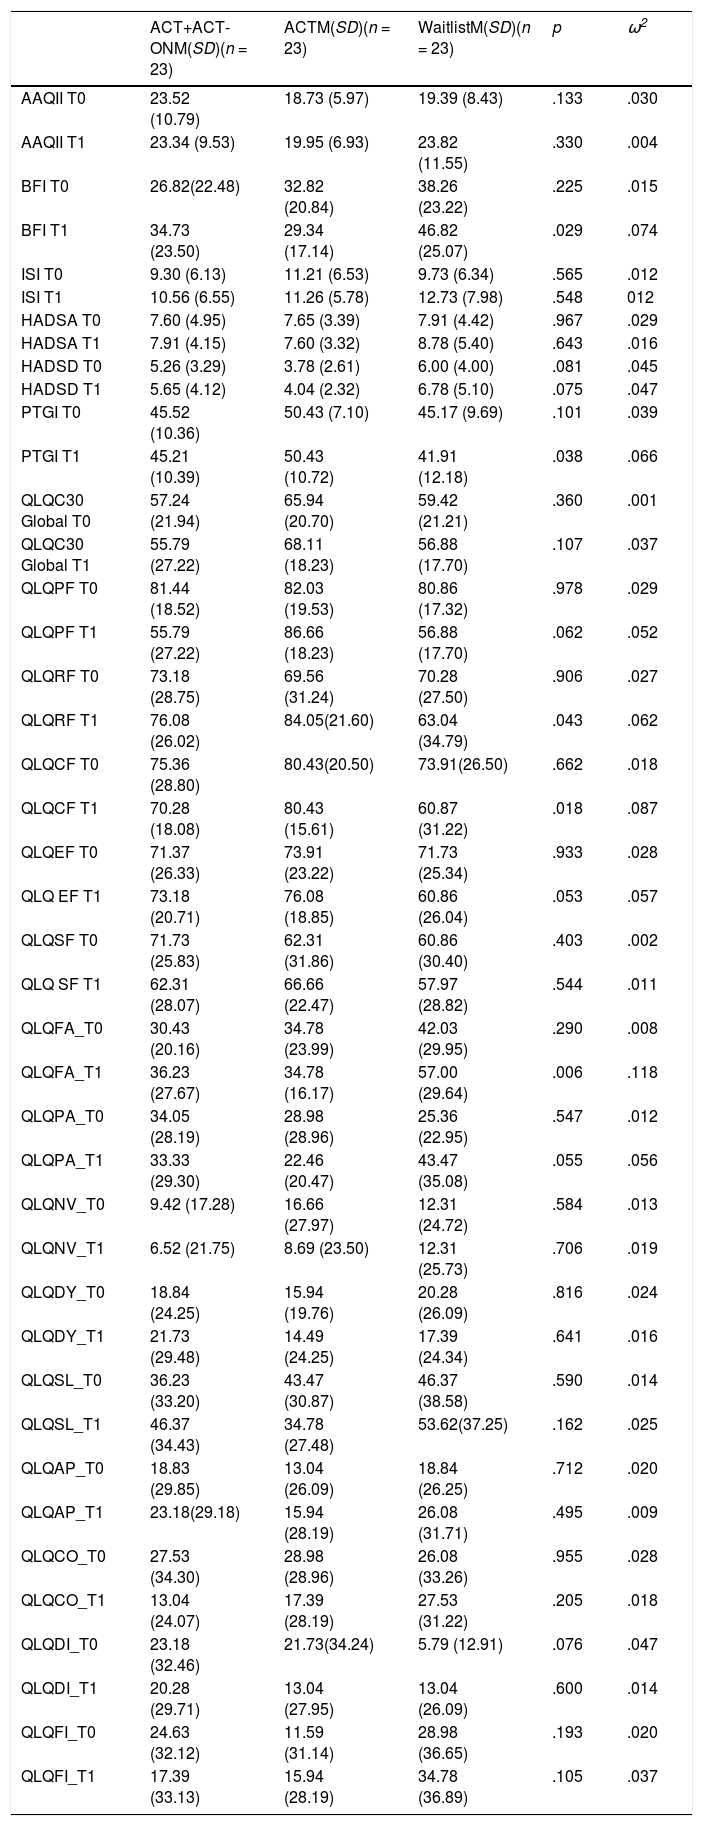
Descriptive statistics and comparative of the scores between the different groups before (T0) and after (T1) the intervention.
Also, there were no differences between the groups in terms of the different variables before the intervention (T0). However, after the interventions, differences were observed between the groups in fatigue, posttraumatic growth, and in the quality of life scores for physical role, cognitive function, as well as fatigue.
Bonferroni´s pos hoc test showed that there were differences in fatigue (T1) between the ACT and the waitlist group (p = .028), but none between the ACT and the ACT+ACT-ON group. In terms of posttraumatic growth (T1), the results are similar, showing differences between the ACT and the waitlist group (p = .028). In terms of the different scores for quality of life after the intervention, the results showed differences in physical role (p = .040), cognitive function (p = .014), and fatigue (p = .020) in the ACT group when compared with the waitlist group.
DiscussionPrevious research has shown positive results when applying acceptance and commitment therapy in cancer patients to reduce the presence of common symptoms such as anxiety, depression and fatigue (Li et al., 2021; Salari et al., 2023; Semenenko et al., 2023). In addition, the use of technological devices such as m-health applications has become very popular in recent years, but the results regarding the effectiveness of their use for therapeutic purposes in cancer patients remain under discussion. (Getu et al., 2021; Li et al., 2021; Richardson et al., 2019). The present trial aimed to establish the efficacy of acceptance and commitment therapy in improving emotional distress, psychological flexibility and associated symptoms in cancer patients, and to assess the efficacy of the use of electronic devices via an app to improve the results of the intervention.
Overall, the results showed worse scores in almost all the variables for the waitlist group when compared to the two ACT groups, particularly for fatigue, which was assessed using two different questionnaires. The scores for fatigue showed significant better scores in post-intervention for the two ACT groups compared with the waitlist group, but when analyzing these differences more closely, the ACT group without app showed better scores. The results for fatigue are in line with previous research involving cancer patients and ACT interventions, which seems to confirm the efficacy of this technique in dealing with fatigue in this population by encouraging patients to use mindfulness techniques. They also highlight the relevance of fatigue as a target for interventions, similar to what network analysis suggests (Doppenberg-Smit et al., 2024; Li et al., 2024; Zhao et al., 2021). Likewise, the scores obtained for posttraumatic growth after the intervention were higher for the two ACT groups, especially when comparing the ACT with the waitlist group. Previous data have shown that ACT may help patients to identify and direct their actions to values that are relevant to them despite the presence of the disease, and this reflection may promote the search for the meaning of one's existence, a concept that is strongly related to posttraumatic growth in these patients (Almeida et al., 2022).
In addition, the results show better scores with regard to physical role on the quality of life scale. This scale includes questions relating to the presence of any impairment experienced by patients when working, carrying out daily activities, practicing hobbies or engaging in leisure activities. According to the data obtained, the two ACT groups showed better scores than the control group. However, statistically significant differences emerged only between the ACT group and the waitlist group. It is possible that this improvement with regard to the mentioned activities is related to the lower levels of fatigue observed and discussed previously, which would enable patients to engage in these activities of daily life with a lesser degree of interference (Al Maqbali et al., 2021). Also, participants in the two ACT groups showed better scores than the waitlist group in cognitive function, with higher function observed in the ACT group. These results are in line with previous research that showed that ACT interventions may improve cognitive function in cancer patients. Although the mechanism underlying this efficacy is not well established, it is possible that ACT activities such as acceptance of current circumstances, management of unwanted thoughts and feelings, and the use of mindfulness-based techniques correlate with this observed improvement (Duval et al., 2022; Shari et al., 2021)
However, the main hypothesis of this study was that using an app will help achieve better scores for the different variables after the intervention, when compared with the group that had no technological support. The results obtained, however, do not confirm this. In a previous study, it was observed that the use of a mobile app led to favorable results in terms of usability among a pilot sample of cancer patients (García-Torres et al., 2023). The fact that this effect does not appear to be confirmed here may be due to other causes, such as a lack of interest in the use of mhealth apps among the participants, and of individualization of the contents of the interventions, which can negatively influence their use (Giebel et al., 2024). In addition, the expected results showing improvements for psychological flexibility, emotional state and insomnia were not observed in the groups that received the ACT intervention, when compared with the waiting list group. Although previous studies show contradictory results with regard to these variables (Li et al., 2021; Salari et al., 2023), the data indicated improvements in the scores obtained, although not enough to be significant, which seems to indicate that the efficacy of ACT interventions increases as time passes after the end of the intervention (Johns et al., 2020). It will be necessary to analyze follow-up data for the complete sample in order to confirm this assumption.
Finally, it is necessary to point out some of the limitations of this study. First, the results are preliminary. It is necessary, therefore, to complete the study with a sufficient number of patients in order to obtain the desired effects, and to carry out follow-up evaluations after the interventions in order to establish their long-term efficacy. Despite this limitation, an analysis of preliminary results of clinical trials helps to make relevant decisions, such as the possible discontinuation of this trial in the event that no effects can be observed. That is not the case here, which indicates that the trial ought to continue. (Ciolino et al., 2023).
There is, however, the issue of patients dropping out of the study. A certain number ended up not participating, or not completing the interventions after being randomized. Reasons were varied, including problems in attending due to distance or adverse treatment effects, all of which negatively influenced the recruitment and retention of participants in the study. Such problems are common in trials involving cancer patients undergoing treatment. However, they should be taken into account to try to minimize the impact of this kind of loss in future trials (Wong et al., 2020). Two other limitations of the trial also ought to be mentioned. Only patients in stages I-III were included and, rather than limiting the focus on one type, patients affected by different types of cancer were invited to participate. However, it should be noted that the needs and characteristics of patients in stages I-III are different from those in stage IV. At that point, the disease has spread to other parts of the body, which means that medical efforts are aimed at managing the disease rather than eliminating the cancer, which justifies their separation from patients in earlier stages of the disease (Koo et al., 2020; National Cancer Institute, 2022). The inclusion of patients with different types of cancer may increase the generalizability of the results obtained despite the heterogeneity and the problems that may cause when interpreting the results, as one of the most common problems in oncology trials is the disparity between the selected samples and the typical patient population. That impedes the generalization of results obtained to real-world settings (Anghel et al., 2025; Habibzadeh, 2022)
ConclusionsDespite the limitations noted, the results indicate that when compared to the waitlist control group, ACT-based interventions lead to positive changes in cancer patients under treatment in the trial variables which is useful for clinical practice with this group of patients. In addition, the data come from a sample of patients with different types and stages of cancer, which increases the generalizability of the study results. It is necessary to increase the number of participants, and to analyze the results during follow-up in order to establish the efficacy of these interventions in an adequate manner.
Declaration of generative AI and AI-assisted technologies in the writing processThe authors did not use any generative AI or AI-assisted technologies in the writing process.
FundingThis work was supported by the Consejería de Economía, Conocimiento, Empresas y Universidad of the Junta de Andalucía (Spain), and the European Regional Development Fund (ERDF) (Grant No. P20_00485).
CRediT authorship contribution statementConceptualization: FGT, MGC, AGS, SR RCM, BL, MJ, EA. Data curation: MGC, FGT. SR. Formal analysis: FGT, RCM. Funding acquisition: FGT. Investigation: SR, RCM, BL, MJ. Methodology; FGT; Project administration: FGT. Resources: FGT, AGS, EA. Software: FGT. Supervision: BL, EA. Validation: FGT, MGC. Visualization: FGT, Roles/Writing – original draft: FGT. Writing – review & editing. FGT.
The authors declare no conflict of interest