No study has yet examined whether a placebo in its traditional meaning—an inert treatment presented as active—can influence functions that tend to naturally decline with age. We aimed to clarify whether a deceptive and open-label placebo procedure would affect psychological, cognitive, and physical functioning in community-dwelling older adults.
MethodsNinety healthy older adults were randomly assigned to one of three conditions: a control group receiving no intervention; a deceptive placebo group receiving placebo pills along with information that these contained active ingredients known to improve functioning and well-being; an open-label placebo group, explicitly informed that the pills were inert but capable of eliciting beneficial mind–body responses. Participants completed self-report measures (perceived stress, psychological well-being, sleepiness, fatigue, optimism, self-efficacy, aging stereotypes) and objective tests of short-term memory, selective attention, and physical performance before and after the 3-week intervention.
ResultsAfter 3 weeks, the open-label placebo group exhibited lower perceived stress compared with both the deceptive placebo and control groups. Short-term memory performance also significantly improved in the open-label placebo group relative to controls. Within-group analyses revealed consistent cognitive and physical improvements in both placebo groups, with particularly pronounced effects in the open-label placebo group.
ConclusionsPlacebo interventions enhanced multiple domains of functioning in older adults, with open-label placebos producing benefits comparable to or greater than deceptive placebos. These findings suggest the potential of open-label placebos as a promising, ethically acceptable approach for supporting healthy aging.
Placebo and nocebo effects are psychobiological phenomena whereby health conditions improve or worsen due to personal expectations, mindsets, and self-perceptions rather than the specific pharmacological effects of treatments or interventions (Evers et al., 2018). Traditionally, placebo effects have been studied using deceptive procedures, in which an inert treatment (such as a sugar pill or saline injection) is presented to patients or research participants as an active medication. In these trials, the inert nature of the treatment is concealed, relying on the belief that for the placebo to work, one must be deceived. However, recent studies indicate that placebos can remain effective even if their inert nature is transparently disclosed. When accompanied by a credible rationale explaining the placebo effect as a powerful mind–body phenomenon, these “open-label” placebos (OLPs) have been shown to produce effects comparable to deceptive placebos across a range of clinical and experimental outcomes (Charlesworth et al., 2017; Guevarra et al., 2024; Kaptchuk et al., 2010; Schaefer et al., 2018). These findings support the view that expectancy-related mechanisms can operate even in the absence of deception.
Beyond clinical populations, placebo effects have also been documented across psychological, cognitive, and physical domains, including attention, working memory, emotional regulation, and motor performance (Benedetti et al., 2023; Fiorio et al., 2022; Guevarra et al., 2020). These domains are particularly relevant in older adulthood, where declines in cognitive and physical functioning are inherent to the aging process. Importantly, older adulthood may represent a useful context in which to examine placebo mechanisms, given the central role of expectations, beliefs, and contextual influences in shaping aging trajectories(Pagnini et al., 2019; Lamont et al., 2015; Hsu et al., 2010; Miche et al., 2014; Stephan et al., 2013). Research on aging stereotypes and Stereotype Embodiment Theory (Levy, 2009) suggests that age-related beliefs and expectations can influence psychological well-being, physiological responses, and functional outcomes (Levy et al., 2000; Levy et al., 2006; Levy et al., 2015). These findings converge with placebo research in highlighting expectancy-related processes as key determinants of health outcomes.
Despite this conceptual overlap, relatively little research has examined placebo responsiveness in the context of healthy aging, particularly in experimental placebo paradigms involving community-dwelling older adults. Existing evidence in older adults primarily derives from clinical trials targeting disease-specific symptoms (e.g., Parkinson’s or Alzheimer’s disease; Kravvariti et al., 2021), whereas placebo effects on broader aspects of functioning in non-clinical aging populations remain underexplored. Moreover, although preliminary work suggests that OLPs may be effective in older adults (e.g., reducing knee pain in osteoarthritis; Olliges et al., 2022), little is known about whether such procedures can influence cognitive and functional outcomes that typically decline with age.
Guided by these considerations, the present study aimed to directly compare deceptive and open-label placebo procedures across multiple domains of functioning in community-dwelling older adults. Specifically, we investigated whether a deceptive placebo presented as a multivitamin supplement and an open-label placebo accompanied by a persuasive rationale would differentially influence psychological, cognitive, and physical outcomes over a three-week period. By comparing outcomes across groups, we sought to clarify the extent to which expectancy-related processes operate under conditions of deception versus transparency and to contribute to a broader understanding of placebo mechanisms in aging.
Based on prior placebo research and theoretical models of expectancy-related mechanisms, we formulated the following hypotheses. First, we expected that both placebo conditions (deceptive placebo [DP] and open-label placebo [OLP]) would show greater improvements than the control group across psychological, cognitive, and physical outcomes. Second, we hypothesized that the OLP condition would produce effects comparable to those observed in the DP condition, consistent with evidence suggesting that expectancy-related mechanisms can operate even in the absence of deception. Third, we expected placebo effects to be more evident in state-like outcomes (e.g., perceived stress and performance-based measures), which are known to be responsive to contextual and expectancy manipulations, than in more stable, trait-like constructs (e.g., optimism, self-efficacy, and aging stereotypes), which were included for exploratory purposes, given their theoretical relevance to expectancy-related processes but relative stability over short intervention periods.
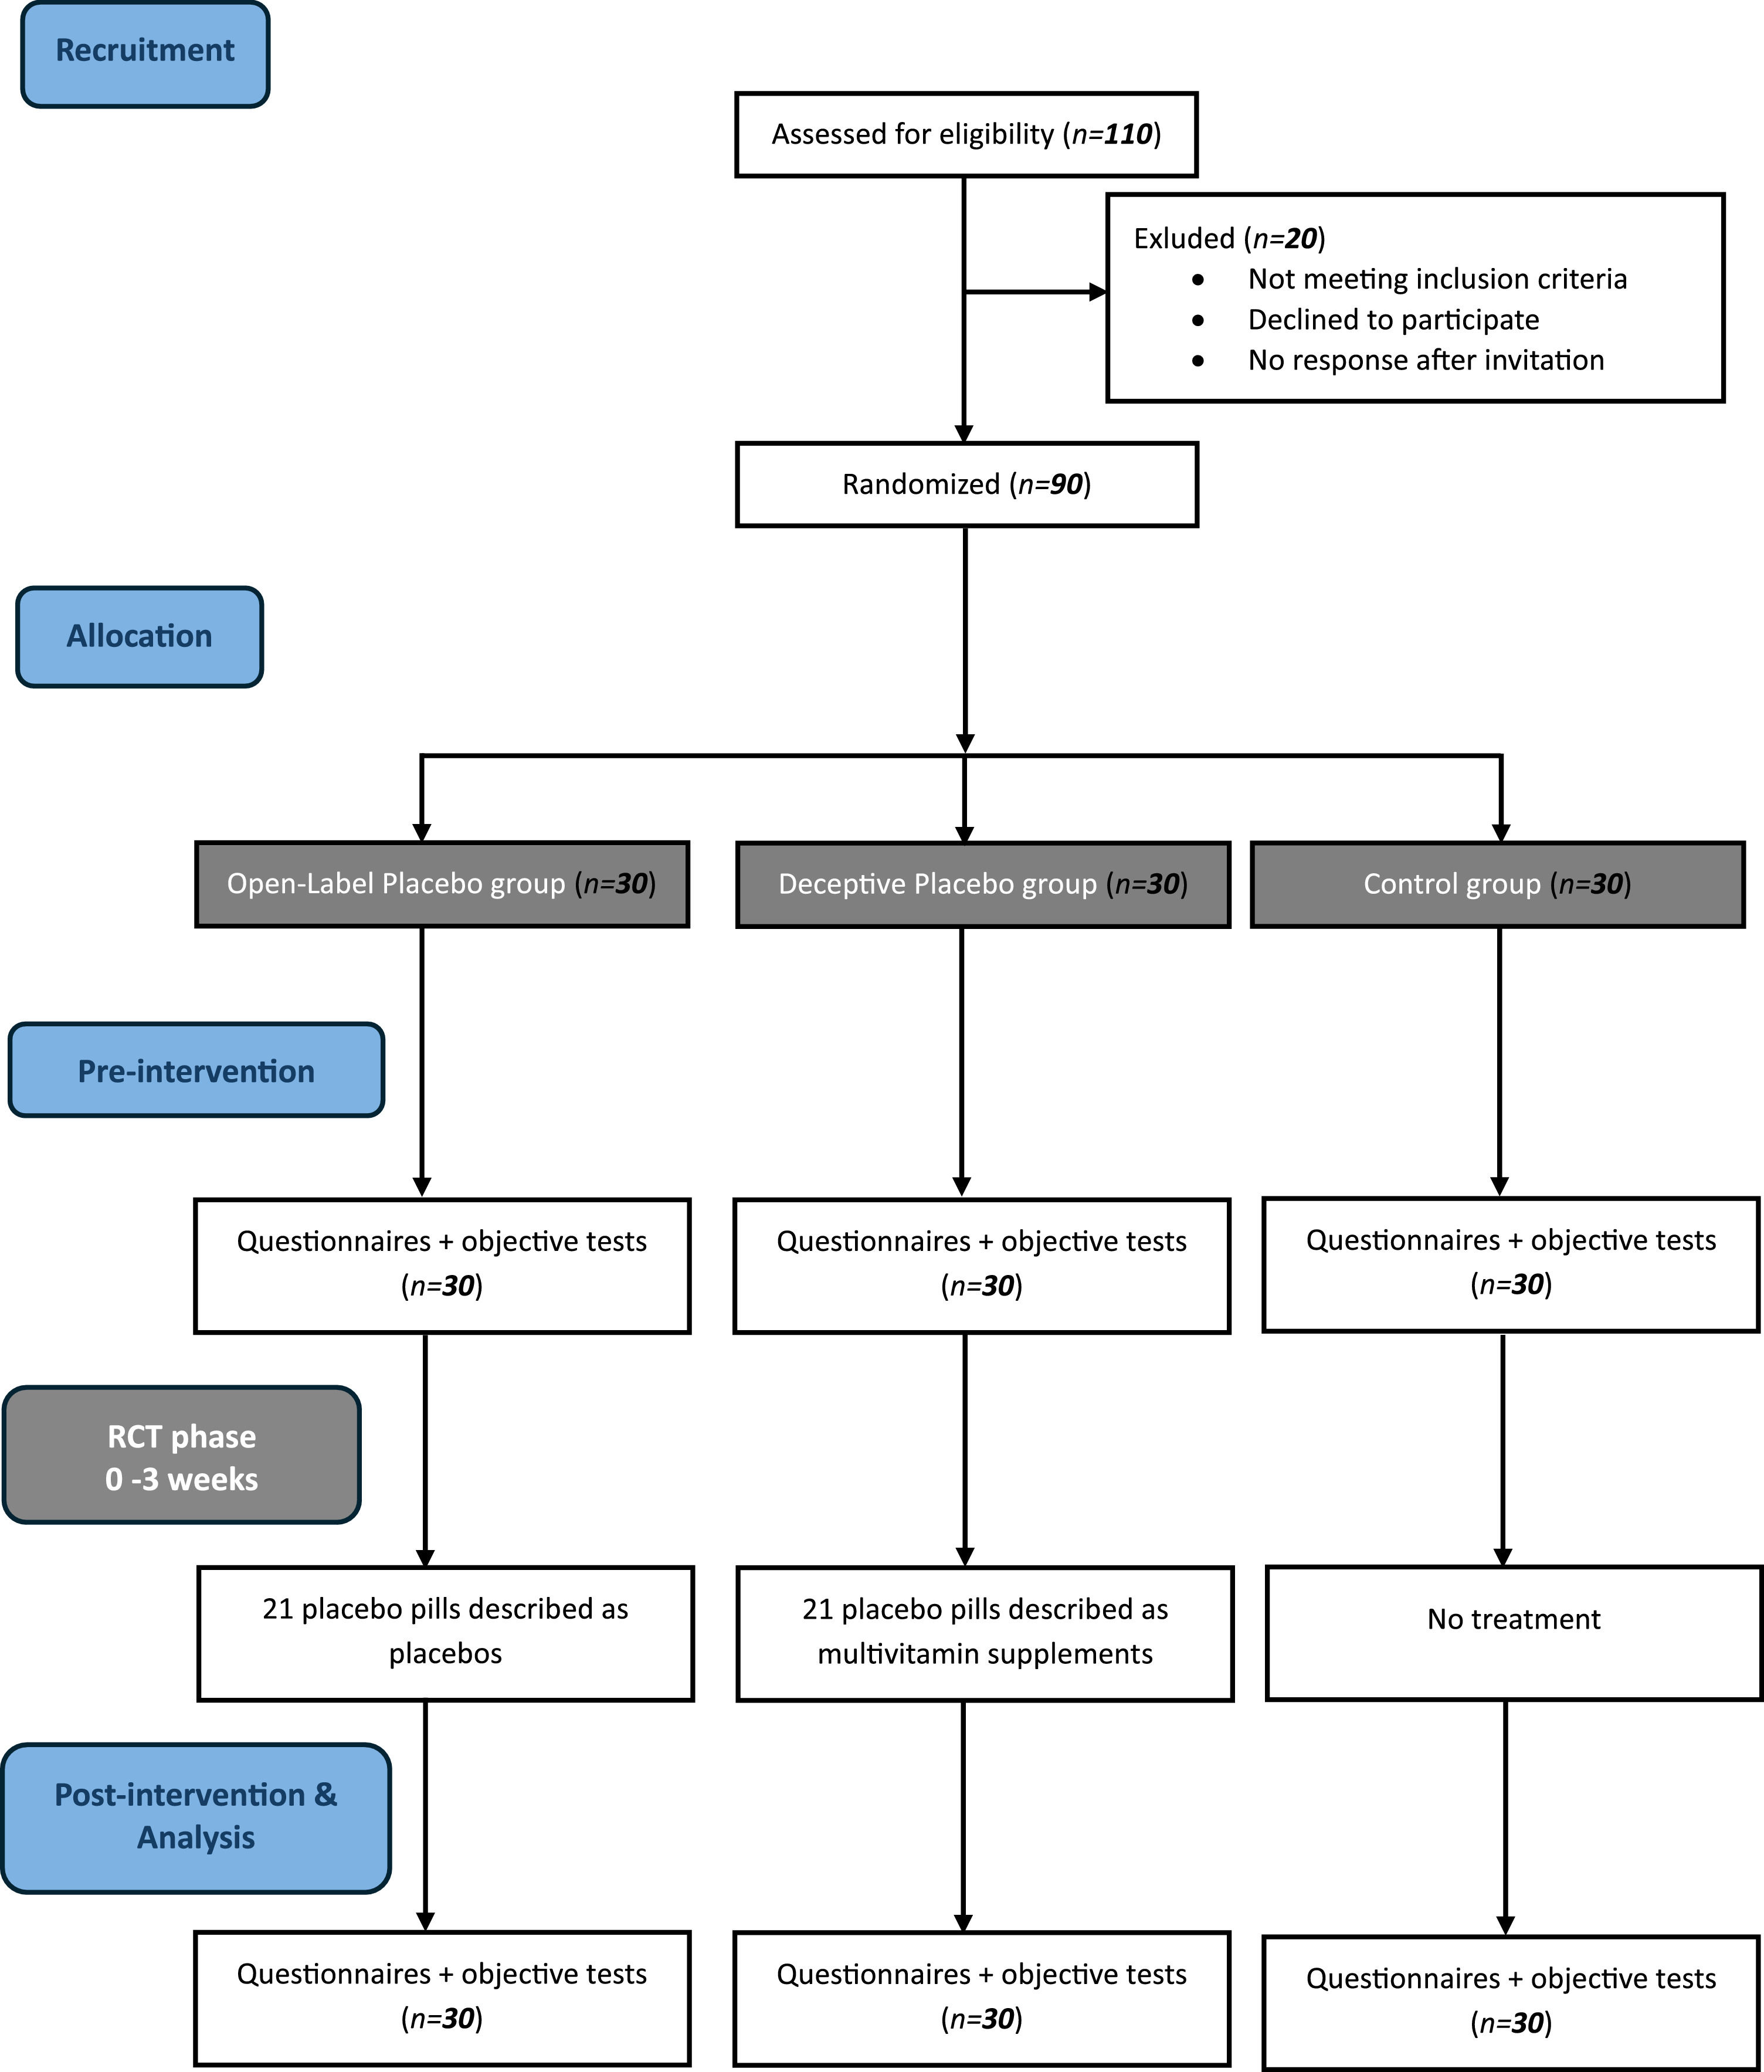
MethodsParticipantsWe initially recruited 110 healthy older adults to account for anticipated exclusions and attrition. From this pool, 90 eligible participants were randomized to one of the three study groups (see section 2.2.1 and Fig. 1 for the study flowchart). The target sample size (N = 90; 30 per group) was determined based on feasibility considerations rather than an a priori power calculation. As an approximate sensitivity analysis, using a one-way omnibus between-groups model in G*Power, this sample size would provide 80 % power at α = 0.05 to detect medium-to-large between-group effects (approximately Cohen’s f = 0.33). Smaller effects may therefore have gone undetected.

Recruitment was conducted through four social–recreational retirement centers in Milan (Italy), flyers distributed in the area of the Università Cattolica del Sacro Cuore, and word of mouth. Participants were randomly assigned to three different groups (30 subjects in each group) using a randomizer function: deceptive placebo, open-label placebo, and control (56 females and 34 males). Participants' ages ranged from 65 to 90 years with an average of 77.01 years (SD = 7.48). Age did not differ significantly across groups. Study announcements described the study as one that was testing the efficacy of a multivitamin supplement for individuals over the age of 65. Criteria for inclusion consisted of being 65 years of age or older, speaking Italian as a first language, and having the ability to read, write, and speak Italian fluently, ensuring comprehension of study instructions and placebo rationales. Exclusion criteria included a history or current presence of physical injuries, psychiatric conditions, or neurodegenerative disorders. Because the study involved administering a placebo presented as a multivitamin supplement, individuals who regularly consumed supplements or multivitamins, or who were currently taking medications, were also excluded. Participants received detailed information about the task and procedure and provided written informed consent to participate in the study. This study was approved by the local committee for approval of the research in humans (CERPS_101/24) of the University of Milan (Italy) and was conducted in accordance with the Declaration of Helsinki.
ProcedureEligible participants who expressed interest in the study were contacted by phone to schedule the first session (pre-intervention). Participants were individually tested in a quiet room located either in one of the four social–recreational retirement centers in Milan or at the Università Cattolica del Sacro Cuore. Each testing room contained a desk, a comfortable chair, and sufficient space to perform the physical performance battery (see section 2.3.2). After providing written informed consent, participants completed subjective questionnaires (see section 2.3.1) via a Qualtrics link (https://www.qualtrics.com). Questionnaire completion required approximately 30 min, and participants were informed that their responses would be collected under full anonymity to ensure privacy rights. After completing the questionnaires, participants performed the cognitive tasks assessing short-term verbal and working memory (Digit Span) and selective attention (Stroop Test) (see Section 2.3.2). Participants were informed that they could discontinue participation at any time or take brief breaks if needed. They then completed the physical performance assessment, which evaluated balance, gait speed, and lower-limb strength/endurance, providing an integrated measure of physical functioning. Although no formal cognitive screening instrument (e.g., MMSE or MoCA) was administered, all participants demonstrated adequate understanding of instructions during baseline assessment procedures.
Following the pre-intervention assessment, participants received the manipulation procedure corresponding to their assigned experimental condition.
ManipulationsDeceptive placebo (DP)Participants in the deceptive placebo group received 21 tablets described as multivitamin supplements purported to enhance functioning and overall quality of life in adults over the age of 65. The manipulation, which involved the use of deception, was accompanied by the following standardized script: “This is a multivitamin supplement containing a complex of vitamins designed specifically for adults over the age of 65. Benefits typically observed within the first week include enhanced cognitive abilities—such as concentration and memory—greater physical energy, and reduced fatigue. In addition, this supplement is expected to improve mood, reduce stress, and promote overall well-being, helping to counter age-related declines in functioning. Beginning today, we ask you to take one tablet per day for three weeks. After this period, we will invite you to return to the same location to repeat some tests and complete the study.”
Participants in the open-label placebo group were given the same 21 tablets as the deceptive placebo group. However, unlike the DP group, the tablets were explicitly described as placebos – substances devoid of specific therapeutic properties that could nonetheless produce beneficial effects through a real and tangible mind-body phenomenon (i.e., the placebo effect). In this condition, no deception was employed. The procedure was accompanied by the following standardized explanation: “We would like to inform you that these tablets have no specific therapeutic properties. They are simply sugar pills that can be safely taken by anyone. The purpose of our research is to investigate the placebo effect, a well-established psychobiological phenomenon demonstrating how the mind can influence the body. In particular, when individuals hold expectations about the efficacy of a treatment, these expectations alone can lead to genuine improvements. Given this, we ask you to take these placebo pills in an ‘open-label’ fashion—that is, knowing that they contain no active ingredients but keeping in mind the body’s natural ability to self-heal. When taking the pills, we ask you to consider the following points:
- (1)
The placebo effect is a powerful and pervasive phenomenon that activates specific brain regions associated with real therapeutic changes;
- (2)
The body’s response to placebo can occur automatically, much like Pavlov’s dogs salivating when they heard the bell;
- (3)
A positive attitude may enhance the effect but is not strictly necessary;
- (4)
Adhering to the treatment schedule is essential.
In light of this information, we now ask you to take these tablets with awareness of their potential to enhance your cognitive and physical abilities and to reduce your stress levels. Starting today, please take one tablet per day for three weeks. At the end of this period, we will invite you to return to this same location to repeat some tests and complete the study.”
Of note, when introducing the example of Pavlovian conditioning, participants were first asked whether they were familiar with the concept. If they indicated familiarity, the experimenter proceeded with the standardized rationale. If not, a brief explanation of Pavlovian conditioning was provided before continuing, as follows: “For example, in classical conditioning studies, Pavlov showed that dogs could learn to associate a neutral stimulus, such as a bell, with food. After repeated pairings, the dogs began to salivate when hearing the bell alone, demonstrating how learned expectations can produce automatic physiological responses.”
Participants in the control group completed the same battery of questionnaires and tests described above but did not receive any treatment. At the end of the pre-intervention session, they were informed: “We are interested in assessing the trend of different functional parameters over time. For this reason, we will ask you to complete several questionnaires and perform some cognitive and physical tests. After three weeks, we will ask you to return to this location to repeat some tests and finalize the study.”
Following the (truthful or deceptive) manipulation, participants in the OLP and DP groups received a pill organizer containing 21 placebo tablets. After three weeks, all participants completed the same questionnaires and underwent the same cognitive and physical assessments as in the pre-intervention session (post-intervention assessment). At the conclusion of the post-intervention session, an oral debriefing was provided, tailored to the different experimental conditions.
MeasuresSubjective measuresThe pre- and post- intervention sessions included the self-administration of questionnaires addressing subjective evaluations of several psychological variables. Measures were selected to capture both state-like outcomes expected to be responsive to short-term placebo interventions and broader dispositional constructs examined exploratorily due to their theoretical links to expectancy processes.
StressPerceived stress was measured using the 10-item version of the Perceived Stress Scale (PSS-10; [Cohen et al., 1994]), to assess the degree to which individuals appraised situations in their lives as stressful. Participants were asked to rate each item (e.g., “In the last month, how often have you felt nervous and ‘stressed’?”) on a 5-point Likert scale ranging from 0 (never) to 4 (very often). Total scores range from 0 to 40, with higher values indicating greater perceived stress.
Psychological well-beingTo investigate whether the placebo procedures influenced psychological well-being, participants were asked to fill out the six-item Psychological General Well-Being Index – Short version (PGWB-S; [Grossi et al., 2006]), to provide a self-perceived measure of health-related quality of life. Participants provided responses on a 6-point Likert scale, ranging from 0 to 5, with higher scores indicating greater subjective well-being (i.e., better psychological health).
Daytime sleepinessWe hypothesized that changes in sleep patterns that are typically observed as one ages (Koh et al., 2006) could affect daytime sleepiness. To this end, the Epworth Sleepiness Scale (ESS; [Johns, 1991]) was administered to assess participants’ general level of daytime sleepiness or propensity to fall asleep in different situations. Responses were provided using a 4-point Likert scale ranging from 0 (would never doze) to 3 (high chance of dozing), with higher scores indicating greater daytime sleepiness.
FatigueParticipants’ level of fatigue was measured using the Fatigue Assessment Scale (FAS; [Michielsen et al., 2003]), to assess fatigue as a unidimensional construct reflecting both physical and mental components. The FAS consists of 10 items (e.g., “I am bothered by fatigue”) rated on a 5-point Likert scale ranging from 1 (never) to 5 (always). Total scores range from 10 to 50, with higher scores indicating higher levels of fatigue.
OptimismGiven the well-established link between the susceptibility to experience placebo effects and optimistic traits (Geers et al., 2007), dispositional optimism was assessed using the 10-item Life Orientation Test – Revised (LOT-R; (Scheier et al., 1994)), a self-report measure designed to evaluate generalized positive outcome expectancies. The Italian validated version by Giannini and colleagues (2008) was employed in the present study. Participants rated each statement on a 5-point Likert scale ranging from 0 (strongly disagree) to 4 (strongly agree), with higher scores indicating greater dispositional optimism.
Self-efficacyPerceived self-efficacy was measured using the Generalized Self-Efficacy Scale (GSE; [Schwarzer & Jerusalem, 1995]), to assess participants’ optimistic self-beliefs in coping with a variety of difficult demands in life. The scale consists of 10 items (e.g., “I can always manage to solve difficult problems if I try hard enough”) rated on a 4-point Likert scale ranging from 1 (not at all true) to 4 (exactly true), with higher scores indicating greater perceived self-efficacy.
Aging stereotypesAttitudes toward aging were assessed using the Aging Stereotypes Questionnaire (ASQ; [Vailati Riboni et al., 2024]), to evaluate individuals’ beliefs and expectations about aging across multiple life domains. The ASQ assesses both positive and negative stereotypes related to aging in areas such as physical decline, cognitive functioning, interpersonal relations, and personal growth. Participants rate their agreement with a series of statements on a Likert scale ranging from 1 (strongly disagree) to 5 (strongly agree). Higher scores on the positive subscale reflect more favorable views of aging, while higher scores on the negative subscale indicate stronger endorsement of negative age-related stereotypes. Participants were asked to indicate their level of agreement with 15 statements reflecting both positive and negative stereotypes about aging, using a 7-point Likert scale (1 = strongly disagree; 7 = strongly agree), with higher total scores indicating stronger negative aging stereotypes.
Objective measuresFollowing the completion of the self-report questionnaires, participants performed physical and cognitive tasks to assess whether the deceptive and open-label placebo procedures differentially influenced objective measures of functioning.
Cognitive performanceShort-term working memory was assessed using the Digit Span subtest from the Wechsler Adult Intelligence Scale (Wechsler, 1997). The test consists of two components: Digit Span Forward and Digit Span Backward. Digit sequences were read out to participants beginning with a length of two digits and two trials were presented at each increasing list length. The experimenter read each sequence slowly (approximately one digit per second) and waited for the participant to repeat it correctly in the same order (Digit Span Forward), or in reverse order (Digit Span Backward) as presented by the experimenter. When a sequence was reported correctly, the examiner proceeded to the next. Testing was discontinued when participants failed to accurately report either trial at one sequence length or when the maximal list length is reached (9 digits forward, 8 backward). The total number of lists reported correctly is combined across forward span (FS) and backward span (BS) to produce a Wechsler total correct score, with higher scores indicating better cognitive performance.
Selective attention and cognitive inhibition were assessed using the Short Stroop Task (Caffarra et al., 2002), a paper-based version adapted for use in Italian populations. The task evaluates selective attention, processing speed, and the ability to inhibit automatic responses. It consists of three conditions: (1) a word-reading condition, in which participants read color names printed in black ink; (2) a color-naming condition, in which participants name the color of a series of colored circles; and (3) an interference condition, in which participants name the ink color of incongruent color words (e.g., the word “red” printed in blue ink). The experimenter sat proximally to the participants and, after explaining the procedure, instructed them to perform the task as quickly as possible. To minimize visual interference, the experimenter helped participants follow the task by sliding a sheet of paper over the test sheet, uncovering one line at a time as the participant completed reading each line. The experimenter recorded the time (T1, T2, and T3) participants took to complete each of the three conditions and noted the number of errors made. Performance was measured as the time required to complete each condition and the number of errors. The interference score reflects the participant’s inhibitory control, with higher completion times or error rates indicating greater difficulty in suppressing automatic reading responses.
Physical functioningPhysical functioning was assessed using the Short Physical Performance Battery (SPPB; [Guralnik et al., 1994]), a standardized measure of lower extremity performance widely used in aging research and clinical settings. The SPPB evaluates three key components of physical function: balance, gait speed, and lower-limb strength. Balance is assessed through a series of standing tasks (side-by-side, semi-tandem, and tandem positions); gait speed is measured over a 4-meter walk at the participant’s usual pace; and lower-limb strength is evaluated using a repeated sit-to-stand test, in which participants stand up from a seated position for five times as quickly as possible without using their arms (i.e., with their arms crossed over the chest). Each component is scored on a 0–4 scale, with higher scores indicating better performance. The total SPPB score ranges from 0 to 12, providing an overall index of physical functioning, where lower scores reflect greater functional limitations.
Data handling and statistical analysisAll subjective variables were analyzed using non-parametric tests due to the ordinal nature of the data. In addition, because Digit span and SPPB scores are discrete, ordinal measures with restricted scoring ranges, and Stroop task times were also markedly right-skewed (Shapiro-Wilk, p < .05), non-parametric methods were considered the most appropriate and robust analytic approach also for these measures.
Between-group differences among the three experimental conditions—deceptive placebo (DP), open-label placebo (OLP), and control (C)—at the post-intervention session were analyzed using the Kruskal–Wallis test conducted separately for each outcome variable (i.e., psychological well-being (PGWB-S), perceived stress (PSS-10), daytime sleepiness (ESS), fatigue (FAS), optimism (LOT-R), self-efficacy (GSE), aging stereotypes (ASQ), Digit Span score, Stroop Time, and physical performance (SPPB)). When significant effects emerged (p < .05), post hoc pairwise comparisons were performed using the Mann–Whitney U test, applying Bonferroni correction where necessary to adjust for multiple comparisons.
To explore changes over time within each group separately, pre- and post-intervention scores were compared using the Wilcoxon signed-rank test. The effect size of all significant results is reported with eta-square (ηH2) and r for Kruskal–Wallis and post-hoc tests respectively (Tomczak & Tomczak, 2014). Descriptive statistics were expressed as medians and interquartile ranges (IQRs). The level of statistical significance was set at p ≤ 0.05 for all analyses. Data analysis was performed using SPSS Statistics software (IBM SPSS Statistics 26, SPSS Inc., Chicago, IL).
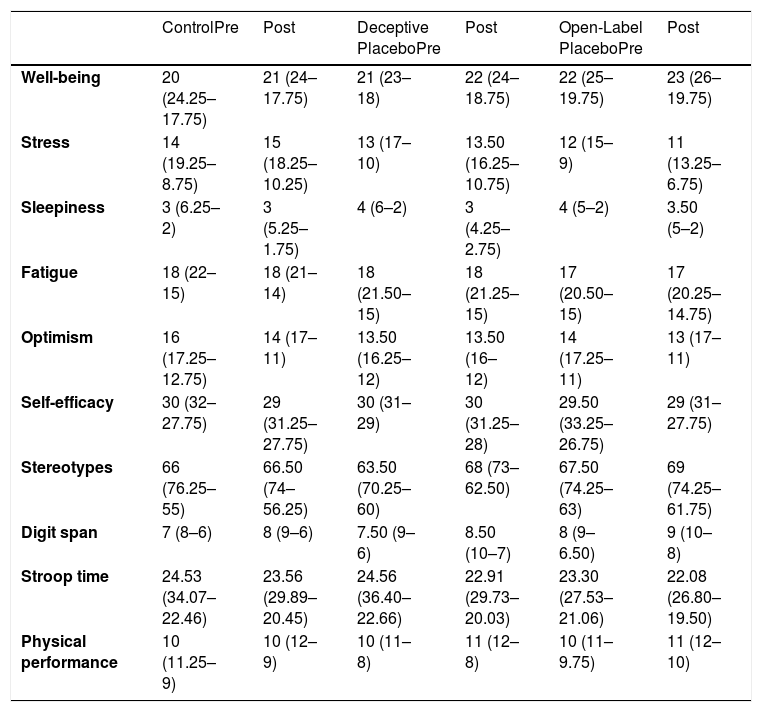
ResultsThe three groups did not statistically differ for age (one-way ANOVA, p=.161), and gender distribution (Chi- squared, p = .954). Table 1 offers an overview of the subjective and objective data of the different groups in the pre-intervention and post-intervention sessions. No significant between-group differences were observed at pre-intervention across subjective (self-report), cognitive, or physical outcomes (Kruskal–Wallis tests; for all, p > .05).
Subjective and objective data (median and interquartile range) of the different groups across sessions.
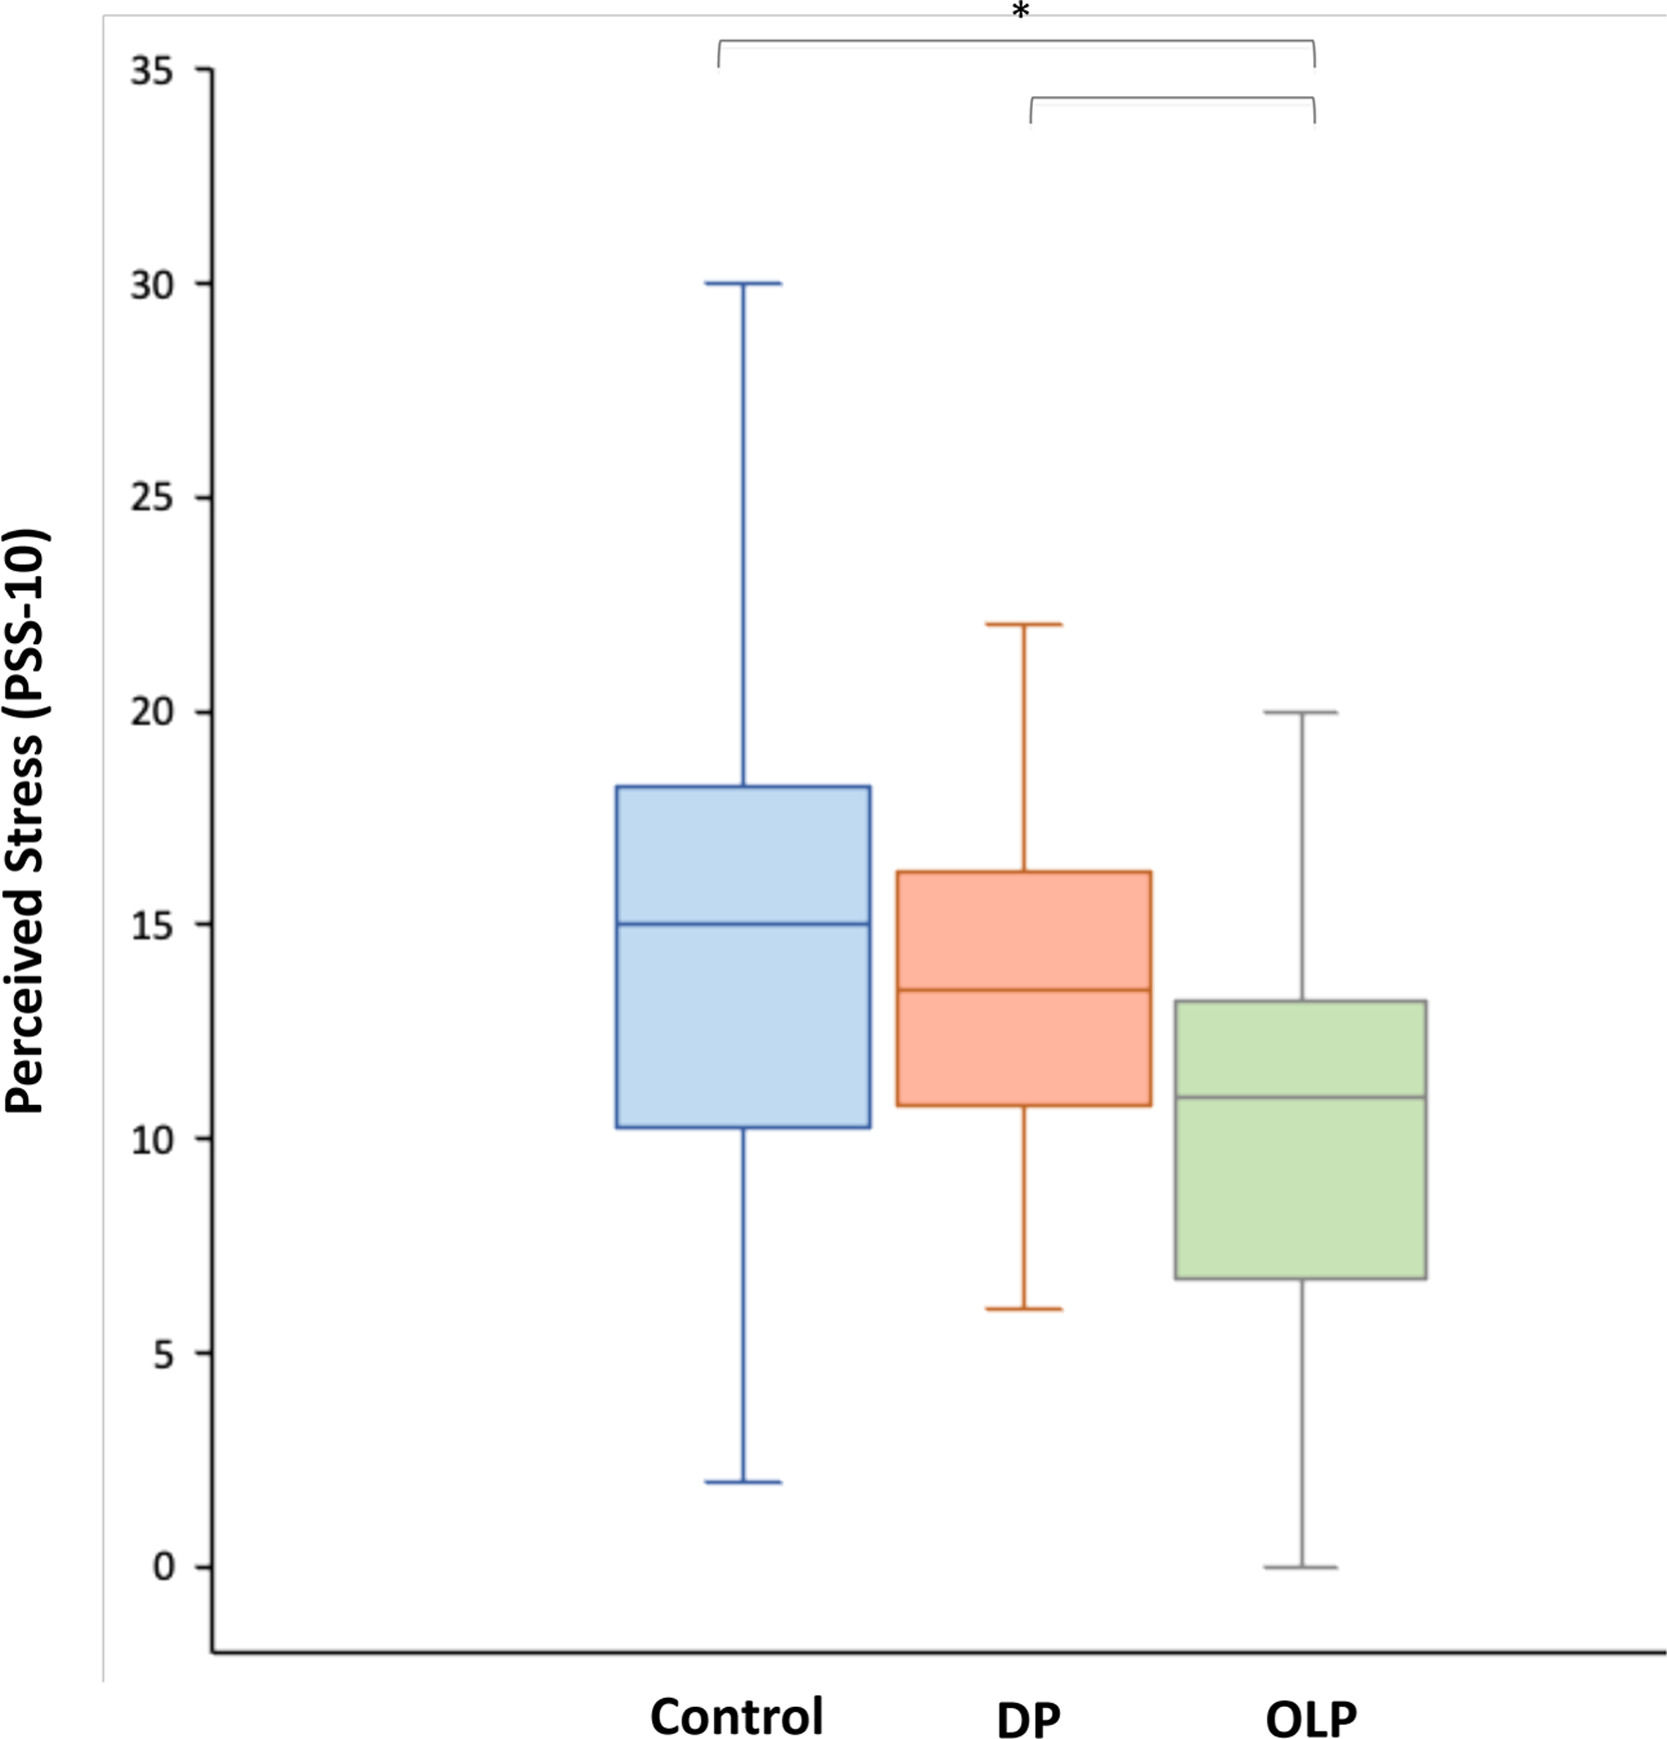
Kruskal–Wallis tests examining post-intervention differences among the three groups (deceptive placebo [DP], open-label placebo [OLP], and control [C]) revealed a significant effect for perceived stress (PSS-10), H(2) > 5.99, p = .015, η²ₕ ≈ 0.08 (Fig. 2). Post hoc pairwise comparisons (Bonferroni-corrected) indicated that the OLP group reported significantly lower perceived stress than both the control group (Z > 2.39, p < .05, r = 0.30–.50) and the DP group (Z > 2.39, p < .05, r = 0.30–.50). Specifically, the OLP group showed a lower median PSS score (Mdn = 11.0, IQR = 6.75 13.25) than both the control group (Mdn = 15.0, IQR = 10.25–18.25) and the DP group (Mdn = 13.5, IQR = 10.75–16.25) (Fig. 2).

No significant between-group differences emerged for psychological well-being (PGWB-S), daytime sleepiness (ESS), fatigue (FAS), optimism (LOT-R), self-efficacy (GSE), or aging stereotypes (ASQ) at post-intervention (for all, p ≥ .30).
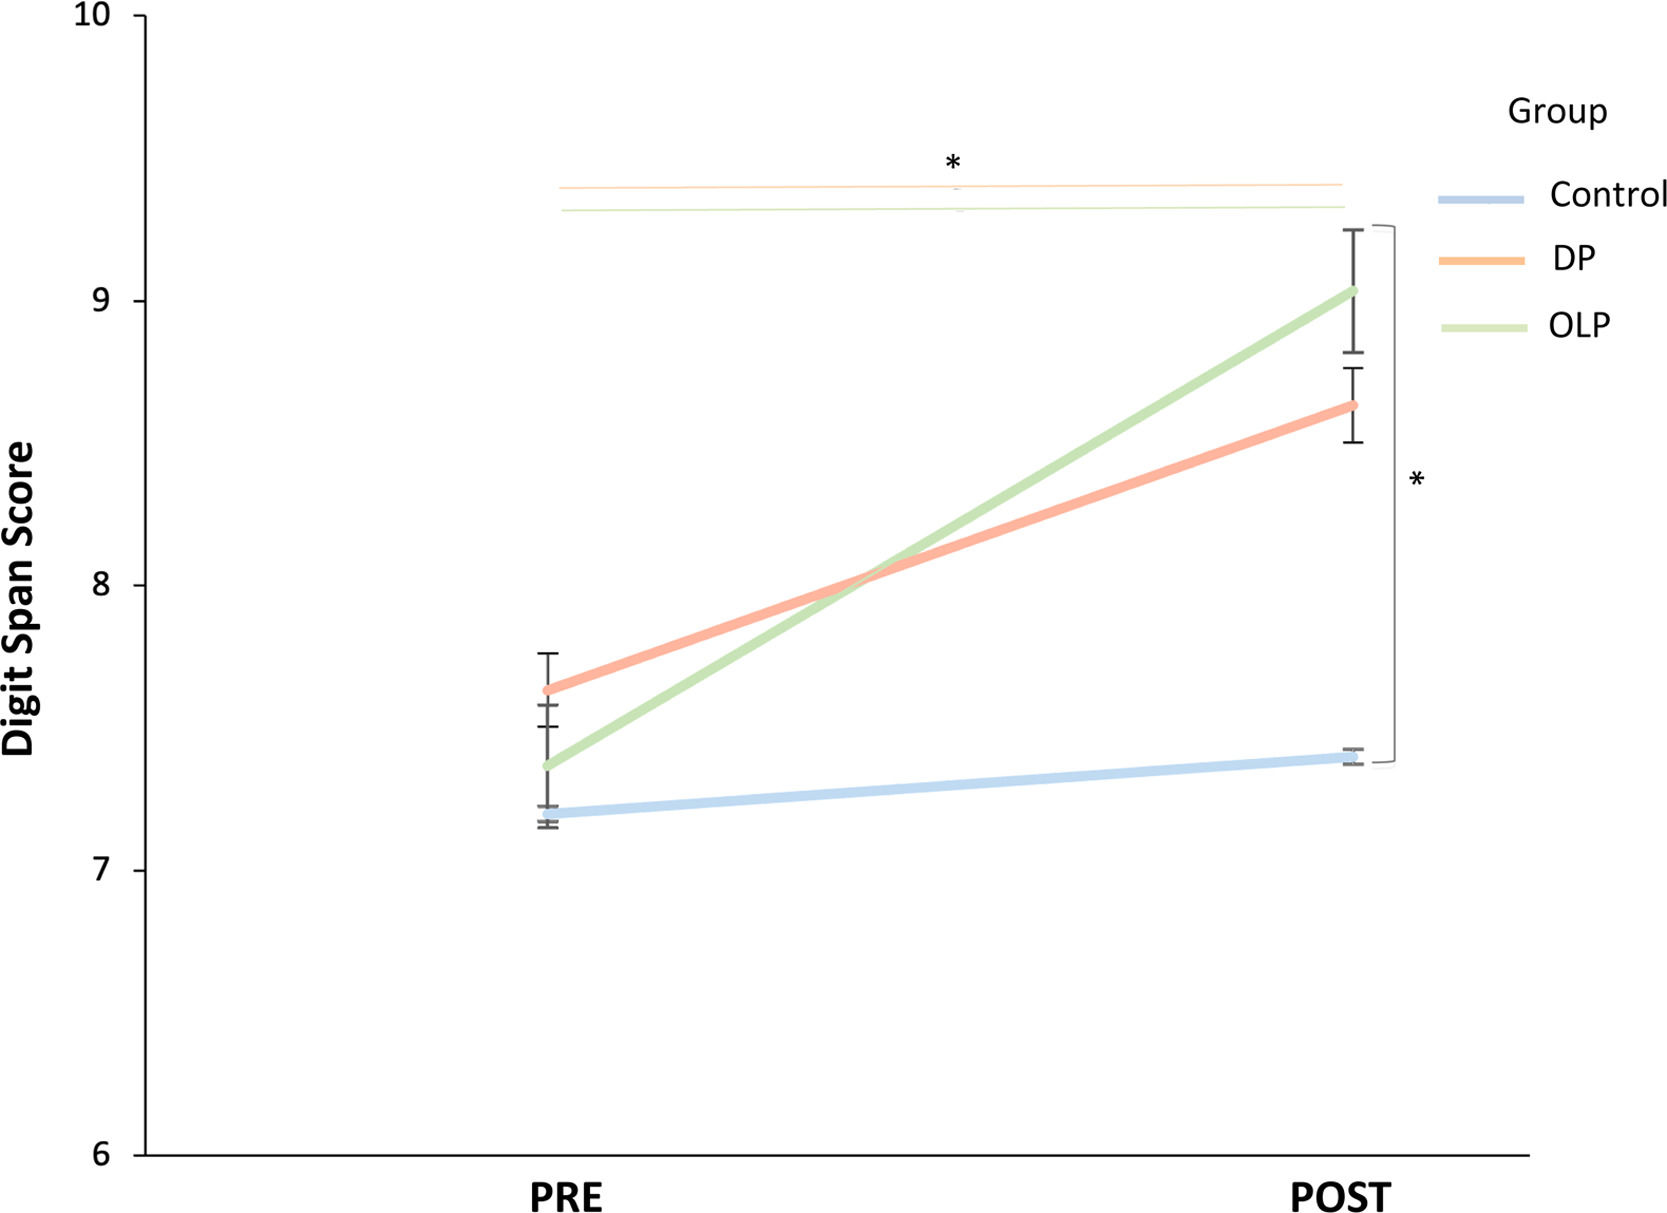
Cognitive performanceA significant between-group difference was observed at post-intervention for Digit Span performance, H(2) > 6.25, p < .05, η²ₕ ≈ 0.08. Post hoc comparisons showed that the OLP group (Mdn = 9.0, IQR = 8.0–10.0) performed significantly better than the control group (Mdn = 8.0, IQR = 6.0–9.0; Z ≥ 2.39, p < .05, r = 0.30–.50). No significant differences were observed between the remaining group comparisons (C vs. DP, DP vs. OLP; for all, p ≥ .10) (Fig. 3A).


Digit Span performance from pre- to post-intervention across groups. Error bars represent standard errors. Significant improvements were observed in the deceptive placebo (DP) and open-label placebo (OLP) groups (*p < .05). Moreover, compared with the control group (blue) the OLP group (green) showed higher digit span scores at the post-intervention session (*p < .05). Stroop completion time from pre- to post-intervention across groups. Error bars represent standard errors. Significant improvements were observed in both placebo groups (**p < .01). A smaller improvement was also observed in the control group (*p < .05), likely reflecting practice effects. SPPB score from pre- to post-intervention across groups. Error bars represent standard errors. Significant improvements were observed in both placebo groups (**p < .001 for OLP; *p < .05 for DP), whereas no significant change was observed in the control group.
No significant between-group differences were found for Stroop completion time at post-intervention (for all, p > .54).
Physical functioningNo significant between-group differences were observed at post-intervention for physical functioning as measured by the SPPB (p = .54).
Within-group pre-post changesSubjective outcomesWithin-group analyses revealed no significant pre–post changes across subjective measures in any group (for all, p > .05).
Cognitive performanceWithin-group analyses indicated significant improvements in Digit Span performance in both placebo groups (Fig. 3A). In the DP group, Digit Span scores increased from pre-intervention (Mdn = 7.50, IQR = 6.0–9.0) to post-intervention (Mdn = 8.50, IQR = 7.0–10.0; Z ≥ 2.18, p < .05, r = 0.30–.50). Similarly, the OLP group showed significant improvement from pre-intervention (Mdn = 8.0, IQR = 6.50–9.0) to post-intervention (Mdn = 9.0, IQR = 8.0–10.0; Z ≥ 3.67, p < .001, r > 0.50). No significant change was observed in the control group (p > .43) (Fig. 3A).
Stroop completion time decreased significantly from pre- to post-intervention in all three groups: DP (Mdn = 24.56 to 22.91; Z ≥ 3.12, p 〈 .01, r 〉 0.50), OLP (Mdn = 23.30 to 22.08; Z ≥ 3.16, p 〈 .01, r 〉 0.50), and control (Mdn = 24.53 to 23.56; Z ≥ 1.96, p < .05, r = 0.30–.50), suggesting a contribution of practice or habituation effects (Fig. 3B).
Physical functioningBoth placebo groups showed significant improvements in SPPB scores from pre- to post-intervention. Improvements were observed in the DP group (Mdn = 10.0 to 11.0; Z ≥ 2.31, p < .05, r ≈ 0.42) and were more pronounced in the OLP group (Mdn = 10.0 to 11.0; Z ≥ 3.51, p < .001, r > 0.50). No significant change was observed in the control group (p = .43) (Fig. 3C).
DiscussionA central contribution of the present study is the direct comparison of deceptive and open-label placebo procedures across multiple domains of functioning in a sample of community-dwelling older adults. Overall, the findings show that placebo interventions were associated with modest improvements in perceived stress, cognitive performance, and psychological functioning, with open-label placebos matching or surpassing the effects of deceptive placebos. These results add to the growing literature showing that placebo mechanisms can operate even when individuals are fully aware that they are receiving an inert substance, underscoring the therapeutic potential of open-label placebos (OLPs) (Ballou et al., 2022; Charlesworth et al., 2017; Kaptchuk et al., 2010; Olliges et al., 2022; Schaefer et al., 2018) and their applicability in aging populations.
Consistent with our hypotheses, we observed a significant reduction in perceived stress in the OLP group relative to both the control and DP groups at post-intervention, suggesting that the open-label procedure provided greater benefits for stress regulation than the deceptive placebo administration. This finding aligns with prior evidence showing that OLPs can reduce self-reported emotional distress and anxiety in healthy individuals (Schaefer et al., 2019, 2021, 2023) through mechanisms such as expectancy formation, mind–body engagement, enhanced self-regulation, and a credible treatment rationale, even when participants know the treatment is inert (Locher et al., 2017; Schaefer et al., 2018). In the present study, the combination of explicit disclosure and a persuasive rationale (Kaptchuk et al., 2010) may have strengthened intrapersonal resources—such as agency and perceived control (Pan et al., 2022)—known to support resilience and healthier aging trajectories (Levy et al., 2002; Robinson & Lachman, 2017; Xu et al., 2025). The less pronounced stress reduction in the DP group further suggests that deception alone may be insufficient to engage these psychosocial mechanisms, likely due to reduced trust or engagement in the absence of transparent information (Guevarra et al., 2024; Miller et al., 2005). Arguably, even positively framed information about an unfamiliar supplement may have elicited uncertainty or suspicion, reinforcing a stricter experimenter–participant hierarchy. By contrast, transparent disclosure in the OLP condition may have enhanced trust in and engagement with the intervention, thereby supporting therapeutic responsiveness (Guevarra et al., 2024; Haas et al., 2022; Pan et al., 2022). In this context, nonverbal cues from the experimenter (e.g., tone, gestures, attentiveness) may also have contributed to reinforcing positive expectations—an effect that may be particularly salient in older adults, who often rely heavily on social and contextual cues (Horta et al., 2024; Smyth & Shanks, 2011; Spreng et al., 2017). Taken together, these observations suggest that OLP effects in the present study may reflect expectancy-related and psychosocial processes. However, treatment expectations were only assessed informally—participants in both placebo groups reported confidence in the intervention’s efficacy at baseline and reaffirmed this during debriefing—through qualitative and not standardized evaluations. Accordingly, it is not possible to determine the extent to which observed improvements reflect placebo mechanisms per se as opposed to broader expectancy-driven or compliance-related influences. In addition, participants in the open-label placebo condition were necessarily aware of the study rationale, which may have increased responsiveness to perceived experimental demands. Future studies should incorporate validated measures of treatment expectations, credibility, adherence, and perceived demand characteristics, as well as additional control conditions, to better isolate the mechanisms underlying placebo responses in older adults.
In line with previous evidence showing that OLPs can match deceptive placebos in domains such as pain, emotional distress, and fatigue (Guevarra et al., 2024; Kaptchuk et al., 2010; Schaefer et al., 2018), the present study extends this literature to cognitive and physical functioning in community-dwelling older adults—an area that has received limited empirical attention. Between-group comparisons indicated that the OLP group outperformed the control group on Digit Span at post-intervention—a difference not observed in the C–DP comparison—supporting the view that OLPs can strengthen attentional and cognitive control through motivational and affective pathways (Guevarra et al., 2020; Schienle et al., 2022). Moreover, the two placebo groups also showed pre–post improvements in memory span and Stroop performance relative to controls. These findings align with theoretical models suggesting that placebo interventions modulate cognitive domains such as inhibitory control and working memory through expectation-driven and affective mechanisms, which may operate similarly in both deceptive and open-label placebo effects (Benedetti et al., 2023; Charlesworth et al., 2017; Guevarra et al., 2020; Kaptchuk et al., 2010; Locher et al., 2017; Sezer et al., 2022; Spille et al., 2023). However, although both placebo groups showed improvements in cognitive performance over time, these within-group changes should be interpreted cautiously, as they do not constitute direct evidence of treatment efficacy. In particular, improvements observed across groups in Stroop performance may reflect practice or habituation effects associated with repeated testing. Similar influences may also have contributed to changes in other cognitive outcomes, including Digit Span performance. Taken together, these findings suggest that the strongest evidence for placebo-related effects in the present study derives from between-group differences favoring the OLP condition.
Within-group improvements in physical performance (SPPB) were observed in both the DP and OLP groups, whereas no change occurred in the control group. Although these findings warrant cautious interpretation, they may suggest a potential role for expectancy-related influences in motor functioning, possibly through perceived capability, motivation, or movement confidence (Carlino et al., 2014; Fiorio et al., 2022; G. Rossettini et al., 2018; Goetz et al., 2002). In addition, prior evidence shows that expectations can influence gait speed, balance, and coordination (Fiorio & Barbiani, 2023), i.e., domains that are central to maintaining functional independence in later life and may thus contribute to overall well-being. The particularly robust pre to post improvements observed in the OLP group further indicate that belief in a purposeful intervention—independent of deception—can enhance outcomes in an objective domain such as physical functioning. This challenges the view that objective improvements arise only under deceptive placebo conditions and the accompanying assumption that OLPs lack biological or objective efficacy (Spille et al., 2023).
Contrarily to our expectations, the absence of changes in the remaining subjective measures (ESS, FAS, LOT-R, GSE, and ASQ), may indicate that placebo effects could be domain-specific, more strongly influencing state-dependent outcomes like perceived stress than broader, trait-like dimensions such as optimism, or self-efficacy, which may be less sensitive to short-term placebo manipulation (Corsi & Colloca, 2017; Zhao et al., 2020). This is consistent with models positing that placebo responses are most likely to emerge when outcomes are state-dependent, dynamic, and susceptible to contextual modulation (G. Rossettini et al., 2018; Schaefer et al., 2018). From a theoretical perspective, our results support the broader applicability of Stereotype Embodiment Theory (Levy, 2009) and mind-body models of aging. Just as self-perceptions and expectations can accelerate or buffer age-related decline, placebo mechanisms appear to leverage these same psychosocial pathways, enhancing multiple domains of functioning even in healthy older adults.
Several limitations should be noted. First, the relatively small sample size may have reduced statistical power to detect smaller effects or group interactions and may partly explain the limited number of significant findings. Although some significant effects were observed—particularly in perceived stress and selected cognitive and physical outcomes—the magnitude of these effects was modest and the number of outcomes examined increases the risk of Type I error despite the use of Bonferroni-corrected post hoc tests. Moreover, the modest sample size, together with the exclusion of individuals taking medications, constrains the generalizability of the findings, particularly to broader populations of older adults who differ in sociodemographic characteristics, cultural backgrounds, health status, and treatment profiles. Taken together, these considerations warrant cautious interpretation of the findings. Secondly, the three-week intervention period restricts conclusions about the long-term durability of placebo-induced changes. Third, although participants were community-dwelling older adults screened through eligibility criteria and functional independence, no formal cognitive screening (e.g., MMSE or MoCA) was conducted. Future studies should incorporate standardized cognitive assessments to better characterize samples and examine whether placebo responsiveness varies as a function of cognitive ability. Fourth, although both subjective and objective measures were included, neurophysiological markers of placebo responsiveness were not assessed. Incorporating indices such as cortisol, heart rate variability, or EEG would allow a more fine-grained understanding of potential alterations in stress physiology or neural processing underlying the observed effects. Finally, the study was not preregistered, which represents an additional limitation given the number of outcomes examined and the exploratory nature of some analyses. Future research would benefit from preregistered designs and larger samples to improve inferential strength and reproducibility.
Implications and future directionsDespite these limitations, the study offers several important implications. The observed efficacy of OLPs suggests their potential as ethical, non-pharmacological interventions to reduce stress, and foster cognitive and physical functioning in older adults. Although placebo effects have traditionally been linked to deception, our findings add to the growing evidence that open-label placebos—when accompanied by a credible mind–body rationale—can be equally or even more effective than deceptive placebos. This approach aligns with principles of autonomy and transparency and represents a low-cost, scalable strategy that can be integrated into cognitive training, physical rehabilitation, or outpatient and community-based programs without ethical concerns or adverse effects (Blease et al., 2016). Importantly, the domain-specific effects observed here also suggest that placebo responsiveness may be optimized by tailoring rationales to the targeted psychological or cognitive domain.
Future research with larger and more diverse samples is warranted to establish the robustness and external validity of the present findings. Such work should also prioritize identifying the mechanisms—such as expectancy formation, emotion regulation, autonomic functioning, and embodied cognition—that mediate placebo responses in older adults and determine whether these effects endure over time. Key questions include whether repeated engagement with OLPs yields sustained or cumulative benefits and how such effects interact with lifestyle interventions such as physical activity or cognitive training. Finally, future studies could incorporate active control conditions (e.g., attention-matched interventions) to better isolate placebo-specific effects, monitoring, and standardized assessments of treatment credibility and blinding to strengthen causal interpretation. Addressing these issues may help identify effective, low-cost, and ethically acceptable strategies for enhancing functioning and well-being in aging populations.
ConclusionsOverall, the present findings suggest that placebo interventions may be associated with modest improvements in selected psychological and performance outcomes in older adults, with the strongest evidence emerging from between-group differences favoring the open-label placebo (OLP) condition. Although some improvements were also observed in the deceptive placebo group, these were primarily evident in within-group analyses and should therefore be interpreted cautiously. The more consistent effects observed in the OLP condition suggest that transparency paired with a credible rationale may engage expectancy-related processes in ways that support short-term changes in selected outcomes.
These findings contribute to the growing literature on open-label placebos and suggest their potential as ethical and transparent approaches for supporting aspects of functioning in aging populations. However, given the modest effect sizes, limited sample size, and variability across outcomes, the present results should be considered preliminary. Future research should examine the durability of these effects, clarify the mechanisms involved, and evaluate the broader applicability of OLPs across diverse health domains in older adults.
Compliance with ethical standardsAll procedures were in accordance with the ethical standards of the 1964 Helsinki Declaration and its later amendments or comparable ethical standards. This study was approved by the local committee for approval of the research in humans (CERPS_101/24) of the University of Milan (Italy).
Author contributionsD.B. and F.P. conceived and planned the study. D.B. coordinated the study, conducted data collection, performed the statistical analyses, and wrote the initial manuscript draft. F.P. and A.A. contributed to the interpretation of findings and provided critical revisions and editorial feedback on the manuscript. All authors reviewed and approved the final version of the manuscript.
FundingThis work was funded by the European Union - Next Generation EU. The views and opinions expressed are only those of the authors and do not necessarily reflect those of the European Union or the European Commission. Neither the European Union nor the European Commission can be held responsible for them.
The authors declare that they have no known competing financial interests or personal relationships that could have appeared to influence the work reported in this paper.
The authors would like to thank to Irene Lux, Marta La Viola, and Elisabetta Bolla for their invaluable assistance with participant recruitment and data collection. The authors also thank all participants for their willingness and motivation to take part in the study.

articles