




Non-pharmacological interventions for sustained-attention difficulties in young adults remain limited. Transcranial pulse stimulation (TPS), a focused ultrasound-based neuromodulation technique, has shown preliminary promise in improving neuropsychiatric symptoms, but its effects on sustained attention in young adults are unclear. We therefore compared TPS with electroencephalography (EEG)-based theta-beta ratio (TBR) neurofeedback (NF) and a wait-list control (WLC) in young adults with subclinical sustained-attention difficulties.
MethodsThis single-centre, three-arm, parallel-group randomised controlled trial enrolled right-handed adults aged 20–34 years with subclinical sustained-attention difficulties. Participants were assigned to TPS, NF, or WLC. Both active interventions comprised 12 sessions over 4 weeks. Primary outcomes were performance indices from the Conners Continuous Performance Test, Third Edition (CPT-3), including detectability (d′), omission errors, commission errors, perseverations, hit reaction time (HRT), HRT standard deviation, reaction-time variability, HRT block change, and HRT interstimulus-interval change. Secondary outcomes included self-report measures of attentional control, psychological distress, anxiety, depression, self-esteem, social connectedness, and additional cognitive tasks. Outcomes were analysed using linear mixed-effects models with false discovery rate correction.
ResultsFifty-seven participants were analysed (TPS = 22, NF = 12, WLC = 23; mean age = 24.2 years; 60% female). At post-treatment, TPS showed greater improvement than NF on 8 of 9 CPT-3 outcomes (false discovery rate-adjusted q = 0.001–0.033; Cohen’s d = −0.93 to −1.61) and greater improvement than WLC on 5 of 9 CPT-3 outcomes (q = 0.001–0.031; d = −0.75 to −1.39). NF did not outperform WLC on any CPT-3 outcome. Among subjective-report outcomes, TPS showed a greater reduction in depressive symptoms than NF (Hospital Anxiety and Depression Scale-Depression, q = 0.028; d = −0.91), whereas no other between-group differences survived correction. No between-group differences in CPT-3 outcomes survived correction at 1- to 3-month follow-up. No serious adverse events occurred. Exploratory EEG analyses suggested successful modulation of the trained TBR target in the NF group, but this did not translate into measurable cognitive benefit.
ConclusionsTPS was associated with greater short-term improvement in sustained attention than NF or WLC in young adults with subclinical attention difficulties. However, durability remains uncertain because between-group effects were not maintained at follow-up. Larger, blinded, sham-controlled trials are needed to determine the specificity, clinical significance, and longer-term durability of TPS effects.
Sustained attention—the capacity to maintain goal-directed focus over time—is a core cognitive skill that supports learning, communication, and everyday self-regulation (Posner & Rothbart, 2007). Across childhood, adolescence, and adulthood, individual differences in sustained attention are reliably associated with variation in academic achievement and everyday functioning (Sharpe & Tyndall, 2025). Difficulties with sustained attention are central to attention-deficit/hyperactivity disorder (ADHD) but also occur dimensionally below diagnostic thresholds (i.e., subthreshold attention deficits), where they are still linked to meaningful functional impairment (Kirova et al., 2019). Pharmacotherapy—especially psychostimulants—remains the most consistently effective option for reducing core symptoms of those with diagnosed attention deficits across the lifespan (Bellato et al., 2025; Ostinelli et al., 2025). However, for individuals with subclinical or subthreshold attention difficulties, evidence-based care pathways are less well defined, and few tailored options are available. Consequently, there is growing interest in safe, scalable, non-pharmacological interventions to strengthen sustained attention across the spectrum of severity.
Non-invasive brain stimulation (NIBS) aims to modulate attention networks by altering cortical excitability. Transcranial pulse stimulation (TPS), a focused-ultrasound modality that delivers ultrashort acoustic pulses, can target deep structures with millimetre-scale precision through the intact skull, offering an exciting alternative to other NIBS methods that primarily target superficial structures (O’Reilly, 2024). Early studies in Alzheimer’s disease reported short-term cognitive gains (Beisteiner et al., 2020), and a pilot study in adolescents with ADHD found ∼30% reductions in proxy-symptom ratings sustained to 1–3 months (Cheung et al., 2024).
Despite growing interest in TPS, evidence for its effects on sustained attention in young adults remains sparse, and no trial has directly compared TPS with EEG neurofeedback, one of the earliest and most widely studied neurobehavioral neuromodulation approaches. EEG neurofeedback uses real-time brain-signal feedback to shape neural activity and behaviour through operant conditioning and is hypothesised to promote self-regulation and neuroplastic change (Sitaram et al., 2017). Although earlier studies and meta-analyses have reported improvements in ADHD symptoms, particularly in pre–post or less stringently blinded designs (Cortese et al., 2016), evidence for specific effects remains mixed. More rigorous sham-controlled and blinded trials have reported limited or no superiority of neurofeedback over sham or active control conditions (Arnold et al., 2021; Schönenberg et al., 2017), and recent syntheses suggest that observed benefits may partly reflect non-specific factors, expectancy effects, or neurofeedback learning that does not consistently transfer to objective attentional performance (Purper-Ouakil, 2023; Westwood et al., 2025). Therefore, comparing TPS with EEG neurofeedback and a wait-list control is important for evaluating their relative shorter-term and longer-term effects on sustained attention. The two approaches differ mechanistically: neurofeedback trains endogenous self-regulation, whereas TPS delivers exogenous acoustic neuromodulation, which may lead to different profiles of efficacy, transfer, and durability.
We therefore conducted a randomized controlled trial comparing TPS with EEG-based neurofeedback in young adults to evaluate their effectiveness in improving attention-related cognitive abilities, including a wait-list control to account for practice and other non-specific effects. The primary performance outcome was the Conners Continuous Performance Test, Third Edition (CPT-3), a well-validated assessment of sustained attention that provides multiple indices, including detectability, omission and commission errors, hit reaction time, reaction-time variability, perseverations, and changes across task blocks and interstimulus intervals (Conners, 2014). To provide a broader overview of attention-related cognitive functioning, we also included complementary cognitive tasks assessing working memory updating using the n-back task (Owen et al., 2005), interference control using the Stroop task (Scarpina & Tagini, 2017), and processing speed/set-shifting using the Color Trails Test (D’Elia et al., 1996). Given the broad impact of sustained attention on overall functioning, we anticipated that improvements in attention might also benefit mood and related psychosocial functioning. Accordingly, we included secondary self-report measures assessing attentional control, general psychological distress, anxiety and depressive symptoms, goal orientation, self-esteem, and social connectedness. Participants were assessed before and after the intervention, with additional follow-up sessions at 1, 2, and 3 months post-intervention to evaluate the durability of treatment effects.
We hypothesised that both active interventions would improve sustained attention relative to the control condition. Furthermore, because TPS provides direct stimulation that affects task performance, it should yield broader and/or more persistent gains than neurofeedback.
MethodsInterventionsTranscranial Pulse Stimulation (TPS): TPS was delivered using the NEUROLITH system (Storz Medical AG, Tägerwilen, Switzerland), a certified ultrasound neuromodulation device. The stimulation protocol followed the parameters described by Beisteiner et al. (2020), adapted for the present attention-focused trial. Each session consisted of single ultrashort ultrasound pressure pulses delivered with a pulse duration of approximately 3 μs, a pulse repetition frequency of 5 Hz, and an energy flux density of 0.2 mJ/mm². Stimulation targets were localized using the device-integrated infrared camera-based MR neuronavigation/tracking system based on a template T1-weighted anatomical image. Target regions included bilateral frontal/prefrontal regions, including the dorsolateral prefrontal cortex, bilateral lateral parietal regions, and the midline parietal/precuneus region. These regions were selected based on the network-based TPS protocol described by Beisteiner et al. (2020) and adapted to engage frontoparietal attention-control networks implicated in sustained attention, executive regulation, attentional allocation, and attentional lapses (Beisteiner et al., 2020; Corbetta & Shulman, 2002; Dosenbach et al., 2008; Esterman et al., 2013; Petersen & Posner, 2012). Each TPS session delivered 6000 pulses in total: 1600 pulses to each frontal/prefrontal hemisphere, 800 pulses to each parietal hemisphere, and 1200 pulses to the midline parietal/precuneus target. Participants wore ear protection during TPS to mitigate audible clicks from the device.
EEG Neurofeedback (NF): Neurofeedback training sessions were conducted in a quiet room with the participant seated in front of a computer. Ag/AgCl scalp electrodes were placed according to the 10–20 system to record EEG, with a focus on the theta-beta ratio at Cz. The NF protocol was implemented as an individualized adaptive theta/beta ratio (TBR)-reduction protocol. Theta and beta were operationalized as 4–7 Hz and 13–30 Hz, respectively. The overall training goal was to reduce TBR, which could be achieved through decreased theta activity, increased beta activity, or both. Before the first training session, participants underwent a baseline qEEG assessment to determine individualized training thresholds. During each 45-minute active training session, participants completed 4–5 training blocks of approximately 8–10 min each, with brief rest periods between blocks. For each block, the training target was set according to the participant’s baseline qEEG threshold and current training performance; beta enhancement was more commonly used as the immediate reinforcement target, while the overarching intervention goal remained TBR reduction. Thresholds were adjusted between blocks according to predefined performance criteria: if participants exceeded the target threshold for >70% of a block, the threshold was increased for the next block; if they achieved the target for <30% of a block, the threshold was decreased for the next block; otherwise, the threshold was maintained. During each 45-minute session, participants engaged in a feedback video game or task where a continuous audiovisual display (for example, a moving graph or animation) responded in real time to their brainwave activity. They were instructed to concentrate and adjust their mental state to keep the feedback within target ranges (for instance, by rewarding increases in beta rhythm or reductions in slow theta activity). The training aimed to reinforce brain states associated with alertness. The coach provided standardized task instructions and brief supportive prompts during active training. These prompts included general self-regulation strategies, such as maintaining relaxed concentration, focused breathing, or visualization. Additional encouragement or strategy reminders were provided on an as-needed basis when participants had difficulty progressing or maintaining the feedback target. Coaching was supportive and procedural in nature and did not alter the predefined adaptive thresholding rules.
Schedule Participants in both the TPS and NF groups completed 12 scheduled sessions over 4 weeks (3 sessions per week; approximately 45 min per session). All participants underwent follow-up assessments at 1, 2, and 3 months post-treatment. Make-up sessions were permitted within the same week to maintain consistency of training intensity. The wait-list control group received no intervention during the study period and was instructed to continue their usual daily routines. All groups were asked to refrain from initiating any new attention-related pharmacological or behavioural treatments during the study period, including psychostimulant medication such as methylphenidate, cognitive training, neurofeedback outside the study, or other neuromodulatory interventions.
Study design and participantsA single-centre, parallel-group randomized trial was conducted with three arms: a TPS intervention group, an NF (EEG neurofeedback) intervention group, and a no-treatment waitlist control group. Participants were randomly assigned in a 1.5:1:1.5 ratio2 to the TPS, NF, or control group using a computer-generated randomization sequence. Due to the nature of the interventions, participants and providers could not be blinded to group assignment. The waitlist control group received no active intervention during the 4-week study period but underwent the same schedule of assessments as the TPS and NF groups. Participants in the control group were offered a choice of intervention after study completion. The trial was conducted at The University of Hong Kong, Hong Kong SAR, between November 2022 and March 2025. Participants were recruited through posters displayed on the HKU campus, online advertisements, and university mass emails. Eligible participants were randomly assigned to one of three arms: a TPS intervention group, an EEG neurofeedback (NF) intervention group, or a no-treatment wait-list control group. Participants received HKD 100 (approximately USD 12.76) for attending the eligibility screening, HKD 1200 (approximately USD 153.12) for completing the baseline assessment, treatment or wait-list period, and post-intervention assessment, and HKD 280 (approximately USD 35.73) for each follow-up visit. The study was approved by the Human Research Ethics Committee of The University of Hong Kong (HREC approval number: EA220456), and all participants provided written informed consent before participation.
Eligibility. Participants were right-handed adults aged 20–34 years with normal (or corrected) vision and hearing, basic literacy, no neurological or psychiatric diagnoses other than ADHD (inattentive or combined), and no intellectual disability (TONI-4 IQ ≥ 90). Sustained attention had to fall at least 0.5 SD below age- and sex-adjusted norms (Heaton et al., 1991) on the Digit Vigilance Test (Lewis & Rennick, 1979) (reaction time or error rate), ensuring a subclinical attention deficit; candidates performing above the normative mean on both metrics were excluded.
Exclusions. Participants were screened out for any brain-related medical history, mild cognitive impairment, current or recent (≤ 6 weeks) corticosteroid use, bleeding or clotting disorders (e.g., hemophilia, thrombosis), alcohol/substance misuse, long-term smoking, or HADS anxiety or depression scores ≥ 10.
Outcome measuresData were gathered using one computerized attention task, three complementary cognitive tasks, and six standardized self-report questionnairesComputerized attention tests. Sustained attention was assessed using the Conners Continuous Performance Test, Third Edition (CPT-3; Multi-Health Systems; Conners, 2014), administered and scored using the standardized Conners CPT-3 software/manual pipeline. The CPT-3 is a computerized go/no-go sustained-attention task in which letters are presented one at a time and participants are instructed to respond to all letters except “X.” The standard administration lasts approximately 14 min and consists of 360 trials arranged into 6 blocks, with 3 sub-blocks per block and 20 trials per sub-block. All outcomes are reported as T-scores, with higher scores indicating poorer performance. Detectability (d′) reflects target–non-target discrimination; omission errors (OMI) reflect missed targets and inattention; commission errors (COM) reflect responses to non-targets and impulsive responding; perseverations (PER) reflect very rapid, anticipatory responses; hit reaction time (HRT) reflects response speed; HRT standard deviation (HRT-SD) and variability (VAR) reflect inconsistency in response speed; HRT block change (HRT-BC) reflects changes in performance across task blocks; and HRT inter-stimulus-interval change (HRT-ISI) reflects changes in performance across different inter-stimulus intervals. These indices are best interpreted as complementary indicators of attentional performance rather than isolated measures of single cognitive processes (Conners, 2014).
Other cognitive tasks. Working memory was assessed using a computerized digit 2-back task programmed and administered in E-Prime 3.0 [ Psychology Software Tools, Pittsburgh, PA, USA]. Participants completed one block of 100 2-back trials, and accuracy and hit reaction time were used as outcome variables (Owen et al., 2005). Cognitive flexibility and interference control were assessed using the paper-and-pencil three-card Victoria Stroop Task, administered with standard test materials (Regard, 1981). The task included the standard Color, Word, and Color-Word conditions, each containing 24 items; naming time was recorded for each condition, and the interference index was computed as I = CW − [(W × C)/(W + C)] following Scarpina and Tagini (Scarpina & Tagini, 2017). Processing speed and set-shifting were assessed using the paper-and-pencil Color Trails Test with standard test materials (D’Elia et al., 1996). Completion time, including error-correction latency, was recorded for Trial 1, which requires sequential number connection, and Trial 2, which requires alternating colour/number sequencing.
Self-report questionnaires. Self-report attention-control was captured by the 20-item Attentional Control Scale (ACS) (Derryberry & Reed, 2002). Psychological distress was screened with the Chinese 12-item General Health Questionnaire (GHQ) (Goldberg & Williams, 1988; Lai & Yue, 2000). The Hospital Anxiety and Depression Scale (HADS) (Zigmond & Snaith, 1983) provided 7-item anxiety and depression subscores. Learning-goal orientation was assessed using the 5-item Goal Orientation Scale (GOS). (Brett & VandeWalle, 1999) Self-esteem was assessed with the Rosenberg Self-Esteem Scale (RSES) (Rosenberg, 1965). Finally, perceived belonging was measured with the 20-item Social Connectedness Scale–Revised (SCS-R) (Lee & Robbins, 1995). Higher ACS, GOS, RSES, and SCS-R totals indicate better functioning; whereas lower error counts, reaction times, CPT measures, and symptom scales (GHQ & HADS) indicate better functioning. See Supplementary Table 10 for detailed self-report questionnaire information.
EEG methods. EEG was acquired using a DEYMED Diagnostic neurofeedback system with a TruScan EEG amplifier (DEYMED Diagnostic., Hronov, Czech Republic). Ag/AgCl electrodes were placed at Cz and Fz according to the international 10–20 system, with A1 and A2 electrodes placed on the left and right earlobes. Both Cz and Fz were referenced to the averaged linked-earlobe reference, calculated as the average of A1 and A2. As a supplement, an exploratory neurophysiological component of the trial, a 5-minute eyes-open resting-state qEEG was recorded at baseline and post-intervention to examine potential neural correlates of treatment response to NF and TPS. EEG data were available for the NF group (n = 12) and a subset of the TPS group (n = 8), as this exploratory substudy was conducted only among participants with available EEG data due to logistical and scheduling constraints. Analyses focused on the midline electrodes Cz and Fz. Extracted indices included relative delta (1–4 Hz), theta (4–7 Hz), alpha (8–13 Hz), and beta (13–30 Hz) power, theta-beta ratio (TBR), aperiodic offset and exponent, and the signal complexity measures sample entropy (SampEn) and approximate entropy (ApEn). Relative band powers reflect the distribution of oscillatory activity across conventional frequency bands; TBR reflects the balance between slower theta and faster beta activity and entropy-based measures index signal irregularity and complexity; and offset and exponent characterize the aperiodic component of the EEG power spectrum. Baseline-to-post changes in these 5-minute EEG measures were then examined separately within the NF and TPS groups. See supplement file 2 for detailed supplementary EEG analysis methods.
Safety and tolerability assessment. Safety and tolerability were monitored throughout the intervention period using a structured adverse-event checklist and open-ended symptom reporting. After intervention sessions, participants were asked whether they had experienced any adverse events or discomfort. The checklist covered common symptoms relevant to non-invasive brain stimulation and neurofeedback, including local scalp discomfort or paresthesia, headache, dizziness or vertigo, nausea, fatigue or drowsiness, and anxiety or mood change. Participants were also asked to report any other symptoms not listed in the checklist. Reported events were categorized by symptom type and summarized descriptively by treatment group. Serious adverse events and discontinuations due to adverse events were recorded separately.
Statistical analysisThe efficacy of TPS and NF interventions was evaluated by analysing changes in outcome measures over time and between groups. Outcome measures were grouped into three conceptually defined families: Conners CPT (d′, OMI, COM, PER, HRT, HRT-SD, VAR, HRT-BC, HRT-ISI.), subjective-report scales (Attentional Control Scale, GHQ-12, GOS, HADS-Anxiety, HADS-Depression, RSES, SCS-R), and other cognitive tests (Stroop times and inference, N-Back accuracy and reaction time, CTT times). For each outcome, we fitted a linear mixed-effects model of the form Value ∼ Timepoint × Group + (1|Participant), where Timepoint (Baseline, Post, Fu1, Fu2, Fu3) and Group (NF, Control, TPS) were treated as fixed factors, and a random intercept captured between-participant variability. Primary efficacy analyses followed an intention-to-treat (ITT) principle: all randomised participants with at least one post-baseline assessment were included and analysed according to their randomised group. Models were estimated by maximum likelihood, and denominator degrees of freedom were computed using the Satterthwaite approximation.
Within-group change was assessed using estimated marginal means (EMMs) of timepoint within each group, comparing each follow-up (Post, Fu1–Fu3) with Baseline (two-sided α=0·05). Between-group effects were assessed as visit-specific 2 × 2 contrasts of the Group×Timepoint interaction (Baseline vs each follow-up), using EMMs from the mixed model. For each follow-up, we compared changes from baseline between groups: (Follow-up − Baseline in group A) − (Follow-up − Baseline in group B). Tests were two-sided (α=0·05) with Satterthwaite degrees of freedom.
To control the false discovery rate (FDR) across multiple contrasts, raw p values were adjusted using the Benjamini–Hochberg procedure separately for each outcome family and contrast type (i.e., within-group vs between-group). Analyses used all available observations under a missing-at-random (MAR) assumption, and likelihood-based mixed models yield valid inferences without outcome imputation. Contrasts with FDR-adjusted p values (q) <0·05 were considered statistically significant. All analyses were conducted in R4.5; analytical choices and contrast definitions were aligned with ICH E9(R1) guidance (Benjamini & Hochberg, 1995; International Council for Harmonisation of Technical Requirements for Pharmaceuticals for Human Use, 2019; Kenward & Roger, 1997; Kuznetsova et al., 2017; Lenth, 2025; National Research, 2010; Satterthwaite, 1946).
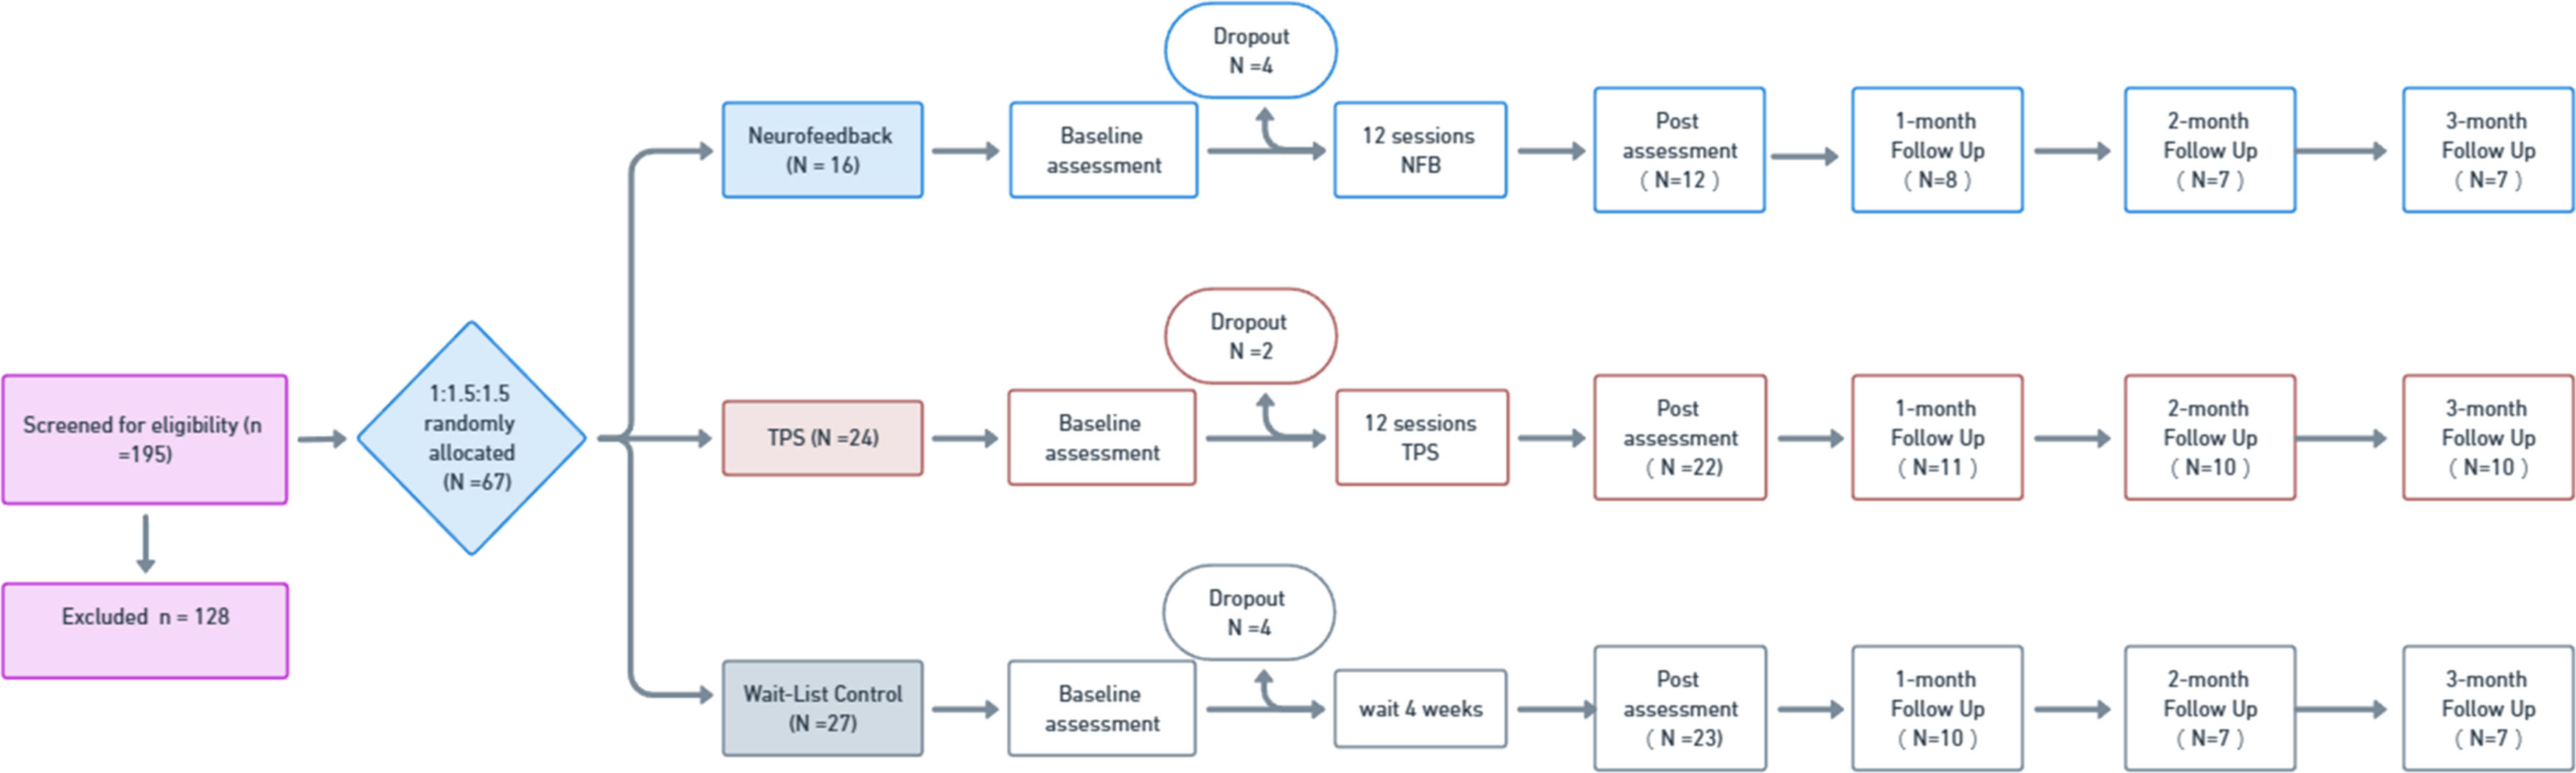
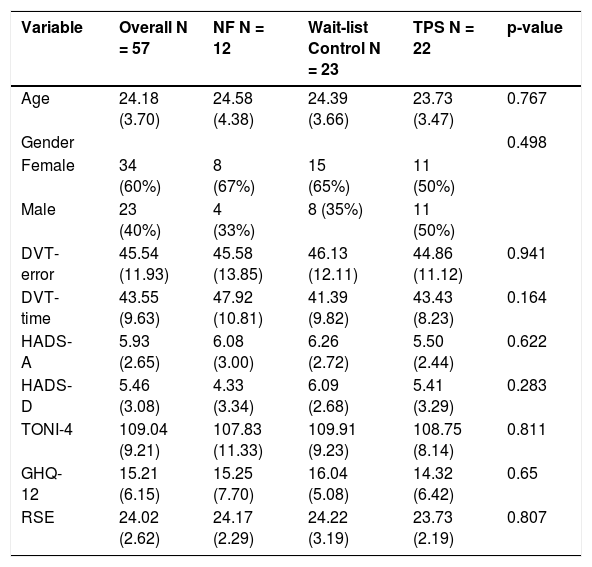
ResultsParticipant characteristics.Fig. 1 depicts participant recruitment and retention. Of 195 individuals screened for eligibility, 67 were randomized in a 1:1.5:1.5 ratio to neurofeedback (NF; n = 16), transcranial pulse stimulation (TPS; n = 24), or wait-list control (WLC; n = 27). Of 195 individuals screened for eligibility, 67 were randomized to neurofeedback (NF; n = 16), transcranial pulse stimulation (TPS; n = 24), or wait-list control (WLC; n = 27). Ten participants withdrew after randomization but before entering the intervention/wait-list phase (NF = 4; TPS = 2; WLC = 4). Across all three arms, withdrawals were attributed to inability to comply with the study schedule and/or changes in personal plans, followed by withdrawal of consent. The remaining 57 participants completed baseline assessment and entered the study. All participants with at least one post-baseline assessment were included in the analysis. Table 1 summarizes demographic and clinical characteristics. The overall sample (N = 57) had a mean age of 24.18 ± 3.70 years, and 60% were female. Baseline age (NF = 24.58 ± 4.38; WLC = 24.39 ± 3.66; TPS = 23.73 ± 3.47; p = .767) and sex distribution (p = .498) were comparable across groups. There were no significant between-group differences at baseline in sustained attention (DVT errors and reaction time), anxiety (HADS-A), depression (HADS-D), nonverbal intelligence (TONI-4), general psychological distress (GHQ-12), or self-esteem (RSE) (all p > .16).

CONSORT flow of participants. Of 195 individuals screened, 128 were excluded and 67 were randomized in a 1:1.5:1.5 ratio to neurofeedback (NF, n = 16), transcranial pulsed stimulation (TPS, n = 24), or wait-list control (WLC, n = 27). After baseline, NF and TPS completed 12 treatment sessions, and WLC waited 4 weeks. Attrition before post-assessment was NF = 4, TPS = 2, WLC = 4, yielding post-treatment samples of NF n = 12, TPS n = 22, and WLC n = 23 (participants included in the analysis). Follow-up completers were: 1-month—NF = 8, TPS = 11, WLC = 10; 2-months—NF = 7, TPS = 10, WLC = 7; 3-months—NF = 7, TPS = 10, WLC = 7.
Demographic characteristics of participants.
Note. DVT-error = Digit Vigilance Test total errors; DVT-time = Digit Vigilance Test mean reaction time (ms); HADS-A = Hospital Anxiety and Depression Scale-Anxiety subscale; HADS-D = Hospital Anxiety and Depression Scale-Depression subscale; TONI-4 = Test of Nonverbal Intelligence, Fourth Edition; GHQ-12 = General Health Questionnaire, 12-item version; RSE = Rosenberg Self-Esteem Scale. Data are mean (SD) for continuous variables and n (%) for categorical variables. p-values for continuous measures were derived from one-way ANOVA; p-value for gender was derived from the chi-square test. Significance threshold was set at p < .05.
Post-treatment assessments were completed by 12 participants in the NF group, 22 in the TPS group, and 23 in the WLC group. Owing to logistical constraints related to the COVID-19 outbreak, follow-up data were available for 29 participants (50.9%) at 1 month, 24 (42.1%) at 2 months, and 24 (42.1%) at 3 months. Follow-up completion rates were 66.7% (8/12), 58.3% (7/12), and 58.3% (7/12) in the NF group; 50.0% (11/22), 45.5% (10/22), and 45.5% (10/22) in the TPS group; and 43.5% (10/23), 30.4% (7/23), and 30.4% (7/23) in the WLC group at 1, 2, and 3 months, respectively.
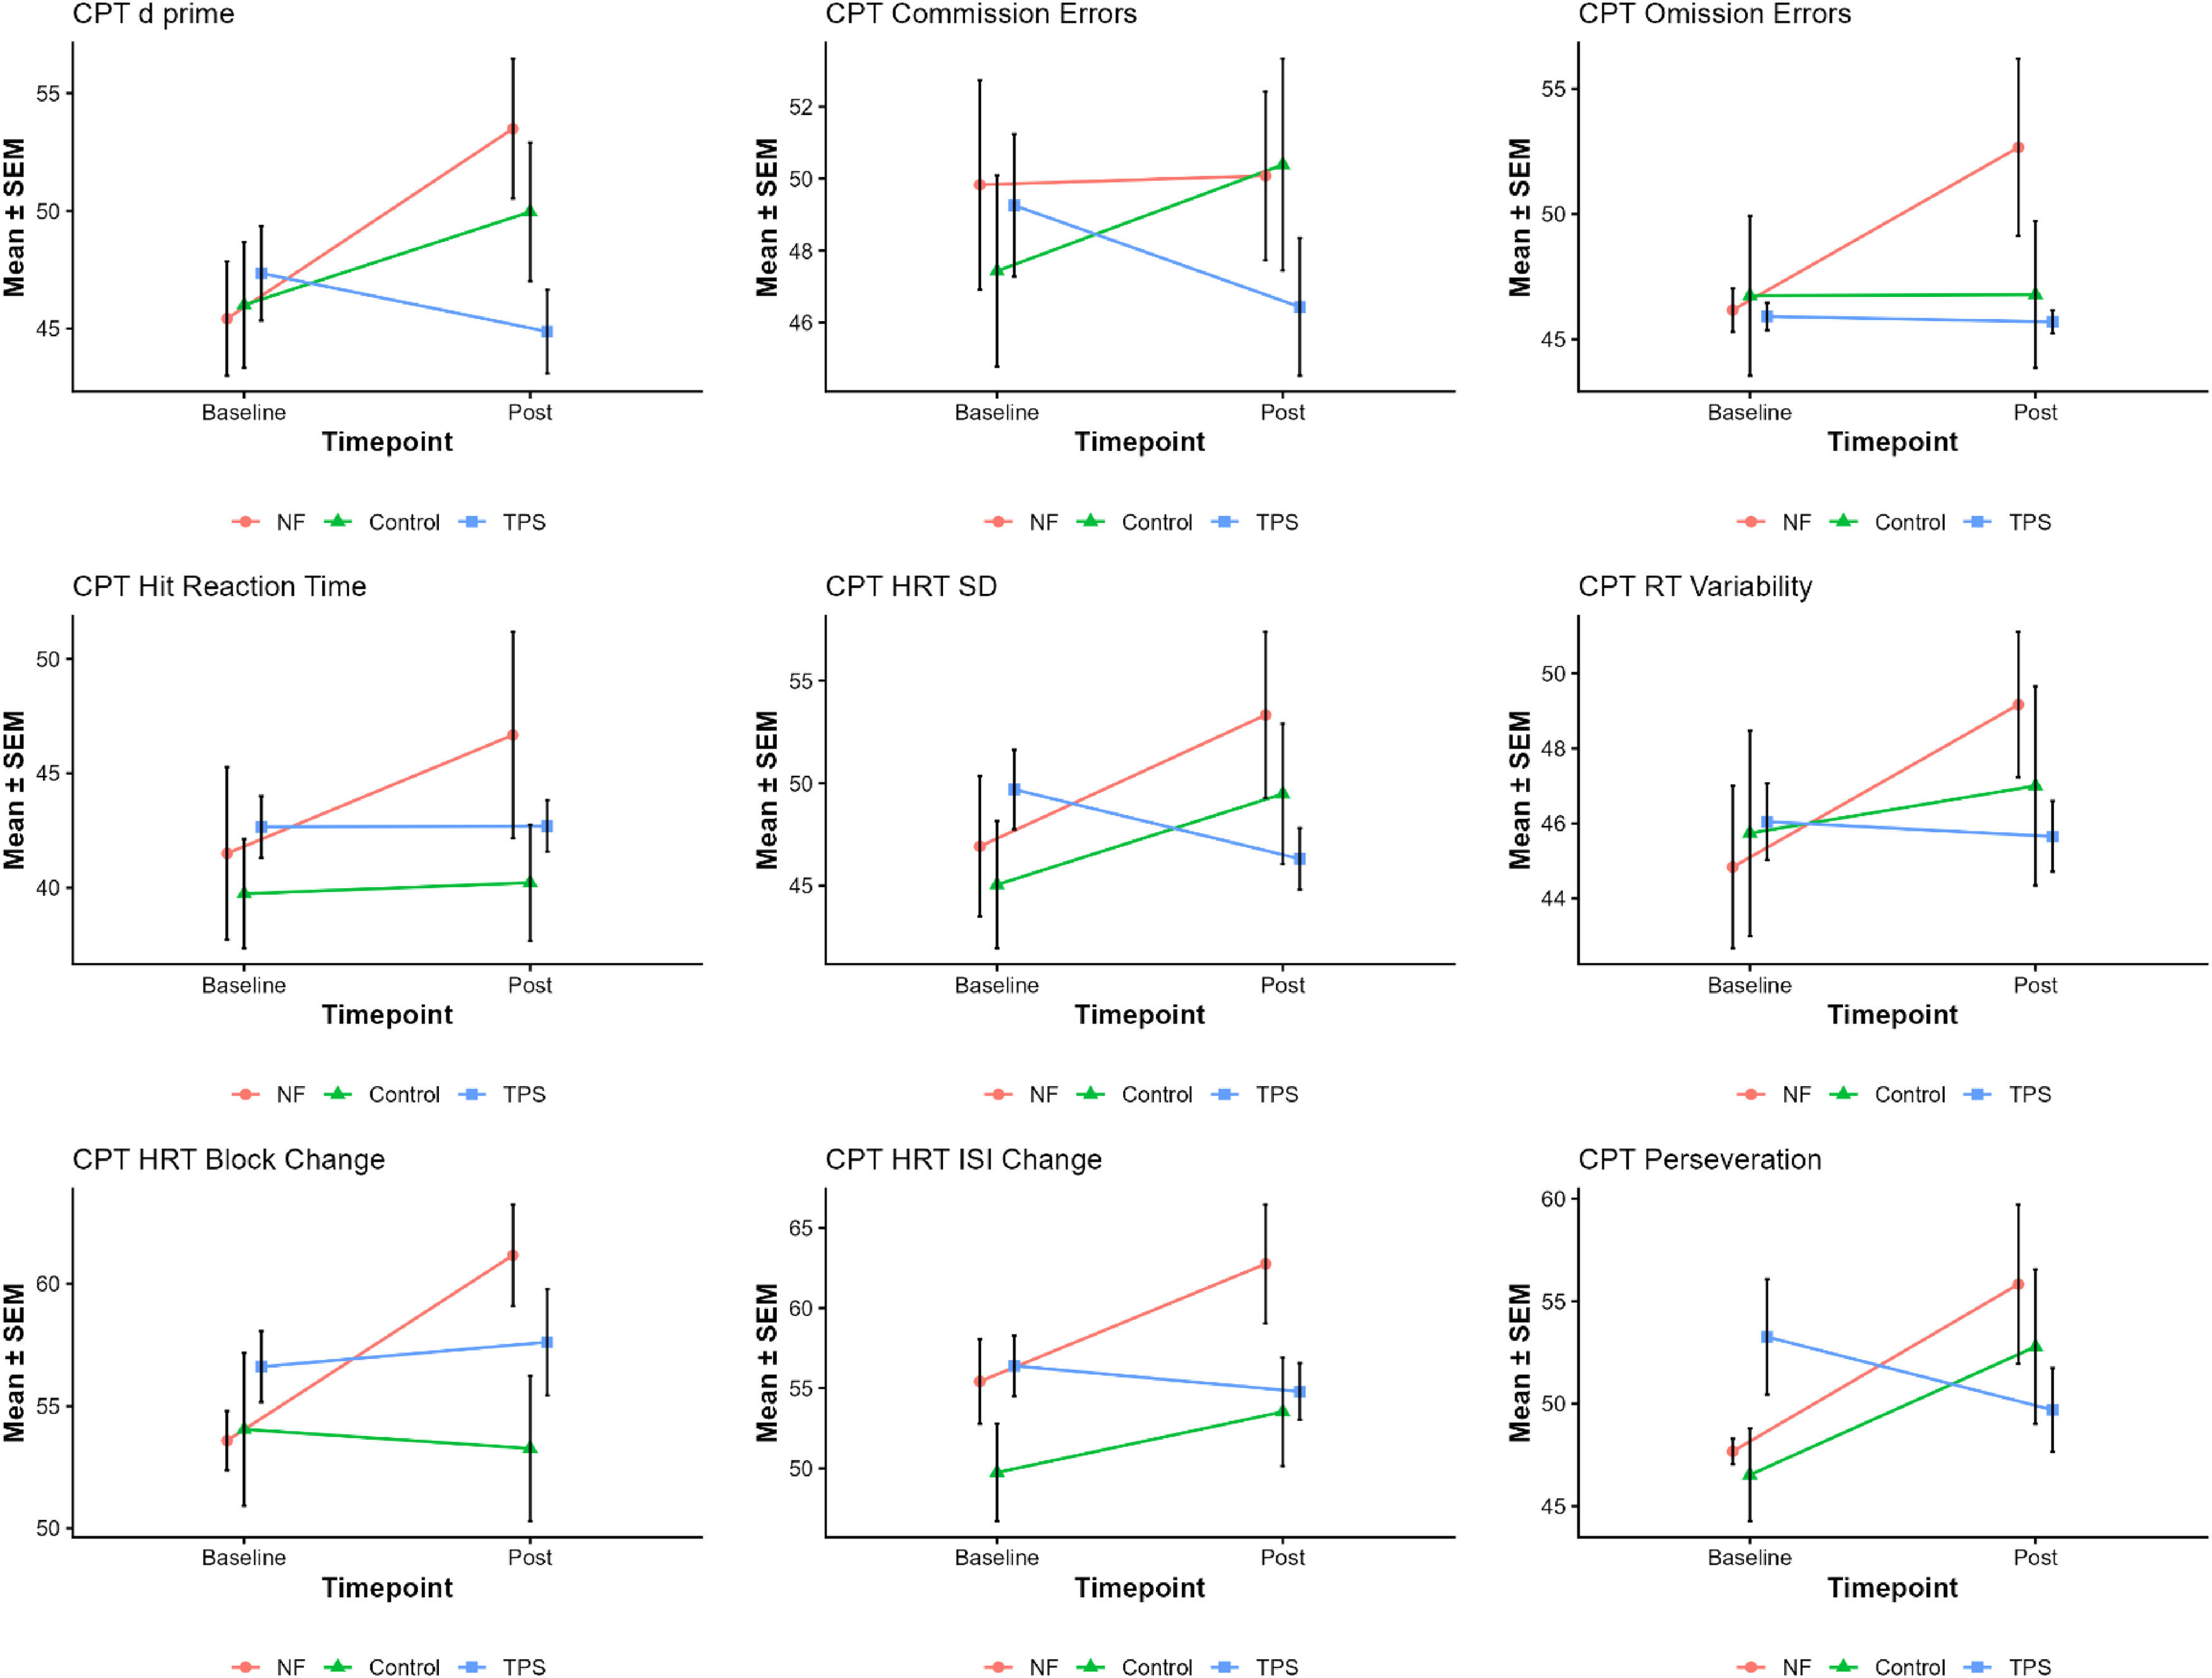
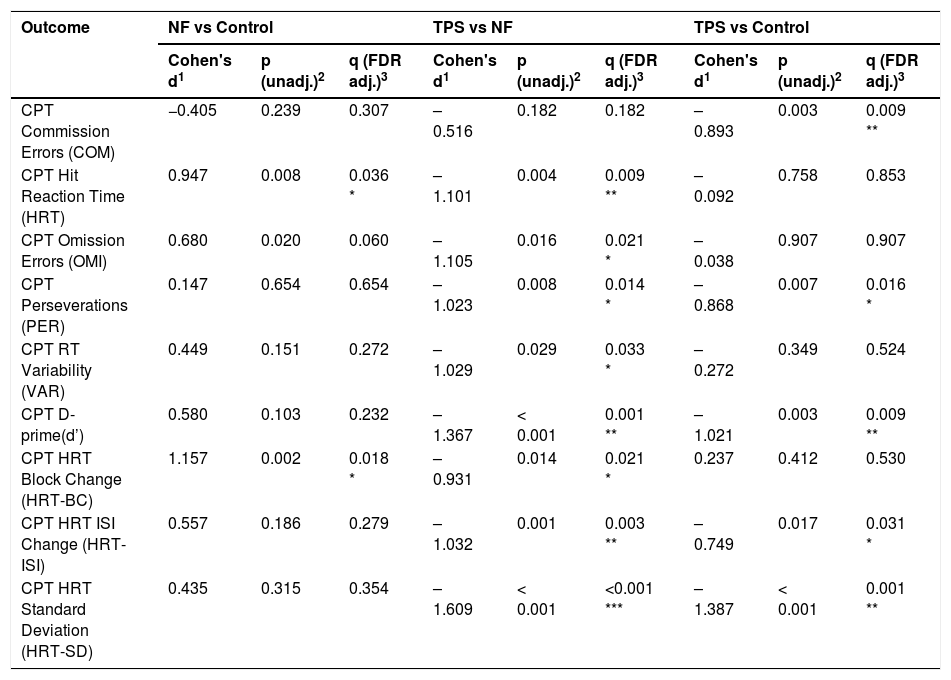
Attention task performance (Conners CPT-3). In between-group analyses (Fig. 2; Table 2), after FDR correction, TPS showed greater pre–post improvement than NF on 8 of 9 CPT-3 outcomes—HRT, OMI, PER, VAR, d′, HRT-BC, HRT-ISI, and HRT-SD (q = 0.001–.033; d = −0.93 to −1.61)—with no significant difference for COM (q = 0.182). Compared with WLC, TPS showed greater improvement on 5 of 9 outcomes—COM, PER, d′, HRT-ISI, and HRT-SD (q = 0.001–.031; d = −0.75 to −1.39); all other contrasts were non-significant (q ≥ 0.524). NF differed from WLC only on HRT and HRT-BC (q = 0.036 and 0.018; d = 0.95 and 1.16), indicating less favorable change in NF than in WLC on these outcomes.

Pre–post changes on Conners CPT-3 outcomes. Group means (±SEM) at baseline and post-intervention for neurofeedback (NF, orange), transcranial pulsed stimulation (TPS, blue), and wait-list control (WLC, green). Panels show: detectability (d′), commission errors (COM), omission errors (OMI), hit reaction time (HRT), HRT standard deviation (HRT-SD), RT variability (VAR), HRT block change (HRT-BC), HRT inter-stimulus-interval change (HRT-ISI), and perseverations (PER). All values are CPT-3 T-scores; higher scores denote poorer performance.
Between-group comparison of pre- to post-intervention changes in Conners CPT scores.
Note. Cohen's d was calculated on each subject's change scores (post - pre) as the difference in mean change between two groups divided by the pooled standard deviation of those change scores. A negative d indicates that the first group produced a greater reduction in score than the second group. p (unadj.) is the unadjusted p-value from the time x group interaction term of the linear mixed model. q (FDR adj.) is the Benjamini-Hochberg false-discovery-rate-adjusted q-value. * q < 0.05, ** q < 0.01, *** q < 0.001.
Within-group analyses (Supplementary Table S1) showed significant pre–post increases in CPT-3 T-scores (indicating worsening) in the NF group on 7 of 9 indices—HRT-BC, HRT-ISI, HRT-SD, HRT, OMI, PER, and VAR (q ≤ 0.024; d = 0.59–1.33)—and in the WLC group on HRT-ISI, HRT-SD, PER, and d′ (q ≤ 0.041; d = 0.50–1.00). In the TPS group, only HRT-SD showed a significant decrease (improvement; q = 0.036; d = −0.51), whereas all other pre–post changes were non-significant (q ≥ 0.171).
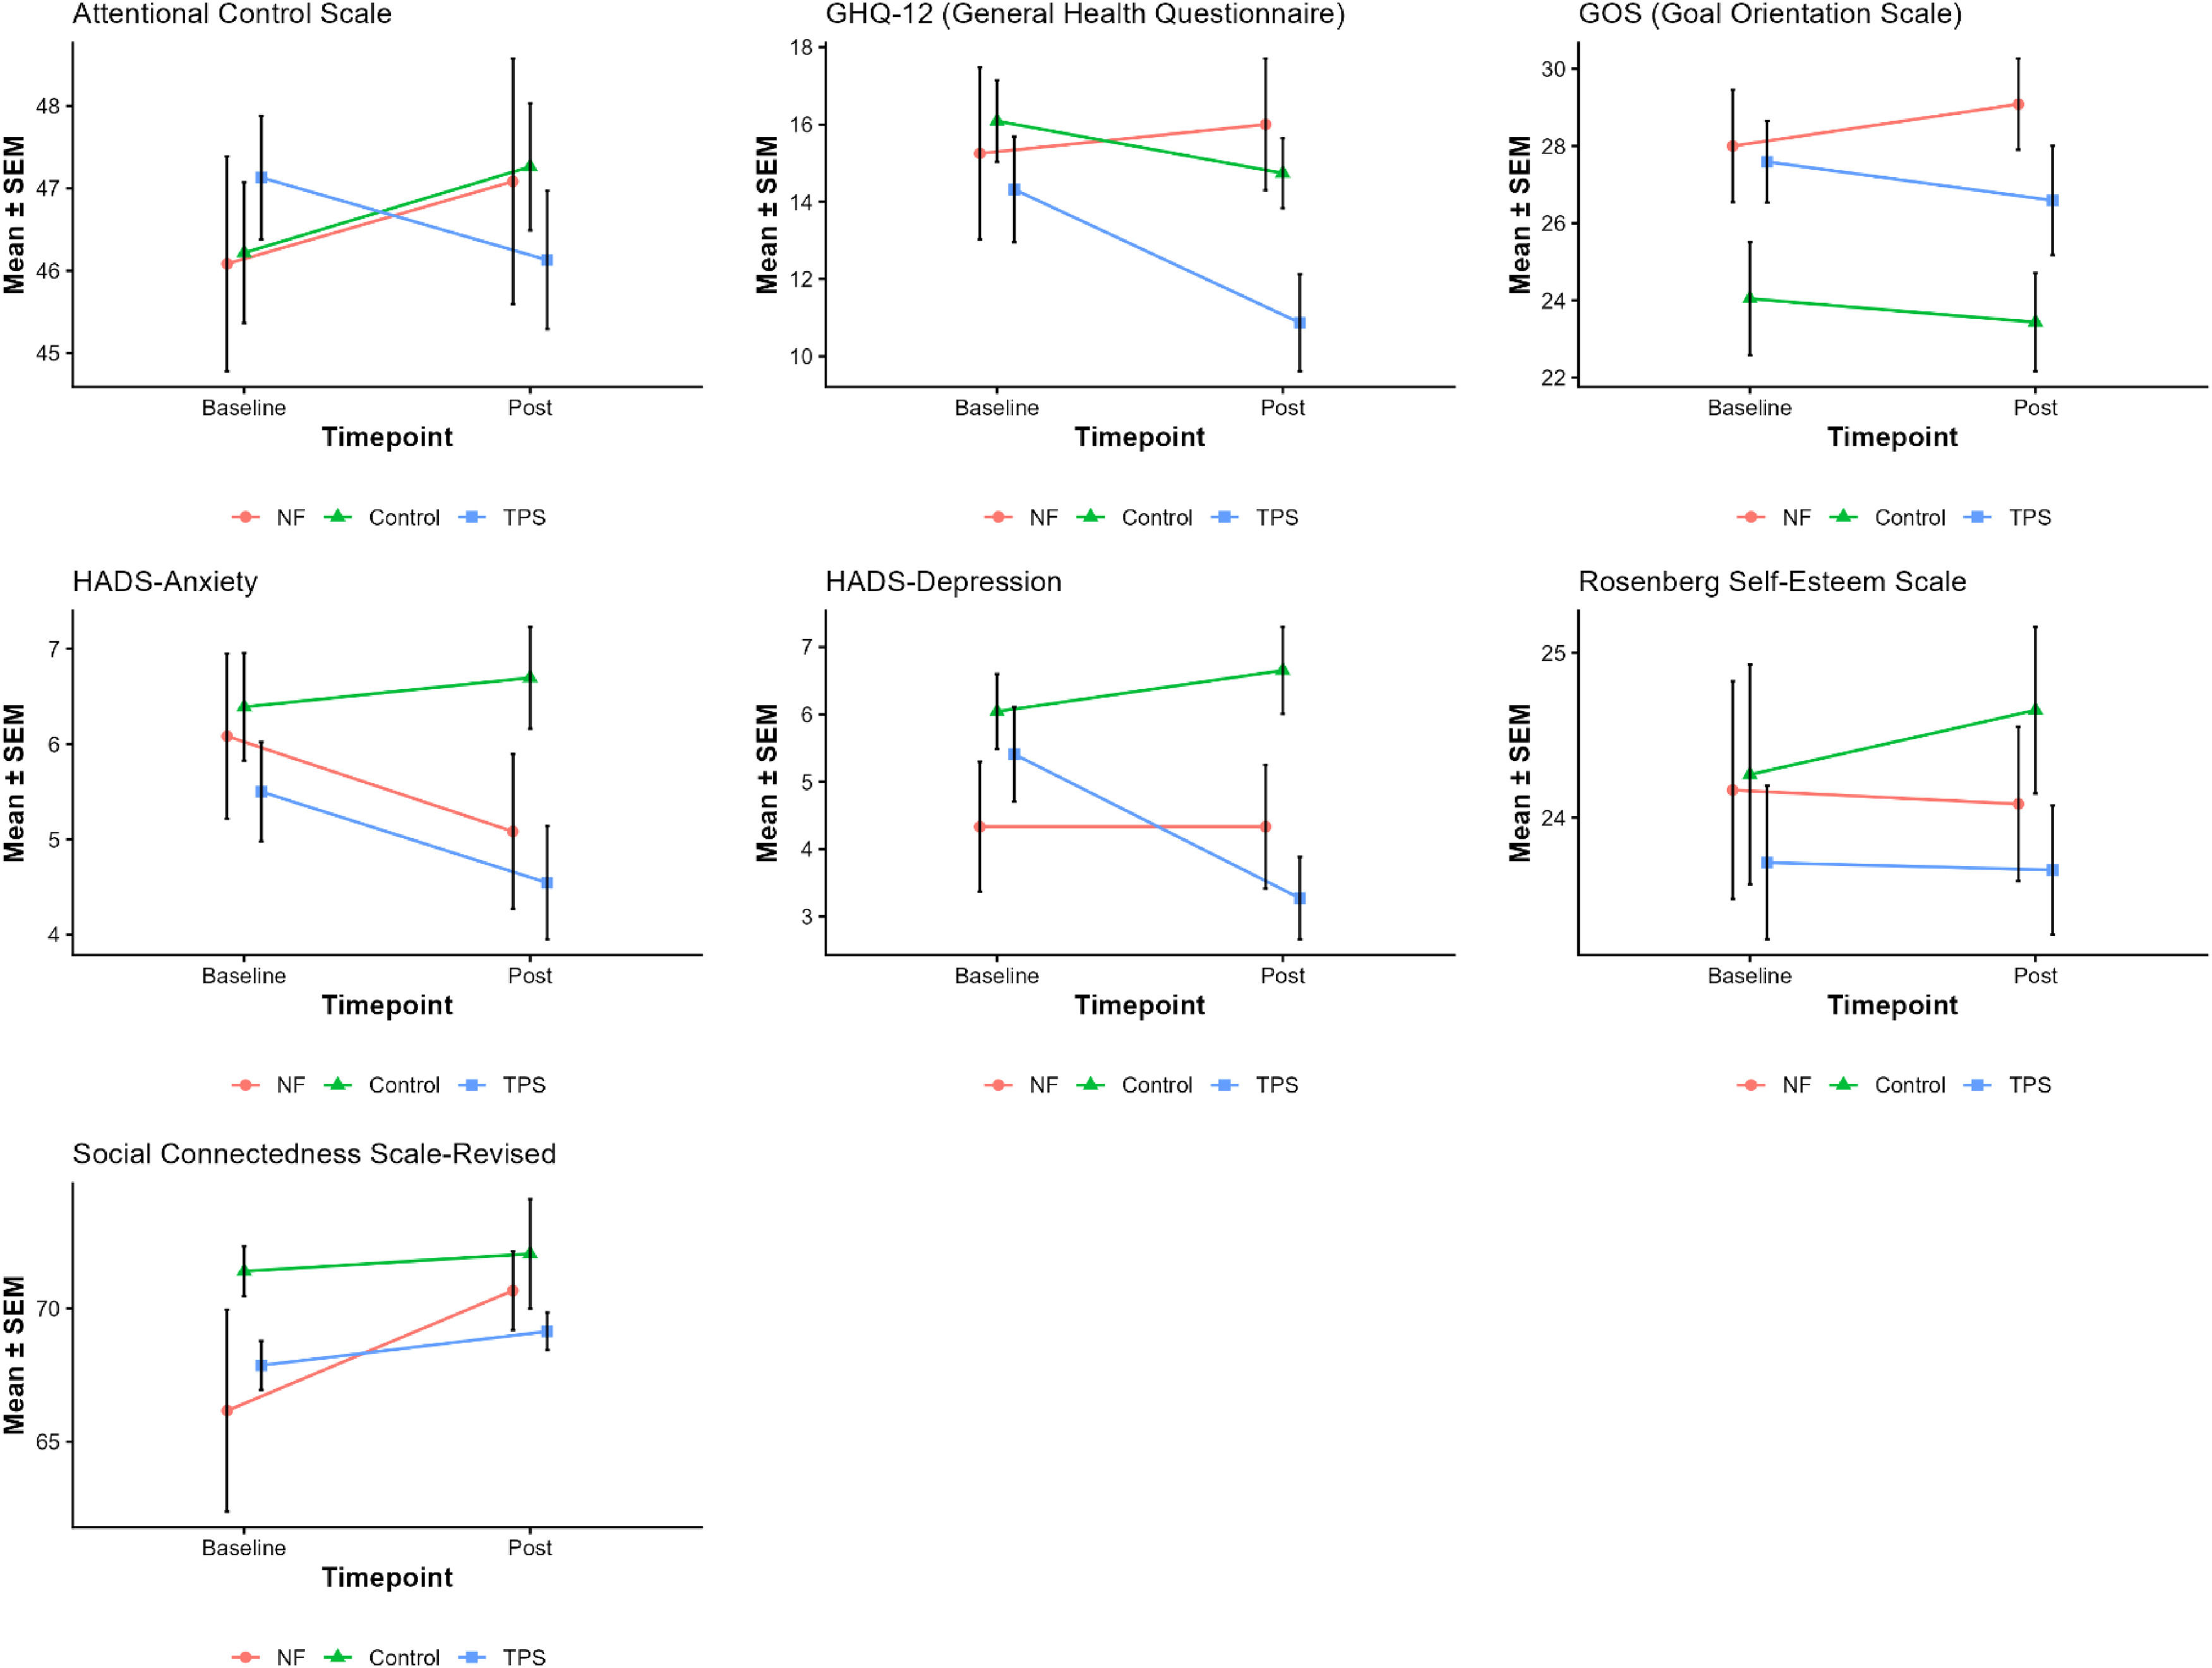
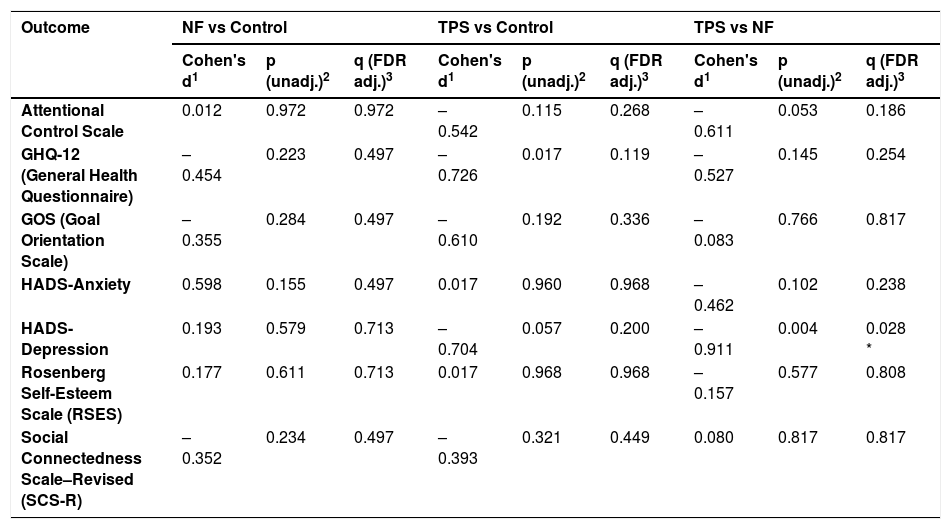
Subjective-report scales. In between-group comparisons of change from baseline to post-intervention, TPS produced a greater reduction in depressive symptoms than NF (HADS-Depression: d = −0.91; p = .004; q = 0.028), which was the only between-group contrast that remained significant after FDR correction. All other between-group differences were non-significant after adjustment (Table 3; Fig. 3).
Between-group comparison of pre- to post-intervention changes in subjective-report scales.
Note. Cohen's d was calculated on each subject's change scores (post - pre) as the difference in mean change between two groups divided by the pooled standard deviation of those change scores. A negative d indicates that the first group produced a greater reduction in score than the second group. p (unadj.) is the unadjusted p-value from the time x group interaction term of the linear mixed model. q (FDR adj.) is the Benjamini-Hochberg false-discovery-rate-adjusted q-value. * q < 0.05, ** q < 0.01, *** q < 0.001.

Pre–post changes on subjective-report outcomes. Group means (±SEM) at baseline and post-intervention for neurofeedback (NF, orange), transcranial pulsed stimulation (TPS, blue), and wait-list control (WLC, green). Panels show: Attentional Control Scale (ACS), General Health Questionnaire-12 (GHQ-12), Goal Orientation Scale (GOS), Hospital Anxiety and Depression Scale—Anxiety (HADS-A) and —Depression (HADS-D), Rosenberg Self-Esteem Scale (RSES), and Social Connectedness Scale–Revised (SCS-R). All values are raw total scores; higher ACS, GOS, RSES, and SCS-R indicate better functioning, whereas higher GHQ-12, HADS-A, and HADS-D denote greater symptom severity.
Within-group analyses (Supplementary Table S2) showed that the TPS group had significant reductions in general psychological distress (GHQ-12; d = −0.69; p = .001; q = 0.007) and depressive symptoms (HADS-Depression; d = −0.73; p = .004; q = 0.007). No other within-group changes in the TPS group met FDR-corrected significance. Neither NF nor WLC showed significant pre–post changes after FDR correction (all q ≥ 0.50).
Other cognitive tests. Within-group analyses (Supplementary Table S3) showed that the TPS group improved on the Stroop interference index, Stroop Color–Word time, Stroop Word time, and CTT Trials 1 and 2 (all q ≤ 0.029). The WLC group improved on Stroop Color time, CTT Trial 1, and N-back reaction time (q ≤ 0.012), whereas the NF group showed no FDR-significant within-group changes. In between-group comparisons, no pre–post differences reached FDR significance for Stroop, CTT, or N-back outcomes (all q ≥ 0.45; Supplementary Table S4).
Follow-up assessments. Follow-up data were available for 29 participants at 1 month (NF = 8, TPS = 11, WLC = 10), 24 at 2 months (NF = 7, TPS = 10, WLC = 7), and 24 at 3 months (NF = 7, TPS = 10, WLC = 7). In between-group contrasts of change from baseline, no Conners CPT-3 outcome differed among groups at any follow-up after FDR correction. The only significant between-group follow-up effect was observed at 1 month for HADS-Depression, with both NF and TPS showing greater reductions than WLC (q = 0.017). No durable between-group advantages were detected at follow-up (Figures S1–S3).
Within-group follow-up analyses (Supplementary Table S6) likewise showed no FDR-significant change from baseline in Conners CPT-3 outcomes in any group (all q ≥ 0.169). Several non-CPT cognitive measures improved within groups, including faster Stroop Word and Color–Word times (q = 0.001–.042), shorter N-back reaction times with modest gains in accuracy (q < 0.001 and q = 0.010–.017), and reduced CTT completion times (q = 0.001–.013), consistent with practice effects.
Exploratory qEEG findings. Exploratory within-session analysis of neurofeedback recordings showed a small but consistent decrease in Cz theta/beta ratio (TBR) across relative training time (β = −0.0027, p < .001; Figure S4). In the NF group, resting-state qEEG showed evidence of modulation of the theta–beta target from baseline to post-intervention. 9/12 NF participants (75.0%) showed reduced Cz theta–beta ratio (TBR). At the group level, Cz TBR decreased from 2.47 to 1.78 (mean change = −0.696, 95% CI = −1.293 to −0.098, p = .026), and Fz TBR decreased from 5.21 to 3.45 (mean change = −1.755, 95% CI = −3.319 to −0.191, p = .031; Figure S5). In contrast, among TPS participants with paired EEG recordings, 4/8 (50.0%) showed reduced Cz TBR, and no significant pre–post TBR change was observed (Cz: mean change = 0.093, p = .676; Fz: mean change = 0.081, p = .774). In the NF-vs-TPS mixed-effects analysis, Group × Timepoint interactions were observed for Cz TBR (beta = −0.789, p = .027) and Fz TBR (beta = −1.836, p = .032). Exploratory EEG–clinical correlations suggested that greater Fz TBR reduction was associated with greater improvement in self-reported attentional control (ACS; r = −0.606, p = .037, Figure S6).
Safety and tolerability. No serious adverse events occurred, and no participant discontinued because of an adverse event. During the intervention phase, TPS (n = 22) was associated with scalp discomfort/paresthesia in 4 participants (18.2%), headache in 2 (9.1%), and anxiety/mood change in 2 (9.1%); dizziness/vertigo and nausea were not reported. In the NF group (n = 12), fatigue/drowsiness occurred in 3 participants (25.0%) and anxiety/mood change in 1 (8.3%); no headache, scalp symptoms, dizziness/vertigo, or nausea were reported. All adverse events were mild, transient, and well tolerated without sequelae. See Tables S7–8 for the complete adverse-event counts and the checklist used.
Power sensitivity analysis. We estimated the minimum detectable effect (MDE) for each visit-specific Group × Time contrast (baseline vs visit) at α = 0.05 and 80% power using paired counts (Supplementary Table S9). At post-treatment, the most highly powered comparison (TPS vs WLC; n = 22 vs 23; df = 43) could detect an effect of approximately d = 0.86, whereas the other pre–post comparisons required d ≈ 1.03. At follow-up, MDEs increased due to attrition: d = 1.29–1.42 at 1 month and d = 1.48–1.63 at 2–3 months. Thus, the study was powered to detect large between-group differences in change at post-treatment, whereas only very large effects were detectable at later follow-ups.
DiscussionIn this randomized controlled trial comparing two non-pharmacological interventions with a wait-list control (WLC), TPS produced significantly greater post-treatment improvements in sustained attention -related cognitive measures in performance among young adults with sub-clinical attention difficulties than either NF or WLC. TPS also yielded greater reductions in depressive symptoms than the other two groups. However, the durability of these effects beyond the immediate post-treatment period remains uncertain. TBR neurofeedback did not confer significant benefits in attention, cognitive performance, or self-reported behavioural health measures compared with the WLC group.
The primary cognitive benefit of TPS was reflected in reduced RT variability on the Conners CPT, with significant improvements observed both within and between groups post-intervention. RT variability reflects the consistency of an individual’s performance and serves as an index of sustained attention stability and susceptibility to momentary lapses (Weissman et al., 2006). Elevated RT variability indicates trial-to-trial fluctuations in attention, often due to mind-wandering or temporary ‘off-task’ states (Esterman et al., 2013). It is linked to failures of top-down executive control in the frontal cortex (Stuss et al., 2003) as well as arousal fluctuations mediated by the locus coeruleus–norepinephrine system (Sara & Bouret, 2012). Clinically, RT variability is among the most robust behavioral markers of ADHD and other disorders characterized by unstable attention (Kofler et al., 2013).
For other Conners CPT outcomes, TPS outperformed NF on COM, HRT, OMI, PER, VAR, d’, HRT-BC, and HRT-ISI, and outperformed WLC on COM, PER, d’, HRT-ISI, and HRT-SD, indicating a broad-spectrum benefit on attention-related cognitive performance. In contrast, both the NF and WLC groups showed significant declines in performance at the second CPT assessment. This pattern is consistent with sustained-attention tasks in which practice effects are minimal and performance often deteriorates at the second measurement (Lee et al., 2016; Zabel et al., 2009), likely due to fatigue, reduced motivation, or loss of task engagement. Notably, the TPS group not only avoided this decline but demonstrated significant gains on HRT-SD and commission errors (unadjusted p = .038), suggesting that TPS may enhance both response speed stability and inhibitory control under sustained cognitive demand.
TPS was the only intervention to show within-group improvements that survived false-discovery-rate correction on self-report measures—reducing general psychological distress (GHQ-12) and depressive symptoms (HADS-Depression). Between-group effects were modest: versus waitlist control, TPS yielded a greater reduction in GHQ-12 and it produced a large, advantage over neurofeedback for HADS-DepressionThese results align with evidence that non-invasive neuromodulation (e.g., TMS(Kan et al., 2023)) can ameliorate neuropsychiatric symptoms and with open-label TPS reports in depressive and non-depressive populations (Cheung et al., 2023; Shinzato et al., 2024), although recent double-blind pilots have not shown superiority over sham (Qin et al., 2025).
Our follow-up analyses were constrained by substantial attrition, leaving the study underpowered for between-group contrasts; accordingly, post-treatment pre–post comparisons constitute the primary results, and longitudinal findings should be interpreted cautiously. At 1 month, both TPS and NF showed greater reductions in depressive symptoms than the waitlist control, but these differences attenuated by 2–3 months. This pattern may reflect non-specific factors (i.e., placebo effect) or natural symptom fluctuation. Overall, the durability of TPS-related improvements in attention and mood beyond the immediate post-treatment window remains uncertain. Future trials should be adequately powered for follow-up endpoints, minimize practice effects (e.g. alternate forms), include blinded assessments, prespecify maintenance/booster schedules, and target high retention to permit definitive inferences about longer-term efficacy.
Observed gains in attention-related cognition following transcranial pulse stimulation (TPS) are consistent with emerging evidence that TPS can enhance neuropsychological performance and large-scale network function in humans (Beisteiner et al., 2020; Chen et al., 2024; Matt et al., 2022). TPS delivers brief, low-intensity ultrasonic pulses to the targeted cortex, and mechanistic studies indicate that ultrasound engages mechanosensitive ion channels and transiently increases neuronal excitability (Sorum et al., 2021; Zhu et al., 2023). Preclinical and human work further shows that patterned ultrasound can induce durable, LTP-like synaptic plasticity and entrainment-based plasticity (Kim et al., 2024; Niu et al., 2022), while ultrasound exposure can upregulate neurotrophic signalling, including brain-derived neurotrophic factor pathways (Liu et al., 2017). Our findings indicate that TPS improves objective measures of sustained attention, extending prior evidence from double-blind randomized controlled trials demonstrating TPS-related reductions in proxy-rated ADHD symptoms (Cheung et al., 2024).
In this randomized trial, TBR neurofeedback did not improve attention-related cognitive performance or self-reported attentional control in young adults with subclinical sustained-attention difficulties. However, we did observe significant improvement in the trained EEG ratio, and these neurophysiological changes were associated with self-reported attention measures. This dissociation may indicate that neurofeedback primarily facilitated acquisition of self-regulation over the targeted EEG signal rather than transfer to objective attentional performance. It is also possible that successfully learning to modulate the feedback signal enhanced participants’ sense of control or self-efficacy in engaging with the BCI system, even in the absence of broader cognitive gains (Kadosh & Staunton, 2019). This pattern is consistent with findings from large, rigorously blinded, sham-controlled randomised trials (Arnold et al., 2021; Schönenberg et al., 2017) and recent meta-analyses in ADHD (Westwood et al., 2025), which suggest that the benefits of EEG neurofeedback are predominantly non-specific and not superior to sham.
Limitations: This study has several limitations. First, the sample size was modest and was powered primarily to detect large effects; accordingly, small-to-moderate effects may have gone undetected. Second, the study used an open-label design without sham TPS or sham neurofeedback conditions. Although an active comparator was included, expectancy effects and other non-specific treatment effects cannot be excluded. Third, follow-up was relatively short (up to 2–3 months) and was further affected by attrition, which reduced power for longitudinal comparisons and limited conclusions regarding the durability of treatment effects. Fourth, the single-centre design may limit generalizability, and residual practice effects on repeated cognitive tasks cannot be ruled out. In addition, affective symptom outcomes were secondary rather than primary endpoints and should therefore be interpreted cautiously. Finally, although participants were asked not to initiate new attention-related pharmacological or behavioural treatments during the study, session-level state variables such as sleep duration, sleep quality, and caffeine intake were not systematically recorded; future trials should monitor these factors because they may influence attention-task performance and neurofeedback engagement.
ConclusionSustained-attention deficits pose significant challenges in clinical and everyday contexts, underscoring the need for effective non-pharmacological interventions. This study provides evidence that transcranial pulse stimulation (TPS) can meaningfully improve sustained attention and attention-related cognitive abilities (such as RT variability) in young adults with attention difficulties, with effects that outlast those of a standard neurofeedback training regimen. As a novel neuromodulation technique, TPS showed superior short-term post-intervention effects on attention-related performance compared with neurofeedback and wait-list control. With further validation in adequately powered, blinded studies, TPS may become a useful addition to existing cognitive and neurobehavioral interventions across both healthy and clinical populations.
FundingThis project was supported by The University of Hong Kong May Endowed Professorship in Neuropsychology.
The authors declare that they have no known competing financial interests or personal relationships that could have appeared to influence the work reported in this paper.


YW and HTAL contributed equally to this work.
This research is approved by THE UNIVERSITY OF HONG KONG Human Research Ethics Committee (EA220456).
Trial registration ClinicalTrials.gov: NCT05834920.
The first 50 randomized participants were allocated with equal probability to TPS, NF, or WLC using a computer-generated 1:1:1 allocation sequence. In the middle of the study, the trained NF coach was no longer available to deliver the intervention to additional newly eligible participants; therefore, the NF arm was closed to further randomization. The remaining 17 participants who met eligibility criteria and proceeded to randomization were allocated with equal probability to TPS or WLC using a computer-generated 1:1 allocation sequence. This staged procedure yielded expected allocations of 25.17 participants to TPS, 16.67 to NF, and 25.17 to WLC, corresponding to an effective expected allocation ratio of 1.51:1.00:1.51, rounded to 1.5:1:1.5. The observed randomized group sizes were TPS = 24, NF = 16, and WLC = 27.

articles
- Download PDF
- Bibliography
- Additional material
