




Clostridioides difficile infection (CDI) is the leading cause of healthcare-associated infectious diarrhea and is associated with significant morbidity and mortality, primarily due to its high recurrence rate. For this reason, the Catalan Society of Gastroenterology commissioned the development of a position paper aimed at providing practical recommendations, grounded in scientific evidence and expert consensus, on the diagnosis and management of CDI.
MethodsThis position paper was developed by specialists in Gastroenterology, Infectious Diseases and Microbiology. It was based on a non-systematic review of the scientific evidence. Recommendations were formulated through expert consensus.
ResultsThe document presents a structured approach to the diagnosis and treatment of CDI, emphasizing individualized management and strategies to reduce recurrence rates. Key components include the role of fecal microbiota transplantation and a therapeutic algorithm informed by disease severity and by whether the episode is initial or recurrent.
ConclusionsThis position paper aims to serve as a practical, evidence-based guide for healthcare professionals involved in the clinical management of CDI, promoting the implementation of optimal therapeutic strategies and addressing the main challenges associated with this infection.
La infección por Clostridioides difficile (ICD) constituye la principal causa de diarrea infecciosa relacionada con la asistencia sanitaria y se asocia con una morbimortalidad significativa, principalmente debido a su elevada tasa de recurrencia. Por este motivo, la Societat Catalana de Digestologia encargó la elaboración de un documento de posicionamiento con el objetivo de proporcionar recomendaciones prácticas, basadas en la evidencia científica y consenso de expertos, sobre el diagnóstico y tratamiento de la ICD.
MétodosEste documento de posicionamiento fue elaborado por especialistas en Aparato Digestivo, Enfermedades Infecciosas y Microbiología. Se llevó a cabo a partir de una revisión no sistemática de la evidencia científica. Las recomendaciones fueron formuladas por consenso entre expertos.
ResultadosEl documento ofrece un enfoque estructurado para el diagnóstico y el tratamiento de la ICD, con énfasis en el tratamiento individualizado y en las estrategias para reducir la tasa de recurrencia de la infección. Se destacan aspectos clave, como el trasplante de microbiota fecal y un algoritmo terapéutico basado en la gravedad y en si se trata de un episodio inicial o de una infección recurrente.
ConclusionesEste documento de posicionamiento tiene como objetivo servir como una guía práctica y basada en la evidencia para los profesionales de la salud involucrados en el manejo clínico de la ICD, favoreciendo la implementación de estrategias terapéuticas óptimas y abordando los principales retos asociados a esta infección.
Clostridioides difficile infection (CDI) is the leading cause of healthcare-associated infectious diarrhoea, as well as one of the main aetiologies of community-acquired infectious diarrhoea, especially in patients with a history of antibiotic therapy. CDI is associated with considerable morbidity and mortality, mainly attributable to its high recurrence rate.
In most cases, CDI manifests as mild to moderate diarrhoea, accompanied by general malaise, abdominal pain, fever and leucocytosis. However, it can sometimes acquire severe characteristics, including fulminant symptoms that require an early, effective and multidisciplinary diagnosis and therapeutic approach.
The main risk factors for developing CDI include antibiotic use, advanced age and prolonged hospitalisation. Management of this infection is aided by early diagnosis, based on a high degree of clinical suspicion, and treatment adjusted to clinical severity and risk of recurrence, together with the implementation of preventive measures aimed at avoiding the spread of the microorganism.
The increasing incidence of CDI,1 along with the introduction of new therapeutic strategies such as faecal microbiota transplantation (FMT), has contributed to its management becoming increasingly complex.
This position paper was promoted by the Societat Catalana de Digestologia [Catalan Society of Gastroenterology] and approved by its scientific committee. The main aim of the paper is to unify diagnostic and therapeutic criteria in a practical and intelligible way, in order to provide healthcare professionals with a useful tool for addressing the challenges posed by CDI.
MethodsThis position paper was created by a multidisciplinary group of experts composed of specialists in Gastroenterology, Infectious Diseases and Microbiology, with expertise in CDI, inflammatory bowel disease (IBD) and FMT.
We conducted a narrative review of the scientific evidence by searching the MEDLINE electronic database (accessed via PubMed) and reviewing relevant international clinical guidelines and consensus documents in the field of CDI. The search was limited to the most recent literature and publications in English and Spanish. The evidence was updated and adapted to our healthcare context.
Virtual meetings were held between group members for joint discussion of content, identification of possible discrepancies and harmonisation of the text. Following these meetings, successive rounds of review and editing of the manuscript were carried out electronically until a consensus text was reached. The recommendations were formulated through expert consensus and approved by all members, without applying systematic methodologies, which is a limitation.
DefinitionsClostridioides difficile infection: compatible clinical symptoms (diarrhoea with ≥3 Bristol 6–7 stools in 24 h, with or without megacolon and/or paralytic ileus), accompanied by microbiological demonstration of toxigenic Clostridioides difficile (CD); or detection of pseudomembranous colitis during endoscopy, colectomy or autopsy, along with a positive test result for toxigenic CD.
Severe Clostridioides difficile infection: presence of any of the following criteria: fever (>38.5 °C), significant leucocytosis (>15 × 109/l), increase in serum creatinine (greater than 50% from baseline) or radiological findings consistent with severe colitis.
Severe-complicated (or fulminant) Clostridioides difficile infection: occurrence of any of the following signs attributable to CDI: hypotension, septic shock, elevated serum lactate, paralytic ileus, toxic megacolon or intestinal perforation.
Therapeutic response: defined as resolution of diarrhoea sustained for at least 48 h after completion of standard treatment (vancomycin or fidaxomicin), without the appearance of new signs indicative of severe disease, and accompanied by an improvement in clinical, laboratory and radiological parameters.
Refractory Clostridioides difficile infection: no response to standard treatment (vancomycin or fidaxomicin) within 3–5 days of starting treatment. Refractory CDI is an uncommon clinical scenario and resistance to standard treatment is exceptional in Europe. Therefore, in these cases it is always recommended to reassess the clinical case and consider alternative or additional diagnoses.
Recurrent Clostridioides difficile infection: occurrence of a new episode of CDI within eight weeks of a previous episode in which symptoms had resolved after completion of treatment. However, it should be noted that the follow-up period used to assess recurrence varies from four to 12 weeks depending on the study.
Asymptomatic Clostridioides difficile carrier state: positive CD test result without associated clinical symptoms.
Microbiological diagnosis of Clostridioides difficile infectionCD is a strict anaerobic, spore-forming, toxin A- and B-producing bacterium. It is mainly found in the gastrointestinal tract of some animals and humans, as well as in the natural and hospital environment. The route of transmission of CDI is faecal-oral. In the healthcare setting, environmental contamination and spread through the contaminated hands of healthcare professionals are very relevant factors. Only toxin-producing strains are responsible for causing the disease.
Diagnostic algorithms for CDI are based on the sequential combination of different tests aimed at detecting toxigenic strains. Fig. 1 shows the proposed sequential algorithm, structured in three steps.2 Detection should only be performed on unformed stool samples.

The screening test is based on the detection of the enzyme glutamate dehydrogenase (GDH), which is present in all CD strains. It is a rapid and highly sensitive test. However, GDH detection lacks specificity, so a positive GDH test result is not, by itself, diagnostic of CDI. In contrast, a negative result rules out infection.
If detection of GDH is positive, it is necessary to determine the presence of toxin and/or the gene encoding the toxin. The proposed diagnostic algorithm uses an enzyme immunoassay (EIA) for the detection of toxin A and/or B. These methods have a sensitivity of 40%–60% and a specificity of over 90%. Positive toxin detection confirms the presence of toxigenic CD.
In the event of a negative result for toxins by EIA, molecular techniques will need to be used to detect the gene coding for toxins A/B. These techniques, based on polymerase chain reaction (PCR), have a sensitivity and specificity of over 90%. A positive result confirms the presence of toxigenic CD.
Therapeutic management of Clostridioides difficile infectionIn CDI, it is essential to ensure adequate fluid and electrolyte replacement and to avoid the administration of drugs that slow intestinal motility (anti-diarrhoeal and/or spasmolytic drugs). It is also recommended that the indication for proton pump inhibitor (PPI) therapy be reviewed and discontinued if not justified.
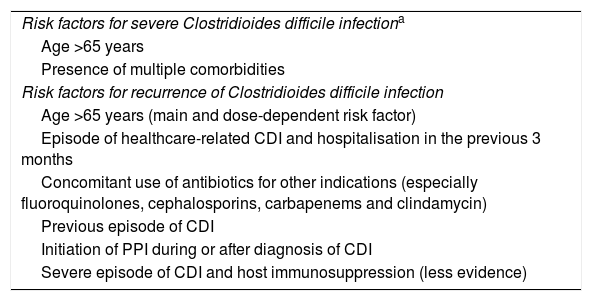
In a case of CDI, the treatment strategy to be followed varies according to the severity of the episode, the individual patient's risk of recurrence and whether it is a first episode or a recurrent infection. Table 1 shows the risk factors associated with severe infection and recurrence of infection.
Risk factors in CDI.
| Risk factors for severe Clostridioides difficile infectiona |
| Age >65 years |
| Presence of multiple comorbidities |
| Risk factors for recurrence of Clostridioides difficile infection |
| Age >65 years (main and dose-dependent risk factor) |
| Episode of healthcare-related CDI and hospitalisation in the previous 3 months |
| Concomitant use of antibiotics for other indications (especially fluoroquinolones, cephalosporins, carbapenems and clindamycin) |
| Previous episode of CDI |
| Initiation of PPI during or after diagnosis of CDI |
| Severe episode of CDI and host immunosuppression (less evidence) |
CDI: Clostridioides difficile infection; PPI: proton pump inhibitors.
Source: Van Prehn et al.10
Standard antibiotic therapy of CDI is based on the administration of fidaxomicin or vancomycin, as well as withholding or minimising other unnecessary antibiotics. Metronidazole therapy is not considered first-line treatment and is relegated to cases where neither vancomycin nor fidaxomicin is available, as it has a lower efficacy and a higher recurrence rate than standard treatment.3,4
Both fidaxomicin and vancomycin have similar cure rates and no differences have been found in the incidence of adverse events.5–7
Fidaxomicin has less impact on the gut microbiota8,9 and has a lower recurrence rate compared to vancomycin, with an absolute risk of recurrence approximately 10%–14% lower. That, however, is with the exception of CD infection caused by the BI/NAP1/027 strain, where recurrence rates are similar with both standard antibiotic therapies.5,6
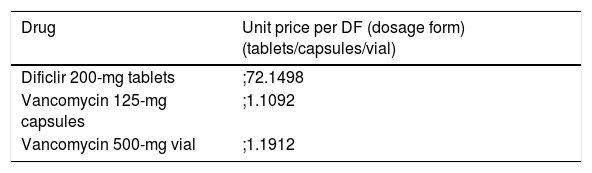
Fidaxomicin is the first-line treatment recommended in the main clinical practice guidelines. Nevertheless, as it costs more than vancomycin (see Table 2), prescribing of fidaxomicin may be less widespread.10–12 However, its use is considered cost-effective due to the lower recurrence rate and the consequent reduction in the readmission rate.13–16
In CDI, vancomycin is effective only when administered orally or rectally. Vancomycin administered intravenously is not effective because it does not reach adequate therapeutic concentrations in the intestinal lumen. Fidaxomicin is administered exclusively by the oral route.
Tigecycline is another therapeutic option. It is an antibiotic with in vitro activity against CD. Its use in the treatment of CDI has not been evaluated in clinical trials and it has only been studied in observational cohorts. However, its use is recommended in patients who have a poor outcome despite adequate standard treatment, as well as in cases of severe or complicated CDI.10
Bezlotoxumab is a monoclonal antibody that targets CD toxin B, indicated for preventing recurrence of CDI.17 During the last quarter of 2024, the marketing of bezlotoxumab (Zinplava®) was suspended due to corporate decisions and it is not therefore included in this treatment algorithm. Similarly, we do not address other recently developed faecal microbiota-based biologicals (Rebyota®, Vowst®), which have shown promising results in clinical trials but are not yet commercially available in Europe.
Disturbance of the gut microbiota or dysbiosis plays a central role in the pathogenesis of CDI. FMT involves the transfer of a solution obtained from the faeces of healthy donors, with the aim of restoring or re-establishing the impaired gut microbiota. FMT can be administered orally via freeze-dried microbiota capsules, via colonoscopy or via enema.
In recurrent CDI, FMT has been shown to be a cost-effective and effective treatment in several clinical trials18–23 and meta-analyses,24–26 with an overall efficacy rate of 87%–89%. This has led to the establishment of international clinical guidelines standardising its use as a viable therapeutic modality in recurrent CDI.10,27,28
The safety profile of FMT is good, even in patients with mild to moderate immunosuppression.27,29 The most commonly reported adverse events are diarrhoea, abdominal discomfort, flatulence and constipation, which in most cases are mild and self-limiting.29 In a systematic review involving more than 4000 patients receiving FMT, an adverse event rate of 19% was detected, 1.4% of which were serious.30
It is recommended that FMT be performed in accredited centres and always using samples from Microbiota Banks that follow standardised programmes for the whole process (donor selection, processing and traceability). Catalonia has a Microbiota Bank with two sites (Hospital Universitario de Bellvitge and Hospital Clínic de Barcelona).
Prior to the administration of FMT, a personalised assessment by an expert multidisciplinary team is necessary to ensure the appropriate indication, select the route of administration and decide which FMT product is suitable in each case, adjusted according to the recipient's serologies and degree of immunosuppression.31,32
Surgical treatment in patients with CDI is reserved for severe, fulminant and/or complicated cases (intestinal perforation, megacolon, refractory septic shock), and always after a multidisciplinary and personalised assessment. Due to the severity of the situation, it is very difficult to establish an evidence-based recommendation regarding the optimal timing of surgery in severe complicated CDI. In the case of a patient who makes poor clinical progress, assessment by the surgical specialist should be carried out at an early stage. In surgically indicated cases, subtotal colectomy with terminal ileostomy or, alternatively, ileostomy with intestinal diversion and colonic lavage followed by antegrade lavage with vancomycin (diverting loop ileostomy) is recommended. However, 30-day mortality in patients who have required total or partial colectomy for CDI is high (>30%).
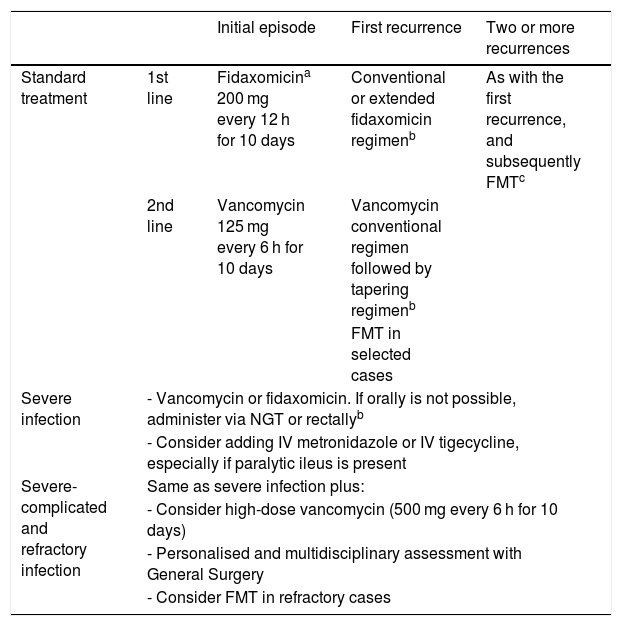
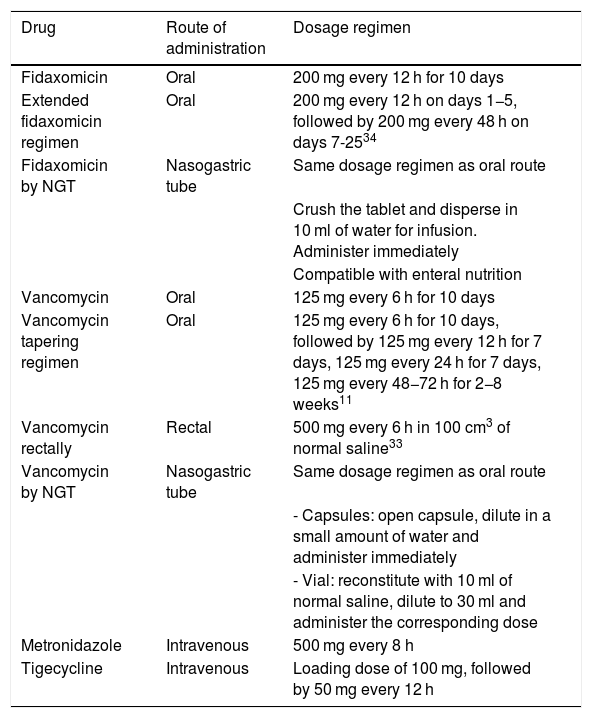
Table 3 shows the recommended treatment algorithm for CDI. It should be noted that even if a clinical response is achieved with CDI treatment, it can take weeks for stool consistency and frequency to return to normal.33Table 4 shows the recommended dosage of the different antibiotics used in CDI according to the route of administration.
Treatment algorithm in CDI.
| Initial episode | First recurrence | Two or more recurrences | ||
|---|---|---|---|---|
| Standard treatment | 1st line | Fidaxomicina 200 mg every 12 h for 10 days | Conventional or extended fidaxomicin regimenb | As with the first recurrence, and subsequently FMTc |
| 2nd line | Vancomycin 125 mg every 6 h for 10 days | Vancomycin conventional regimen followed by tapering regimenb | ||
| FMT in selected cases | ||||
| Severe infection | - Vancomycin or fidaxomicin. If orally is not possible, administer via NGT or rectallyb | |||
| - Consider adding IV metronidazole or IV tigecycline, especially if paralytic ileus is present | ||||
| Severe-complicated and refractory infection | Same as severe infection plus: | |||
| - Consider high-dose vancomycin (500 mg every 6 h for 10 days) | ||||
| - Personalised and multidisciplinary assessment with General Surgery | ||||
| - Consider FMT in refractory cases | ||||
CDI: Clostridioides difficile infection; FMT: faecal microbiota transplantation; NGT: nasogastric tube; PPI: proton pump inhibitors.
Treatment of choice, especially if there are risk factors for CDI recurrence (age >65 years, healthcare-related CDI episode, hospitalisation within the previous 3 months, previous CDI episode, concomitant antibiotic use, immunosuppression, severe CDI episode and initiation of PPI during or after CDI diagnosis).
Table 4 specifies the different antibiotic dosage regimens according to the route of administration.
Route of administration and dosage regimen of antibiotics in CDI.
| Drug | Route of administration | Dosage regimen |
|---|---|---|
| Fidaxomicin | Oral | 200 mg every 12 h for 10 days |
| Extended fidaxomicin regimen | Oral | 200 mg every 12 h on days 1−5, followed by 200 mg every 48 h on days 7-2534 |
| Fidaxomicin by NGT | Nasogastric tube | Same dosage regimen as oral route |
| Crush the tablet and disperse in 10 ml of water for infusion. Administer immediately | ||
| Compatible with enteral nutrition | ||
| Vancomycin | Oral | 125 mg every 6 h for 10 days |
| Vancomycin tapering regimen | Oral | 125 mg every 6 h for 10 days, followed by 125 mg every 12 h for 7 days, 125 mg every 24 h for 7 days, 125 mg every 48−72 h for 2−8 weeks11 |
| Vancomycin rectally | Rectal | 500 mg every 6 h in 100 cm3 of normal saline33 |
| Vancomycin by NGT | Nasogastric tube | Same dosage regimen as oral route |
| - Capsules: open capsule, dilute in a small amount of water and administer immediately | ||
| - Vial: reconstitute with 10 ml of normal saline, dilute to 30 ml and administer the corresponding dose | ||
| Metronidazole | Intravenous | 500 mg every 8 h |
| Tigecycline | Intravenous | Loading dose of 100 mg, followed by 50 mg every 12 h |
Metronidazole and tigecycline are indicated in cases of severe or complicated CDI, and the duration of treatment in both cases should be adjusted according to clinical response and medical judgement, following a multidisciplinary and personalised assessment.
There is good evidence from randomised controlled studies comparing fidaxomicin with vancomycin for the treatment of CDI.5,6 According to this evidence:
- •
Fidaxomicin is considered the first-line treatment (200 mg every 12 h for 10 days) in patients with CDI, especially in those at high risk of recurrence of infection (see risk factors for recurrence in Table 1).10,11 Moreover, as mentioned above, it has less impact on the gut microbiota.8,9
- •
In a first episode of uncomplicated CDI without risk factors for recurrence, vancomycin (125 mg every 6 h for 10 days) is a therapeutic alternative.10,11
- •
Both fidaxomicin and vancomycin have similar cure rates and no significant differences in the incidence of adverse events.5–7
- •
Metronidazole administration is reserved only for cases where none of the standard antibiotics is available.10,11
In recurrent CDI there is a lack of clinical trials, and the available data on the evidence for antibiotic therapy are based on sub-analyses of other trials. The optimal treatment when fidaxomicin has been administered in the initial episode (new standard-dose fidaxomicin regimen versus extended fidaxomicin versus vancomycin tapering regimen) remains to be clarified.
- •
In general, it is recommended to prioritise fidaxomicin, especially in cases where vancomycin has been administered previously.10,11
- •
There are no clinical trials comparing fidaxomicin at the conventional dosage (200 mg every 12 h for 10 days) versus extended therapy (200 mg every 12 h on days 1−5, followed by 200 mg every 48 h on days 7–25).34
- •
If vancomycin is administered, the standard dose followed by a tapering regimen is recommended (the dosage is shown in Table 4), as sub-analyses showed less recurrence with the tapering regimen than with the standard dose.35
- •
After appropriate antibiotic therapy, the treatment of choice in recurrent CDI is FMT (high level of evidence recommendation). Leading clinical practice guidelines recommend FMT from the second recurrence of infection (third episode).10,27,28
- •
Recent randomised studies and clinical guidelines27,29,36 also consider FMT as a therapeutic tool in the first recurrence of infection in selected cases (high risk of recurrence and/or morbidity associated with recurrent CDI).
In uncomplicated CDI that does not respond to medical treatment (uncomplicated refractory CDI), FMT can be considered as rescue therapy in association with standard antibiotic therapy.27,29 However, refractory infection is not a common clinical scenario and resistance to standard treatment (vancomycin or fidaxomicin) is very rare. Therefore, in these cases it is recommended to reassess the case and consider alternative or additional diagnoses.
Therapeutic management of severe and severe-complicated (fulminant) Clostridioides difficile infectionIn severe CDI and especially in severe-complicated CDI, a multidisciplinary assessment including specialists in General Surgery is always recommended for a personalised and early assessment. In severe complicated CDI, prior to microbiological confirmation, empirical antibiotic therapy can be initiated if there is a high degree of clinical suspicion.33
- •
In severe CDI, both vancomycin and fidaxomicin can be administered at standard doses. There are no data to support the superiority of one of these drugs over the other in this clinical scenario.10 In the subgroup of patients with severe CDI, both treatments showed similar results in terms of cure and recurrence rates in phase 3 clinical trials.5,6
- •
If the oral route is not possible, standard antibiotic therapy should be administered via nasogastric tube or rectally (see Table 4).
- •
In severe complicated CDI, there is no standardised optimal treatment, as these patients are often excluded from prospective studies. They were also not included in the Phase 3 clinical trials that demonstrated equivalence of efficacy between fidaxomicin and vancomycin.
- •
There is insufficient evidence to support the use of high doses of vancomycin (500 mg every 6 h),10,37 but as that regimen is recommended in some clinical guidelines,11,12 it has been included in this treatment algorithm. It is important to mention that the use of high doses of oral vancomycin in severe-fulminant forms can be associated with side effects, particularly in patients with renal failure or when administered by enema, as vancomycin can be absorbed and pass into the bloodstream.38
- •
In severe CDI, metronidazole can be added; it should be administered intravenously (500 mg every 8 h) and always in combination with standard treatment (oral fidaxomicin or vancomycin).10,11
- •
The addition of intravenous tigecycline should be considered in patients who make poor progress despite adequate standard antibiotic therapy and in cases of severe-complicated CDI, with a loading dose of 100 mg, followed by 50 mg every 12 h.10
- •
FMT is a promising rescue therapy in severe-fulminant CDI that does not respond to medical treatment, especially in individuals who are not candidates for surgery.10,27,29,39–42 The possibility of FMT should be assessed after complications requiring surgery (toxic megacolon, perforation, refractory septic shock, etc.) have been ruled out. Despite the severity of the clinical condition, FMT is considered a safe and effective treatment. It has been reported that in this scenario intensive management (multiple FMT) is necessary, always in combination with standard antibiotic therapy. The level of evidence available for FMT in severe-fulminant CDI is lower than in recurrent CDI. However, given the high mortality rate associated with surgical intervention and the fact that many patients are not candidates for surgery, FMT is a rescue treatment to be considered.
It should be noted that, in all cases, it is essential to ensure appropriate standard antibiotic therapy prior to FMT. FMT is considered the treatment of choice in recurrent CDI (≥2 recurrences, 3rd episode) according to the leading clinical practice guidelines.10,27,28 It would also be indicated in the following clinical scenarios:
- 1
Severe or fulminant CDI: FMT is considered a rescue treatment option in cases of lack of response to standard antibiotic therapy, particularly in patients who are not candidates for surgery due to age and/or comorbidities,10,27,29 always after ruling out complications such as toxic megacolon, perforation and refractory septic shock.
- 2
Uncomplicated and refractory CDI: rescue treatment option, always after ruling out alternative diagnoses that explain the lack of response to standard antibiotic therapy.27,29
- 3
Recurrent CDI (1st recurrence, 2nd episode): FMT may be considered in selected cases, but always after multidisciplinary assessment.27,29
Patients with inflammatory bowel disease (IBD) are at high risk of CDI,43,44 which can complicate diagnosis and aggravate the course of the disease.45–51 Traditional risk factors for CDI, such as antibiotic exposure, may not be as relevant, as the underlying intestinal dysbiosis independently predisposes to infection. Although IBD is a risk factor for CDI, the exclusion of these patients in clinical trials limits the information available on diagnosis and management in this scenario.52 Therefore, an integrated therapeutic approach that considers the simultaneous treatment of CDI and IBD is essential.
The diagnosis of CDI in patients with IBD is particularly complex, as CD colonisation is more common in this population and many symptoms are identical to those of IBD activity. Therefore, if new symptoms appear or gastrointestinal symptoms worsen, CDI should be suspected and appropriate diagnostic tests performed. Knowing the distribution and previous activity of the IBD is key to correctly interpreting the role of CD in this context. Changes in the location, extent or presentation of IBD may suggest CD involvement.
In terms of treatment, fidaxomicin is the first choice due to its more selective spectrum, bactericidal activity and lower recurrence rate.5 Although patients with IBD were excluded from clinical trials, observational and pharmacokinetic data suggest that it is safe and effective in this population.53 Vancomycin is a viable alternative, especially when fidaxomicin is not available.54 At the same time, continued IBD treatment, including immunosuppressants, is necessary to prevent persistent inflammation from impairing dysbiosis and negatively affecting the response to the CDI treatment.
FMT is a safe treatment option in patients with IBD and CDI.12,29,44,55–57 However, it has been reported in two studies that some patients may experience a flare-up of IBD after FMT.55,58 In addition, dysbiosis associated with inflammation in IBD may reduce the efficacy of FMT. Lastly, FMT for the treatment of recurrent CDI should not, under any circumstances, replace the specific management of IBD.27
Pregnancy and breastfeedingWomen with CDI during pregnancy are more likely to require caesarean section and to develop obstetric complications.59,60 Clinical trials usually do not include pregnant or breastfeeding patients, so limited information is available. In the event of an episode of CDI during pregnancy and/or breastfeeding, treatment with oral vancomycin is recommended.10,12 Some intravenous formulations of vancomycin contain excipients that cannot be administered during pregnancy, so the use of vancomycin capsules is advised.10
There are currently no adequate studies on the use of fidaxomicin in pregnant or breastfeeding women. In animal studies, no abnormalities in the foetus have been detected and systemic absorption of fidaxomicin is minimal. However, due to lack of evidence, fidaxomicin should be reserved for cases refractory to vancomycin.
Practical questions- 1
Is it necessary to prolong treatment with vancomycin or fidaxomicin if other antibiotics prescribed for other indications cannot be discontinued? In CDI, the concomitant use of antibiotics affects both the cure of the infection and the risk of subsequent recurrence. However, there is insufficient evidence to prolong antibiotic therapy for CDI in this clinical scenario.33,61
- 2
Should a stool diagnostic test be repeated to ensure definitive cure of CDI? No. Response to treatment is based on resolution of symptoms (diarrhoea), and a repeat diagnostic test is not recommended if the patient is asymptomatic. Moreover, toxigenic CD can be detected in faeces for weeks, despite the absence of symptoms and appropriate standard antibiotic therapy.33
- 3
Should asymptomatic CD carriers be treated? In the case of a positive stool microbiological test without diagnostic criteria (see section on definitions), antibiotic therapy is not indicated. Moreover, testing for CD in asymptomatic individuals is not recommended.33
- 4
Should proton pump inhibitor (PPI) therapy be discontinued in CDI? Discontinuation of PPI is recommended in cases where the indication is questionable or unnecessary, but always after an appropriate risk/benefit assessment.10
- 5
Should prophylaxis be implemented to prevent CDI?
- •
Prescribing of probiotics to prevent CDI during antibiotic therapy is not recommended.10,12
- •
CDI-specific antibiotics are not recommended for patients requiring systemic antibiotic therapy.10
- •
The administration of anti-CDI antibiotics during systemic antibiotic therapy may be considered in very selected patients with a history of multiple episodes of CDI precipitated by systemic antibiotic therapy, but always after an appropriate multidisciplinary assessment. In this clinical scenario, the benefit of prevention must be weighed against the effects on the microbiota, the acquisition of antimicrobial resistance and the risk of recurrent CDI.10,12
- •
This section focuses on infection prevention and control measures in situations of sporadic or endemic cases of CD. We do not address epidemic outbreak management.
Measures to prevent nosocomial transmissionA CDI is considered to be hospital-acquired or related to hospitalisation when the patient develops symptoms from the third day in hospital (considering the day of admission as day 1) or has been admitted to hospital in the previous four weeks.62,63
Healthcare professionals' hands, the environment and medical equipment contaminated by CD spores are the main mechanisms of hospital transmission.64
Contact precautions are recommended for patients with CDI65–68:
- •
Place patients in single rooms where possible. Alternatively, they may share a room with another patient with CDI, provided there is no discordant colonisation by other microorganisms of epidemiological interest (e.g., methicillin-resistant Staphylococcus aureus, vancomycin-resistant enterococci).
- •
Healthcare professionals should put on gloves and gown (after proper hand hygiene) before entering the patient's room. Within the room, gloves should be changed immediately if visibly soiled, after touching or handling materials or surfaces contaminated with faeces, between procedures, and before caring for another patient in the same room. The gloves and gown should be removed just before leaving the room.
- •
Hand hygiene: hand hygiene should be performed according to World Health Organization (WHO) guidelines:
- o
Before putting on gloves.
- o
After removing the gloves.
- o
Between glove changes when performing different procedures on the same patient.
- o
Hand-washing with soap and water is recommended as the method of choice, as the removal of spores is more effective because of the rinsing part of this technique.69,70 However, it should be noted that no clinical studies have shown an increase in the incidence of hospital-acquired CDI with the use of alcohol solutions.65,71,72
When a tap is not available nearby and hand hygiene is required - for example, when performing different procedures on the same patient without being able to leave the room to wash with soap and water - alcohol-based solutions available within the room should be used. On completion of patient care, when leaving the room, the healthcare professional should preferably wash with soap and water at the nearest hand hygiene sink.
- •
The use of gloves and gowns by family members and visitors is an unresolved issue. The application of contact precautions in this group could have a minimal impact on nosocomial acquisition of CD, and the risk of hospital transmission will depend on the degree of interaction with other patients.73 In any case, hand hygiene before entering and after leaving the patient's room should always be recommended.65
- •
Environmental cleaning and disinfection: daily environmental and terminal cleaning of rooms, which is the responsibility of the cleaning company, should be carried out according to the specific procedure using a detergent and disinfectant product with effective concentration against spores (e.g., sodium hypochlorite at a dilution of 1:10 [5000 ppm], hydrogen peroxide). The need to use new technologies, such as ultraviolet light in the terminal cleaning of rooms, remains a subject of debate. Ultraviolet light is capable of inactivating CD spores, but is considered a complementary technique that should never replace proper manual cleaning and disinfection of surfaces. In fact, the addition of ultraviolet light to manual cleaning may not provide additional benefit in terms of reducing the in-hospital incidence of CDI.65,74,75
- •
Cleaning and disinfection of clinical material: clinical material should be for the exclusive use of the patient whenever possible. Reusable or shared equipment (for example, stethoscopes) should be cleaned and disinfected according to facility-specific procedures and using the indicated product with sporicidal efficacy.
- •
Transfer of the patient: the destination department should be informed in order to avoid delays and to put appropriate measures in place. When preparing the patient in the room, prior to transfer, and at the receiving department, the healthcare professional should perform hand hygiene and put on gown and gloves. The bed should be covered with a clean sheet and the rails cleaned with the indicated sporicidal product. During transport, the healthcare professional should not wear a gown or gloves, except in the event of close contact with the patient. In incontinent patients, the use of appropriate nappies should be ensured.
- •
Most guidelines recommend maintaining contact precautions for at least 48 h after the resolution of diarrhoea (stool type 5–7 on the Bristol scale).65,66,76 Antibiotic therapy for CD reduces faecal bacterial inoculum and environmental contamination, the most rapid reduction being with fidaxomicin, followed by vancomycin and, to a lesser extent, metronidazole.77–79
- •
In the case of clinical improvement in patients with a prior positive test within the previous seven days, the CD toxin test should not be repeated to decide on the withdrawal of contact precautions. Colonisation by the toxigenic CD strain may persist for weeks after clinical cure.33
- •
Often during treatment, patients may maintain a pasty stool consistency (stool type 5 or 6 on the Bristol scale) due to non-infectious causes, such as dysbiosis. In this situation, an individual clinical assessment should be carried out to decide whether contact precautions can be withdrawn and to rule out alternative diagnoses that explain the symptoms.
The article does not contain any patient data.
FundingThis document has been promoted and endorsed by the Societat Catalana de Digestologia [Catalan Society of Gastroenterology] and has not received any funding.
The authors have no conflicts of interest to declare.


