



Early intervention in psychosis has become a major priority in mental health care, supported by evidence that reducing the duration of untreated psychosis improves long-term outcomes. However, despite growing interest in clinical high-risk states for psychosis (CHR-P), structured preventive services remain scarce in many public healthcare systems, including Spain. The PREGAP programme was developed in the Basque Country as a specialised early intervention service for young people at CHR-P and with first-episode psychosis (FEP). This work aims to synthesise practical lessons derived from its early implementation to inform the development of similar services in other settings.
MethodsThis article follows a narrative and practice-oriented approach grounded in the real-world implementation of the PREGAP programme. The ten lessons were derived through an iterative process combining clinical observations, analysis of organisational challenges and referral pathways, multidisciplinary team discussions, and feedback from individuals with lived experience participating in the “Elkar Entzun” initiative.
ResultsTen interrelated lessons were identified, including rapid multisectoral referral pathways, targeted training for referrers, standardised assessment procedures, multidisciplinary psychosocial care, cultural sensitivity, continuity of care, integration of clinical practice with research and teaching, collaborative treatment planning, and incorporation of experts by experience. These lessons emerged from the practical challenges involved in implementing a specialised CHR-P service within a decentralised public healthcare system with limited previous infrastructure.
ConclusionsThe PREGAP experience suggests that implementing CHR-P services requires not only applying evidence-based recommendations, but also adapting them to the organisational and contextual realities of each healthcare system.
In recent decades, the management of psychotic disorders has undergone a significant shift toward early detection and intervention. This transformation has been driven by growing evidence that reducing the duration of untreated psychosis (DUP) improves long-term outcomes, including symptom severity, functional recovery, and relapse rates.1 As a result, specialized Early Intervention Services (EIS) have emerged worldwide as a gold-standard model for individuals experiencing a first episode of psychosis (FEP), delivering phase-specific, intensive treatment via multidisciplinary teams that integrate pharmacological, psychological, and social interventions.2
However, critical changes in the trajectory of psychosis often emerge earlier, during the clinical high-risk state for psychosis (CHR-P). This phase is defined by the presence of attenuated psychotic symptoms, brief intermittent psychotic episodes, or a combination of genetic risk and functional decline.3 In clinical practice, CHR-P individuals frequently present with prominent mood and anxiety symptoms rather than frank psychosis.4 Neurocognitive deficits are already present, with CHR-P individuals showing medium-to-large impairments across cognitive domains compared to healthy controls,5 though less severe than in individuals with FEP.6,7 Additionally, over 75% present with at least one comorbid mental disorder at baseline, leading to substantial functional impairment.4 The CHR-P stage is associated not only with psychological and cognitive symptoms, but also with systemic physiological changes, such as increased pro-inflammatory markers and HPA axis dysregulation.8 These findings position the CHR-P stage as a key window for clinical intervention—both to prevent or delay psychosis onset and to reduce the significant psychological burden already present.
Evidence-based interventions at the CHR-P stage have shown limited and inconsistent benefits in preventing psychosis or improving long-term outcomes. Commonly used approaches—such as cognitive-behavioral therapy, family therapy, omega-3 supplementation, or antipsychotics—have not demonstrated robust or sustained effects on transition rates, symptom severity, or functional recovery.9 These findings underscore the complexity and heterogeneity of the CHR-P population and highlight the need for more precise, adaptive, and personalized intervention strategies. While current approaches may offer modest benefits for some individuals, particularly within comprehensive early detection services, future efforts should aim to optimize care by better aligning interventions with individual needs and risk profiles.
Despite the proliferation of EIS in many healthcare systems, few services have established structured, sustainable programmes specifically aimed at CHR-P individuals. In the Basque Country (Spain), this gap led to the creation of the PREGAP Programme (Prebentziorako Gazte-Programa Psikosian) in 2023: a multidisciplinary, community-oriented early detection and intervention service for young people aged 16 to 35 years who meet criteria for CHR-P. PREGAP complements the existing FEP treatment programme (Lehenak Service) at the Basurto University Hospital and is integrated into the broader mental health care network of Bizkaia.
In the Spanish public healthcare system, and particularly in the Basque Country, structured services specifically targeting the CHR-P population remain scarce. Prior to the implementation of PREGAP, early detection of psychosis risk largely depended on non-specialised services, including primary care, paediatric services, and general mental health teams, often without standardized referral pathways or shared diagnostic frameworks. This lack of dedicated infrastructure required the development of the programme from the ground up, including the creation of referral networks, training strategies, and coordination mechanisms across multiple sectors. To our knowledge, PREGAP is currently the first service in the Basque Country to provide systematic assessment and longitudinal follow-up for individuals at CHR-P, and one of the few programmes specifically dedicated to this population within Spain. As such, the lessons derived from PREGAP are closely linked to the challenges of implementing a new service within a decentralised and resource-constrained healthcare system. This context shaped many of the operational and clinical decisions described throughout the present work.
PREGAP operates as a multidisciplinary outpatient programme integrated within the public mental health network of Bizkaia and coordinated through the Psychiatry Department of Basurto University Hospital. The programme was created in January 2023 as an extension of the existing Lehenak early intervention service for first-episode psychosis, with the aim of addressing the preventive phase preceding the onset of frank psychosis. It provides specialised assessment and longitudinal follow-up for young people aged 16–35 years presenting with attenuated psychotic symptoms, brief intermittent psychotic episodes, or other clinical features compatible with CHR-P states, using structured assessment instruments such as the CAARMS. Referrals are accepted from multiple sectors, including community mental health services, emergency departments, primary care, paediatric services, educational settings, inpatient units, and social or community resources. Clinical care combines psychiatric, psychological, nursing, and social interventions within a community-oriented and recovery-focused framework adapted to the developmental and functional needs of each user.
This article outlines ten lessons learned during the implementation of an early intervention programme for psychosis, based on the practical experience of the PREGAP team. These insights emerged through the development and early deployment of the programme and aim to serve as a pragmatic, experience-based guide for clinicians, service managers, and policy-makers seeking to establish similar initiatives. Special attention is given to cultural sensitivity, integration with community resources, family involvement and the translation of clinical practice into research and innovation.
MethodsThis article presents a critical, experience-based reflection on the implementation of an early intervention service for individuals at CHR-P. Rather than a systematic review or formal implementation study, this work follows a narrative and practice-oriented approach grounded in the real-world experiences of the PREGAP team and informed by iterative multidisciplinary reflection throughout the programme’s early implementation phase.
The ten lessons described were derived through an iterative process combining (1) clinical observations from the early implementation of the PREGAP programme, (2) analysis of service organisation and referral patterns, and (3) regular structured multidisciplinary discussions within the team. Throughout the implementation phase, regularly scheduled meetings were held among programme coordinators and clinical staff to identify recurrent operational difficulties, barriers to care, and potential strategies for service improvement based on the challenges encountered in routine practice. Lessons were prioritised according to the frequency, clinical relevance, and organisational impact of the challenges identified during the implementation process.
In addition, several discussion and feedback sessions were conducted with individuals with lived experience of psychosis participating in “Elkar Entzun”, a participatory initiative linked to the programme. These sessions provided qualitative insights into users’ experiences of accessibility, continuity of care, communication, stigma, and therapeutic needs, helping refine several of the lessons presented in the manuscript.
This process aimed to ensure that the lessons reflected not only general principles of early intervention, but also context-specific adaptations required within the Spanish public healthcare system. Although this process did not follow a formal Delphi or qualitative implementation methodology, efforts were made to achieve consensus across clinicians and stakeholders involved in the programme.
The objective is to share transferable insights and practical strategies that may inform the development of CHR-P services in diverse contexts. What follows is a synthesis of ten key lessons aimed at guiding the planning and refinement of CHR-P intervention programmes.
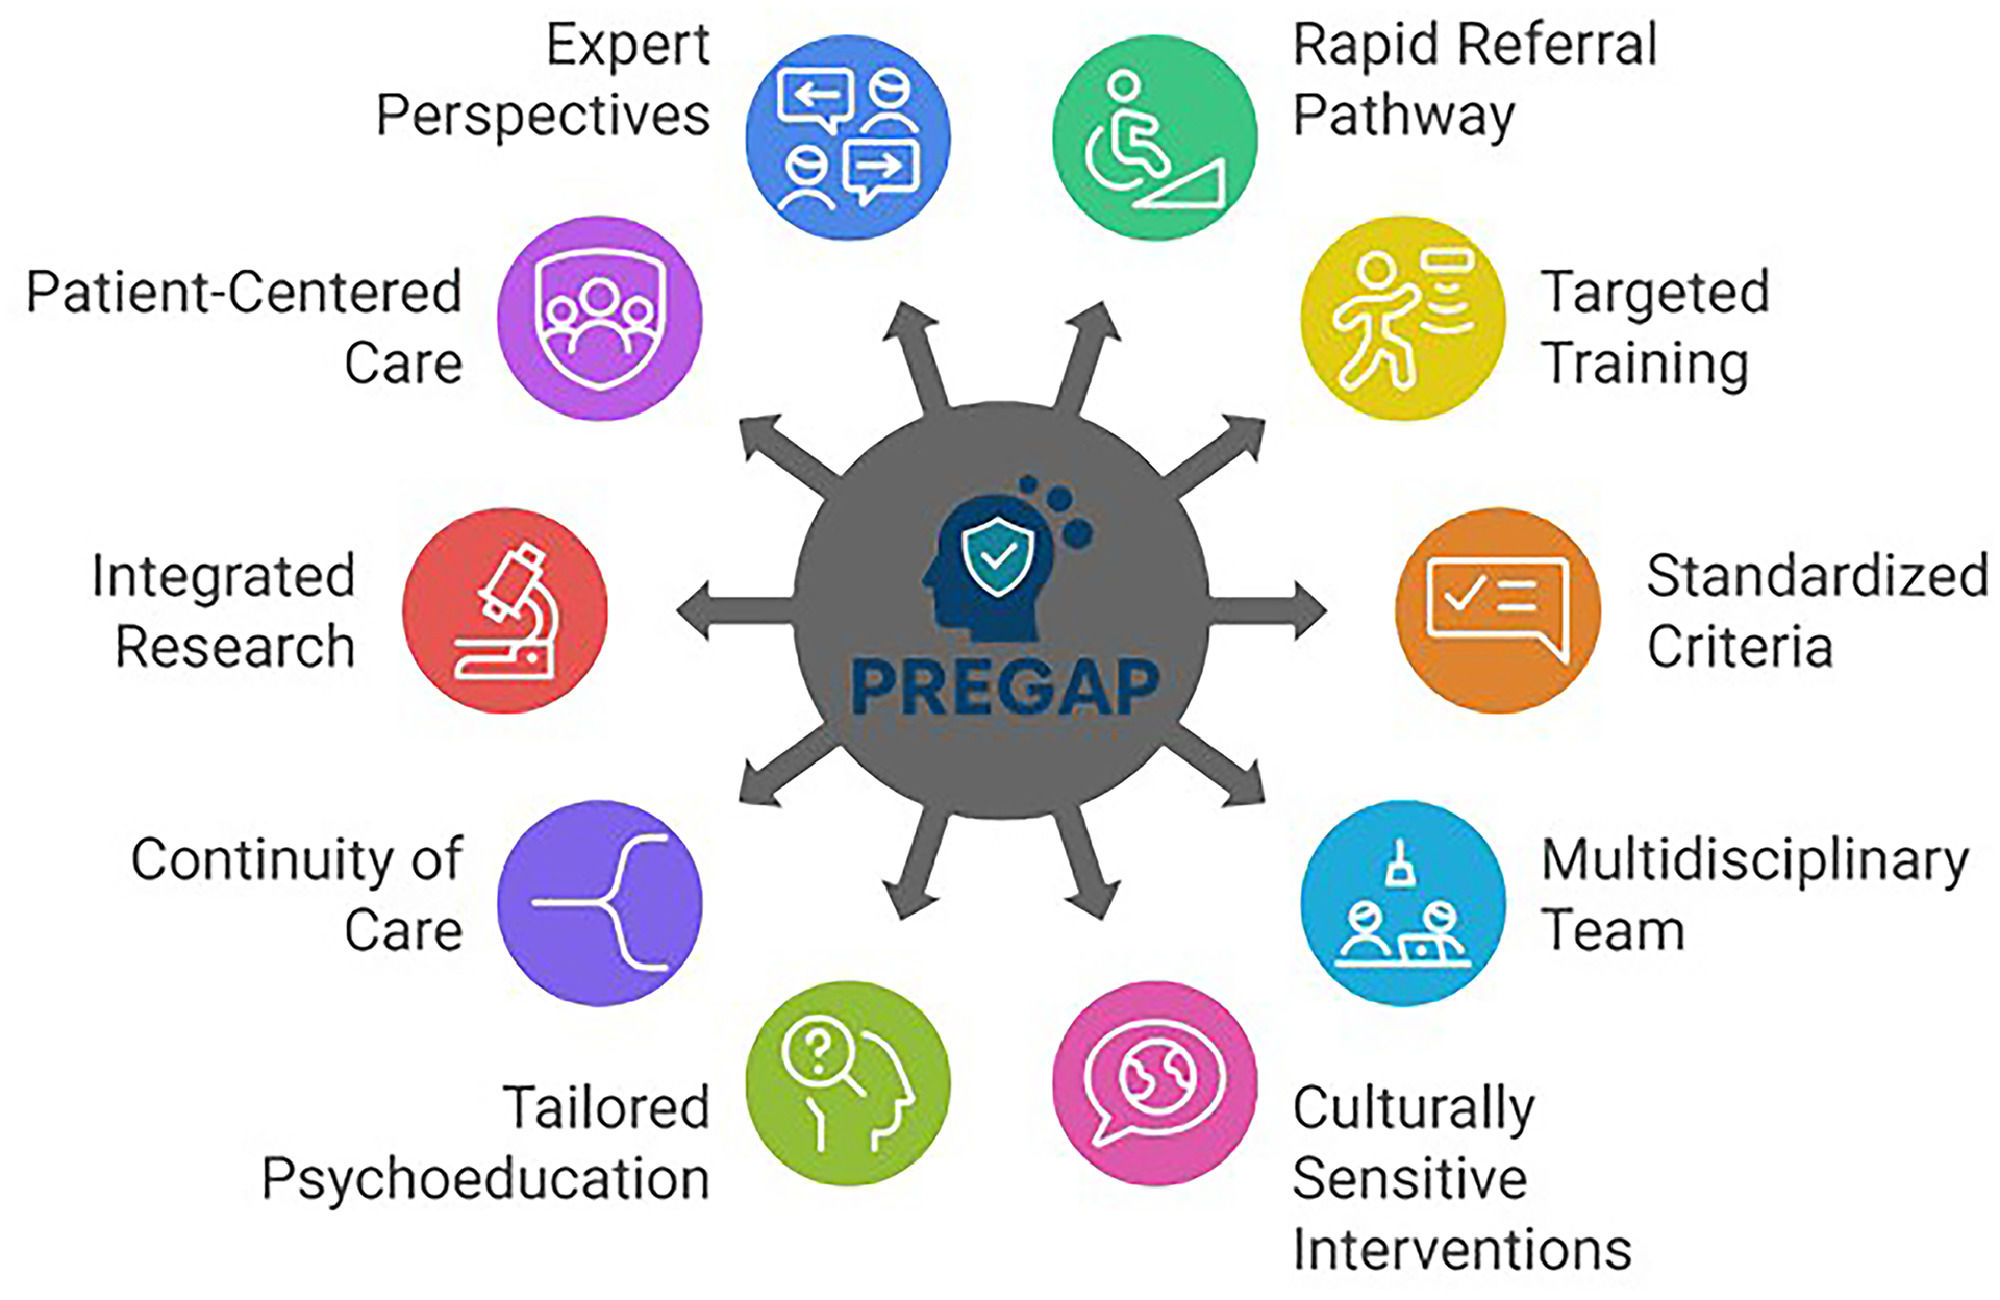
ResultsThe following section summarizes the main insights derived from the early implementation of the PREGAP programme. Ten key lessons are presented, reflecting the progressive development of the service and covering aspects such as referral pathways, professional training, multidisciplinary care, cultural sensitivity, continuity, and user participation. Fig. 1 illustrates how these components are integrated within the PREGAP model, forming a coherent framework that connects clinical practice, research, and education.

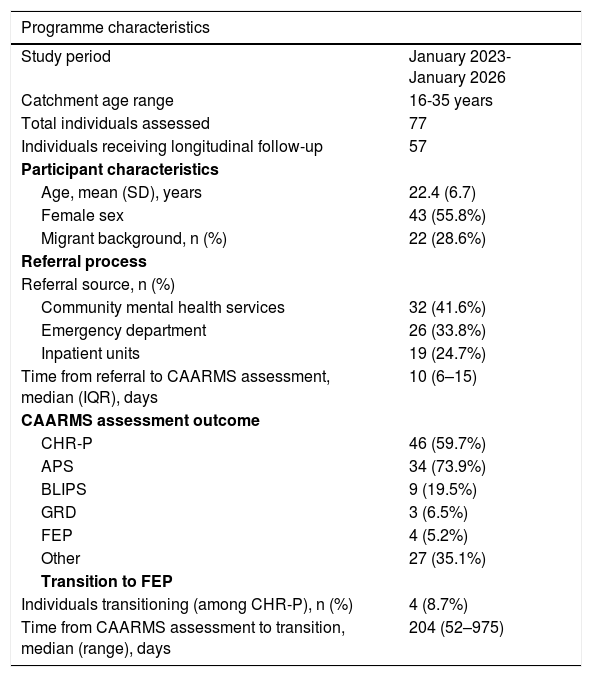
To contextualise the implementation experience described in the present work, Table 1 summarises the operational and clinical indicators of the PREGAP programme. These data provide the empirical context from which the implementation lessons presented below were derived. To contextualise the implementation experience described in the present work, Table 1 summarises the available descriptive characteristics of the PREGAP programme during its initial implementation phase.
Operational and clinical indicators of the PREGAP programme during the implementation phase. Abbreviations: APS, attenuated psychotic symptoms; BLIPS, brief limited intermittent psychotic symptoms; CAARMS, Comprehensive Assessment of At-Risk Mental States; CHR-P, clinical high risk for psychosis; FEP, first-episode psychosis; GRD, genetic risk and deterioration; IQR, interquartile range; SD, standard deviation.
As shown in Table 1, not all referred individuals ultimately met CHR-P criteria following specialised CAARMS assessment. Among the 77 individuals assessed, 46 met CHR-P criteria, 4 already presented with a first episode of psychosis, and 27 were assigned alternative clinical diagnoses. Consequently, not all assessed individuals required longitudinal follow-up within the programme, as some were referred to specialised FEP services while others were considered more appropriately managed within alternative specialised mental health services according to their clinical needs (e.g., eating disorders or trauma-related programmes). These operational findings illustrate the practical challenges associated with referral triage, specialised assessment, and care pathway allocation during the implementation of an early psychosis prevention service, providing the empirical context from which several of the implementation lessons presented below were derived. Not all assessed individuals ultimately required longitudinal follow-up within the programme, as some did not meet CHR-P criteria following specialised CAARMS assessment, others already presented with a first episode of psychosis requiring referral to FEP services, some declined continued follow-up, and in other cases alternative specialised services (e.g., eating disorders or trauma-related programmes) were considered more appropriate according to the individual’s clinical needs.
Lesson 1. Design a rapid and multisectoral referral pathwayTimely access to specialized care is a foundational principle of early intervention in psychosis. Yet, referral delays (often driven by insufficient awareness of CHR-P criteria, ambiguity regarding clinical thresholds, or administrative complexity) continue to hinder service engagement. During the implementation period, the median time from referral to specialised CAARMS assessment was 10 days (IQR 6–15; Table 1), suggesting that the referral pathway developed within PREGAP facilitated timely access to specialised assessment. This operational indicator reinforces the importance of establishing an agile, well-defined, and multisectoral referral pathway to promote early identification and reduce delays in access to appropriate care. In our experience at PREGAP, the establishment of an agile, well-defined, and multisectoral referral pathway was essential to promote early identification and reduce the duration of untreated symptoms in at-risk youth.
In our setting, the absence of a pre-existing CHR-P detection network meant that many initial referrals arrived late in the clinical trajectory or with poorly defined referral reasons, often requiring additional coordination between services before specialised assessment could take place. In many cases, clinicians across the network identified significant psychological distress, functional deterioration, or emerging psychotic-like experiences, but the absence of a specialised CHR-P pathway often resulted in fragmented follow-up, repeated emergency department visits, or delays in access to appropriate care. In some individuals, attenuated symptoms appeared to become more clinically severe over time before specialised assessment was finally conducted. These challenges directly informed the need to prioritise simple, rapid, and highly accessible referral pathways during the early phases of implementation.
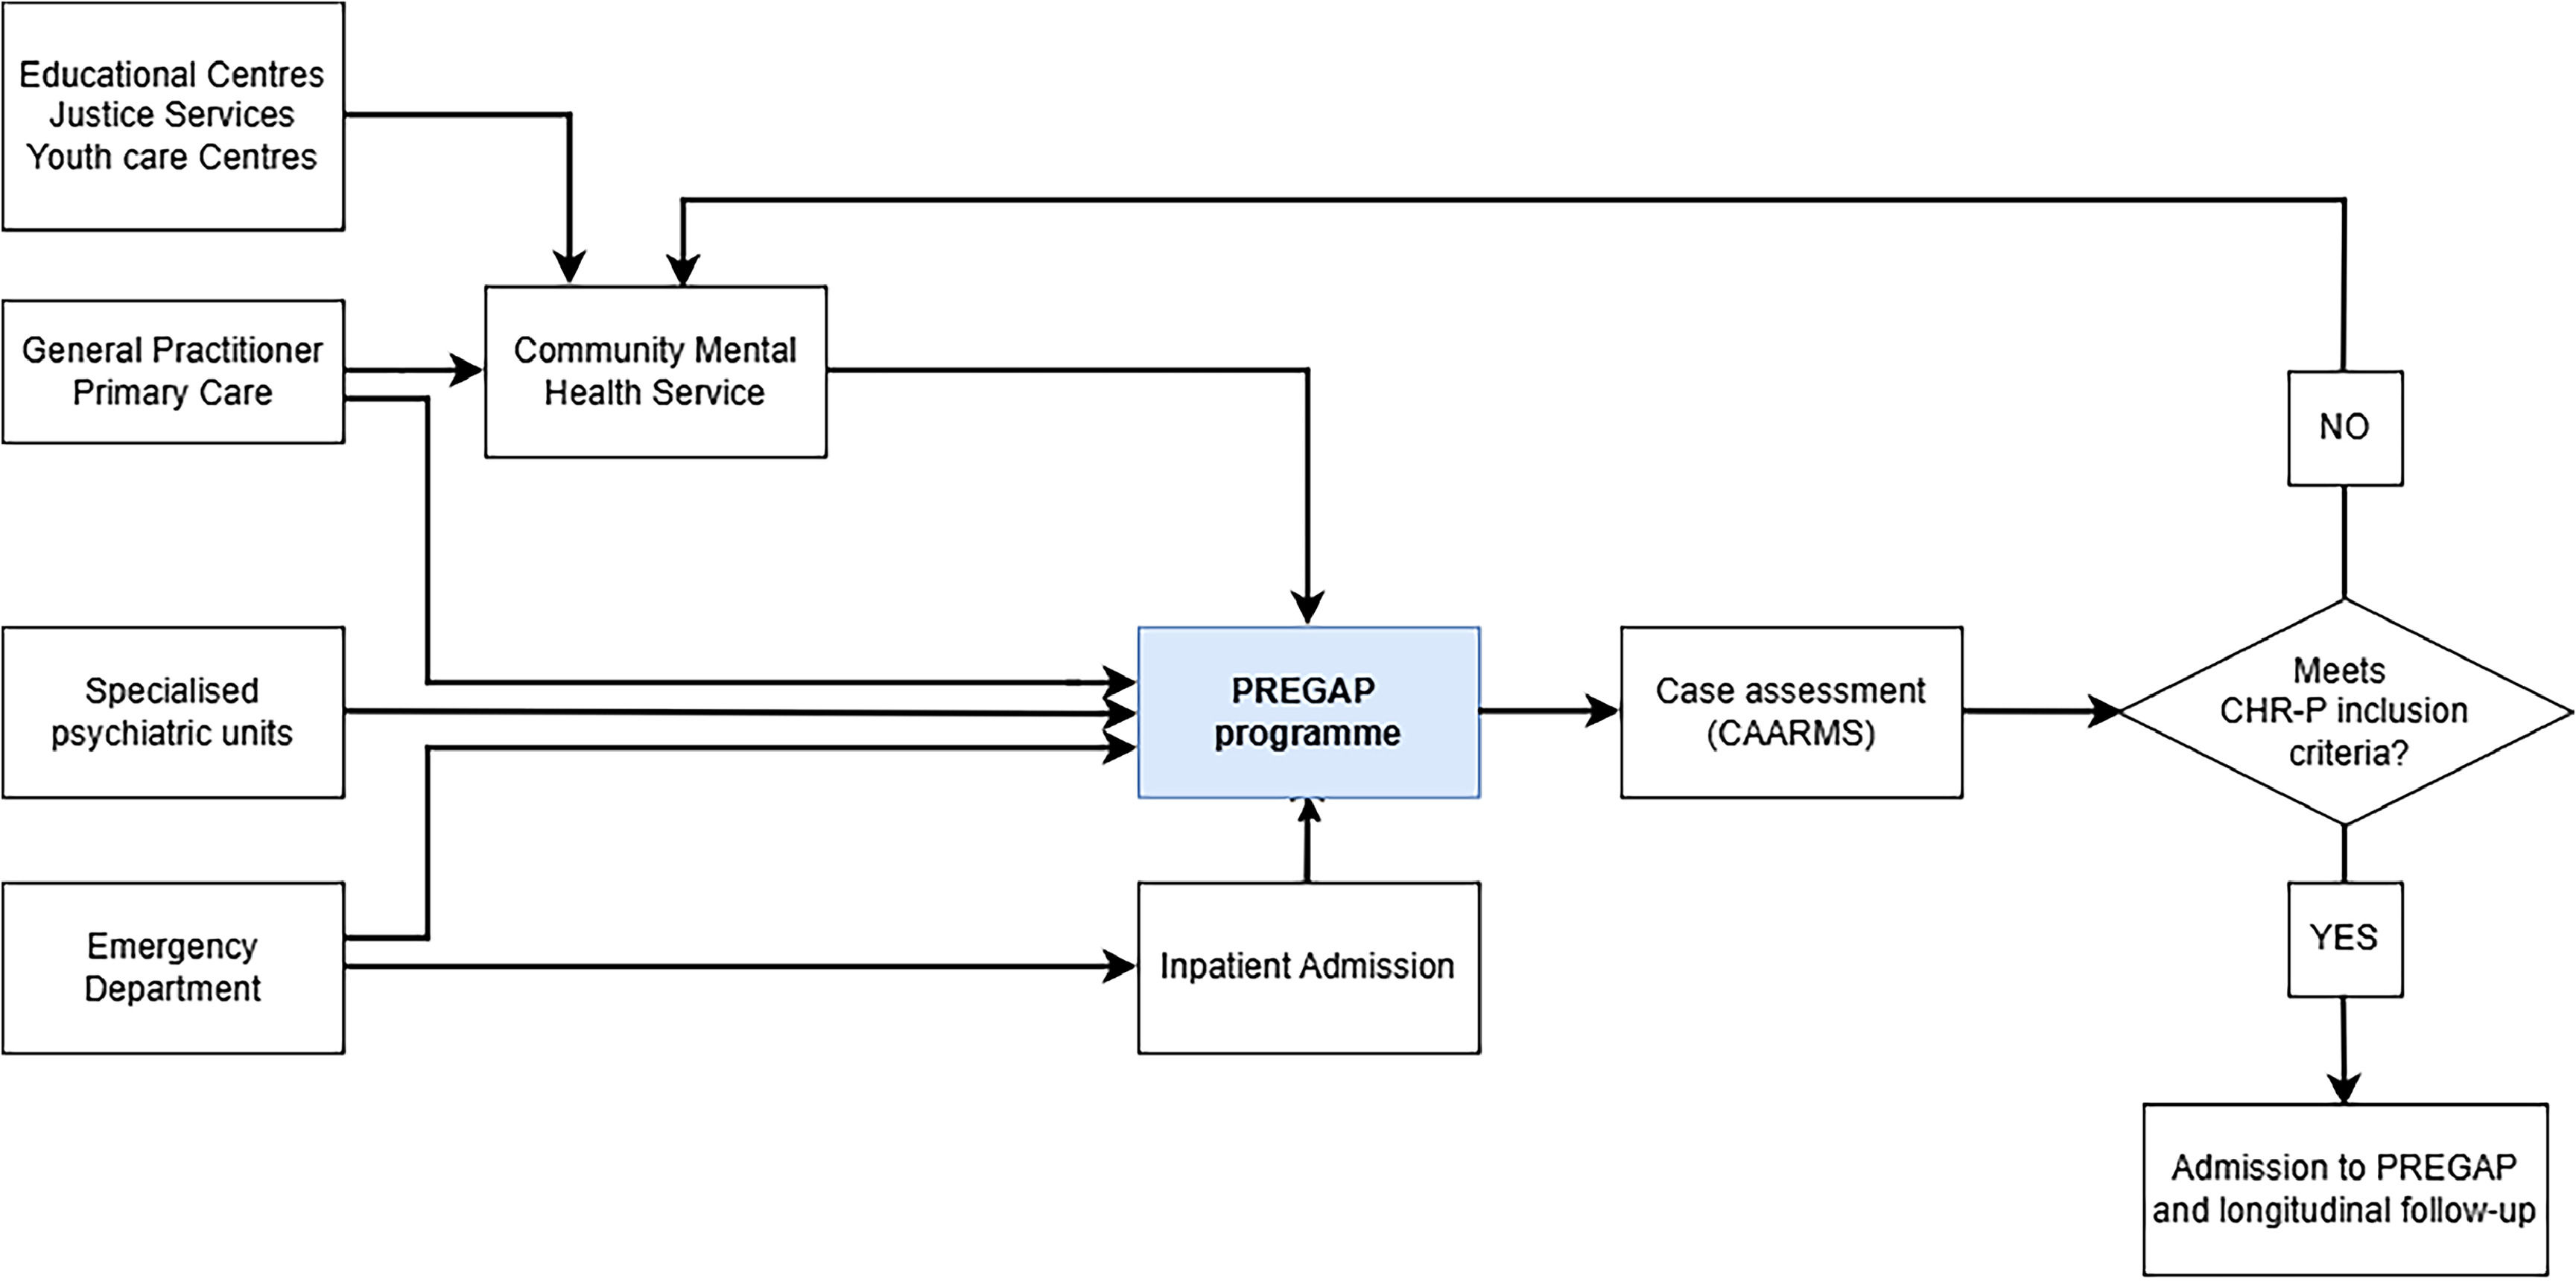
This process required active collaboration with a broad range of stakeholders, including not only psychiatrists but also primary care physicians, paediatric services, school-based professionals, emergency departments, and social care providers. Clear documentation of referral criteria streamlined communication channels, and explicit pathways for accessing the programme enhanced both the speed and appropriateness of referrals. Proactive outreach was crucial: our team conducted in-person visits to key institutions to present the programme, clarify inclusion criteria, and foster ongoing partnerships. Making ourselves available for direct proved fundamental to building trust and sustaining inter-professional engagement. The operational structure of the referral and admission process implemented within PREGAP is illustrated in Fig. 2.

While PREGAP does not currently accept direct self-referrals from individuals or families, this could represent a valuable future direction. Allowing young people to seek help autonomously might reduce barriers to early assessment and increase empowerment. However, implementing such a model requires broader public awareness of the prodromal signs of psychosis to avoid service saturation with inappropriate or false-positive referrals. Furthermore, self-referral pathways are particularly challenging in the context of psychosis, where limited insight and difficulties in recognizing emerging symptoms often delay help-seeking. Balancing accessibility with clinical precision therefore remains a key challenge for early detection programmes.
Developing a decentralized and responsive referral infrastructure not only expanded the programme’s reach but also ensured equitable access across diverse sociodemographic groups. In sum, a well-integrated referral system must be visible, technically sound, and embedded within the local care ecosystem to maximize early detection efforts.
Lesson 2. Provide targeted training and outreach to referral sourcesWhile a structured referral system is necessary, it must be actively supported through sustained efforts to raise awareness and build competence among potential referrers. At PREGAP, we observed that even when pathways were in place, many professionals were uncertain about early signs of psychosis, CHR-P criteria, or the appropriate timing for referral. During the first stages of implementation, we also observed substantial variability in referral quality depending on the professional background and level of previous exposure to early psychosis concepts. This was also reflected in the CAARMS assessment outcomes, with more than one third of assessed individuals ultimately not meeting criteria for CHR-P or FEP and receiving alternative clinical diagnoses (Table 1), highlighting the need for continuous training and calibration of referral criteria across services. This reinforced the importance of sustained and context-adapted training efforts rather than one-time educational interventions.
To address this, we developed a targeted outreach and training strategy aimed at key sectors, including primary care, paediatrics, social services, and community mental health centres. Particular emphasis was placed on general practitioners, who often act as the first point of contact for young people and families. Training also extended to pharmacists, school counsellors, and law enforcement officers, who may encounter early warning signs of distress or behavioural change in community settings. These activities combined information sessions with sensitisation efforts to promote understanding, reduce stigma, and encourage timely referral.
Educational activities focused on improving recognition of subthreshold psychotic symptoms, understanding functional decline, and differentiating CHR-P from non-specific psychological distress. Rather than relying solely on written materials or guidelines, we prioritized direct contact, since interactive sessions held within professionals’ own setting allowed for case-based discussion, practical clarification, and ongoing dialogue.
We found that professionals were more likely to engage with the programme when they felt informed, valued, and part of a collaborative effort. Creating spaces for mutual feedback and clinical dialogue helped transform referrers from passive informants into collaborators. This strategy not only improved the accuracy and timeliness of referrals but also fostered a shared responsibility for early detection across the network of care.
To further enhance consistency and sustainability, PREGAP is now developing standardized training seminars and educational materials, combining in-person workshops with digital resources. These structured sessions aim to ensure that all professionals across the care network receive uniform, evidence-based information, while allowing adaptation to local contexts and clinical realities.
Lesson 3. Use clear and standardized diagnostic criteriaOne of the first challenges in developing an early psychosis intervention programme is the reliable identification of individuals at CHR-P. This population is highly heterogeneous, encompassing attenuated psychotic symptoms (APS), brief intermittent psychotic episodes (BLIPS), and genetic risk with functional decline (GRD). Importantly, the CHR-P label covers a wide range of symptom presentations, functional levels, and trajectories, including differences in transition risk, symptom persistence, and likelihood of remission.10–14 This degree of variability has led to ongoing debate about the clinical utility and conceptual coherence of the CHR-P construct itself, posing significant challenges for outcome prediction and treatment planning.15,16 This heterogeneity was also reflected in our implementation experience, where more than 40% of individuals referred with suspected CHR-P ultimately did not meet CHR-P criteria following CAARMS assessment (Table 1), instead being classified as FEP or receiving alternative clinical diagnoses, underscoring the importance of structured diagnostic evaluation using validated instruments such as the CAARMS to ensure consistency across assessments.
In this context, using a structured and validated instrument such as the CAARMS is essential to ensure consistency across assessments. However, the value of the CAARMS depends on rigorous and standardized administration. At PREGAP, we observed that proper training and inter-rater reliability checks were necessary to avoid over- or under-identification of CHR-P status. Beyond technical scoring, clinicians must also conduct thorough and nuanced interviews, exploring each symptom domain in depth and allowing sufficient time for clarification. In our experience, ambiguous application of diagnostic thresholds or superficial exploration of symptom content can lead to inappropriate inclusion, either by capturing individuals with non-specific distress or by missing those with subtle but clinically relevant risk signs.
Accurate and transparent communication of diagnostic impressions is also essential. Providing patients with a clear and specific clinical formulation facilitates appropriate referral and engagement with the most suitable service. Conversely, the tendency to rely on broad or non-specific labels (e.g., “behavioural alteration”) may delay referral to specialised programmes and hinder timely access to targeted intervention.
Establishing precise diagnostic procedures not only improves the quality of care but also supports the integrity of clinical research. Therefore, we recommend structured assessment protocols, regular training updates for clinicians, and multidisciplinary discussion of borderline cases to optimize diagnostic accuracy in real-world settings.
Lesson 4. Build a multidisciplinary team tailored to non-pharmacological interventionCHR-P care requires a shift from traditional psychiatric models toward a more integrative and preventive approach. Given the limited and inconsistent evidence regarding the efficacy of antipsychotic (AP) treatment in this population, international guidelines prioritize psychological and psychosocial interventions as first-line approaches.17–19 At PREGAP, the clinical model is structured around a multidisciplinary team including psychologists, nurses, social workers, and psychiatrists. Administrative staff trained and sensitized to mental health needs also play a key role in managing user enquiries and coordinating communication, ensuring accessibility and a welcoming environment for young people and families. This configuration enables a flexible, individualized approach, with interventions adapted to each person’s functional profile and evolving clinical needs. In practice, many of the patients referred to the programme presented with significant affective, anxiety-related, interpersonal, or functional difficulties that extended beyond attenuated psychotic symptoms alone. This reinforced the need for flexible multidisciplinary interventions capable of addressing complex and evolving clinical presentations.
Psychological interventions are the cornerstone of CHR-P care. Cognitive behavioural therapy (CBT) is the most consistently recommended approach for managing prodromal symptoms, dysfunctional thinking and maladaptative coping strategies, and may also improve functioning and reduce distress in individuals who do not transition to psychosis. However, recent meta-analyses have questioned the robustness of CBT’s effects in this population, underscoring the need for further high-quality research on CBT and other psychotherapeutic options.20,21 In clinical practice, additional strategies such as psychoeducation, family-based interventions, and supportive counselling are often included as part of a broader therapeutic package, enhancing engagement, insight, and social integration.
When psychological approaches alone are insufficient, cautious use of pharmacological treatment may be considered. For APs, all major guidelines advise against routine preventive use in CHR-P and recommend a “need-based” approach limited to short-term, symptom-oriented indications.18 Such use may be appropriate in cases of progressive positive symptoms, accelerated functional decline, significant psychological distress, risk of self-harm or aggression, or failure of psychosocial strategies. In these situations, low doses are employed for limited durations, not as a preventive measure against psychosis but to alleviate acute suffering and support functional stabilization. Baseline AP exposure may, in fact, act more as a proxy for illness severity than as a protective factor, further supporting a cautious and individualized prescribing strategy.
Finally, comorbid conditions such as anxiety, depression, or sleep disturbances are common in CHR-P populations and may occasionally justify the selective use of non-antipsychotic pharmacological interventions.22,23 These should always be embedded within a broader psychosocial treatment plan and carefully tailored to individual clinical needs and preferences. Given the elevated risk of physical comorbidities in this population,8,24 integrating professionals focused on physical health and lifestyle—such as exercise or health promotion specialists—can further support recovery and overall well-being.
At PREGAP, interventions are explicitly aligned with each individual’s functional goals, social prognosis, and personal aspirations —whether related to education, employment, relationships or autonomy. Rather than focusing solely on symptom control or prevention of psychosis onset, the team supports patients in reclaiming a sense of purpose and direction, building resilience, and improving overall quality of life. Such a recovery-oriented perspective helps strengthen the therapeutic alliance and sustain engagement, particularly among individuals whose main concerns lie outside the psychosis spectrum.
Lesson 5. Design culturally sensitive and context-specific interventionsThe marked clinical heterogeneity of CHR-P presentations (see Lesson 3) is further amplified by diversity in cultural background, migration history, adoption status, gender identity, and other intersecting minority identities.25,26 These factors shape how mental health difficulties are experienced and addressed, and can influence engagement as much as symptom profile itself.27 In our catchment area, these challenges were particularly relevant in migrant populations and socially vulnerable groups, where stigma, language barriers, and differences in explanatory models of illness sometimes complicated early engagement with services. This was particularly pertinent given that 28.6% of individuals assessed in PREGAP had a migrant background (Table 1). At PREGAP, this understanding informs our commitment to culturally sensitive care, which we regard not as a symbolic gesture of inclusion, but as an evidence-based requirement for effective early intervention.28
We address structural barriers through measures like professional interpreters, adapted psychoeducational materials in multiple languages, collaborating with community associations that support migrant or minority groups, and maintaining flexibility in clinical interviews to explore individuals’ personal belief systems and culturally embedded explanatory models of illness. Family participation is actively encouraged, with sensitivity to different cultural norms and family structures, while stigma—particularly in communities where mental health is rarely discussed—is explicitly addressed in psychoeducation and group interventions.
In some cases, culturally matched peer support is also facilitated, whereby individuals are connected with others from similar cultural, linguistic, or religious backgrounds who can contribute to therapeutic engagement through culturally grounded peer support.
Lesson 6. Facilitate subjective understanding and provide tailored psychoeducationBeyond symptom reduction, CHR-P care should actively support individuals in making sense of their experiences. Evidence from phenomenological and cognitive research indicates that self-interpretation and meaning-making processes can influence clinical trajectories, with the appraisal of anomalous experiences playing a central role in determining distress, functional impact, and need for care.29
Psychoeducation is therefore a core therapeutic component in services attending CHR-P populations, not only to convey information, but also to help individuals and families develop coherent, non-stigmatizing narratives that support engagement and recovery. This applies equally to children and adolescents, who should receive age-appropriate, clear explanations about symptoms and mental health, rather than being excluded on the assumption that they cannot understand or cope with such information.30
At PREGAP, psychoeducation is adapted to the user’s developmental stage, level of psychopathology and communication style. This includes integrating personal narratives and explanatory models provided by the individual and their family, in order to promote insight, reduce uncertainty, and foster a sense of agency in managing symptoms. Families are involved as active partners in the process, while ensuring that the user’s perspective remains central, which in turn strengthens engagement, therapeutic alliance and the likelihood of sustained recovery.
Lesson 7. Ensure continuity of care and planned transitionsMaintaining continuity of care is essential in CHR-P intervention, particularly given the fluctuating and heterogeneous course of individuals at CHR-P. Unplanned service disengagement or abrupt transitions can disrupt therapeutic gains, increase distress, and heighten the risk of relapse or functional decline. Therefore, establishing clear, transparent criteria for discharge, referral to FEP services, or transfer to alternative resources is essential.
This was particularly relevant in our setting, where the transition between child and adolescent mental health services and adult mental health services often occurs around the age of 18, potentially generating fragmentation in care during a particularly vulnerable developmental period if not actively coordinated. These challenges highlight the importance of youth-oriented and developmentally informed models of care capable of ensuring continuity across traditional service boundaries.
Within the PREGAP framework, transition planning is initiated at an early stage and conducted in a collaborative manner with the service user and their family, ensuring that decisions are clinically justified, clearly communicated, and aligned with the individual’s preferences. Discharge may also be considered in cases of sustained clinical improvement, contingent upon user agreement, with explicit provision of information on available resources and pathways for re-accessing care if needed. No user exits the programme without a defined follow-up plan, which may involve primary care, community mental health services, or other specific programmes. When clinically indicated, coordinated care plans should be developed jointly with receiving teams, incorporating crisis management strategies and mechanisms for expedited re-engagement in the event of symptom recurrence.
Lesson 8. Integrate clinical care with applied research and teachingThe integration of clinical practice and applied research is a defining feature of high-quality CHR-P services, enabling continuous refinement of interventions and the generation of knowledge with direct translational impact. Close coordination between clinical and research staff ensures efficient recruitment, informed consent, and ethical conduct of studies without compromising patient care. At PREGAP, systematic collection of clinical, functional, and sociodemographic data has supported collaborative research, such as the recent study by Catalán et al.,31 which identified specific associations between peripheral inflammation markers (IL-6 and TNF-α) and social cognition in early psychosis. As longitudinal data accumulate, such findings will allow for re-evaluation of clinical priorities and adaptation of service provision.
As part of a university hospital, the programme also plays an active role in medical education, offering training to psychiatry residents and medical students. This threefold mission fosters an environment in which patient care is continuously informed by research findings and enriched by ongoing educational activity.
Lesson 9. Listen to patient needs – and to our own as professionalsIn CHR-P care, aligning the expectations of patients, families, and clinicians can be challenging. Evidence from early psychosis services shows that patients often prioritize relief from affective and cognitive symptoms and a rapid return to daily functioning, whereas clinicians may place greater emphasis on managing positive symptoms and achieving longer-term objectives such as relapse prevention and resilience building.32 Differences can also emerge in treatment preferences: while many patients value a broad range of interventions, their views on the relative importance of pharmacological versus psychosocial approaches may not fully match those of the clinical team.33 In our experience, these differences were especially visible during the early stages of engagement, when many young people sought help primarily for anxiety, emotional distress, or functional difficulties rather than for psychotic-like experiences themselves.
Within PREGAP, treatment planning is approached as a collaborative and dynamic process, with goals discussed explicitly from the outset, revisited at regular intervals, and any differences in priorities openly acknowledged, facilitating realistic plans that respect the patient’s pace of change while safeguarding essential clinical objectives.
For clinicians, this approach also requires both self-awareness and reflective practice. Recognising the influence of our own professional expectations, and the emotional impact when progress diverges from anticipated trajectories, helps sustain a collaborative stance and minimise frustration. By promoting a shared understanding of objectives, timelines, treatment modalities, and limitations, this process strengthens engagement and enhances the likelihood of achieving meaningful, sustainable outcomes.
Lesson 10. Incorporate perspectives of experts by experienceThe perspectives of people with lived experience of psychosis are an essential source of knowledge for developing and refining CHR-P services. Involving service users as active partners in decision-making helps ensure that interventions are relevant, acceptable, and responsive to real needs, while also challenging traditional models of service.
At PREGAP, this principle is operationalised through the inclusion of former and current service users in consultative groups and focused feedback sessions, where they contribute to the planning, evaluation, and ongoing improvement of the programme. For instance, the content of the present article has been reviewed and refined in collaboration with a group of experts by experience participating in “Elkar Entzun”—a pioneering initiative originating from PREGAP that aims to embed experiential knowledge into mental health systems by systematically incorporating the voices of users, carers, and communities. This collaboration ensures that the lessons presented here reflect both clinical expertise and the perspectives of those directly affected.
This approach is consistent with recent bottom-up initiatives co-written with experts by experience, which show that lived experience is not merely a complement but an indispensable source of knowledge for guiding service development, research priorities, and educational practices.34
DiscussionThe present work synthesises practical lessons derived from the early implementation of PREGAP, a specialised programme for individuals at CHR-P and FEP within the Basque public healthcare system. Rather than proposing a new theoretical model or replacing international recommendations, this article aims to provide a pragmatic implementation-oriented framework grounded in the operational, clinical, and organisational challenges encountered during the development of a de novo early psychosis prevention service. The lessons presented emerged from real-world experience and reflect both the opportunities and barriers involved in translating evidence-based recommendations into routine clinical practice.
Importantly, the implementation of PREGAP occurred in a context with limited prior CHR-P infrastructure, which differs substantially from regions with well-established early intervention networks, such as the OASIS service in South London35 or the Early Psychosis Prevention and Intervention Centre (EPPIC) in Australia.36 Although these highly specialised programmes have shaped the field, they represent only one end of the implementation spectrum. International experience has shown that early intervention services can be successfully implemented across diverse healthcare systems. Their availability, degree of implementation, and sustainability remain highly heterogeneous, reflecting differences in health system organisation, funding mechanisms, referral pathways, and policy commitment.37 Evidence from recent studies indicates that the implementation of dedicated CHR-P services remains heterogeneous across Southern Europe, Latin America, Central and Eastern Europe, and several Asian countries, where healthcare systems often face fragmented referral pathways, limited specialised resources, and variable institutional support.37–39 While Italy has developed the most structured CHR-P network in Southern Europe (ITAPP)40, implementation in Spain has largely centred on FEP services, with specialised CHR-P programmes emerging through regional clinical-academic initiatives.37 For example, the Early Intervention Program in Catalonia and the recent validation of the Spanish version of the CAARMS interview further support the feasibility of structured CHR-P assessment within public clinical settings.41 Likewise, only a small number of specialised CHR-P programmes have been described in Latin America42, including initiatives in Chile43 and Brazil.44 Similar heterogeneity has also been reported across Asia, where specialised CHR-P programmes such as SHARP45 in China and multicentre ARMS services in Japan46 coexist with regions in which early intervention services remain largely limited to research centres or urban academic settings because of structural and resource constraints. Taken together, these examples suggest that many healthcare systems seeking to establish specialised CHR-P services face organisational challenges similar to those encountered during the implementation of PREGAP. In such settings, many of the processes described in international guidelines (e.g., referral pathways, specialised teams, or structured assessments) are already embedded within the healthcare system. In contrast, our experience required the simultaneous development of these components, often in the absence of dedicated resources, established protocols, or widespread familiarity with CHR-P concepts among professionals. This highlights the need for flexible, context-sensitive implementation strategies when translating evidence-based models into real-world settings with different levels of service maturity.
In this context, implementation depended not only on the creation of specialised procedures, but also on progressively building inter-service collaboration, increasing awareness of CHR-P concepts across the network, and integrating early intervention principles within existing mental health structures. This frequently required prioritising flexibility, coordination, and progressive network-building over the immediate implementation of highly specialised standalone services.
Rather than replicating these models directly, PREGAP required adaptation to the organisational realities of the local public healthcare network. The novelty of the present work lies not in redefining established CHR-P principles, but in illustrating the practical adaptations required to translate these recommendations into routine clinical practice within a decentralised and resource-constrained public healthcare system.
Our experience also highlighted the importance of adopting developmentally informed and youth-oriented models of care when implementing CHR-P services. This is consistent with recent youth mental health frameworks emphasising that most mental disorders have their typical onset between 12 and 25 years of age, making this period a critical window for prevention and early intervention.47 The transition from child and adolescent mental health services to adult mental health services often occurs during the same developmental period in which attenuated psychotic symptoms emerge, creating a potential risk of fragmentation precisely when continuity of care may be most needed. This organisational and developmental hiatus has been described as a major barrier to continuity of care and one of the key challenges that youth-oriented early intervention services may help overcome.48
In decentralised healthcare systems such as ours, these transitions may be further complicated by differences in organisational structures, referral pathways, and clinical cultures across services. In this context, effective early intervention required not only specialised assessment protocols, but also active coordination between child/adolescent and adult teams, flexibility regarding age boundaries, and a stronger focus on continuity, engagement, and functional recovery throughout the broader developmental trajectory of young people. These experiences support the growing relevance of youth mental health approaches that aim to overcome traditional service divisions and provide more integrated care during critical transitional stages of illness development.48,49 These aspects are often underrepresented in international guidelines, despite having substantial impact on the feasibility and sustainability of real-world service implementation. Thus, addressing these challenges may be particularly important for public healthcare systems attempting to scale up early psychosis prevention services beyond highly specialised academic centres. By facilitating earlier identification, improving coordination between referral sources, and streamlining access to specialised assessment, these implementation strategies may also contribute to reducing delays in access to care and potentially minimising the DUP in decentralised healthcare systems
At the same time, several limitations should be acknowledged. This work does not aim to evaluate the clinical efficacy of the programme, and the number of individuals clinically attended remains relatively limited, reflecting the early developmental phase of the service. Furthermore, the lessons presented were derived from an experience-based and consensus-driven process rather than from formal implementation science methodologies such as Delphi procedures or qualitative thematic analysis. The present reflections should therefore be interpreted as pragmatic implementation insights rather than definitive evidence-based recommendations.
Nevertheless, these reflections may contribute to the growing literature on the implementation of CHR-P services by illustrating the organisational adaptations, coordination strategies, and contextual challenges involved in translating early intervention principles into routine clinical practice. This may be particularly relevant for decentralised public healthcare systems or regions with limited previous CHR-P infrastructure, where implementation often depends on progressive integration within existing mental health networks rather than on the immediate development of highly specialised standalone services.
Future research should further evaluate the long-term sustainability, scalability, and clinical outcomes of these models, as well as the impact of implementation strategies on accessibility, continuity of care, and functional recovery in young people at risk of psychosis.
ConclusionThis work synthesises practical lessons derived from the early implementation of the PREGAP programme, offering an experience-based and implementation-oriented perspective on the development of CHR-P services within a decentralised public healthcare system. Beyond specific clinical strategies, the present reflections highlight the importance of flexible referral networks, multidisciplinary collaboration, youth-oriented continuity of care, cultural sensitivity, and progressive integration within existing mental health structures when developing early psychosis prevention services.
The PREGAP experience suggests that implementing CHR-P care involves not only the application of evidence-based recommendations, but also their adaptation to the organisational, cultural, and resource-related realities of each healthcare context. In this regard, implementation may depend as much on coordination, accessibility, and sustainability as on diagnostic sophistication or specialised interventions alone.
Although the present work does not aim to establish definitive evidence-based recommendations, these reflections may contribute to the growing literature on the real-world implementation of early psychosis services, particularly in regions with limited previous CHR-P infrastructure. With appropriate contextual adaptation, the principles described here may help inform the development of more integrated, accessible, and developmentally informed models of care for young people at risk of psychosis.
Ethical considerationsThis article is based on the practical experience of the PREGAP programme and does not involve the collection of new experimental data from human participants. All descriptions are drawn from routine clinical practice and team discussions. For the empirical studies cited, including those previously published with data derived from PREGAP, ethical approval was obtained from the Ethics Committee of the Basque Country, and written informed consent was secured from all participants in accordance with the Declaration of Helsinki.
FundingBorja Pedruzo was supported by the Biobizkaia PostMIR Fellowship 2024-2025 (Grant Number: BB/I/PMIR/24/002). Claudia Aymerich was funded by the Alicia Koplowitz Foundation. The publication of this article was funded by the Biobizkaia Health Research Institute with resources from the Research Commission of OSI Bilbao Basurto.
Dr. Pedruzo reports having received support to attend scientific meetings from Janssen, ROVI, and Lundbeck in the last five years. Dr. Aymerich is supported by the Alicia Koplowitz Foundation and has received personal fees or grants from Janssen-Cilag and Neuraxpharm, outside the current work. Dr. Salazar de Pablo has received personal fees from Janssen-Cilag and Menarini. Dr. Catalán reports having received support to attend scientific meetings from Janssen, ROVI, and Lundbeck in the last five years. She is also supported by the Instituto de Salud Carlos III, Spanish Ministry of Economy and Competitiveness. All other authors report no biomedical financial interests or potential conflicts of interest.

