




The main objective of the study is to evaluate the performance of the FilmArray® Pneumonia Plus (FA-PP) panel in critically ill patients with suspected pneumonia compared to conventional culture, in both pandemic and pospandemic periods, and its impact on therapeutic decision-making.
MethodsObservational study including 225 patients (314 samples) during COVID-19 pandemic and post-pandemic periods. FA-PP and culture results were compared assessing sensitivity (Se), specificity, predictive values, level of concordance between them and the impact on antibiotic prescription.
ResultsFA-PP detected 133% more bacterial targets than culture and 48% more positive samples. Excluding off-panel bacteria, the panel showed high sensitivity of up to 100% in patients with pneumonia and a negative predictive value (NPV) of over 98%. In the post-pandemic period, the overall Se (78.6%) and Se in patients with pneumonia (81%), as well as the overall NPV and in pneumonia (94%), were higher than in the pandemic period, with significant differences (p<0.05). Twenty-six per cent of pneumonia episodes involved bacteria not included in the panel. The positive concordance between the two tests was 72%. In 56% of cases with pneumonia, antibiotic was modified after the results. During the pandemic period, the panel served to modify treatment towards initiation or escalation.
ConclusionsThe FA-PP is a valuable tool for optimizing the diagnosis and management of pneumonia in the ICU, with a clinical impact on the appropriateness of antibiotic treatment. There were differences in the impact of the panel between the pandemic and post-pandemic periods.
El principal objetivo del estudio es valuar el rendimiento del panel sindrómico FilmArray® Pneumonia Plus (FA-PP) en pacientes críticos con sospecha de neumonía, comparado con el cultivo convencional, y su impacto en la toma de decisiones sobre el tratamiento antibiótico empírico.
MétodosEstudio observacional en 225 pacientes (314 muestras) en periodo pandémico y pos-pandémico COVID-19. Se compararon resultados de FA-PP y cultivo, calculando sensibilidad (Se), especificidad (E), valores predictivos y concordancia y el impacto del panel en el tratamiento antibiótico empírico.
ResultadosEl FA-PP detectó 133% más dianas bacterianas que el cultivo y un 48% más de muestras positivas. Excluyendo las bacterias sin diana, el panel mostró alta sensibilidad, hasta un 100% en pacientes con neumonía y un valor predictivo negativo (NPV) superior al 98%. En el periodo pos-pandémico, la Se global (78,6%) y en pacientes con neumonía (81%) y el NPV global y con neumonía (94%) fueron mayores que en el pandémico, con diferencias significativas (p<0.05). El 26% de los episodios de neumonía involucraron bacterias no incluidas en el panel. La concordancia positiva entre ambas pruebas del 72%. En un 56% de los casos con neumonía se modificó el antibiótico tras los resultados. En período pandémico, el panel sirvió para modificar el tratamiento hacia el inicio o escalada.
ConclusionesEl FA-PP constituye una herramienta valiosa para optimizar el diagnóstico y manejo de la neumonía en UCI, con impacto clínico en la adecuación del tratamiento antibiótico. Hubo diferencias en el impacto del panel entre período pandémico y pos-pandémico.
The concept of early targeted antimicrobial therapy, or early adjustment of empirical antimicrobial treatment, is aimed at the rapid identification of the causative bacteria and the prompt optimization of empirical antibiotic regimens. In recent years, rapid microbiological diagnostic techniques based on polymerase chain reaction (PCR) have been developed, employing multiplex panels capable of detecting a broad range of bacterial and fungal targets. The integration of molecular diagnostics into the clinical management of patients with severe infections has substantially improved therapeutic decision-making,1,2 and has even allowed the development of evidence-based algorithms that incorporate test results while taking into account patient-specific factors and the resources available at each institution.3–5 Therefore, it is essential that each institution assess the performance of these techniques, ensure their appropriate implementation, and evaluate their potential impact on clinical outcomes relative to conventional culture-based methods.
This study, conducted at Miguel Servet University Hospital (HUMS), aimed to assess the clinical utility of the multiplex syndromic PCR panel (FilmArray Pneumonia Plus, BioFire® Diagnostics; hereafter FA-PP) for the early diagnosis of severe pneumonia in patients admitted to the intensive care unit (ICU). We analyzed the correlation between FA-PP results and those obtained from semiquantitative cultures of broncoalveolar lavage (BAL) or tracheal aspirate (TA) specimens, which were considered the reference standard. In addition, we compared findings across two distinct periods: the COVID-19 pandemic (2020–2022) and the post-pandemic phase (2023–2024). The potential confounding effect of prior antibiotic exposure at the time of sampling was also examined for both diagnostic methods. Moreover, we evaluated the impact of FA-PP results on antibiotic management and therapeutic adjustment patterns were compared between 2020–2022 and 2023–2024.
Materials and methodsWe conducted a retrospective, descriptive study of patients admitted to the intensive care unit (ICU) of Miguel Servet University Hospital with an initial suspicion of severe pneumonia, between March 2020 and December 2024. Data collected included ICU length of stay (days), time from ICU admission to respiratory sample collection and FA-PP testing, patient COVID-19 status, type of pneumonia (community-acquired pneumonia [CAP], aspiration pneumonia [AP], nosocomial pneumonia [NP], and ventilator-associated pneumonia [VAP]), other infectious and non-infectious diagnoses, and antimicrobial prescriptions both before and after respiratory sampling (S0 see supplementary materials).
We retrospectively assessed the rapid results provided by the FA-PP panel (<3h) and compared them with those obtained from routine semiquantitative culture (definitive at 48h, including susceptibility testing), using only respiratory samples from TA and BAL. Only samples for which both FA-PP and culture were performed simultaneously were included. Conventional culture was considered the diagnostic reference standard, although its sensitivity is reduced in the presence of prior antibiotic exposure. To address this limitation, concordance indices between both methods were also calculated.
All BAL were included as well as all tracheal aspirates with high quality features (Gram staining and semiquantitative cultures). Culture results were interpreted semiquantitatively based on bacterial load,5–7 with a threshold of ≥104CFU/mL for BAL and ≥105CFU/mL for TA. Cultures positive for Legionella, did not apply quantification criteria. Likewise, FA-PP results were interpreted as positive when copy numbers ranged between 104 and 107copies/mL, as described in previous studies.8,9 “Off-panel” bacteria were defined as organisms not targeted by FA-PP but nevertheless considered clinically relevant for final antimicrobial management. Three analyses were performed:
- 1.
Sample-level analysis was performed to calculate the sensitivity and specificity of FA-PP relative to semiquantitative culture (without excluding off-panel bacteria), both for the entire cohort and for patients with a final diagnosis of pneumonia. True positives (TP) were defined as concordant positive results (including partial concordance), true negatives (TN) as concordant negatives, false positives (FP) as FA-PP positive/culture negative, and false negatives (FN) as FA-PP negative/culture positive. The Youden index and likelihood ratios with 95% confidence intervals were also calculated.
- 2.
Pathogen-level analysis assessed the diagnostic sensitivity and specificity of FA-PP for each microorganism detected.
- 3.
Concordance analysis described negative agreement (FA-PP negative with culture negative or ≤103CFU/mL), positive agreement (FA-PP positive with culture positive: BAL ≥104CFU/mL; TA ≥105CFU/mL), and overall agreement (negative plus positive) between the two methods, as previously defined by Murphy et al. and Buchan et al.8,9
We further examined the potential impact of FA-PP results on immediate antibiotic management. The appropriateness or adequacy of the treatment has not been studied. Antibiotic prescriptions before and after FA-PP reporting were reviewed and categorized according to established definitions9,10: initiation (starting a new regimen), escalation (broadening the spectrum or adding an agent), de-escalation (narrowing the spectrum), continuation (no change), and discontinuation (withdrawal of all antibiotics). The proportion of patients in whom therapy was modified based on FA-PP findings was calculated. The decision to initiate, continue, escalate, or de-escalate antibiotics after FA-PP results was left to the discretion of the attending physician.
Statistical analyses were performed using SPSS v.20 and Epidat 3.1. A significance threshold of p<0.05 was applied. For categorical variables, chi-square testing with Bonferroni correction was used, while quantitative variables were analyzed with Student's t test and ANOVA for comparison of means. Because some patients contributed more than one respiratory sample during their ICU stay, each sample was analysed as an independent diagnostic episode. When multiple samples originated from the same patient, they were included independently for diagnostic performance analyses. To account for potential within-patient correlation, antibiotic modifications were summarized per patient (Table S5).
The study was approved by the Research Ethics Committee of the Autonomous Community of Aragon (protocol C.I. PI24/468, December 10, 2024). All authors had full access to the study data and reviewed and approved the final manuscript.
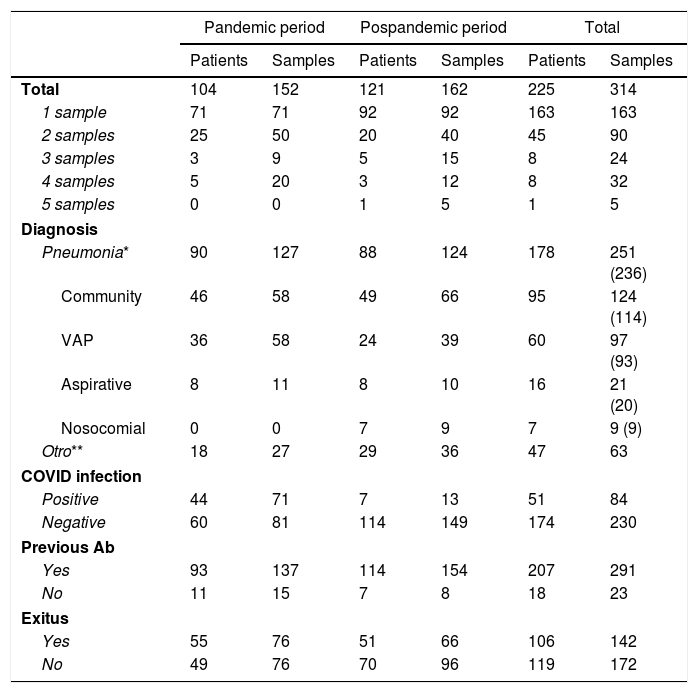
ResultsWe included 225 patients with suspected pneumonia, yielding 314 respiratory samples (65 TA and 249 BAL). The mean ICU length of stay was 38.97 days (range 0–167), with 49.83 days (±3.36; 0–167) during the pandemic period and 29.29 days (±2.93; 1–149) in the post-pandemic period (p=0.0001). The mean time from ICU admission to FA-PP testing was 13.36 days (±1.7; 0–96) during the pandemic and 8.68 days (±1.4; 0–121) post-pandemic (p=0.005).
Of the 225 patients, 178 were ultimately diagnosed with pneumonia, with a similar total number of cases across both periods. Fifty-one patients were COVID-19 positive, representing 42% of patients during the pandemic and 5.8% post-pandemic (p=0.000). Among the 178 pneumonia patients, 251 samples were collected. Most samples (236/251; 94%) were from patients who had received prior antibiotic therapy, and 200 of these cultures were negative (84.75%). All but 18 patients received at least one dose of antibiotics prior to FA-PP testing (92%) (Table 1).
Baseline characteristics of patients and respiratory samples.
| Pandemic period | Pospandemic period | Total | ||||
|---|---|---|---|---|---|---|
| Patients | Samples | Patients | Samples | Patients | Samples | |
| Total | 104 | 152 | 121 | 162 | 225 | 314 |
| 1 sample | 71 | 71 | 92 | 92 | 163 | 163 |
| 2 samples | 25 | 50 | 20 | 40 | 45 | 90 |
| 3 samples | 3 | 9 | 5 | 15 | 8 | 24 |
| 4 samples | 5 | 20 | 3 | 12 | 8 | 32 |
| 5 samples | 0 | 0 | 1 | 5 | 1 | 5 |
| Diagnosis | ||||||
| Pneumonia* | 90 | 127 | 88 | 124 | 178 | 251 (236) |
| Community | 46 | 58 | 49 | 66 | 95 | 124 (114) |
| VAP | 36 | 58 | 24 | 39 | 60 | 97 (93) |
| Aspirative | 8 | 11 | 8 | 10 | 16 | 21 (20) |
| Nosocomial | 0 | 0 | 7 | 9 | 7 | 9 (9) |
| Otro** | 18 | 27 | 29 | 36 | 47 | 63 |
| COVID infection | ||||||
| Positive | 44 | 71 | 7 | 13 | 51 | 84 |
| Negative | 60 | 81 | 114 | 149 | 174 | 230 |
| Previous Ab | ||||||
| Yes | 93 | 137 | 114 | 154 | 207 | 291 |
| No | 11 | 15 | 7 | 8 | 18 | 23 |
| Exitus | ||||||
| Yes | 55 | 76 | 51 | 66 | 106 | 142 |
| No | 49 | 76 | 70 | 96 | 119 | 172 |
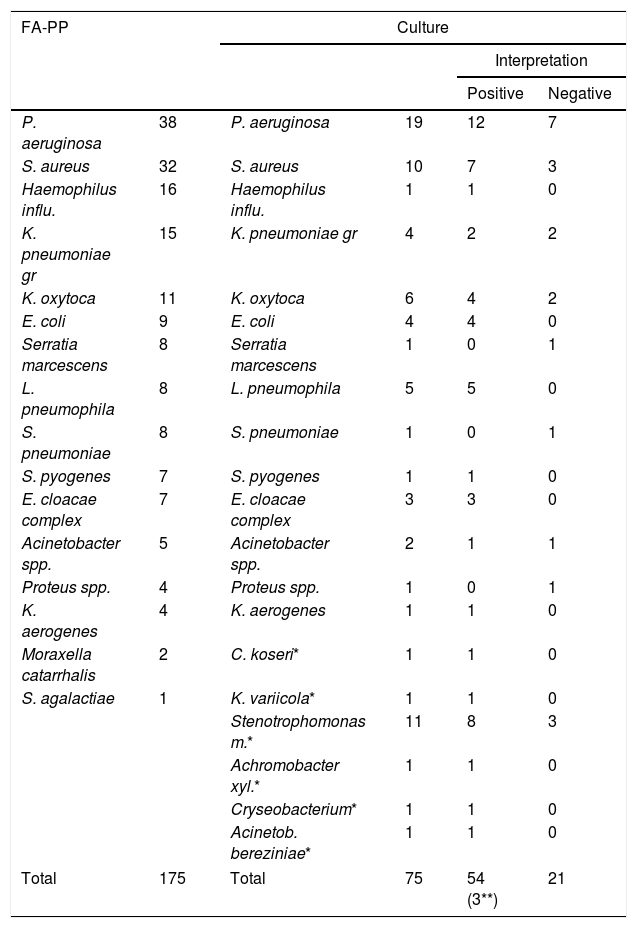
Across all 314 samples, FA-PP detected 175 bacterial pathogens compared to 75 detected by culture. FA-PP identified ≥3 microorganisms in 3.5% of samples (11 samples, 5 BAL: 1 AP, 1 VAP, 1 CAP, 2 bacteremia and 6 TA: 3 CAP, 1 NP, 1 VAP, 1 no infection). The overall positivity rate per sample for FA-PP was 42.6% (134/314). The most frequently detected bacteria were Pseudomonas aeruginosa (n=38) and Staphylococcus aureus (n=32). Of the 16 Haemophilus influenzae detected by FA-PP, only one was confirmed positive by culture (Table 2).
Total number of samples and bacteria detected by FA-PP and conventional culture.
| FA-PP | Culture | ||||
|---|---|---|---|---|---|
| Interpretation | |||||
| Positive | Negative | ||||
| P. aeruginosa | 38 | P. aeruginosa | 19 | 12 | 7 |
| S. aureus | 32 | S. aureus | 10 | 7 | 3 |
| Haemophilus influ. | 16 | Haemophilus influ. | 1 | 1 | 0 |
| K. pneumoniae gr | 15 | K. pneumoniae gr | 4 | 2 | 2 |
| K. oxytoca | 11 | K. oxytoca | 6 | 4 | 2 |
| E. coli | 9 | E. coli | 4 | 4 | 0 |
| Serratia marcescens | 8 | Serratia marcescens | 1 | 0 | 1 |
| L. pneumophila | 8 | L. pneumophila | 5 | 5 | 0 |
| S. pneumoniae | 8 | S. pneumoniae | 1 | 0 | 1 |
| S. pyogenes | 7 | S. pyogenes | 1 | 1 | 0 |
| E. cloacae complex | 7 | E. cloacae complex | 3 | 3 | 0 |
| Acinetobacter spp. | 5 | Acinetobacter spp. | 2 | 1 | 1 |
| Proteus spp. | 4 | Proteus spp. | 1 | 0 | 1 |
| K. aerogenes | 4 | K. aerogenes | 1 | 1 | 0 |
| Moraxella catarrhalis | 2 | C. koseri* | 1 | 1 | 0 |
| S. agalactiae | 1 | K. variicola* | 1 | 1 | 0 |
| Stenotrophomonas m.* | 11 | 8 | 3 | ||
| Achromobacter xyl.* | 1 | 1 | 0 | ||
| Cryseobacterium* | 1 | 1 | 0 | ||
| Acinetob. bereziniae* | 1 | 1 | 0 | ||
| Total | 175 | Total | 75 | 54 (3**) | 21 |
Among the 314 samples, bacteria were isolated by culture in 71 samples; however, only 54 of these met the quantitative threshold to be considered truly positive. The overall culture negativity rate was 83%. A total of 75 bacterial isolates were identified. The most frequently isolated pathogen was P. aeruginosa (19 samples), followed by Stenotrophomonas maltophilia (11 samples) and S. aureus (10 samples).
Of the 21 bacteria detected by culture but interpreted as negative, all except three S. maltophilia isolates at 103CFU/mL were identified by FA-PP ≥104copies/mL. Notably, 33% of negative culture interpretations corresponded to P. aeruginosa. It is also important to note the presence of polymicrobial cultures in which some isolates did not reach significant quantification (see S1 and S2 supplementary material).
Compared with conventional bacterial culture, the FA-PP panel increased the number of positive samples by 48% and the total number of bacterial targets detected by 133%. In addition to detecting 167 bacterial pathogens and 8 Legionella pneumophila serogroup I (5 confirmed by culture), FA-PP identified 39 viral agents, including 14 Rhinovirus/Enterovirus, 13 Influenza A, 3 Metapneumovirus, 3 Parainfluenza, 3 non-COVID Coronaviruses, 2 Influenza B, and 1 Respiratory Syncytial Virus. In 15 samples, only viral targets were detected.
“Off-panel” bacteria accounted for 24% (13/54) of culture-isolated bacteria considered relevant for antibiotic therapy. Among the 42 positive cultures from pneumonia patients, 11 isolates were “off-panel” bacteria (6 Stenotrophomonas, 1 Acinetobacter bereziniae, 1 Achromobacter, 1 Citrobacter koseri, 1 Klebsiella variicola, and 1 Chryseobacterium sp.), representing 26.2% of pneumonia episodes with positive cultures. The most frequently isolated “off-panel” bacterium in quantitative culture was S. maltophilia (15%; 8/54).
Of the 178 patients diagnosed with pneumonia, 163 (93%) received at least one dose of antibiotics prior to FA-PP testing. The most commonly prescribed empiric antibiotics were meropenem, linezolid, cotrimoxazole, levofloxacin, and azithromycin. Among the 225 patients, 117 had received meropenem prior to testing, of whom 61 received a combination of meropenem and linezolid (53 with a final diagnosis of pneumonia).
During the pandemic period, 95.5% of COVID-19-positive patients had received prior antibiotics, compared with 100% in the post-pandemic period.
Comparative performance of FA-PP and conventional cultureAmong the 314 respiratory samples, 44 were positive by both methods (14.0%; 40 with concordant pathogens), and 172 were negative by both methods (55.4%). FA-PP-positive/culture-negative results were observed in 91 samples (28.3%), whereas FA-PP-negative/culture-positive results occurred in 7 samples (2.2%). The overall FA-PP positivity rate was 43%.
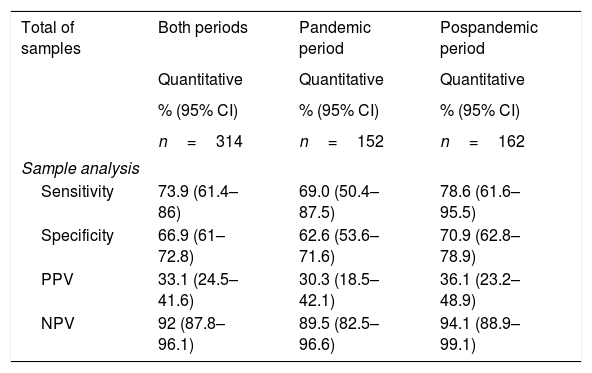
Overall, the FA-PP panel demonstrated moderate diagnostic performance, with a sensitivity (Se) of 73.9%, specificity (Sp) of 66.9%, positive predictive value (PPV) of 33%, and negative predictive value (NPV) of 92%. Stratification by period revealed improved performance in the post-pandemic phase, with Se 78.6%, Sp 70.9%, PPV 36%, and NPV 94%. In samples from patients with a final pneumonia diagnosis, similar trends were observed though Se, Sp, and PPV were slightly lower (Table 3).
Diagnostic performance of the FA-PP panel versus culture: per-sample quantitative analysis by period.
| Total of samples | Both periods | Pandemic period | Pospandemic period |
|---|---|---|---|
| Quantitative | Quantitative | Quantitative | |
| % (95% CI) | % (95% CI) | % (95% CI) | |
| n=314 | n=152 | n=162 | |
| Sample analysis | |||
| Sensitivity | 73.9 (61.4–86) | 69.0 (50.4–87.5) | 78.6 (61.6–95.5) |
| Specificity | 66.9 (61–72.8) | 62.6 (53.6–71.6) | 70.9 (62.8–78.9) |
| PPV | 33.1 (24.5–41.6) | 30.3 (18.5–42.1) | 36.1 (23.2–48.9) |
| NPV | 92 (87.8–96.1) | 89.5 (82.5–96.6) | 94.1 (88.9–99.1) |
| Samples from patients with pneumonia | Both periods | Pandemic period | Pospandemic period |
|---|---|---|---|
| Quantitative | Quantitative | Quantitative | |
| % (95% CI) | % (95% CI) | % (95% CI) | |
| n=251 | n=125 | n=126 | |
| Sample analysis | |||
| Sensitivity | 72.7 (58.4–87) | 65.2 (43.6–86.9) | 81 (61.8–100) |
| Specificity | 63.7 (57–70.6) | 57.8 (47.7–67.9) | 69.5 (60.2–78.8) |
| PPV | 30 (20.7–39) | 25.8 (13.7–38) | 34.7 (20.3–49) |
| NPV | 91.7 (86.8–96.5) | 88.1 (79.5–96.6) | 94.8 (89.2–100) |
| Samples from patients with pneumoniaExcluded off-panel bacteria | Pandemic | Pospandemic |
|---|---|---|
| Quantitative | Quantitative | |
| % (95% CI) | % (95% CI) | |
| n=117 | n=122 | |
| Sample analysis | ||
| Sensitivity | 100 (96.7–100) | 94.1 (80–100) |
| Specificity | 57.8 (47.7–68) | 69.5 (60.2–78.8) |
| PPV | 25.9 (13.7–38) | 33.3 (19–47.7) |
| NPV | 100 (99.1–100) | 98.6 (95.3–100) |
During the pospandemic period, both overall Se (78.6%) and Se in pneumonia patients (81%), as well as overall NPV and NPV in pneumonia (94%), were higher than in the pandemic period, with statistically significant differences (p<0.05). In this cohort and during the pandemic period, exclusion of off-panel microorganisms from the analysis yielded Se and NPV of 100% (Table 3). Analysis per microorganism was also done (S3 supplementary materials).
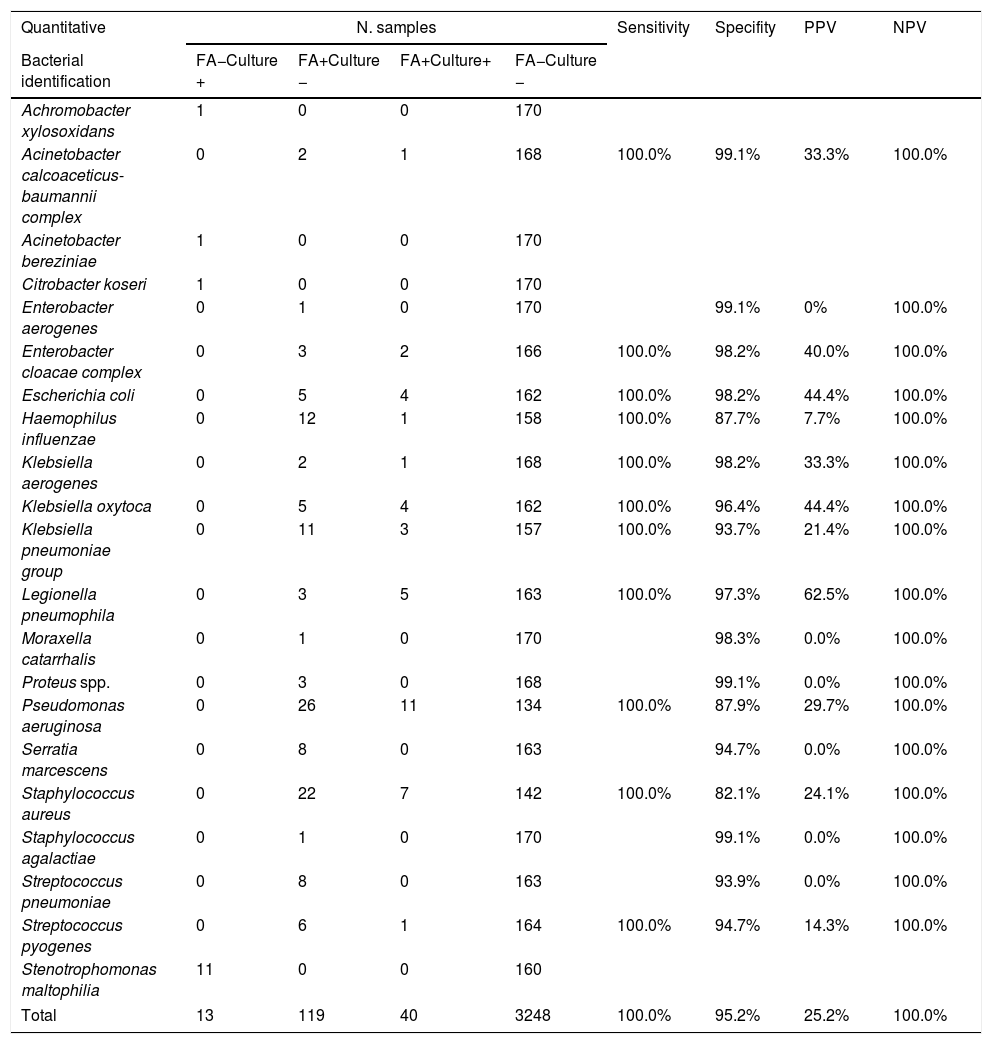
For all samples, including those from pneumonia patients, high Se and Sp values >90% were observed for each microorganism targeted by the panel (Table 4).
Sensitivity and specificity by bacterial species according to FA-PP and culture results.
| Quantitative | N. samples | Sensitivity | Specifity | PPV | NPV | |||
|---|---|---|---|---|---|---|---|---|
| Bacterial identification | FA−Culture + | FA+Culture − | FA+Culture+ | FA−Culture − | ||||
| Achromobacter xylosoxidans | 1 | 0 | 0 | 170 | ||||
| Acinetobacter calcoaceticus-baumannii complex | 0 | 2 | 1 | 168 | 100.0% | 99.1% | 33.3% | 100.0% |
| Acinetobacter bereziniae | 1 | 0 | 0 | 170 | ||||
| Citrobacter koseri | 1 | 0 | 0 | 170 | ||||
| Enterobacter aerogenes | 0 | 1 | 0 | 170 | 99.1% | 0% | 100.0% | |
| Enterobacter cloacae complex | 0 | 3 | 2 | 166 | 100.0% | 98.2% | 40.0% | 100.0% |
| Escherichia coli | 0 | 5 | 4 | 162 | 100.0% | 98.2% | 44.4% | 100.0% |
| Haemophilus influenzae | 0 | 12 | 1 | 158 | 100.0% | 87.7% | 7.7% | 100.0% |
| Klebsiella aerogenes | 0 | 2 | 1 | 168 | 100.0% | 98.2% | 33.3% | 100.0% |
| Klebsiella oxytoca | 0 | 5 | 4 | 162 | 100.0% | 96.4% | 44.4% | 100.0% |
| Klebsiella pneumoniae group | 0 | 11 | 3 | 157 | 100.0% | 93.7% | 21.4% | 100.0% |
| Legionella pneumophila | 0 | 3 | 5 | 163 | 100.0% | 97.3% | 62.5% | 100.0% |
| Moraxella catarrhalis | 0 | 1 | 0 | 170 | 98.3% | 0.0% | 100.0% | |
| Proteus spp. | 0 | 3 | 0 | 168 | 99.1% | 0.0% | 100.0% | |
| Pseudomonas aeruginosa | 0 | 26 | 11 | 134 | 100.0% | 87.9% | 29.7% | 100.0% |
| Serratia marcescens | 0 | 8 | 0 | 163 | 94.7% | 0.0% | 100.0% | |
| Staphylococcus aureus | 0 | 22 | 7 | 142 | 100.0% | 82.1% | 24.1% | 100.0% |
| Staphylococcus agalactiae | 0 | 1 | 0 | 170 | 99.1% | 0.0% | 100.0% | |
| Streptococcus pneumoniae | 0 | 8 | 0 | 163 | 93.9% | 0.0% | 100.0% | |
| Streptococcus pyogenes | 0 | 6 | 1 | 164 | 100.0% | 94.7% | 14.3% | 100.0% |
| Stenotrophomonas maltophilia | 11 | 0 | 0 | 160 | ||||
| Total | 13 | 119 | 40 | 3248 | 100.0% | 95.2% | 25.2% | 100.0% |
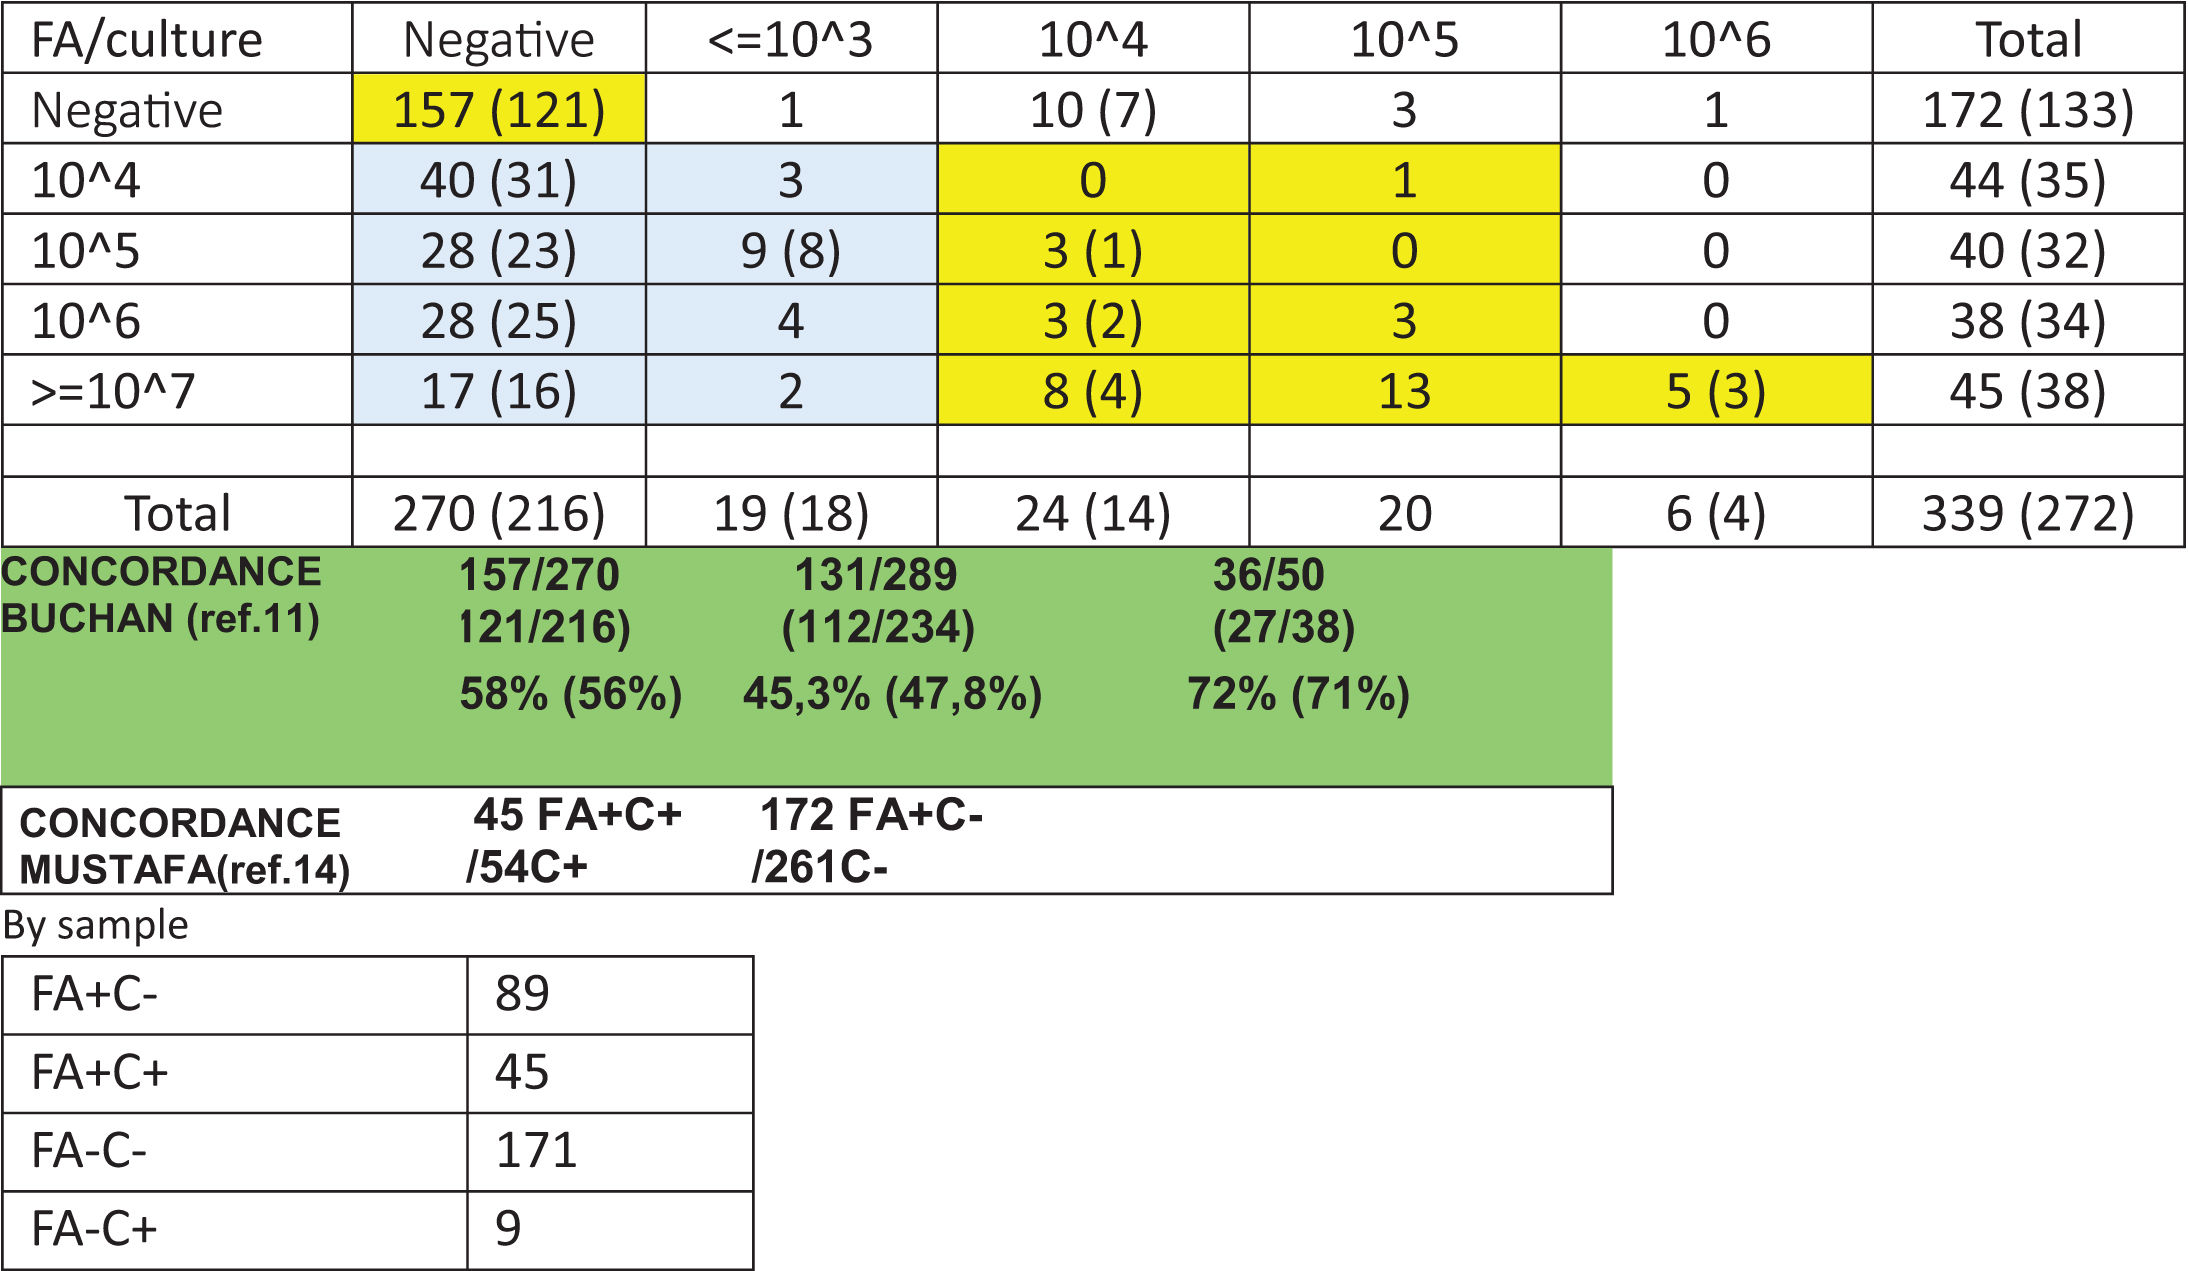
Following the methodology of Buchan et al.,9 negative concordance between FA-PP and culture at the microorganism level was 58%, and positive concordance was 72%, yielding an overall concordance of 66%. Excluding off-panel microorganisms, positive concordance increased to 97.3%. Notably, 45% of samples were FA-PP positive but culture negative (Table 5).

Using the sample-level concordance approach recommended by Mustafa et al.,11 negative concordance was 66% and positive concordance 83.3%, with 28% of samples FA-PP positive and culture negative.
Among the 314 included samples, all 54 panel-target bacteria that grew in culture were detected by FA-PP. Concordance was 100% for monomicrobial cultures (46/46), but only 44% for polymicrobial cultures or samples with multiple panel targets. Two samples showed species-level discrepancies: in one tracheal aspirate, the panel detected K. pneumoniae ≥107copies/mL while culture yielded P. aeruginosa at 105CFU/mL; in one BAL, the panel result was K. pneumoniae ≥107copies/mL whereas K. variicola at 105CFU/mL was isolated in culture.
Impact on empirical antibiotic therapyAcross all samples, antibiotic therapy was modified in 55% of cases following FA-PP reporting: 61% during the pandemic versus 51% post-pandemic (p=0.15). In the subset of pneumonia patients, 56% of cases underwent therapy modification, whereas in the post-pandemic period only 44% were adjusted (S4 supplementary material).
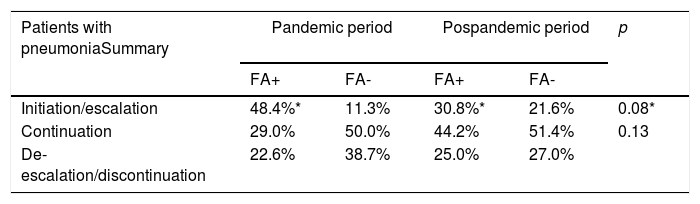
For positive FA-PP results, the most frequent action during the pandemic was escalation (48.4%), compared to continuation (44.2%) post-pandemic (p=0.08). Negative FA-PP results led to therapy continuation in both periods (50% and 51.4%, respectively) (Table 6a). Among 15 FA-PP-positive samples without prior antibiotics, therapy was initiated in 13 cases and maintained in 2 (K. oxytoca and S. aureus).
Interventions according to type of FA-PP result in the pandemic and post-pandemic periods.
Therapeutic adjustments following positive FA-PP results were similar between COVID-positive and COVID-negative patients. Negative results prompted de-escalation or discontinuation slightly less frequently in COVID patients, without statistical significance (S5 supplementary materials).
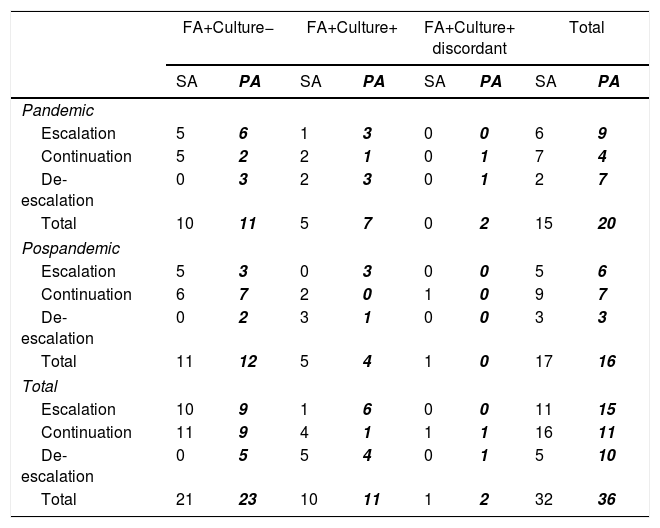
Analysis by pathogen revealed that for S. aureus or P. aeruginosa, initiation or escalation predominated over de-escalation during the pandemic (43% vs. 26%), while maintenance predominated in the pospandemic period (48% vs. 18%) (Table 6b). For P. aeruginosa, 35% of therapies were de-escalated during the pandemic versus 18.8% post-pandemic (p<0.05). For S. aureus, therapy was maintained in 50% of positive cases, despite methicillin resistance detected in only one patient.
Interventions for positive FA-PP results S. aureus (regular font) and Pseudomonas aeruginosa (bold italics) by period.
| FA+Culture− | FA+Culture+ | FA+Culture+ discordant | Total | |||||
|---|---|---|---|---|---|---|---|---|
| SA | PA | SA | PA | SA | PA | SA | PA | |
| Pandemic | ||||||||
| Escalation | 5 | 6 | 1 | 3 | 0 | 0 | 6 | 9 |
| Continuation | 5 | 2 | 2 | 1 | 0 | 1 | 7 | 4 |
| De-escalation | 0 | 3 | 2 | 3 | 0 | 1 | 2 | 7 |
| Total | 10 | 11 | 5 | 7 | 0 | 2 | 15 | 20 |
| Pospandemic | ||||||||
| Escalation | 5 | 3 | 0 | 3 | 0 | 0 | 5 | 6 |
| Continuation | 6 | 7 | 2 | 0 | 1 | 0 | 9 | 7 |
| De-escalation | 0 | 2 | 3 | 1 | 0 | 0 | 3 | 3 |
| Total | 11 | 12 | 5 | 4 | 1 | 0 | 17 | 16 |
| Total | ||||||||
| Escalation | 10 | 9 | 1 | 6 | 0 | 0 | 11 | 15 |
| Continuation | 11 | 9 | 4 | 1 | 1 | 1 | 16 | 11 |
| De-escalation | 0 | 5 | 5 | 4 | 0 | 1 | 5 | 10 |
| Total | 21 | 23 | 10 | 11 | 1 | 2 | 32 | 36 |
SA: S. aureus; PA: P. aeruginosa.
Considering the hospital-specific epidemiology and microbiological patterns, and the two periods defined by COVID-19 incidence, this study evaluated not only diagnostic concordance but also the impact on clinical decision-making in complex, dynamic scenarios.
The study was conducted primarily on BAL samples (249), confirming their suitability and yielding results partially consistent with recent literature.11,12 This contrasts with studies including larger numbers of sputum and tracheal aspirates,5,13,14 which may differ in sensitivity and bacterial diversity detected by the panel. Importantly, over 90% of patients received at least one antibiotic dose prior to sampling, impacting culture results.
Diagnostic performance of FA-PP versus conventional cultureThe FA-PP panel demonstrated high sensitivity and, notably, a consistently high negative predictive value (NPV), maintained across different epidemiological periods and in patients with a final diagnosis of pneumonia.
The overall sample positivity rate was 42.6%. FA-PP detected 175 bacterial pathogens, compared with only 75 identified by conventional culture. Consequently, the panel's sensitivity for detecting bacteria in critically ill patients with suspected pneumonia – most of whom were receiving antibiotic therapy – was approximately twice that of culture. The apparent specificity may be underestimated, as culture can yield false-negative results in the presence of prior antibiotic treatment. Local epidemiology, including a substantial proportion of off-panel bacteria, resulted in an overall sensitivity of 74% and NPV of 92%, with similar figures in patients ultimately diagnosed with pneumonia, highlighting the panel's utility in ruling out bacterial infection. These findings align with recently published real-world studies reporting a global panel positivity of 44.8%.11,15
Previous reports14,16–18 have described sensitivities and specificities approaching 100% in COVID-19 and oncology patients, often prompting initiation or escalation of antibiotics. In our cohort, during the pandemic, sensitivity and NPV – excluding off-panel microorganisms – reached 100% in pneumonia samples, although specificity and positive predictive value (PPV) remained low. This likely reflects the reduced culture yield associated with prior antibiotic exposure, considering that respiratory samples were obtained, on average, 13 days after ICU admission.
Compared with conventional bacterial culture, FA-PP increased the number of positive samples by 48% and the total number of bacterial targets detected by 133%. These results are consistent with other studies and recent meta-analyses,5,11,13,19 reinforcing the role of rapid molecular diagnostics as a reliable tool to exclude bacterial infection and optimize empiric therapy in critically ill patients, particularly for P. aeruginosa and S. aureus. Our findings corroborate prior multicenter studies demonstrating that FA-PP significantly enhances bacterial identification rates and shortens diagnostic turnaround times.8,9,20 Additionally, Rand et al.6 showed that bacterial loads of 106–107copies/mL correlate well with causality as determined by conventional culture, whereas lower loads (104–105copies/mL) were most predictive when specific pathogens such as P. aeruginosa and S. aureus were detected.
Diagnostic concordanceConsistent with Buchan et al.,9 negative concordance between FA-PP and culture was moderate (58%), whereas positive concordance was higher (72%), with 45% of samples FA-PP positive/culture negative, highlighting the superior capacity of FA-PP to detect pathogens in patients receiving antibiotics or with low bacterial loads. Comparable studies report positive concordance of 45.2%.11,15 Mustafa et al.11 found 21% FA-PP positive/culture negative, 2.4% culture positive/FA-PP negative, and 31.4% negative in both methods in COVID-19 VAP patients, similar to our 28% and 2.2% findings. This pattern is explained by prior antibiotic therapy (present in 92% of our cohort vs. up to 75% in literature), differences in bacterial quantification, with optimal correlation at ≥106copies/mL (panel) and ≥105CFU/μL (culture),13,15 and potential colonization without active infection.21 Over-detection of H. influenzae (16 cases) was observed, as described in the literature, reflecting the high sensitivity of FA-PP to oral flora bacteria.3,8,9,22 Only in four cases – two catheter-related bloodstream infections, one abdominal sepsis, and one case without infection – did the panel detect concentrations ≥106copies/ml in respiratory samples (one BAL and three tracheal aspirates, respectively) (see Table 5).
Overall concordance based on culture quantification was 66%. Notably, P. aeruginosa was isolated in one-third of cultures deemed negative, despite positive panel detection, underscoring the importance of integrating molecular and conventional results in clinical practice. Culture also identified off-panel pathogens, such as S. maltophilia, accounting for 26% of VAP episodes, consistent with other reports.1,9,19,23,24 The FA-PP is constrained by its closed target list, which does not include clinically important pathogens such as Aspergillus spp. or S. maltophilia, potentially limiting its standalone utility in immunocompromised patients or in those at risk for infections caused by emerging pathogens. This gap is particularly relevant in ventilator-associated pneumonia (VAP), where extensive carbapenem use may shape the microbiological ecology toward organisms not covered by the panel, thereby diminishing its usefulness.
Clinical and therapeutic impactCOVID-19 significantly influenced ICU stay and respiratory infection management. Mean ICU stay was 49.8 days during the pandemic vs. 29.3 days in the post-pandemic (p=0.0001), reflecting greater patient complexity. Time to FA-PP request decreased post-pandemic (8.68 vs. 13.36 days, p=0.005), suggesting earlier diagnostics as clinical workflows normalized. Pneumonia diagnoses were similar across periods despite sample number differences, indicating disease burden from ventilatory support and prolonged ICU stay as key determinants.
Antibiotic regimens were modified in 56.2% of pneumonia patients based on FA-PP and/or culture results, consistent with prior studies reporting >70% modifications.1,25 FA-PP led to therapy changes in 55% of patients; most frequently therapy was maintained (44.6%), reflecting cautious practice until culture confirmation, especially post-pandemic.26–28 Positive FA-PP results prompted escalation or initiation (43%), whereas negative results favored maintenance (61%), with limited justification for expansion or de-escalation, similar to other COVID-19 cohorts.1,22,28,29
Therapy initiation or escalation predominated with positive FA-PP; negative results prompted maintenance or reduction of coverage, even post-pandemic, consistent with clinical trials and prescription studies.29,30P. aeruginosa infections showed limited de-escalation: 35% pandemic vs. 18.8% post-pandemic, likely due to clinical severity and perceived risk; literature reports greater de-escalation for Gram-positive than Gram-negative pathogens.1,30 COVID status did not alter FA-PP-based decisions. Delayed panel request during the pandemic may have increased culture negativity, supporting early molecular diagnostics for stewardship.2,5,9
LimitationsMain limitations include single-center, retrospective design, limiting generalizability. FA-PP was requested at the ICU upon suspicion of CAP, HAP/VAP in line with American and European consensus guidelines.4,5,31,32 High prior antibiotic exposure affects traditional culture performance, potentially increasing exclusive panel positivity and complicating differentiation between colonization and infection as described by other authors, where culture remains the gold standard in the diagnosis of bacterial respiratory tract infections. It may be difficult to accurately recover all pathogens in clinical samples, as culture results would be more affected by host immune response and prior antibiotic usage.8,9 Mortality and clinical outcomes were not included, nor panel-driven therapeutic changes, addressed elsewhere.5,11 Panel composition limits detection of off-target pathogens.
Implications and perspectivesDespite limitations, results support FA-PP as a complementary tool for therapeutic decisions, with high sensitivity and NPV. The panel is particularly relevant for guiding antibiotic therapy in pneumonia, even if not as striking as in studies with lower-quality respiratory samples, but with sufficient NPV to de-escalate or stop unnecessary treatments.15,23 Early FA-PP implementation post-pandemic may promote rational antibiotic use and de-escalation strategies. Interpretation must consider clinical context, potential discordance with culture, and panel limitations. Future research should assess early panel use on mortality and ICU-related costs.
CRediT authorship contribution statementAll co-authors have had access to the study data and have reviewed and approved the final manuscript. They all declare the accuracy of the data and tables included in the text as original work from their research.
Ethical considerationsThe study was approved by the Research Ethics Committee of the Autonomous Community of Aragon (file number C.I. PI24/468), dated December 10, 2024.
Informed consentAll data from the samples used were pseudonymized.
Declaration of generative AI and AI-assisted technologies in the writing processThe English version of the manuscript was produced using DeepL online translator, and the academic style was reviewed using ChatGPT 5.0.
FundingThe study was conducted without any grants, scholarships, or financial aid from any institution and using the resources of the principal investigator's institution.
Conflict of interestDr. Juan M. García-Lechuz has given presentations for BioMérieux, and the Aragonese Society of Microbiology, of which he is the current president, receives sponsorship from this same company for its annual scientific conference.
The other authors declare no conflict of interest.
The following are the supplementary data to this article:



