





Inflammation is a major determinant of abdominal aortic aneurysms (AAA). Interferon stimulated gene 15 (ISG15) has a role in vascular remodelling in AAA. This study investigates the mechanisms whereby ISG15 might affect vascular remodelling and function.
MethodsWe used vascular smooth muscle cells (VSMC) from wild type (ISG15+/+) o ISG15 knockout (ISG15−/−) mice, aorta from ISG15+/+ and ISG15−/− mice infused with angiotensin II (1.44mg/kg/day, sc, 14 days), and human AAA. We also performed a model of recombinant ISG15 infusion (rISG15, sc, 100 and 500ng/day, 14 days) in mice.
ResultsIn VSMC, ISG15 deficiency increased the expression of contractile (Acta2, Tagln) and synthetic (Fn1, Col1a2, Col3, Col4) markers and decreased the expression of the calcification marker Spp1. Ang II infusion changed the expression of phenotype markers differently in aorta from ISG15+/+ or ISG15−/− mice. ISG15 expression showed a negative correlation with expression of contractile markers (ACTA2, CNN1), and with COL3a1, in human samples from patients with AAA or with stenotic aorto-iliac pathology. rISG15 infusion induced hypotrophic vascular remodelling in mesenteric arteries without affecting vascular mechanics. Aorta of ISG15−/− contracted more to thromboxane A2 analogue U46619, compared to ISG15−/− mice. Both aorta and mesenteric arteries from rISG15-treated mice showed less contractility than control mice.
ConclusionsISG15 participates in pathological vascular remodelling probably by modulating VSMC phenotype. These changes could also impact in the vascular function.
La inflamación es un componente principal de los aneurismas aórticos abdominales (AAA). El gen estimulado por interferón 15 (ISG15) tiene un papel en el AAA. Se han investigado los mecanismos por los cuales ISG15 podría participar en el remodelado y en la función vasculares.
MétodosSe utilizaron células musculares lisas (CMLV) de ratones control (ISG15+/+) o deficientes en ISG15 (ISG15−/−), aortas procedentes de ratones ISG15+/+ o ISG15−/− infundidos o no con angiotensina II (Ang II, 1,44mg/Kg/día, sc, 14 días) y muestras de AAA humanos. Se realizó un modelo de infusión de proteína ISG15 recombinante (ISG15r, sc, 100 y 500ng/día, 14 días) en ratones.
ResultadosEn CMLV la deficiencia de ISG15 aumentó la expresión de marcadores de fenotipo contráctil (Acta2, Tagln) y sintético (Fn1, Col1a2, Col3, Col4) y disminuyó la del marcador de fenotipo calcificante Spp1. Ang II moduló la expresión de marcadores de fenotipo de manera diferente en aorta de ratones ISG15+/+ e ISG15−/−. La expresión de ISG15 correlacionó negativamente con la expresión de marcadores contráctiles (ACTA2, CNN1), así como con COL3a1, en muestras humanas procedentes de pacientes con AAA o con patología estenosante aorto-iliaca. ISG15r indujo un remodelado vascular hipotrófico en arterias mesentéricas sin afectar a la mecánica vascular. La aorta de los ratones ISG15−/− contrajo más al análogo de tromboxano A2 U46619, comparada con los ratones ISG15−/−. La aorta y las arterias mesentéricas de los ratones infundidos con ISG15r muestran menor contractilidad que los ratones controles.
ConclusionesISG15 participa en el remodelado vascular patológico posiblemente por su papel en el control del fenotipo de las CMLV. Dichos cambios podrían además impactar en la función vascular.
Vascular remodelling is an active process involving changes in the growth, death, or migration of vascular smooth muscle cells (VSMC) and in the synthesis, reorganisation, and degradation of the extracellular matrix (ECM).1 It occurs in response to long-term changes in haemodynamic conditions and contributes to the pathophysiology of vascular disease.1 Of the various clinical conditions in which remodelling occurs, abdominal aortic aneurysms (AAA) are among the most devastating.2 AAA is an essentially asymptomatic and potentially fatal vascular disease characterised by permanent dilation of the aorta by more than 3cm.3,4 Risk factors associated with AAA include smoking, advanced age, male sex, family history of AAA, peripheral arterial disease, hypertension, presence of aortic aneurysms elsewhere, race, and dyslipidaemia.3,4 Mechanisms commonly implicated in the development of AAA include vascular inflammation, modification of the phenotype of VSMC and various alterations in ECM proteins,4 which also play a fundamental role in vascular contraction.
VSMC are a dynamic cell type with the ability to switch between different functionally distinct phenotypes.5 The presence of VSMC with different phenotypes has been described in AAA. For example, AAAs generally show a decrease in contractile phenotype VSMC and an increase in secretory, senescent, or proinflammatory VSMC, which contribute to the dilatation of the vessel wall and could affect its functionality.6,7 Proinflammatory VSMC show an increase in the production of various cytokines such as interleukin (IL)1β, tumour necrosis factor (TNF), IL6, and a high expression of metalloproteinases (MMP2 and 9), allowing the infiltration of immune system cells such as T cells, macrophages, dendritic cells, neutrophils, B cells, and mast cells8 that perpetuate the vascular inflammatory cycle.9
AAA is associated with an increase in the expression of several inflammatory mediators.10–12 IFNγ levels are elevated in both animal models of AAA and human aneurysms,12–17 and recent studies seem to point to a possible role for type I IFNs in aneurysm pathology.18 In this context, a unique subtype of IFN-induced macrophages has recently been demonstrated to be involved in AAA formation and rupture.19
IFN signalling induces a signalling cascade that leads to the expression of several interferon-stimulated genes (ISGs). ISG15 encodes a ubiquitin-like protein that is predominantly expressed in cells of the immune system.20–22 The ISG15 protein can be found in free form or conjugated to substrate proteins, inducing a reversible post-translational modification in newly synthesised proteins called ISGylation. Both ISG15 and the enzymes involved in ISGylation are induced in response to various IFNs, as well as in response to lipopolysaccharides or TNFα.23,24 While ISGylation appears to modulate processes such as viral infection, cancer progression, response to hypoxia, and exosome secretion,25–28 the function of free ISG15 is less well understood and appears to be related to modulation of immune cell activity.18,19,25–28
At the vascular level, the role of ISG15 is largely unknown. ISG15 has been found in exosomes released from human microvascular endothelial cells in the context of HIV infection.29 ISG15 also appears to play a role in vascular remodelling. In a cohort of individuals with cardiovascular risk factors such as hypertension or diabetes, a positive correlation was found between ISG15 expression and carotid intima-media thickness.30 A potential role for ISG15 in atherosclerosis has also been suggested.31 In the context of aortic aneurysm, ISG15 expression was shown to be higher in two mouse models of aneurysm and in human aneurysms compared to control mice and patients without aneurysm.30,32 In addition, mice carrying a mutation in the deISGylating enzyme USP18, which inhibits its protease activity, develop aortic aneurysms after infusion of angiotensin II (Ang II).30 However, the mechanisms responsible for the role of ISG15 in pathological vascular remodelling are not fully understood. The aim of this study is to analyse the role of ISG15 in the phenotype of VSMC and its possible contribution to vascular remodelling and function.
Material and methodsAnimal modelsAnimal studies were approved by the Research Ethics Committee of the Autonomous University of Madrid (UAM) and by the General Directorate of the Environment, Community of Madrid, Spain (PROEX 345/14 and 183.2/20). The animals were cared for in accordance with Spanish Animal Protection Law RD53/2013, which incorporates the European Union Directive 2010/63/EU on the protection of animals used for experimental and other scientific purposes. Animal experiments were performed according to ARRIVE guidelines.
Male C57BL/6J wild-type (ISG15+/+) and ISG15 knockout (ISG15−/−) mice30 were kindly provided by Dr Klaus-Peter Knobeloch (University of Freiburg, Germany) and housed in the conventional animal facility of the UAM under controlled temperature and humidity conditions, with standard chow, access to water ad libitum, and a 12-h light/dark cycle. Both groups of mice were treated with Ang II (1.44mg/kg/day, 14 days) administered subcutaneously through Alzet osmotic minipumps (model 2002, Durect Corp., Cupertino, CA, USA) implanted under isoflurane (2%) anaesthesia.
In another set of experiments, C57BL/6J mice were randomly divided into three groups: control and infused with recombinant ISG15 (human ISG15, catalogue 12,729-HNAE, Sino Biological, Germany) at doses of 100 and 500ng/day via continuous release pumps (Alzet 2002) for 14 days.
Preparation of tissuesThe mice were euthanised by CO2 inhalation. Immediately after sacrifice, the aorta and the first-order branches distal to the superior mesenteric artery were isolated and cleaned off at and connective tissue in cold Krebs-Henseleit (KHS) solution (4°C) (115mM NaCl, 25mM NaHCO3, 4.7mM KCl, 1.2mM MgSO4·7H2O, 2.5mM CaCl2, 1.2mM KH2PO4, 11.1mM glucose, and .01mM Na2EDTA). Analysis of vascular function and structural and mechanical properties was performed on the day of sacrifice.
Vascular smooth muscle cell cultureVSMC were obtained from the aortas of 2-month-old ISG15+/+ and ISG15−/− mice. The aortas were immersed in cold PBS to remove connective tissue and fat. The aortas were incubated for 45min at 37°C in serum-free DMEM medium containing 2mg/mL type 2 collagenase, l-glutamine (10mmol/L), and antibiotics (penicillin 100 units/mL and streptomycin 100μg/mL) in an atmosphere of 95% air and 5% CO2. The aortas were then cut into small rings, and the explants were seeded in DMEM containing 20% fetal bovine serum. The cells were then trypsinised and subcultured. For analysis of phenotypic markers, the VSMC were starved for 24h in serum-free medium. All experiments were performed between passages 3 and 7.
Human samplesHuman studies were conducted in accordance with the tenets of the Declaration of Helsinki and approved by the Ethics and Research Committee of La Princesa University Hospital (Madrid, Spain) (protocol PI-825). The characteristics of the patients are shown in Table 1. Patients aged 18 years or older with AAA or aorto-iliac occlusive disease (non-AAA) were enrolled. All patients were informed of the investigational nature of the study and provided their written informed consent. Patients were recruited into the study if they were candidates for open surgery, regardless of their symptomatic status, had an AAA with a maximum diameter of 5.5cm or more (5cm or more in women) as measured by imaging techniques (Doppler ultrasound or computed axial tomography), or had rapid growth (more than .5cm/semester) during follow-up. Exclusion criteria included active inflammatory and neoplastic disease, autoimmune disease, positive HIV serology, pregnancy, and recreational drug use. Aortic wall samples were obtained from 34 patients, 27 of whom had AAA (diameter >5.5cm) and 7 of whom had non-aneurysmal aortic pathology (diameter <3.0cm) at the time of open surgery at the Department of Angiology and Vascular Surgery, La Princesa University Hospital. Samples were stored at −80°C for gene expression studies using q-PCR analysis.
Clinical characteristics of patients who underwent open surgery for abdominal aortic aneurysm (AAA) repair or aorto-iliac (non-AAA) pathology.
| No-AAA | AAA | |
|---|---|---|
| Number of samples | 7 | 27 |
| Age (years) | 68.71±2.69 | 70.65±1.44 |
| Sex (male/female) | 7/0 | 25/2 |
| Weight (kg) | 66.86±3.67 | 88.19±2.86* |
| Height (m) | 1.70±.02 | 1.71±.01 |
| Body mass index (kg/m2) | 23.3±1.49 | 29,95±.97* |
| Abdominal circumference (cm) | 89.60±10.95 | 113.4±2.43* |
| Diabetes mellitus (%) | 14% | 16% |
| Hypertension (%) | 43% | 60% |
| Dyslipidaemia (%) | 28% | 56% |
| *Heart disease (%) | 28% | 40% |
| CKD (%) | 0% | 28% |
| Smoker (%) | 100% | 88% |
| COPD | 14% | 24% |
| Stroke | 0% | 12% |
| Peripheral vascular disease | 71% | 16%* |
| Medication | ||
| Antidiabetic | 0% | 12% |
| Insulin | 0% | 0% |
| Antihypertensive | 43% | 62% |
| Statins | 43% | 75% |
| Antiplatelet | 43% | 50% |
| Anticoagulant | 14% | 21% |
| Beta-blockers | 28% | 29% |
Values are expressed as mean±SEM, number of subjects or percentages. Heart disease includes congenital heart disease, ischaemic cardiomyopathy, valvular heart disease, heart failure, arrhythmia, dilated cardiomyopathy, open heart surgery, and previous coronary endovascular procedures.
CKD: chronic kidney disease; COPD: chronic obstructive pulmonary disease.
Total RNA was obtained using TRI Reagent® (Sigma-Aldrich, Cat. No. T9424) according to the manufacturer's recommendations. RNA was transcribed into cDNA using the NZY first-strand cDNA synthesis kit (Nzytech). The level of mRNA expression was analysed by real-time PCR (q-PCR) on an ABI 7500 Fast system (Invitrogen Life Technologies), using custom specific primers (Sigma-Aldrich) or pre-designed probes provided by the Assay-on-Demand system (Applied Biosystems) or by Integrated DNA Technologies (Illinois, USA) (Table 2). The normalisation control was 18S in multiplex RT-PCR and β-actin for the others. The 2−ΔΔCt method was used to calculate relative mRNA expression levels.
Primers or probes used in mRNA expression studies.
| Human | |||
| ACTB | Beta-Actin | NM_001101 | F: 5′-AGAGCTACGAGCTGCCTGAC |
| R: 5′-AGCACTGTGTTGGCGTACAG | |||
| ACTA2 | Alpha-2 actin, smooth muscle | NM_001613 | F: 5′TCGTTACTACTGCTGAGCGTGAGA |
| R:5′ AAGGATGGCTGGAACAGGGTC | |||
| CNN1 | Calponin | NM_001299 | Hs.PT.58.38799164 |
| COL1a2 | Collagen 1 alpha 2 | NM_000089 | F: 5′-CAGCCGCTTCACCTACAG |
| R: 5′-AATCACTGTCTTGCCCCAGG | |||
| COL3a1 | Collagen 3a1 | NM_000090 | Hs.PT.58.4249241 |
| CCN2 | Connective tissue growth factor | NM_001901 | Hs.PT.58.14485164.g |
| ISG15 | ISG15 ubiquitin-like modifier | NM_005101 | Hs.PT.58.39185901.g |
| SPP1 | Osteopontin | NM_000582 | Hs.PT.58.19252426 |
| RNA18S1 | 18S ribosomal 1 | X03205 | 4310893E |
| Mouse | |||
| Acta2 | Alpha-2 actin, smooth muscle | NM_007392 | Mm.PT.58.16320644 |
| Col1a2 | Collagen1 alpha 2 | NM_007743 | F: 5`-GTCCTAGTCGATGGCTGCCTC3 |
| R: 5`-AGCACCACCAATGTCCAGAG3 | |||
| Col3 | Collagen 3 alpha 1 | NM_009930 | Mm.PT.58.13848686 |
| Col4 | Collagen 4 alpha 1 | NM_009931 | Mm.PT.58.31838522 |
| Fn1 | Fibronectin 1 | NM_001276408 | F: 5`-ATGAGAAGCCTGGATCCCCT3 |
| R: 5`-GGAAGGGTAACCAGTTGGGG3 | |||
| Klf4 | Krueppel-like factor 4 | NM_010637 | Mm.PT.58.10779296 |
| Spp1 | Osteopontin | NM_001204201 | Mm.PT.58.43709208 |
| Tgln2 | Transgelin | NM_178598 | Mm.PT.58.28725952 |
The aortas of the animal models were fixed, dehydrated, embedded in paraffin, sectioned at 5μm thickness and stained with haematoxylin-eosin to evaluate the vascular structure. Analysis was performed using Image J software (Image J, NIH, Bethesda, MD, USA).
Pressure myographThe structural and mechanical properties of the mesenteric arteries were studied in a pressure myograph (Danish Myo Tech, model P100, J.P. Trading I/S). The clean arteries were mounted on two glass microcannulas and secured with nylon surgical suture. After tying off the small branches, the length of the vessels was adjusted so that their walls were parallel without stretching. The segment was then adjusted to a pressure of 45mmHg and allowed to equilibrate for 30min at 37°C in calcium-free KHS (0Ca2+; calcium omitted and 1mmol/L EGTA added) perfused intravascularly and extravascularly. A pressure-diameter curve was obtained by increasing the intraluminal pressure in steps of 20mmHg from 3 to 120mmHg for 2min at each pressure. At each step, a photograph was taken during the last 30s when the measurements were stable. The internal (Di0Ca) and external (De0Ca) diameters were measured at at least three different points at each intraluminal pressure using Image J analysis software.
The structural parameters of the vessel wall were calculated as follows:
Mechanical parameters were calculated using the following formulae:
Strain=(Di0Ca–D00Ca)/D00Ca where D00Ca is the internal diameter at 3mmHg.
Circumferential stress=(P×Di0Ca)/(2GP), where P is intraluminal pressure (1mmHg=1334×103 dynes×cm–2) and WP is the wall pressure at each intraluminal pressure.
Geometry-independent arterial stiffness was determined by Young's modulus (E=stress/strain). This relationship is not linear, so it is more appropriate to obtain the slope of the stress/strain curve (β), which was obtained by fitting the data for each animal to an exponential curve.30
Confocal microscopyIntact, fixed mesenteric arteries obtained from the pressure myograph were incubated with the nuclear dye Hoechst 33,342 (.01mg/mL; Thermo Fisher Scientific) for 15min. The arteries were then mounted on slides with silicone wells for observation under a Leica TCS SP5 confocal microscope. At least two .5μm thick optical sections were taken along the artery and the number of VSMC was quantified using Image J.
Vascular functionTwo mm segments of aorta and mesenteric artery were mounted on a wire myograph (Danish MyoTech, Aarhus, Denmark). The arteries were first equilibrated in oxygenated KHS continuously bubbled with 95% O2 and 5% CO2 for 30min. and then stretched to their optimal internal diameter for development of active tension. To check the functional integrity of the arterial segments, an initial exposure to a high K+solution (120mmol/L KCl) was performed. Concentration-response curves were then plotted for phenylephrine (1nmol/L−30μmol/L; Sigma-Aldrich) and the thromoxane A2 analogue, U46619 (.1nmol/L−1μmol/L; Cayman Chemical, USA) in arteries with intact endothelium. Data were acquired and analysed using LabChart® software (ADInstruments, New South Wales, Australia). Vasoconstrictor responses were expressed in mN/mm.
Data analysis and statisticsData were analysed using Graphpad Prism 8 software (Graphpad Software, Inc, San Diego, CA, USA). All data were expressed as the mean±standard error of the mean number of animals or patients. After checking the normality of the distribution of the populations using a Shapiro–Wilk test, differences between populations were determined using a non-parametric paired test (Student's t-test) or the appropriate non-parametric test (Mann–Whitney). For structural, mechanical, and vascular function data, a repeated measures test using the general linear model procedure or two-way ANOVA followed by a Bonferroni post-test was used. Correlation analyses were performed using Spearman’s correlation test. In all cases, p<.05 was considered statistically significant.
ResultsRole of ISG15 in vascular smooth muscle cell phenotypeISG15 mRNA expression is increased in mouse and human aneurysm specimens.30,32 In addition, mice with increased ISG15 expression develop AAA in response to Ang II.30 To further investigate the mechanisms by which ISG15 might induce such remodelling, we isolated and cultured VSMC from ISG15+/+ and ISG15−/− mice and analysed changes in the expression of contractile phenotype markers (Acta2, Tgln2), synthetic phenotype (Fn1, Col1a2, Col3, Col4) and calcification or osteoblast-like phenotype markers (Spp1, Klf4). VSMC from ISG15−/− mice showed higher expression of contractile and synthetic phenotype markers and decreased expression of the calcification phenotype marker Spp1compared to those from ISG15+/+ mice (Fig. 1A).

ISG15 modulates vascular smooth muscle cell (VSMC) phenotype: (A) mRNA expression levels of contractile (Acta2, Tgln2), synthetic (Fn1, Col1a2, Col3, Col4) and calcification (Spp1, Klf4) phenotype markers in VSMC from the aorta of ISG15+/+ and ISG15−/− mice. n is represented by the number of dots in each case and represents independent cultures. *p<.05 vs. ISG15+/+ by unpaired t-test. (B) Expression levels of contractile (Acta2), synthetic (Col3), and calcification (Spp) phenotype markers in the aorta of ISG15+/+ and ISG15−/− treated with angiotensin II for 2 weeks. n is represented by the number of dots in each case and represents different animals. *p<.05 vs. control and +p<.05 vs. ISG15+/+ by one-way ANOVA.
We then infused ISG15+/+ and ISG15−/− mice with Ang II and measured some of these phenotype markers in the aorta. Ang II reduced Acta2 gene expression in ISG15+/+ mice, an effect that was not observed in ISG15−/− mice. The aortas of ISG15−/− mice showed lower basal expression of Col3, which was not altered by Ang II in either genotype. Ang II also increased Spp1 expression in ISG15+/+ mice and this expression was decreased in the aortas of ISG15−/− mice (Fig. 1B).
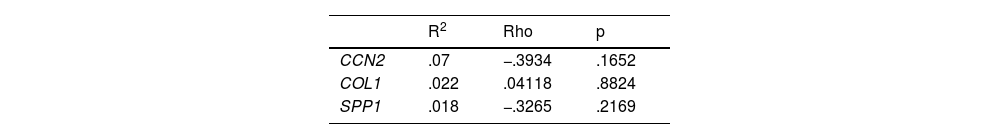
ISG15 expression negatively correlates with contractile markers in human aortic samplesWe then evaluated the expression of contractile and synthetic phenotype markers in human AAA samples and compared them with samples from patients with aorto-iliac pathology without AAA. We observed that AAA samples showed decreased expression of the contractile marker CNN1 and the calcification marker SPP1 but not of other synthetic or contractile markers such as ACTA2, CCN2, COL1a2, or COL3a1 (Fig. 2A). However, ISG15 expression was negatively correlated with some markers such as ACTA2, CNN1, and COL3a1 (Fig. 2B, Table 3), suggesting a possible role for ISG15 in the phenotype of SMC in vascular pathology.

Expression of phenotype-related genes in human samples. (A) mRNA expression levels of different markers of contractile (ACTA2 and CNN1), synthetic (COL1a2, COL3a1, CCN2) and calcification (SPP1) phenotype in aortic samples from patients with AAA or non-aneurysmal iliac aortopathy (Non-AAA). (B) Correlation between ISG15 mRNA expression levels and different contractile (ACTA2, CNN1) or synthetic (COL3a1) markers in these samples. The number of samples is represented by the number of dots in each case and represents different patients. *p<.05 vs. ISG15+/+ by Mann–Whitney test.
To confirm the effect of ISG15 on vascular structure, we performed an ISG15r infusion model in mice for 2 weeks. In the aorta, ISG15r induced a tendency to decrease the internal and external diameters and the thickness of the vessel wall, especially at a dose of 500ng/day (Fig. 3A). ISG15r infusion caused an increase in gene expression of the markers Col3 and Spp1 and no changes in Acta2 at a dose of 100ng/day (Fig. 3B). At a dose of 500ng/day, the expression of these markers did not change and even decreased for Col3 (Fig. 3B). In addition, ISG15r at a dose of 100ng/day induced hypotrophic remodelling in mesenteric arteries, characterised by a decrease in external and internal diameter, wall thickness and cross-sectional area (Fig. 4A–E). The dose of 500ng/day produced a decrease in wall thickness but did not significantly affect the other parameters studied. This ISG15r-induced remodelling could be due to changes in the number of VSMC in the vessel wall, as 3D visualisation of mesenteric arteries by confocal microscopy showed a trend towards fewer VSMC in arteries from mice infused with ISG15r (Fig. 4F).

Effect of recombinant ISG15 (ISG15r) on aortic vascular structure. (A) Representative images (objective ×10 and zoom 1) and quantification of the diameter and wall thickness of aortic cross-sections and (B) aortic expression levels of mRNA of contractile (Acta2), synthetic (Col3), and calcification (Spp1) phenotype markers in control mice and mice infused with ISG15r at doses of 100 and 500ng/day for 14 days. The number of samples is represented by the number of dots and represents different animals. *p<0.05 vs. ISG15+/+ by unpaired t-test.

Effect of recombinant ISG15 (ISG15r) on the structure of mesenteric arteries. Outer diameter (A), inner diameter (B), wall thickness (C), wall-to-lumen ratio (D), and cross-sectional area (E) of mesenteric arteries from C57BL/6J mice infused or not (control) with ISG15r at doses of 100 and 500ng/day for 14 days. n=8; *p<.05 vs. control by two-way ANOVA. (F) Number of vascular smooth muscle cells in mesenteric arteries of control mice or mice infused with ISG15r (100ng/day) obtained by confocal microscopy. n=8. n is represented by the number of dots and represents different animals.
We then evaluated possible changes in vascular mechanics and observed that ISG15r infusion did not induce significant changes in strain, stress, distensibility, or stress-strain ratio (a marker of stiffness independent of wall geometry) at either of the two doses analysed (Fig. 5), suggesting that the changes observed in the vascular structure of mesenteric arteries in ISG15r-infused mice were likely due to changes in vascular cells rather than in the ECM.

Effect of recombinant ISG15 (ISG15r) on mesenteric artery mechanics. Deformation (A), circumferential stress (B), incremental distensibility (C), and stress–strain relationship (D) of mesenteric arteries from C57BL/6J mice infused or not (control) with ISG15r at doses of 100 and 500ng/day for 14 days. n=8. The parameter β represents the slope of the stress-strain relationship. n is represented by the number of dots and represents different animals.
Any change in the structure of the vascular wall could affect its function. Therefore, we evaluated the contractile capacity of arteries from ISG15+/+ and ISG15−/− mice, as well as those from the ISG15r infusion model. As shown in Fig. 6A, aortas from ISG15−/− mice showed no changes in response to phenylephrine, but an increase in contraction to the thromboxane A2 analogue U46619 was observed. In contrast, ISG15r infusion caused a decrease in contractile responses to phenylephrine in the aorta and mesenteric arteries, particularly at a dose of 500ng/day (Fig. 6B).

Role of ISG15 in vascular contractility. (A) Contractile response to phenylephrine (Phe) or the thromboxane A2 analogue U46619 in aortic segments from ISG15+/+ and ISG15−/− mice. (B) Contractile response to phenylephrine (Phe) in aortic segments and mesenteric arteries from C57BL/6J mice infused or not (control) with ISG15r at doses of 100 and 500ng/day for 14 days. n=5–7. *p<.05 vs. ISG15+/+ by two-way ANOVA vs. ISG15+/+ or control mice.
Vascular remodelling is a key factor in the development of diseases such as AAA.1,2 Given that AAA is a potentially fatal disease for which there is no effective pharmacological prophylactic treatment,2–4 further investigation into the mechanisms involved in its development is crucial. An infiltration of various types of immune system cells has been described in AAA, with macrophages being the most abundant.10 These infiltrating immune cells and the vascular cells themselves release pro-inflammatory cytokines such as IL6, TNF, and IFNγ locally and systemically, the levels of which correlate with AAA growth or rupture.10 Several studies have implicated IFNs in the development of AAAs, although their role is not fully defined. For example, IFNγ appears to be involved in the activation of metalloproteinases, collagenases, and elastases, and thus in the degradation of the matrix associated with AAA.12–14 In addition, ISG15 has recently been described to be involved in various vascular structural and mechanical changes associated with hypertension and AAA development30 and its expression is increased in murine and human AAA samples.32
One of the mechanisms involved in the development of AAA is the alteration in the phenotype of VSMC, which dedifferentiate from their healthy contractile state to secretory, senescent, or proinflammatory phenotypes.5–7 Our data show that VSMC from ISG15+/+ and ISG15−/− control mice differ in various phenotype markers, which could play an important role in the vascular wall’s response to different stimuli. More specifically, ISG15 deficiency is associated with increased expression of both contractile and ECM markers (collagens and fibronectin-1) as well as decreased expression of the calcification phenotype marker Spp1, which does not appear to significantly affect, at least apparently, the artery phenotype of a control mouse. However, it is possible that these changes may predispose the vessel to structural changes in various diseases (e.g., AAA, atherosclerosis, hypertension, restenosis) where phenotypic changes in SMC play a major role. Furthermore, in Ang II-infused mice, the loss of the contractility marker Acta2 in ISG15+/+ mice is not observed in ISG15−/− mice, and these mice also appear to have lower expression of markers such as Spp1 or Col3. In human samples, we found that ISG15 expression levels correlate negatively with two contractile markers, suggesting that ISG15 may play a role in the contractile function of VSMC, which could explain the alterations in VSMC contractility in patients with aneurysms.33 We also found a negative correlation between ISG15 and COL3a1 indicating that ISG15 could also contribute to the loss of ECM that occurs in advanced AAA. Overall analysis of these results suggests that the elimination of ISG15 could promote a state of vascular protection against AAA, although further studies are needed to fully confirm this hypothesis. It is interesting to note that samples from patients with AAA showed decreased expression of the contractile marker CNN1, but not ACTA2, and of the calcification marker SPP1, although not of other markers, compared to patients without AAA. Since the patients without AAA used in this study already have significant vascular damage, we cannot rule out a role for ISG15 in other vascular pathologies. It would also be necessary to increase the number of human samples included in the analysis to further investigate the role of ISG15 in the vascular phenotype.
The data presented here and previously published data30 show that depletion of ISG15 could protect against vascular injury. In this study, we also show for the first time that exogenous ISG15 administration induces changes in the wall structure and could modulate the phenotype of VSMC. Thus, after administration, there is a tendency for the diameter and thickness of the aortic wall to decrease, associated with an increase in the expression of phenotypic markers at the lowest dose studied, and clear hypotrophic effects in mesenteric arteries, possibly due to a reduction in the number or size of VSMC. There are no previous data on the role of free ISG15 in VSMC. However, it has been reported that VSMC may respond to type 1 IFNs, which would induce oxidative stress and mitochondrial damage leading the transition to the senescent phenotype in a process mediated by the cGAS-STING (cyclic AMP-GMP synthetase-IFN gene stimulator) pathway, which is closely related to ISG15.34–37 A limitation of our study is that we cannot know whether the concentrations of ISG15 administered are within the pathophysiological range observed in mice. However, these results allow us to confirm the effect of ISG15 on SMC. They also encourage us to study its role in pathological situations where its expression is increased.
The phenotypic and structural changes induced by ISG15 could have a functional impact on signalling mediated by different contractile agonists, as suggested by the increased contractility observed with the thromboxane A2 analogue U46619, but not with phenylephrine, in the aortas of ISG15−/− mice compared to their controls. In contrast, and consistent with hypotrophic vascular remodelling and a possible loss of VSMC, arteries from ISG15r-infused mice show reduced contractility. These results complement previously published findings on the role of ISG15 in endothelial function30 and suggest that VSMC is an additional target of ISG15 in the control of vascular tone.
ConclusionsOur work demonstrates a potential role for ISG15 as a regulator of the VSMC phenotype and vascular structure and function. Our results suggest that blocking ISG15 could prevent the transition of VSMC from healthy contractile phenotypes to pathological phenotypes, with beneficial effects on contractility, inflammation, and vascular remodelling.
FundingThis work was undertaken thanks to funding from the Spanish Arteriosclerosis Foundation (FEA Grant 2021-Basic Research). In addition, the study received funding from MCIN/AEI/10.13039/501100011033 and from ”ERDF A way of making Europe”, PID2020-116498RB-I00, through the RED2022-134541-T research networks funded by MICIU/AEI/10. 13039/501100011033 and PI21/00084, from the Social Security Health Research Fund.
The authors have no conflict of interests to declare.

articles
