



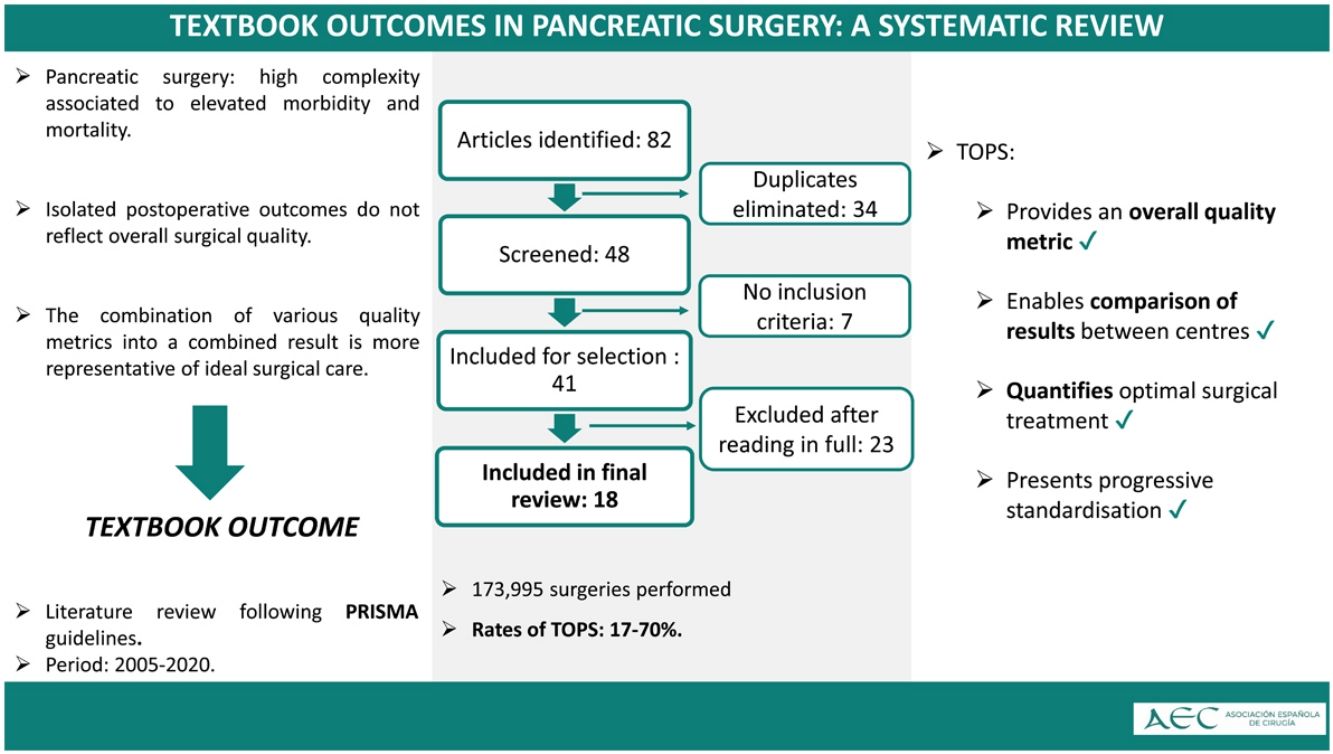
Pancreatectomy is associated with high morbidity and mortality, making the evaluation of surgical outcomes essential. The textbook outcome in pancreatic surgery (TOPS) combines multiple quality metrics into a single composite endpoint, providing a more representative assessment of optimal surgical care.
Following PRISMA guidelines, a literature search was conducted for studies on postoperative TOPS after pancreatectomy, analyzing methodology, rates, associated factors, inter-hospital variability, and overall findings.
Of 82 publications identified, 18 observational studies were included, encompassing a total of 173.995 pancreatic resections. TOPS definitions were heterogeneous, and rates ranged from 17% to 70%. TOPS was associated with patient, hospital, and surgery-related factors.
This systematic review summarizes the contemporary international experience with TOPS as a patient-centered composite metric, suitable for quantifying “ideal” care and comparing outcomes among centers performing pancreatic surgery.
La pancreatectomía se asocia a elevada morbimortalidad, lo que hace esencial evaluar los resultados quirúrgicos. El textbook outcome en cirugía pancreática (TOCP) combina múltiples métricas de calidad en un único resultado, ofreciendo una valoración más representativa de la atención quirúrgica ideal.
Siguiendo las pautas PRISMA, se realizó una búsqueda de artículos sobre TOCP posoperatorio tras pancreatectomía, analizando metodología, tasas, factores asociados, variabilidad hospitalaria y hallazgos generales.
De 82 publicaciones identificadas, se incluyeron 18 estudios observacionales, con un total de 173.995 resecciones pancreáticas. Las definiciones de TOCP fueron heterogéneas y las tasas oscilaron entre el 17% y el 70%. El TOCP se asoció con factores del paciente, del hospital y propios de la intervención quirúrgica.
Esta revisión sistemática resume la experiencia internacional contemporánea con el TOCP como métrica compuesta centrada en el paciente, adecuada para cuantificar una atención “ideal” y comparar resultados entre centros que realizan cirugía pancreática.

Pancreatic disease represents a highly complex multidisciplinary challenge. The incidence of pancreatic cancer has gradually risen in recent decades, increasing its relevance in research and in the scientific literature. As a result, publications on pancreatic surgery in Spain have experienced a progressive increase in recent years.1
Pancreatic surgery entails high morbidity (26–40%) and mortality (2–12%), so the continuous audit of surgical outcomes is extremely important.2 “Isolated” postoperative metrics, like mortality, readmissions and hospital stay, have been used as important measures to evaluate surgical care. However, when examined individually, these measures often do not reflect surgical quality in a comprehensive manner. In this context, several combinations of criteria have been described which, when all fulfilled, constitute what has been defined as a “Textbook Outcome” (TO): a single composite result representing the ideal surgical care. In general, a TO is observed when patients undergo a surgical resection in the absence of major postoperative complications, prolonged stay, mortality or readmission.
These quality indicators of the surgical process, known as TOs, have been validated in areas like oesophagogastric surgery and hepatic surgery,3 and are starting to be applied in pancreatic surgery. In the case of the Textbook Outcome in Pancreatic Surgery (TOPS), this indicator takes into consideration an absence of: (1) mortality, (2) pancreatic fistula, (3) haemorrhage, (4) biliary fistula, (5) Clavien–Dindo grade > II complications, and (6) hospital readmission. TOPS is considered achieved in cases that fulfil all of these criteria. Previous studies have identified this indicator, along with its monitoring and progressive improvement, as a potential benchmarking tool for pancreatic surgery. The frequency with which a TO is achieved at a given centre provides an important composite quality measure which is easy to interpret for patients and represents an assessment of care covering the entire spectrum of the disease.
Although data on TOPS outcomes is limited, efforts have been made to define a consensus-based strategy that can be accepted internationally. The criteria must encompass the ideal perioperative and postoperative care after surgery. Previous studies based on audit criteria have suggested that a centralisation of pancreatic surgery volume could contribute to improve complication and mortality rates. In order to reduce these rates and limit the costs for the healthcare system, the effect of establishing high-volume specialised units is currently being studied.
MethodologyFollowing the PRISMA guidelines, a search for scientific articles on TOPS was conducted across the PubMed, EMBASE, Scopus and Cochrane databases, updated as of 31 December 2024. The eligibility and exclusion criteria were defined prior to the search, in accordance with PRISMA recommendations.
In order to structure the research question, the PICO model (Population, Intervention, Comparator and Outcome) recommended for systematic reviews, was applied:
- •
P (Population): patients undergoing pancreatic surgery.
- •
I (Intervention): use of TO as a composite quality metric.
- •
C (Comparator): classical surgical outcome parameters analysed in isolation.
- •
O (Outcome): overall and comparative measurement of surgical quality, stratification capacity between centres, and use in benchmarking.
The research question derived from this framework was the following:
In patients undergoing pancreatic surgery, does the use of the Textbook Outcome as a composite metric enable a more precise and comprehensive assessment of surgical quality, compared with classical parameters analysed in isolation?
The search strategy (in Spanish) included: ((Textbook outcomes) O (Resultados de libro) Y ((Páncreas) O (Pancreático)) Y ((Cirugía) O (Resección pancreática) O (Pancreatectomía)).
((Textbook outcomes) OR (Textbook outcomes) AND ((Pancreas) OR (Pancreatic)) AND ((Surgery) OR (Pancreatic resection) OR (Pancreatectomy)).
All the scientific articles including adult patients undergoing pancreatic resection in which the TO was evaluated were identified. Duplicate series, narrative reviews and editorials were excluded. Potentially eligible studies were assessed by screening the title and abstract, applying the predefined inclusion and exclusion criteria. Selection of studies and data extraction were conducted independently by two reviewers, with discrepancies resolved by consensus. Subsequently, selected articles were read in full for final inclusion.
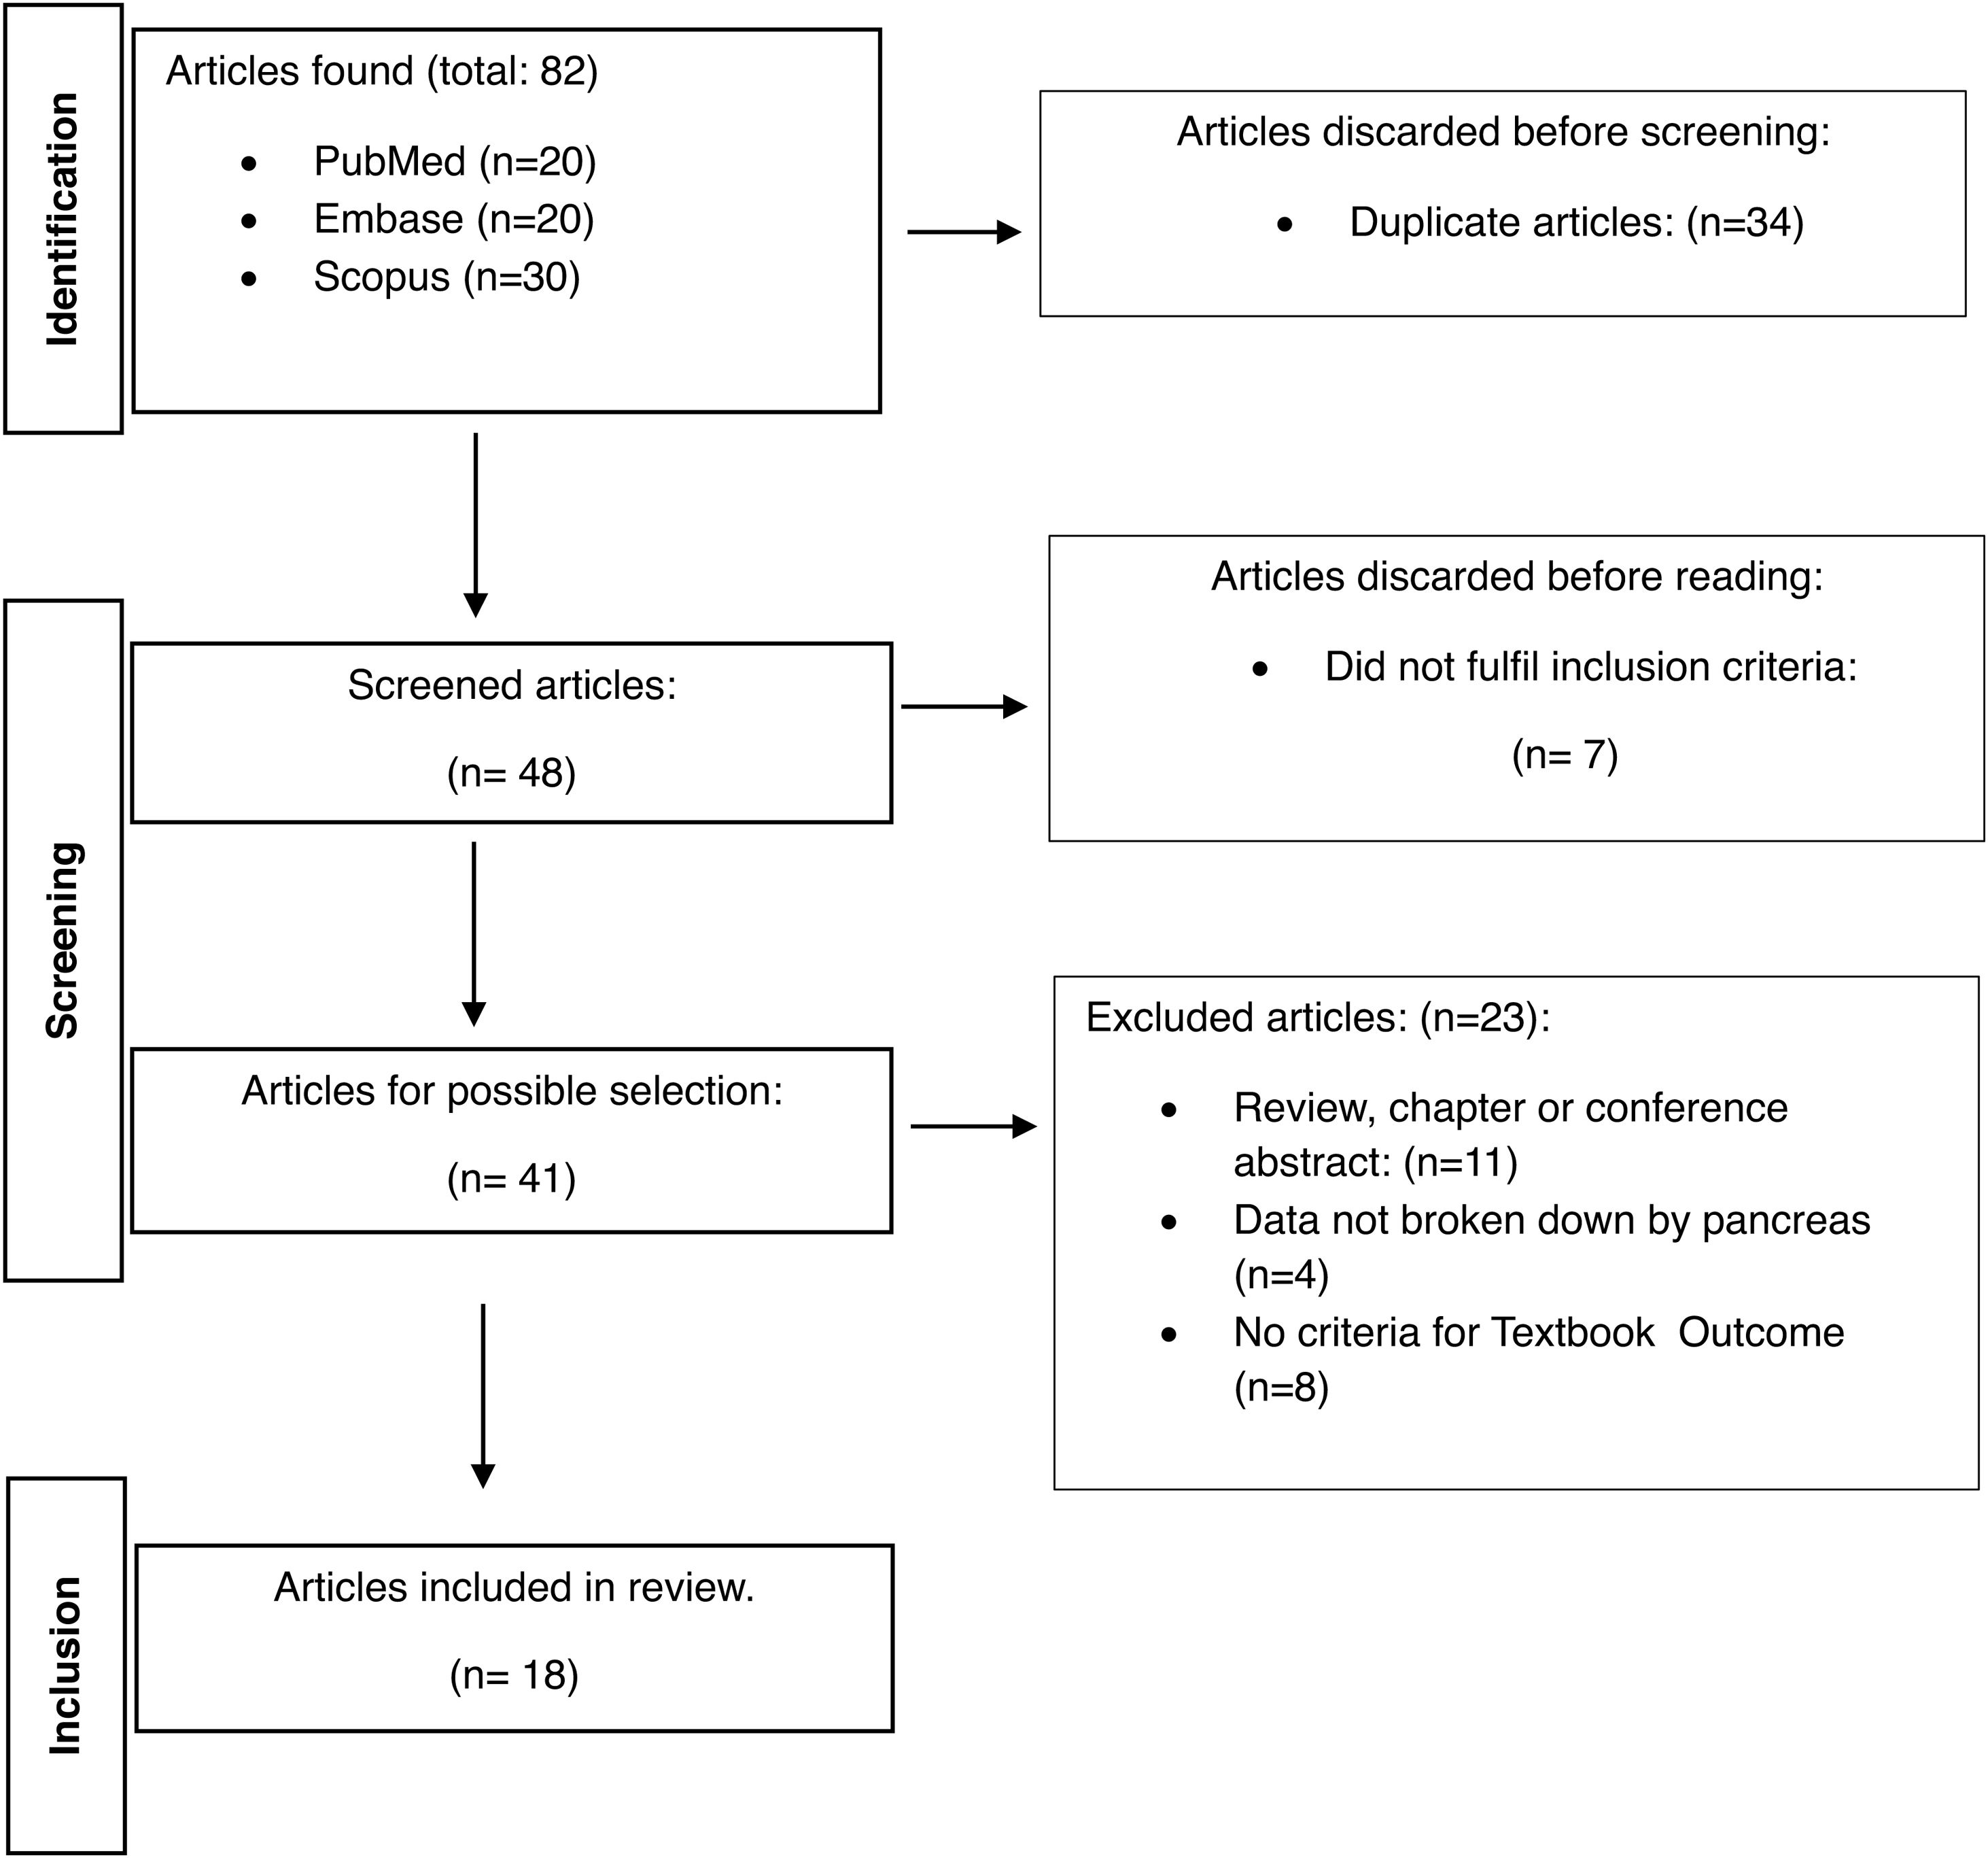
The search and selection process is described in Fig. 1.

Selected studies were organised and analysed according to author, scientific journal, year of publication, source of data, period of surgical treatments, number of patients who underwent pancreatic resection surgery, disease inclusion criteria, and type of surgical intervention.
Regarding the Textbook Outcome in Pancreatic Surgery (TOPS), the parameters included in each study, the overall rates of TOPS achieved and possible inter-hospital variations were registered. Moreover, factors associated to achieving TOPS and the factor with the highest negative impact on this achievement (“incomplete textbook outcome”) were identified.
In cases where studies included multivariate analyses, the factor with the greatest absolute effect was recorded. Publications which conducted an analysis of survival via Kaplan–Meier curves or corresponding Hazard Ratios (HR) were also noted.
Finally, the main conclusions of each study were summarised and their methodological quality was evaluated using the Newcastle–Ottawa scale (NOS), which grades observational studies with a maximum score of 9 points, distributed into three domains: selection (0–4 points), comparability (0–2 points) and outcomes (0–3 points).
ResultsA total of 82 publications were identified in all the databases consulted, of which 34 were removed due to duplication. The 48 remaining articles were examined and it was concluded that 7 did not fulfil the inclusion criteria, since they did not evaluate TO. After examining the abstracts, 23 records were excluded for being conference abstracts, not presenting data disaggregated by pancreatic surgery or not fulfilling the inclusion criteria. Ultimately, 18 studies were included which fulfilled the eligibility criteria (Fig. 1).
All the studies were retrospective and observational, mostly corresponding to evidence level IIb, and analysing a combined total of 173,995 patients undergoing pancreatic resection between the years 2005 and 2020. Overall, the methodological quality, assessed via the Newcastle–Ottawa scale (NOS), was high, with scores between 6 and 9 points (mean 8.4 ± 0.9). A clear trend was observed towards progressive improvement in the quality of the studies over time: works published before 2021 had scores between 6 and 8, whereas after the year 2022 most articles achieved the maximum score of 9/9, thus reflecting stronger methodological rigour, standardisation of the Textbook Outcome, and the systematic use of multivariate analyses.
Out of the total publications, 39% were based on national databases, 22% on international multicentre collaborations, 17% on administrative databases, like US Medicare, 11% on national multicentre studies, and 11% on single-centre studies.
The surgical procedures analysed included mainly pancreaticoduodenectomies and distal pancreatectomies (56%); of which 33% only included pancreaticoduodenectomy and 11% distal pancreatectomy. In total, 17% of the series employed minimally invasive approaches. In terms of indication, 61% of the studies included patients with any pancreatic pathology, 33% focused on ductal adenocarcinoma and 5% on neuroendocrine tumours.
Nearly all the studies (89%) except for two, included 2 of the original TO criteria: absence of mortality and of readmission. In total, 83% of the studies included the criterion of absence of major complications (Clavien–Dindo ≥ III). Intra-hospital or 30-day mortality was considered in 53% of cases, and at 90 days in 47%. Readmission was defined at 30 days in 62% of studies. Moreover, only 61% of the studies included length of admission, with the majority establishing a cut-off point at the 75th percentile for patients with the same diagnostic procedure.
The rates of TO ranged between 17% and 70%. In addition, 28% of the studies only analysed oncological criteria (oncological textbook outcome or OTO), with lower rates (17–54%) compared to those which examined overall TO (43–70%). Series including both benign and malignant pathologies presented the highest variability (43–70%), whereas studies focusing exclusively on pancreatic cancer showed more homogeneous rates (42–55%). The factor which prevented achievement of a TO most frequently was the presence of CD complications grade > II (10–33 %). Other factors contributing to failure to achieve TO were readmission, prolonged hospital stay, and oncological criteria. A notable heterogeneity among studies was observed, with overall variations of 17–70 %, and inter-hospital variations of 59–74 % within the same study.
Only 3 of the 18 studies (16.7%) conducted survival analysis using Kaplan–Meier curves. Two of them, focusing on pancreatic adenocarcinoma, demonstrated a significantly higher overall survival among patients who achieved OTO, whereas the study by Partelli et al.,25 conducted in non-functioning pancreatic neuroendocrine tumours, did not find an association between the achievement of TO and survival.
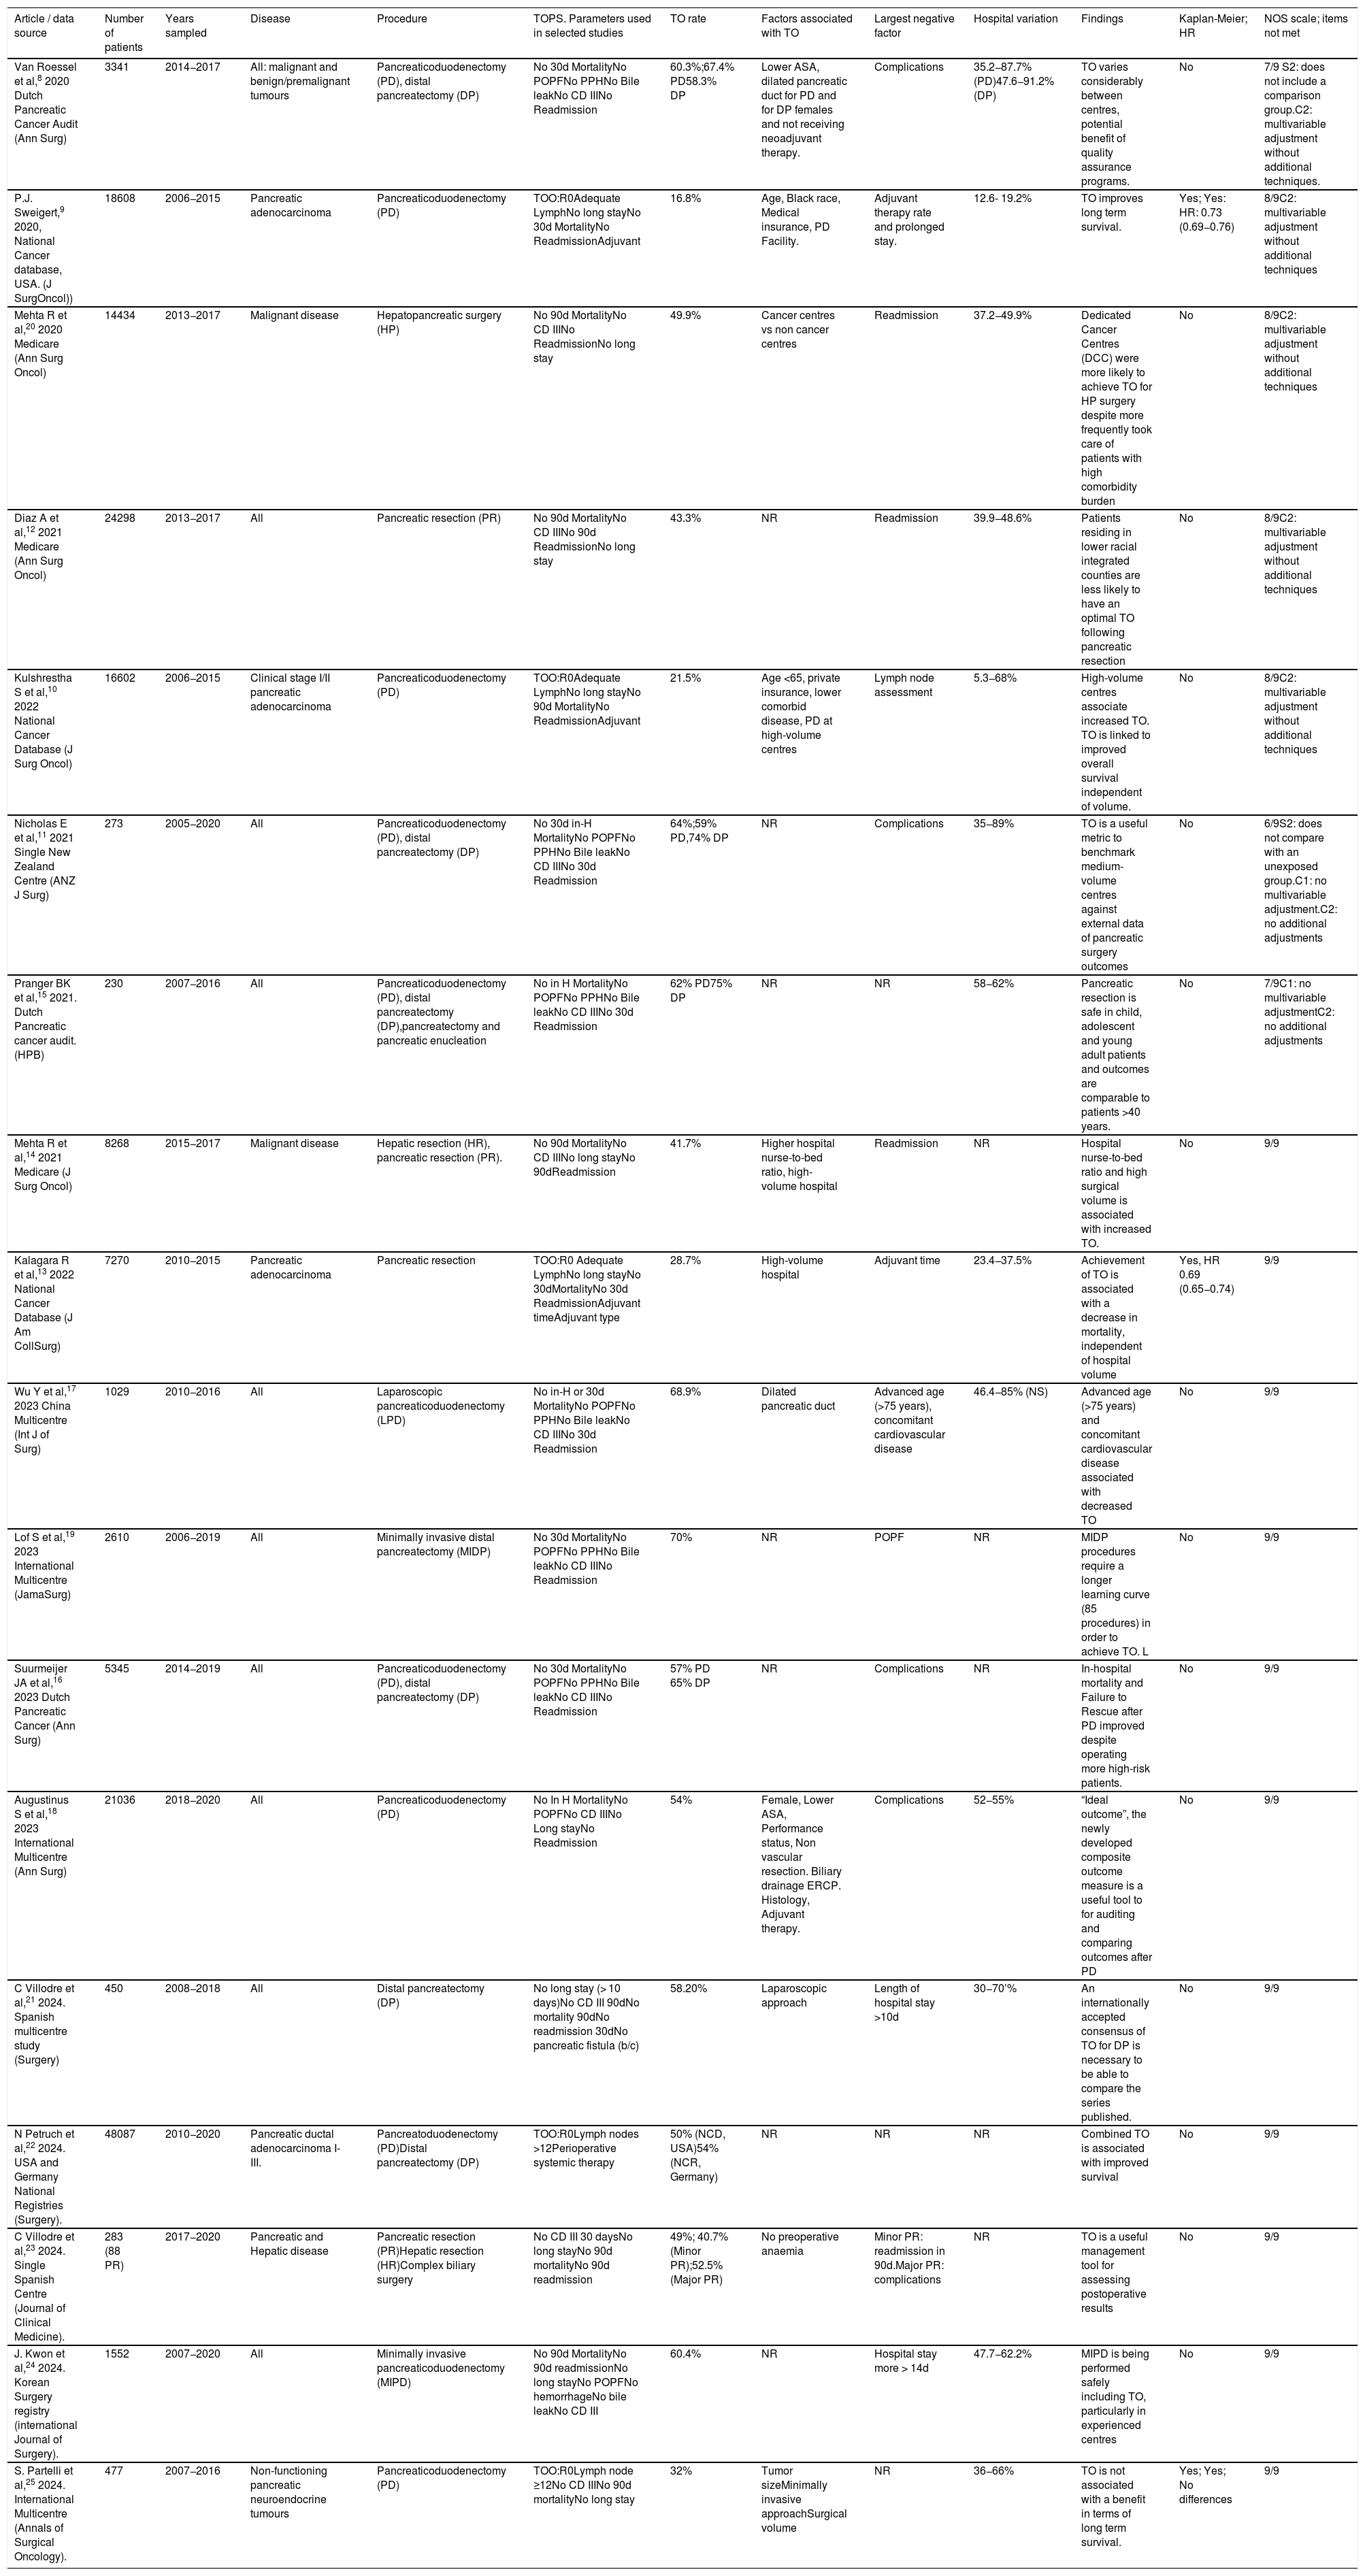
Table 1 shows the studies selected and their main characteristics.
Summary of selected studies.
| Article / data source | Number of patients | Years sampled | Disease | Procedure | TOPS. Parameters used in selected studies | TO rate | Factors associated with TO | Largest negative factor | Hospital variation | Findings | Kaplan-Meier; HR | NOS scale; items not met |
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Van Roessel et al,8 2020 Dutch Pancreatic Cancer Audit (Ann Surg) | 3341 | 2014−2017 | All: malignant and benign/premalignant tumours | Pancreaticoduodenectomy (PD), distal pancreatectomy (DP) | No 30d MortalityNo POPFNo PPHNo Bile leakNo CD IIINo Readmission | 60.3%;67.4% PD58.3% DP | Lower ASA, dilated pancreatic duct for PD and for DP females and not receiving neoadjuvant therapy. | Complications | 35.2−87.7% (PD)47.6−91.2% (DP) | TO varies considerably between centres, potential benefit of quality assurance programs. | No | 7/9 S2: does not include a comparison group.C2: multivariable adjustment without additional techniques. |
| P.J. Sweigert,9 2020, National Cancer database, USA. (J SurgOncol)) | 18608 | 2006−2015 | Pancreatic adenocarcinoma | Pancreaticoduodenectomy (PD) | TOO:R0Adequate LymphNo long stayNo 30d MortalityNo ReadmissionAdjuvant | 16.8% | Age, Black race, Medical insurance, PD Facility. | Adjuvant therapy rate and prolonged stay. | 12.6- 19.2% | TO improves long term survival. | Yes; Yes: HR: 0.73 (0.69−0.76) | 8/9C2: multivariable adjustment without additional techniques |
| Mehta R et al,20 2020 Medicare (Ann Surg Oncol) | 14434 | 2013−2017 | Malignant disease | Hepatopancreatic surgery (HP) | No 90d MortalityNo CD IIINo ReadmissionNo long stay | 49.9% | Cancer centres vs non cancer centres | Readmission | 37.2−49.9% | Dedicated Cancer Centres (DCC) were more likely to achieve TO for HP surgery despite more frequently took care of patients with high comorbidity burden | No | 8/9C2: multivariable adjustment without additional techniques |
| Diaz A et al,12 2021 Medicare (Ann Surg Oncol) | 24298 | 2013−2017 | All | Pancreatic resection (PR) | No 90d MortalityNo CD IIINo 90d ReadmissionNo long stay | 43.3% | NR | Readmission | 39.9−48.6% | Patients residing in lower racial integrated counties are less likely to have an optimal TO following pancreatic resection | No | 8/9C2: multivariable adjustment without additional techniques |
| Kulshrestha S et al,10 2022 National Cancer Database (J Surg Oncol) | 16602 | 2006−2015 | Clinical stage I/II pancreatic adenocarcinoma | Pancreaticoduodenectomy (PD) | TOO:R0Adequate LymphNo long stayNo 90d MortalityNo ReadmissionAdjuvant | 21.5% | Age <65, private insurance, lower comorbid disease, PD at high-volume centres | Lymph node assessment | 5.3−68% | High-volume centres associate increased TO. TO is linked to improved overall survival independent of volume. | No | 8/9C2: multivariable adjustment without additional techniques |
| Nicholas E et al,11 2021 Single New Zealand Centre (ANZ J Surg) | 273 | 2005−2020 | All | Pancreaticoduodenectomy (PD), distal pancreatectomy (DP) | No 30d in-H MortalityNo POPFNo PPHNo Bile leakNo CD IIINo 30d Readmission | 64%;59% PD,74% DP | NR | Complications | 35−89% | TO is a useful metric to benchmark medium-volume centres against external data of pancreatic surgery outcomes | No | 6/9S2: does not compare with an unexposed group.C1: no multivariable adjustment.C2: no additional adjustments |
| Pranger BK et al,15 2021. Dutch Pancreatic cancer audit. (HPB) | 230 | 2007−2016 | All | Pancreaticoduodenectomy (PD), distal pancreatectomy (DP),pancreatectomy and pancreatic enucleation | No in H MortalityNo POPFNo PPHNo Bile leakNo CD IIINo 30d Readmission | 62% PD75% DP | NR | NR | 58−62% | Pancreatic resection is safe in child, adolescent and young adult patients and outcomes are comparable to patients >40 years. | No | 7/9C1: no multivariable adjustmentC2: no additional adjustments |
| Mehta R et al,14 2021 Medicare (J Surg Oncol) | 8268 | 2015−2017 | Malignant disease | Hepatic resection (HR), pancreatic resection (PR). | No 90d MortalityNo CD IIINo long stayNo 90dReadmission | 41.7% | Higher hospital nurse-to-bed ratio, high-volume hospital | Readmission | NR | Hospital nurse-to-bed ratio and high surgical volume is associated with increased TO. | No | 9/9 |
| Kalagara R et al,13 2022 National Cancer Database (J Am CollSurg) | 7270 | 2010−2015 | Pancreatic adenocarcinoma | Pancreatic resection | TOO:R0 Adequate LymphNo long stayNo 30dMortalityNo 30d ReadmissionAdjuvant timeAdjuvant type | 28.7% | High-volume hospital | Adjuvant time | 23.4−37.5% | Achievement of TO is associated with a decrease in mortality, independent of hospital volume | Yes, HR 0.69 (0.65−0.74) | 9/9 |
| Wu Y et al,17 2023 China Multicentre (Int J of Surg) | 1029 | 2010−2016 | All | Laparoscopic pancreaticoduodenectomy (LPD) | No in-H or 30d MortalityNo POPFNo PPHNo Bile leakNo CD IIINo 30d Readmission | 68.9% | Dilated pancreatic duct | Advanced age (>75 years), concomitant cardiovascular disease | 46.4−85% (NS) | Advanced age (>75 years) and concomitant cardiovascular disease associated with decreased TO | No | 9/9 |
| Lof S et al,19 2023 International Multicentre (JamaSurg) | 2610 | 2006−2019 | All | Minimally invasive distal pancreatectomy (MIDP) | No 30d MortalityNo POPFNo PPHNo Bile leakNo CD IIINo Readmission | 70% | NR | POPF | NR | MIDP procedures require a longer learning curve (85 procedures) in order to achieve TO. L | No | 9/9 |
| Suurmeijer JA et al,16 2023 Dutch Pancreatic Cancer (Ann Surg) | 5345 | 2014−2019 | All | Pancreaticoduodenectomy (PD), distal pancreatectomy (DP) | No 30d MortalityNo POPFNo PPHNo Bile leakNo CD IIINo Readmission | 57% PD 65% DP | NR | Complications | NR | In-hospital mortality and Failure to Rescue after PD improved despite operating more high-risk patients. | No | 9/9 |
| Augustinus S et al,18 2023 International Multicentre (Ann Surg) | 21036 | 2018−2020 | All | Pancreaticoduodenectomy (PD) | No In H MortalityNo POPFNo CD IIINo Long stayNo Readmission | 54% | Female, Lower ASA, Performance status, Non vascular resection. Biliary drainage ERCP. Histology, Adjuvant therapy. | Complications | 52−55% | “Ideal outcome”, the newly developed composite outcome measure is a useful tool to for auditing and comparing outcomes after PD | No | 9/9 |
| C Villodre et al,21 2024. Spanish multicentre study (Surgery) | 450 | 2008−2018 | All | Distal pancreatectomy (DP) | No long stay (> 10 days)No CD III 90dNo mortality 90dNo readmission 30dNo pancreatic fistula (b/c) | 58.20% | Laparoscopic approach | Length of hospital stay >10d | 30−70’% | An internationally accepted consensus of TO for DP is necessary to be able to compare the series published. | No | 9/9 |
| N Petruch et al,22 2024. USA and Germany National Registries (Surgery). | 48087 | 2010−2020 | Pancreatic ductal adenocarcinoma I-III. | Pancreatoduodenectomy (PD)Distal pancreatectomy (DP) | TOO:R0Lymph nodes >12Perioperative systemic therapy | 50% (NCD, USA)54% (NCR, Germany) | NR | NR | NR | Combined TO is associated with improved survival | No | 9/9 |
| C Villodre et al,23 2024. Single Spanish Centre (Journal of Clinical Medicine). | 283 (88 PR) | 2017−2020 | Pancreatic and Hepatic disease | Pancreatic resection (PR)Hepatic resection (HR)Complex biliary surgery | No CD III 30 daysNo long stayNo 90d mortalityNo 90d readmission | 49%; 40.7% (Minor PR);52.5% (Major PR) | No preoperative anaemia | Minor PR: readmission in 90d.Major PR: complications | NR | TO is a useful management tool for assessing postoperative results | No | 9/9 |
| J. Kwon et al,24 2024. Korean Surgery registry (international Journal of Surgery). | 1552 | 2007−2020 | All | Minimally invasive pancreaticoduodenectomy (MIPD) | No 90d MortalityNo 90d readmissionNo long stayNo POPFNo hemorrhageNo bile leakNo CD III | 60.4% | NR | Hospital stay more > 14d | 47.7−62.2% | MIPD is being performed safely including TO, particularly in experienced centres | No | 9/9 |
| S. Partelli et al,25 2024. International Multicentre (Annals of Surgical Oncology). | 477 | 2007−2016 | Non-functioning pancreatic neuroendocrine tumours | Pancreaticoduodenectomy (PD) | TOO:R0Lymph node ≥12No CD IIINo 90d mortalityNo long stay | 32% | Tumor sizeMinimally invasive approachSurgical volume | NR | 36−66% | TO is not associated with a benefit in terms of long term survival. | Yes; Yes; No differences | 9/9 |
ASA: American Society of Anesthesiologists Performance Status; CD: Clavien-Dindo Classification of surgical complications; ERCP: endoscopic retrograde cholangiopancreatography; HR: Hazard Ratio; LOS: Length of Stay; NOS: Newcastle-Ottawa scale; NR: not reported; POPF: Post-Operative Pancreatic Fistula; PPH: Post-Pancreatectomy Haemorrhage; TO: Textbook Outcome; TOO: Textbook Oncologic Outcome; TOPS: Textbook Outcome in Pancreatic Surgery.
Pancreatic cancer is a highly aggressive neoplasm which currently constitutes the fourth leading cause of cancer-related death in Western countries.2 Surgery remains the fundamental pillar in the treatment of pancreatic cancer and the only potentially curative option, with a morbidity rate of around 50% and a 90-day mortality ranging between 2 and 8%.4,5 In this context, the evaluation of surgical care using objective and standardised quality measures becomes increasingly relevant, and the Textbook Outcome in Pancreatic Surgery (TOPS) has become consolidated as a composite metric that enables a comprehensive assessment of postoperative outcomes.
The definitions of TOPS have shown notable heterogeneity since its introduction in 2020. Although all the studies employed an “all or nothing” structure, the selection of criteria varied based on the design, surgical indication, and type of cohort in each study. In 2020, two main models were described: the TO defined in Annals of Surgery by van Roessel et al.,8 focused on immediate clinical outcomes, and the OTO defined in Journal of Surgical Oncology by Sweigert et al.,9 focused on oncological parameters.
In spite of this initial variability, recent literature has tended towards greater standardisation, based on widely accepted criteria such as an absence of major complications, mortality, prolonged hospital stay, and readmission, complemented in oncological studies by R0 resection, adequate lymphadenectomy, and optimal administration of adjuvant therapy. This evolution reflects a methodological maturation of the concept and its adaptation to different clinical environments. Nevertheless, the criterion of hospital stay remains heterogeneous in its definition and cut-off point, which currently limits its uniform integration into TOPS variables.
Our analysis evidenced a significant variability in the achievement of TOPS, with rates ranging between 17% and 70%. Series including both benign and malignant pathologies showed higher values, while exclusively oncological cohorts presented more homogeneous results, probably due to their greater clinical complexity and the impact of criteria like R0 and the administration of adjuvant treatment.
Major complications (Clavien–Dindo > II) were consistently the main obstacle to achieving TOPS. These findings agree with the literature on pancreatic surgery, where postoperative complications remain the main determinant of recovery and healthcare costs.
Another notable finding in our review was the level of inter-hospital variability, with relevant differences within individual studies. These results reinforce the usefulness of TOPS as a benchmarking tool, since it enables areas of improvement to be identified and objectively compares quality between centres by volume, resources, and organisational processes.
Only three studies included an analysis of survival using Kaplan–Meier curves. In two of them, focusing on pancreatic adenocarcinoma, patients who achieved an OTO presented higher overall survival, an expected result given that this criterion incorporates oncological variables that are closely linked to the prognosis. On the other hand, the study by Partelli et al.,25 examining non-functioning pancreatic neuroendocrine tumours, did not find this association, probably due to the less aggressive nature of these neoplasms and the reduced influence of perioperative factors on long-term survival. Overall, the available evidence suggests that, for exocrine pancreatic cancer, the concept of OTO could provide additional prognostic information. However, doubts remain as to whether the achievement of non-oncological TO can also be translated into a significant improvement in survival, an aspect which should be studied further.
Data published in 2025 provide a complementary dimension to the concept of measuring surgical quality. A systematic review and meta-analysis of ERAS programmes in pancreatic surgery found that standardisation of perioperative management reduces hospital stay and costs without increasing complications or readmission rates, thus promoting achievement of a TO.6
Moreover, a systematic clinical review in pancreatic adenocarcinoma identified that the main determinants of survival —R0 resection, adequate lymphadenectomy, early start of adjuvant therapy, and treatment at high-volume centres— closely match the items in OTO.7 These findings support the hypothesis that integrating process-based strategies (ERAS) with oncological and structural standards (OTOPS) constitutes a robust overall quality model.
To the best of our knowledge, the present work is the first systematic review published on TOPS. The findings of this review could serve as a starting point to develop consensus-based quality indicators, facilitate comparisons between different centres, and guide future research aimed at the continuous improvement of pancreatic surgery.6
ConclusionsTOPS has emerged as a composite metric capable of reliably summarising the overall quality of pancreatic surgery. The present analysis shows a progressive methodological improvement, a trend towards standardisation of criteria, and a possible association with better clinical outcomes. These findings establish TOPS as a key indicator in quality monitoring and benchmarking among centres, as well as a solid starting point for future international consensus strategies.7
FundingThe present review did not receive any specific funding from public, private or non-profit entities.
The authors have no conflicts of interests to declare.


