




Main treatment options for pharyngoesophageal diverticulum are the surgical excision or diverticulopexy, always associated with a myotomy, and the endoscopic peroral myotomy. The aim of this study was to describe the outcomes of a consecutive surgical series.
MethodsObservational study of patients who underwent open surgery (2004–2024) and who had a 2-years structured follow-up. Main outcome were symptom resolution and postoperative complications. Baseline characteristics, surgical technique, reinterventions, readmission and recurrence were also analyzed. Descriptive statistics was used, including percentages, mean and standard deviations, and medians with complete ranges.
ResultsDuring the study period, 40 patients (73% male) were operated on, with a mean age of 72 ± 11 years. Ninety-five percent presented dysphagia and/or regurgitation, while 2 patients were referred due to a history of pneumonia to bronchoaspiration. The most frequent surgical technique was cricopharyngeal myotomy combined with diverticulectomy. Postoperative morbidity was 15%, with no cases of esophageal fistula. There was no mortality, and the median hospital stay was 3 days. Initial symptom resolution was achieved in 95% of patients. During follow-up (median 7 years [1–20]), 2 recurrences were observed at 18 and 24 months, respectively, both successfully managed endoscopically.
ConclusionsSurgical treatment achieves symptoms resolution in the vast majority of cases, with limited morbidity and recurrence.
Las principales alternativas terapéuticas del divertículo faringoesofágico son la cirugía (miotomía con resección o pexia) y el tratamiento endoscópico (septotomía transoral). El objetivo de este estudio es describir los resultados de una serie consecutiva de pacientes tratados quirúrgicamente.
MétodosEstudio observacional descriptivo de pacientes intervenidos quirúrgicamente (2004–2024), con un seguimiento protocolizado hasta los 24 meses. Las variables principales fueron la resolución de los síntomas y las complicaciones postoperatorias. Se analizaron además las características clínicas basales, la técnica quirúrgica, las readmisiones, las reintervenciones y las recidivas. Se utilizó estadística descriptiva con cálculo de porcentaje, medias y desviaciones estándar y medianas y rangos completos.
ResultadosDurante el período del estudio se intervinieron 40 pacientes (73% hombres), con una media de edad de 72 ± 11 años. El 95% consultó por disfagia y/o regurgitación y 2 pacientes fueron referidos por historia de neumonías secundarias a broncoaspiración. La técnica quirúrgica más frecuente fue la miotomía del cricofaríngeo asociada a una diverticulectomía. La morbilidad postoperatoria fue del 15%, sin demostrarse fístula esofágica en ningún caso. No hubo mortalidad postoperatoria y la estancia mediana fue de 3 días. La resolución inicial de los síntomas fue del 95%. Durante el seguimiento (mediana de 7 años [1–20]), se constataron 2 recidivas (a los 18 y 24 meses, respectivamente), ambas tratadas con éxito por vía endoscópica.
ConclusionesEl tratamiento quirúrgico permite la resolución de los síntomas en la práctica mayoría de casos, con una morbilidad y una recidiva limitadas.

Pharyngoesophageal diverticulum (POD), also known as Zenker's diverticulum, is a rare condition characterised by a loss of distensibility of the upper oesophageal sphincter.1 The most important symptoms are dysphagia and regurgitation, although in the most severe cases, frequent bronchoaspiration and pneumonia may occur.2
Surgical treatment requires a cervical approach involving a myotomy of the cricopharyngeal muscle and resection of the diverticulum (diverticulectomy), with diverticulopexy or pexy reserved for small diverticula.3,4 The most significant postoperative complications are leak and cervical haematomas, both of which can be serious.5 In the long term, the most significant complication is the persistence of symptoms, whether or not they are associated with recurrence.
In recent decades, endoscopic techniques have been proposed as an alternative to surgery. These techniques involve performing a myotomy transorally to create a wide opening between the oesophagus and the diverticulum, facilitating its emptying.6,7
Some authors have compared the results of the two approaches.8–10 They found differences in terms of symptom resolution (in favour of surgery), the need for reoperations due to persistent symptoms or recurrence of the diverticulum (more frequent with endoscopic treatment) and recovery times and hospital stays (longer with surgery).
This study aims to describe the short- and long-term results of surgical treatment for POD in consecutive patients, with a focus on symptom resolution, postoperative complications, recurrence, and reoperation rates.
MethodsStudy design and participantsThis descriptive, observational study examined consecutive cases of patients with POD who underwent surgery by the same surgeon at a university hospital between 2004 and 2024. Protocolised follow-up was conducted for up to 24 months after surgery. The primary outcome was symptom resolution. Other analysed variables included baseline clinical characteristics, preoperative studies, surgical techniques, postoperative complications, hospital stays, recurrences, and reoperations. The sex variable was defined as the biological characteristic at birth (male/female).
Patients treated endoscopically were excluded. One patient whose primary diagnosis was gastric cancer was also excluded. This patient underwent laparoscopic gastrectomy in conjunction with surgical treatment of POD. The established follow-up is unavailable due to postoperative complications arising from the abdominal oncological surgery.
The study was approved by the Clinical Research Ethics Committee (CEIC, no. 2025/11930) of the Hospital del Mar Medical Research Institute (IMIM) and was conducted in accordance with the MInCir initiative for reporting descriptive observational studies.11
Preoperative clinical assessmentDuring the preoperative consultation, a detailed medical history was taken, focusing in particular on aspects such as dysphagia or regurgitation, as well as vomiting, pain, coughing, aspiration, and halitosis. The severity of dysphagia was estimated using the scale proposed by Duranceau and Ferraro,12 which assesses frequency (occasional: 1 point; more than once a month and less than once a week: 2 points; more than once a week, but not daily: 3 points; daily: 4 points), duration (less than 6 months: 1 point; 6 months to 2 years: 2 points; 2–5 years: 3 points; more than 5 years: 4 points), and intensity (mild: 1 point; moderate: 2 points; marked: 3 points; severe: 4 points). The sum of the points obtained in the frequency and duration sections is multiplied by the score obtained in the intensity section, giving a minimum result of 2 points and a maximum of 32. This system classifies dysphagia into four levels: mild (2–7 points), moderate (8–15 points), marked (16–23 points), and severe (24–32 points). In addition, the Charlson comorbidity index13 was calculated for all patients, and the necessary tests were performed to confirm the diagnosis (contrast oesophageal transit, video fluoroscopy, and/or oesophagogastroscopy).
Surgical techniqueThe surgery was performed under general anaesthesia and orotracheal intubation, with routine antibiotic prophylaxis administered beforehand. The surgical technique involved a left oblique cervicotomy following the anterior border of the sternocleidomastoid muscle. After retracting the prethyroid muscles and ligating the inferior thyroid artery, the oesophagus and pharyngoesophageal junction were identified. Then, a 36 French Maloney tube was inserted orally and used as a guide during the myotomy and diverticular resection. An extensive myotomy was performed, including the cricopharyngeal muscle, 2 cm of the cervical oesophagus proximal to it and 1 cm of the posterior hypopharyngeal muscle.14 The diverticulum was excised using a linear mechanical suturing device to maintain the oesophageal calibre with the aid of the Maloney tube. Where the diverticulum measured < 10 mm, it was fixed to the prevertebral fascia. In all cases, a drain was placed in the area of the oesophageal section before closing the surgical wound.
Postoperative assessment and follow-upPostoperative complications occurring within 90 days after surgery were recorded and classified according to the Clavien-Dindo proposal.15 The length of hospital stay, readmissions at 90 days, and the need for reoperations were also documented.
All patients were followed up in outpatient consultations at the Gastrointestinal Surgery Unit. A first postoperative check-up (within 2 months of surgery) was systematically performed, including an evaluation with videolaryngoscopy and video fluoroscopy, followed by followed by clinical follow-up at 6, 12, 18, and 24 months, at which time patients were discharged with instructions to return for consultation if symptoms recurred. All patients who developed symptoms suggestive of recurrence also underwent oesophageal transit (barium swallow).
All patients were followed up by telephone survey in August 2025, using a standardised questionnaire to assess the severity of dysphagia, if present.12
Statistical analysisBasic descriptive statistics were used to calculate means and standard deviations for demographic characteristics, medians, and extreme values (full range) for surgical data and postoperative outcomes, using Stata 11.0 software.
ResultsDuring the study period, 40 patients (75% men) underwent surgery, with a mean age of 72 ± 11 years. Of these patients, 57.5% (23 patients) had a high comorbidity burden (Charlson index ≥ 3), of whom 37.5% (15 patients) were classified as ASA III or IV.
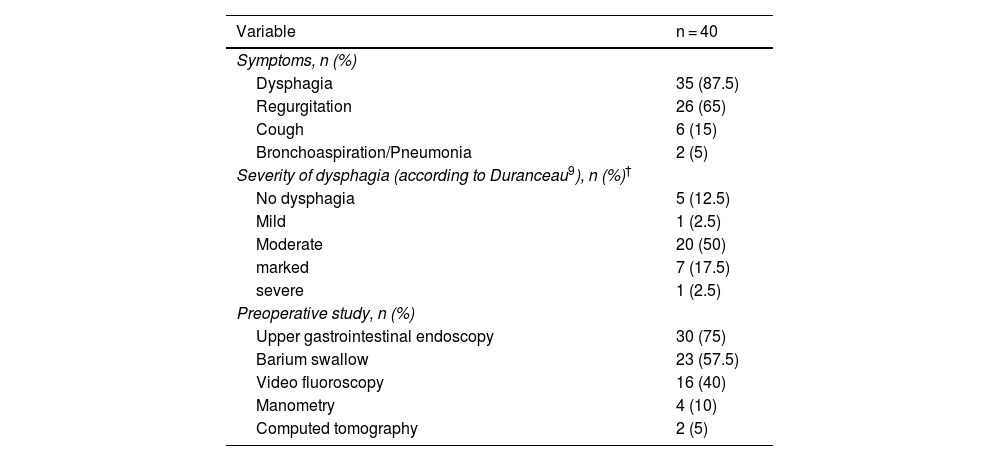
As shown in Table 1, the most frequent reasons for consultation were dysphagia and regurgitation, with 95% of patients presenting with at least one of these symptoms. The mean dysphagia score was 13 ± 5, and 70% of patients presented with moderate, severe, or very severe dysphagia. In two cases, surgery was indicated due to recurrent pneumonia secondary to bronchoaspiration, one of which was necrotising. The preoperative studies performed are detailed in Table 1.
Baseline clinical characteristics and preoperative study of patients.
| Variable | n = 40 |
|---|---|
| Symptoms, n (%) | |
| Dysphagia | 35 (87.5) |
| Regurgitation | 26 (65) |
| Cough | 6 (15) |
| Bronchoaspiration/Pneumonia | 2 (5) |
| Severity of dysphagia (according to Duranceau9), n (%)† | |
| No dysphagia | 5 (12.5) |
| Mild | 1 (2.5) |
| Moderate | 20 (50) |
| marked | 7 (17.5) |
| severe | 1 (2.5) |
| Preoperative study, n (%) | |
| Upper gastrointestinal endoscopy | 30 (75) |
| Barium swallow | 23 (57.5) |
| Video fluoroscopy | 16 (40) |
| Manometry | 4 (10) |
| Computed tomography | 2 (5) |
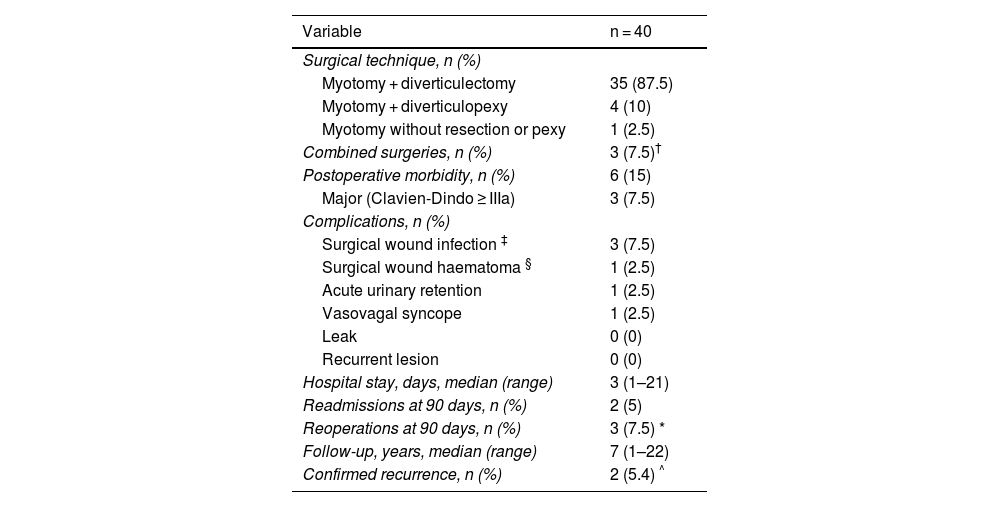
The operative characteristics and postoperative results are presented in Table 2. The most frequently performed surgical technique was cricopharyngeal myotomy with diverticulectomy (87.5%). The mean surgical time was 123 ± 36 min. The overall postoperative morbidity rate was 15%, with surgical wound infection being the most frequent complication (3 cases). There was no evidence of leak in any case. The median hospital stay was 3 days (range 1–21). Three patients were readmitted due to major complications: a cervical abscess in 2 cases and a cervical haematoma in 1 case. All of these complications required surgical intervention. Routine postoperative videolaryngoscopy revealed no recurrent nerve injury. There was no postoperative mortality.
Operative and postoperative variables.
| Variable | n = 40 |
|---|---|
| Surgical technique, n (%) | |
| Myotomy + diverticulectomy | 35 (87.5) |
| Myotomy + diverticulopexy | 4 (10) |
| Myotomy without resection or pexy | 1 (2.5) |
| Combined surgeries, n (%) | 3 (7.5)† |
| Postoperative morbidity, n (%) | 6 (15) |
| Major (Clavien-Dindo ≥ IIIa) | 3 (7.5) |
| Complications, n (%) | |
| Surgical wound infection ‡ | 3 (7.5) |
| Surgical wound haematoma § | 1 (2.5) |
| Acute urinary retention | 1 (2.5) |
| Vasovagal syncope | 1 (2.5) |
| Leak | 0 (0) |
| Recurrent lesion | 0 (0) |
| Hospital stay, days, median (range) | 3 (1–21) |
| Readmissions at 90 days, n (%) | 2 (5) |
| Reoperations at 90 days, n (%) | 3 (7.5) * |
| Follow-up, years, median (range) | 7 (1–22) |
| Confirmed recurrence, n (%) | 2 (5.4) ^ |
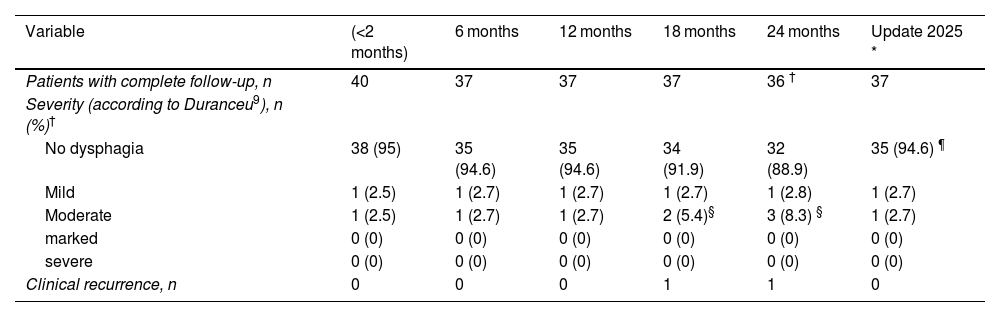
Table 3 summarises the follow-up data for this series. At the first postoperative check-up (always within 2 months), 38 patients (95%) were asymptomatic. Two patients (one with a history of laryngeal surgery and one with a nutcracker oesophagus) had persistent dysphagia, although it was less severe than preoperatively (progressing from marked/severe to mild/moderate). There was no evidence of POD recurrence. In two patients, dysphagia reappeared (at 18 and 24 months, respectively) and was associated with recurrence of POD. Both cases were successfully treated with an endoscopic myotomy using bipolar forceps (Ligasure®) and a flexible endoscope. They have remained asymptomatic for over 12 months following endoscopic treatment.
Assessment of dysphagia during follow-up.
| Variable | (<2 months) | 6 months | 12 months | 18 months | 24 months | Update 2025 * |
|---|---|---|---|---|---|---|
| Patients with complete follow-up, n | 40 | 37 | 37 | 37 | 36 † | 37 |
| Severity (according to Duranceu9), n (%)† | ||||||
| No dysphagia | 38 (95) | 35 (94.6) | 35 (94.6) | 34 (91.9) | 32 (88.9) | 35 (94.6) ¶ |
| Mild | 1 (2.5) | 1 (2.7) | 1 (2.7) | 1 (2.7) | 1 (2.8) | 1 (2.7) |
| Moderate | 1 (2.5) | 1 (2.7) | 1 (2.7) | 2 (5.4)§ | 3 (8.3) § | 1 (2.7) |
| marked | 0 (0) | 0 (0) | 0 (0) | 0 (0) | 0 (0) | 0 (0) |
| severe | 0 (0) | 0 (0) | 0 (0) | 0 (0) | 0 (0) | 0 (0) |
| Clinical recurrence, n | 0 | 0 | 0 | 1 | 1 | 0 |
In August 2025 (median follow-up of 7 years), the status of 37 patients (92.5%) in the series was updated by telephone. Complete resolution of symptoms was observed in 35 of them [35/37, (94.6%)] and the persistence of some degree of dysphagia only in the 2 patients mentioned above.
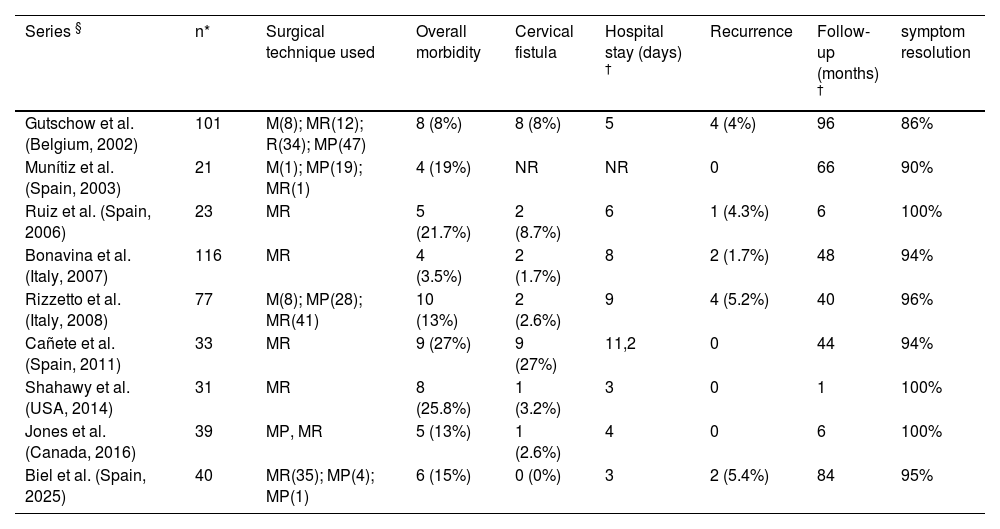
DiscussionThe results obtained in this series reinforce the importance of surgery in an era characterised by endoscopic techniques. Symptom resolution is almost complete, with a very low rate of clinical recurrence. The most controversial point is the complication rate. One in 6 patients experiences some type of complication, which could be considered high for elective, superficial, and functional surgery, even when the patient's preoperative situation is taken into account (advanced average age, high rate of comorbidities and perhaps, although this aspect has not been analysed in our study, a certain degree of malnutrition caused by severe or very severe dysphagia experienced by a large proportion of patients). However, a study by the ACS-NSQIP16 found no direct relationship between comorbidities and complications. In our experience, complications related to the surgical wound are particularly prevalent, especially infectious complications, despite the antibiotic prophylaxis administered to all patients and the usual precautions taken in the surgical field. In addition, two patients required reoperation to resolve an infectious complication. While this figure may seem high, it is similar to those reported in other studies in our field, ranging from the 19% of Munitiz et al.17 and the 21% of Ruiz et al.18 to the 27% of Cañete et al.19; however, in the latter study, all complications were due to leak, which were completely absent in our study. Table 4 details the most relevant results obtained in national and international series in which myotomy was performed via a cervical approach. As in our series, symptom control was achieved in 95%–100% of patients, with a clinical recurrence rate of less than 5%. However, hospital stay, and the duration of patient follow-up can vary greatly, from 1 to 21 days. These factors can clearly influence the detected recurrence rate. It is important to compare our results with those obtained by Bonavina et al.,20 in the largest series published to date (116 patients). Their overall morbidity rate was lower, with one case of mortality and a fistula rate of 2%.
Summary of the results of pharyngoesophageal diverticulum treatment in Spain and worldwide.
| Series § | n* | Surgical technique used | Overall morbidity | Cervical fistula | Hospital stay (days) † | Recurrence | Follow-up (months) † | symptom resolution |
|---|---|---|---|---|---|---|---|---|
| Gutschow et al. (Belgium, 2002) | 101 | M(8); MR(12); R(34); MP(47) | 8 (8%) | 8 (8%) | 5 | 4 (4%) | 96 | 86% |
| Munítiz et al. (Spain, 2003) | 21 | M(1); MP(19); MR(1) | 4 (19%) | NR | NR | 0 | 66 | 90% |
| Ruiz et al. (Spain, 2006) | 23 | MR | 5 (21.7%) | 2 (8.7%) | 6 | 1 (4.3%) | 6 | 100% |
| Bonavina et al. (Italy, 2007) | 116 | MR | 4 (3.5%) | 2 (1.7%) | 8 | 2 (1.7%) | 48 | 94% |
| Rizzetto et al. (Italy, 2008) | 77 | M(8); MP(28); MR(41) | 10 (13%) | 2 (2.6%) | 9 | 4 (5.2%) | 40 | 96% |
| Cañete et al. (Spain, 2011) | 33 | MR | 9 (27%) | 9 (27%) | 11,2 | 0 | 44 | 94% |
| Shahawy et al. (USA, 2014) | 31 | MR | 8 (25.8%) | 1 (3.2%) | 3 | 0 | 1 | 100% |
| Jones et al. (Canada, 2016) | 39 | MP, MR | 5 (13%) | 1 (2.6%) | 4 | 0 | 6 | 100% |
| Biel et al. (Spain, 2025) | 40 | MR(35); MP(4); MP(1) | 6 (15%) | 0 (0%) | 3 | 2 (5.4%) | 84 | 95% |
M, myotomy only; MR, myotomy and resection or diverticulectomy; MP, myotomy and fixation or diverticulopexy; R, resection only; NR, not reported.
Regarding the surgical technique, the standard procedure in our series is myotomy associated with diverticulum resection. However, it is important to note that the choice of technique may be influenced by factors such as the size of the diverticulum. Thus, for small diverticula, diverticulopexy seems to be an effective alternative. This is consistent with the findings reported by Rizzetto et al.,21 regarding treatment tailored to each case according to diverticulum size, as well as with the findings reported in a series involving only myotomy + diverticulopexy, which produced excellent results in terms of morbidity and no recurrences.22
In recent years, there has been a surge in endoscopic techniques for treating POD. In general terms, when comparing the results of the two approaches, the complication and symptom resolution rates are lower in endoscopic techniques, although the recurrence rate is higher.6,10,23–26 It is important to note that the difference in complications between surgical and endoscopic techniques is even greater when analysing the results of groups of ENT specialists, who are more likely to use the endoscopic approach.26 A systematic review has shown that surgery is associated with significantly higher rates of symptom resolution than endoscopic techniques.9 Therefore, we advocate the surgical approach due to its greater capacity for resolution. However, the endoscopic approach can be a very useful additional technique for treating recurrences, as some authors have demonstrated.27,28 The two patients in our series with recurrence were successfully treated endoscopically.
This study has two clear limitations. Firstly, it is a retrospective observational study of a relatively small sample size, although it is the largest in the national context (see Table 4). The study's greatest strengths are its long follow-up period (more than 7 years) and the use of a standardised protocol throughout, which lends consistency to the results, particularly with regard to recurrence rate and dysphagia control.
ConclusionsSurgical treatment of POD achieves a high rate of symptom resolution, with no mortality and a low rate of long-term clinical recurrence.
Financial supportNo external funding was received for the study.
The authors have no conflicts of interest to declare.
Authors are grateful to Dr. María Alejandra Guerrero (Hospital Universitari Joan XXIII, Tarragona, Spain) for her assistance in data collection.


