




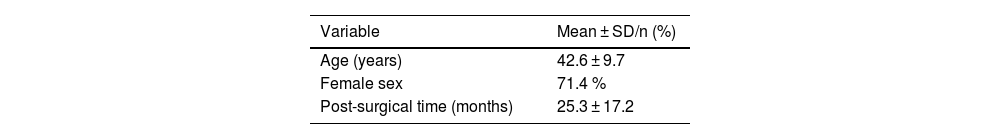
Food satisfaction and the relationship with food are key determinants of quality of life after bariatric surgery; however, the factors that modulate them remain poorly defined. The objective of this study was to analyse the eating experience of bariatric surgery patients and identify the clinical, behavioural, and psychosocial factors that influence it.
MethodsA cross-sectional study was conducted with 63 patients (71.4% women; age 42.6 ± 9.7 years) who underwent gastric bypass or gastric sleeve surgery (25.3 ± 17.2 months). Sociodemographic data, postoperative time, and self-reported variables were collected: eating satisfaction (Likert 1–5), relationship with food (VAS 1–10), self-esteem, physical activity, and eating patterns. ANOVA and multiple linear regression (α = 0.05) were applied.
Results47.6% reported being able to eat any food. These patients showed greater food satisfaction than those reporting restrictions (4.20 ± 0.68 vs. 3.48 ± 0.87; F = 12.96; p < 0.001; η2 < p <!--/ sub--> = 0.18). The timing of the main meal was associated with the relationship with food (F = 3.49; p = 0.037): lunch (7.62 ± 1.89) > dinner (5.38 ± 2.77). The multivariate model explained 45% of the variance in the relationship with food (R² = 0.454): self-esteem (β = 0.53; p < 0.001) and physical activity (β = 0.23; p = 0.043) were independent predictors, while postoperative time was not significant (p = 0.232).
ConclusionsPerceived dietary flexibility, self-esteem, and regular physical activity are the main determinants of a satisfactory eating experience after bariatric surgery, above and beyond the mere passage of time. These results support the inclusion of psychological interventions and structured physical exercise in multidisciplinary postoperative follow-up.
La satisfacción alimentaria y la relación con la comida son determinantes clave de la calidad de vida tras la cirugía bariátrica; sin embargo, los factores que las modulan siguen poco definidos. El objetivo del estudio es analizar la experiencia alimentaria de pacientes operados de cirugía bariátrica e identificar los factores clínicos, conductuales y psicosociales que la condicionan.
MétodosEstudio transversal con 63 pacientes (71,4 % mujeres; edad 42,6 ± 9,7 años) intervenidos de bypass gástrico o manga gástrica (25,3 ± 17,2 meses de evolución). Se recogieron datos sociodemográficos, tiempo posquirúrgico y variables auto-informadas: satisfacción al comer (Likert 1–5), relación con la comida (EVA 1–10), autoestima, actividad física y patrón de ingesta. Se aplicaron ANOVA y regresión lineal múltiple (α = 0,05).
ResultadosEl 47,6 % declaró poder ingerir cualquier alimento. Estos pacientes mostraron mayor satisfacción alimentaria que quienes referían restricciones (4,20 ± 0,68 vs. 3,48 ± 0,87; F = 12,96; p < 0,001; η2 < sub > p = 0,18). El momento de la ingesta principal se asoció a la relación con la comida (F = 3,49; p = 0,037): almuerzo (7,62 ± 1,89) > cena (5,38 ± 2,77). El modelo multivariante explicó el 45 % de la varianza en la relación con la comida (R² = 0,454): autoestima (β = 0,53; p < 0,001) y actividad física (β = 0,23; p = 0,043) fueron predictores independientes, mientras que el tiempo posquirúrgico no resultó significativo (p = 0,232).
ConclusionesLa percepción de flexibilidad dietética, la autoestima y la práctica regular de actividad física son los principales determinantes de una experiencia alimentaria satisfactoria tras la cirugía bariátrica, por encima del mero paso del tiempo. Estos resultados apoyan la inclusión de intervenciones psicológicas y de ejercicio físico estructurado en el seguimiento multidisciplinar postoperatorio.

Class III severe obesity (SO), defined as a body mass index (BMI) of ≥40 kg/m2,1 represents a global public health challenge with ever increasing prevalence. Beyond its metabolic and cardiovascular implications,2 SO severely compromises health-related quality of life (HRQoL) through physical limitations, social stigmatisation and psychological disorders that cause individual discomfort, poor academic performance and difficulties in the full integration of individuals.3,4 The treatment approach to obesity is aimed at improving or eliminating associated comorbidities and reducing the impact of future complications related to excess weight.5 Bariatric surgery (BS) has established itself as the most effective intervention to achieve sustained weight loss and improvement in comorbidities in these patients,6,7 Post-surgical success depends not only on anthropometric changes and the resolution of diabetes but also on the patient’s degree of psychological, social and behavioural to his or her new situation in terms of their physical body and diet. 8
There is no cure for obesity and the aim of treatment is to attenuate or eliminate the diseases associated with it; to avoid its complications and, thirdly, to improve the person's well-being. Therefore, the classic outcome measures of a treatment intervention, such as mortality and morbidity, including the cost-effectiveness ratio, are insufficient to correctly assess the impact of a treatment measure on obesity.9
Among the determining factors involved in adaptation to life after BS are: satisfaction with food; management of food-related anxiety; perception of control; and restructuring of the body image.10,11
HRQoL is a multidimensional and dynamic concept which encompasses the impact of the disease and the treatments applied on the individual and their environment. It encompasses physical, emotional and social well-being,12 emerging as a critical outcome that reflects the patient's subjective perception of his or her postoperative health status.13–15
It can be said that most people with obesity who request treatment with BS do so because of the deterioration in their quality of life, even if they are not aware of this.9 Longitudinal studies show that BS produces significant improvements in HRQoL16
The aim of this study was to analyse the degree of food satisfaction amongst patients undergoing BS; identify factors that are significantly associated with such satisfaction; and explore predictors of a healthy relationship with food.
Material and methodStudy design and participantsA retrospective cross-sectional observational study was conducted on a sample of 63 adult patients who had undergone bariatric surgery in the previous five years in a tertiary hospital. Data analysis was conducted between January and April 2025.
The inclusion criteria were: (a) having undergone bariatric surgery (gastric bypass or gastric sleeve), (b) having at least 3 months of postoperative evolution, (c) absence of any active surgical complications or acute psychiatric diseases at the time of the study. All participants signed informed consent.
InstrumentsRetrospective data collection was through participants’ medical records. The data analysed was obtained through the instruments used for routine practice in outpatient visits for post-hoc follow-up of BS17; in this case, the Moorehead-Ardelt II0 (MA-II) questionnaire9 and the assessment of dietary quality from the questionnaire described by Suter et al.18 Each patient completed a single questionnaire. For studies that have already been run, the General Data Protection Regulation (GDPR, Regulation (EU) 2016/679) allows data to be used for scientific research purposes without explicit consent, provided that certain conditions are met. In this case, Article 9(j) applies: the processing of sensitive data (such as health data) for scientific research purposes, provided that this is based on a legal standard and appropriate safeguards are in place, under Article 89.
The Moorehead-Ardelt II (MA-II) Questionnaire is a widely used standardised instrument for the assessment of health-related quality of life (HRQoL) in patients undergoing bariatric surgery. This questionnaire assesses key dimensions of postoperative psychosocial and physical well-being, considering five items: self-esteem, physical activity, social life, work and activities of daily living, and satisfaction with diet. Each item was scored on a scale of −1 to +1, producing an overall result that classified the success of the surgery as “failure", "fair", "good", "very good" or "excellent". Cultural and linguistic adaptation to Spanish was crucial to ensure cross-cultural validity, since concepts such as "self-esteem" or "satisfaction with diet" are influenced by specific sociocultural contexts. The adapted version involved not only a linguistic translation but also a semantic adaptation that reflected the particularities of Spanish-speaking populations, avoiding interpretative biases.9
For the study, an anonymised database was designed that included sociodemographic and clinical variables, along with post-surgical dietary experience, the Moorehead-Ardelt II (MA-II) questionnaire9 and the evaluation of the quality of the diet in the questionnaire described by Suter et al., translated into Spanish and adapted accordingly.18
Statistical analysisFrequency and percentage analyses were performed to describe categorical variables. For between-group comparisons, one-factor ANOVA tests were used. A multiple linear regression model was constructed with the relationship with food as a dependent variable. The level of statistical significance was set at p < 0.05. The analyses were run with Python version 3.13 (Pandas, Statsmodels and Seaborn).
ResultsA total of 63 patients were included, all of whom underwent bariatric surgery and had no additional comorbidity (mean age 42.6 ± 9.7 years; 71.4% women; mean postoperative time 25.3 ± 17.2 months) (Table 1).
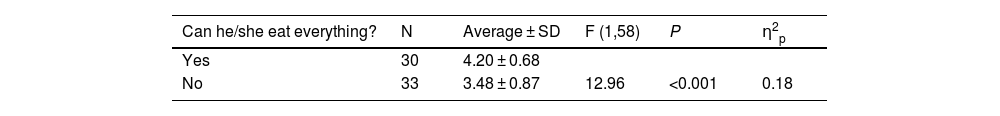
A total of 47.6% (n = 30) of the participants reported that they could currently “eat everything” that is, tolerate all types of foods and preparations. While 52.4% (n = 33) manifested some type of restriction.
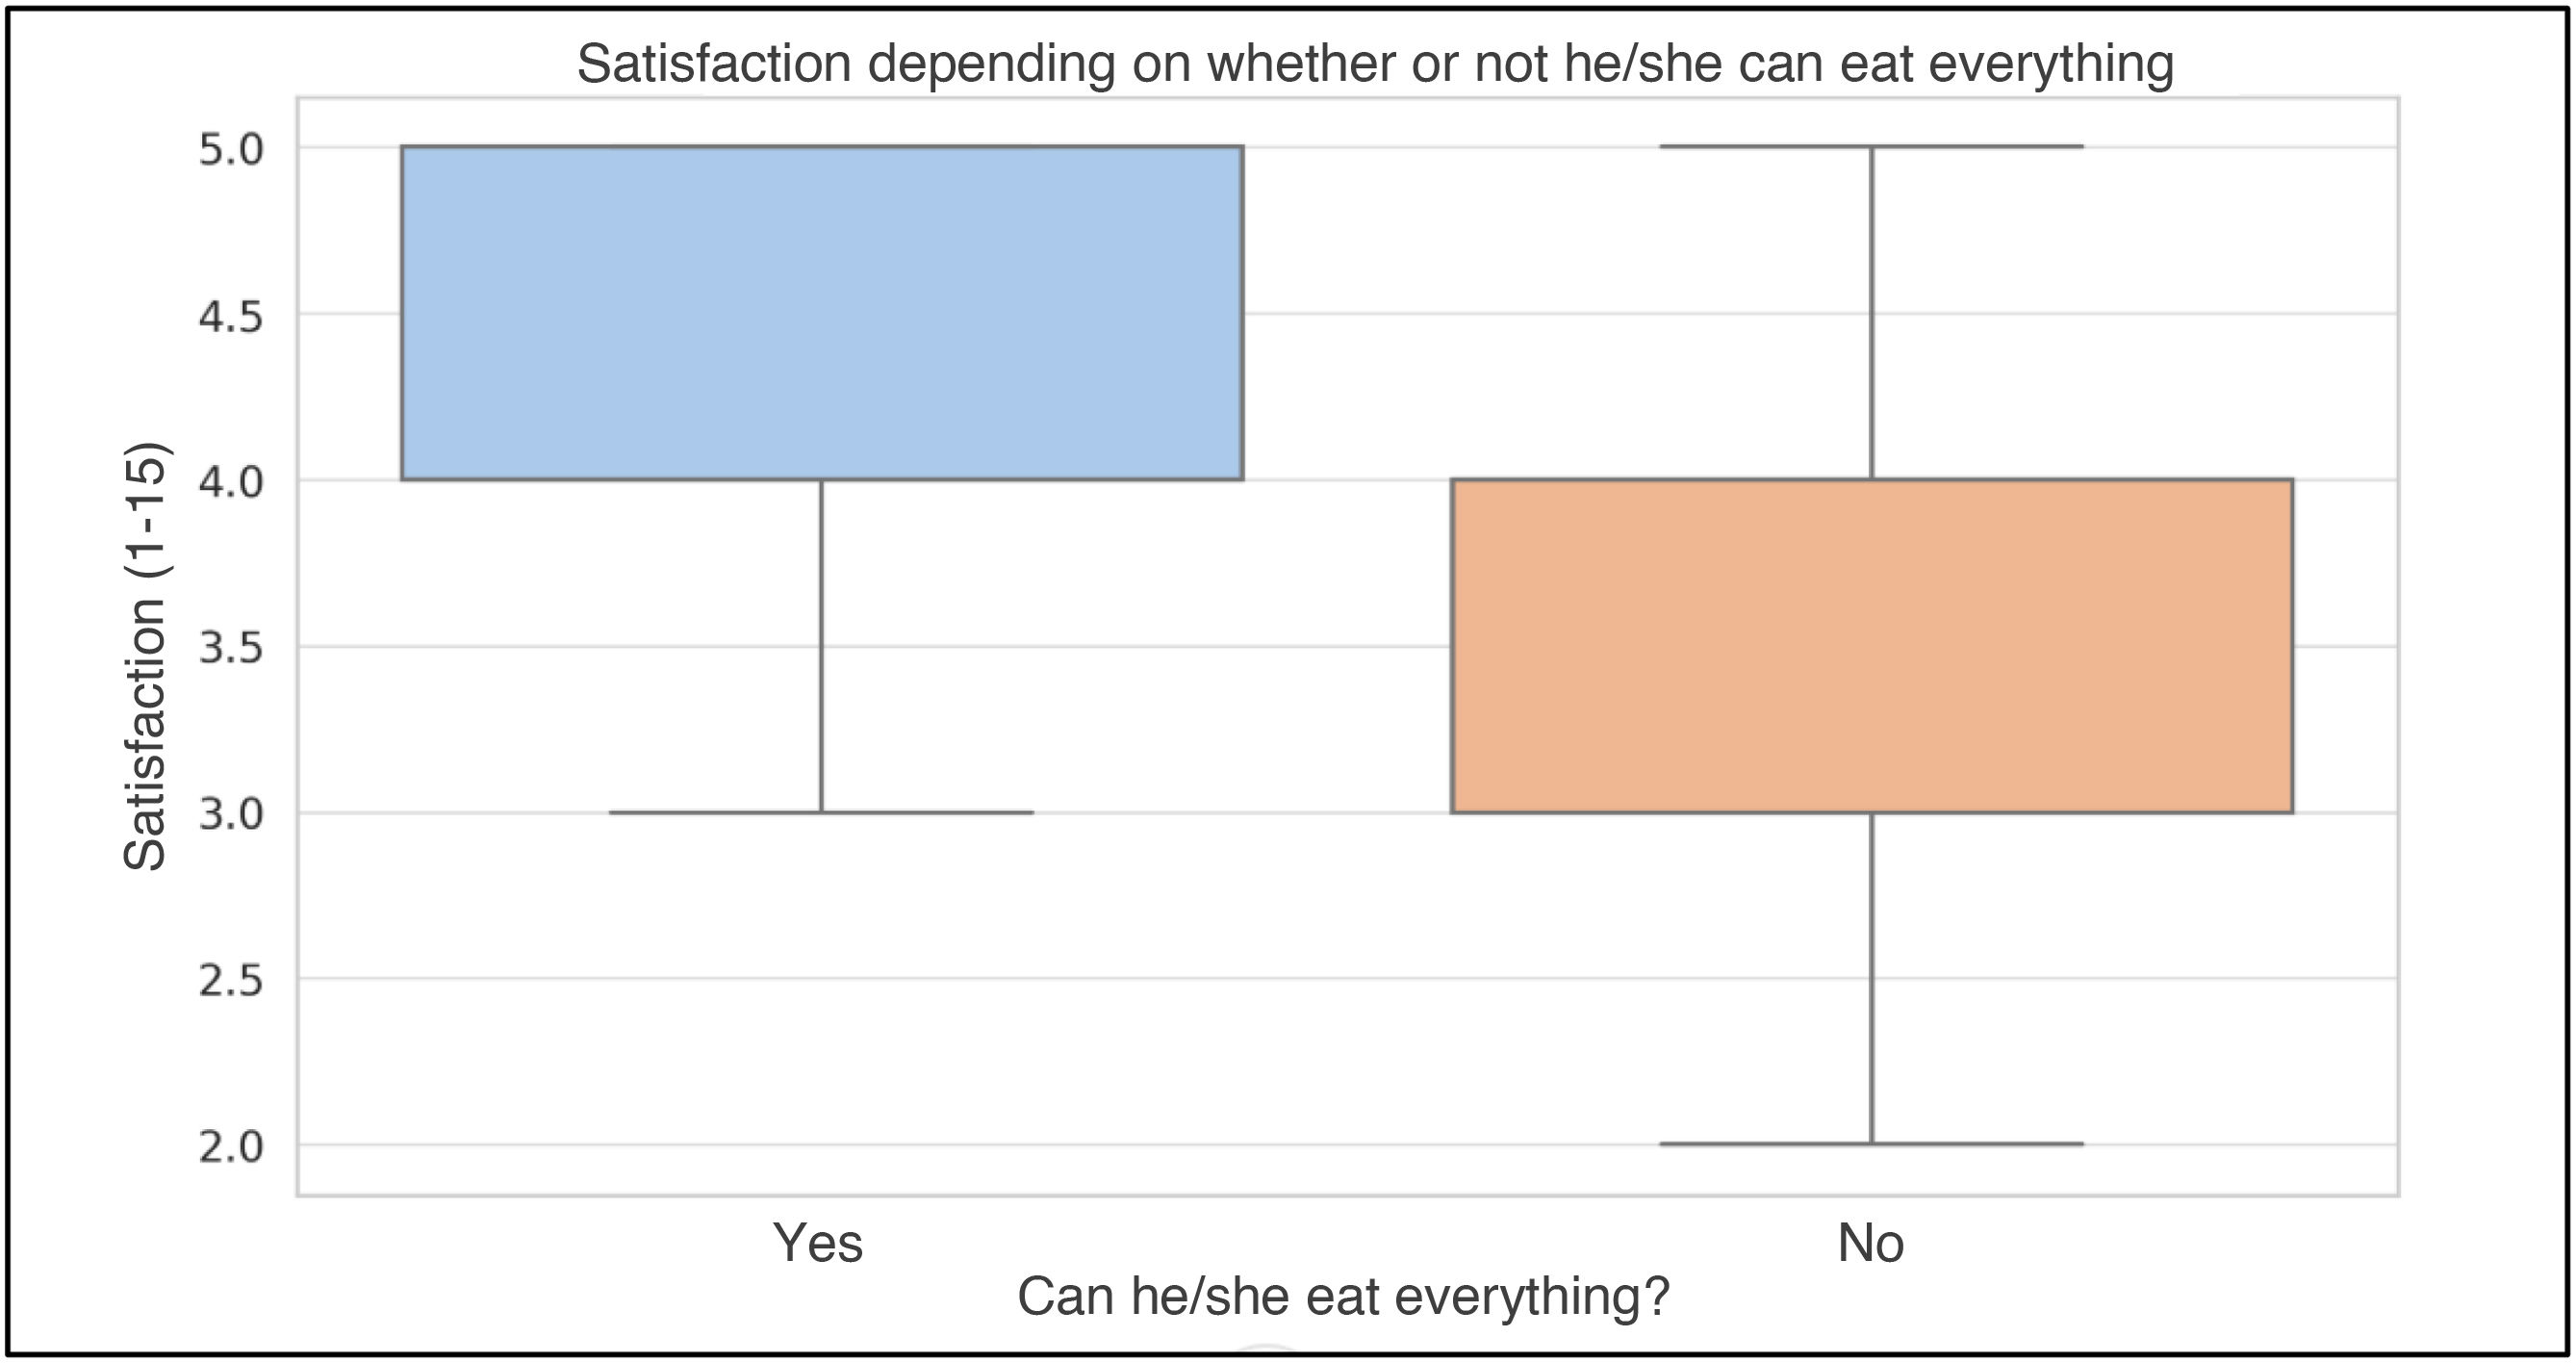
Overall satisfaction with their diet (scale 1–5) was significantly higher in patients without dietary restrictions (M = 4.20, SD = 0.68), compared to those who reported dietary limitations (M = 3.48, SD = 0.87). The analysis of variance showed statistically significant differences (F(1, 58) = 12.96, p < 0.001, η2_p = 0.18) (Table 2; Fig. 1).

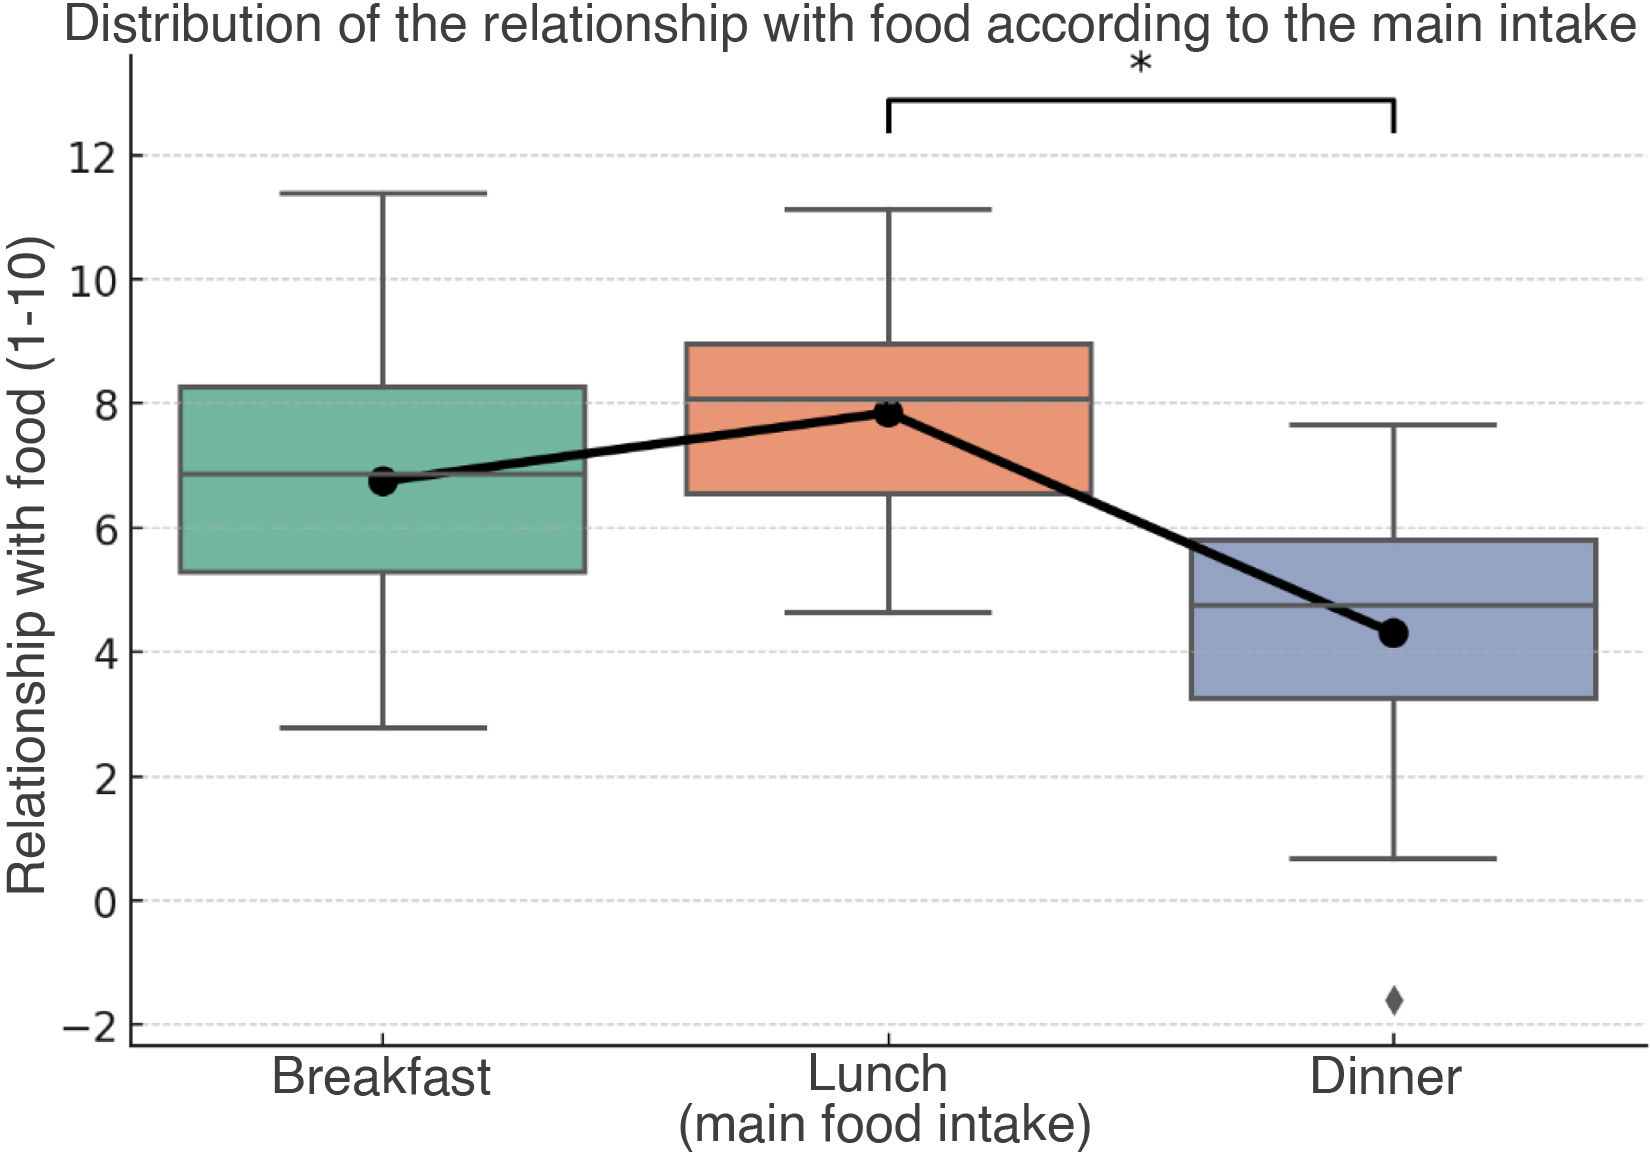
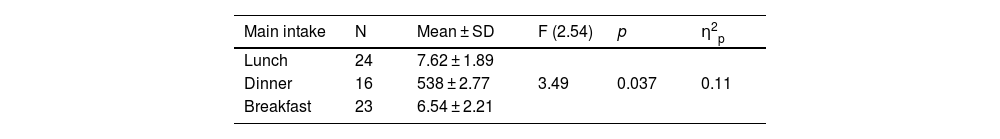
When analysing the time of day when the main intake occurred, significant differences were observed in the subjective relationship with food (scale 1–10) (F(2, 54) = 3.49, p = 0.037, η2_p = 0.11). Patients who identified lunch as the main meal of the day showed a more positive relationship with their diet (M = 7.62, SD = 1.89) compared to those whose main intake was at dinner (M = 5.38, SD = 2.77). Tukey's post hoc tests indicated significant differences between the two groups (p = 0.029) but with no relevant differences between them in the case of breakfast (Table 3; Fig. 2).

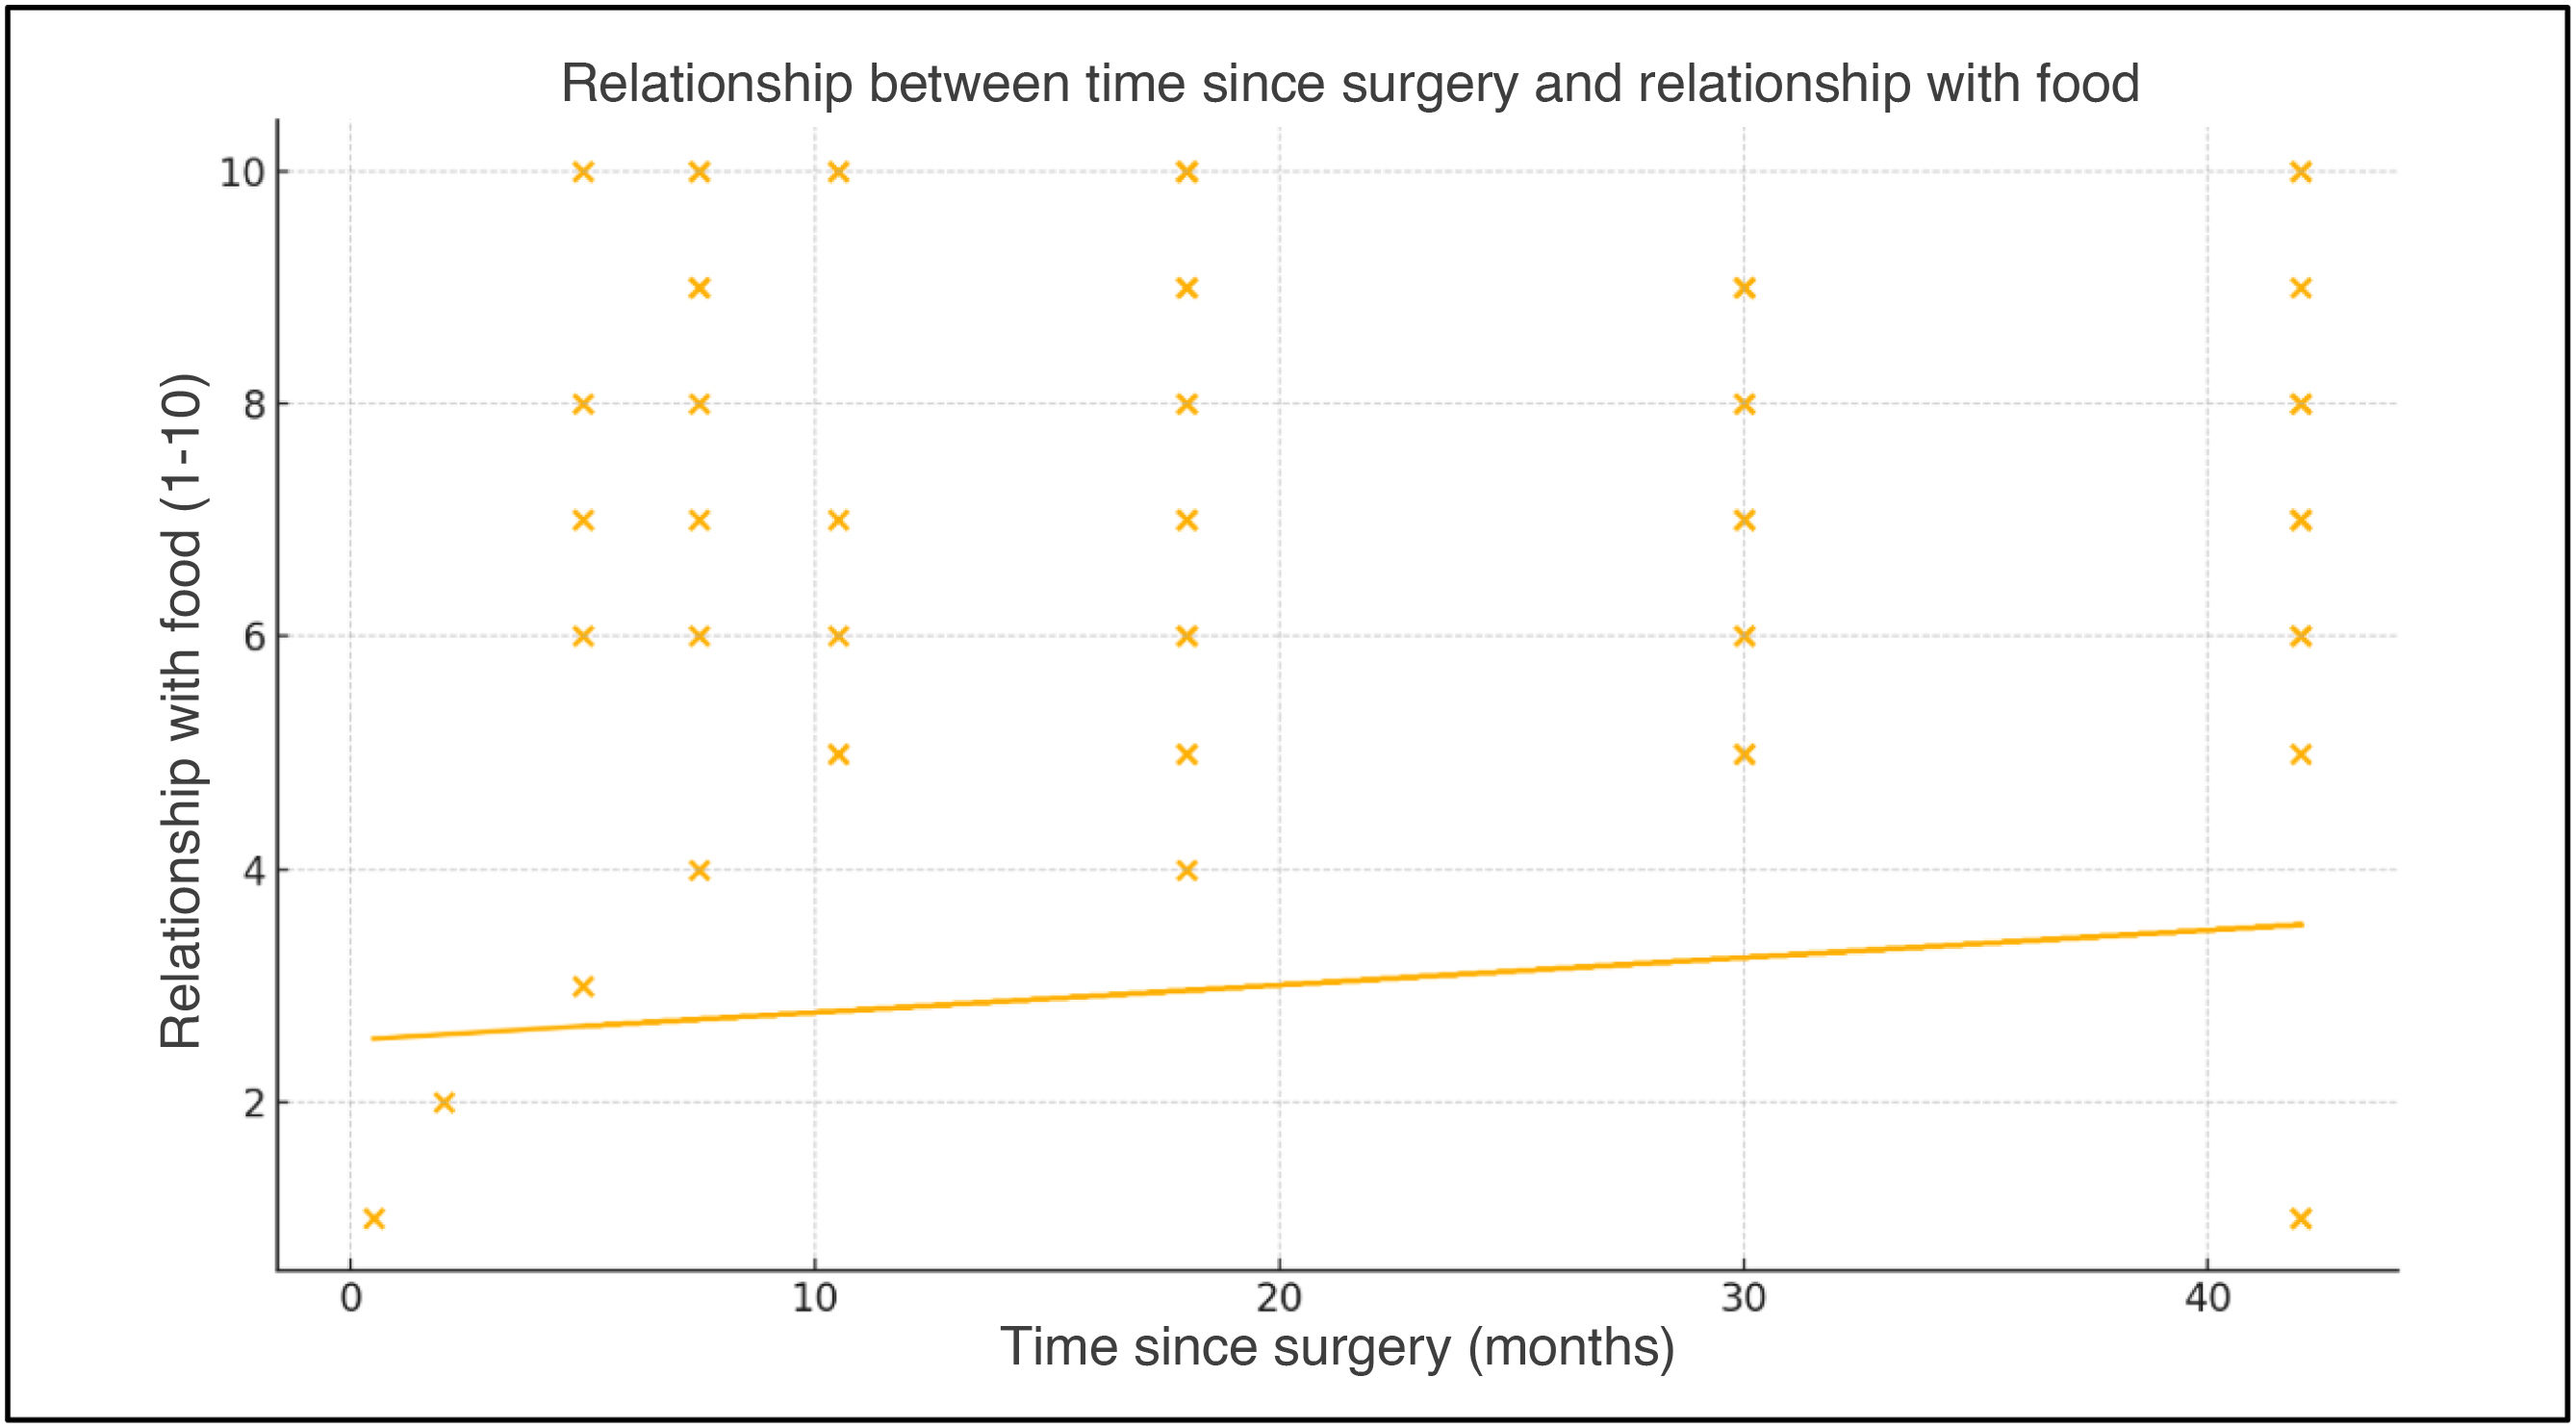
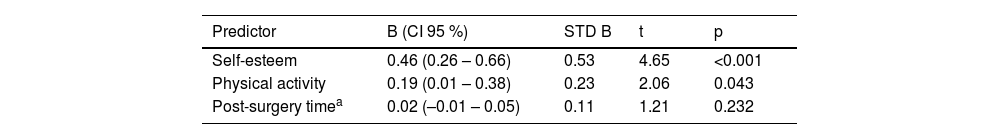
A multiple linear regression model was constructed with the food relationship score as the dependent variable, including as predictors the time elapsed since surgery (in months), self-esteem and frequency of physical activity. This model was statistically significant as a dependent variable (F (3, 65) = 18.02, p < 0.001), which explains 45.4 % of the total variance (R2 = 0.454).
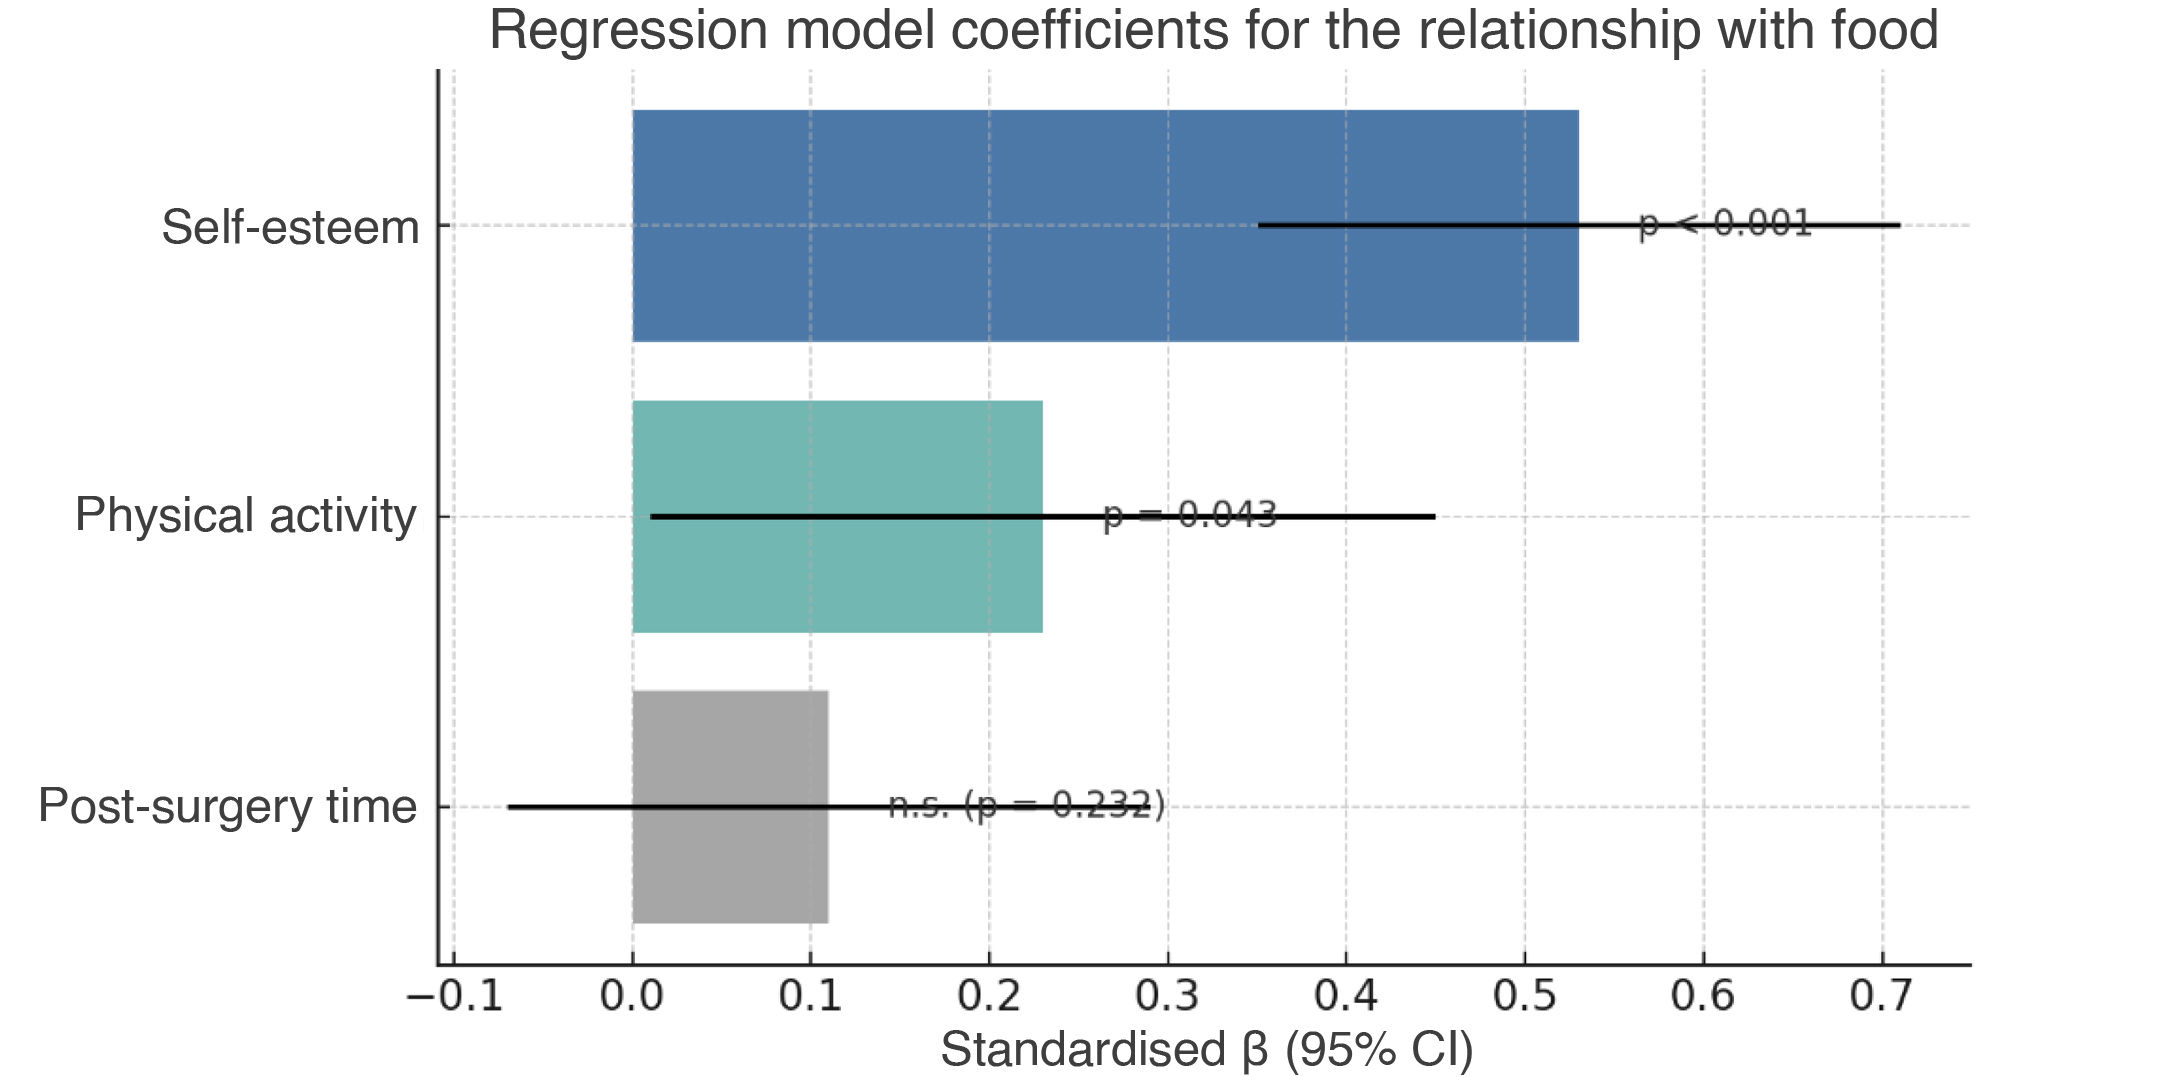
Self-esteem was the strongest predictor (β = 0.53, p < 0.001), followed by physical activity (β = 0.23, p = 0.043). The time since surgery did not reach statistical significance (p = 0.232) (Table 3; Fig. 3).

No multicollinearity problems were observed (FIV < 2), and the model residuals met the assumptions of normality (Shapiro–Wilk = 0.96, p = 0.39) and homoscedasticity (Breusch–Pagan = 3.01, p = 0.27).
The coefficients are detailed in Table 4.
Satisfaction with the main intakes of food after bariatric surgery.
| Predictor | B (CI 95 %) | STD B | t | p |
|---|---|---|---|---|
| Self-esteem | 0.46 (0.26 – 0.66) | 0.53 | 4.65 | <0.001 |
| Physical activity | 0.19 (0.01 – 0.38) | 0.23 | 2.06 | 0.043 |
| Post-surgery timea | 0.02 (–0.01 – 0.05) | 0.11 | 1.21 | 0.232 |
The coefficients (B) and their direction of effect are shown in Fig. 4.

Non-standardised coefficients (B) and 95% confidence intervals of the multiple linear regression model were taken to predict the relationship with food. Self-esteem showed the strongest effect (p < 0.001), followed by physical activity (p = 0.043).
These results support the influence of dietary flexibility, self-esteem, and physical activity on dietary experience after bariatric surgery, providing evidence for patient-centred, multidisciplinary follow-up interventions.
DiscussionThe findings of this study provide relevant evidence on the psychosocial factors that influence dietary satisfaction after bariatric surgery.
People with obesity, especially women between the ages of 65 and 74, have a significantly poorer quality of life than people with normal weight, especially as regards the dimension of vitality, with a strong association between the degree of obesity and the decrease in self-perception of health.19 Several studies show that people with obesity have a decrease in their HRQoL. There appears to be a relationship between BMI and the degree of HRQoL committment.20,21 The knowledge of the impossibility of leading the life these individuals would surely like is as serious a consequence as any other aspect related to the morbidity and mortality of the disease. However, there is a lack of knowledge and awareness among health care professionals and the general public regarding BS.22 These elements are especially relevant considering that some patients may develop symptoms of dissatisfaction, guilt or frustration associated with their new eating limitations.10,11
In particular, it was observed that those patients who reported the ability to “eat everything” showed higher levels of satisfaction. This data should not be interpreted as an absence of dietary control but as a perception of flexibility, possibly associated with greater dietary self-efficacy.23
Likewise, the time of day when the main food intake occurred also demonstrated an association with the perceived relationship with food. This result may reflect more structured lifestyles and greater dietary planning, factors that have been shown to contribute to better outcomes after surgery.24
Multiple regression confirmed the importance of self-esteem as a key variable. This finding is consistent with previous studies showing that high self-esteem acts as a protective factor against postoperative eating dysfunction and improves adherence to clinical recommendations.8,19 Physical activity, on the other hand, was also positively associated with a better relationship with food, reinforcing the need to promote regular physical exercise as part of multidisciplinary follow-up. These results are consistent with the study by Tibisay et al., which found a significant association between the presence of obesity, a low-quality diet, a complete lack of physical activity, and a depressive syndrome, which occurs predominantly in women.25 For all these reasons, it is considered essential to address psychoeducational interventions or those of physical activity during pre- and post-surgical consultations.
In Karlsson's study, maximum weight loss improvements after BS were observed during the first year of weight loss and thereafter (1 and 6 years); followed by a weight regain phase which began accompanied by a gradual decrease in HRQoL.20 However, these gains show interindividual variability and may be attenuated in the long term by surgical complications, weight regain, or residual eating disorders.16,26 Fernández Rodríguez et al.’s study27 used the Moorehead-Ardelt II (MA-II) questionnaire9 as part of the Bariatric Analysis and Reporting Outcome System (BAROS), since the MA-II assesses subjective aspects of psychological and social well-being (such as self-esteem, sexuality or relationship with food) which the BAROS system does not assess directly, since the latter uses the MA-II in summary form as a component within a broader system of global assessment of the surgical outcome and highlights that 72.2% of subjects considered that their quality of life improved after BS, highlighting that the best results are obtained in the first two years.27 Other studies have shown that physical, social, mental, and emotional functions created favourable changes in terms of HRQoL over a period of 3–12 months after surgery; while later in time these values were disputed, since some studies report that their values stabilised or decreased, while others suggest that HRQoL continues to improve after two to four years.28,25
A systematic review identified several important sources of bias in non-randomised studies on the effectiveness of bariatric surgery on mortality, as compared with non-surgical interventions.26 There is inconsistent evidence on the association between preoperative mental health problems and postoperative weight loss. Evidence of moderate quality supports an association between BS and lower rates of postoperative depression.29 This heterogeneity underscores the need to assess HRQoL using validated and culturally adapted instruments, capable of detecting dimensions not captured by traditional biomedical parameters.26,29 In addition, those operated on with BS can achieve excellent weight loss, however remain dissatisfied with the result of the operation with respect to the quality and quantity of their diet.18
In our study, contrary to what might be expected, the time elapsed from surgery was not significantly associated with the relationship with food, suggesting that there is no linear or automatic adaptation over time. This finding highlights the importance of continuous individualised evaluation, beyond the first postoperative months.
This study, based on a sample of 63 patients, has limitations both in terms of its sample size and its cross-sectional design. First, the number of participants determines the accuracy of the estimates: although sufficient to describe the overall proportion of satisfied patients, the confidence intervals remain wide (±10–12%), which restricts the ability to perform analyses in subgroups or multivariate models without risk of overfitting and low statistical power.30,31
On the other hand, the cross-sectional design offers only a specific snapshot of food satisfaction, without enabling causal relationships to be established or temporal evolution to be assessed.32,33 Satisfaction after bariatric surgery can vary depending on postoperative time, the type of surgical technique and the support received, factors that are difficult to isolate in a cross-section, with a risk of selection bias, information and confusion.34
Despite these limitations, this study provides useful information on patient perception and can serve as a basis for longitudinal and multicentre studies that could further examine the determinants of food satisfaction in this population.
The results of this study show that patients undergoing bariatric surgery who perceive that they can “eat everything” with greater dietary flexibility have higher levels of food satisfaction, and that self-esteem and regular physical activity are significant predictors of a healthier relationship with food, without being influenced by the time elapsed since the intervention.
Ethical considerationsAll authors have contributed substantially to the manuscript and approve the final version presented. Individually, DPO and MEM conceived and designed the study; MAGR and FJGC created the database and performed the analysis and interpretation of the data. DPO and MAGR drafted the article, and FJGC, MEM, and JBL reviewed the style of the work and critically reviewed the intellectual content.
FundingThis manuscript has not received any funding.
None.


