




To evaluate the Failure to Rescue (FTR) rate in a pancreatic surgery unit between 2020 and 2024, and to identify the limitations of this indicator when interpreting successful outcomes.
Material and methodsA retrospective study based on a prospective database. All patients who underwent elective pancreatic surgery with curative intent between January 2020 and December 2024 were included. Preoperative, intraoperative, and postoperative clinical variables were collected. The 30- and 90-day FTR was defined as mortality among patients who experienced at least one major postoperative complication (MPC) (Clavien-Dindo ≥3).
ResultsOf the 173 patients operated on, 37 (21.39%) developed major complications. The overall FTR rate was 8.11%. The most frequent complication was pancreatic fistula (17.92%), followed by intra-abdominal collections (15.03%), post-pancreatectomy haemorrhage (13.87%), and delayed gastric emptying (5.20%). The reoperation rate was 9.25%, and overall mortality was 1.73%.
ConclusionThe observed FTR rate is comparable to that of high-volume international centres. FTR, being a ratio between mortality and major complications, can be distorted in series with a low rate of such complications, which requires it to be interpreted with caution and not used as a standalone quality indicator of a surgical unit.
Evaluar la tasa de fallo al rescate (FTR) en una unidad de cirugía pancreática entre 2020 y 2024, e identificar las limitaciones de este indicador al interpretar los resultados de éxito.
Material y métodosEstudio retrospectivo sobre una base de datos prospectiva. Se incluyeron todos los pacientes sometidos a cirugía pancreática programada con intención curativa entre enero de 2020 y diciembre de 2024. Se recopilaron variables clínicas preoperatorias, intraoperatorias y postoperatorias. El FTR a 30 y 90 días se definió como la mortalidad entre pacientes que presentaron al menos una complicación mayor postoperatoria (CMP) (Clavien-Dindo ≥3).
ResultadosDe los 173 pacientes intervenidos, 37 (21,39%) presentaron complicaciones mayores. La tasa global de FTR fue del 8,11%. La complicación más frecuente fue la fístula pancreática (17,92%), seguida de las colecciones intraabdominales (15,03%), la hemorragia postpancreatectomía (13,87%) y el retraso del vaciamiento gástrico (5,20%). La tasa de reintervención quirúrgica fue del 9,25% y la mortalidad global de la serie del 1,73%.
ConclusiónLa tasa de FTR observada es comparable a la de centros de alto volumen a nivel internacional. El FTR, al ser un cociente entre mortalidad y complicaciones mayores, puede verse distorsionado en series con baja tasa de este tipo de complicaciones, lo que obliga a interpretarlo con precaución y no debe usarse como parámetro aislado de calidad de una unidad quirúrgica.

Failure to Rescue (FTR) is used as an indicator to assess the quality of a surgical unit, since it measures mortality among patients who suffer at least one major complication within 30 or 90 days after a surgical intervention. This parameter emerges as key indicator of hospital quality in highly complex procedures, since it reflects not only the onset of major complications, but also the capacity of the system to intervene effectively in case of severe adverse events.1,2
Pancreatic surgery is one of the most demanding and complex interventions from a technical standpoint, and is associated with a high mortality rate, even at high-volume centres. Complications such as pancreatic fistula, postoperative haemorrhage and intraabdominal infections represent significant problems that can lead to mortality unless they are managed early and effectively. Therefore, FTR provides an indirect measure of the effectiveness of care at a surgical unit.3–5
Detecting postoperative complications early and establishing specific measures to prevent FTR represent a daily challenge in clinical practice. Factors such as the experience of the surgical team, the implementation of well-defined protocols, and the optimisation of available resources are essential to improving postoperative results.6,7 The use of these tools enables the identification of critical areas, as well as implementation of improvements in the early detection and treatment of postoperative complications.8
The objective of the present study was to analyse the rates of FTR at the pancreatic surgery unit of a tertiary hospital between the years 2020 and 2024, as well as to determine the limitations of this indicator to assess successful results.
Material and methodsA retrospective study was conducted between January 2020 and December 2024, using an institutional prospective database. The population included all the patients who underwent elective pancreatic surgery with curative intent, excluding emergency procedures and palliative interventions.
The data collected included preoperative clinical variables, (age, sex, ASA classification, neoadjuvant treatment), intraoperative clinical variables (type of pancreatic resection, surgical approach, histopathological diagnosis), and postoperative clinical variables (type and severity of complications according to the Clavien-Dindo classification,9 need for reoperation, hospital stay and mortality at 30 and 90 days).
FTR was defined as mortality among patients who presented with at least one major complication (Clavien-Dindo ≥3), within 30 and 90 days after surgery.5 The numerator was defined as all those patients who died after presenting with severe complications. The denominator included all those patients who experienced severe complications.1 The definitions employed were those proposed by the International Study Group of Pancreatic Surgery (ISGPS) to classify specific complications5,10–13:
- -
Postoperative pancreatic fistula (POPF) was identified as the leakage of fluid through an intraabdominal drain after the third postoperative day, with an amylase concentration greater than three times the upper limit of normality and with clinical relevance.10
- -
Post-pancreatectomy haemorrhage (PPH) was categorised according to location, time of onset, and severity, classified into three grades.10
- -
Delayed gastric emptying (DGE) was defined as the inability to resume a normal oral diet due to delayed gastric evacuation, without evidence of a mechanical obstruction.10
- -
Biliary fistula was diagnosed when there was evidence of bile leakage after the third postoperative day or when there was a need for radiological or surgical intervention as a result of biliary collections or biliary peritonitis.10
All the patients were treated according to an early recovery protocol (fast-track), which included early start of an oral diet, programmed analytical monitoring on the first and third postoperative days, and measurement of amylase in peritoneal fluid on the third postoperative day. In the absence of pancreatic fistula, the abdominal drain was removed on the third postoperative day. Otherwise, a new determination was carried out on the fifth day. In the event of complications, the procedure was to follow a standardised therapeutic algorithm, initially prioritising a conservative medical treatment. In the absence of response or the presence of specific complications, resolution was attempted via endoscopic techniques or radiologically-guided intervention. Lastly, surgical treatment was indicated in refractory or more severe situations. This stepwise approach enabled clinical management to be standardised and ensured a protocolised management of complications.
The statistical analysis was conducted using the software package RStudio (version 2024.12.0 + 467). Quantitative variables were expressed as mean and standard deviation or as median and interquartile range. The normality of variables was evaluated using the Kolmogorov-Smirnov test, which enabled determination of whether the most adequate measure of central tendency was the mean or median. Qualitative variables were presented as absolute or relative frequencies.
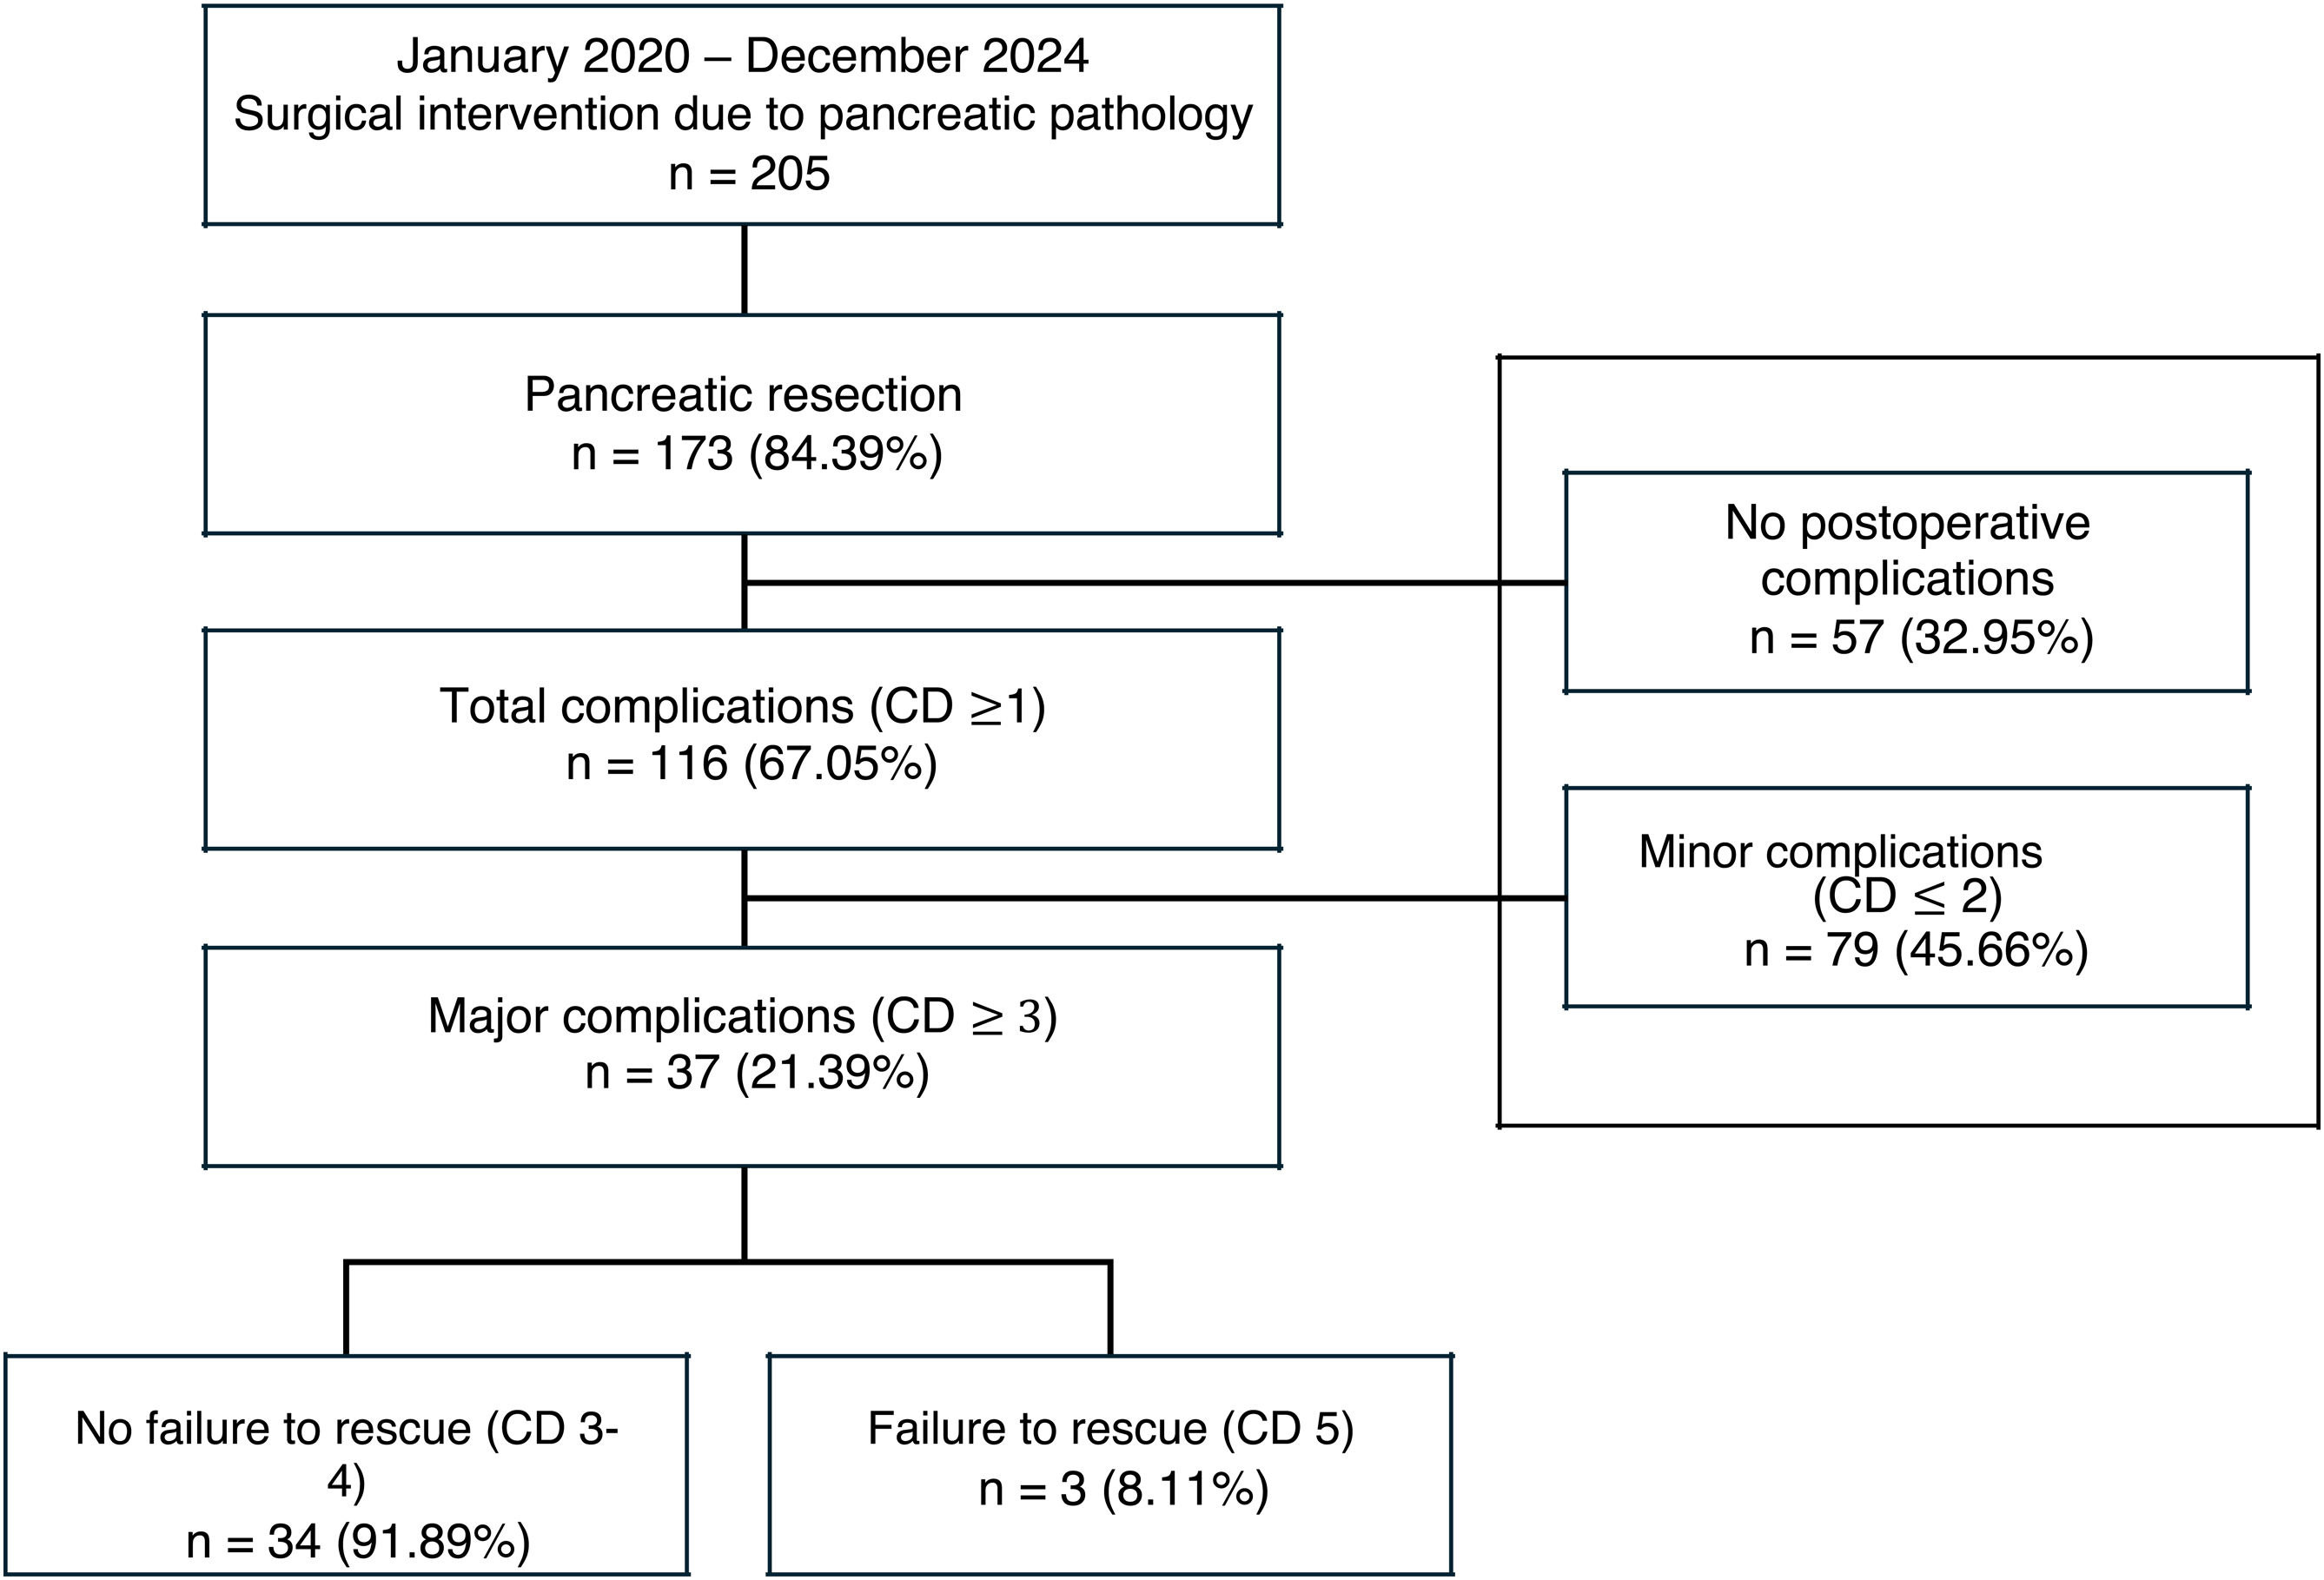
ResultsA total of 205 patients with pancreatic pathologies underwent surgery throughout the study period, of whom 173 (84.39%) underwent elective pancreatic resection surgery (Fig. 1).

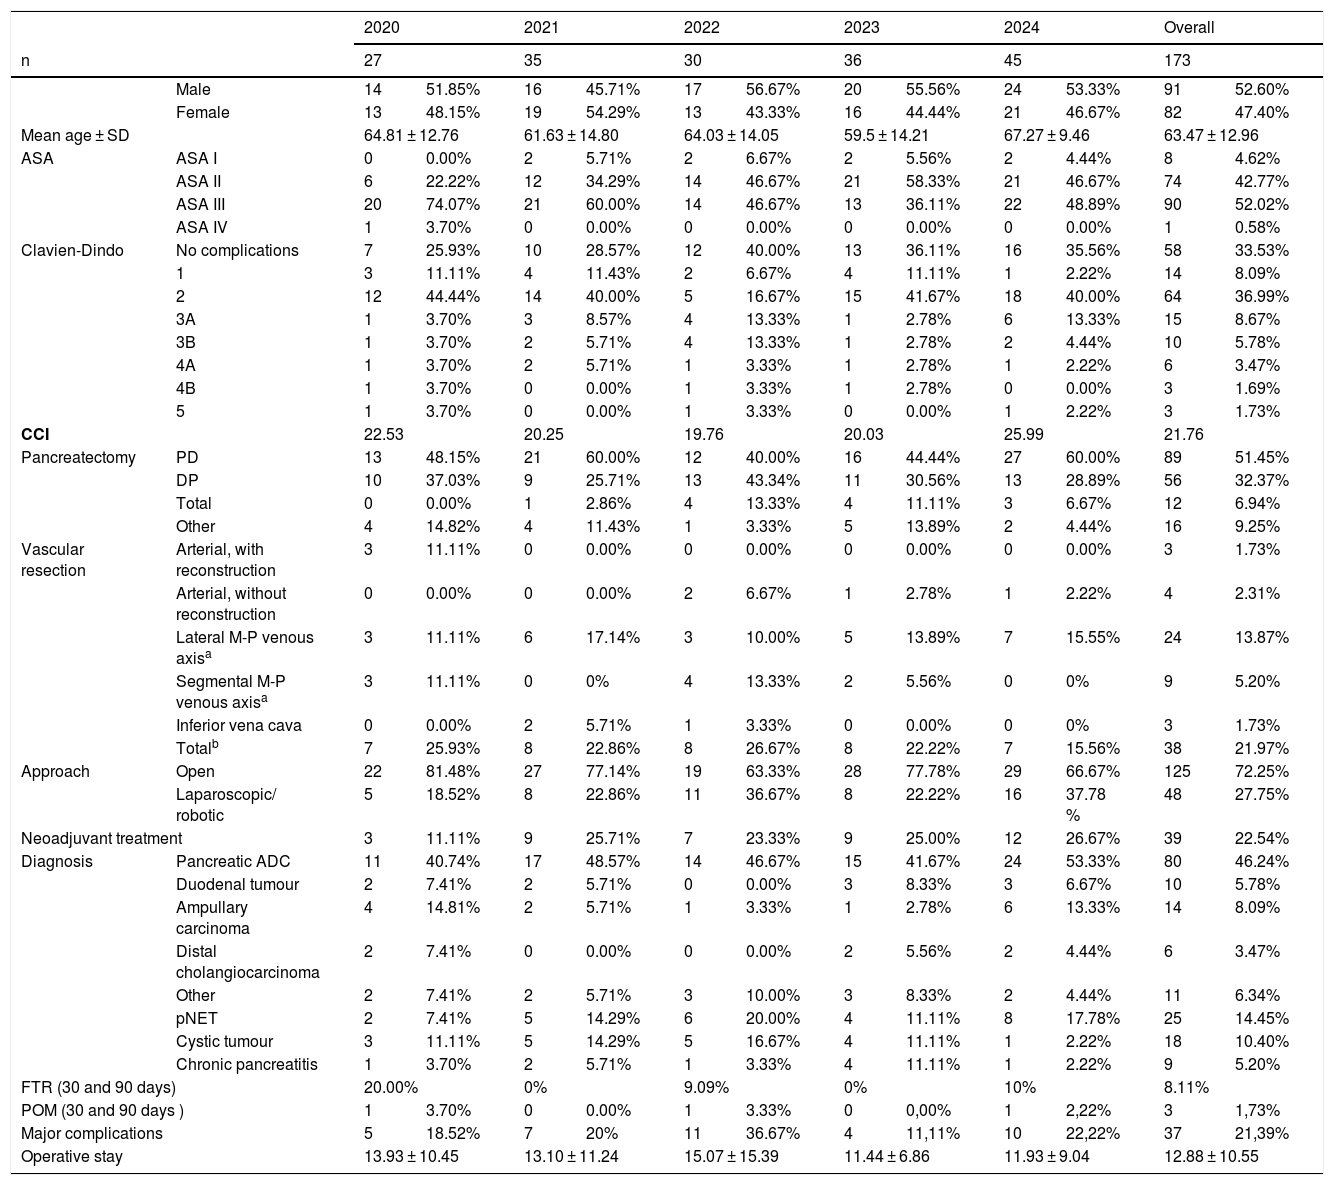
The mean age was 63.47 (SD ± 12.96) years, and 82 (47.40%) were female. The most frequent diagnosis was pancreatic adenocarcinoma (46.24%), followed by pancreatic neuroendocrine tumour (14.45%) as shown in Table 1. In 38 patients (21.9%), the intervention was vascular resection, corresponding to 33 venous resections of the mesenteric-portal axis, 3 resections of the inferior vena cava, and 7 arterial resections.
Characteristics of patients (n = 173).
| 2020 | 2021 | 2022 | 2023 | 2024 | Overall | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| n | 27 | 35 | 30 | 36 | 45 | 173 | |||||||
| Male | 14 | 51.85% | 16 | 45.71% | 17 | 56.67% | 20 | 55.56% | 24 | 53.33% | 91 | 52.60% | |
| Female | 13 | 48.15% | 19 | 54.29% | 13 | 43.33% | 16 | 44.44% | 21 | 46.67% | 82 | 47.40% | |
| Mean age ± SD | 64.81 ± 12.76 | 61.63 ± 14.80 | 64.03 ± 14.05 | 59.5 ± 14.21 | 67.27 ± 9.46 | 63.47 ± 12.96 | |||||||
| ASA | ASA I | 0 | 0.00% | 2 | 5.71% | 2 | 6.67% | 2 | 5.56% | 2 | 4.44% | 8 | 4.62% |
| ASA II | 6 | 22.22% | 12 | 34.29% | 14 | 46.67% | 21 | 58.33% | 21 | 46.67% | 74 | 42.77% | |
| ASA III | 20 | 74.07% | 21 | 60.00% | 14 | 46.67% | 13 | 36.11% | 22 | 48.89% | 90 | 52.02% | |
| ASA IV | 1 | 3.70% | 0 | 0.00% | 0 | 0.00% | 0 | 0.00% | 0 | 0.00% | 1 | 0.58% | |
| Clavien-Dindo | No complications | 7 | 25.93% | 10 | 28.57% | 12 | 40.00% | 13 | 36.11% | 16 | 35.56% | 58 | 33.53% |
| 1 | 3 | 11.11% | 4 | 11.43% | 2 | 6.67% | 4 | 11.11% | 1 | 2.22% | 14 | 8.09% | |
| 2 | 12 | 44.44% | 14 | 40.00% | 5 | 16.67% | 15 | 41.67% | 18 | 40.00% | 64 | 36.99% | |
| 3A | 1 | 3.70% | 3 | 8.57% | 4 | 13.33% | 1 | 2.78% | 6 | 13.33% | 15 | 8.67% | |
| 3B | 1 | 3.70% | 2 | 5.71% | 4 | 13.33% | 1 | 2.78% | 2 | 4.44% | 10 | 5.78% | |
| 4A | 1 | 3.70% | 2 | 5.71% | 1 | 3.33% | 1 | 2.78% | 1 | 2.22% | 6 | 3.47% | |
| 4B | 1 | 3.70% | 0 | 0.00% | 1 | 3.33% | 1 | 2.78% | 0 | 0.00% | 3 | 1.69% | |
| 5 | 1 | 3.70% | 0 | 0.00% | 1 | 3.33% | 0 | 0.00% | 1 | 2.22% | 3 | 1.73% | |
| CCI | 22.53 | 20.25 | 19.76 | 20.03 | 25.99 | 21.76 | |||||||
| Pancreatectomy | PD | 13 | 48.15% | 21 | 60.00% | 12 | 40.00% | 16 | 44.44% | 27 | 60.00% | 89 | 51.45% |
| DP | 10 | 37.03% | 9 | 25.71% | 13 | 43.34% | 11 | 30.56% | 13 | 28.89% | 56 | 32.37% | |
| Total | 0 | 0.00% | 1 | 2.86% | 4 | 13.33% | 4 | 11.11% | 3 | 6.67% | 12 | 6.94% | |
| Other | 4 | 14.82% | 4 | 11.43% | 1 | 3.33% | 5 | 13.89% | 2 | 4.44% | 16 | 9.25% | |
| Vascular resection | Arterial, with reconstruction | 3 | 11.11% | 0 | 0.00% | 0 | 0.00% | 0 | 0.00% | 0 | 0.00% | 3 | 1.73% |
| Arterial, without reconstruction | 0 | 0.00% | 0 | 0.00% | 2 | 6.67% | 1 | 2.78% | 1 | 2.22% | 4 | 2.31% | |
| Lateral M-P venous axisa | 3 | 11.11% | 6 | 17.14% | 3 | 10.00% | 5 | 13.89% | 7 | 15.55% | 24 | 13.87% | |
| Segmental M-P venous axisa | 3 | 11.11% | 0 | 0% | 4 | 13.33% | 2 | 5.56% | 0 | 0% | 9 | 5.20% | |
| Inferior vena cava | 0 | 0.00% | 2 | 5.71% | 1 | 3.33% | 0 | 0.00% | 0 | 0% | 3 | 1.73% | |
| Totalb | 7 | 25.93% | 8 | 22.86% | 8 | 26.67% | 8 | 22.22% | 7 | 15.56% | 38 | 21.97% | |
| Approach | Open | 22 | 81.48% | 27 | 77.14% | 19 | 63.33% | 28 | 77.78% | 29 | 66.67% | 125 | 72.25% |
| Laparoscopic/ robotic | 5 | 18.52% | 8 | 22.86% | 11 | 36.67% | 8 | 22.22% | 16 | 37.78 % | 48 | 27.75% | |
| Neoadjuvant treatment | 3 | 11.11% | 9 | 25.71% | 7 | 23.33% | 9 | 25.00% | 12 | 26.67% | 39 | 22.54% | |
| Diagnosis | Pancreatic ADC | 11 | 40.74% | 17 | 48.57% | 14 | 46.67% | 15 | 41.67% | 24 | 53.33% | 80 | 46.24% |
| Duodenal tumour | 2 | 7.41% | 2 | 5.71% | 0 | 0.00% | 3 | 8.33% | 3 | 6.67% | 10 | 5.78% | |
| Ampullary carcinoma | 4 | 14.81% | 2 | 5.71% | 1 | 3.33% | 1 | 2.78% | 6 | 13.33% | 14 | 8.09% | |
| Distal cholangiocarcinoma | 2 | 7.41% | 0 | 0.00% | 0 | 0.00% | 2 | 5.56% | 2 | 4.44% | 6 | 3.47% | |
| Other | 2 | 7.41% | 2 | 5.71% | 3 | 10.00% | 3 | 8.33% | 2 | 4.44% | 11 | 6.34% | |
| pNET | 2 | 7.41% | 5 | 14.29% | 6 | 20.00% | 4 | 11.11% | 8 | 17.78% | 25 | 14.45% | |
| Cystic tumour | 3 | 11.11% | 5 | 14.29% | 5 | 16.67% | 4 | 11.11% | 1 | 2.22% | 18 | 10.40% | |
| Chronic pancreatitis | 1 | 3.70% | 2 | 5.71% | 1 | 3.33% | 4 | 11.11% | 1 | 2.22% | 9 | 5.20% | |
| FTR (30 and 90 days) | 20.00% | 0% | 9.09% | 0% | 10% | 8.11% | |||||||
| POM (30 and 90 days ) | 1 | 3.70% | 0 | 0.00% | 1 | 3.33% | 0 | 0,00% | 1 | 2,22% | 3 | 1,73% | |
| Major complications | 5 | 18.52% | 7 | 20% | 11 | 36.67% | 4 | 11,11% | 10 | 22,22% | 37 | 21,39% | |
| Operative stay | 13.93 ± 10.45 | 13.10 ± 11.24 | 15.07 ± 15.39 | 11.44 ± 6.86 | 11.93 ± 9.04 | 12.88 ± 10.55 | |||||||
ADC: pancreatic adenocarcinoma; ASA: American Society of Anesthesiologists score; CCI: Charlson comorbidity index; DP: distal pancreatectomy; E-E: end-to-end; FTR: failure to rescue; pancreatic pNET: pancreatic neuroendocrine tumour; PD: pancreaticoduodenectomy; POM: postoperative mortality; SD: standard deviation.
Following the classification of the International Study Group of Pancreatic Surgery (ISGPS): Lateral resection (type 1: venorrhaphy and type 2: patch); Segmental resection (type 3: E-E anastomosis and type 4: graft interposition).30
In terms of outcomes, 67.05% patients presented with at least one postoperative complication, while major complications (Clavien–Dindo ≥3) were identified in 21.39% of cases. The overall mortality rate, at both 30 and 90 days, was 1.73%, with no mortality among patients who suffered minor complications. The FTR rate at 30 and 90 days was 8.11%, with an interannual variation ranging between 0% and 20%. The mean postoperative stay was 12.88 (SD ± 10.55) days (Table 1).
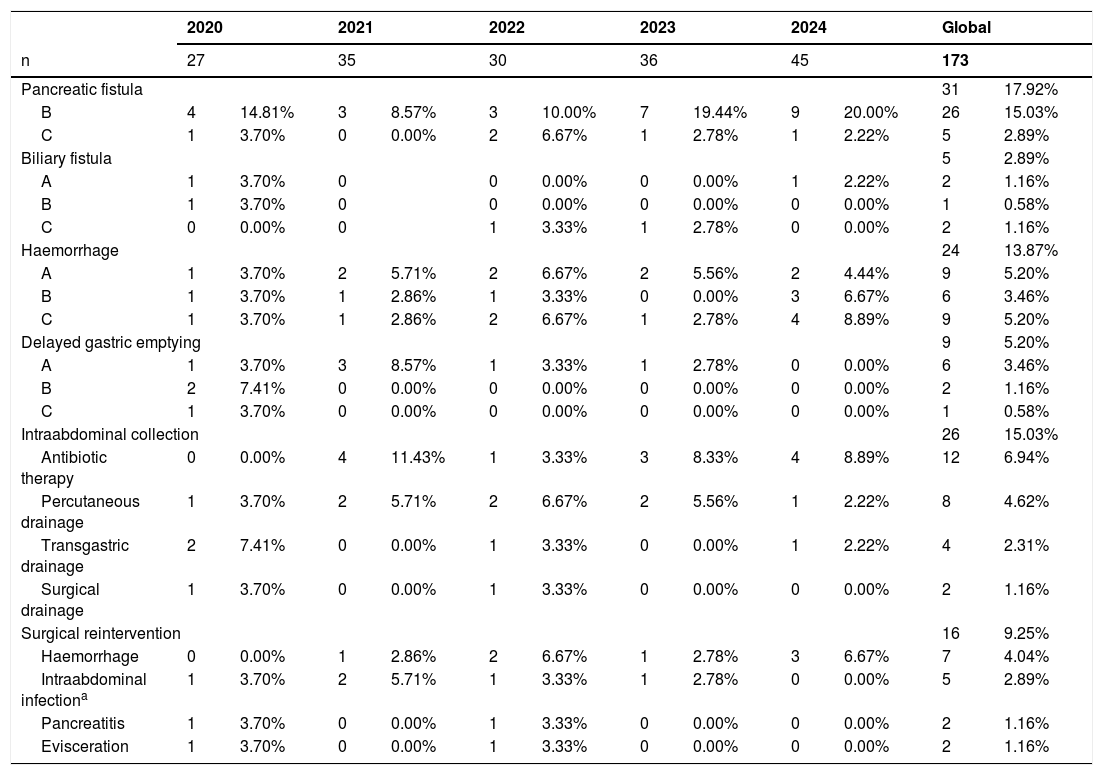
The most frequent complication was POPF grade B/C (17.92%), followed by intraabdominal collection (15.03%). In addition, 14 patients with intraabdominal collection required some type of drainage (percutaneous, transgastric or surgical). PPH occurred in 24 patients (13.87%), of grade C in 5.20% of cases. Table 2 shows the specific complications of pancreatic resections and their severity grade. The rate of surgical reintervention was 9.25% (n = 16), with the most frequent cause being intraabdominal bleeding, observed in 7 patients.
Specific complications following pancreatic resection. Classified according to the International Study Group of Pancreatic Surgery (ISGPS) (n = 173).
| 2020 | 2021 | 2022 | 2023 | 2024 | Global | |||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| n | 27 | 35 | 30 | 36 | 45 | 173 | ||||||
| Pancreatic fistula | 31 | 17.92% | ||||||||||
| B | 4 | 14.81% | 3 | 8.57% | 3 | 10.00% | 7 | 19.44% | 9 | 20.00% | 26 | 15.03% |
| C | 1 | 3.70% | 0 | 0.00% | 2 | 6.67% | 1 | 2.78% | 1 | 2.22% | 5 | 2.89% |
| Biliary fistula | 5 | 2.89% | ||||||||||
| A | 1 | 3.70% | 0 | 0 | 0.00% | 0 | 0.00% | 1 | 2.22% | 2 | 1.16% | |
| B | 1 | 3.70% | 0 | 0 | 0.00% | 0 | 0.00% | 0 | 0.00% | 1 | 0.58% | |
| C | 0 | 0.00% | 0 | 1 | 3.33% | 1 | 2.78% | 0 | 0.00% | 2 | 1.16% | |
| Haemorrhage | 24 | 13.87% | ||||||||||
| A | 1 | 3.70% | 2 | 5.71% | 2 | 6.67% | 2 | 5.56% | 2 | 4.44% | 9 | 5.20% |
| B | 1 | 3.70% | 1 | 2.86% | 1 | 3.33% | 0 | 0.00% | 3 | 6.67% | 6 | 3.46% |
| C | 1 | 3.70% | 1 | 2.86% | 2 | 6.67% | 1 | 2.78% | 4 | 8.89% | 9 | 5.20% |
| Delayed gastric emptying | 9 | 5.20% | ||||||||||
| A | 1 | 3.70% | 3 | 8.57% | 1 | 3.33% | 1 | 2.78% | 0 | 0.00% | 6 | 3.46% |
| B | 2 | 7.41% | 0 | 0.00% | 0 | 0.00% | 0 | 0.00% | 0 | 0.00% | 2 | 1.16% |
| C | 1 | 3.70% | 0 | 0.00% | 0 | 0.00% | 0 | 0.00% | 0 | 0.00% | 1 | 0.58% |
| Intraabdominal collection | 26 | 15.03% | ||||||||||
| Antibiotic therapy | 0 | 0.00% | 4 | 11.43% | 1 | 3.33% | 3 | 8.33% | 4 | 8.89% | 12 | 6.94% |
| Percutaneous drainage | 1 | 3.70% | 2 | 5.71% | 2 | 6.67% | 2 | 5.56% | 1 | 2.22% | 8 | 4.62% |
| Transgastric drainage | 2 | 7.41% | 0 | 0.00% | 1 | 3.33% | 0 | 0.00% | 1 | 2.22% | 4 | 2.31% |
| Surgical drainage | 1 | 3.70% | 0 | 0.00% | 1 | 3.33% | 0 | 0.00% | 0 | 0.00% | 2 | 1.16% |
| Surgical reintervention | 16 | 9.25% | ||||||||||
| Haemorrhage | 0 | 0.00% | 1 | 2.86% | 2 | 6.67% | 1 | 2.78% | 3 | 6.67% | 7 | 4.04% |
| Intraabdominal infectiona | 1 | 3.70% | 2 | 5.71% | 1 | 3.33% | 1 | 2.78% | 0 | 0.00% | 5 | 2.89% |
| Pancreatitis | 1 | 3.70% | 0 | 0.00% | 1 | 3.33% | 0 | 0.00% | 0 | 0.00% | 2 | 1.16% |
| Evisceration | 1 | 3.70% | 0 | 0.00% | 1 | 3.33% | 0 | 0.00% | 0 | 0.00% | 2 | 1.16% |
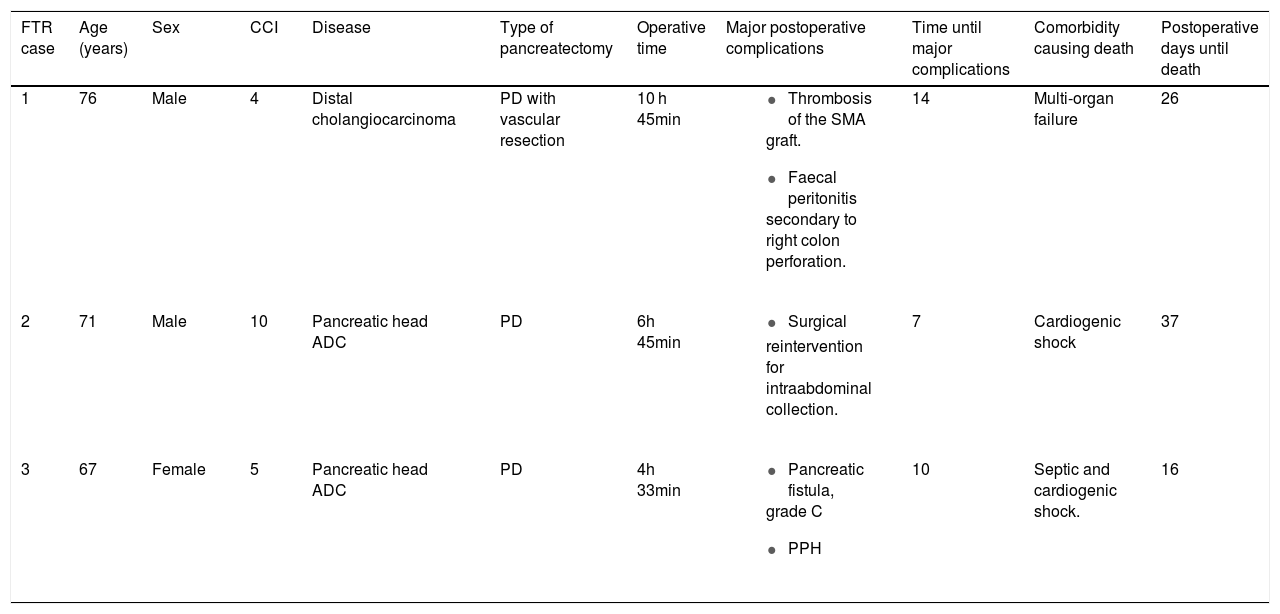
The characteristics of the 3 patients who died and who, therefore, represented cases of FTR, are described in Table 3. All of them had undergone pancreaticoduodenectomy (PD). Thus, the specific rate of FTR for the subgroup of patients who underwent PD was 14.29%, with 21 patients (23.60%) presenting with major complications.
Characteristics of patients who underwent FTR (n = 3).
| FTR case | Age (years) | Sex | CCI | Disease | Type of pancreatectomy | Operative time | Major postoperative complications | Time until major complications | Comorbidity causing death | Postoperative days until death |
|---|---|---|---|---|---|---|---|---|---|---|
| 1 | 76 | Male | 4 | Distal cholangiocarcinoma | PD with vascular resection | 10 h 45min |
| 14 | Multi-organ failure | 26 |
| 2 | 71 | Male | 10 | Pancreatic head ADC | PD | 6h 45min |
| 7 | Cardiogenic shock | 37 |
| 3 | 67 | Female | 5 | Pancreatic head ADC | PD | 4h 33min |
| 10 | Septic and cardiogenic shock. | 16 |
ADC: adenocarcinoma; CCI: Charlson Comorbidity Index; FTR: failure to rescue; PD: pancreaticoduodenectomy; PPH: post-pancreatectomy haemorrhage; SMA: superior mesenteric artery.
Pancreatic surgery represents one of the greatest challenges in digestive surgery due to its high complexity and technical demands, and is associated with a high postoperative morbidity even at specialised centres. The rate of major complications remains high in spite of advances in surgical techniques and perioperative management protocols.11,12
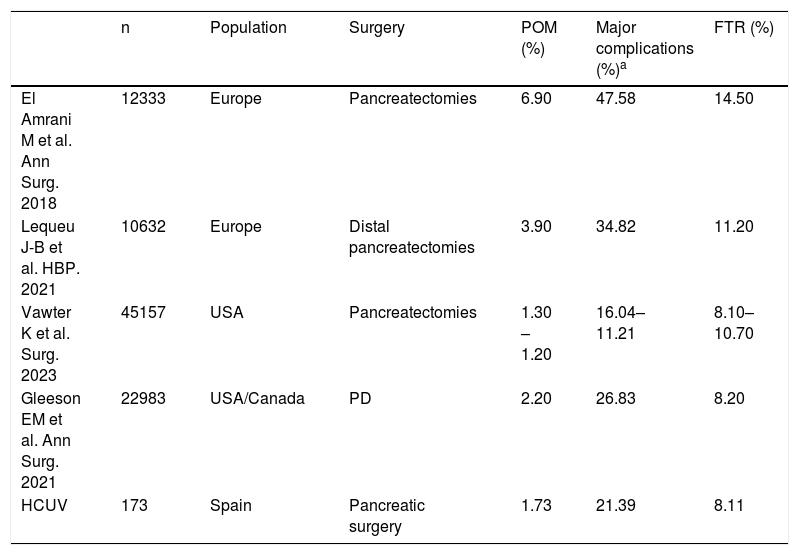
FTR has been proposed as a sensitive indicator to assess the quality of surgical care, as it reflects not only the onset of complications, but also the effectiveness of the hospital in terms of management and resolution to decrease mortality.2,11 In our series, the rate of FTR observed was 8.11%, in line with international standards at high-volume centres, as summarised in Table 4. This figure suggests an adequate response capacity for major complications.2,14
Failure to rescue, major complications and postoperative mortality in different series.
| n | Population | Surgery | POM (%) | Major complications (%)a | FTR (%) | |
|---|---|---|---|---|---|---|
| El Amrani M et al. Ann Surg. 2018 | 12333 | Europe | Pancreatectomies | 6.90 | 47.58 | 14.50 |
| Lequeu J-B et al. HBP. 2021 | 10632 | Europe | Distal pancreatectomies | 3.90 | 34.82 | 11.20 |
| Vawter K et al. Surg. 2023 | 45157 | USA | Pancreatectomies | 1.30 – 1.20 | 16.04–11.21 | 8.10–10.70 |
| Gleeson EM et al. Ann Surg. 2021 | 22983 | USA/Canada | PD | 2.20 | 26.83 | 8.20 |
| HCUV | 173 | Spain | Pancreatic surgery | 1.73 | 21.39 | 8.11 |
FTR: failure to rescue; HCUV: Valencia University Clinic Hospital; PD: pancreaticoduodenectomy; POM: postoperative mortality.
However, a year-by-year analysis of our data revealed notable limitations in the interpretation of FTR as an isolated indicator. For example, in the year 2020, a relatively low rate of major complications (18.5%) was observed, but alongside an elevated FTR of 20%, whereas in 2022, with a higher incidence of severe complications (36.7%), the FTR was 9.1%. These findings highlight the impact that small absolute changes in mortality can have on the denominator of FTR, which in turn can distort the perception of clinical management, particularly in moderate-sized samples. These variations underscore the need to interpret FTR as a complement to other indicators, such as risk-adjusted mortality, surgical volume, and the rate of major complications. In addition, for its correct evaluation, FTR should be complemented by other parameters that enable specialists to identify these different characteristics, such as analyses focused on timing of complications or response time.7,14,15
In order to improve the response capacity to complications, thereby reducing mortality and FTR, it is necessary to consider both structural variables (including availability of an ICU, interventional radiology, and the use of standardised protocols) and characteristics inherent to the patients themselves (age, comorbidities, nutritional status). Although some of these factors cannot be modified, there are some effective interventions which have been proven to have an impact on reducing FTR, such as centralisation of complex pathologies, close monitoring of high-risk patients by trained staff, and the implementation of protocols for the early detection of complications, including surgical checklists and continuous improvement systems like NSQIP.16
The relationship between hospital volume and postoperative complications, as well as the connection with the rate of FTR, has been studied extensively. High-volume hospitals present lower rates of FTR due to their greater experience, better resources, and standardised protocols.17,18 In fact, some studies suggest that FTR could be up to 50% lower at these centres, thus reinforcing the importance of hospital centralisation for highly complex pathologies, like pancreatic surgery.3,19 Nevertheless, geographical and logistical barriers, as well as the limited availability of high-volume centres, have meant that, at present, such centralisation is still not a reality in most cases.6,11
Given that PD constitutes the most complex and high-risk pancreatic resection, we consider it relevant to analyse its FTR specifically. The rate of FTR among patients who underwent PD was 14.29%, which reinforces the need for a response capacity in cases of severe complications among this particularly sensitive subgroup.
In our series, the overall mortality was 1.73%, significantly lower than the specific quality standard for oncological pancreatic surgery at a national and international level, which stands at around 5%.20 This figure underscores the importance of maintaining homogeneous and evidence-based surgical protocols, as well as adequate training for the early identification and adequate treatment of complications.20
As pointed out by previous studies, there are preoperative and postoperative factors which are significantly associated with a higher risk of FTR following PD, some key examples of which are age ≥65 years, hypoalbuminemia (≤3.5 g/dL), onset of shock, acute renal failure, and the need for reintubation.18 Although some of these factors —such as advanced age and high comorbidity— are not easily modifiable, others like hypoalbuminemia can be optimised through preoperative nutritional preparation programmes. Likewise, the onset of septic shock and reintubation usually reflect treatable intraabdominal complications (such as collections or fistulas) which could be prevented or controlled through an early detection and treatment strategy including interventional radiology. Therefore, the implementation of close monitoring protocols, an agile clinical response, and adequately-trained multidisciplinary teams could contribute decisively to mitigate the impact of these factors and reduce the rate of FTR.7,21
Minor complications deserve special attention, since their accumulation during the first postoperative week can anticipate an unfavourable clinical course. This highlights the importance of continuous training of staff and a multidisciplinary approach for early intervention.14,22
There is evidence supporting the effectiveness of using structured tools to analyse errors in the management of complications. Brunner et al (2021) proposed a clinical review model which could identify opportunities for improvement.23,24 This type of tools are essential to analyse and improve outcomes. Similarly, Chen et al. (2018) note that FTR entails a considerable economic cost, due to a greater use of resources, prolonged hospital stays, and frequent readmissions.13
The inclusion of temporal analysis and the evaluation of rescue capacity based on the type of complication and onset window could provide a more precise perspective on opportunities for improvement. The development of multidisciplinary strategies, involving different specialists, could significantly contribute to optimise surgical results. We consider that, beyond reflecting only the technical skill of the surgical team, FTR constitutes an essential tool to evaluate the organisational, structural and response capacity of the healthcare system as a whole. As pointed out by Ghaferi et al. and Kinny-Köster et al., severe medical complications, such as congestive heart failure and sepsis, are associated with a lower probability of rescue, especially when they take place in the first days after surgery.1,25 This suggests that early multidisciplinary intervention is a key factor in improving the survival rate.
Although the results of this study refer to a single-centre series with a limited sample size, they reinforce the idea that FTR should not be interpreted in isolation, as its analysis could be affected by the relative incidence of complications, the surgical volume, and the structural characteristics of each centre. Moreover, the annual variability observed in FTR, in part attributable to the low rate of adverse events, also underscores the need to employ complementary indicators.
In this context, we consider that FTR should be analysed in conjunction with other tools which enable a broader and more detailed assessment of surgical performance. Among them, the Textbook Outcome, a parameter encompassing an absence of major complications, reoperations, readmissions, mortality, and positive surgical margins, and which has been validated as a reference for an “ideal outcome”, or the Benchmark Values, defined in low-risk cohorts, enable objective and comparable standards to be established among centres.26,27 Lastly, even though the concept of surgical futility is increasingly cited in highly complex procedures, its application in pancreatic surgery remains limited due to the absence of standardised criteria enabling interventions to be identified as futile in a reproducible manner.28,29 As a consequence, despite its promise, this tool requires further development before it can be systematically incorporated into quality audits. Combined, these parameters, complementary to FTR, are capable of providing a more comprehensive view of the care process, from patient selection to recovery, and contribute to a more equitable comparison between surgical centres.
Future multicentre studies, with analyses stratified by type of complication, applying risk-adjusted models and analysing the temporal window of events, could provide a more accurate picture of the role of FTR in the assessment of pancreatic surgery outcomes. The integration of FTR into a broader panel of quality indicators will enable a more robust and equitable assessment between institutions, favouring continuous improvement of surgical patient care.
In conclusion, although the rate of FTR of 8.11% in our study reflects an effective management of complications and is in line with figures for international high-volume centres, a stratified year-by-year analysis demonstrates a need to study this parameter alongside other quality indicators in order to adequately interpret care outcomes.
FundingThis study did not receive specific financing from public, commercial or non-profit entities.
The authors have no conflict of interests to declare.


