




Primary biliary cholangitis (PBC) is a chronic autoimmune liver disease (AILD) characterized by progressive destruction of intrahepatic bile ducts, leading to cholestasis.1 The prevalence of PBC in the United States has increased, rising from 21.7 to 39.2 per 100,000 persons.1,2 For end-stage liver disease in PBC, liver transplantation (LT) is the only therapeutic option that has been shown to prolong survival.3,4 Post-LT outcomes in PBC have been favorable, with 5-year patient survival ranging from 82–90 % and graft survival from 71–81 %.5,6 PBC frequently overlaps with other liver diseases, including MASLD. In fact, approximately 28 % of patients with PBC have been shown to have MASLD.7
Metabolic dysfunction-associated steatotic liver disease (MASLD) affects approximately 30 % of the global adult population.4 Its prevalence varies by region, with the highest rates in North Africa and the Middle East (41.7 %) and the lowest in high-income countries (17.3 %).8 MASLD represents a spectrum ranging from simple steatosis to more severe forms, such as metabolic dysfunction-associated steatohepatitis (MASH), which, similar to PBC, can progress to advanced fibrosis, cirrhosis, and hepatocellular carcinoma (HCC).9,10
The interplay between PBC and MASLD is of growing clinical and prognostic significance, given the rising prevalence of metabolic syndrome in recent years.10 Each of these conditions presents unique challenges, as their interaction is known to cause accelerated fibrosis progression.11 However, it is unclear whether accelerated fibrosis in patients with both PBC and MASLD translates into worse clinical outcomes.
Studies have revealed that the growing prevalence of MASLD among patients with PBC further complicates diagnosis and prognosis.11,12 Hernández-Pérez et al. found that PBC patients with histologically confirmed MASLD overlap had higher rates of liver-related mortality and liver transplantation.7 Similarly, Sorrentino et al. reported steatosis in 40.5 % of PBC patients, with 14.9 % demonstrating steatohepatitis, linking it to accelerated disease progression.12 We hypothesize that the presence of diabetes, a known accelerator of metabolic and fibrotic injury13, may act synergistically in patients with concurrent PBC and MASLD, compounding disease severity beyond what is observed with either condition alone.
Despite this concern, no studies have specifically examined the outcome of PBC and MASLD overlap in the transplant population. This study aims to address this gap. Herein, we aimed to compare pre-LT outcomes (i.e., waitlist dropout and transplant probability) and post-LT outcomes (i.e., patient and graft survival up to 10 years) between PBC patients with and without MASLD. Secondarily, we compared post-LT patient and graft survival between PBC and PBC/MASLD patients with and without diabetes.
2Materials and Methods2.1Study populationWe conducted a comprehensive retrospective study using the United Network for Organ Sharing (UNOS)/Organ Procurement and Transplantation Network (OPTN) database to identify adult patients aged ≥18 years with PBC and concomitant MASLD/PBC who were listed for LT between January 1, 2002, and April 4, 2024. Patients were excluded if they had any of the following (1) prior organ transplantation (2) multi-organ transplantation (3) split/reduced LT or (4) transferred to or received LT at another center to prevent counting multiple-listed patients (5) missing data in any of the variables used for predictors of long term outcomes (6) any other concomitant liver disease etiology including autoimmune hepatitis or primary sclerosing cholangitis.
The authors’ institution deemed the UNOS database as publicly available de-identified data; thus, institutional review board (IRB) approval was not required. The data reported here were supplied by UNOS as the contractor for OPTN.
2.2Study variablesThis study included variables at the time of candidate listing for LT. Recipients and donor variables were categorized into two groups: PBC and concomitant PBC/MASLD. We included primary diagnoses of liver diseases. Etiologies were defined using OPTN/UNOS primary listing diagnosis codes, listed in the variable Transplant Candidate Registration (TCR): PBC (codes 4220) and MASLD (code 4214). Patients diagnosed with cryptogenic cirrhosis (codes 4208 and 2013) who had a body mass index of 30 or higher were classified within the metabolic MASLD group, consistent with the methodology used in prior research.14–16
Recipient demographics included age, sex, race, blood group, BMI, and comorbidities such as diabetes mellitus, ascites, encephalopathy, spontaneous bacterial peritonitis (SBP), presence of hepatocellular carcinoma (HCC), prior dialysis (within the week before LT), prior abdominal surgery, and portal vein thrombosis (PVT). Laboratory variables comprised the Model for End-Stage Liver Disease (MELD) score. The geographic region was also considered. Donor variables encompassed age, sex, race, body mass index (BMI), diabetes mellitus, cold ischemia time (CIT), and donor risk index (DRI). We also captured life-support status at listing, defined as the use of major organ-support therapies such as invasive mechanical ventilation or other organ-support devices (e.g., ECMO or ventricular assist devices).
2.3OutcomesPrimary outcomes were pre-LT outcomes and post-LT outcomes between PBC patients with and without MASLD. Pre-LT outcomes included waitlist dropout and LT probability. Waitlist dropout was a composite outcome defined as removal due to death before LT, clinical deterioration, or "other." Transplant probability was defined as the cumulative incidence (probability) of undergoing LT after WL, with death, clinical deterioration, or other removal treated as competing risks.
Post-LT outcomes were patient and graft survival after LT at 1-, 3-, 5-, and 10-years. Patient survival was defined as the time from the date of LT until the date of death or last follow-up. Graft survival was defined as the time from the date of LT until graft failure, last follow-up, or the need for a re-LT.
In the subgroup analysis, secondary outcomes were differences in patient and graft survival after LT at 1-, 3, 5-, and 10-years between PBC and MASLD patients with and without diabetes.
2.4Statistical analysisContinuous variables were summarized as means with standard deviation (SD) and median with interquartile range (IQR), using ANOVA or the Kruskal-Wallis test according to the underlying distribution. Categorical variables were summarized using frequencies and percentages, and the chi-square test was performed as the comparative measure.
To evaluate post-transplant outcomes, we performed propensity score matching to adjust for potential confounding by age, sex, BMI, candidate race, and comorbidities present at the time of transplant, including use of life support, dialysis, hepatic encephalopathy, and ascites. We also included the MELD score at transplant, candidate diabetes status, donor age, donor race, and donor history of diabetes. For pre-transplant analyses, we considered the same candidate-related variables; however, complications were assessed at the time of waitlisting, and donor variables were excluded. To mitigate confounding bias and enhance validity, we conducted exact 1:1 matching between the PBC and PBC/MASLD groups for both pre- and post-transplant analyses. Matching was performed using propensity scores derived from a greedy nearest-neighbor algorithm with a caliper width of 0.1, ensuring close balance across baseline characteristics.
Kaplan-Meier failure functions were utilized to graphically depict the cumulative incidence of waitlist removal and transplantation. The Kaplan-Meier method was applied to estimate the time-to-event distributions, and comparisons between the groups were performed using the log-rank test to assess statistical significance. These analyses allowed for clear visualization and comparison of the failure probabilities over time.
Kaplan–Meier estimates, followed by the nonparametric log-rank test and propensity score matching, were used to assess survival rates between the study groups. Cox proportional hazard regression models were performed, and the multivariate analysis was adjusted for recipient variables (race, diabetes, encephalopathy, transjugular intrahepatic portosystemic shunt [TIPS], previous abdominal surgery, dialysis, PVT, and MELD), donor characteristics (age, diabetes), and geographic region. Forward manual selection of variables, including those with a p-value <0.05 and those of clinical relevance, was performed. Sensitivity analyses were conducted by stratifying outcomes by PBC and PBC/MASLD, and by excluding patients classified as MASLD based on cryptogenic cirrhosis with obesity.
All 95 % CIs were based on two-sided hypothesis tests, with p < 0.05 considered statistically significant. The statistical analysis was executed using Stata version 19.0 MP (StataCorp LP, College Station, TX, USA).
2.5Ethical considerationsNo direct patient contact or intervention occurred, and the study was conducted in accordance with the ethical standards of the 1964 Declaration of Helsinki and its later amendments. All data were handled confidentially, and no individual patient was identified from the dataset. The interpretation and reporting of these data are the sole responsibility of the authors and do not represent an official policy or interpretation of OPTN or the U.S. Government.
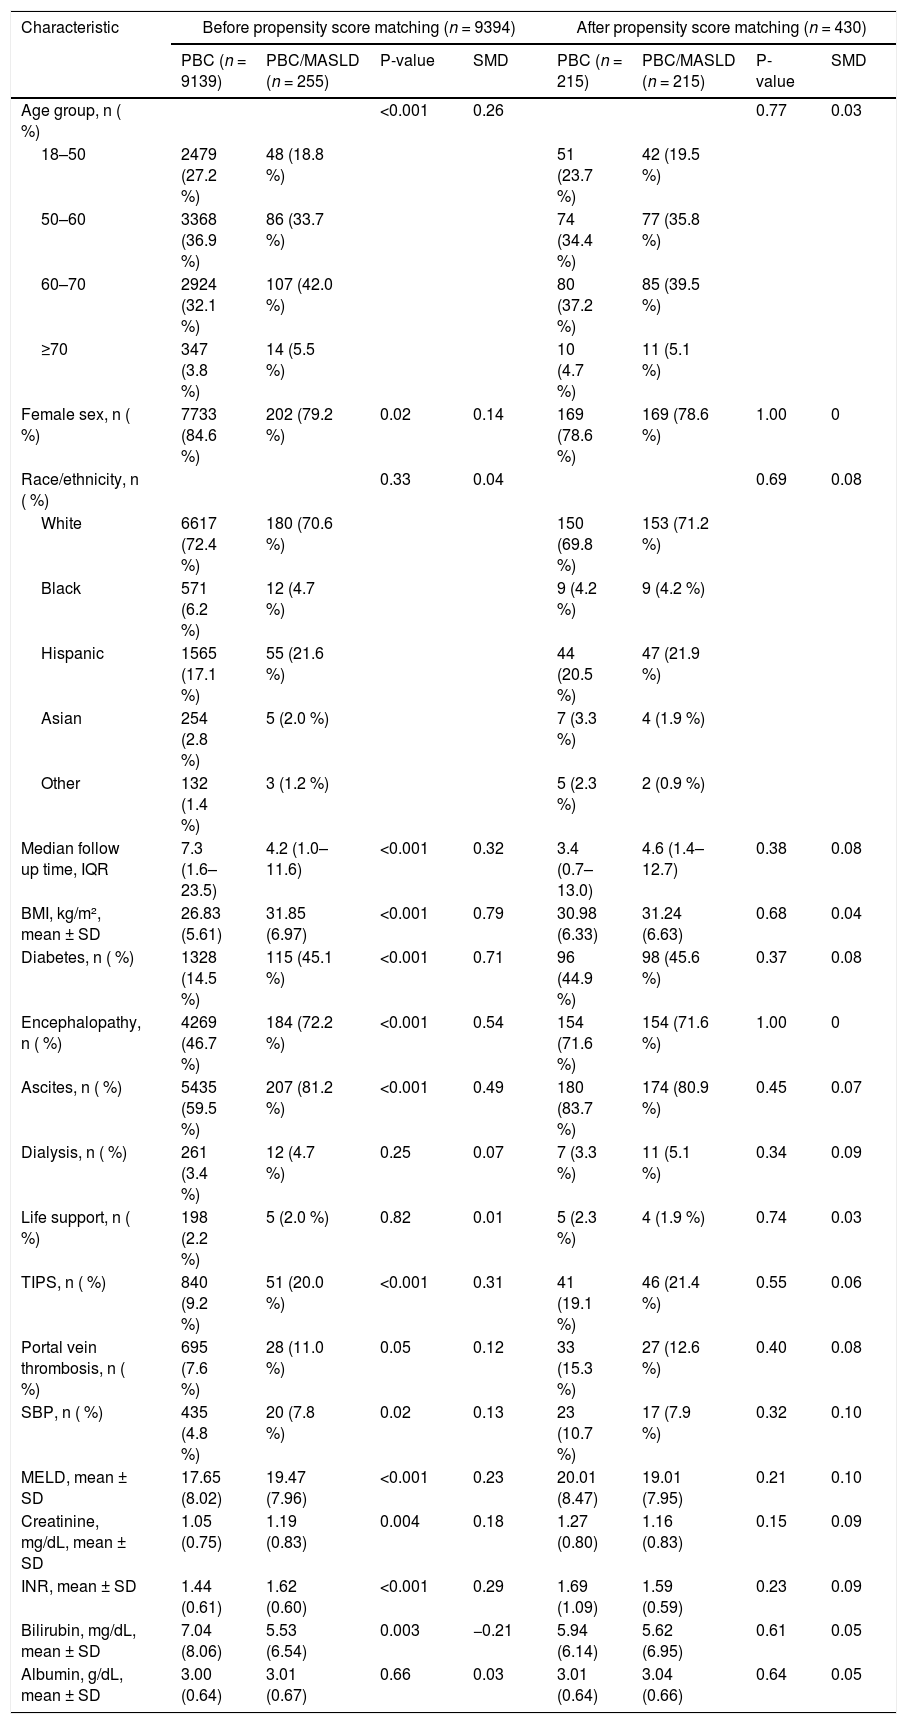
3Results3.1Study sampleThe pre-transplant cohort included 9394 patients before propensity score matching, of whom 9139 had PBC alone and 255 had PBC/MASLD (Table 1). However, the two patient groups were largely imbalanced (standardized mean difference p < 0.05 for 13 of 17 variables). After 1:1 propensity score matching (215 in each group), covariate balancing was achieved across all patient characteristics (standardized mean difference [SMD] p > 0.05 for all).
Baseline characteristics of the pre-liver transplant population.
Abbreviations: BMI, Body Mass Index; INR, International Normalized Ratio; IQR, Interquartile Range; MASLD, Metabolic Dysfunction-Associated Steatotic Liver Disease; MELD, Model for End-stage Liver Disease; PBC, Primary Biliary Cholangitis; SBP, Spontaneous Bacterial Peritonitis; SD, Standard Deviation; SMD, Standardized Mean Difference; TIPS, Transjugular Intrahepatic Portosystemic Shunt.
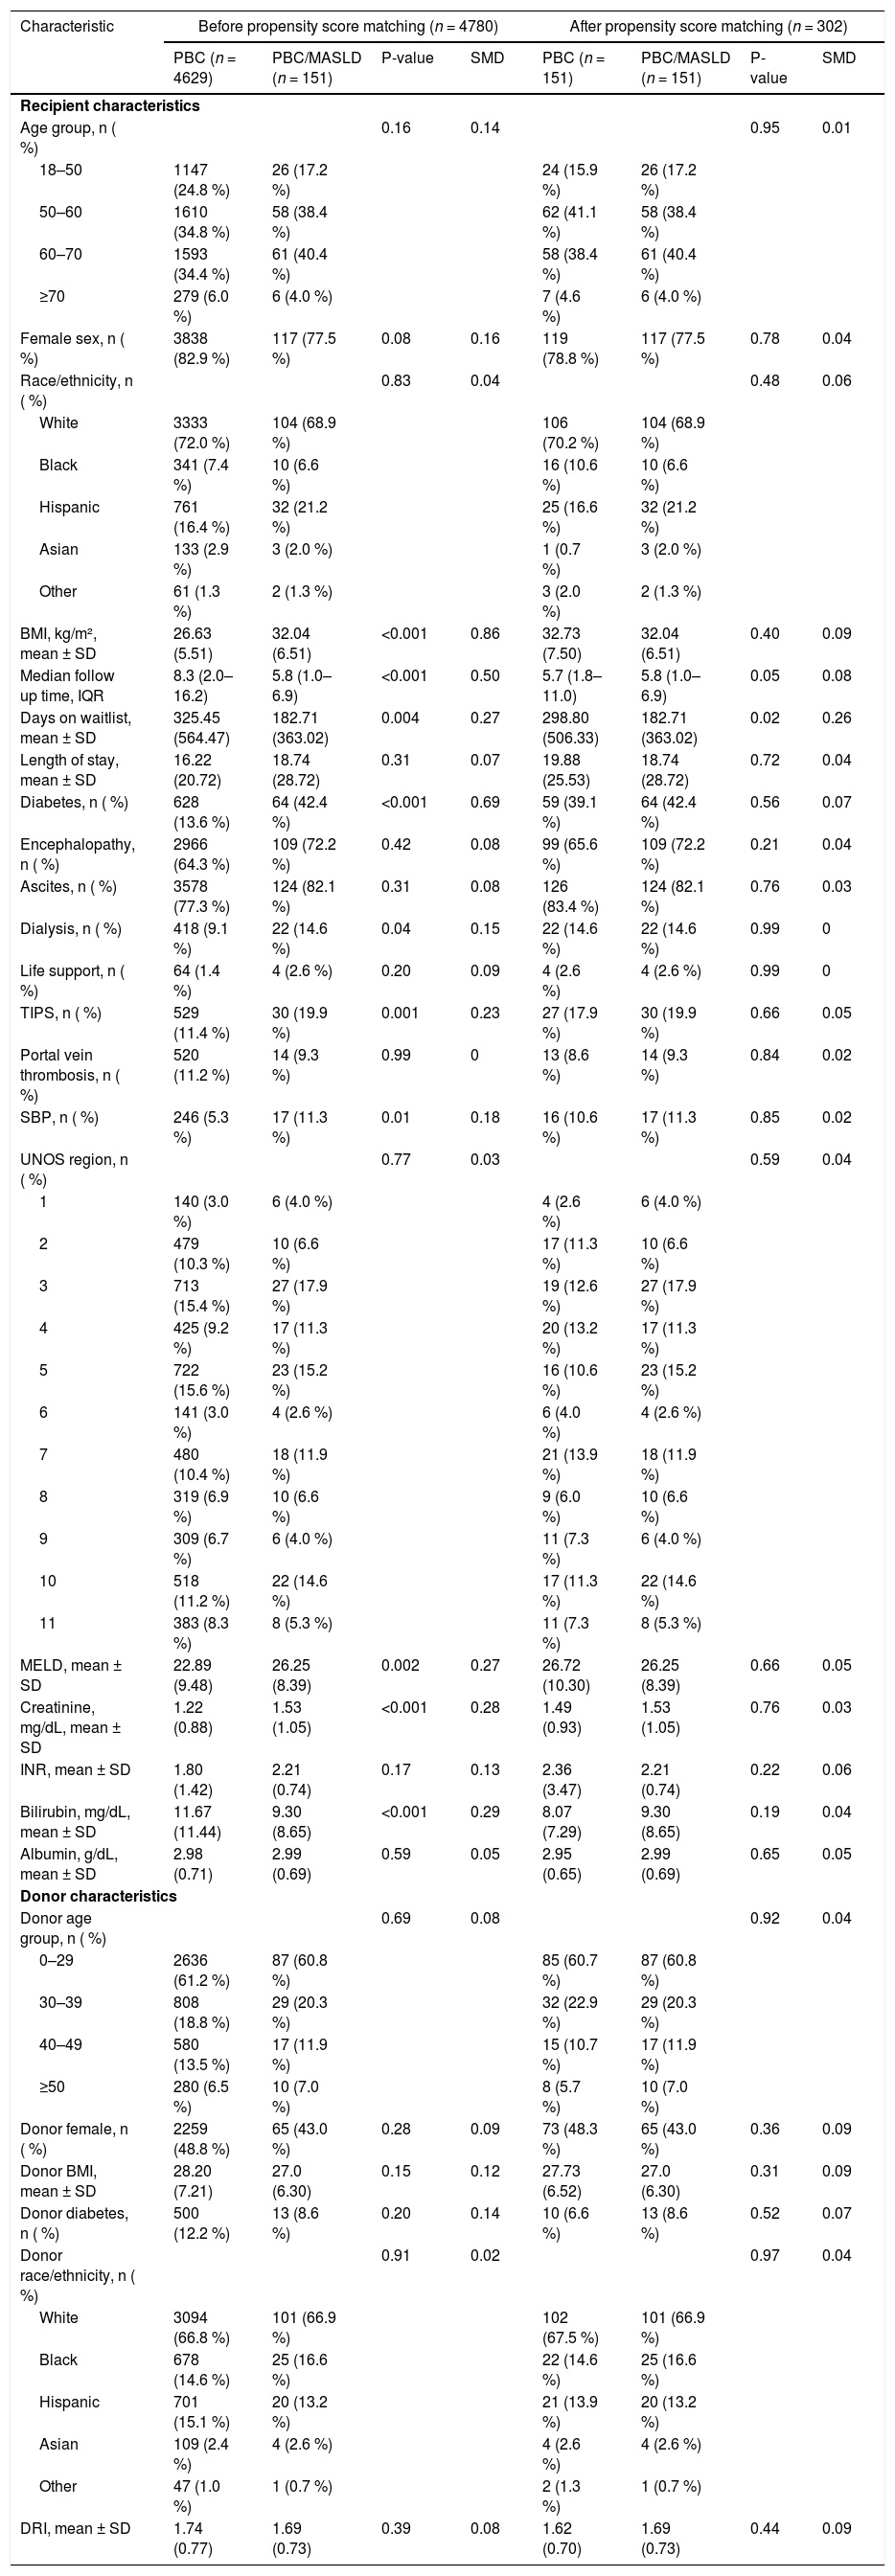
The post-transplant cohort included 4780 liver transplant recipients before propensity score matching, of whom 4629 had PBC alone and 151 had PBC/MASLD (Table 2); however, the two patient groups were imbalanced. After 1:1 propensity score matching (151 in each group), covariate balancing was achieved on all variables except for waitlist time (SMD, 0.26).
Baseline characteristics of the post-liver transplant population.
Abbreviations: BMI, Body Mass Index; DRI, Donor Risk Index; INR, International Normalized Ratio; IQR, Interquartile Range; MASLD, Metabolic-Associated Steatotic Liver Disease; MELD, Model for End-stage Liver Disease; PBC, Primary Biliary Cholangitis; SBP, Spontaneous Bacterial Peritonitis; SD, Standard Deviation; SMD, Standardized Mean Difference; TIPS, Transjugular Intrahepatic Portosystemic Shunt; UNOS, United Network for Organ Sharing.
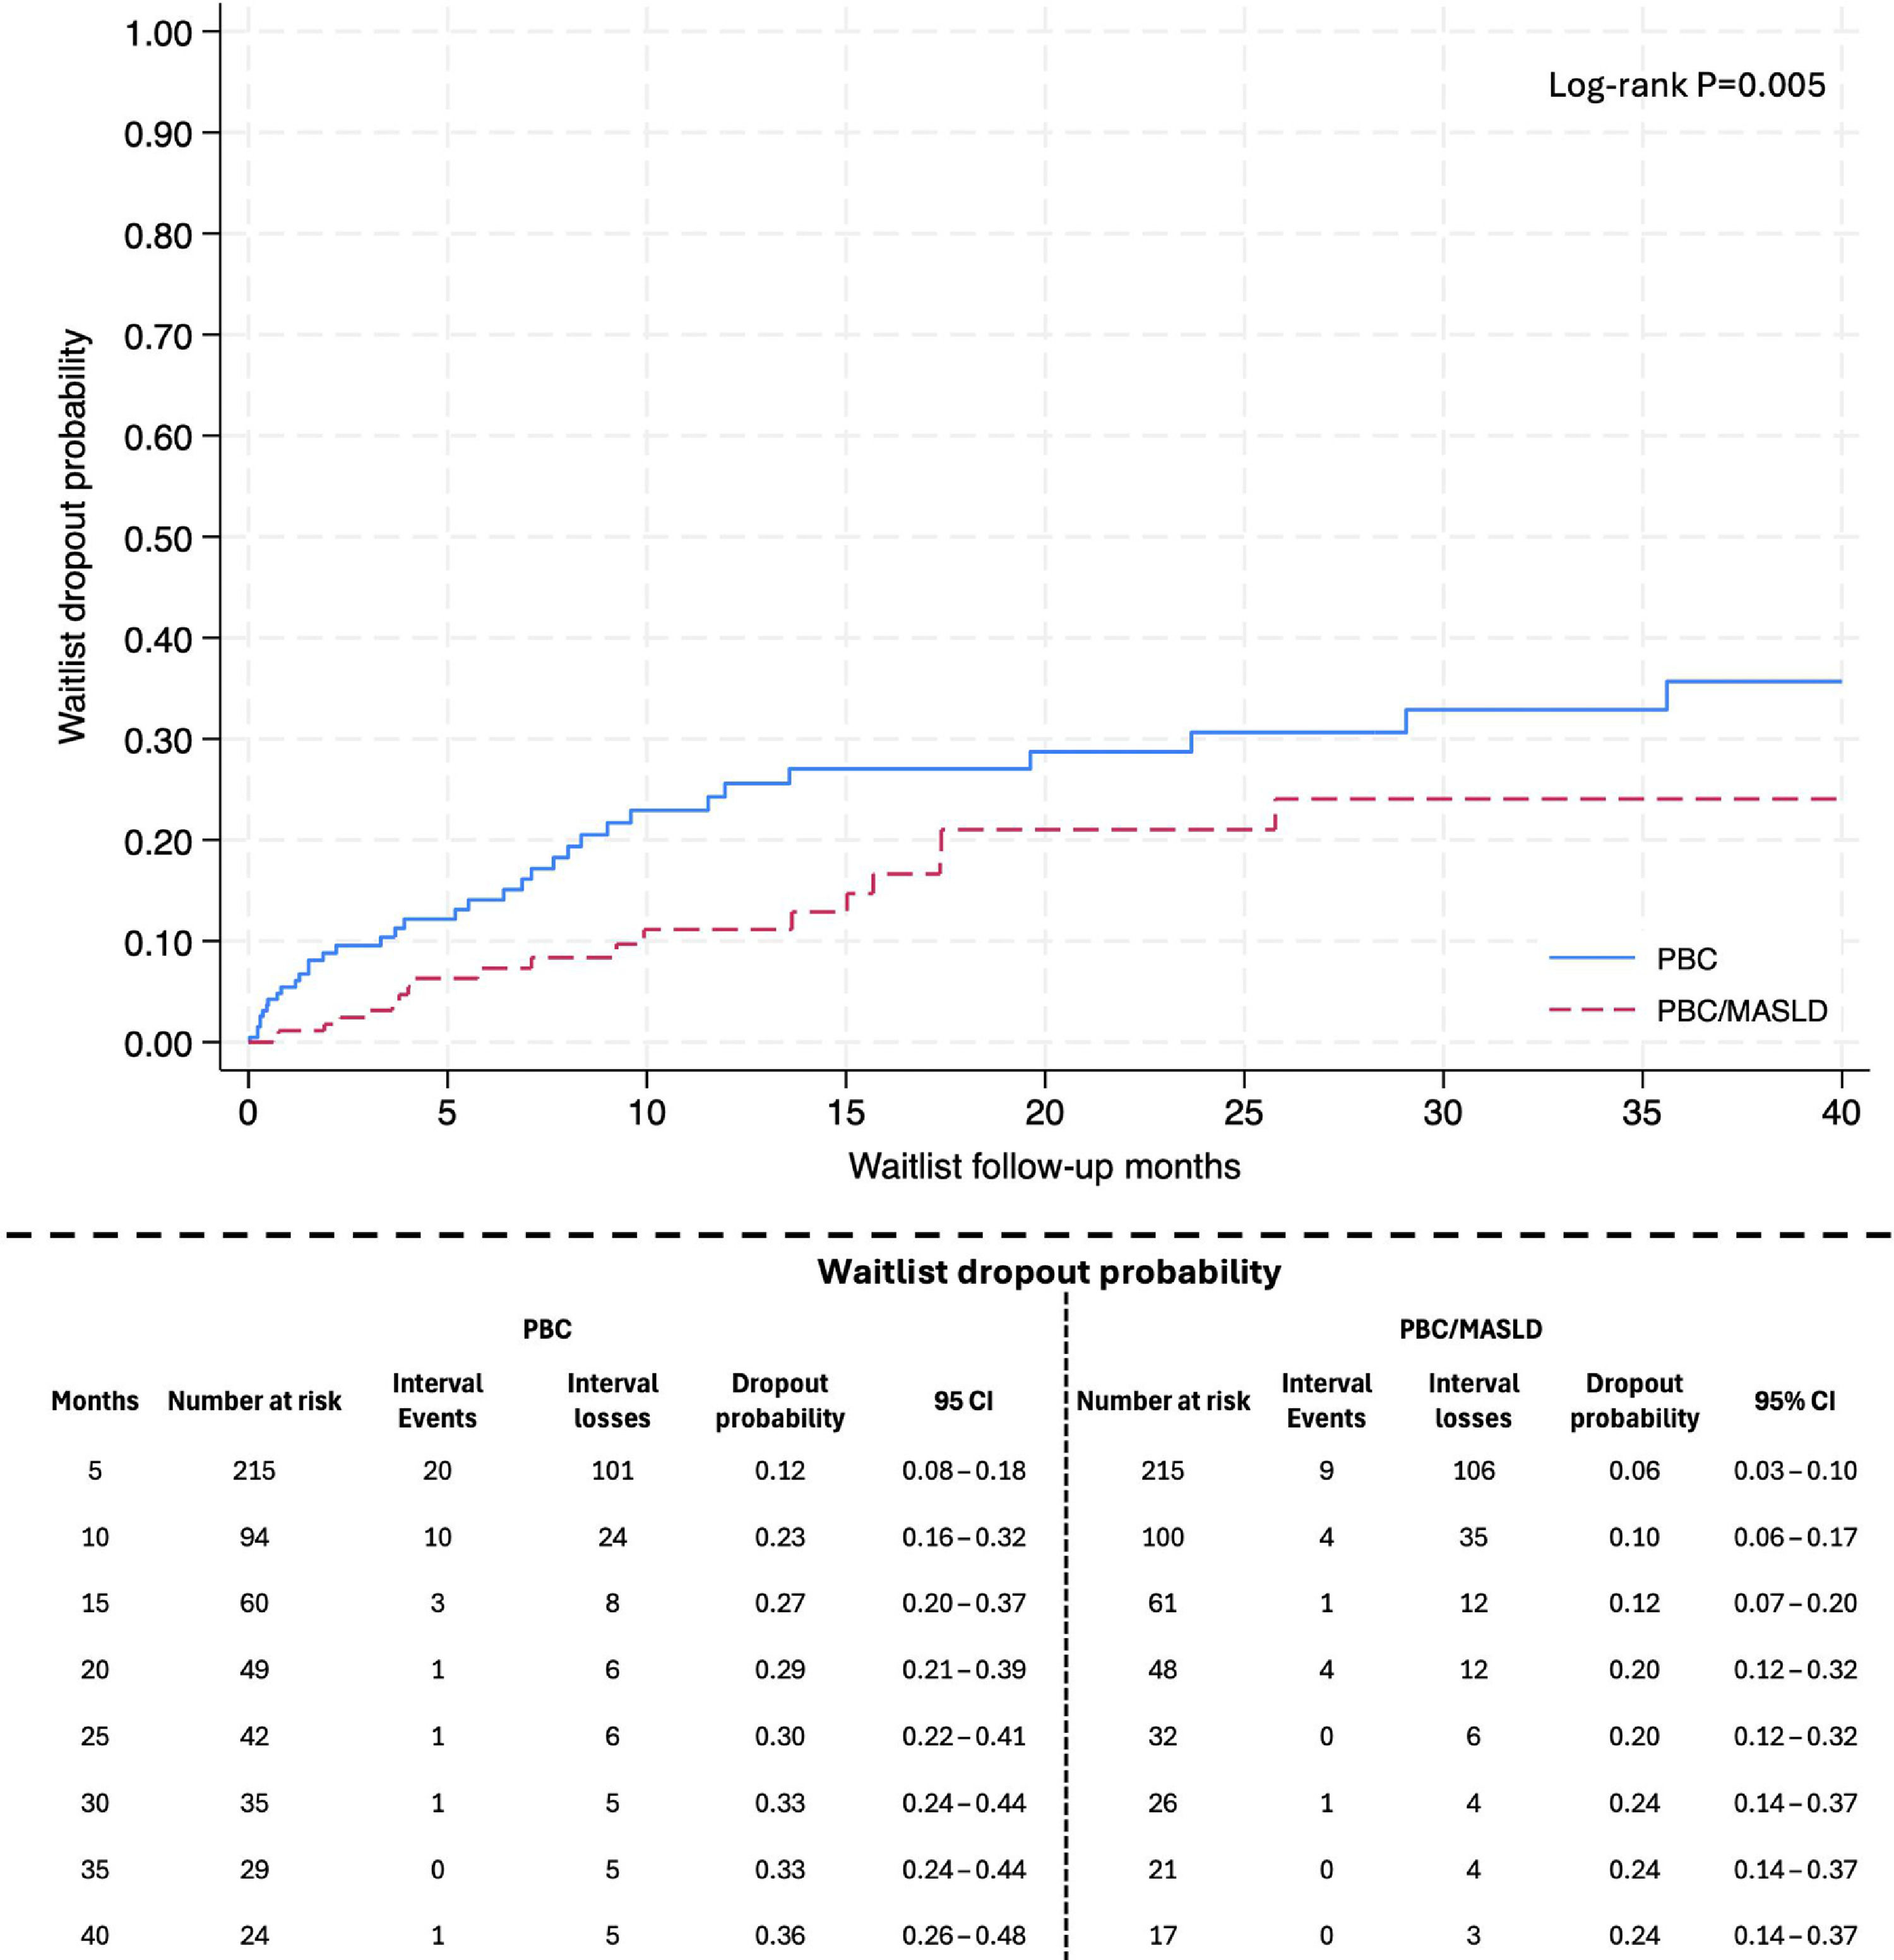
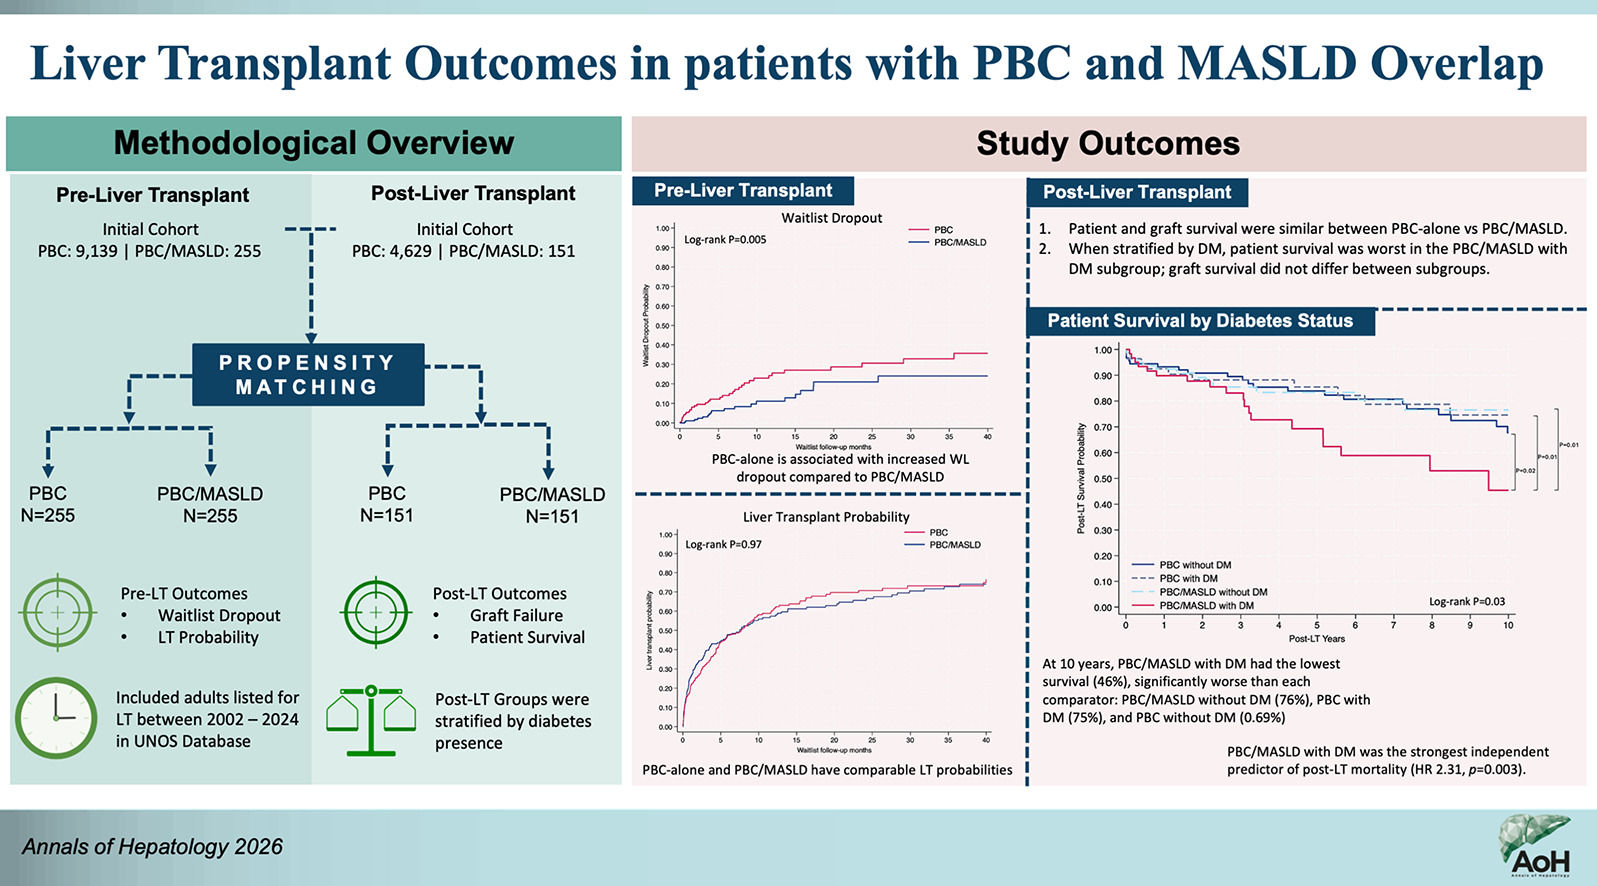
Waitlist dropout (Fig. 1) showed a statistically significant difference between the PBC and PBC/MASLD groups (log-rank p = 0.005). At 5 months, dropout probability was 0.12 (95 CI: 0.08–0.18) for PBC and 0.06 (95 CI: 0.03–0.10) for PBC/MASLD. By 10 months, dropout probability increased to 0.23 (95 CI: 0.16–0.32) in PBC and 0.10 (95 CI: 0.06–0.17) in PBC/MASLD. At 20 months, dropout probability reached 0.29 (95 CI: 0.21–0.39) for PBC and 0.20 (95 CI: 0.13–0.32) for PBC/MASLD. Long-term dropout at 40 months was 0.36 (95 CI: 0.26–0.48) for PBC and 0.24 (95 CI: 0.14–0.37) for PBC/MASLD.

Waitlist dropout rates in the first 40 months after listing.
Abbreviations: CI: Confidence interval; MASLD: Metabolic dysfunction-associated steatotic liver disease; PBC: Primary biliary cholangitis.
Definitions: Waitlist dropout probabilities were estimated using the Kaplan-Meier method; Number at risk represents patients remaining under observation at each time point; Interval events indicate the number of deaths occurring within each time interval; Interval losses represent patients censored (lost to follow-up or study end) within each time interval.
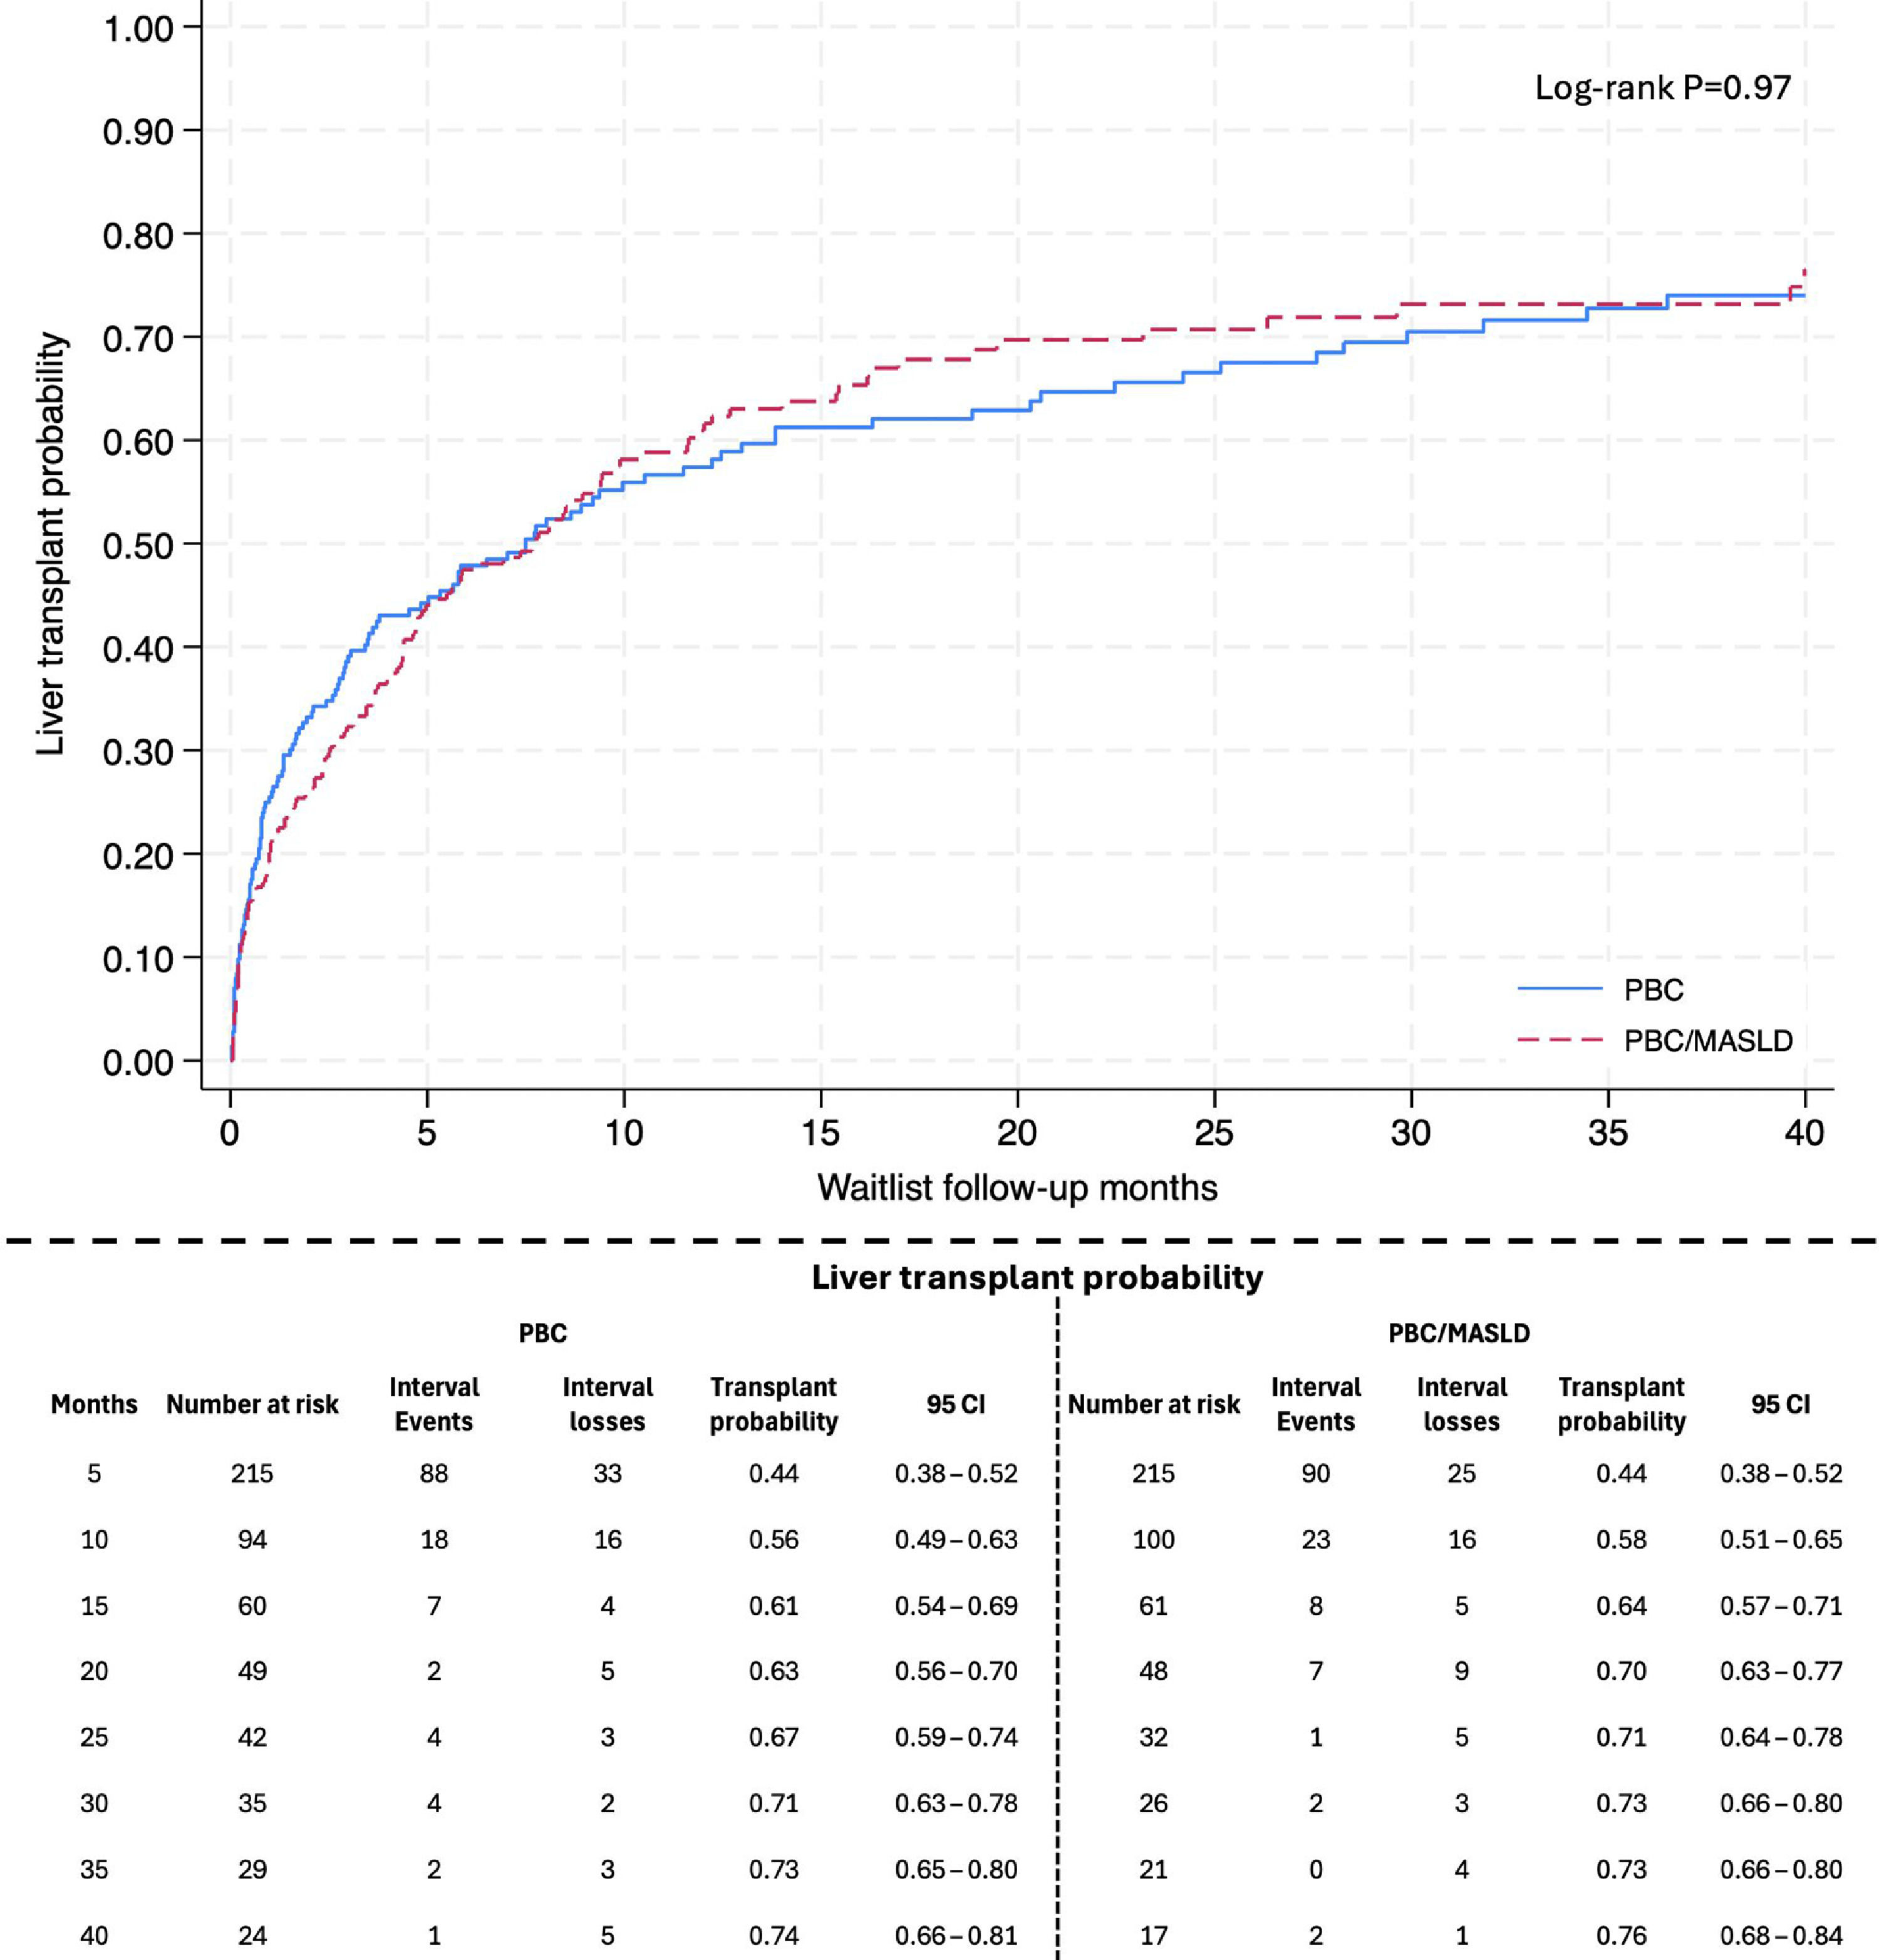
Transplant probabilities (Fig. 2) did not demonstrate a statistically significant difference between the PBC and PBC/MASLD groups (log-rank p = 0.97). At 5 months, liver transplant probability was 0.44 (95 CI: 0.38–0.52) for PBC and 0.44 (95 CI: 0.38–0.52) for PBC/MASLD. By 10 months, the probability increased to 0.58 (95 CI: 0.51–0.65) for PBC and 0.56 (95 CI: 0.49–0.63) for PBC/MASLD. By 20 months, probabilities further increased to 0.70 (95 CI: 0.63–0.77) for PBC and 0.63 (95 CI: 0.56–0.70) for PBC/MASLD. Long-term transplant probability at 40 months was 0.76 (95 CI: 0.68–0.84) for PBC and 0.74 (95 CI: 0.66–0.81) for PBC/MASLD.

Probability of receiving a liver transplant in the first 40 months after listing.
Abbreviations: CI: Confidence interval; MASLD: Metabolic dysfunction-associated steatotic liver disease; PBC: Primary biliary cholangitis.
Definitions: Transplant probabilities were estimated using the Kaplan-Meier method; Number at risk represents patients remaining under observation at each time point; Interval events indicate the number of deaths occurring within each time interval; Interval losses represent patients censored (lost to follow-up or study end) within each time interval.
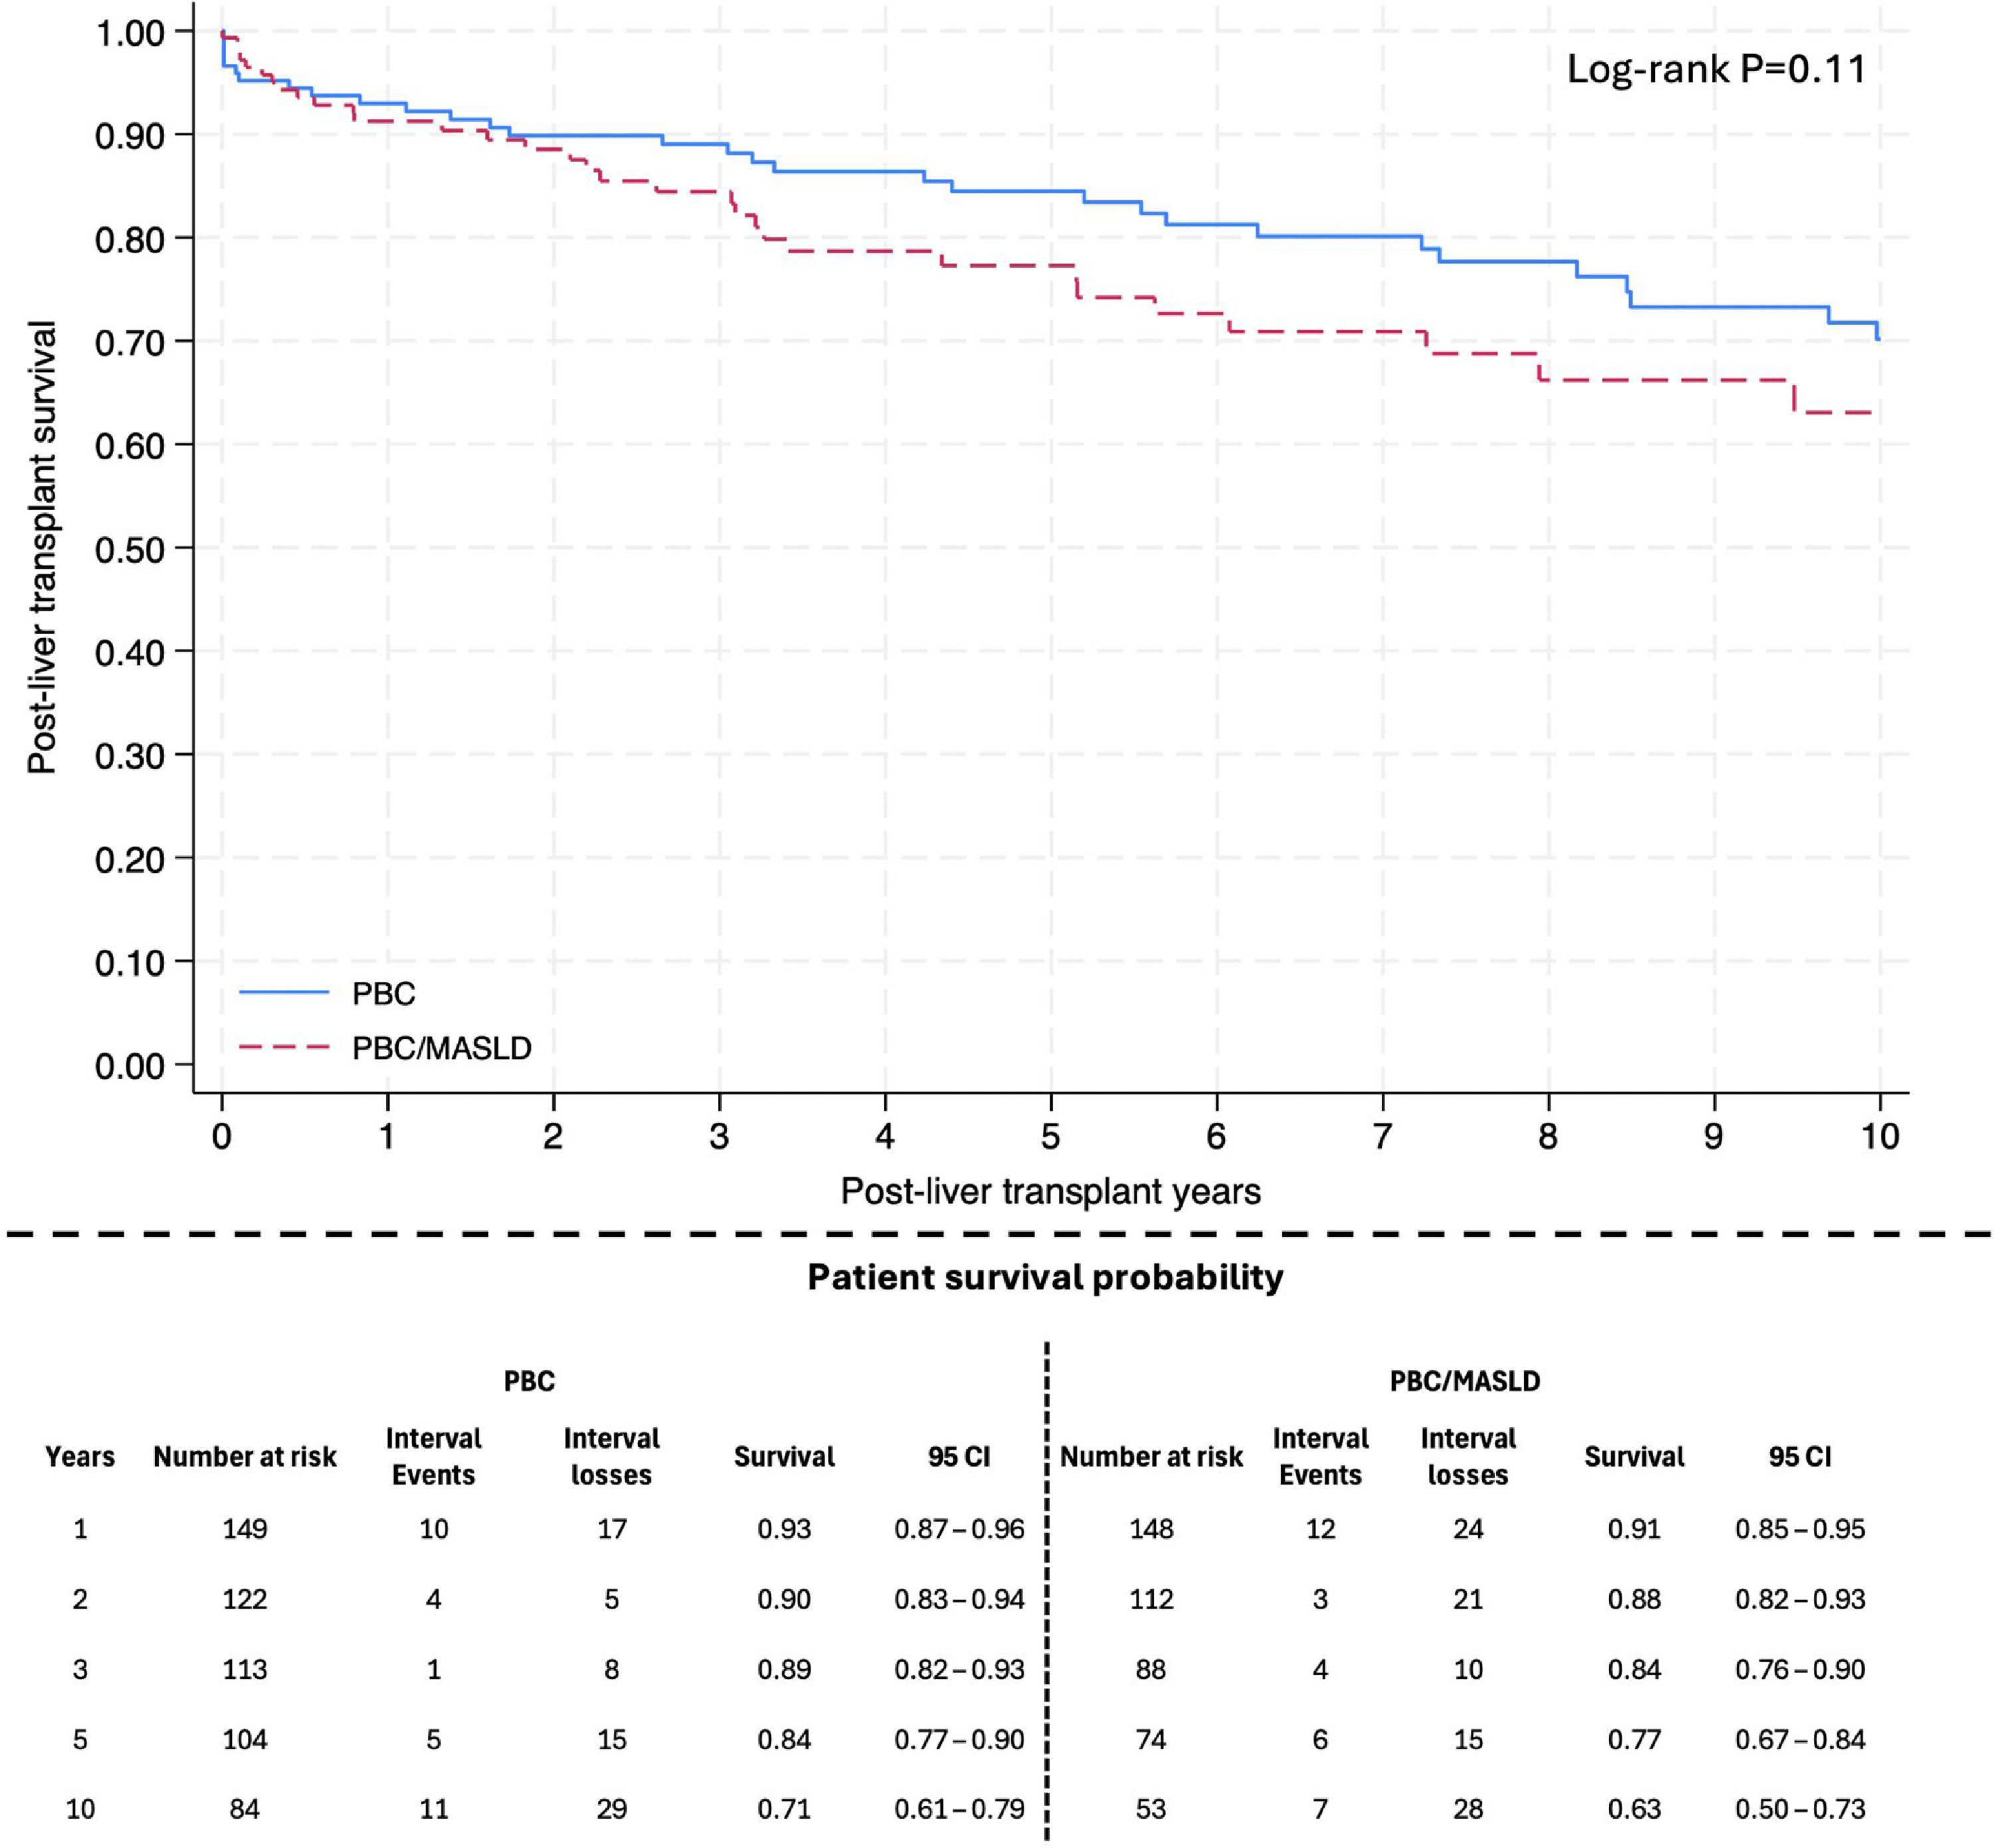
The Kaplan-Meier analysis of post-transplant patient survival (Fig. 3) showed no statistically significant difference between the PBC and PBC/MASLD groups (log-rank p = 0.11). At 1 year, patient survival probability was 0.93 (95 CI: 0.87–0.96) for PBC and 0.91 (95 CI: 0.85–0.95) for PBC/MASLD. At 3 years, survival was 0.89 (95 % CI: 0.82–0.93) for PBC and 0.84 (95 CI: 0.76–0.90) for PBC/MASLD. At 5 years, survival declined to 0.84 (95 CI: 0.77–0.90) for PBC and 0.77 (95 CI: 0.67–0.84) for PBC/MASLD. At 10 years, survival was 0.71 (95 CI: 0.61–0.79) for PBC and 0.63 (95 CI: 0.50–0.73) for PBC/MASLD.

Patient survival over the last decade.
Abbreviations: CI: Confidence interval; MASLD: Metabolic dysfunction-associated steatotic liver disease; PBC: Primary biliary cholangitis.
Definitions: Survival probabilities were estimated using the Kaplan-Meier method; Number at risk represents patients remaining under observation at each time point; Interval events indicate the number of deaths occurring within each time interval; Interval losses represent patients censored (lost to follow-up or study end) within each time interval.
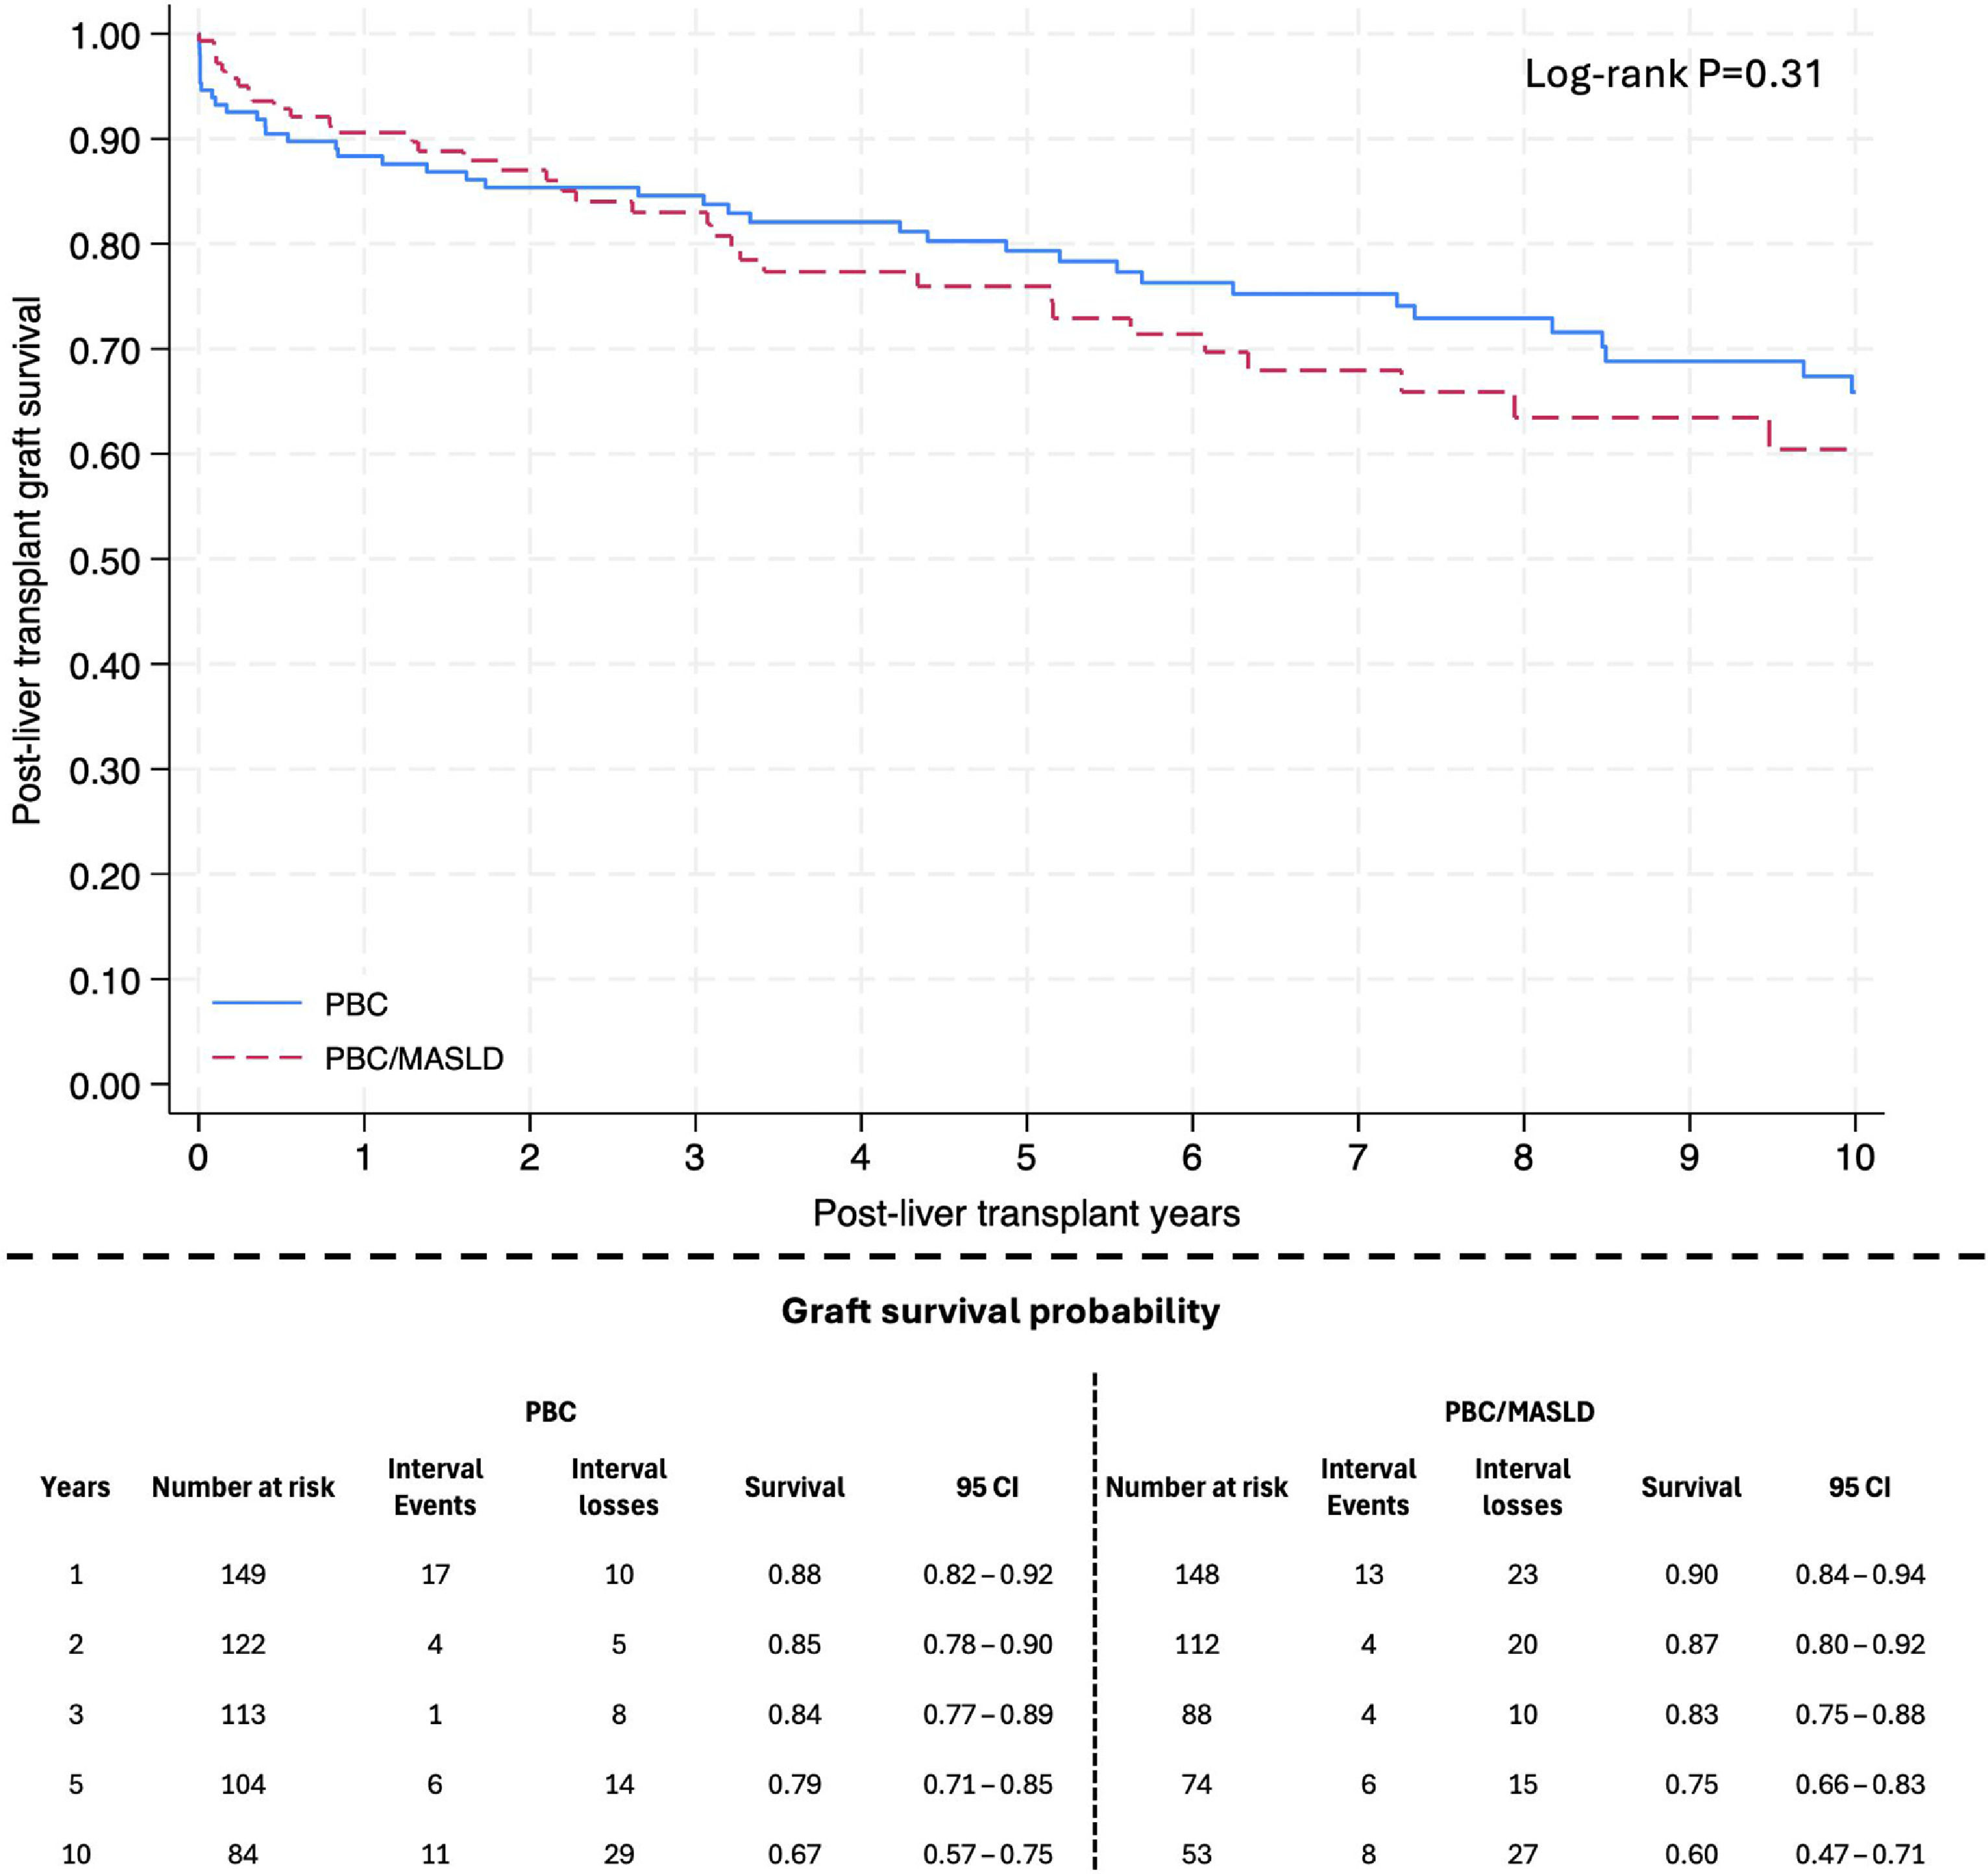
Graft survival (Fig. 4) showed no statistically significant difference between the PBC and PBC/MASLD groups (log-rank p = 0.31). At 1 year, graft survival probability was 0.88 (95 CI: 0.82–0.92) for PBC and 0.90 (95 CI: 0.84–0.94) for PBC/MASLD. By 3 years, survival was 0.84 (95 CI: 0.77–0.89) for PBC and 0.83 (95 % CI: 0.75–0.88) for PBC/MASLD. At 5 years, graft survival probability declined to 0.79 (95 % CI: 0.73–0.87) for PBC and 0.75 (95 % CI: 0.66–0.83) for PBC/MASLD. At 10 years, long-term graft survival was 0.67 (95 CI: 0.57–0.75) for PBC and 0.60 (95 CI: 0.47–0.71) for PBC/MASLD.

Graft survival over the last decade
Abbreviations: CI: Confidence interval; MASLD: Metabolic dysfunction-associated steatotic liver disease; PBC: Primary biliary cholangitis.
Definitions: Survival probabilities were estimated using the Kaplan-Meier method; Number at risk represents patients remaining under observation at each time point; Interval events indicate the number of deaths occurring within each time interval; Interval losses represent patients censored (lost to follow-up or study end) within each time interval.
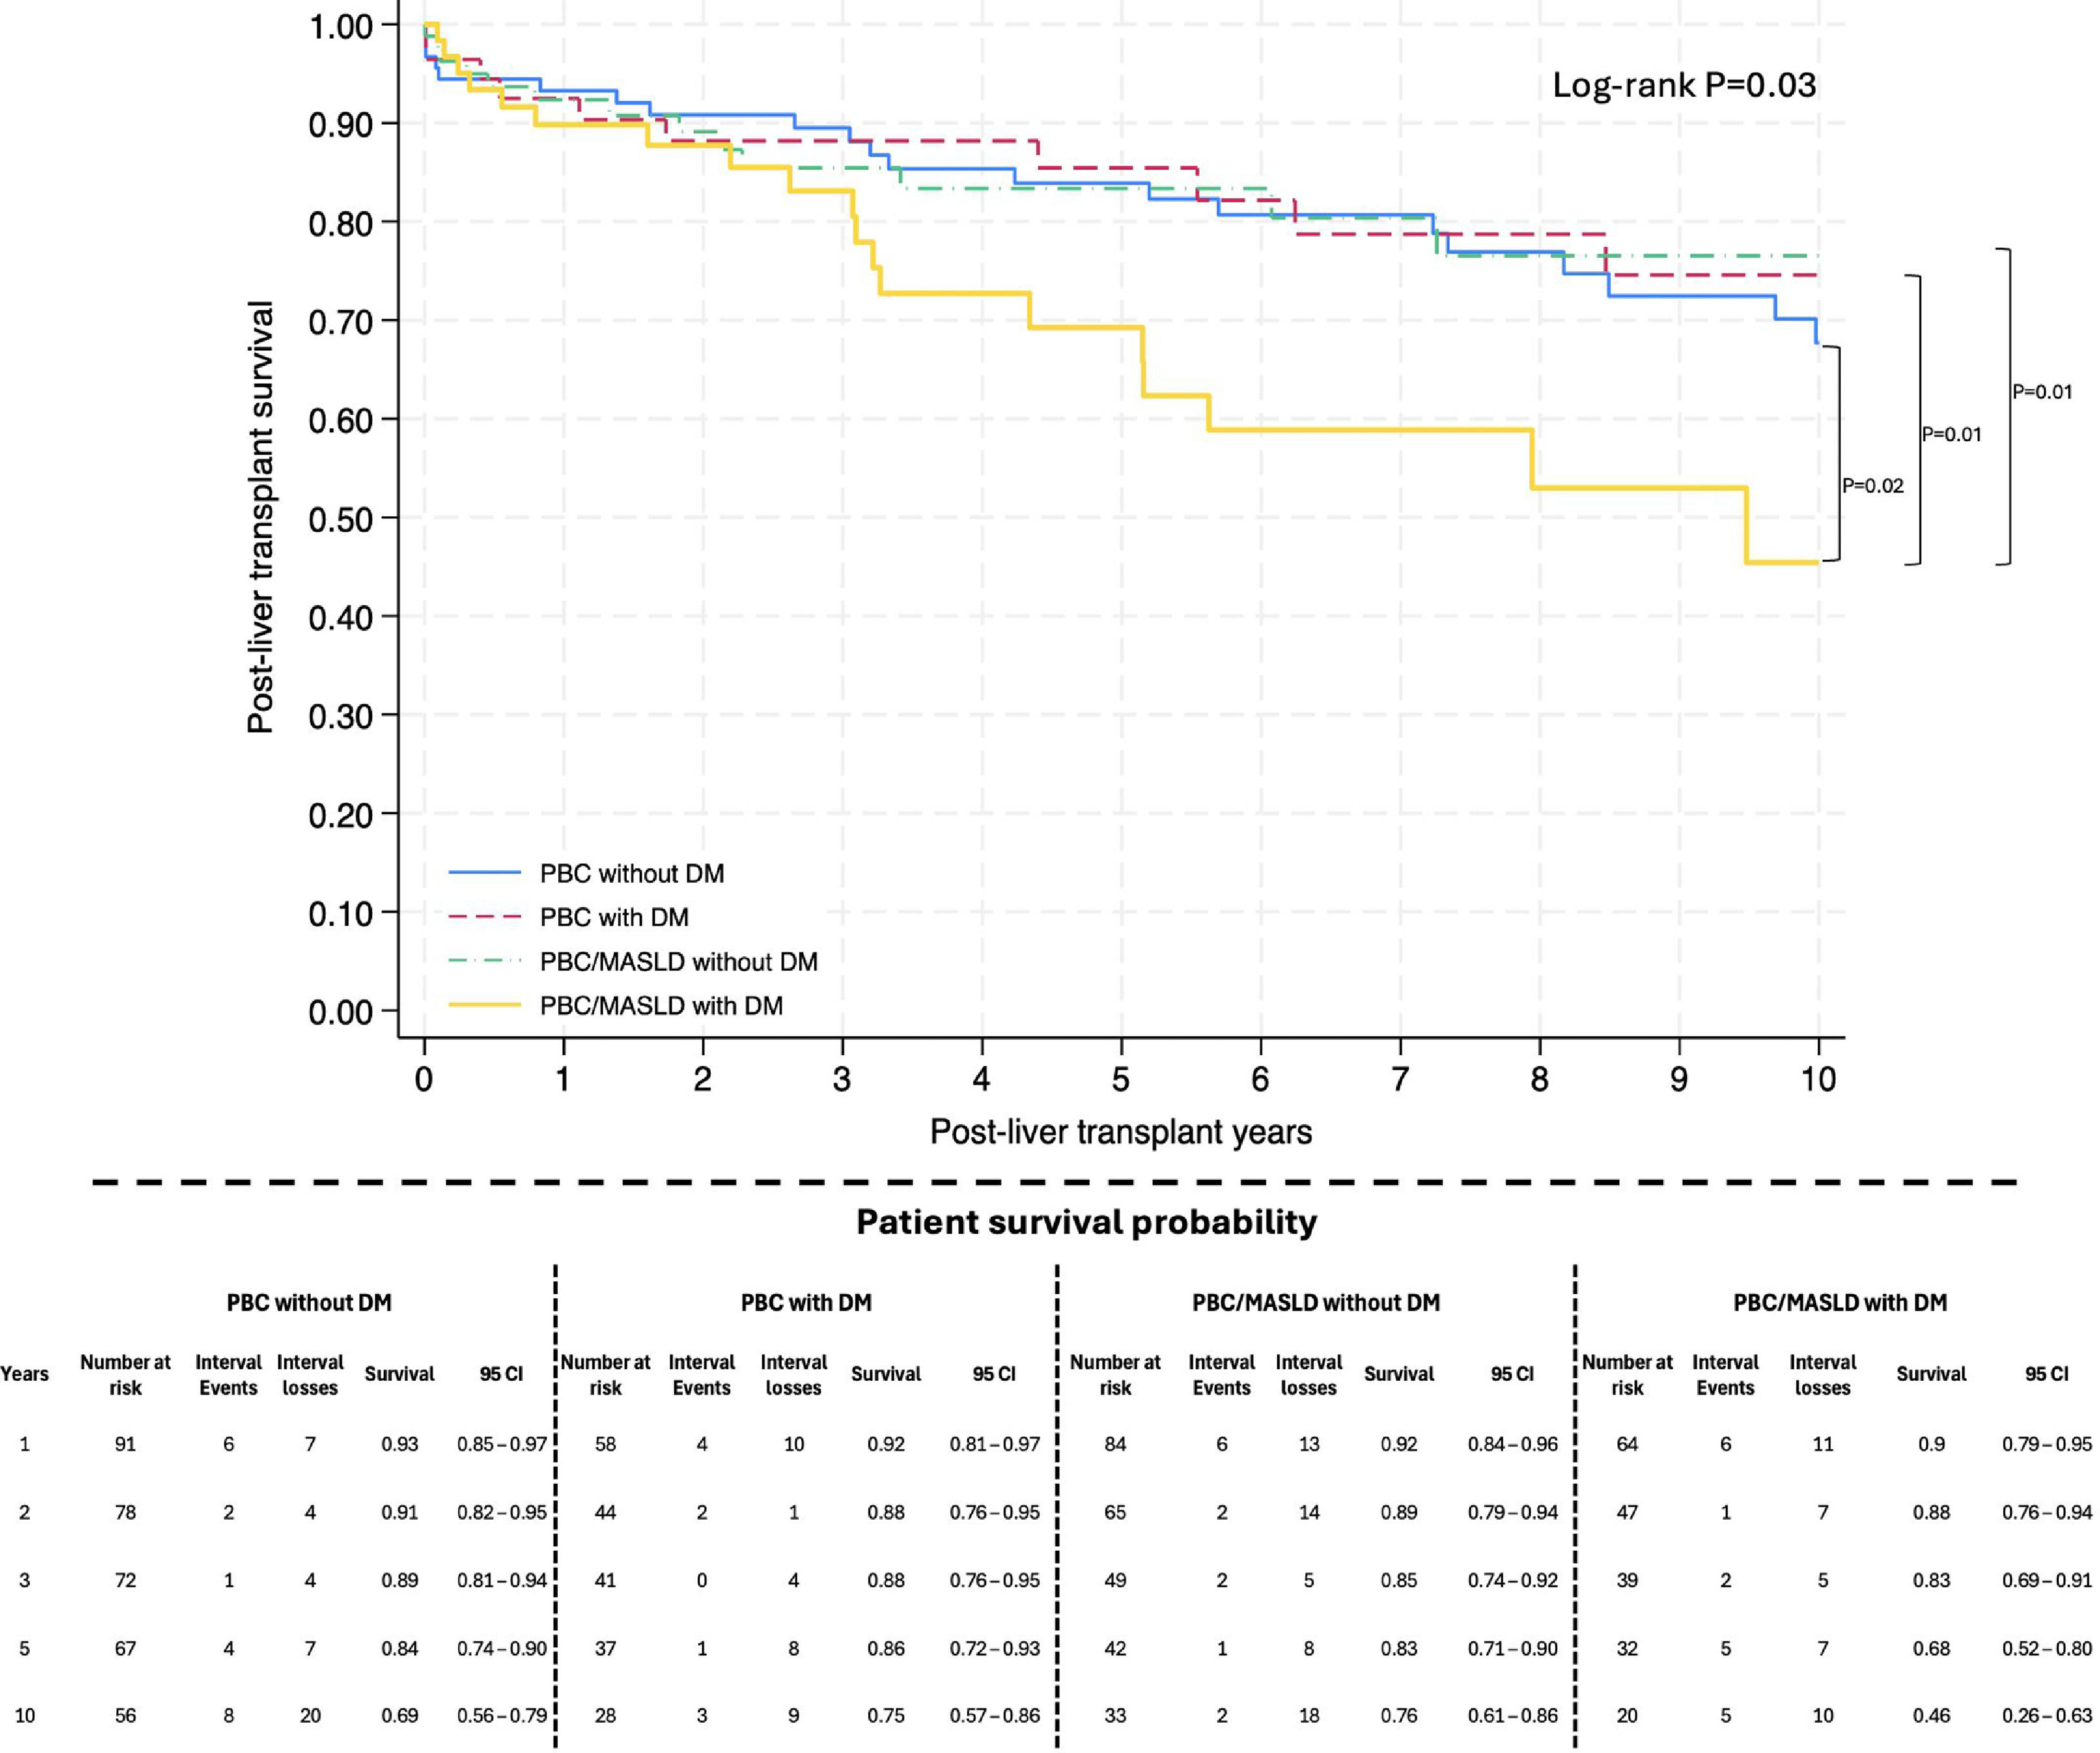
When stratifying post-transplant patient survival by diabetes status (Fig. 5), the survival curves differed significantly (log-rank p = 0.03). Patient survival probability at 1 year was 0.93 for PBC without diabetes (95 CI: 0.85–0.97), 0.92 for PBC with diabetes (95 CI: 0.81–0.97), 0.92 for PBC/MASLD without diabetes (95 CI: 0.84–0.96), and 0.90 for PBC/MASLD with diabetes (95 CI: 0.79–0.95). By 5 years, survival was 0.84 (95 CI: 0.74–0.90), 0.86 (95 CI: 0.72–0.93), 0.83 (95 CI: 0.71–0.90), and 0.68 (95 CI: 0.52–0.80), respectively. At 10 years, survival was 0.69 (95 CI: 0.56–0.79), 0.75 (95 CI: 0.57–0.86), 0.76 (95 CI: 0.61–0.86), and 0.46 (95 CI: 0.26–0.63), respectively; the lowest survival was observed in PBC/MASLD with diabetes, which was significantly lower compared to PBC/MASLD without diabetes (p = 0.01), PBC with diabetes (p = 0.01), and PBC without diabetes (p = 0.02).

Patient survival over the last decade by diabetes status.
Abbreviations: CI: Confidence interval; MASLD: Metabolic dysfunction-associated steatotic liver disease; PBC: Primary biliary cholangitis.
Definitions: Survival probabilities were estimated using the Kaplan-Meier method; Number at risk represents patients remaining under observation at each time point; Interval events indicate the number of deaths occurring within each time interval; Interval losses represent patients censored (lost to follow-up or study end) within each time interval.
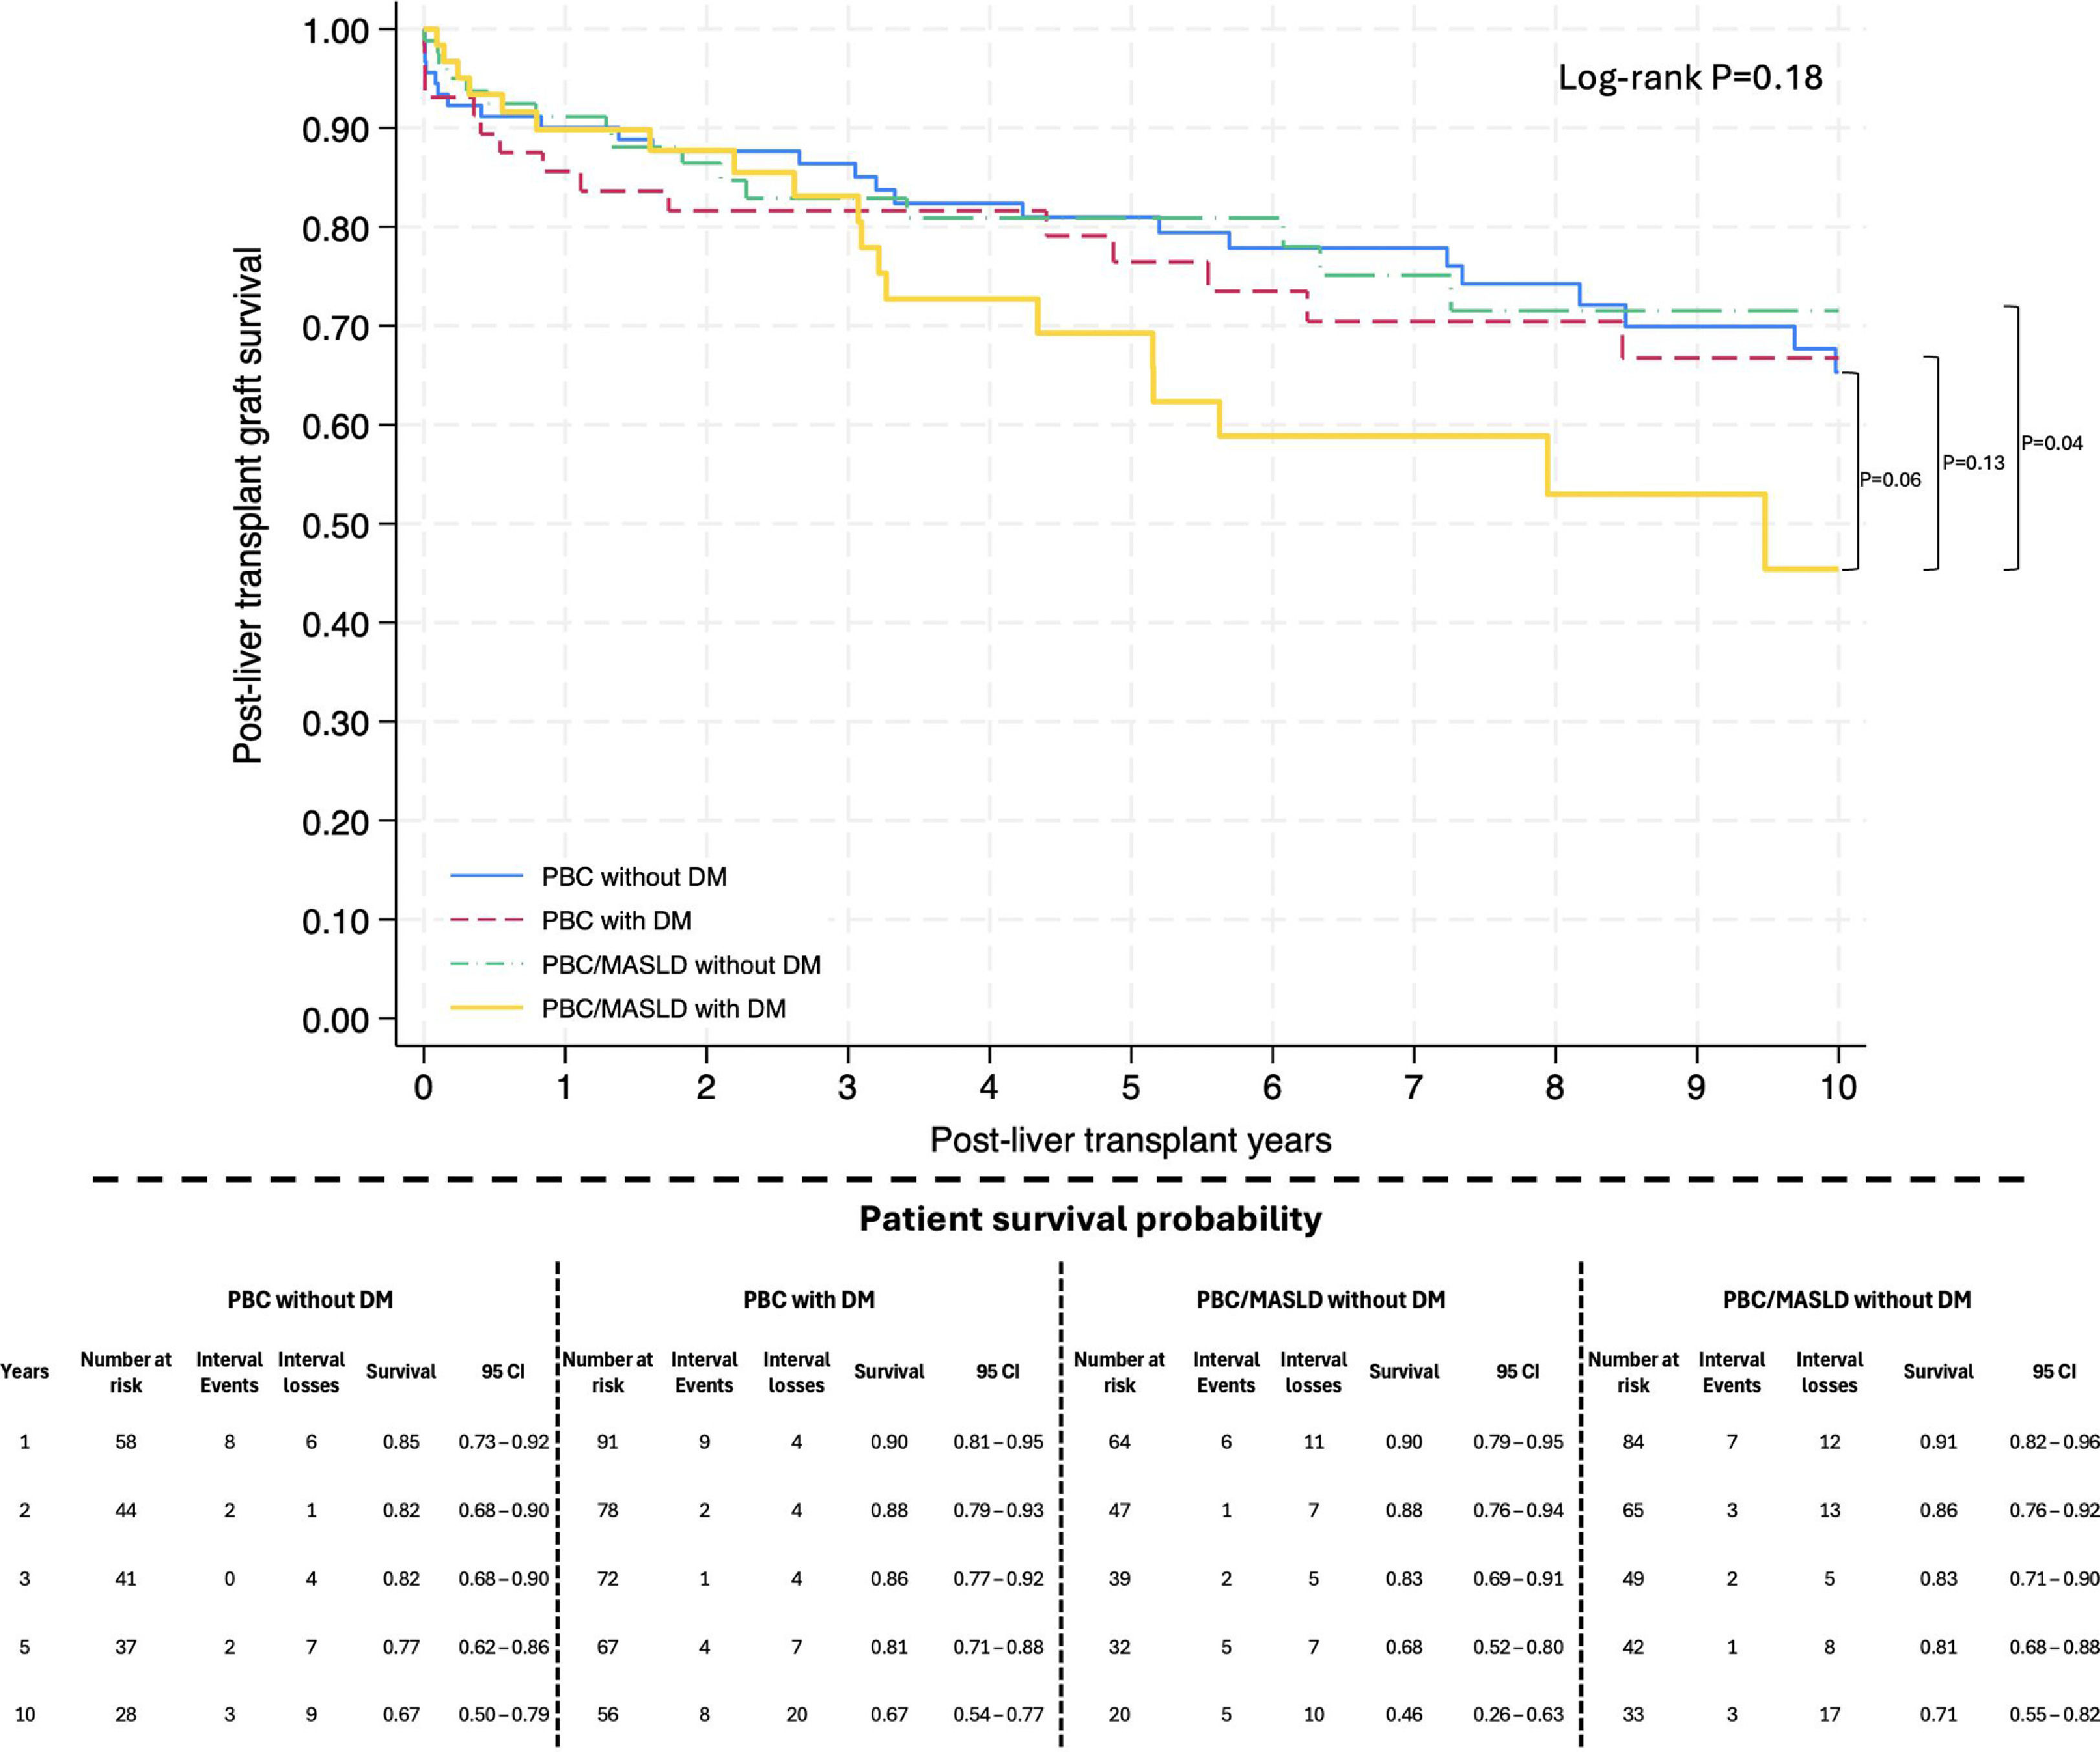
Graft survival stratified by diabetes status (Fig. 6) showed no statistically significant difference between groups (log-rank p = 0.18). Graft survival probability at 1 year was 0.90 for PBC with diabetes (95 CI: 0.81–0.95), 0.85 for PBC without diabetes (95 CI: 0.73–0.92), 0.91 for PBC/MASLD with diabetes (95 CI: 0.82–0.96), and 0.90 for PBC/MASLD without diabetes (95 CI: 0.79–0.95). By 5 years, survival was 0.81 (95 CI: 0.71–0.88), 0.77 (95 CI: 0.62–0.86), 0.81 (95 CI: 0.68–0.88), and 0.68 (95 CI: 0.52–0.80), respectively. At 10 years, long-term graft survival was 0.67 (95 CI: 0.57–0.75) for PBC and 0.60 (95 CI: 0.47–0.71) for PBC/MASLD, with lower survival observed in the PBC/MASLD with diabetes subgroup compared to PBC/MASLD without diabetes (p = 0.04), PBC with diabetes (p = 0.13), and PBC without diabetes (p = 0.06).

Graft survival over the last decade by diabetes status.
Abbreviations: CI: Confidence interval; MASLD: Metabolic dysfunction-associated steatotic liver disease; PBC: Primary biliary cholangitis.
Definitions: Survival probabilities were estimated using the Kaplan-Meier method; Number at risk represents patients remaining under observation at each time point; Interval events indicate the number of deaths occurring within each time interval; Interval losses represent patients censored (lost to follow-up or study end) within each time interval.
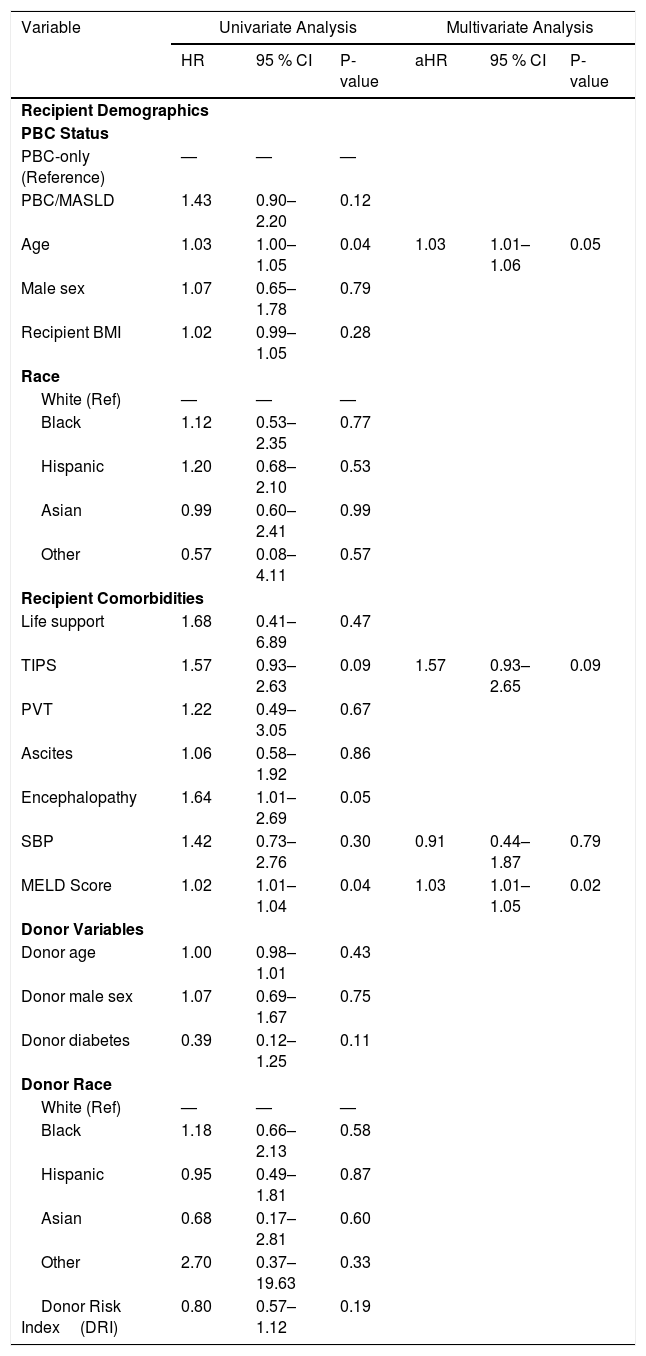
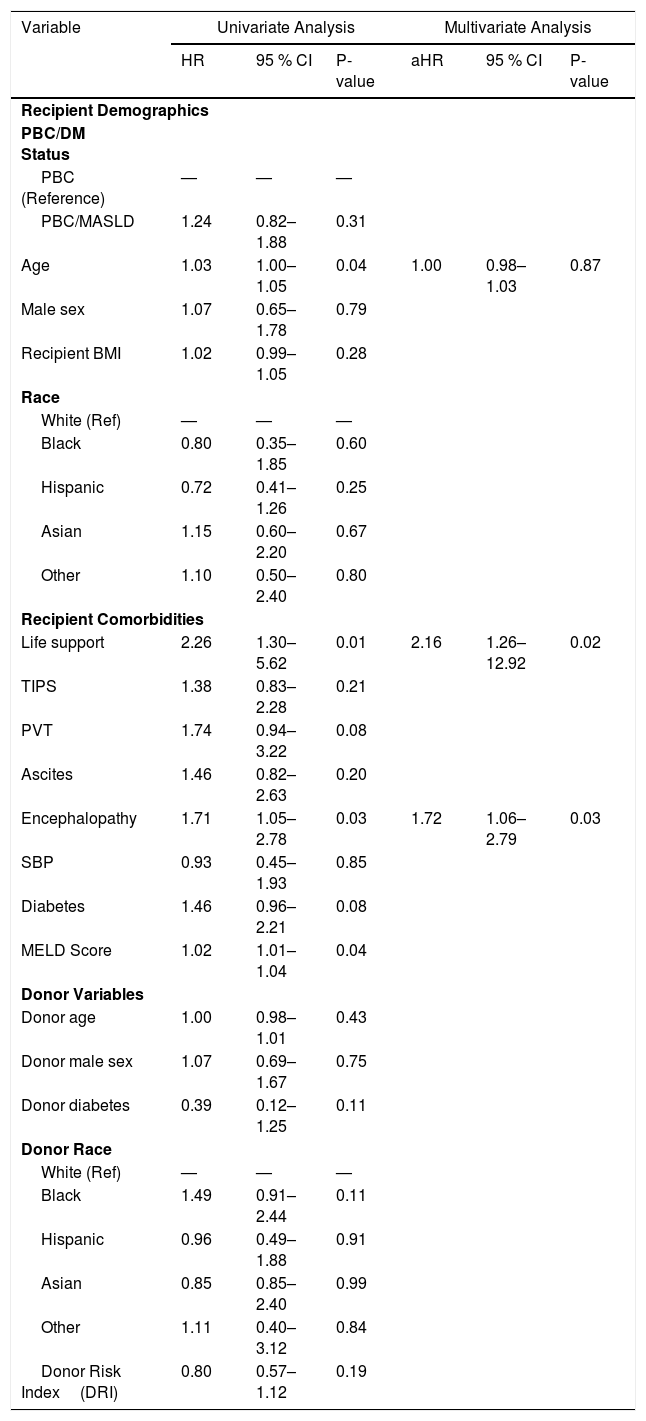
In univariate analysis for predictors of post-LT patient mortality (Table 3), PBC/MASLD was not significantly associated with mortality (HR 1.43; 95 % CI, 0.90–2.20; p = 0.12). In the multivariate model, only age (aHR 1.03; 95 % CI, 1.01–1.06; p = 0.05) and MELD score (aHR 1.03; 95 % CI, 1.01–1.05; p = 0.02) were independently associated with post-LT mortality. Similarly, in stepwise analysis for predictors of graft failure (Table 4), PBC/MASLD status was not significant in univariate analysis (HR 1.24; 95 % CI, 0.82–1.88; p = 0.31). Life support (aHR 2.16; 95 % CI, 1.26–12.92; p = 0.02) and encephalopathy (aHR 1.72; 95 % CI, 1.06–2.79; p = 0.03) were the only independent predictors of graft failure.
Stepwise Cox regression analysis for predictors of post-LT patient mortality.
Abbreviations: aHR, Adjusted Hazard Ratio; BMI, Body Mass Index; CI, Confidence Interval; DM, Diabetes Mellitus; DRI, Donor Risk Index; HR, Hazard Ratio; MASLD, Metabolic-Associated Steatotic Liver Disease; MELD, Model for End-stage Liver Disease; PBC, Primary Biliary Cholangitis; PVT, Portal Vein Thrombosis; SBP, Spontaneous Bacterial Peritonitis; TIPS, Transjugular Intrahepatic Portosystemic Shunt.
Stepwise Cox regression analysis for predictors of graft failure.
Abbreviations: aHR, Adjusted Hazard Ratio; BMI, Body Mass Index; CI, Confidence Interval; DM, Diabetes Mellitus; DRI, Donor Risk Index; HR, Hazard Ratio; MASLD, Metabolic-Associated Steatotic Liver Disease; MELD, Model for End-stage Liver Disease; PBC, Primary Biliary Cholangitis; PVT, Portal Vein Thrombosis; SBP, Spontaneous Bacterial Peritonitis; TIPS, Transjugular Intrahepatic Portosystemic Shunt.
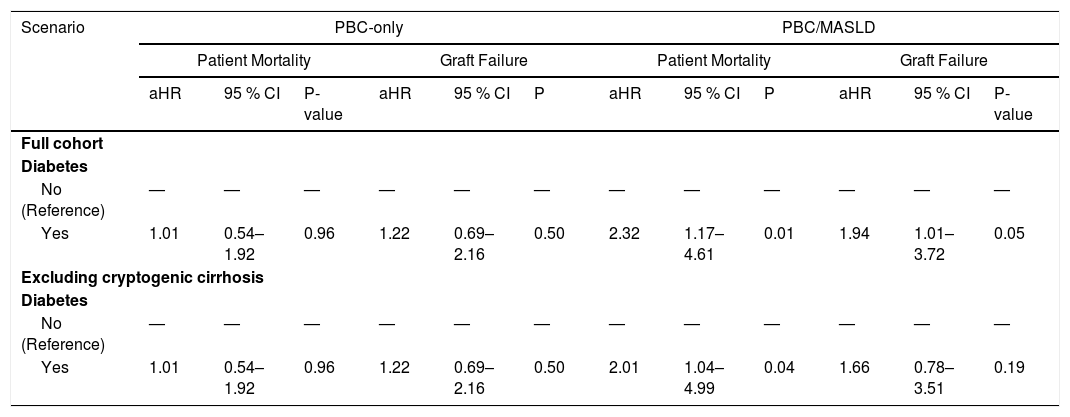
In sensitivity analyses adjusted for variables that entered the multivariable models (Table 5), DM in PBC-only patients was not associated with patient mortality (aHR 1.01; 95 % CI, 0.54–1.92; p = 0.96) or graft failure (aHR 1.22; 95 % CI, 0.69–2.16; p = 0.50), whereas among PBC/MASLD patients, DM was significantly associated with a doubling of patient mortality (aHR 2.32; 95 % CI, 1.17–4.61; p = 0.01). After excluding patients classified as MASLD based on cryptogenic cirrhosis, the association between DM and patient mortality remained significant (aHR 2.01; 95 % CI, 1.04–4.99; p = 0.04).
Sensitivity analysis by PBC status.
Models adjusted for independent variables that were significant in the univariable analysis for each scenario. Abbreviations: aHR, adjusted hazard ratio; CI, confidence interval; MASLD, metabolic dysfunction-associated steatotic liver disease; PBC, primary biliary cholangitis.
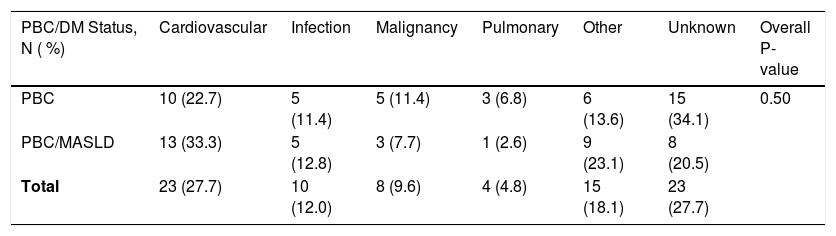
Across the causes of death listed (n = 83), the leading causes were cardiovascular (27.7 %) and unknown (27.7 %), followed by other (18.1 %), infection (12.0 %), malignancy (9.6 %), and pulmonary (4.8 %) (Table 6). In PBC without DM, unknown (31.0 %) and cardiovascular (24.1 %) predominated. In PBC with DM, unknown causes were highest (40.0 %), with cardiovascular disease second (20.0 %). In PBC/MASLD without DM, cardiovascular (38.9 %) were most frequent, whereas PBC/MASLD with DM showed a more even distribution (cardiovascular 28.6 %; infection/malignancy/other each 14.3 %). There was no significant difference across the causes of mortality between the groups (p = 0.50).
Causes of post-LT mortality by PBC status.
Abbreviations: DM, Diabetes Mellitus; MASLD, Metabolic-Associated Steatotic Liver Disease; PBC, Primary Biliary Cholangitis.
We compared pre-LT outcomes (i.e., waitlist dropout and transplant probability up to 40 months) and post-LT outcomes (i.e., patient and graft survival up to 10 years) between PBC patients with and without MASLD. Secondarily, we compared post-LT patient and graft survival between PBC and PBC/MASLD patients with and without diabetes. Several main findings emerged from our study.
First, in the unmatched group, patients with PBC/MASLD had higher rates of adverse events, as noted by the increased need for life support and burden of encephalopathy and ascites, as well as higher MELD scores. This is consistent with Hernández-Pérez et al., who reported higher UK PBC and Globe scores in PBC/MASLD.7 UK-PBC and Globe scores are strong predictors of PBC disease severity and UDCA response.17,18 However, other studies have reported that the presence of fatty liver disease does not change PBC disease activity and severity based on APRI and FIB-4 scores.19,20 It is plausible that concurrent MASLD and diminished clinical response to UDCA may have contributed to the increased liver-related adverse events and higher MELD scores observed in our PBC/MASLD cohort before LT.
Second, though there was no difference between PBC and PBC/MASLD in regards to LT probabilities, patients with PBC alone experienced more waitlist dropout compared to those with PBC/MASLD overlap, a finding that has not previously been reported in the literature. Prior studies have largely focused on comparisons between PBC and the broader NAFLD/MASLD or MASH populations rather than specific overlap syndromes. Notably, Zhou et al. reported higher 24-month waitlist mortality in PBC compared to MASH (23.0 % vs 20.0 %), and Nagai et al. similarly observed higher short- and intermediate-term waitlist mortality for PBC over MASH in adults.21,22 However, neither addressed outcomes in PBC/MASLD overlaps, highlighting the novelty of our data.
One potential contributing factor for the higher waitlist dropout in PBC-only patients is the unmeasured confounding factors in the UNOS database, particularly frailty and cardiometabolic risk factors. Frailty, including sarcopenia and low physiologic reserve, is prevalent in PBC and strongly predicts waitlist dropout.23–28 PBC-specific mechanisms, chronic cholestasis with fat-soluble vitamin deficiency, persistent fatigue and pruritus causing inactivity and sarcopenic obesity masked by BMI, accelerate muscle loss even at modest MELD, which potentially increases dropout on the waitlist.26,28–30 Standardized frailty metrics (e.g., Liver Frailty Index, handgrip, 6-minute walk) are not captured in the UNOS database; thus, observed differences may reflect greater prevalence and severity of unmeasured frailty burden in PBC-only patients compared to PBC/MASLD overlap patients.24–28,30 Similar limitations have been highlighted in other cholestatic cohorts using UNOS, reinforcing the impact of unmeasured patient-level factors on outcomes.29–31
Another possibility for the increased waitlist dropout in the PBC-only group is that the MELD score may not fully capture the unique pathophysiology of cholestatic liver disease. As evidenced by the performance of PBC-specific prognostic scores, MELD may fail to incorporate important markers of disease severity in PBC, potentially underestimating risk in this population.32
Third, our post-LT analysis showed no significant differences in patient and graft survival between groups over a 10-year follow-up. This finding aligns with previous studies showing similar early post-LT survival between MASLD and other liver transplant indications.33
When stratified by diabetes, PBC/MASLD patients with diabetes had the greatest odds of post-LT mortality. This suggests that diabetes is associated with increased risk of mortality and graft failure in PBC/MASLD patients. The finding could be attributed to higher rates of metabolic complications after LT in diabetics. Similarly, in our analysis, PBC/MASLD with diabetes had a 132 % higher post-LT patient mortality risk within 10 years, compared to those without diabetes.
Our data reveal that while PBC/MASLD overlap does not significantly alter post- LT mortality, the addition of diabetes to the PBC/MASLD overlap confers an increase in mortality risk. We hypothesize that this may be related to a synergistic interaction between PBC/MASLD and diabetes. Notably, graft failure itself did not significantly vary between groups, suggesting that diabetes primarily drives patient mortality via systemic complications rather than graft-specific dysfunction. Diabetes is known to exacerbate steatosis, inflammation, and impair graft regeneration, while PBC-related cholestasis impairs bile acid and FXR-mediated glucose/lipid homeostasis.34,35
Our study had several limitations and strengths. The UNOS database is a national database that lacks granularity, particularly regarding cardiovascular risk factors. Additionally, the UNOS database did not have variables of PBC-specific treatments, frailty outcomes, or response to diabetes management. We also acknowledge that the PBC/MASLD cohort may be underrepresented in the UNOS database because overlapping etiologies are not consistently captured in secondary diagnosis codes.14 Another important limitation involves the categorization of patients with cryptogenic cirrhosis and BMI ≥30 kg/m² as MASLD, while consistent with prior UNOS-based studies,14–16 this may introduce potential misclassification bias.
Despite these limitations, a key strength of our study lies in the use of a robust and large sample size, which allowed us to obtain a sizeable cohort of PBC/MASLD overlap patients. We further strengthened the validity of our comparative analyses by using nearest neighbor propensity score matching to closely balance baseline characteristics between groups, thereby reducing confounding and potential selection bias. We also adjusted for multiple confounding factors to achieve reliable multivariate analysis results.
5ConclusionsIn summary, our study reveals that PBC patients experience more waitlist dropout compared to those with PBC/MASLD overlap. Importantly, there was no significant difference in LT rates between these groups. Furthermore, the presence of diabetes in the PBC/MASLD cohort was independently associated with significantly decreased patient survival at 10 years post-LT. These results underscore the importance of optimizing diabetes screening and metabolic management post-LT in PBC/MASLD patients. Given the substantial negative impact of diabetes on long-term post-LT outcomes, targeted interventions for glycemic and cardiometabolic risk control are of high priority in this population. Future research should focus on defining optimal strategies for diabetes management before and after transplantation to improve survival outcomes in PBC/MASLD patients.
FundingThis research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors.
Author contributionsLeandro Sierra: Conceptualization, Data curation, Formal analysis, Investigation, Methodology, Software, Visualization, Writing – original draft, Writing – review & editing; Shahana Prakash: Investigation, Writing – review & editing; Jamak Modaresi Esfeh: Investigation, Writing – review & editing; Omar T. Sims: Methodology, Conceptualization, Project administration, Supervision, Writing – review & editing; Dian J. Chiang: Methodology, Conceptualization, Project administration, Supervision, Writing – review & editing.
None.






